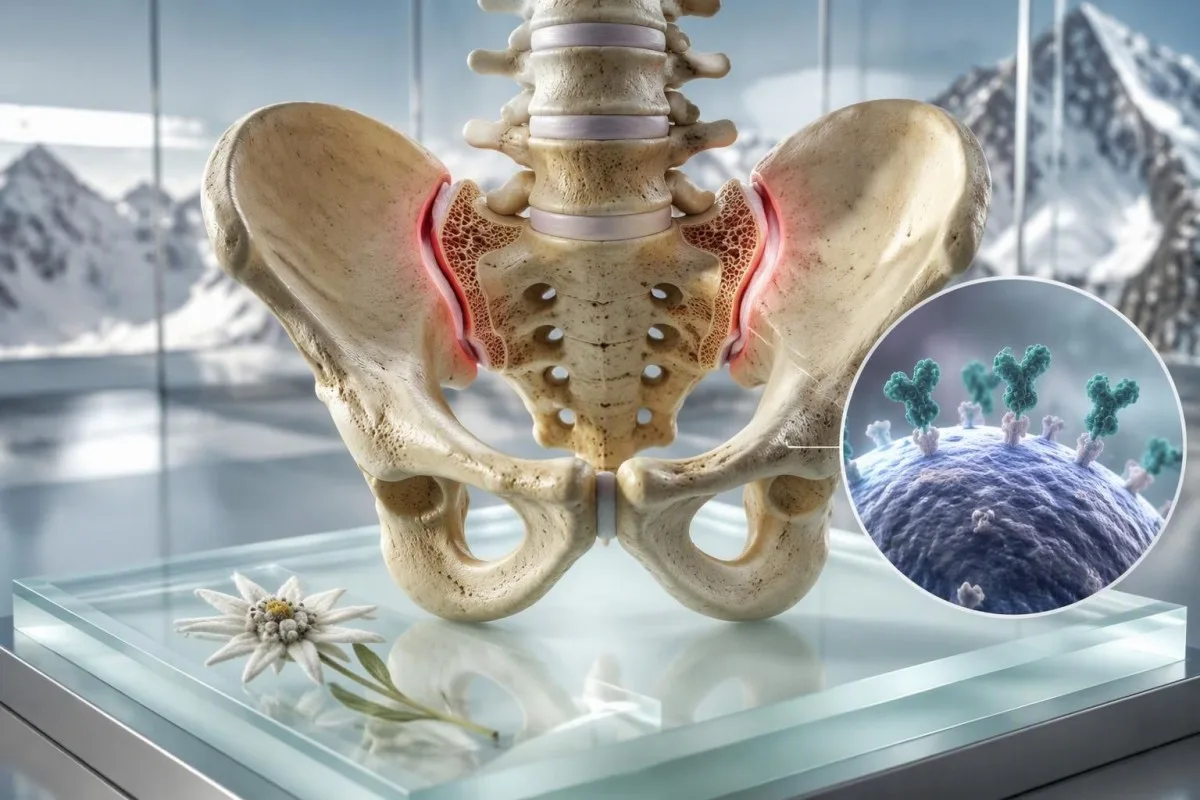
លទ្ធផលវិជ្ជមានចំពោះ HLA-B27 បង្ហាញពីសញ្ញាប្រព័ន្ធភាពស៊ាំដែលទទួលមរតក មិនមែនជាការធ្វើរោគវិនិច្ឆ័យទេ។ វាមានសារសំខាន់បំផុតនៅពេលដែលវារួមជាមួយនឹងការឈឺខ្នងដែលចាប់ផ្តើមមុនអាយុ 45 ឆ្នាំ ការរលាកភ្នែកដែលកើតឡើងភ្លាមៗម្តងហើយម្តងទៀត រោគសើរស្បែក រោគរលាកពោះវៀន ឬប្រវត្តិគ្រួសារជិតស្និទ្ធនៃជំងឺរលាកសន្លាក់ឆ្អឹងខ្នង។.


- HLA-B27 វិជ្ជមាន មានន័យថាអ្នកមានសញ្ញាហ្សែន; អ្នកផ្ទុកជាច្រើនដែលមានសុខភាពល្អមិនដែលកើតជំងឺរលាកឡើយ។.
- ការឈឺខ្នងដោយសារការរលាក ជាធម្មតាចាប់ផ្តើមមុនអាយុ 45 ឆ្នាំ មានរយៈពេលយូរជាង 3 ខែ មានភាពប្រសើរឡើងដោយការធ្វើចលនា ហើយជាញឹកញាប់រំខានដល់ការគេងនៅពាក់កណ្ដាលអធ្រាត្រទីពីរ។.
- ការរលាកផ្នែកខាងមុខស្រួចស្រាវ បណ្តាលឲ្យមានភ្នែកក្រហម ឈឺ និងងាយនឹងពន្លឺ ជាមួយនឹងការមើលឃើញព្រិលៗ ហើយត្រូវការការវាយតម្លៃផ្នែកភ្នែកនៅថ្ងៃតែមួយ។.
- CRP ធម្មតា មិនរាប់បញ្ចូលជំងឺរលាកឆ្អឹងខ្នងផ្នែកកណ្តាល; CRP កើនឡើងក្នុងតែមួយផ្នែកនៃមនុស្សដែលមានជំងឺសកម្មប៉ុណ្ណោះ។.
- ការស្កេន MRI សន្លាក់ sacroiliac អាចបង្ហាញពីការឆ្លើយតបនៃជាលិកាសកម្មមុនពេលកាំរស្មី X ធម្មតាបង្ហាញការផ្លាស់ប្តូររចនាសម្ព័ន្ធ។.
- ប្រវត្តិសុខភាពគ្រួសារ នៃជំងឺរលាកសន្លាក់ឆ្អឹងខ្នង ការរលាកភ្នែក រោគសើរស្បែក ឬជំងឺរលាកពោះវៀន បង្កើនតម្លៃនៃការបញ្ជូនទៅផ្នែករោគសញ្ញាសន្លាក់ដែលមានគោលដៅ។.
- ការធ្វើតេស្ត HLA-B27 គួរ回答临床问题;对于单纯的机械性腰痛,它不是一个有用的筛查测试。.
- 紧急眼部症状 压倒实验室结果:在就医治疗眼痛或视力改变之前,请勿等待 HLA-B27 测试结果。.
លទ្ធផលវិជ្ជមានចំពោះ HLA-B27 ប្រាប់អ្នកនូវអ្វីដែលជាការពិត
HLA-B27 阳性意味着一个人携带特定的 HLA I 类基因变异;这并不意味着他们患有强直性脊柱炎或将来会患上它。. 只有当症状和体检结果指向脊柱关节炎谱系疾病时,该检测才具有临床价值。在我的实践中,最有害的误解是将阳性结果视为一种预测,而不是基于概率的证据的一部分。.
大约 6.1% 的美国成年人携带 HLA-B27,尽管其患病率因祖先和地理位置而异。. 它在某些北欧和原住民人群中更常见,在其他人群中则不常见,因此在不同社区中,其结果的预测价值也不同。阴性结果降低了与 HLA-B27 相关的疾病的可能性,但不能排除中轴型脊柱关节炎。.
HLA-B27 检测的含义是二元的:检测到或未检测到,而不是高或低。. 实验室通常使用来自实验室样本的分子分型,结果不会因睡眠、饮食、疾病发作或药物而波动。这与炎症标志物根本不同,例如 អេសអរ, ,其变化可能在几天到几周内发生。.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគឈាម AI 将重要的 HLA 结果与相关的炎症标志物并列,但仅凭遗传标记无法诊断脊柱关节炎。 Thomas Klein, MD 建议患者提出更简单的问题:该检测是为了回答什么临床问题?我们的 មគ្គុទេសក៍ biomarker 解释了为什么标记的或阳性结果总是需要其实验室方法和临床背景。.
为什么阳性结果可能比实际情况更令人担忧
大多数 HLA-B27 阳性的人从不患强直性脊柱炎。. 该标记物参与抗原呈递,但从携带它到患病的生物学途径仍不完整;肠道微生物、免疫调节和其他基因似乎也起作用。这种不确定性是真实的,临床医生不应将遗传关联转化为预测。.
HLA-B27 និងជំងឺរលាកសន្លាក់ឆ្អឹងខ្នង៖ សមាគមទល់នឹងការធ្វើរោគវិនិច្ឆ័យ
在许多北欧队列中,大约 80% 至 95% 的影像学强直性脊柱炎患者 HLA-B27 呈阳性,但该标记物既不是诊断的必需条件,也不是充分条件。. 医生根据整体模式诊断中轴型脊柱关节炎:症状、体征、影像学、实验室结果和竞争性解释。.
在 45 岁之前开始的慢性背痛患者中,HLA-B27 阳性结果具有最大的诊断价值。. 对于一个 55 岁的患者,他的第一次背痛是在 52 岁举起家具后开始的,同样的结果通常改变很小。这就是为什么在没有临床预期概率的情况下进行的检测会带来更多焦虑而非清晰。.
ASAS 分类框架允许在有慢性背痛(始于 45 岁之前)的 HLA-B27 阳性患者中,当存在至少另外两个脊柱关节炎特征(如葡萄膜炎、银屑病、炎症性肠病、关节炎、附着点炎或家族史)时,符合中轴型脊柱关节炎通路(Rudwaleit 等人,2009 年)。. 分类标准有助于研究的一致性;它们不是家庭诊断清单。.
影像学强直性脊柱炎描述了 X 射线上的既定骶髂关节结构改变,而无影像学中轴型脊柱关节炎可能 X 射线正常。. MRI can identify active bone-marrow tissue response earlier, although athletic loading, pregnancy-related changes, and degenerative disease can also make MRI interpretation tricky. A focused unexplained pain work-up អាចជួយបង្កើតភាពខុសគ្នាដ៏ទូលាយ។.
The risk number patients usually want
First-degree relatives of a person with HLA-B27-associated ankylosing spondylitis have a higher risk than the general population, but family risk is not destiny. Risk estimates differ substantially by sex, ancestry, and whether the affected relative has radiographic disease. I do not recommend testing healthy children or siblings merely to settle worry unless a specialist identifies a specific clinical reason.
ការឈឺខ្នងដោយសារការរលាកខុសពីការឈឺខ្នងធម្មតាដោយរបៀបណា
Inflammatory back pain typically begins gradually before age 45, persists for more than 3 months, improves with exercise, and does not improve reliably with rest. Mechanical pain more often follows a strain, worsens predictably with loading, and settles when the provoking movement stops.
Waking in the second half of the night because of back or buttock pain is a useful clue when it occurs repeatedly, not once after a poor mattress. Alternating buttock pain, morning stiffness lasting longer than 30 minutes, and marked improvement after getting moving add weight to the inflammatory pattern. None is individually diagnostic; together, they are more persuasive.
I often see a 32-year-old runner who says, I loosen up after the first kilometre. That is not proof of inflammation—many musculoskeletal problems warm up—but pain that returns after sitting, wakes them near 4 a.m., and has continued for 9 months deserves more than generic stretching advice. Pain severity is less informative than the pattern over time.
NICE advises rheumatology referral for back pain beginning before 45 and lasting more than 3 months when several spondyloarthritis features coexist; HLA-B27 testing can support referral when exactly three features are present. New bowel or bladder dysfunction, saddle numbness, fever, unexplained weight loss, cancer history, or rapidly progressive weakness requires urgent assessment for causes beyond spondyloarthritis. Review the practical distinction between inflammation and injury in our psoriasis laboratory guide, particularly if skin disease is also present.
A useful two-week symptom record
Record wake time, stiffness duration, exercise response, buttock location, and anti-inflammatory medicine response for 14 days before an appointment. This produces more diagnostic value than a generic pain score from 0 to 10, because rheumatologists are looking for a reproducible inflammatory rhythm.
នៅពេលណាដែលភ្នែកក្រហមដែលទាក់ទងនឹង HLA-B27 ត្រូវការការថែទាំនៅថ្ងៃតែមួយ
A painful red eye with light sensitivity, blurred vision, or a smaller-looking pupil can be acute anterior uveitis and needs same-day assessment by an eye specialist or emergency eye service. HLA-B27-associated uveitis often starts suddenly in one eye and can recur, sometimes in the other eye at a later date.
Acute anterior uveitis is not the same as conjunctivitis. Conjunctivitis commonly causes discharge or gritty discomfort; uveitis more often causes deep aching pain, photophobia, reduced visual clarity, and redness concentrated around the iris. A normal-looking external eye does not reliably exclude it, especially early on.
Roughly half of acute anterior uveitis cases in many European-derived cohorts are HLA-B27 positive, but eye doctors still consider infection, sarcoidosis, Behçet disease, inflammatory bowel disease, trauma, and medication effects. Do not use leftover steroid eye drops without an examination, because steroid drops can worsen undiagnosed corneal infection and raise eye pressure. មគ្គុទេសក៍របស់យើងសម្រាប់ Behçet eye symptoms covers another condition where oral ulcers and eye symptoms change the urgency.
Treatment commonly uses prescription topical corticosteroid drops plus pupil-dilating drops, with a taper directed by ophthalmology. Follow-up matters because pressure elevation and swelling at the back of the eye can occur even when pain improves. A recurrent episode should trigger communication between ophthalmology and rheumatology rather than parallel, disconnected care.
រោគសញ្ញាដែលមិនគួររង់ចាំការណាត់ជួបធម្មតា
Sudden vision loss, a curtain or shower of new floaters, severe headache with nausea, halos around lights, or severe eye pain needs emergency evaluation immediately. These features can signal diagnoses other than uveitis, including acute angle-closure glaucoma or retinal disease, where delay can threaten sight.
រោគសញ្ញាផ្សេងៗទៀតដែលធ្វើឲ្យ HLA-B27 កាន់តែមានន័យ
HLA-B27 becomes more clinically meaningful when back or eye symptoms occur with psoriasis, inflammatory bowel disease, heel enthesitis, swollen joints, or a close relative with related disease. This cluster is called the spondyloarthritis spectrum because different tissues may be involved at different times.
Enthesitis is inflammation where a tendon or ligament attaches to bone, commonly causing focal pain at the Achilles insertion or bottom of the heel. It differs from diffuse foot ache because the tenderness is usually sharply localized and may be worst after rest. Ultrasound can help, but body weight, sports loading, and footwear can produce similar symptoms.
Psoriasis-related nail pitting, separation of the nail plate, or a whole swollen finger or toe can be particularly helpful diagnostic clues. A person does not need widespread psoriasis for this to count; a small scalp patch or a long history of flaky plaques behind the ears may matter. Photographing an intermittent rash before it fades can save a surprising amount of time at review.
Chronic diarrhoea, nocturnal stool urgency, rectal bleeding, or unintended weight loss should prompt bowel evaluation rather than being attributed to stress. Faecal calprotectin is useful for detecting intestinal tissue response but is not specific for Crohn disease or ulcerative colitis; our calprotectin comparison explains its limitations. The connection matters because bowel inflammation can steer both imaging choices and treatment selection.
Symptoms that do not fit neatly
Fatigue is common in active inflammatory disease but is too non-specific to establish a diagnosis. Iron deficiency, sleep disruption, thyroid dysfunction, mood disorders, medications, and prolonged pain can all contribute, so I look for a coherent pattern rather than assigning fatigue to HLA-B27.
ប្រវត្តិគ្រួសារផ្លាស់ប្តូរជំហានបន្ទាប់ដោយរបៀបណា
A first-degree relative with ankylosing spondylitis, recurrent uveitis, psoriasis, inflammatory bowel disease, or reactive arthritis increases suspicion when compatible symptoms are present. Family history supports a referral decision; it does not make testing or imaging mandatory in a person with no symptoms.
Ask relatives about diagnoses and major symptoms, not only whether they carry HLA-B27. People may remember being told they had iritis, a stiff spine, Crohn disease, or psoriasis but have never heard the term spondyloarthritis. The age at symptom onset is especially valuable: back pain that began at 22 tells a different story from osteoarthritis diagnosed at 72.
Kantesti AI គឺជាអ្វីមួយដែល វេទិកាបកស្រាយការធ្វើតេស្តឈាម AI that can organise family-shared laboratory histories with consent, but family-history patterns still require a clinician to verify diagnoses. A useful record includes affected relative, relationship, condition, age at onset, eye episodes, and relevant imaging. Our អ្នកតាមដានប្រវត្តិគ្រួសារ offers a practical template for recording that detail.
Routine HLA-B27 testing in symptom-free relatives usually does not improve outcomes. The result can create false reassurance when negative and unnecessary fear when positive, because no proven preventive treatment is prescribed simply for carrier status. A child with persistent limp, eye symptoms, or swollen joints needs paediatric assessment based on symptoms, whatever the family genotype.
What to bring to a specialist appointment
Bring prior X-ray or MRI reports, eye-clinic letters, medication dates, and a one-page family history. Imaging discs or digital access are often more useful than repeating scans, particularly because sacroiliac-joint MRI requires experienced interpretation.
ហេតុអ្វីបានជាការធ្វើតេស្ដការរលាកធម្មតាមិនរាប់បញ្ចូលរឿងនេះចេញ
Normal CRP and ESR do not rule out axial spondyloarthritis or HLA-B27-associated uveitis. These tests measure systemic inflammatory activity indirectly, and localized disease can be clinically active while both results remain within the laboratory reference interval.
CRP is often reported in mg/L, with many laboratories using less than 5 mg/L as a reference threshold, while ESR reference limits vary with age and sex. A CRP of 2 mg/L can coexist with active sacroiliac inflammation on MRI. Conversely, a CRP of 28 mg/L is non-specific and may reflect infection, obesity, dental inflammation, or another inflammatory condition.
A complete blood count, liver profile, kidney profile, CRP, and ESR are baseline context tests rather than diagnostic proof. Anaemia, raised platelets, low albumin, or iron deficiency can suggest persistent inflammation or bowel involvement, but each has alternative explanations. This is one reason inflammatory conditions should not be inferred from a single marker.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគតេស្តឈាមដោយ AI that can compare CRP, platelets, haemoglobin, and albumin across dates, helping users identify a pattern to discuss with their clinician. It cannot see sacroiliitis on an MRI or assess a painful eye. For antibody results that can be over-interpreted in a similar way, see our explanation of ការធ្វើតេស្ត ANA.
Medication and test interpretation
NSAIDs can reduce CRP and improve symptoms without proving or disproving the diagnosis. Do not stop prescribed anti-inflammatory medication before testing unless the clinician managing your care specifically asks you to; an artificial flare is not a safe diagnostic strategy.
ការស្កេនណាដែលជួយបាន ហើយការស្កេននីមួយៗអាចខកខានអ្វីខ្លះ
MRI of the sacroiliac joints is the preferred scan when axial spondyloarthritis is suspected but X-rays are normal or inconclusive. X-rays show structural change that often develops slowly, whereas MRI can show active bone-marrow tissue response and other early changes.
A normal lumbar-spine MRI does not replace a dedicated sacroiliac-joint MRI protocol. The relevant joints are lower and more lateral than the area commonly imaged for a slipped disc. I have seen patients reassured by an ordinary lumbar scan that was simply not designed to answer the inflammatory question.
MRI findings require clinical correlation because bone-marrow oedema can occur after intense exercise, childbirth, mechanical stress, and degenerative change. The radiology report should describe location, depth, distribution, erosions, fat change, and structural features; a vague statement of oedema alone is not enough. A rheumatologist may ask for image review when the report and symptom pattern disagree.
Pelvic X-rays remain useful for documenting chronic sacroiliac structural changes, but a normal X-ray does not close the case in a younger person. CT shows structure very clearly but uses ionising radiation and is not generally the first choice for early inflammatory disease. If persistent inflammation affects mobility, bone-health assessment may also be relevant; read our bone loss laboratory guide.
Why the scan report can sound uncertain
Radiologists appropriately use terms such as compatible with or non-specific when the imaging pattern is not definitive. That wording is not evasive; it reflects a real overlap between inflammatory and mechanical findings, and it prevents imaging from being treated as a diagnosis in isolation.
នៅពេលណាដែលត្រូវស្នើបញ្ជូនទៅផ្នែករោគសញ្ញាសន្លាក់
Ask for rheumatology evaluation when chronic back pain began before age 45 and is accompanied by inflammatory features, HLA-B27 positivity, recurrent uveitis, psoriasis, bowel symptoms, heel enthesitis, or a relevant family history. A positive test plus one convincing clinical feature is more useful than a positive test discovered during broad screening.
A referral is reasonable even when CRP is normal and X-rays are unremarkable if the clinical pattern is compelling. The 2019 ACR/SAA/SPARTAN guideline recommends treatment decisions based on disease activity, function, comorbidities, and patient preferences rather than a genetic result alone (Ward et al., 2019). This approach prevents both delayed diagnosis and reflexive overtreatment.
At the appointment, expect questions about age at onset, morning stiffness, night waking, response to NSAIDs, eye attacks, skin lesions, bowel symptoms, infection preceding arthritis, and family history. A rapid and clear response to a full-dose NSAID may support suspicion, but it is not a diagnostic test. NSAIDs also improve ordinary back pain.
Thomas Klein, MD, recommends making a dated timeline rather than trying to remember every symptom in the consulting room. Include medication dose and duration, especially if using ibuprofen, naproxen, or diclofenac, because kidney function, blood pressure, ulcer risk, and anticoagulant use alter the safety calculation. Our medication trend guide explains why repeat kidney and liver results may matter during longer courses.
When an orthopaedic or physiotherapy assessment may be better first
Back pain starting after age 45 following a specific injury, with clear load-related triggers and no inflammatory features, more often benefits initially from musculoskeletal care. That is a probability statement, not a dismissal; persistent uncertainty or new eye, skin, bowel, or joint symptoms warrants reassessment.
ការព្យាបាលមើលទៅដូចម្តេចប្រសិនបើជំងឺរលាកឆ្អឹងខ្នងផ្នែកកណ្តាលត្រូវបានបញ្ជាក់
Confirmed axial spondyloarthritis is treated with education, regular movement, targeted physiotherapy, and anti-inflammatory medicines; biologic or targeted synthetic medicines are reserved for persistent active disease. HLA-B27 status does not determine treatment by itself.
Exercise is treatment, not a test of willpower. A programme that maintains spinal extension, hip mobility, chest expansion, and aerobic capacity is generally more sustainable than sporadic intense workouts. Most patients find short daily mobility work of 10 to 20 minutes easier to keep than a single ambitious weekend session.
NSAIDs are usually considered first-line when safe, but dose and duration must be individualised. Naproxen 500 mg twice daily is a common adult anti-inflammatory dose, yet it may be unsuitable with chronic kidney disease, prior ulcer bleeding, heart failure, uncontrolled hypertension, anticoagulants, or pregnancy. Gastroprotection may be appropriate for some people, but it does not remove kidney or cardiovascular risk.
Biologic medicines such as TNF inhibitors and IL-17 inhibitors require screening and specialist monitoring because infection risk and comorbidities affect selection. Recurrent uveitis, psoriasis, and inflammatory bowel disease influence which agent best fits the whole person. This is one reason a diagnosis based only on an HLA-B27 result can lead to the wrong treatment conversation.
Avoid the supplement trap
No supplement has been shown to prevent HLA-B27-associated spondyloarthritis in healthy carriers. Correcting a documented vitamin D, iron, or B12 deficiency can improve general health, but it is not a substitute for assessment of inflammatory back pain or a painful red eye.
របៀបតាមដានលទ្ធផលដោយមិនត្រូវជាប់នឹងវា
The most useful record combines symptoms, function, medications, eye episodes, imaging, and laboratory trends rather than repeatedly retesting HLA-B27. Once accurately typed, HLA-B27 status does not need serial monitoring because your inherited marker does not change.
Track functional measures that mean something to you, such as minutes until morning stiffness eases, uninterrupted sleep, walking tolerance, or ability to turn while driving. These details show treatment response more honestly than a single good or bad day. Note whether an eye flare preceded a back-pain change by days or weeks.
Kantesti can organise imported laboratory reports across time and flag changes for discussion, but it should not be used to self-start or stop prescription treatment. Our clinical framework is described in the មគ្គុទេសក៍បច្ចេកវិទ្យា AI: results are interpreted as context for professional care, not as a replacement for examination or imaging.
Repeating CRP during a flare can be useful when a clinician is also following symptoms and treatment response, but routine weekly testing is rarely helpful. In my experience, a symptom record every day and blood work at clinically meaningful intervals yields less noise and fewer false alarms. Laboratory trends only become informative when collection dates, infections, exercise, and medicines are documented.
A note about privacy and family data
Genetic information can affect relatives as well as the person tested, so share reports deliberately. Keep the original laboratory report, remove unrelated identifiers when appropriate, and obtain consent before adding another adult's results to a shared family record.
ការយល់ច្រឡំទូទៅអំពីការមានលទ្ធផលវិជ្ជមានចំពោះ HLA-B27
HLA-B27 positivity does not mean your immune system is attacking your spine, that you are contagious, or that you need treatment while symptom-free. It is a common inherited allele whose significance depends on the clinical setting.
Myth: a positive HLA-B27 test explains every ache. Fact: mechanical back pain remains common among HLA-B27 carriers. Strain, disc disease, hip disorders, hypermobility, fibromyalgia, kidney stones, and pelvic conditions still deserve a normal differential diagnosis. The marker should sharpen clinical reasoning, not end it.
Myth: a negative HLA-B27 test rules out ankylosing spondylitis. Fact: HLA-B27-negative axial spondyloarthritis occurs, especially across populations with lower background carrier frequency. When imaging and clinical features are persuasive, a negative result should not be used to deny specialist review.
Myth: genes are the same as destiny. Fact: genetics influence risk, but no preventive biologic therapy is indicated for a well HLA-B27 carrier. This is conceptually similar to the limits of MTHFR result interpretation: genetic information is medically useful only when the result changes an evidence-based decision.
Can stress cause a flare?
Stress can worsen pain, sleep, fatigue, and coping, but it does not explain away objective uveitis or inflammatory arthritis. Treating sleep and stress is worthwhile alongside medical care; it should never delay eye assessment or replace a work-up for persistent inflammatory symptoms.
សំណួរដែលធ្វើឲ្យការណាត់ជួបលើកដំបូងមានប្រយោជន៍ជាង
The best first appointment questions focus on probability, alternative diagnoses, and the next decision—not on whether HLA-B27 is good or bad. A clinician should be able to explain what finding would increase or decrease their suspicion and what test would change management.
Ask whether your symptoms meet an inflammatory-back-pain pattern and which features argue against it. Then ask whether dedicated sacroiliac MRI is appropriate, whether an ophthalmology referral is needed, and whether psoriasis or bowel symptoms warrant coordinated review. This approach respects uncertainty without letting it become inaction.
Ask how long to try a treatment, what outcome defines success, and which adverse effects need a call. For NSAIDs, the specific safety discussion should include kidney function, blood pressure, gastrointestinal history, pregnancy plans, and interacting drugs. For biologics, ask about screening, vaccines, infection precautions, and how uveitis or bowel disease changes the choice.
Kantesti's clinical content is medically reviewed with structured quality controls; readers can examine our វិធីសាស្ត្រធ្វើឲ្យមានសុពលភាពផ្នែកវេជ្ជសាស្ត្ររបស់យើង និងសមត្ថភាព/គុណវុឌ្ឍិរបស់ ក្រុមប្រឹក្សាវេជ្ជសាស្រ្ត. A laboratory interpretation is most valuable when it helps you ask a better question of the clinician who can examine you.
ស្គ្រីបការជួបប្រជុំដ៏ខ្លី
Say: My back pain started at age 29, has lasted 14 months, wakes me at 4 a.m., improves after 30 minutes of movement, and I had a painful light-sensitive eye last spring. That one sentence gives a rheumatologist more usable information than stating only that an HLA-B27 result was positive.
រោគសញ្ញាបន្ទាន់និងផែនការជំហានបន្ទាប់ដែលមានសុវត្ថិភាព
Seek same-day urgent eye care for eye pain, light sensitivity, red eye with blurred vision, or any sudden visual change; seek emergency care for new weakness, bladder or bowel dysfunction, saddle numbness, high fever, or severe unremitting back pain. Do not wait for repeat blood work, an MRI booking, or a rheumatology appointment when these red flags occur.
For non-urgent symptoms, book a primary-care review within weeks if back pain has lasted more than 3 months and began before age 45, especially with HLA-B27 positivity or family history. Bring your HLA report, symptom timeline, medication list, eye-clinic letters, and prior images. A targeted referral is generally faster and more useful than repeating broad autoimmune panels.
As of September 27, 2026, the central clinical principle remains unchanged: HLA-B27 is a risk marker, not a diagnosis. Thomas Klein, MD, has found that patients do best when they treat a positive result as a prompt to notice patterns—then obtain the right eye, primary-care, or rheumatology assessment rather than catastrophising or ignoring symptoms.
កាន់តេស្ទី គឺជា សេវាកម្មបកស្រាយការធ្វើតេស្តរបស់ AI lab built to explain laboratory reports in plain language while preserving the boundary between information and diagnosis. Learn how our organisation approaches this work on our ទំព័រ About Us and find further patient education in the ប្លុក Kantesti.
ផ្នែកបោះពុម្ពផ្សាយស្រាវជ្រាវ
Kantesti LTD. (2026)។. មគ្គុទេសក៍ប្រភេទឈាម B អវិជ្ជមាន ការពិនិត្យឈាម LDH និងការរាប់កោសិកាឈាមក្រហមវ័យក្មេង (Reticulocyte Count). Figshare។. https://doi.org/10.6084/m9.figshare.31333819. Related author records may be located through ច្រកស្រាវជ្រាវ និង Academia.edu.
Kantesti LTD. (2026)។. រាគបន្ទាប់ពីតមអាហារ ចំណុចខ្មៅនៅក្នុងលាមក និងការណែនាំអំពីប្រព័ន្ធរំលាយអាហារឆ្នាំ ២០២៦. Figshare។. https://doi.org/10.6084/m9.figshare.31438111. Related author records may be located through ច្រកស្រាវជ្រាវ និង Academia.edu.
These publications are not evidence for diagnosing HLA-B27-associated disease and should not replace the rheumatology and ophthalmology references cited above. They are listed as Kantesti research records for transparency.
សំណួរដែលសួរញឹកញាប់
តើការមានលទ្ធផល HLA-B27 វិជ្ជមានមានន័យថាខ្ញុំមានជំងឺ ankylosing spondylitis ដែរឬទេ?
ទេ ។ លទ្ធផល HLA-B27 វិជ្ជមាន មានន័យថា អ្នកមានហ្សែនដែលទាក់ទងនឹងជំងឺរលាកសន្លាក់ឆ្អឹងខ្នង និងជំងឺពាក់ព័ន្ធនានា ប៉ុន្តែអ្នកដែលមានហ្សែននេះជាច្រើននៅតែមានសុខភាពល្អពេញមួយជីវិត ។ នៅក្នុងក្រុមអ្នកជំងឺរលាកសន្លាក់ឆ្អឹងខ្នងដែលមានលក្ខណៈវិទ្យុសកម្ម ប្រហែល 80% ទៅ 95% មានលទ្ធផល HLA-B27 វិជ្ជមាន ប៉ុន្តែផ្ទុយទៅវិញ ភាគច្រើននៃអ្នកដែលមានលទ្ធផលវិជ្ជមាន មិនមានជំងឺនេះទេ ។ ការធ្វើរោគវិនិច្ឆ័យតម្រូវឲ្យមានរោគសញ្ញាដែលត្រូវគ្នា ការពិនិត្យ ការថតរូបភាព និងការបដិសេធមូលហេតុផ្សេងៗ ។.
រោគសញ្ញាឈឺខ្នងណាដែលបង្ហាញពីការរលាកដែលទាក់ទងនឹង HLA-B27?
ការឈឺខ្នង គឺ gợi ý ជាង axial spondyloarthritis នៅពេលដែលវាចាប់ផ្តើមមុនអាយុ 45 ឆ្នាំ វិវឌ្ឍន៍ជាបន្តបន្ទាប់ មានរយៈពេលជាង 3 ខែ ប្រសើរឡើងដោយចលនា និងបង្កឱ្យមានការរឹងនៅពេលព្រឹករយៈពេលជាង 30 នាទី។ ការភ្ញាក់ដដែលៗនៅពាក់កណ្ដាលយប់ និងការឈឺគូទឆ្លាស់គ្នា បន្ថែមនូវព័ត៌មានមានប្រយោជន៍។ លទ្ធផល HLA-B27 វិជ្ជមាន បង្កើនតម្លៃនៃលំនាំនេះ ប៉ុន្តែគ្រូពេទ្យនៅតែត្រូវវាយតម្លៃមូលហេតុនៃការកន្ត្រាក់ និងសញ្ញាគ្រោះថ្នាក់។.
តើ HLA-B27 អាចបណ្តាលឱ្យកើតជំងឺរលាកភ្នែកបានទេ?
HLA-B27 មិនបានបណ្តាលឱ្យមានបញ្ហាភ្នែកទាំងអស់ដោយផ្ទាល់ទេ ប៉ុន្តែវាមានទំនាក់ទំនងយ៉ាងខ្លាំងជាមួយនឹងជំងឺរលាកភ្នែកផ្នែកខាងមុខស្រួចស្រាវ។ រោគសញ្ញានៃជំងឺរលាកភ្នែកប្រភេទនេះជាធម្មតាបណ្តាលឱ្យភ្នែកមួយមានការឡើងក្រហមភ្លាមៗ ឈឺចាប់យ៉ាងជ្រៅ ភ្នែកប្រតិកម្មនឹងពន្លឺ និងការមើលឃើញព្រឹលៗ។ វាទាមទារឱ្យមានការពិនិត្យដោយគ្រូពេទ្យឯកទេសភ្នែកក្នុងថ្ងៃតែមួយ។ ប្រហែលពាក់កណ្តាលនៃករណីជំងឺរលាកភ្នែកផ្នែកខាងមុខស្រួចស្រាវមានលទ្ធផល HLA-B27 វិជ្ជមាននៅក្នុងក្រុមជនជាតិអឺរ៉ុបជាច្រើន ទោះបីជាការរីករាលដាលប្រែប្រួលទៅតាមប្រជាជន និងមូលហេតុផ្សេងៗទៀតត្រូវតែពិចារណាក៏ដោយ។.
តើខ្ញុំគួរទៅជួបគ្រូពេទ្យជំនាញខាងជំងឺឈឺសន្លាក់ឆ្អឹងទេ ប្រសិនបើខ្ញុំមានលទ្ធផល HLA-B27 វិជ្ជមាន ប៉ុន្តែមិនមានរោគសញ្ញាអ្វីឡើយ?
មនុស្សភាគច្រើនដែលមានលទ្ធផល HLA-B27 វិជ្ជមាន និងគ្មានរោគសញ្ញា មិនតម្រូវឱ្យមានការតាមដានជាប្រចាំពីគ្រូពេទ្យជំនាញខាងជំងឺរលាកសន្លាក់ ឬការព្យាបាលបង្ការទេ។ ការពិនិត្យឡើងវិញគឺសមហេតុផល ប្រសិនបើការឈឺខ្នងរ៉ាំរ៉ៃចាប់ផ្តើមមុនអាយុ 45 ឆ្នាំ មានជំងឺរលាកភ្នែកកើតឡើងវិញ ជំងឺស្បែករបកក្រហម រោគសញ្ញាពោះវៀនដែលនៅតែមាន ការឈឺកែងជើងពីជំងឺរលាកសរសៃពួរ សន្លាក់ហើម ឬប្រវត្តគ្រួសារដ៏រឹងមាំកើតឡើង។ ការធ្វើតេស្ត HLA-B27 ម្តងទៀតគឺគ្មានប្រយោជន៍ទេ ពីព្រោះស្ថានភាព HLA ដែលបានពីកំណើតមិនផ្លាស់ប្តូរតាមពេលវេលាទេ។.
តើ CRP និង ESR អាចមានលក្ខណៈធម្មតាជាមួយជំងឺ ankylosing spondylitis បានទេ?
បាទ/ចាស។ CRP ត្រូវបានរាយការណ៍ជាទូទៅថាធម្មតាក្រោម 5 mg/L នៅក្នុងមន្ទីរពិសោធន៍ជាច្រើន ប៉ុន្តែ CRP និង ESR ធម្មតា មិនរាប់បញ្ចូលជំងឺរលាកសន្លាក់ឆ្អឹងខ្នង axSpA ឬជំងឺរលាកភ្នែក uveitis សកម្មឡើយ។ សូចនាករទាំងនេះឆ្លុះបញ្ចាំងពីសកម្មភាពរលាកទូទៅ និងអាចនៅតែធម្មតា នៅពេលដែលការរលាកមានទីតាំងនៅសន្លាក់ sacrum និង ilium ឬភ្នែក។ MRI, លំនាំរោគសញ្ញា, ការពិនិត្យរាងកាយ, និងការវាយតម្លៃពីអ្នកជំនាញ អាចផ្តល់ព័ត៌មានច្រើនជាងលទ្ធផលរលាកធម្មតាដាច់ដោយឡែកមួយ។.
តើការធ្វើតេស្ត HLA-B27 ធ្វើឡើងពីឈាមឬទេ?
ការធ្វើតេស្ត HLA-B27 ត្រូវបានអនុវត្តជាទូទៅពីគំរូមន្ទីរពិសោធន៍ដោយប្រើវិធីសាស្ត្រម៉ូលេគុល ឬវិធីសាស្ត្រផ្អែកលើលំហូរកោសិកា (flow-cytometry) ហើយមន្ទីរពិសោធន៍ជាច្រើនប្រើគំរូឈាម។ ការធ្វើតេស្តនេះមានលក្ខណៈគុណភាព (qualitative) ត្រូវបានរាយការណ៍ថាបានរកឃើញឬមិនបានរកឃើញ ផ្ទុយទៅនឹងកម្រិតដែលមានជួរធម្មតា។ របបអាហារ ការហាត់ប្រាណ និងសកម្មភាពជំងឺមិនផ្លាស់ប្តូរលទ្ធផលទេ ពីព្រោះ HLA-B27 ត្រូវបានទទួលមរតក ផ្ទុយទៅនឹងសញ្ញារលាក។.
ទទួលការវិភាគឈាមដោយ AI ដែលមានថាមពលថ្ងៃនេះ
ចូលរួមជាមួយអ្នកប្រើប្រាស់ជាង 2 លាននាក់នៅទូទាំងពិភពលោក ដែលទុកចិត្ត Kantesti សម្រាប់ការវិភាគលទ្ធផលតេស្តមន្ទីរពិសោធន៍ភ្លាមៗ និងត្រឹមត្រូវ។ ផ្ទុកឡើងលទ្ធផលពិនិត្យឈាមរបស់អ្នក ហើយទទួលការបកស្រាយយ៉ាងទូលំទូលាយនៃសញ្ញាសម្គាល់ (biomarkers) 15,000+ ក្នុងរយៈពេលប៉ុន្មានវិនាទី។.
📚 ឯកសារស្រាវជ្រាវដែលបានយោង
Klein, T., Mitchell, S., & Weber, H. (2026). មគ្គុទេសក៍ប្រភេទឈាម B អវិជ្ជមាន ការពិនិត្យឈាម LDH និងចំនួន Reticulocyte.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
Klein, T., Mitchell, S., & Weber, H. (2026). រាគបន្ទាប់ពីតមអាហារ ចំណុចខ្មៅនៅក្នុងលាមក និងការណែនាំអំពីប្រព័ន្ធរំលាយអាហារឆ្នាំ ២០២៦.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
📖 ឯកសារយោងវេជ្ជសាស្ត្រខាងក្រៅ
Rudwaleit M et al. (2009)។. The development of Assessment of SpondyloArthritis international Society classification criteria for axial spondyloarthritis. Part II: validation and final selection..។ Annals of the Rheumatic Diseases។.
Ward MM et al. (2019). 2019 Update of the American College of Rheumatology/Spondylitis Association of America/SPARTAN Recommendations for the Treatment of Ankylosing Spondylitis and Nonradiographic Axial Spondyloarthritis..។.
Ramiro S et al. (2023). ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update..។ Annals of the Rheumatic Diseases។.
⚕️ ការបដិសេធផ្នែកវេជ្ជសាស្ត្រ
អត្ថបទនេះមានគោលបំណងសម្រាប់ការអប់រំប៉ុណ្ណោះ ហើយមិនមែនជាការផ្តល់ដំបូន្មានផ្នែកវេជ្ជសាស្ត្រទេ។ សូមពិគ្រោះជាមួយអ្នកផ្តល់សេវាសុខភាពដែលមានសមត្ថភាពជានិច្ច សម្រាប់ការសម្រេចចិត្តអំពីការធ្វើរោគវិនិច្ឆ័យ និងការព្យាបាល។.
សញ្ញាទុកចិត្ត E-E-A-T
បទពិសោធន៍
ការពិនិត្យព្យាបាលដោយវេជ្ជបណ្ឌិតលើដំណើរការការបកស្រាយលទ្ធផលមន្ទីរពិសោធន៍។.
ជំនាញ
ផ្តោតលើវិទ្យាសាស្ត្រមន្ទីរពិសោធន៍ថា សញ្ញាសម្គាល់ (biomarkers) មានឥរិយាបថយ៉ាងដូចម្តេចក្នុងបរិបទព្យាបាល។.
ភាពមានសិទ្ធិអំណាច
សរសេរដោយវេជ្ជបណ្ឌិត Thomas Klein ជាមួយការពិនិត្យឡើងវិញដោយវេជ្ជបណ្ឌិត Sarah Mitchell និងសាស្ត្រាចារ្យវេជ្ជបណ្ឌិត Hans Weber។.
ភាពគួរឱ្យទុកចិត្ត
ការបកស្រាយដោយផ្អែកលើភស្តុតាង ជាមួយផ្លូវបន្តតាមដានច្បាស់លាស់ ដើម្បីកាត់បន្ថយការភ័យខ្លាច។.