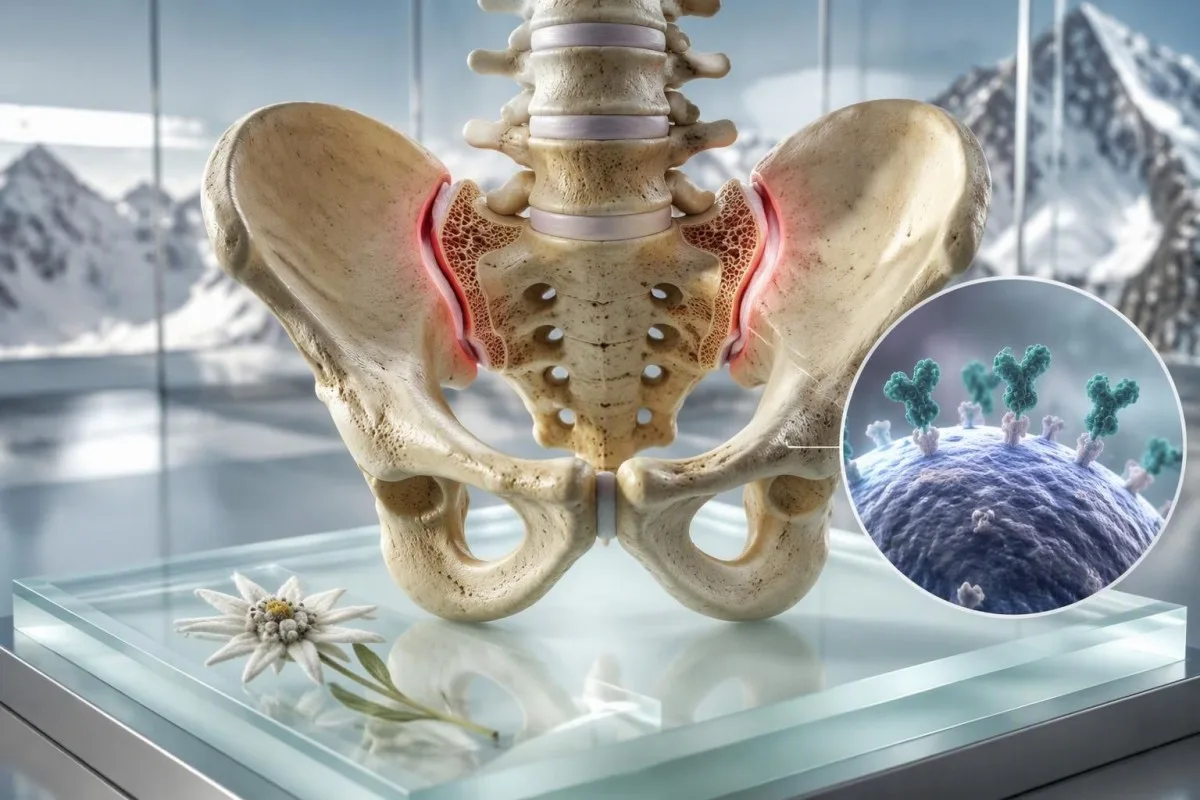
یو مثبت د HLA-B27 پایله د میراثي معافیتي سیسټم نښه په ګوته کوي، نه تشخیص. دا هغه وخت ډیره مهمه ده کله چې دا د 45 کلنۍ څخه دمخه د ملا درد، د سترګو ناڅاپي سوزش، psoriasis، د کولمو سوزش، یا د spondyloarthritis نږدې کورنۍ تاریخ سره مل وي.


- HLA-B27 مثبت پدې معنی چې تاسو د جنیټیک نښه لرئ؛ ډیری روغ رمټ لرونکي هیڅکله التهابي ناروغي نه لري.
- التهابي ملا درد معمولا د 45 کلنۍ څخه دمخه پیل کیږي، له 3 میاشتو څخه ډیر دوام کوي، د حرکت سره ښه کیږي، او ډیری وختونه د شپې په دویمه نیمایي کې خوب ګډوډوي.
- Acute anterior uveitis سور، دردناک، روښانه حساس سترګې د لید د تیاره کیدو سره لامل کیږي او ورته ورځني ophthalmology ارزونې ته اړتیا لري.
- نورمال CRP axial spondyloarthritis نه خارجوي؛ CRP په فعال ناروغۍ لرونکو خلکو کې یوازې په یوه تناسب کې لوړیږي.
- د مقعد د مفصلونو MRI کولی شي فعال نسج غبرګون وښیې مخکې له دې چې ساده ایکس رې له جوړښتي بدلون وښیې.
- د کورنۍ روغتیایی تاریخ د ankylosing spondylitis، uveitis، psoriasis، یا التهابي د کولمو ناروغۍ ارزښت د هدف لرونکي روماتولوژي حوالې ارزښت زیاتوي.
- د HLA-B27 ازموینه باید یوه کلینیکي پوښتنه ځواب کړي؛ دا د عادي میخانیکي ملا درد لپاره ګټوره ازموینه نه ده.
- د سترګو عاجل نښې د لابراتواري پایلو څخه ډیر مهم دي: د سترګو درد یا لید بدلون لپاره د مرستې په لټه کې کیدو دمخه د HLA-B27 ازموینې ته انتظار مه کوئ.
د HLA-B27 مثبت پایله څه شی ښیې
د HLA-B27 مثبت معنی دا ده چې یو شخص یو ځانګړی HLA کلاس I جنیټیک ډول لري؛ دا پدې معنی ندي چې دوی انکیلوزینګ سپونډیلیتس لري یا به یې رامینځته کړي. دا ازموینه یوازې هغه وخت کلینیکي ګټور کیږي کله چې نښې او د معاینې موندنې د سپونډیلوارتریت سپیکٹرم حالت ته اشاره کوي. زما په تمرین کې، ترټولو زیان رسونکی غلط فهم دی چې مثبته پایله د وړاندوینې په توګه درملنه کیږي نه د احتمال پر بنسټ یوې برخې شواهدو په توګه.
HLA-B27 د متحده ایالاتو په شاوخوا 6.1% لویانو کې شتون لري، که څه هم خپریدل د اصل او جغرافیې له مخې په شدید ډول توپیر لري. دا په ځینو شمالي اروپايي او اصلي نفوسو کې ډیر عام دی او په نورو کې نادر دی، نو یوه پایله په مختلفو ټولنو کې مختلف وړاندوینې ارزښت لري. منفي پایله د HLA-B27-اړوند ناروغۍ احتمال کموي مګر د محوري سپونډیلوارتریت رد نشي کولی.
د HLA-B27 ازموینې معنی دوه ګونې ده: کشف شوی یا نه کشف شوی، لوړ یا ټیټ نه. لابراتوارونه معمولا د لابراتواري نمونې څخه د مالیکولر ټایپینګ کاروي، او پایله د خوب، رژیم، فلیر، یا درملو سره نه بدلیږي. دا په بنسټیزه توګه د التهابي مارکرونو څخه توپیر لري لکه د ESR کچه, ، کوم چې په ورځو تر اونیو پورې بدلیږي.
کانټیسټي یو دی د AI د وینې معاینې شنونکی چې د اړونده التهابي مارکرونو تر څنګ یوه وارد شوي HLA پایله ځای په ځای کوي، مګر دا یوازې له جنیټیک مارکر څخه سپونډیلوارتریت تشخیص نشي کولی. توماس کلین، MD، ناروغانو ته مشوره ورکوي چې ساده پوښتنه وپوښتي: د کوم کلینیکي ستونزې لپاره ازموینه ترتیب شوې وه؟ زموږ د بایومارکر لارښود تشریح کوي چې ولې نښه شوي یا مثبتې پایلې تل د هغې لابراتواري میتود او کلینیکي شرایطو ته اړتیا لري.
ولې یوه مثبت پایله له هغه څه څخه ډیره الارم کیدی شي چې ده
ډیری HLA-B27-مثبت خلک هیڅکله انکیلوزینګ سپونډیلیتس رامینځته نه کوي. دا نښه د انټيجن وړاندې کولو کې برخه اخلي، مګر د جنیټیک لیږد څخه تر ناروغۍ پورې بیولوژیکي لاره نامکمل پاتې ده؛ د کولمو میکروبونه، د معافیت تنظیم، او نور جینونه برخه اخلي. دا ناڅرګندتیا ریښتیا ده، او کلینیکان باید د جنیټیک تړاو په وړاندوینې بدل نه کړي.
د HLA-B27 او ankylosing spondylitis ترمنځ اړیکه او تشخیص
د شعاع لرونکي انکیلوزینګ سپونډیلیتس لرونکي خلکو څخه شاوخوا 80% تر 95% په ډیری شمالي اروپايي کوهورتونو کې HLA-B27 مثبت دي، مګر دا نښه د تشخیص لپاره نه اړین او نه کافي ده. ډاکټران د ټولې نمونې څخه د محوري سپونډیلوارتریت تشخیص کوي: نښې، فزیکي موندنې، امیجنگ، لابراتواري پایلې، او سیالي توضیحات.
د HLA-B27 مثبتې پایلې ترټولو لوی تشخیصی ارزښت په هغه چا کې لري چې د 45 کلونو څخه دمخه پیل شوي مزمن ملا درد لري. په 55 کلنۍ کې چې د لومړي ملا درد یې په 52 کلنۍ کې فرنیچر پورته کولو وروسته پیل شو، ورته پایله اکثرا ډیر لږ بدلیږي. له همدې امله یوه ازموینه چې پرته له کلینیکي مخکینۍ احتمال څخه ترتیب شوې وي، له وضاحت څخه ډیر اضطراب رامینځته کولی شي.
د ASAS طبقه بندي چوکاټ اجازه ورکوي چې د HLA-B27-مثبت کس چې د 45 کلونو څخه دمخه پیل شوي مزمن ملا درد لري د محوري سپونډیلوارتریت په لاره کې پوره شي کله چې لږترلږه دوه نور سپونډیلوارتریت ځانګړتیاوې شتون ولري، لکه uveitis، psoriasis، د التهابي بغل ناروغي، arthritis، enthesitis، یا د کورنۍ تاریخ (Rudwaleit et al., 2009). د طبقه بندي معیارونه د څیړنې ثبات کې مرسته کوي؛ دوی د کور تشخیصی لیست نه دي.
د شعاع لرونکي انکیلوزینګ سپونډیلیتس د X-ray په واسطه د سیکرولیاک مشترک تاسیس شوي جوړښتي بدلون تشریح کوي، پداسې حال کې چې غیر شعاع لرونکي محوري سپونډیلوارتریت ممکن نورمال X-rays ولري. MRI can identify active bone-marrow tissue response earlier, although athletic loading, pregnancy-related changes, and degenerative disease can also make MRI interpretation tricky. A focused unexplained pain work-up کولی شي پراخه توپیر تشریح کولو کې مرسته وکړي.
The risk number patients usually want
First-degree relatives of a person with HLA-B27-associated ankylosing spondylitis have a higher risk than the general population, but family risk is not destiny. Risk estimates differ substantially by sex, ancestry, and whether the affected relative has radiographic disease. I do not recommend testing healthy children or siblings merely to settle worry unless a specialist identifies a specific clinical reason.
د التهابي ملا درد د عادي ملا له درد څخه څنګه توپیر لري
Inflammatory back pain typically begins gradually before age 45, persists for more than 3 months, improves with exercise, and does not improve reliably with rest. Mechanical pain more often follows a strain, worsens predictably with loading, and settles when the provoking movement stops.
Waking in the second half of the night because of back or buttock pain is a useful clue when it occurs repeatedly, not once after a poor mattress. Alternating buttock pain, morning stiffness lasting longer than 30 minutes, and marked improvement after getting moving add weight to the inflammatory pattern. None is individually diagnostic; together, they are more persuasive.
I often see a 32-year-old runner who says, I loosen up after the first kilometre. That is not proof of inflammation—many musculoskeletal problems warm up—but pain that returns after sitting, wakes them near 4 a.m., and has continued for 9 months deserves more than generic stretching advice. Pain severity is less informative than the pattern over time.
NICE advises rheumatology referral for back pain beginning before 45 and lasting more than 3 months when several spondyloarthritis features coexist; HLA-B27 testing can support referral when exactly three features are present. New bowel or bladder dysfunction, saddle numbness, fever, unexplained weight loss, cancer history, or rapidly progressive weakness requires urgent assessment for causes beyond spondyloarthritis. Review the practical distinction between inflammation and injury in our psoriasis laboratory guide, particularly if skin disease is also present.
A useful two-week symptom record
Record wake time, stiffness duration, exercise response, buttock location, and anti-inflammatory medicine response for 14 days before an appointment. This produces more diagnostic value than a generic pain score from 0 to 10, because rheumatologists are looking for a reproducible inflammatory rhythm.
کله چې د HLA-B27 سره تړلی سور سترګې ورته ورځني پاملرنې ته اړتیا لري
A painful red eye with light sensitivity, blurred vision, or a smaller-looking pupil can be acute anterior uveitis and needs same-day assessment by an eye specialist or emergency eye service. HLA-B27-associated uveitis often starts suddenly in one eye and can recur, sometimes in the other eye at a later date.
Acute anterior uveitis is not the same as conjunctivitis. Conjunctivitis commonly causes discharge or gritty discomfort; uveitis more often causes deep aching pain, photophobia, reduced visual clarity, and redness concentrated around the iris. A normal-looking external eye does not reliably exclude it, especially early on.
Roughly half of acute anterior uveitis cases in many European-derived cohorts are HLA-B27 positive, but eye doctors still consider infection, sarcoidosis, Behçet disease, inflammatory bowel disease, trauma, and medication effects. Do not use leftover steroid eye drops without an examination, because steroid drops can worsen undiagnosed corneal infection and raise eye pressure. زموږ لارښود د Behçet eye symptoms covers another condition where oral ulcers and eye symptoms change the urgency.
Treatment commonly uses prescription topical corticosteroid drops plus pupil-dilating drops, with a taper directed by ophthalmology. Follow-up matters because pressure elevation and swelling at the back of the eye can occur even when pain improves. A recurrent episode should trigger communication between ophthalmology and rheumatology rather than parallel, disconnected care.
هغه نښې چې باید د منظم ملاقات لپاره انتظار ونه کړي
Sudden vision loss, a curtain or shower of new floaters, severe headache with nausea, halos around lights, or severe eye pain needs emergency evaluation immediately. These features can signal diagnoses other than uveitis, including acute angle-closure glaucoma or retinal disease, where delay can threaten sight.
نورې نښې چې د HLA-B27 ارزښت زیاتوي
HLA-B27 becomes more clinically meaningful when back or eye symptoms occur with psoriasis, inflammatory bowel disease, heel enthesitis, swollen joints, or a close relative with related disease. This cluster is called the spondyloarthritis spectrum because different tissues may be involved at different times.
Enthesitis is inflammation where a tendon or ligament attaches to bone, commonly causing focal pain at the Achilles insertion or bottom of the heel. It differs from diffuse foot ache because the tenderness is usually sharply localized and may be worst after rest. Ultrasound can help, but body weight, sports loading, and footwear can produce similar symptoms.
Psoriasis-related nail pitting, separation of the nail plate, or a whole swollen finger or toe can be particularly helpful diagnostic clues. A person does not need widespread psoriasis for this to count; a small scalp patch or a long history of flaky plaques behind the ears may matter. Photographing an intermittent rash before it fades can save a surprising amount of time at review.
Chronic diarrhoea, nocturnal stool urgency, rectal bleeding, or unintended weight loss should prompt bowel evaluation rather than being attributed to stress. Faecal calprotectin is useful for detecting intestinal tissue response but is not specific for Crohn disease or ulcerative colitis; our calprotectin comparison explains its limitations. The connection matters because bowel inflammation can steer both imaging choices and treatment selection.
Symptoms that do not fit neatly
Fatigue is common in active inflammatory disease but is too non-specific to establish a diagnosis. Iron deficiency, sleep disruption, thyroid dysfunction, mood disorders, medications, and prolonged pain can all contribute, so I look for a coherent pattern rather than assigning fatigue to HLA-B27.
د کورنۍ تاریخ څنګه راتلونکی ګام بدلوي
A first-degree relative with ankylosing spondylitis, recurrent uveitis, psoriasis, inflammatory bowel disease, or reactive arthritis increases suspicion when compatible symptoms are present. Family history supports a referral decision; it does not make testing or imaging mandatory in a person with no symptoms.
Ask relatives about diagnoses and major symptoms, not only whether they carry HLA-B27. People may remember being told they had iritis, a stiff spine, Crohn disease, or psoriasis but have never heard the term spondyloarthritis. The age at symptom onset is especially valuable: back pain that began at 22 tells a different story from osteoarthritis diagnosed at 72.
Kantesti AI یو AI د وینې ازموینې تشریح پلیټفارم that can organise family-shared laboratory histories with consent, but family-history patterns still require a clinician to verify diagnoses. A useful record includes affected relative, relationship, condition, age at onset, eye episodes, and relevant imaging. Our د کورنۍ د تاریخ ثبتوونکی offers a practical template for recording that detail.
Routine HLA-B27 testing in symptom-free relatives usually does not improve outcomes. The result can create false reassurance when negative and unnecessary fear when positive, because no proven preventive treatment is prescribed simply for carrier status. A child with persistent limp, eye symptoms, or swollen joints needs paediatric assessment based on symptoms, whatever the family genotype.
What to bring to a specialist appointment
Bring prior X-ray or MRI reports, eye-clinic letters, medication dates, and a one-page family history. Imaging discs or digital access are often more useful than repeating scans, particularly because sacroiliac-joint MRI requires experienced interpretation.
ولې د التهاب عادي ازموینې دا نه ردوي
Normal CRP and ESR do not rule out axial spondyloarthritis or HLA-B27-associated uveitis. These tests measure systemic inflammatory activity indirectly, and localized disease can be clinically active while both results remain within the laboratory reference interval.
CRP is often reported in mg/L, with many laboratories using less than 5 mg/L as a reference threshold, while ESR reference limits vary with age and sex. A CRP of 2 mg/L can coexist with active sacroiliac inflammation on MRI. Conversely, a CRP of 28 mg/L is non-specific and may reflect infection, obesity, dental inflammation, or another inflammatory condition.
A complete blood count, liver profile, kidney profile, CRP, and ESR are baseline context tests rather than diagnostic proof. Anaemia, raised platelets, low albumin, or iron deficiency can suggest persistent inflammation or bowel involvement, but each has alternative explanations. This is one reason inflammatory conditions should not be inferred from a single marker.
کانټیسټي یو دی د AI پر بنسټ د وینې ازموینې تحلیل وسیله that can compare CRP, platelets, haemoglobin, and albumin across dates, helping users identify a pattern to discuss with their clinician. It cannot see sacroiliitis on an MRI or assess a painful eye. For antibody results that can be over-interpreted in a similar way, see our explanation of د ANA ازموینه.
Medication and test interpretation
NSAIDs can reduce CRP and improve symptoms without proving or disproving the diagnosis. Do not stop prescribed anti-inflammatory medication before testing unless the clinician managing your care specifically asks you to; an artificial flare is not a safe diagnostic strategy.
کوم سکینونه مرسته کوي، او هر سکین څه له لاسه ورکولی شي
MRI of the sacroiliac joints is the preferred scan when axial spondyloarthritis is suspected but X-rays are normal or inconclusive. X-rays show structural change that often develops slowly, whereas MRI can show active bone-marrow tissue response and other early changes.
A normal lumbar-spine MRI does not replace a dedicated sacroiliac-joint MRI protocol. The relevant joints are lower and more lateral than the area commonly imaged for a slipped disc. I have seen patients reassured by an ordinary lumbar scan that was simply not designed to answer the inflammatory question.
MRI findings require clinical correlation because bone-marrow oedema can occur after intense exercise, childbirth, mechanical stress, and degenerative change. The radiology report should describe location, depth, distribution, erosions, fat change, and structural features; a vague statement of oedema alone is not enough. A rheumatologist may ask for image review when the report and symptom pattern disagree.
Pelvic X-rays remain useful for documenting chronic sacroiliac structural changes, but a normal X-ray does not close the case in a younger person. CT shows structure very clearly but uses ionising radiation and is not generally the first choice for early inflammatory disease. If persistent inflammation affects mobility, bone-health assessment may also be relevant; read our bone loss laboratory guide.
Why the scan report can sound uncertain
Radiologists appropriately use terms such as compatible with or non-specific when the imaging pattern is not definitive. That wording is not evasive; it reflects a real overlap between inflammatory and mechanical findings, and it prevents imaging from being treated as a diagnosis in isolation.
کله باید د روماتولوژي حوالې غوښتنه وکړئ
Ask for rheumatology evaluation when chronic back pain began before age 45 and is accompanied by inflammatory features, HLA-B27 positivity, recurrent uveitis, psoriasis, bowel symptoms, heel enthesitis, or a relevant family history. A positive test plus one convincing clinical feature is more useful than a positive test discovered during broad screening.
A referral is reasonable even when CRP is normal and X-rays are unremarkable if the clinical pattern is compelling. The 2019 ACR/SAA/SPARTAN guideline recommends treatment decisions based on disease activity, function, comorbidities, and patient preferences rather than a genetic result alone (Ward et al., 2019). This approach prevents both delayed diagnosis and reflexive overtreatment.
At the appointment, expect questions about age at onset, morning stiffness, night waking, response to NSAIDs, eye attacks, skin lesions, bowel symptoms, infection preceding arthritis, and family history. A rapid and clear response to a full-dose NSAID may support suspicion, but it is not a diagnostic test. NSAIDs also improve ordinary back pain.
Thomas Klein, MD, recommends making a dated timeline rather than trying to remember every symptom in the consulting room. Include medication dose and duration, especially if using ibuprofen, naproxen, or diclofenac, because kidney function, blood pressure, ulcer risk, and anticoagulant use alter the safety calculation. Our medication trend guide explains why repeat kidney and liver results may matter during longer courses.
When an orthopaedic or physiotherapy assessment may be better first
Back pain starting after age 45 following a specific injury, with clear load-related triggers and no inflammatory features, more often benefits initially from musculoskeletal care. That is a probability statement, not a dismissal; persistent uncertainty or new eye, skin, bowel, or joint symptoms warrants reassessment.
که چیرې axial spondyloarthritis تایید شي نو درملنه څنګه ښکاري
Confirmed axial spondyloarthritis is treated with education, regular movement, targeted physiotherapy, and anti-inflammatory medicines; biologic or targeted synthetic medicines are reserved for persistent active disease. HLA-B27 status does not determine treatment by itself.
Exercise is treatment, not a test of willpower. A programme that maintains spinal extension, hip mobility, chest expansion, and aerobic capacity is generally more sustainable than sporadic intense workouts. Most patients find short daily mobility work of 10 to 20 minutes easier to keep than a single ambitious weekend session.
NSAIDs are usually considered first-line when safe, but dose and duration must be individualised. Naproxen 500 mg twice daily is a common adult anti-inflammatory dose, yet it may be unsuitable with chronic kidney disease, prior ulcer bleeding, heart failure, uncontrolled hypertension, anticoagulants, or pregnancy. Gastroprotection may be appropriate for some people, but it does not remove kidney or cardiovascular risk.
Biologic medicines such as TNF inhibitors and IL-17 inhibitors require screening and specialist monitoring because infection risk and comorbidities affect selection. Recurrent uveitis, psoriasis, and inflammatory bowel disease influence which agent best fits the whole person. This is one reason a diagnosis based only on an HLA-B27 result can lead to the wrong treatment conversation.
Avoid the supplement trap
No supplement has been shown to prevent HLA-B27-associated spondyloarthritis in healthy carriers. Correcting a documented vitamin D, iron, or B12 deficiency can improve general health, but it is not a substitute for assessment of inflammatory back pain or a painful red eye.
پایلې څنګه تعقیب کړئ پرته لدې چې ورسره قید شئ
The most useful record combines symptoms, function, medications, eye episodes, imaging, and laboratory trends rather than repeatedly retesting HLA-B27. Once accurately typed, HLA-B27 status does not need serial monitoring because your inherited marker does not change.
Track functional measures that mean something to you, such as minutes until morning stiffness eases, uninterrupted sleep, walking tolerance, or ability to turn while driving. These details show treatment response more honestly than a single good or bad day. Note whether an eye flare preceded a back-pain change by days or weeks.
Kantesti can organise imported laboratory reports across time and flag changes for discussion, but it should not be used to self-start or stop prescription treatment. Our clinical framework is described in the د AI ټکنالوژۍ لارښود: results are interpreted as context for professional care, not as a replacement for examination or imaging.
Repeating CRP during a flare can be useful when a clinician is also following symptoms and treatment response, but routine weekly testing is rarely helpful. In my experience, a symptom record every day and blood work at clinically meaningful intervals yields less noise and fewer false alarms. Laboratory trends only become informative when collection dates, infections, exercise, and medicines are documented.
A note about privacy and family data
Genetic information can affect relatives as well as the person tested, so share reports deliberately. Keep the original laboratory report, remove unrelated identifiers when appropriate, and obtain consent before adding another adult's results to a shared family record.
د HLA-B27 مثبت کیدو په اړه عام غلط فهمونه
HLA-B27 positivity does not mean your immune system is attacking your spine, that you are contagious, or that you need treatment while symptom-free. It is a common inherited allele whose significance depends on the clinical setting.
Myth: a positive HLA-B27 test explains every ache. Fact: mechanical back pain remains common among HLA-B27 carriers. Strain, disc disease, hip disorders, hypermobility, fibromyalgia, kidney stones, and pelvic conditions still deserve a normal differential diagnosis. The marker should sharpen clinical reasoning, not end it.
Myth: a negative HLA-B27 test rules out ankylosing spondylitis. Fact: HLA-B27-negative axial spondyloarthritis occurs, especially across populations with lower background carrier frequency. When imaging and clinical features are persuasive, a negative result should not be used to deny specialist review.
Myth: genes are the same as destiny. Fact: genetics influence risk, but no preventive biologic therapy is indicated for a well HLA-B27 carrier. This is conceptually similar to the limits of MTHFR result interpretation: genetic information is medically useful only when the result changes an evidence-based decision.
Can stress cause a flare?
Stress can worsen pain, sleep, fatigue, and coping, but it does not explain away objective uveitis or inflammatory arthritis. Treating sleep and stress is worthwhile alongside medical care; it should never delay eye assessment or replace a work-up for persistent inflammatory symptoms.
هغه پوښتنې چې لومړنۍ غونډه ډیر ګټوره کوي
The best first appointment questions focus on probability, alternative diagnoses, and the next decision—not on whether HLA-B27 is good or bad. A clinician should be able to explain what finding would increase or decrease their suspicion and what test would change management.
Ask whether your symptoms meet an inflammatory-back-pain pattern and which features argue against it. Then ask whether dedicated sacroiliac MRI is appropriate, whether an ophthalmology referral is needed, and whether psoriasis or bowel symptoms warrant coordinated review. This approach respects uncertainty without letting it become inaction.
Ask how long to try a treatment, what outcome defines success, and which adverse effects need a call. For NSAIDs, the specific safety discussion should include kidney function, blood pressure, gastrointestinal history, pregnancy plans, and interacting drugs. For biologics, ask about screening, vaccines, infection precautions, and how uveitis or bowel disease changes the choice.
Kantesti's clinical content is medically reviewed with structured quality controls; readers can examine our د طبي تایید (validation) طریقه او د زموږ د طبي مشورتي بورډ. A laboratory interpretation is most valuable when it helps you ask a better question of the clinician who can examine you.
یوه لنډه غونډې سکریپټ
Say: My back pain started at age 29, has lasted 14 months, wakes me at 4 a.m., improves after 30 minutes of movement, and I had a painful light-sensitive eye last spring. That one sentence gives a rheumatologist more usable information than stating only that an HLA-B27 result was positive.
عاجلې نښې او خوندي راتلونکی ګام
Seek same-day urgent eye care for eye pain, light sensitivity, red eye with blurred vision, or any sudden visual change; seek emergency care for new weakness, bladder or bowel dysfunction, saddle numbness, high fever, or severe unremitting back pain. Do not wait for repeat blood work, an MRI booking, or a rheumatology appointment when these red flags occur.
For non-urgent symptoms, book a primary-care review within weeks if back pain has lasted more than 3 months and began before age 45, especially with HLA-B27 positivity or family history. Bring your HLA report, symptom timeline, medication list, eye-clinic letters, and prior images. A targeted referral is generally faster and more useful than repeating broad autoimmune panels.
As of September 27, 2026, the central clinical principle remains unchanged: HLA-B27 is a risk marker, not a diagnosis. Thomas Klein, MD, has found that patients do best when they treat a positive result as a prompt to notice patterns—then obtain the right eye, primary-care, or rheumatology assessment rather than catastrophising or ignoring symptoms.
کانټیسټي یو دی د AI لاب ټېسټ د تفسیر خدمت built to explain laboratory reports in plain language while preserving the boundary between information and diagnosis. Learn how our organisation approaches this work on our د About Us پاڼه and find further patient education in the د کانټیسټي بلاګ.
د څېړنې خپرونې برخه
Kantesti LTD. (2026). د B منفي د وینې ډول، د LDH د وینې ازموینې او د Reticulocyte Count لارښود. Figshare. https://doi.org/10.6084/m9.figshare.31333819. Related author records may be located through د څېړنې دروازه او اکاډیمیا.ایډو.
Kantesti LTD. (2026). د روژې وروسته اسهال، په غایطه موادو کې تور داغونه او د معدې ناروغي لارښود ۲۰۲۶. Figshare. https://doi.org/10.6084/m9.figshare.31438111. Related author records may be located through د څېړنې دروازه او اکاډیمیا.ایډو.
These publications are not evidence for diagnosing HLA-B27-associated disease and should not replace the rheumatology and ophthalmology references cited above. They are listed as Kantesti research records for transparency.
پوښتل شوې پوښتنې
ایا د HLA-B27 مثبت کیدل پدې معنی دي چې زه س liés spondylitis لرم؟
نه. د HLA-B27 مثبت پایله پدې معنی ده چې تاسو یو جینیټیک مارکر لرئ چې د انکیلوزینګ سپونډیلیتس او اړوندو شرایطو سره تړاو لري، مګر ډیری لیږدونکي د ژوند په اوږدو کې روغ پاتې کیږي. د راډیوګرافیک انکیلوزینګ سپونډیلیتس سره په ډلو کې، شاوخوا 80% تر 95% پورې HLA-B27 مثبت دي، مګر برعکس ریښتیا ندي: ډیری مثبت خلک دا حالت نلري. تشخیص لپاره مناسب علایم، معاینه، امیجنگ، او د نورو لاملونو استثناء ته اړتیا ده.
د ملا درد کوم علایم د HLA-B27-اړه لرونکي سوزش ښيي؟
کله چې د ملا درد له ۴۵ کلنۍ څخه مخکې پیل شي، په تدریجي ډول پیل شي، له ۳ میاشتو څخه ډیر دوام وکړي، د حرکت سره ښه شي، او د سهار له سستوالي سره چې له ۳۰ دقیقو څخه ډیر دوام کوي، نو دا د محوري سپونډیلوآرتریت په اړه ډیر شک لري. د شپې په دویمه نیمایي کې په مکرر ډول ویښیدل او د دواړو لورو د نخاعي درد شتون اضافي ګټور نښې دي. د HLA-B27 مثبت پایله د دې نمونې ارزښت زیاتوي، مګر یو کلینیک پوه لاهم اړتیا لري چې میخانیکي لاملونه او سور بیرغونه ارزوي.
ایا HLA-B27 کولی شي د Uveitis لامل شي؟
HLA-B27 په مستقیم ډول د سترګو هرې ستونزې لامل نه کیږي، مګر دا د حادې قدامي Uveitis سره په کلکه تړاو لري. دا ډول Uveitis معمولا ناڅاپي یوې سترګې سوروالی، ژور درد، د رڼا حساسیت، او د لید تیاره کیدو لامل کیږي؛ دا د سترګو متخصص لخوا د ورځې په ورته وخت کې ارزونې ته اړتیا لري. په ډیری اروپایی نفوس کې د حادې قدامي Uveitis شاوخوا نیمایي قضیې HLA-B27 مثبتې دي، که څه هم د نفوس له مخې توپیر لري او بدیل لاملونه باید په پام کې ونیول شي.
که زما HLA-B27 مثبت وي خو هیڅ نښې نلرم، ایا زه باید د روماتولوژیست سره مشوره وکړم؟
د ډېری ناروغانو برعکس چې علایم نه لري او د HLA-B27 مثبت دي، منظم روماتولوژي تعقیب او مخنیوي درملنې ته اړتیا نلري. که د 45 کلونو څخه مخکې د ملا درد پیل شي، تکراري Uveitis، psoriasis، د کولمو دوامداره علایم، د enthesitis له امله د پښو درد، پړسوب بندونه، یا د کورنۍ قوي تاریخ رامینځته شي، بیاکتنه منطقي ده. د HLA-B27 ازموینې تکرار ګټور ندي ځکه چې میراثي HLA حالت په وخت سره نه بدلیږي.
ایا د انکیلوزینګ سپونډیلیتس سره CRP او ESR نورمال کیدی شي؟
هو. CRP معمولاً د ډیرو لابراتوارونو لخوا د 5 mg/L څخه ټیټ په توګه عادي راپور کیږي، مګر یو عادي CRP او ESR د محوري سپوندیلوارتریت یا فعال Uveitis خارج نه کوي. دا مارکرونه د سیسټمیک انفلاسیون فعالیت منعکس کوي او کولی شي عادي پاتې شي کله چې انفلاسیون په مقعد-iliac مفصلونو یا سترګو پورې محدود وي. MRI، د نښو نمونې، فزیکي معاینه، او د متخصص ارزونه ممکن د یو واحد عادي انفلاسیون پایلې څخه ډیر معلوماتي وي.
ایا د HLA-B27 ازموینه له وینې څخه اخیستل کیږي؟
د HLA-B27 ټایپ کول معمولا د مالیکولر یا فلو-سایټومیټري پر بنسټ میتودونو په کارولو سره د لابراتوار نمونې څخه ترسره کیږي، او ډیری لابراتوارونه د وینې نمونه کاروي. ازموینه کیفی ده، د غلظت په پرتله د موندل شوي یا نه موندل شوي په توګه راپور کیږي، د نورمال حد سره. رژیم، تمرین، او د ناروغۍ فعالیت پایله نه بدله کوي، ځکه چې HLA-B27 په میراثي ډول ترلاسه کیږي نه د التهاب نښه.
همدا نن د AI په مرسته د وینې ازموینې تحلیل ترلاسه کړئ
له 2M+ څخه زیات کاروونکي په ټوله نړۍ کې زموږ په Kantesti باور لري چې د لابراتوار ازموینو تحلیل په فوري او دقیق ډول کوي. خپل د وینې ازموینې پایلې اپلوډ کړئ او په ثانیو کې د 15,000+ بایومارکرونو بشپړه تشریح ترلاسه کړئ.
📚 د څېړنې خپرونې چې حواله شوې دي
کلین، ټي، مېچېل، ایس، او وېبر، ایچ. (2026). د وینې ډول B منفي، د LDH د وینې ازموینې او د Reticulocyte شمېرنې لارښود. Kantesti د AI طبي څېړنه.
کلین، ټي، مېچېل، ایس، او وېبر، ایچ. (2026). د روژې وروسته اسهال، په غایطه موادو کې تور داغونه او د معدې ناروغي لارښود ۲۰۲۶. Kantesti د AI طبي څېړنه.
📖 بهرني طبي مراجع
رودوالېت M او نور. (2009). The development of Assessment of SpondyloArthritis international Society classification criteria for axial spondyloarthritis. Part II: validation and final selection.. د روماتیکو ناروغیو کلنۍ راپورونه (Annals of the Rheumatic Diseases).
Ward MM et al. (2019). 2019 Update of the American College of Rheumatology/Spondylitis Association of America/SPARTAN Recommendations for the Treatment of Ankylosing Spondylitis and Nonradiographic Axial Spondyloarthritis.. Arthritis Care & Research.
Ramiro S et al. (2023). ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update.. د روماتیکو ناروغیو کلنۍ راپورونه (Annals of the Rheumatic Diseases).
⚕️ طبي ردونه
دا مقاله یوازې د زده کړې لپاره ده او طبي مشوره نه جوړوي. د تشخیص او درملنې د پرېکړو لپاره تل د وړ روغتیايي خدمت وړاندې کوونکي سره سلا وکړئ.
د E-E-A-T باور نښې
تجربه
د ډاکټر تر مشرۍ لاندې کلینیکي بیاکتنه د لابراتواري تفسیر د کاري بهیرونو لپاره.
تخصص
د لابراتواري طب تمرکز پر دې چې بایومارکرونه په کلینیکي شرایطو کې څنګه چلند کوي.
واک ورکول
د ډاکټر توماس کلاین له خوا لیکل شوی، د ډاکټر سارا میچل او پروف. ډاکټر هانس ویبر له خوا بیاکتنه.
اعتبار
د شواهدو پر بنسټ تفسیر د روښانه تعقیبي لارو چارو سره، تر څو اندیښنه کمه شي.