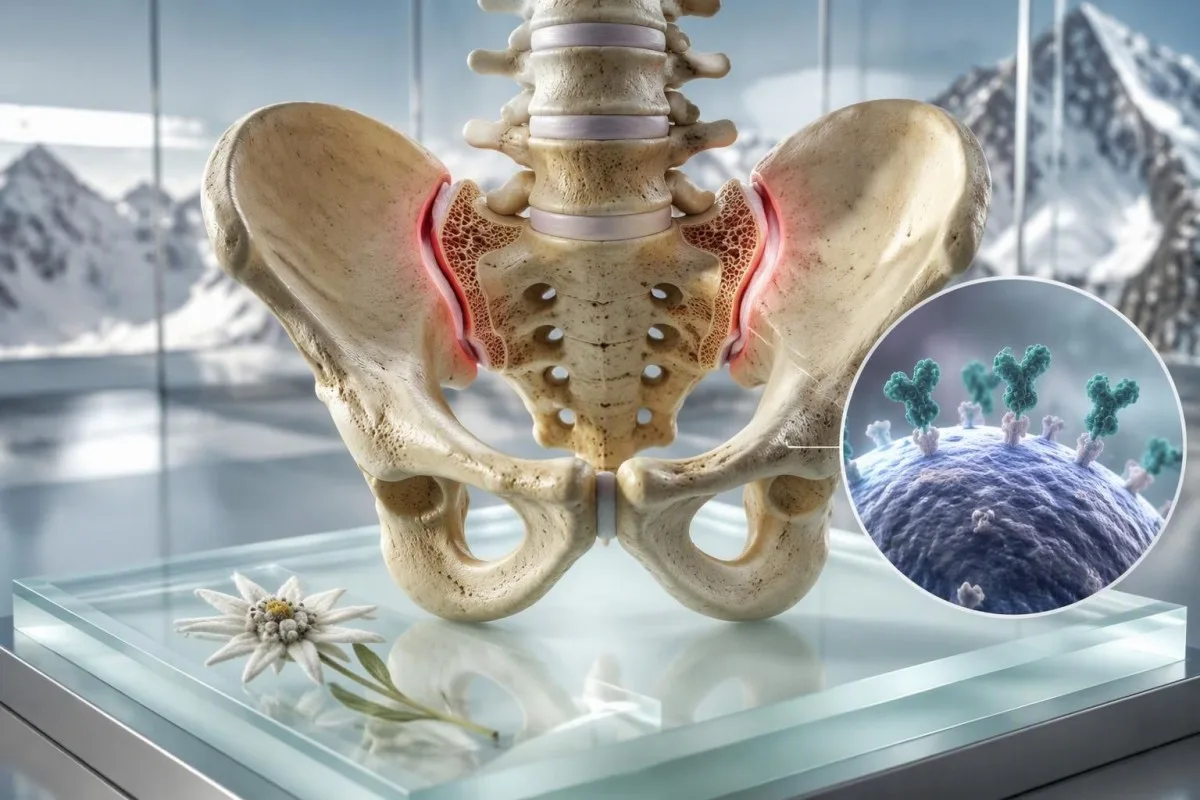
ผลบวกของ HLA-B27 บ่งชี้ถึงเครื่องหมายภูมิคุ้มกันที่ได้รับทางพันธุกรรม ไม่ใช่การวินิจฉัย มีความสำคัญมากที่สุดเมื่อมาพร้อมกับอาการปวดหลังที่เริ่มขึ้นก่อนอายุ 45 ปี, การอักเสบที่ตาอย่างฉับพลันซ้ำๆ, โรคสะเก็ดเงิน, การอักเสบของลำไส้, หรือประวัติครอบครัวใกล้ชิดของโรคข้อสันหลังอักเสบ.


- ผลบวกของ HLA-B27 หมายความว่าคุณมียีนเครื่องหมาย; ผู้ที่มียีนนี้จำนวนมากที่ไม่เคยเป็นโรคอักเสบ.
- อาการปวดหลังจากการอักเสบ มักจะเริ่มก่อนอายุ 45 ปี, เกิดขึ้นนานกว่า 3 เดือน, ดีขึ้นเมื่อเคลื่อนไหว, และมักรบกวนการนอนหลับในช่วงครึ่งหลังของคืน.
- ม่านตาอักเสบเฉียบพลันด้านหน้า ทำให้ตาแดง, เจ็บปวด, แพ้แสง, เห็นภาพไม่ชัด และต้องการการประเมินโดยจักษุแพทย์ภายในวันเดียวกัน.
- CRP ປົກກະຕິ ไม่ได้ยกเว้นโรคข้อสันหลังอักเสบแกนกลาง; CRP สูงขึ้นในคนที่มีโรคที่กำลังดำเนินอยู่เพียงบางส่วน.
- การสแกน MRI ข้อต่อกระเบนเหน็บ สามารถแสดงการตอบสนองของเนื้อเยื่อที่กำลังดำเนินอยู่ก่อนที่ภาพ X-ray ธรรมดาจะแสดงการเปลี่ยนแปลงโครงสร้าง.
- ປະຫວັດຄອບຄົວ ของโรคข้อสันหลังยึดติด, ม่านตาอักเสบ, โรคสะเก็ดเงิน, หรือโรคอักเสบในลำไส้ จะเพิ่มคุณค่าของการส่งต่อไปยังแผนกโรคข้อที่ตรงเป้าหมาย.
- ການກວດ HLA-B27 ຄວນຕອບຄຳຖາມທາງຄລີນິກ; ມັນບໍ່ແມ່ນການກວດຄັດກອງທີ່ເປັນປະໂຫຍດສຳລັບອາການເຈັບຫຼັງສ່ວນລຸ່ມແບບກົນຈັກທີ່ບໍ່ສັບສົນ.
- ອາການທາງຕາທີ່ຮີບດ່ວນ ມີຄວາມສຳຄັນກວ່າຜົນການກວດໃນຫ້ອງທົດລອງ: ຢ່າລໍຖ້າການກວດ HLA-B27 ກ່ອນທີ່ຈະໄປພົບແພດຍ້ອນອາການເຈັບຕາຫຼືການປ່ຽນແປງຂອງສາຍຕາ.
ผลบวกของ HLA-B27 บอกอะไรคุณจริงๆ
HLA-B27 ທີ່ເປັນບວກໝາຍຄວາມວ່າບຸກຄົນມີຊະນິດພັນທາງພັນທຸກຳ HLA class I ສະເພາະ; ມັນບໍ່ໄດ້ໝາຍຄວາມວ່າພວກເຂົາເປັນ ankylosing spondylitis ຫຼືຈະເປັນມັນ. ການກວດນີ້ຈະມີປະໂຫຍດທາງຄລີນິກກໍຕໍ່ເມື່ອມີອາການແລະຜົນການກວດພົບຊີ້ບອກເຖິງສະພາບການຂອງ ankylosing spondylitis. ໃນການປະຕິບັດຂອງຂ້ອຍ, ຄວາມເຂົ້າໃຈຜິດທີ່ເປັນອັນຕະລາຍທີ່ສຸດຄືການຖືວ່າຜົນເປັນບວກເປັນການຄາດຄະເນແທນທີ່ຈະເປັນສ່ວນໜຶ່ງຂອງຫຼັກຖານທີ່ອີງໃສ່ຄວາມໜ້າຈະເປັນ.
HLA-B27 ພົບໃນປະຊາກອນປະມານ 6.1% ຂອງຜູ້ໃຫຍ່ໃນສະຫະລັດ, ເຖິງແມ່ນວ່າການແຜ່ກະຈາຍຈະແຕກຕ່າງກັນຢ່າງຫຼວງຫຼາຍຕາມເຊື້ອຊາດ ແລະພູມສາດ. ມັນພົບຫຼາຍໃນບາງປະຊາກອນເອີຣົບເໜືອ ແລະຊົນເຜົ່າພື້ນເມືອງ ແລະພົບໜ້ອຍໃນກຸ່ມອື່ນໆ, ດັ່ງນັ້ນຜົນລັບຈຶ່ງມີຄຸນຄ່າໃນການຄາດຄະເນທີ່ແຕກຕ່າງກັນໃນຊຸມຊົນທີ່ແຕກຕ່າງກັນ. ຜົນລັບທີ່ເປັນລົບຫຼຸດຜ່ອນຄວາມເປັນໄປໄດ້ຂອງພະຍາດທີ່ກ່ຽວຂ້ອງກັບ HLA-B27 ແຕ່ບໍ່ສາມາດຕັດພະຍາດ axial spondyloarthritis ອອກໄດ້.
ຄວາມໝາຍຂອງການກວດ HLA-B27 ແມ່ນສອງຄ່າ: ພົບຫຼືບໍ່ພົບ, ບໍ່ແມ່ນສູງຫຼືຕ່ຳ. ຫ້ອງທົດລອງມັກຈະໃຊ້ການກວດຊະນິດພັນຈາກຕົວຢ່າງໃນຫ້ອງທົດລອງ, ແລະຜົນລັບຈະບໍ່ປ່ຽນແປງຕາມການນອນ, ອາຫານ, ການອັກເສບ, ຫຼືຢາ. ນັ້ນແຕກຕ່າງພື້ນຖານກັບຕົວຊີ້ວັດການອັກເສບເຊັ່ນ ອັດຕາການເຕັ້ນຂອງຫົວໃຈແລະຫຼອດເລືອດໃນສະໝອງ (ESR), ເຊິ່ງສາມາດປ່ຽນແປງໄດ້ໃນເວລາຫຼາຍມື້ຫາຫຼາຍອາທິດ.
ແຄນເທສຕີ ເປັນ AI ເຄື່ອງວິເຄາະເລືອດ ທີ່ວາງຜົນ HLA ທີ່ນຳເຂົ້າໄວ້ຂ້າງຕົວຊີ້ວັດການອັກເສບທີ່ກ່ຽວຂ້ອງ, ແຕ່ມັນບໍ່ສາມາດວິນິດໄສ spondyloarthritis ຈາກຕົວຊີ້ວັດທາງພັນທຸກຳເທົ່ານັ້ນ. Thomas Klein, MD, ແນະນຳໃຫ້ຄົນເຈັບຖາມຄຳຖາມທີ່ງ່າຍກວ່າ: ບັນຫາທາງຄລີນິກໃດທີ່ການກວດໄດ້ສັ່ງໃຫ້ຕອບ? ຄູ່ມື biomarker ອະທິບາຍວ່າເປັນຫຍັງຜົນທີ່ຖືກໝາຍ ຫຼືຜົນລັບທີ່ເປັນບວກຈຶ່ງຕ້ອງການວິທີການກວດໃນຫ້ອງທົດລອງ ແລະບໍລິບົດທາງຄລີນິກສະເໝີ.
ເປັນຫຍັງຜົນລັບທີ່ເປັນບວກຈຶ່ງຮູ້ສຶກໜ້າຕົກໃຈກວ່າທີ່ມັນເປັນ
ຄົນສ່ວນຫຼາຍທີ່ເປັນ HLA-B27 ບວກບໍ່ເຄີຍເປັນ ankylosing spondylitis. ຕົວຊີ້ວັດມີສ່ວນຮ່ວມໃນການນຳສະເໜີ antigen, ແຕ່ເສັ້ນທາງຊີວະສາດຈາກການຖືມັນໄປສູ່ການເປັນພະຍາດຍັງບໍ່ສຳເລັດ; ຈຸລິນຊີໃນລຳໄສ້, ການຄວບຄຸມພູມຄຸ້ມກັນ, ແລະຍີນອື່ນໆມີສ່ວນຮ່ວມ. ຄວາມບໍ່ແນ່ນອນນັ້ນແມ່ນຈິງ, ແລະຜູ້ຊ່ຽວຊານດ້ານຄລີນິກບໍ່ຄວນປ່ຽນຄວາມກ່ຽວຂ້ອງທາງພັນທຸກຳໄປເປັນການຄາດຄະເນ.
HLA-B27 และโรคข้อสันหลังยึดติด: ความสัมพันธ์กับการวินิจฉัย
ປະມານ 80% ຫາ 95% ຂອງຄົນທີ່ເປັນ radiographic ankylosing spondylitis ເປັນ HLA-B27 ບວກໃນກຸ່ມຄົນເອີຣົບເໜືອບາງກຸ່ມ, ແຕ່ຕົວຊີ້ວັດນີ້ບໍ່ແມ່ນສິ່ງຈຳເປັນຫຼືພຽງພໍສຳລັບການວິນິດໄສ. ທ່ານໝໍວິນິດໄສ axial spondyloarthritis ຈາກຮູບແບບທັງໝົດ: ອາການ, ການກວດຮ່າງກາຍ, ການສະແກນ, ຜົນການກວດໃນຫ້ອງທົດລອງ, ແລະຄຳອະທິບາຍທາງເລືອກ.
ຜົນ HLA-B27 ທີ່ເປັນບວກມີຄຸນຄ່າໃນການວິນິດໄສສູງສຸດໃນຄົນທີ່ມີອາການເຈັບຫຼັງຊໍາເຮື້ອທີ່ເລີ່ມຕົ້ນກ່ອນອາຍຸ 45 ປີ. ໃນຄົນອາຍຸ 55 ປີ ຜູ້ທີ່ເຈັບຫຼັງຄັ້ງທຳອິດເລີ່ມຕົ້ນຫຼັງຈາກຍົກເຟີນີເຈີເມື່ອອາຍຸ 52 ປີ, ຜົນລັບດຽວກັນນີ້ມັກຈະບໍ່ຄ່ອຍປ່ຽນແປງ. ນີ້ແມ່ນເຫດຜົນທີ່ການກວດທີ່ສັ່ງໂດຍບໍ່ມີຄວາມເປັນໄປໄດ້ທາງຄລີນິກກ່ອນການກວດສາມາດສ້າງຄວາມກັງວົນຫຼາຍກວ່າຄວາມຊັດເຈນ.
ລະບົບການຈັດປະເພດ ASAS ອະນຸຍາດໃຫ້ຄົນທີ່ເປັນ HLA-B27 ບວກທີ່ມີອາການເຈັບຫຼັງຊໍາເຮື້ອເລີ່ມຕົ້ນກ່ອນອາຍຸ 45 ປີ ບັນລຸເສັ້ນທາງ axial spondyloarthritis ເມື່ອມີຄຸນລັກສະນະຂອງ spondyloarthritis ອື່ນໆຢ່າງໜ້ອຍສອງຢ່າງ, ເຊັ່ນ: uveitis, psoriasis, ພະຍາດລຳໄສ້ອັກເສບ, arthritis, enthesitis, ຫຼືປະຫວັດຄອບຄົວ (Rudwaleit et al., 2009). ເກณฑ์ການຈັດປະເພດຊ່ວຍໃຫ້ການຄົ້ນຄວ້າສອດຄ່ອງ; ພວກມັນບໍ່ແມ່ນລາຍການກວດວິນິດໄສຢູ່ເຮືອນ.
Radiographic ankylosing spondylitis ອະທິບາຍເຖິງການປ່ຽນແປງໂຄງສ້າງຂອງຂໍ້ຕໍ່ sacroiliac ທີ່ສ້າງຕັ້ງຂຶ້ນໃນ X-ray, ໃນຂະນະທີ່ non-radiographic axial spondyloarthritis ອາດມີ X-ray ປົກກະຕິ. MRI ສາມາດລະບຸການຕອບສະໜອງຂອງເນື້ອເຍື່ອໃນໄຂກະດູກທີ່ກຳລັງເກີດຂຶ້ນໄດ້ໄວ, ເຖິງແມ່ນວ່າການອອກແຮງງານຂອງນັກກິລາ, ການປ່ຽນແປງທີ່ກ່ຽວຂ້ອງກັບການຖືພາ, ແລະພະຍາດທີ່ເສື່ອມສະຫຼາຍກໍ່ສາມາດເຮັດໃຫ້ການຕີຄວາມ MRI ຫຍຸ້ງຍາກໄດ້. ການກວດຫາອາການເຈັບທີ່ບໍ່ມີສາເຫດ ສາມາດຊ່ວຍກຳນົດການວິນິດໄສທີ່ເປັນໄປໄດ້ອື່ນໆ.
ຕົວເລກຄວາມສ່ຽງທີ່ຄົນເຈັບມັກຕ້ອງການ
ຍາດພີ່ນ້ອງລະດັບທຳອິດຂອງຄົນທີ່ມີໂລກຂໍ້ອັກເສບສັນຫຼັງທີ່ກ່ຽວຂ້ອງກັບ HLA-B27 ມີຄວາມສ່ຽງສູງກວ່າປະຊາກອນທົ່ວໄປ, ແຕ່ຄວາມສ່ຽງຂອງຄອບຄົວບໍ່ແມ່ນຈຸດຈົບ. ການປະເມີນຄວາມສ່ຽງແຕກຕ່າງກັນຢ່າງຫຼວງຫຼາຍຕາມເພດ, ການສືບເຊື້ອ, ແລະວ່າຍາດພີ່ນ້ອງທີ່ຖືກກະທົບມີພະຍາດທີ່ເຫັນໄດ້ຈາກການຖ່າຍຮູບລັງສີ. ຂ້າພະເຈົ້າບໍ່ແນະນຳໃຫ້ທົດສອບເດັກນ້ອຍ ຫຼືອ້າຍເອື້ອຍນ້ອງທີ່ສຸຂະພາບດີພຽງເພື່ອແກ້ໄຂຄວາມກັງວົນ ເວັ້ນເສຍແຕ່ຜູ້ຊ່ຽວຊານຈະລະບຸເຫດຜົນທາງຄລີນິກສະເພາະ.
อาการปวดหลังจากการอักเสบแตกต่างจากอาการปวดหลังทั่วไปอย่างไร
ອາການເຈັບຫຼັງອັກເສບມັກເລີ່ມຕົ້ນຄ່ອຍໆ ກ່ອນອາຍຸ 45 ປີ, ດົນກວ່າ 3 ເດືອນ, ດີຂຶ້ນເມື່ອອອກກຳລັງກາຍ, ແລະບໍ່ດີຂຶ້ນຢ່າງໜ້າເຊື່ອຖືເມື່ອພັກຜ່ອນ. ອາການເຈັບຈາກກົນຈັກມັກເກີດຂຶ້ນຕາມຫຼັງຈາກການເຄັ່ງຕຶງ, ຮ້າຍແຮງຂຶ້ນຕາມການໂຫຼດທີ່ຄາດເດົາໄດ້, ແລະດີຂຶ້ນເມື່ອການເຄື່ອນໄຫວທີ່ເຮັດໃຫ້ເກີດອາການຢຸດລົງ.
ການຕື່ນນອນໃນເຄິ່ງຫຼັງຂອງຄືນຍ້ອນອາການເຈັບຫຼັງຫຼືກົ້ນເປັນຄຳແນະນຳທີ່ເປັນປະໂຫຍດເມື່ອມັນເກີດຂຶ້ນຊ້ຳໆ, ບໍ່ແມ່ນຄັ້ງດຽວຫຼັງຈາກທີ່ນອນບໍ່ດີ. ອາການເຈັບກົ້ນສະຫຼັບກັນ, ອາການແຂງໃນຕອນເຊົ້າທີ່ດົນກວ່າ 30 ນາທີ, ແລະການປັບປຸງຢ່າງຫຼວງຫຼາຍຫຼັງຈາກເລີ່ມເຄື່ອນໄຫວ ໄດ້ເພີ່ມນ້ຳໜັກໃສ່ຮູບແບບການອັກເສບ. ບໍ່ມີອັນໃດອັນໜຶ່ງສາມາດວິນິດໄສໄດ້; ຮ່ວມກັນ, ພວກເຂົາເຈົ້າແມ່ນການຊັກຊວນຫຼາຍກວ່າ.
ຂ້ອຍມັກເຫັນນັກແລ່ນອາຍຸ 32 ປີເວົ້າວ່າ, ຂ້ອຍຮູ້ສຶກຜ່ອນຄາຍຫຼັງຈາກກິໂລແມັດທຳອິດ. ນັ້ນບໍ່ແມ່ນຫຼັກຖານຂອງການອັກເສບ—ບັນຫາຂອງລະບົບກ້າມເນື້ອຫຼາຍຢ່າງອຸ່ນຂຶ້ນ—ແຕ່ອາການເຈັບທີ່ກັບຄືນມາຫຼັງຈາກນັ່ງ, ເຮັດໃຫ້ພວກເຂົາຕື່ນນອນປະມານ 4 ໂມງເຊົ້າ, ແລະໄດ້ດຳເນີນໄປເປັນເວລາ 9 ເດືອນ ຄວນໄດ້ຮັບການແນະນຳຫຼາຍກວ່າການຍືດເສັ້ນແບບທົ່ວໄປ. ຄວາມຮຸນແຮງຂອງອາການເຈັບມີໜ້ອຍກວ່າການອະທິບາຍຮູບແບບໃນໄລຍະເວລາ.
NICE ແນະນຳການສົ່ງຕໍ່ນັກ rheumatology ສໍາລັບອາການເຈັບຫຼັງທີ່ເລີ່ມກ່ອນອາຍຸ 45 ປີ ແລະດົນກວ່າ 3 ເດືອນເມື່ອມີຄຸນລັກສະນະຂອງ spondyloarthritis ຫຼາຍຢ່າງຄົງຢູ່; ການທົດສອບ HLA-B27 ສາມາດສະໜັບສະໜູນການສົ່ງຕໍ່ເມື່ອມີຄຸນລັກສະນະສາມຢ່າງຄົງຢູ່. ການເຮັດວຽກຂອງລໍາໄສ້ຫຼືກະເພາະປັດສະວະໃຫม่, ການຊາຂອງອະໄວຍະວະເພດ, ໄຂ້, ນ້ຳໜັກລົດລົງທີ່ບໍ່ມີສາເຫດ, ປະຫວັດການເປັນມະເລັງ, ຫຼືຄວາມອ່ອນແອທີ່ຮ້າຍແຮງຂຶ້ນຢ່າງໄວຕ້ອງການການປະເມີນດ່ວນສໍາລັບສາເຫດນອກເໜືອຈາກໂລກຂໍ້ອັກເສບສັນຫຼັງ. ທົບທວນຄວາມແຕກຕ່າງທີ່ໃຊ້ໄດ້ຈິງລະຫວ່າງການອັກເສບແລະການບາດເຈັບໃນ ຄູ່ມືຫ້ອງທົດລອງໂລກສະເກັດເງິນ, ໂດຍສະເພາະແມ່ນຖ້າມີພະຍາດຜິວໜັງຢູ່ນໍາ.
ບັນທຶກອາການສອງອາທິດທີ່ມີປະໂຫຍດ
ບັນທຶກເວລາຕື່ນນອນ, ໄລຍະເວລາແຂງ, ການຕອບສະໜອງຕໍ່ການອອກກຳລັງກາຍ, ຕຳແໜ່ງກົ້ນ, ແລະການຕອບສະໜອງຂອງຢາຕ້ານການອັກເສບເປັນເວລາ 14 ວັນກ່ອນການນັດໝາຍ. ນີ້ເຮັດໃຫ້ມີມູນຄ່າການວິນິດໄສຫຼາຍກວ່າຄະແນນອາການເຈັບທົ່ວໄປຈາກ 0 ຫາ 10, ເພາະວ່ານັກວິນິດໄສໂລກຂໍ້ກຳລັງຊອກຫາຈັງຫວະການອັກເສບທີ່ສາມາດເຮັດຊ້ຳໄດ້.
เมื่ออาการตาแดงที่เกี่ยวข้องกับ HLA-B27 ต้องการการดูแลภายในวันเดียวกัน
ຕາແດງເຈັບທີ່ມີອາການແພ້ແສງສະຫວ່າງ, ວິໄສທັດມືດ, ຫຼືຮູຕາທີ່ເບິ່ງຄືວ່ານ້ອຍກວ່າສາມາດເປັນໂລກຕາອັກເສບດ້ານໜ້າແບບສ້ວຍແຫຼມແລະຕ້ອງໄດ້ຮັບການປະເມີນໃນມື້ດຽວໂດຍຜູ້ຊ່ຽວຊານດ້ານຕາຫຼືບໍລິການຕາສຸກເສີນ. ໂລກຕາອັກເສບທີ່ກ່ຽວຂ້ອງກັບ HLA-B27 ມັກຈະເລີ່ມຕົ້ນຢ່າງກະທັນຫັນໃນຕາດຽວແລະສາມາດເກີດຂຶ້ນອີກ, ບາງຄັ້ງກໍເກີດຂຶ້ນໃນຕາອີກເບື້ອງໜຶ່ງໃນວັນທີຕໍ່ມາ.
ໂລກຕາອັກເສບດ້ານໜ້າແບບສ້ວຍແຫຼມບໍ່ແມ່ນອັນດຽວກັບໂລກຕາແດງ. ໂລກຕາແດງມັກຈະເຮັດໃຫ້ມີການໄຫຼອອກຫຼືຄວາມບໍ່ສະບາຍແບບຊາຍເມັດ; ໂລກຕາອັກເສບມັກຈະເຮັດໃຫ້ເກີດອາການເຈັບເລິກ, ຄວາມແພ້ແສງສະຫວ່າງ, ການເບິ່ງເຫັນແຈ້ງຫຼຸດລົງ, ແລະອາການແດງທີ່ຢູ່ອ້ອມຂ້າງຮູມ່ານຕາ. ຕາພາຍນອກທີ່ເບິ່ງປົກກະຕິບໍ່ສາມາດກຳຈັດມັນໄດ້ຢ່າງໜ້າເຊື່ອຖື, ໂດຍສະເພາະແມ່ນໃນໄລຍະເລີ່ມຕົ້ນ.
ປະມານເຄິ່ງໜຶ່ງຂອງກໍລະນີ uveitis ດ້ານໜ້າສ້ ຳຄັນໃນກຸ່ມຄົນເຊື້ອສາຍເອີຣົບສ່ວນຫຼາຍແມ່ນ HLA-B27 ບວກ, ແຕ່ຈັກກະແພດຍັງພິຈາລະນາການຕິດເຊື້ອ, sarcoidosis, ພະຍາດ Behçet, ພະຍາດ ລຳ ໄສ້ອັກເສບ, ການບາດເຈັບ, ແລະຜົນກະທົບຂອງຢາ. ຢ່າໃຊ້ຢາຢອດຕາສະເຕີຣອຍດ໌ທີ່ເຫລືອໂດຍບໍ່ໄດ້ກວດ, ເພາະວ່າຢາຢອດສະເຕີຣອຍດ໌ສາມາດເຮັດໃຫ້ການຕິດເຊື້ອຂອງແກ້ວຕາທີ່ບໍ່ໄດ້ຮັບການວິນິດໄສຮ້າຍແຮງຂຶ້ນແລະເພີ່ມຄວາມດັນຕາ. ຄູ່ມືຂອງພວກເຮົາ ອາການແສບຕາຂອງ Behçet ກວມເອົາສະພາບອື່ນທີ່ເປັນບາດແຜໃນປາກ ແລະ ອາການທາງຕາປ່ຽນຄວາມຮີບດ່ວນ.
ການປິ່ນປົວມັກຈະໃຊ້ຢາຢອດ Corticosteroid ພາຍນອກຕາມໃບສັ່ງແພດ, ພ້ອມກັບຢາຢອດທີ່ຂະຫຍາຍຮູມ່ານຕາ, ໂດຍມີການຫຼຸດລົງຕາມຄຳແນະນຳຂອງຈັກກະແພດ. ການຕິດຕາມແມ່ນສຳຄັນເພາະວ່າຄວາມດັນສູງ ແລະ ອາການບວມຢູ່ດ້ານຫຼັງຂອງຕາສາມາດເກີດຂຶ້ນໄດ້ແມ້ວ່າອາການເຈັບຈະດີຂຶ້ນກໍ່ຕາມ. ອາການທີ່ເກີດຂຶ້ນຊ້ຳຄວນກະຕຸ້ນໃຫ້ເກີດການສື່ສານລະຫວ່າງຈັກກະແພດ ແລະ ໝໍຮັກສາຂໍ້ຕໍ່ ແທນທີ່ຈະເປັນການດູແລແບບຂະໜານ, ທີ່ບໍ່ເຊື່ອມຕໍ່ກັນ.
ອາການທີ່ບໍ່ຄວນລໍຖ້ານັດຫມາຍປົກກະຕິ
ການສູນເສຍການເບິ່ງເຫັນຢ່າງກະທັນຫັນ, ຜ້າມ່ານຫຼືການຫຼຸດລົງຂອງຈຸດດ່າງດຳໃໝ່, ເຈັບຫົວຢ່າງຮຸນແຮງພ້ອມກັບອາການຄັນ, ແວ່ນຕາອ້ອມແສງ, ຫຼືເຈັບຕາຢ່າງຮຸນແຮງຕ້ອງໄດ້ຮັບການປະເມີນສຸກເສີນທັນທີ. ຄຸນລັກສະນະເຫຼົ່ານີ້ສາມາດເປັນສັນຍານບົ່ງຊີ້ທີ່ແຕກຕ່າງຈາກ uveitis, ລວມທັງ ຕໍ້ຫີນສ້ ຳຄັນ ຫຼື ພະຍາດຈໍ້າຕາ, ບ່ອນທີ່ການຊັກຊ້າສາມາດເປັນອັນຕະລາຍຕໍ່ການເບິ່ງເຫັນ.
อาการอื่นๆ ที่ทำให้ HLA-B27 มีความสำคัญมากขึ้น
HLA-B27 ມີຄວາມໝາຍທາງຄລີນິກຫຼາຍຂຶ້ນເມື່ອມີອາການເຈັບຫຼັງຫຼືຕາເກີດຂຶ້ນກັບ Psoriasis, ພະຍາດລຳໄສ້ອັກເສບ, Enthesitis ທີ່ສົ້ນຕີນ, ຂໍ້ຕໍ່ໃຄ່ບວມ, ຫຼືຍາດພີ່ນ້ອງໃກ້ຊິດທີ່ເປັນພະຍາດທີ່ກ່ຽວຂ້ອງ. ກຸ່ມອາການນີ້ເອີ້ນວ່າ "spondyloarthritis spectrum" ເພາະວ່າເນື້ອເຍື່ອຕ່າງໆອາດຈະມີສ່ວນຮ່ວມໃນເວລາທີ່ແຕກຕ່າງກັນ.
Enthesitis ແມ່ນການອັກເສບບ່ອນທີ່ເສັ້ນເອັນ ຫຼື ເສັ້ນເອັນຕິດກັບກະດູກ, ໂດຍທົ່ວໄປແລ້ວເຮັດໃຫ້ເກີດອາການເຈັບຈຸດຢູ່ບໍລິເວນ Achilles insertion ຫຼື ດ້ານລຸ່ມຂອງສົ້ນຕີນ. ມັນແຕກຕ່າງຈາກອາການເຈັບຕີນທົ່ວໄປ ເພາະຄວາມເຈັບປວດມັກຈະຢູ່ສະເພາະບ່ອນ ແລະ ອາດຈະຮ້າຍແຮງທີ່ສຸດຫຼັງຈາກພັກຜ່ອນ. Ultrasound ສາມາດຊ່ວຍໄດ້, ແຕ່ ນ້ ຳໜັກໂຕ, ການອອກກຳລັງກາຍ, ແລະ ເກີບສາມາດເຮັດໃຫ້ເກີດອາການຄ້າຍຄືກັນ.
ການເປັນຂຸ່ນຂອງເລັບທີ່ກ່ຽວຂ້ອງກັບ Psoriasis, ການແຍກຂອງແຜ່ນເລັບ, ຫຼືນິ້ວມືຫຼືນິ້ວຕີນທັງໝົດທີ່ໃຄ່ບວມສາມາດເປັນຂໍ້ຄຶດທີ່ເປັນປະໂຫຍດໂດຍສະເພາະໃນການວິນິດໄສ. ບຸກຄົນບໍ່ຈຳເປັນຕ້ອງເປັນ Psoriasis ທີ່ແຜ່ລາມເພື່ອໃຫ້ເລື່ອງນີ້ມີຄ່າ; ບາງສ່ວນນ້ອຍໆຢູ່ໜັງຫົວ ຫຼື ປະຫວັດຍາວຂອງແຜ່ນໜັງທີ່ລອກອອກຢູ່ຫຼັງຫູອາດຈະສຳຄັນ. ການຖ່າຍຮູບຜື່ນທີ່ເປັນໆຫາຍໆກ່ອນມັນຈາງຫາຍໄປສາມາດຊ່ວຍປະຢັດເວລາໄດ້ຢ່າງໜ້າປະຫລາດໃຈເມື່ອທົບທວນ.
ຖອກທ້ອງຊໍາເຮື້ອ, ຄວາມຮີບດ່ວນໃນການຂັບຖ່າຍໃນເວລາກາງຄືນ, ເລືອດອອກທາງຮູທະວານ, ຫຼືນ້ ຳໜັກລຸດລົງໂດຍບໍ່ໄດ້ຕັ້ງໃຈຄວນກະຕຸ້ນໃຫ້ມີການປະເມີນລຳໄສ້ແທນທີ່ຈະຖືວ່າເປັນຍ້ອນຄວາມຄຽດ. Faecal calprotectin ມີປະໂຫຍດໃນການກວດຫາການຕອບສະໜອງຂອງເນື້ອເຍື່ອໃນລຳໄສ້ ແຕ່ບໍ່ສະເພາະເຈาะຈົງກັບພະຍາດ Crohn ຫລື ພະຍາດ Ulcerative colitis; ຂອງພວກເຮົາ ການປຽບທຽບ calprotectin ອະທິບາຍຂໍ້ຈຳກັດຂອງມັນ. ການເຊື່ອມຕໍ່ມີຄວາມສຳຄັນເພາະວ່າການອັກເສບຂອງລຳໄສ້ອາດຈະຊີ້ ນຳ ທັງການເລືອກຮູບພາບ ແລະ ການເລືອກການປິ່ນປົວ.
ອາການທີ່ບໍ່ເຂົ້າກັນຢ່າງແນ່ນອນ
ຄວາມເມື່ອຍລ້າເປັນເລື່ອງທຳມະດາໃນພະຍາດອັກເສບທີ່ກຳລັງດຳເນີນຢູ່ ແຕ່ບໍ່ສະເພາະເຈາະຈົງເກີນໄປທີ່ຈະກຳນົດການວິນິດໄສ. ການຂາດທາດເຫຼັກ, ການນອນຫຼັບບໍ່ເປັນລະບົບ, ຄວາມຜິດປົກກະຕິຂອງຕ່ອມໄທລອຍ, ຄວາມຜິດປົກກະຕິທາງອາລົມ, ຢາ, ແລະ ອາການເຈັບທີ່ຍາວນານ ສາມາດປະກອບສ່ວນໄດ້ທັງໝົດ, ສະນັ້ນຂ້ອຍຊອກຫາຮູບແບບທີ່ສອດຄ່ອງ ແທນທີ່ຈະກຳນົດຄວາມເມື່ອຍລ້າໃຫ້ກັບ HLA-B27.
ประวัติครอบครัวเปลี่ยนแปลงขั้นตอนต่อไปอย่างไร
ຍາດພີ່ນ້ອງລະດັບທຳອິດທີ່ມີ ankylosing spondylitis, uveitis ທີ່ເກີດຂຶ້ນຊ້ຳ, psoriasis, ພະຍາດລຳໄສ້ອັກເສບ, ຫລື ຂໍ້ຕໍ່ອັກເສບ reactive ເພີ່ມຄວາມສົງໄສເມື່ອມີອາການທີ່ເຂົ້າກັນໄດ້. ປະຫວັດຄອບຄົວສະໜັບສະໜູນການຕັດສິນໃຈສົ່ງຕໍ່; ມັນບໍ່ໄດ້ເຮັດໃຫ້ການທົດສອບຫຼືການຖ່າຍຮູບເປັນສິ່ງຈຳເປັນໃນຄົນທີ່ບໍ່ມີອາການ.
Ask relatives about diagnoses and major symptoms, not only whether they carry HLA-B27. People may remember being told they had iritis, a stiff spine, Crohn disease, or psoriasis but have never heard the term spondyloarthritis. The age at symptom onset is especially valuable: back pain that began at 22 tells a different story from osteoarthritis diagnosed at 72.
Kantesti AI គឺជាអ្វីមួយដែល ແພລດຟອມການອ່ານຜົນກວດເລືອດຂອງ AI that can organise family-shared laboratory histories with consent, but family-history patterns still require a clinician to verify diagnoses. A useful record includes affected relative, relationship, condition, age at onset, eye episodes, and relevant imaging. Our ຕົວຕິດຕາມປະຫວັດຄອບຄົວ offers a practical template for recording that detail.
Routine HLA-B27 testing in symptom-free relatives usually does not improve outcomes. The result can create false reassurance when negative and unnecessary fear when positive, because no proven preventive treatment is prescribed simply for carrier status. A child with persistent limp, eye symptoms, or swollen joints needs paediatric assessment based on symptoms, whatever the family genotype.
What to bring to a specialist appointment
Bring prior X-ray or MRI reports, eye-clinic letters, medication dates, and a one-page family history. Imaging discs or digital access are often more useful than repeating scans, particularly because sacroiliac-joint MRI requires experienced interpretation.
เหตุใดการทดสอบการอักเสบตามปกติจึงไม่สามารถตัดภาวะนี้ออกได้
Normal CRP and ESR do not rule out axial spondyloarthritis or HLA-B27-associated uveitis. These tests measure systemic inflammatory activity indirectly, and localized disease can be clinically active while both results remain within the laboratory reference interval.
CRP is often reported in mg/L, with many laboratories using less than 5 mg/L as a reference threshold, while ESR reference limits vary with age and sex. A CRP of 2 mg/L can coexist with active sacroiliac inflammation on MRI. Conversely, a CRP of 28 mg/L is non-specific and may reflect infection, obesity, dental inflammation, or another inflammatory condition.
A complete blood count, liver profile, kidney profile, CRP, and ESR are baseline context tests rather than diagnostic proof. Anaemia, raised platelets, low albumin, or iron deficiency can suggest persistent inflammation or bowel involvement, but each has alternative explanations. This is one reason inflammatory conditions should not be inferred from a single marker.
ແຄນເທສຕີ ເປັນ ឧបករណ៍វិភាគតេស្តឈាមដែលដំណើរការដោយ AI that can compare CRP, platelets, haemoglobin, and albumin across dates, helping users identify a pattern to discuss with their clinician. It cannot see sacroiliitis on an MRI or assess a painful eye. For antibody results that can be over-interpreted in a similar way, see our explanation of ການກວດ ANA.
Medication and test interpretation
NSAIDs can reduce CRP and improve symptoms without proving or disproving the diagnosis. Do not stop prescribed anti-inflammatory medication before testing unless the clinician managing your care specifically asks you to; an artificial flare is not a safe diagnostic strategy.
การสแกนใดบ้างที่ช่วยได้ และแต่ละการสแกนสามารถพลาดอะไรไปได้บ้าง
MRI of the sacroiliac joints is the preferred scan when axial spondyloarthritis is suspected but X-rays are normal or inconclusive. X-rays show structural change that often develops slowly, whereas MRI can show active bone-marrow tissue response and other early changes.
A normal lumbar-spine MRI does not replace a dedicated sacroiliac-joint MRI protocol. The relevant joints are lower and more lateral than the area commonly imaged for a slipped disc. I have seen patients reassured by an ordinary lumbar scan that was simply not designed to answer the inflammatory question.
MRI findings require clinical correlation because bone-marrow oedema can occur after intense exercise, childbirth, mechanical stress, and degenerative change. The radiology report should describe location, depth, distribution, erosions, fat change, and structural features; a vague statement of oedema alone is not enough. A rheumatologist may ask for image review when the report and symptom pattern disagree.
Pelvic X-rays remain useful for documenting chronic sacroiliac structural changes, but a normal X-ray does not close the case in a younger person. CT shows structure very clearly but uses ionising radiation and is not generally the first choice for early inflammatory disease. If persistent inflammation affects mobility, bone-health assessment may also be relevant; read our bone loss laboratory guide.
Why the scan report can sound uncertain
Radiologists appropriately use terms such as compatible with or non-specific when the imaging pattern is not definitive. That wording is not evasive; it reflects a real overlap between inflammatory and mechanical findings, and it prevents imaging from being treated as a diagnosis in isolation.
เมื่อใดควรขอส่งต่อไปยังแผนกโรคข้อ
Ask for rheumatology evaluation when chronic back pain began before age 45 and is accompanied by inflammatory features, HLA-B27 positivity, recurrent uveitis, psoriasis, bowel symptoms, heel enthesitis, or a relevant family history. A positive test plus one convincing clinical feature is more useful than a positive test discovered during broad screening.
A referral is reasonable even when CRP is normal and X-rays are unremarkable if the clinical pattern is compelling. The 2019 ACR/SAA/SPARTAN guideline recommends treatment decisions based on disease activity, function, comorbidities, and patient preferences rather than a genetic result alone (Ward et al., 2019). This approach prevents both delayed diagnosis and reflexive overtreatment.
At the appointment, expect questions about age at onset, morning stiffness, night waking, response to NSAIDs, eye attacks, skin lesions, bowel symptoms, infection preceding arthritis, and family history. A rapid and clear response to a full-dose NSAID may support suspicion, but it is not a diagnostic test. NSAIDs also improve ordinary back pain.
Thomas Klein, MD, recommends making a dated timeline rather than trying to remember every symptom in the consulting room. Include medication dose and duration, especially if using ibuprofen, naproxen, or diclofenac, because kidney function, blood pressure, ulcer risk, and anticoagulant use alter the safety calculation. Our medication trend guide explains why repeat kidney and liver results may matter during longer courses.
When an orthopaedic or physiotherapy assessment may be better first
Back pain starting after age 45 following a specific injury, with clear load-related triggers and no inflammatory features, more often benefits initially from musculoskeletal care. That is a probability statement, not a dismissal; persistent uncertainty or new eye, skin, bowel, or joint symptoms warrants reassessment.
การรักษาเป็นอย่างไรหากได้รับการยืนยันว่าเป็นโรคข้อสันหลังอักเสบแกนกลาง
Confirmed axial spondyloarthritis is treated with education, regular movement, targeted physiotherapy, and anti-inflammatory medicines; biologic or targeted synthetic medicines are reserved for persistent active disease. HLA-B27 status does not determine treatment by itself.
Exercise is treatment, not a test of willpower. A programme that maintains spinal extension, hip mobility, chest expansion, and aerobic capacity is generally more sustainable than sporadic intense workouts. Most patients find short daily mobility work of 10 to 20 minutes easier to keep than a single ambitious weekend session.
NSAIDs are usually considered first-line when safe, but dose and duration must be individualised. Naproxen 500 mg twice daily is a common adult anti-inflammatory dose, yet it may be unsuitable with chronic kidney disease, prior ulcer bleeding, heart failure, uncontrolled hypertension, anticoagulants, or pregnancy. Gastroprotection may be appropriate for some people, but it does not remove kidney or cardiovascular risk.
Biologic medicines such as TNF inhibitors and IL-17 inhibitors require screening and specialist monitoring because infection risk and comorbidities affect selection. Recurrent uveitis, psoriasis, and inflammatory bowel disease influence which agent best fits the whole person. This is one reason a diagnosis based only on an HLA-B27 result can lead to the wrong treatment conversation.
Avoid the supplement trap
No supplement has been shown to prevent HLA-B27-associated spondyloarthritis in healthy carriers. Correcting a documented vitamin D, iron, or B12 deficiency can improve general health, but it is not a substitute for assessment of inflammatory back pain or a painful red eye.
วิธีติดตามผลลัพธ์โดยไม่ยึดติดกับมัน
The most useful record combines symptoms, function, medications, eye episodes, imaging, and laboratory trends rather than repeatedly retesting HLA-B27. Once accurately typed, HLA-B27 status does not need serial monitoring because your inherited marker does not change.
Track functional measures that mean something to you, such as minutes until morning stiffness eases, uninterrupted sleep, walking tolerance, or ability to turn while driving. These details show treatment response more honestly than a single good or bad day. Note whether an eye flare preceded a back-pain change by days or weeks.
Kantesti can organise imported laboratory reports across time and flag changes for discussion, but it should not be used to self-start or stop prescription treatment. Our clinical framework is described in the ຄູ່ມືເທັກໂນໂລຍີ AI: results are interpreted as context for professional care, not as a replacement for examination or imaging.
Repeating CRP during a flare can be useful when a clinician is also following symptoms and treatment response, but routine weekly testing is rarely helpful. In my experience, a symptom record every day and blood work at clinically meaningful intervals yields less noise and fewer false alarms. Laboratory trends only become informative when collection dates, infections, exercise, and medicines are documented.
A note about privacy and family data
Genetic information can affect relatives as well as the person tested, so share reports deliberately. Keep the original laboratory report, remove unrelated identifiers when appropriate, and obtain consent before adding another adult's results to a shared family record.
ความเข้าใจผิดทั่วไปเกี่ยวกับการเป็นผลบวกของ HLA-B27
HLA-B27 positivity does not mean your immune system is attacking your spine, that you are contagious, or that you need treatment while symptom-free. It is a common inherited allele whose significance depends on the clinical setting.
Myth: a positive HLA-B27 test explains every ache. Fact: mechanical back pain remains common among HLA-B27 carriers. Strain, disc disease, hip disorders, hypermobility, fibromyalgia, kidney stones, and pelvic conditions still deserve a normal differential diagnosis. The marker should sharpen clinical reasoning, not end it.
Myth: a negative HLA-B27 test rules out ankylosing spondylitis. Fact: HLA-B27-negative axial spondyloarthritis occurs, especially across populations with lower background carrier frequency. When imaging and clinical features are persuasive, a negative result should not be used to deny specialist review.
Myth: genes are the same as destiny. Fact: genetics influence risk, but no preventive biologic therapy is indicated for a well HLA-B27 carrier. This is conceptually similar to the limits of MTHFR result interpretation: genetic information is medically useful only when the result changes an evidence-based decision.
Can stress cause a flare?
Stress can worsen pain, sleep, fatigue, and coping, but it does not explain away objective uveitis or inflammatory arthritis. Treating sleep and stress is worthwhile alongside medical care; it should never delay eye assessment or replace a work-up for persistent inflammatory symptoms.
คำถามที่ทำให้การนัดหมายครั้งแรกมีประโยชน์มากขึ้น
The best first appointment questions focus on probability, alternative diagnoses, and the next decision—not on whether HLA-B27 is good or bad. A clinician should be able to explain what finding would increase or decrease their suspicion and what test would change management.
Ask whether your symptoms meet an inflammatory-back-pain pattern and which features argue against it. Then ask whether dedicated sacroiliac MRI is appropriate, whether an ophthalmology referral is needed, and whether psoriasis or bowel symptoms warrant coordinated review. This approach respects uncertainty without letting it become inaction.
Ask how long to try a treatment, what outcome defines success, and which adverse effects need a call. For NSAIDs, the specific safety discussion should include kidney function, blood pressure, gastrointestinal history, pregnancy plans, and interacting drugs. For biologics, ask about screening, vaccines, infection precautions, and how uveitis or bowel disease changes the choice.
Kantesti's clinical content is medically reviewed with structured quality controls; readers can examine our ວິທີການຢືນຢັນທາງການແພດຂອງພວກເຮົາ និងសមត្ថភាព/គុណវុឌ្ឍិ (credentials) របស់ ຄະນະທີ່ປຶກສາດ້ານການແພດ. A laboratory interpretation is most valuable when it helps you ask a better question of the clinician who can examine you.
A concise appointment script
Say: My back pain started at age 29, has lasted 14 months, wakes me at 4 a.m., improves after 30 minutes of movement, and I had a painful light-sensitive eye last spring. That one sentence gives a rheumatologist more usable information than stating only that an HLA-B27 result was positive.
อาการเร่งด่วนและแผนขั้นตอนต่อไปที่ปลอดภัย
Seek same-day urgent eye care for eye pain, light sensitivity, red eye with blurred vision, or any sudden visual change; seek emergency care for new weakness, bladder or bowel dysfunction, saddle numbness, high fever, or severe unremitting back pain. Do not wait for repeat blood work, an MRI booking, or a rheumatology appointment when these red flags occur.
For non-urgent symptoms, book a primary-care review within weeks if back pain has lasted more than 3 months and began before age 45, especially with HLA-B27 positivity or family history. Bring your HLA report, symptom timeline, medication list, eye-clinic letters, and prior images. A targeted referral is generally faster and more useful than repeating broad autoimmune panels.
As of September 27, 2026, the central clinical principle remains unchanged: HLA-B27 is a risk marker, not a diagnosis. Thomas Klein, MD, has found that patients do best when they treat a positive result as a prompt to notice patterns—then obtain the right eye, primary-care, or rheumatology assessment rather than catastrophising or ignoring symptoms.
ແຄນເທສຕີ ເປັນ ບໍລິການຕີຄວາມຜົນການກວດຂອງ AI built to explain laboratory reports in plain language while preserving the boundary between information and diagnosis. Learn how our organisation approaches this work on our ໜ້າ About Us and find further patient education in the ບລັອກ Kantesti.
ພາກສ່ວນການຕີພິມງານວິຈັຍ
Kantesti LTD. (2026). ຄູ່ມືປະເພດເລືອດ B ລົບ, ການກວດ LDH ແລະການນັບ reticulocyte. Figshare. https://doi.org/10.6084/m9.figshare.31333819. Related author records may be located through ປະຕູຄົ້ນຄວ້າ ແລະ Academia.edu.
Kantesti LTD. (2026). ຖອກທ້ອງຫຼັງຈາກອົດອາຫານ, ມີຈຸດດຳໃນອາຈົມ ແລະ ຄູ່ມືກ່ຽວກັບລະບົບຍ່ອຍອາຫານ ປີ 2026. Figshare. https://doi.org/10.6084/m9.figshare.31438111. Related author records may be located through ປະຕູຄົ້ນຄວ້າ ແລະ Academia.edu.
These publications are not evidence for diagnosing HLA-B27-associated disease and should not replace the rheumatology and ophthalmology references cited above. They are listed as Kantesti research records for transparency.
ຄໍາຖາມທີ່ຖາມເລື້ອຍໆ
ຖ້າຜົນກວດ HLA-B27 ເປັນບວກໝາຍຄວາມວ່າຂ້ອຍເປັນໂລກຂໍ້ອັກເສບສັນຫຼັງຄົດບໍ?
ບໍ່. ຜົນບວກຂອງ HLA-B27 ໝາຍຄວາມວ່າທ່ານມີເຄື່ອງໝາຍພັນທຸກຳທີ່ກ່ຽວຂ້ອງກັບ ankylosing spondylitis ແລະພະຍາດທີ່ກ່ຽວຂ້ອງ, ແຕ່ຜູ້ຖືຫຼາຍຄົນຍັງມີສຸຂະພາບດີຕະຫຼອດຊີວິດ. ໃນກຸ່ມຄົນທີ່ມີ ankylosing spondylitis ທີ່ເຫັນໄດ້ຈາກຮູບ X-ray, ປະມານ 80% ຫາ 95% ຈະມີ HLA-B27 ບວກ, ແຕ່ກໍ່ບໍ່ແມ່ນຄວາມຈິງ: ຄົນສ່ວນໃຫຍ່ທີ່ບວກບໍ່ມີພະຍາດດັ່ງກ່າວ. ການວິນິດໄສຮຽກຮ້ອງໃຫ້ມີອາການທີ່ເຂົ້າກັນໄດ້, ການກວດ, ການຖ່າຍຮູບ, ແລະການຍົກເວັ້ນສາເຫດອື່ນໆ.
อาการปวดหลังแบบใดที่บ่งบอกถึงการอักเสบที่เกี่ยวข้องกับ HLA-B27?
อาการปวดหลัง บ่งชี้ถึงภาวะ axial spondyloarthritis ได้มากขึ้น เมื่อเริ่มมีอาการก่อนอายุ 45 ปี เริ่มค่อยเป็นค่อยไป เป็นนานกว่า 3 เดือน ดีขึ้นเมื่อเคลื่อนไหว และทำให้เกิดอาการปวดตึงในตอนเช้าเป็นเวลานานกว่า 30 นาที การตื่นนอนซ้ำในช่วงครึ่งหลังของคืน และอาการปวดสะโพกสลับข้าง เพิ่มข้อมูลที่เป็นประโยชน์ ผลตรวจ HLA-B27 เป็นบวก ช่วยเพิ่มความน่าเชื่อถือของรูปแบบนี้ แต่แพทย์ยังคงต้องประเมินสาเหตุจากกลไกและสัญญาณอันตราย.
HLA-B27 ສາມາດເຮັດໃຫ້ເກີດການອັກເສບໃນຕາໄດ້ບໍ?
HLA-B27 ບໍ່ໄດ້ກໍ່ໃຫ້ເກີດບັນຫາສາຍຕາທຸກຢ່າງໂດຍກົງ, ແຕ່ມັນກ່ຽວພັນຢ່າງໜັກແໜ້ນກັບການອັກເສບຂອງເສັ້ນເລືອດໃນຕາດ້ານໜ້າແບບສ້ວຍແຫຼມ (acute anterior uveitis). ການອັກເສບຂອງເສັ້ນເລືອດໃນຕາຊະນິດນີ້ມັກຈະເຮັດໃຫ້ຕາແດງຢ່າງກະທັນຫັນຂ້າງດຽວ, ເຈັບເລິກ, ແສງເຂົ້າຕາບໍ່ໄດ້ (light sensitivity), ແລະຕາມົວ; ມັນຕ້ອງການການກວດໂດຍຈັກກະແພດຕາພາຍໃນມື້ດຽວ. ປະມານເຄິ່ງໜຶ່ງຂອງກໍລະນີການອັກເສບຂອງເສັ້ນເລືອດໃນຕາດ້ານໜ້າແບບສ້ວຍແຫຼມແມ່ນມີຜົນກວດ HLA-B27 ເປັນບວກໃນຫຼາຍກຸ່ມປະຊາກອນທີ່ມາຈາກເອີລົບ, ເຖິງວ່າຄວາມຊຸກຊີ້ຈະແຕກຕ່າງກັນໄປຕາມປະຊາກອນແລະຕ້ອງໄດ້ພິຈາລະນາສາເຫດອື່ນໆ.
ຂ້ອຍຄວນໄປພົບແພດໝໍພະຍາດຂໍ້, ຖ້າຂ້ອຍກວດພົບວ່າຕິດເຊື້ອ HLA-B27 ແຕ່ບໍ່ມີອາການບໍ?
ຄົນສ່ວນຫຼາຍທີ່ເປັນພາຫະພະຍາດ HLA-B27 ແຕ່ບໍ່ສະແດງອາການ ບໍ່ຈຳເປັນຕ້ອງໄດ້ຮັບການຕິດຕາມຈາກແພດຊ່ຽວຊານດ້ານຂໍ້ຕໍ່ ຫຼື ການປິ່ນປົວແບບປ້ອງກັນ. ການກວດສອບຄືນຈະມີຄວາມໝາຍເມື່ອອາການເຈັບຫຼັງຊຳເຮື້ອເລີ່ມຕົ້ນກ່ອນອາຍຸ 45 ປີ, ຕາອັກເສບຊ້ຳເລື້ອ, ໂລກສະເກັດເງິນ, ອາການກະເພາະລຳໄສ້ບໍ່ຫາຍ, ເຈັບສົ້ນຕີນຈາກການອັກເສບຂອງຈຸດທີ່ກ້າມເນື້ອຕິດກັບກະດູກ, ຂໍ້ບວມ, ຫຼື ມີປະຫວັດຄອບຄົວທີ່ແຂງແຮງ. ການກວດຊ້ຳ HLA-B27 ບໍ່ເປັນປະໂຫຍດ ເພາະສະຖານະ HLA ທີ່ໄດ້ຮັບມາຍັງຄົງທີ່ຕະຫຼອດເວລາ.
CRP ແລະ ESR ສາມາດເປັນປົກກະຕິໄດ້ກັບ ankylosing spondylitis ບໍ?
ແມ່ນແລ້ວ. CRP ໂດຍທົ່ວໄປແລ້ວມີລາຍງານວ່າເປັນປົກກະຕິຕໍ່າກວ່າ 5 mg/L ໃນຫ້ອງທົດລອງຫຼາຍແຫ່ງ, ແຕ່ CRP ແລະ ESR ທີ່ເປັນປົກກະຕິບໍ່ສາມາດຕັດອອກ axial spondyloarthritis ຫລື uveitis ທີ່ກຳລັງອັກເສບໄດ້. ຕົວຊີ້ວັດເຫຼົ່ານີ້ສະທ້ອນເຖິງການອັກເສບທົ່ວຮ່າງກາຍ ແລະ ສາມາດຢູ່ເປັນປົກກະຕິເມື່ອການອັກເສບຢູ່ສະເພາະຂໍ້ sacroiliac ຫລື ຕາ. MRI, ຮູບແບບອາການ, ການກວດຮ່າງກາຍ, ແລະ ການປະເມີນຜົນໂດຍຜູ້ຊ່ຽວຊານອາດຈະໃຫ້ຂໍ້ມູນໄດ້ດີກວ່າຜົນການອັກເສບປົກກະຕິພຽງຄັ້ງດຽວ.
Is HLA-B27 testing done from blood?
ການກວດຫາ HLA-B27 ໂດຍທົ່ວໄປແມ່ນເຮັດໄດ້ຈາກຕົວຢ່າງໃນຫ້ອງທົດລອງໂດຍໃຊ້ມາດຕະການວິທີການທາງໂມເລກຸນຫຼືວິທີການທີ່ອີງໃສ່ flow-cytometry, ແລະຫຼາຍຫ້ອງທົດລອງໃຊ້ຕົວຢ່າງເລືອດ. ການກວດແມ່ນມີຄຸນນະພາບ, ລາຍງານເປັນ "ພົບ" ບໍ່ໄດ້ "ພົບ", ແທນທີ່ຈະເປັນຄວາມເຂັ້ມຂົ້ນທີ່ມີລະດັບປົກກະຕິ. ອາຫານ, ການອອກກໍາລັງກາຍ, ແລະກິດຈະກໍາຂອງພະຍາດບໍ່ໄດ້ປ່ຽນແປງຜົນ, ເພາະວ່າ HLA-B27 ໄດ້ຮັບມາແທນທີ່ຈະເປັນເຄື່ອງຫມາຍການອັກເສບ.
ຮັບການວິເຄາະຜົນກວດເລືອດດ້ວຍ AI ທັນທີ
ເຂົ້າຮ່ວມຜູ້ໃຊ້ຫຼາຍກວ່າ 2 ລ້ານຄົນທົ່ວໂລກ ທີ່ໄວ້ໃຈ Kantesti ສຳລັບການວິເຄາະການກວດເລືອດທີ່ທັນທີ ແລະຖືກຕ້ອງ. ອັບໂຫຼດຜົນກວດເລືອດຂອງທ່ານ ແລະຮັບການຕີຄວາມໝາຍຢ່າງຄົບຖ້ວນຂອງ biomarker 15,000+ ໃນວິນາທີ.
📚 ບົດຄວາມວິຈັຍທີ່ອ້າງອີງ
Klein, T., Mitchell, S., & Weber, H. (2026). ຄູ່ມືປະເພດເລືອດ B ລົບ, ການກວດເລືອດ LDH ແລະຈຳນວນເມັດເລືອດແດງອ່ອນ (Reticulocyte Count). ການຄົ້ນຄວ້າທາງການແພດຂອງ AI Kantesti.
Klein, T., Mitchell, S., & Weber, H. (2026). ຖອກທ້ອງຫຼັງຈາກອົດອາຫານ, ມີຈຸດດຳໃນອາຈົມ ແລະ ຄູ່ມືກ່ຽວກັບລະບົບຍ່ອຍອາຫານ ປີ 2026. ການຄົ້ນຄວ້າທາງການແພດຂອງ AI Kantesti.
📖 ເອກະສານອ້າງອີງທາງການແພດພາຍນອກ
⚕️ ຂໍ້ສັງເກດທາງການແພດ
ບົດຄວາມນີ້ມີຈຸດປະສົງເພື່ອການສຶກສາເທົ່ານັ້ນ ແລະບໍ່ແມ່ນຄຳແນະນຳທາງການແພດ. ຄວນປຶກສາຜູ້ໃຫ້ບໍລິການດ້ານສຸຂະພາບທີ່ມີຄຸນວຸດທິສະເໝີ ສຳລັບການວິນິດໄຊ ແລະ ການຕັດສິນໃຈດ້ານການຮັກສາ.
ສັນຍານຄວາມໄວ້ໃຈ E-E-A-T
ປະສົບການ
ການທົບທວນຄລີນິກຂອງແພດຜູ້ນຳພາ ກ່ຽວກັບຂັ້ນຕອນການຕີຄວາມໝາຍຜົນການກວດໃນຫ້ອງທົດລອງ.
ຄວາມຊ່ຽວຊານ
ວິຊາການແພດທົດລອງ (ການແພດທາງຫ້ອງທົດລອງ) ເນັ້ນໃສ່ວ່າຕົວຊີ້ວັດ (biomarkers) ມີພຶດຕິກຳແນວໃດໃນບັນບົດທາງຄລີນິກ.
ຄວາມເປັນອຳນາດ
ຂຽນໂດຍທ່ານດຣ. Thomas Klein ໂດຍມີການກວດທານໂດຍທ່ານດຣ. Sarah Mitchell ແລະ ສາດສະດາຈານດຣ. Hans Weber.
ຄວາມໜ້າເຊື່ອຖື
ການຕີຄວາມໝາຍອີງຕາມຫຼັກຖານດ້ວຍເສັ້ນທາງຕິດຕາມທີ່ຊັດເຈນ ເພື່ອຫຼຸດການຕົກໃຈ.