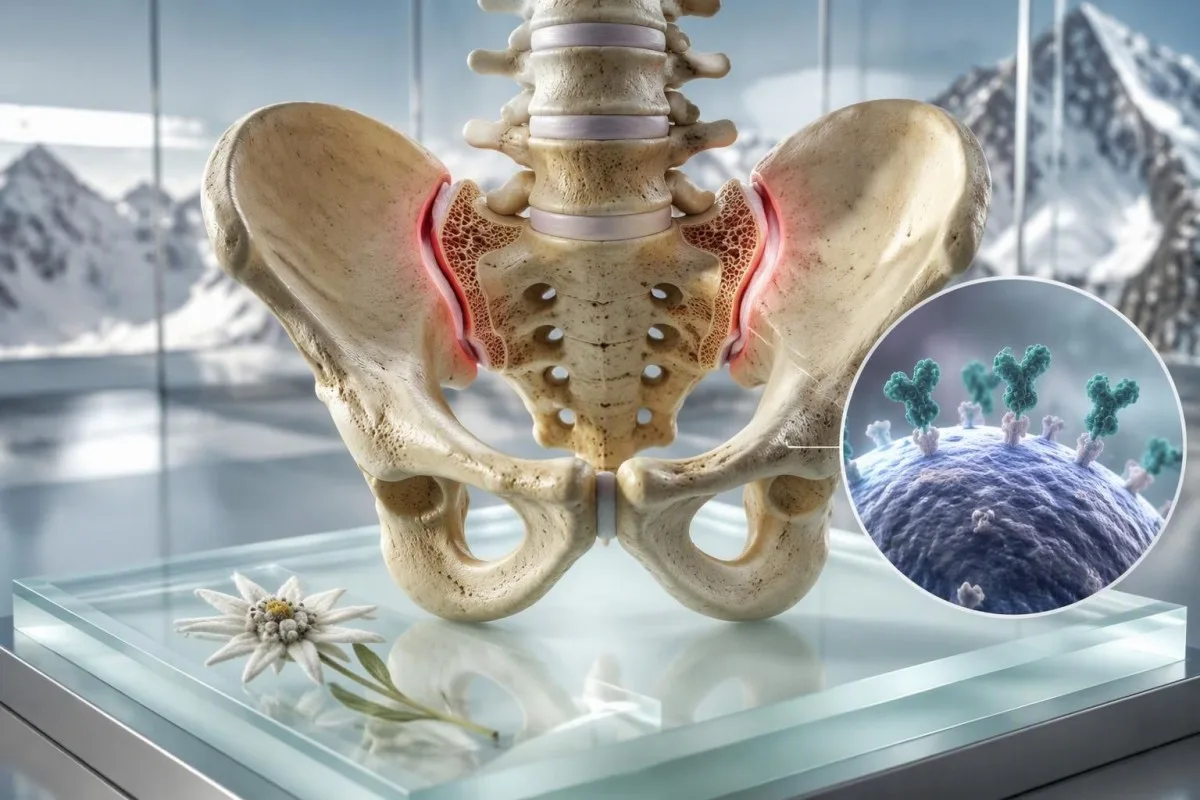
এটিএ-বি২৭ (HLA-B27) ধনাত্মক ফলাফলৰ দ্বাৰা বংশগত ৰোগ প্ৰতিৰোধ ক্ষমতাৰ এক চিহ্নিতকাৰীৰ চিনাক্ত কৰা হয়, কোনো ৰোগ নিৰ্ণয় নহয়। ইয়াৰ গুৰুত্ব আটাইতকৈ বেছি হয় যেতিয়া ই ৪৫ বছৰৰ আগতে আৰম্ভ হোৱা পিঠিৰ বিষ, চকুৰ উন্মুখ হোৱা প্রদাহ, সৰু পিত্তৰোগ, অন্ত্ৰৰ প্ৰদাহ, বা স্পণ্ডিলোআৰ্থ্ৰাইটিছৰ নিকটাত্মীয়ৰ চিকিৎসা ইতিহাসৰ সৈতে জড়িত থাকে।.


- এটিএ-বি২৭ (HLA-B27) ধনাত্মক মানে আপুনি জিনগত চিহ্নিতকাৰী বহন কৰে; বহু সুস্থ বাহকৰ কেতিয়াও প্ৰদাহজনিত ৰোগ নহয়।.
- প্ৰদাহজনক পিঠিৰ বিষ সাধাৰণতে ৪৫ বছৰৰ আগতে আৰম্ভ হয়, ৩ মাহতকৈ বেছি সময় ধৰি থাকে, নড়াচড়াৰ সৈতে উপশম হয়, আৰু নিশাৰ দ্বিতীয় ভাগত টোপনি ভঙা উচিত।.
- তীক্ষ্ণ এंटेৰিওৰ ইউভাইটিছ চকু ৰঙা, বেদনাদায়ক, পোহৰৰ প্ৰতি সংবেদনশীল, দৃষ্টি ঝাপসা আৰু একেদিনা চক্ষু বিশেষজ্ঞৰ মূল্যায়নৰ প্ৰয়োজন হয়।.
- স্বাভাৱিক CRP এক্সিয়াল স্পণ্ডাইলোআৰ্থ্ৰাইটিছক বাতিল নকৰে; CRP কেৱল সক্ৰিয় ৰোগৰ এক অনুপাতে বৃদ্ধি হয়।.
- মেৰুদণ্ডৰ স্কেন (MRI sacroiliac joints) সাধাৰণ এক্স-ৰে (X-rays) কাঠামোগত পৰিৱৰ্তন দেখুৱাৰ আগতে সক্ৰিয় টিছুৰ প্ৰতিক্ৰিয়া দেখুৱাব পাৰে।.
- পৰিয়ালৰ স্বাস্থ্য ইতিহাস এঙ্কাইলজিং স্পণ্ডাইলাইটিছ, ইউভাইটিছ, ছৰিয়াছিছ, বা প্রদাহজনক মলা-জ্বলা ৰোগৰ ক্ষেত্ৰত এক নিৰ্দিষ্ট ৰিউমাটোলজি পৰামৰ্শৰ মূল্য বৃদ্ধি কৰে।.
- HLA-B27 পৰীক্ষা এটা একোটা ক্লিনিকেল প্ৰশ্নৰ উত্তৰ দিব লাগে; ই সাধাৰণ মেকানিকেল পিঠিৰ বিষৰ বাবে একোটা উপযোগী স্ক্রীনিং পৰীক্ষা নহয়।.
- চকুৰ তাৎক্ষণিক লক্ষণ যিকোনো ৰোগ নিৰ্ণয়ৰ ফলাফলৰ ওপৰত গুৰুত্বপূৰ্ণ; চকুৰ বিষ বা দৃষ্টিৰ পৰিবৰ্তনৰ বাবে চিকিৎসা কৰোৱাৰ আগতে HLA-B27 পৰীক্ষাৰ বাবে অপেক্ষা নকৰিব।.
এটা ধনাত্মক এটিএ-বি২৭ (HLA-B27) ফলাফলৰ দ্বাৰা আপুনি কি তথ্য লাভ কৰে
HLA-B27 পজিটিভ মানে এজন ব্যক্তিয়ে এটা বিশেষ HLA শ্ৰেণীৰ জিনগত ৰূপ ধাৰণ কৰে; ইয়াৰ মানে এইটো নহয় যে তেওঁলোকৰ এঙ্কাইলজিং স্পনডাইলাইটিছ আছে বা হ'ব।. পৰীক্ষাটো কেবল তেতিয়াহে ক্লিনিকেলি উপযোগী হয় যেতিয়া লক্ষণ আৰু পৰীক্ষাৰ ফলাফল স্পনডাইলআৰ্থ্ৰাইটিছ-স্পেকট্ৰামৰ কোনো ৰোগৰ দিশত নিৰ্দেশ কৰে। মোৰ অনুশীলনত, আটাইতকৈ ক্ষতিকাৰক ভুল বুজাবুজিটো হৈছে এক পজিটিভ ফলাফলক ভৱিষ্যদ্বাণী হিচাপে বিবেচনা কৰা, এটা সম্ভাৱনা-ভিত্তিক প্ৰমাণৰ এটা অংশ হিচাপে নহয়।.
আমেৰিকা যুক্তৰাষ্ট্ৰৰ প্ৰায় ৬.১% প্ৰাপ্তবয়স্ক লোকৰ মাজত HLA-B27 পোৱা যায়, যদিও বংশ আৰু ভৌগোলিকতাৰ ওপৰত ইয়াৰ প্ৰচলনত তীক্ষ্ণ ভিন্নতা দেখা যায়।. ই কিছু উত্তৰ ইউৰোপীয় আৰু আদিবাসী জনসংখ্যাৰ মাজত অধিক সাধাৰণ আৰু আন কিছুমানৰ মাজত কম সাধাৰণ, সেয়েহে পৰিণামটো বিভিন্ন সম্প্ৰদায়ত বিভিন্ন পূৰ্বানুমানৰ মূল্য বহন কৰে। এটা নেগেটিভ পৰিণাম HLA-B27-সম্পৰ্কিত ৰোগৰ সম্ভাৱনা কমায় কিন্তু এक्सीয়াল স্পনডাইলআৰ্থ্ৰাইটিছক বাতিল কৰিব নোৱাৰে।.
HLA-B27 পৰীক্ষাৰ অৰ্থ দ্বিমুখী: সনাক্ত কৰা বা নহয়, উচ্চ বা নিম্ন নহয়।. লেবৰটৰীয়ে সাধাৰণতে এটা লেবৰটৰী নমুনাৰ পৰা মলিকিউলাৰ টাইপিং ব্যৱহাৰ কৰে, আৰু পৰিণাম টোপনি, আহাৰ, ফ্লেয়াৰ, বা ঔষধৰ সৈতে সলনি নহয়। এইটো প্রদাহজনক মাৰ্কাৰৰ দৰে ভিন্ন, যেনে ই এছ আৰ, যিবোৰ দিনৰ পৰা সপ্তাহলৈ সলনি হ'ব পাৰে।.
কান্টেষ্টি হৈছে এক... এ আই ব্লাড টেষ্ট এনালাইজাৰ যিটোৱে এটা আমদানিকৃত HLA ফলাফল প্রাসংগিক প্রদাহজনক মাৰ্কাৰৰ সৈতে কাষত ৰাখে, কিন্তু ই এটা জিনগত মাৰ্কাৰৰ পৰা স্পনডাইলআৰ্থ্ৰাইটিছ নিৰ্ণয় কৰিব নোৱাৰে। থমাছ ক্লেইন, MD, ৰোগীক সৰল প্ৰশ্নটো সুধিবলৈ পৰামৰ্শ দিয়ে: পৰীক্ষাটো কি ক্লিনিকেল সমস্যাৰ উত্তৰ দিবলৈ অৰ্ডাৰ কৰা হৈছিল? আমাৰ biomarker guide ব্যাখ্যা কৰে কিয় এটা ফ্ল্যাগ কৰা বা পজিটিভ পৰিণামৰ সদায় ইয়াৰ লেবৰটৰী পদ্ধতি আৰু ক্লিনিকেল প্ৰেক্ষাপটৰ প্ৰয়োজন হয়।.
কিয় এটা পজিটিভ পৰিণাম যিমান তাৰতকৈ বেছি উদ্বেগজনক হ'ব পাৰে
বেছিভাগ HLA-B27-পজিটিভ লোকে কেতিয়াও এঙ্কাইলজিং স্পনডাইলাইটিছত আক্ৰান্ত নহয়।. মাৰ্কাৰটো এণ্টিজেন প্ৰেজেণ্টেশ্বনত অংশগ্ৰহণ কৰে, তথাপিও ইয়াক ধাৰণ কৰাৰ পৰা ৰোগ হোৱালৈকে জৈৱিক পথ অসম্পূৰ্ণ থাকে; অন্ত্রৰ অণুজীব, ৰোগ প্ৰতিৰোধৰ নিয়ন্ত্ৰণ, আৰু আন জিনবোৰে অৱদান যোগায় বুলি ভবা হয়। সেই অনিশ্চয়তা বাস্তৱ, আৰু চিকিৎসকে এটা জিনগত সম্পৰ্কক এটা পূৰ্বানুমানলৈ পৰিৱৰ্তন কৰা উচিত নহয়।.
এটিএ-বি২৭ (HLA-B27) আৰু এঙ্কাইলজিং স্পণ্ডাইলাইটিছ: সম্পৰ্ক বনাম ৰোগ নিৰ্ণয়
প্ৰায় ৪০% ৰ পৰা ৪২% লোকৰ ৰেডিঅ'গ্ৰাফিক এঙ্কাইলজিং স্পনডাইলাইটিছ উত্তৰ ইউৰোপীয় ক'হৰ্টৰ বহুতোৰ মাজত HLA-B27 পজিটিভ হয়, কিন্তু মাৰ্কাৰটো নিৰ্ণয়ৰ বাবে প্ৰয়োজনীয় বা পৰ্যাপ্ত নহয়।. চিকিৎসকসকলে সমগ্ৰ ধৰণটোৰ পৰা এक्सीয়াল স্পনডাইলআৰ্থ্ৰাইটিছ নিৰ্ণয় কৰে: লক্ষণ, শাৰীৰিক অনুসন্ধান, ইমেজিং, লেবৰটৰী ফলাফল, আৰু প্ৰতিদ্বন্দ্বী ব্যাখ্যা।.
এটা পজিটিভ HLA-B27 পৰিণামৰ সৰ্বাধিক ৰোগ নিৰ্ণয়ৰ মূল্য তেওঁলোকৰ মাজত থাকে যিসকলৰ মাজত কৰ্কটৰোগৰ দৰে দীৰ্ঘস্থায়ী পিঠিৰ বিষ ৪ বজাতকৈ কম বয়সত আৰম্ভ হয়।. এজন ৫৫ বছৰীয়া ব্যক্তিৰ ক্ষেত্ৰত যাৰ প্ৰথম পিঠিৰ বিষ ৫২ বছৰ বয়সত ফৰ্নিচাৰ দাঙি থাকোঁতে আৰম্ভ হৈছিল, সেই একে পৰিণামটোৱে বহুতো সময়ত খুব কম পৰিবৰ্তন আনে। এইটোৱেই কাৰণ কিয় এটা ক্লিনিকেল প্ৰাক-পৰীক্ষা সম্ভাৱনাৰ অবিহনে অৰ্ডাৰ কৰা পৰীক্ষাই স্পষ্টতাতকৈ অধিক উদ্বেগ সৃষ্টি কৰিব পাৰে।.
ASAS শ্ৰেণীবিভাজনৰ ফ্ৰেমৱৰ্কে এজন HLA-B27-পজিটিভ ব্যক্তিক ৪০ বছৰ বয়সৰ আগতে আৰম্ভ হোৱা দীৰ্ঘস্থায়ী পিঠিৰ বিষৰ সৈতে এक्सीয়াল স্পনডাইলআৰ্থ্ৰাইটিছ পথত পৰিণত হ'বলৈ দিয়ে যেতিয়া কমেও দুটা আন স্পনডাইলআৰ্থ্ৰাইটিছৰ বৈশিষ্ট্য উপস্থিত থাকে, যেনে ইউভিটিছ, ছৰিয়াসিস, প্রদাহজনক অন্ত্রৰ ৰোগ, আৰ্থ্ৰাইটিছ, এন্টেচিটিছ, বা পৰিয়ালৰ ইতিহাস (ৰুডৱালেট এট আল., ২০০৯)।. শ্ৰেণীবিভাজনৰ মানদণ্ডই গৱেষণাৰ সামঞ্জস্যত সহায় কৰে; সিহঁত কোনো ঘৰুৱা ৰোগ নিৰ্ণয়ৰ তালিকা নহয়।.
ৰেডিঅ'গ্ৰাফিক এঙ্কাইলজিং স্পনডাইলাইটিছে এক্স-ৰেত ছাক্ৰোইলিয়াক-জয়েন্টৰ স্থাপন কৰা গঠনমূলক পৰিৱৰ্তনক বৰ্ণনা কৰে, আনহাতে নন্-ৰেডিঅ'গ্ৰাফিক এक्सीয়াল স্পনডাইলআৰ্থ্ৰাইটিছত সাধাৰণ এক্স-ৰে থাকিব পাৰে।. MRI can identify active bone-marrow tissue response earlier, although athletic loading, pregnancy-related changes, and degenerative disease can also make MRI interpretation tricky. A focused unexplained pain work-up অধিক পাঠ গঢ় দিয়াত সহায় কৰিব পাৰে।.
The risk number patients usually want
First-degree relatives of a person with HLA-B27-associated ankylosing spondylitis have a higher risk than the general population, but family risk is not destiny. Risk estimates differ substantially by sex, ancestry, and whether the affected relative has radiographic disease. I do not recommend testing healthy children or siblings merely to settle worry unless a specialist identifies a specific clinical reason.
কেনেদৰে প্ৰদাহজনক পিঠিৰ বিষ সাধাৰণ পিঠিৰ বিষৰ পৰা ভিন্ন হয়
Inflammatory back pain typically begins gradually before age 45, persists for more than 3 months, improves with exercise, and does not improve reliably with rest. Mechanical pain more often follows a strain, worsens predictably with loading, and settles when the provoking movement stops.
Waking in the second half of the night because of back or buttock pain is a useful clue when it occurs repeatedly, not once after a poor mattress. Alternating buttock pain, morning stiffness lasting longer than 30 minutes, and marked improvement after getting moving add weight to the inflammatory pattern. None is individually diagnostic; together, they are more persuasive.
I often see a 32-year-old runner who says, I loosen up after the first kilometre. That is not proof of inflammation—many musculoskeletal problems warm up—but pain that returns after sitting, wakes them near 4 a.m., and has continued for 9 months deserves more than generic stretching advice. Pain severity is less informative than the pattern over time.
NICE advises rheumatology referral for back pain beginning before 45 and lasting more than 3 months when several spondyloarthritis features coexist; HLA-B27 testing can support referral when exactly three features are present. New bowel or bladder dysfunction, saddle numbness, fever, unexplained weight loss, cancer history, or rapidly progressive weakness requires urgent assessment for causes beyond spondyloarthritis. Review the practical distinction between inflammation and injury in our psoriasis laboratory guide, particularly if skin disease is also present.
A useful two-week symptom record
Record wake time, stiffness duration, exercise response, buttock location, and anti-inflammatory medicine response for 14 days before an appointment. This produces more diagnostic value than a generic pain score from 0 to 10, because rheumatologists are looking for a reproducible inflammatory rhythm.
কেতিয়া এটিএ-বি২৭ (HLA-B27) সম্বন্ধীয় ৰঙা চকুৰ বাবে একেদিনা চিকিৎসাৰ প্ৰয়োজন হয়
A painful red eye with light sensitivity, blurred vision, or a smaller-looking pupil can be acute anterior uveitis and needs same-day assessment by an eye specialist or emergency eye service. HLA-B27-associated uveitis often starts suddenly in one eye and can recur, sometimes in the other eye at a later date.
Acute anterior uveitis is not the same as conjunctivitis. Conjunctivitis commonly causes discharge or gritty discomfort; uveitis more often causes deep aching pain, photophobia, reduced visual clarity, and redness concentrated around the iris. A normal-looking external eye does not reliably exclude it, especially early on.
Roughly half of acute anterior uveitis cases in many European-derived cohorts are HLA-B27 positive, but eye doctors still consider infection, sarcoidosis, Behçet disease, inflammatory bowel disease, trauma, and medication effects. Do not use leftover steroid eye drops without an examination, because steroid drops can worsen undiagnosed corneal infection and raise eye pressure. আমাৰ গাইড Behçet eye symptoms covers another condition where oral ulcers and eye symptoms change the urgency.
Treatment commonly uses prescription topical corticosteroid drops plus pupil-dilating drops, with a taper directed by ophthalmology. Follow-up matters because pressure elevation and swelling at the back of the eye can occur even when pain improves. A recurrent episode should trigger communication between ophthalmology and rheumatology rather than parallel, disconnected care.
এনে লক্ষণ যিয়ে সাধাৰণ এপইণ্টমেণ্টৰ বাবে অপেক্ষা কৰা উচিত নহয়
Sudden vision loss, a curtain or shower of new floaters, severe headache with nausea, halos around lights, or severe eye pain needs emergency evaluation immediately. These features can signal diagnoses other than uveitis, including acute angle-closure glaucoma or retinal disease, where delay can threaten sight.
অন্য কোনবোৰ লক্ষণৰ বাবে এটিএ-বি২৭ (HLA-B27) অধিক অৰ্থপূৰ্ণ হৈ উঠে
HLA-B27 becomes more clinically meaningful when back or eye symptoms occur with psoriasis, inflammatory bowel disease, heel enthesitis, swollen joints, or a close relative with related disease. This cluster is called the spondyloarthritis spectrum because different tissues may be involved at different times.
Enthesitis is inflammation where a tendon or ligament attaches to bone, commonly causing focal pain at the Achilles insertion or bottom of the heel. It differs from diffuse foot ache because the tenderness is usually sharply localized and may be worst after rest. Ultrasound can help, but body weight, sports loading, and footwear can produce similar symptoms.
Psoriasis-related nail pitting, separation of the nail plate, or a whole swollen finger or toe can be particularly helpful diagnostic clues. A person does not need widespread psoriasis for this to count; a small scalp patch or a long history of flaky plaques behind the ears may matter. Photographing an intermittent rash before it fades can save a surprising amount of time at review.
Chronic diarrhoea, nocturnal stool urgency, rectal bleeding, or unintended weight loss should prompt bowel evaluation rather than being attributed to stress. Faecal calprotectin is useful for detecting intestinal tissue response but is not specific for Crohn disease or ulcerative colitis; our calprotectin comparison explains its limitations. The connection matters because bowel inflammation can steer both imaging choices and treatment selection.
Symptoms that do not fit neatly
Fatigue is common in active inflammatory disease but is too non-specific to establish a diagnosis. Iron deficiency, sleep disruption, thyroid dysfunction, mood disorders, medications, and prolonged pain can all contribute, so I look for a coherent pattern rather than assigning fatigue to HLA-B27.
পৰিয়ালৰ চিকিৎসা ইতিহাসৰ দ্বাৰা পৰৱৰ্তী পদক্ষেপ কেনেদৰে সলনি হয়
A first-degree relative with ankylosing spondylitis, recurrent uveitis, psoriasis, inflammatory bowel disease, or reactive arthritis increases suspicion when compatible symptoms are present. Family history supports a referral decision; it does not make testing or imaging mandatory in a person with no symptoms.
Ask relatives about diagnoses and major symptoms, not only whether they carry HLA-B27. People may remember being told they had iritis, a stiff spine, Crohn disease, or psoriasis but have never heard the term spondyloarthritis. The age at symptom onset is especially valuable: back pain that began at 22 tells a different story from osteoarthritis diagnosed at 72.
Kantesti AI হৈছে এটা AI তেজ পৰীক্ষাৰ ফলাফল প্লেটফৰ্ম that can organise family-shared laboratory histories with consent, but family-history patterns still require a clinician to verify diagnoses. A useful record includes affected relative, relationship, condition, age at onset, eye episodes, and relevant imaging. Our পাৰিবাৰিক ইতিহাস ট্ৰেকাৰ offers a practical template for recording that detail.
Routine HLA-B27 testing in symptom-free relatives usually does not improve outcomes. The result can create false reassurance when negative and unnecessary fear when positive, because no proven preventive treatment is prescribed simply for carrier status. A child with persistent limp, eye symptoms, or swollen joints needs paediatric assessment based on symptoms, whatever the family genotype.
What to bring to a specialist appointment
Bring prior X-ray or MRI reports, eye-clinic letters, medication dates, and a one-page family history. Imaging discs or digital access are often more useful than repeating scans, particularly because sacroiliac-joint MRI requires experienced interpretation.
কিয় সাধাৰণ প্রদাহ পৰীক্ষাই এইবোৰক বাতিল নকৰে
Normal CRP and ESR do not rule out axial spondyloarthritis or HLA-B27-associated uveitis. These tests measure systemic inflammatory activity indirectly, and localized disease can be clinically active while both results remain within the laboratory reference interval.
CRP is often reported in mg/L, with many laboratories using less than 5 mg/L as a reference threshold, while ESR reference limits vary with age and sex. A CRP of 2 mg/L can coexist with active sacroiliac inflammation on MRI. Conversely, a CRP of 28 mg/L is non-specific and may reflect infection, obesity, dental inflammation, or another inflammatory condition.
A complete blood count, liver profile, kidney profile, CRP, and ESR are baseline context tests rather than diagnostic proof. Anaemia, raised platelets, low albumin, or iron deficiency can suggest persistent inflammation or bowel involvement, but each has alternative explanations. This is one reason inflammatory conditions should not be inferred from a single marker.
কান্টেষ্টি হৈছে এক... এআই-চালিত রক্ত পরীক্ষার বিশ্লেষণ সরঞ্জাম that can compare CRP, platelets, haemoglobin, and albumin across dates, helping users identify a pattern to discuss with their clinician. It cannot see sacroiliitis on an MRI or assess a painful eye. For antibody results that can be over-interpreted in a similar way, see our explanation of ANA পৰীক্ষা.
Medication and test interpretation
NSAIDs can reduce CRP and improve symptoms without proving or disproving the diagnosis. Do not stop prescribed anti-inflammatory medication before testing unless the clinician managing your care specifically asks you to; an artificial flare is not a safe diagnostic strategy.
কোনবোৰ স্কেন সহায়ক, আৰু প্ৰতিটো স্কেনত কি কি তথ্য নিৰীক্ষণ কৰা নহয়
MRI of the sacroiliac joints is the preferred scan when axial spondyloarthritis is suspected but X-rays are normal or inconclusive. X-rays show structural change that often develops slowly, whereas MRI can show active bone-marrow tissue response and other early changes.
A normal lumbar-spine MRI does not replace a dedicated sacroiliac-joint MRI protocol. The relevant joints are lower and more lateral than the area commonly imaged for a slipped disc. I have seen patients reassured by an ordinary lumbar scan that was simply not designed to answer the inflammatory question.
MRI findings require clinical correlation because bone-marrow oedema can occur after intense exercise, childbirth, mechanical stress, and degenerative change. The radiology report should describe location, depth, distribution, erosions, fat change, and structural features; a vague statement of oedema alone is not enough. A rheumatologist may ask for image review when the report and symptom pattern disagree.
Pelvic X-rays remain useful for documenting chronic sacroiliac structural changes, but a normal X-ray does not close the case in a younger person. CT shows structure very clearly but uses ionising radiation and is not generally the first choice for early inflammatory disease. If persistent inflammation affects mobility, bone-health assessment may also be relevant; read our bone loss laboratory guide.
Why the scan report can sound uncertain
Radiologists appropriately use terms such as compatible with or non-specific when the imaging pattern is not definitive. That wording is not evasive; it reflects a real overlap between inflammatory and mechanical findings, and it prevents imaging from being treated as a diagnosis in isolation.
কিয় ৰিউমাটোলজিৰ ওচৰলৈ গৈ পৰামৰ্শ লোৱা উচিত
Ask for rheumatology evaluation when chronic back pain began before age 45 and is accompanied by inflammatory features, HLA-B27 positivity, recurrent uveitis, psoriasis, bowel symptoms, heel enthesitis, or a relevant family history. A positive test plus one convincing clinical feature is more useful than a positive test discovered during broad screening.
A referral is reasonable even when CRP is normal and X-rays are unremarkable if the clinical pattern is compelling. The 2019 ACR/SAA/SPARTAN guideline recommends treatment decisions based on disease activity, function, comorbidities, and patient preferences rather than a genetic result alone (Ward et al., 2019). This approach prevents both delayed diagnosis and reflexive overtreatment.
At the appointment, expect questions about age at onset, morning stiffness, night waking, response to NSAIDs, eye attacks, skin lesions, bowel symptoms, infection preceding arthritis, and family history. A rapid and clear response to a full-dose NSAID may support suspicion, but it is not a diagnostic test. NSAIDs also improve ordinary back pain.
Thomas Klein, MD, recommends making a dated timeline rather than trying to remember every symptom in the consulting room. Include medication dose and duration, especially if using ibuprofen, naproxen, or diclofenac, because kidney function, blood pressure, ulcer risk, and anticoagulant use alter the safety calculation. Our medication trend guide explains why repeat kidney and liver results may matter during longer courses.
When an orthopaedic or physiotherapy assessment may be better first
Back pain starting after age 45 following a specific injury, with clear load-related triggers and no inflammatory features, more often benefits initially from musculoskeletal care. That is a probability statement, not a dismissal; persistent uncertainty or new eye, skin, bowel, or joint symptoms warrants reassessment.
যদি এক্সিয়াল স্পণ্ডাইলোআৰ্থ্ৰাইটিছ নিশ্চিত হয়, তেন্তে চিকিৎসা কেনে হ'ব
Confirmed axial spondyloarthritis is treated with education, regular movement, targeted physiotherapy, and anti-inflammatory medicines; biologic or targeted synthetic medicines are reserved for persistent active disease. HLA-B27 status does not determine treatment by itself.
Exercise is treatment, not a test of willpower. A programme that maintains spinal extension, hip mobility, chest expansion, and aerobic capacity is generally more sustainable than sporadic intense workouts. Most patients find short daily mobility work of 10 to 20 minutes easier to keep than a single ambitious weekend session.
NSAIDs are usually considered first-line when safe, but dose and duration must be individualised. Naproxen 500 mg twice daily is a common adult anti-inflammatory dose, yet it may be unsuitable with chronic kidney disease, prior ulcer bleeding, heart failure, uncontrolled hypertension, anticoagulants, or pregnancy. Gastroprotection may be appropriate for some people, but it does not remove kidney or cardiovascular risk.
Biologic medicines such as TNF inhibitors and IL-17 inhibitors require screening and specialist monitoring because infection risk and comorbidities affect selection. Recurrent uveitis, psoriasis, and inflammatory bowel disease influence which agent best fits the whole person. This is one reason a diagnosis based only on an HLA-B27 result can lead to the wrong treatment conversation.
Avoid the supplement trap
No supplement has been shown to prevent HLA-B27-associated spondyloarthritis in healthy carriers. Correcting a documented vitamin D, iron, or B12 deficiency can improve general health, but it is not a substitute for assessment of inflammatory back pain or a painful red eye.
আপোনাৰ ফলাফলবোৰৰ সৈতে মোকাবিলা কৰিও কেনেদৰে ইয়াক নিয়ন্ত্ৰণত ৰাখিব
The most useful record combines symptoms, function, medications, eye episodes, imaging, and laboratory trends rather than repeatedly retesting HLA-B27. Once accurately typed, HLA-B27 status does not need serial monitoring because your inherited marker does not change.
Track functional measures that mean something to you, such as minutes until morning stiffness eases, uninterrupted sleep, walking tolerance, or ability to turn while driving. These details show treatment response more honestly than a single good or bad day. Note whether an eye flare preceded a back-pain change by days or weeks.
Kantesti can organise imported laboratory reports across time and flag changes for discussion, but it should not be used to self-start or stop prescription treatment. Our clinical framework is described in the AI প্রযুক্তি গাইড: results are interpreted as context for professional care, not as a replacement for examination or imaging.
Repeating CRP during a flare can be useful when a clinician is also following symptoms and treatment response, but routine weekly testing is rarely helpful. In my experience, a symptom record every day and blood work at clinically meaningful intervals yields less noise and fewer false alarms. Laboratory trends only become informative when collection dates, infections, exercise, and medicines are documented.
A note about privacy and family data
Genetic information can affect relatives as well as the person tested, so share reports deliberately. Keep the original laboratory report, remove unrelated identifiers when appropriate, and obtain consent before adding another adult's results to a shared family record.
এটিএ-বি২৭ (HLA-B27) ধনাত্মক হোৱা সম্পৰ্কে সাধাৰণ ভুল ধাৰণা
HLA-B27 positivity does not mean your immune system is attacking your spine, that you are contagious, or that you need treatment while symptom-free. It is a common inherited allele whose significance depends on the clinical setting.
Myth: a positive HLA-B27 test explains every ache. Fact: mechanical back pain remains common among HLA-B27 carriers. Strain, disc disease, hip disorders, hypermobility, fibromyalgia, kidney stones, and pelvic conditions still deserve a normal differential diagnosis. The marker should sharpen clinical reasoning, not end it.
Myth: a negative HLA-B27 test rules out ankylosing spondylitis. Fact: HLA-B27-negative axial spondyloarthritis occurs, especially across populations with lower background carrier frequency. When imaging and clinical features are persuasive, a negative result should not be used to deny specialist review.
Myth: genes are the same as destiny. Fact: genetics influence risk, but no preventive biologic therapy is indicated for a well HLA-B27 carrier. This is conceptually similar to the limits of MTHFR result interpretation: genetic information is medically useful only when the result changes an evidence-based decision.
Can stress cause a flare?
Stress can worsen pain, sleep, fatigue, and coping, but it does not explain away objective uveitis or inflammatory arthritis. Treating sleep and stress is worthwhile alongside medical care; it should never delay eye assessment or replace a work-up for persistent inflammatory symptoms.
কোনবোৰ প্ৰশ্নৰ দ্বাৰা প্ৰথম সাক্ষাৎকাৰ অধিক ফলপ্ৰসূ কৰিব পাৰি
The best first appointment questions focus on probability, alternative diagnoses, and the next decision—not on whether HLA-B27 is good or bad. A clinician should be able to explain what finding would increase or decrease their suspicion and what test would change management.
Ask whether your symptoms meet an inflammatory-back-pain pattern and which features argue against it. Then ask whether dedicated sacroiliac MRI is appropriate, whether an ophthalmology referral is needed, and whether psoriasis or bowel symptoms warrant coordinated review. This approach respects uncertainty without letting it become inaction.
Ask how long to try a treatment, what outcome defines success, and which adverse effects need a call. For NSAIDs, the specific safety discussion should include kidney function, blood pressure, gastrointestinal history, pregnancy plans, and interacting drugs. For biologics, ask about screening, vaccines, infection precautions, and how uveitis or bowel disease changes the choice.
Kantesti's clinical content is medically reviewed with structured quality controls; readers can examine our চিকিৎসাগত বৈধতা (medical validation) পদ্ধতি আৰু আমাৰ মেডিকেল এডভাইজাৰী ব’ৰ্ড. A laboratory interpretation is most valuable when it helps you ask a better question of the clinician who can examine you.
এটা সংক্ষিপ্ত নিযুক্তি স্ক্ৰিপ্ট
Say: My back pain started at age 29, has lasted 14 months, wakes me at 4 a.m., improves after 30 minutes of movement, and I had a painful light-sensitive eye last spring. That one sentence gives a rheumatologist more usable information than stating only that an HLA-B27 result was positive.
তাৎক্ষণিক লক্ষণ আৰু এক নিৰাপদ পৰৱৰ্তী পৰিকল্পনা
Seek same-day urgent eye care for eye pain, light sensitivity, red eye with blurred vision, or any sudden visual change; seek emergency care for new weakness, bladder or bowel dysfunction, saddle numbness, high fever, or severe unremitting back pain. Do not wait for repeat blood work, an MRI booking, or a rheumatology appointment when these red flags occur.
For non-urgent symptoms, book a primary-care review within weeks if back pain has lasted more than 3 months and began before age 45, especially with HLA-B27 positivity or family history. Bring your HLA report, symptom timeline, medication list, eye-clinic letters, and prior images. A targeted referral is generally faster and more useful than repeating broad autoimmune panels.
As of September 27, 2026, the central clinical principle remains unchanged: HLA-B27 is a risk marker, not a diagnosis. Thomas Klein, MD, has found that patients do best when they treat a positive result as a prompt to notice patterns—then obtain the right eye, primary-care, or rheumatology assessment rather than catastrophising or ignoring symptoms.
কান্টেষ্টি হৈছে এক... AI lab test interpretation service-ত built to explain laboratory reports in plain language while preserving the boundary between information and diagnosis. Learn how our organisation approaches this work on our About Us পৃষ্ঠাত আছে and find further patient education in the কান্টেষ্টি ব্লগ.
গৱেষণা প্ৰকাশনা অংশ
Kantesti LTD. (2026)।. B নেগেটিভ তেজৰ ধৰণ, LDH তেজ পৰীক্ষা আৰু ৰেটিকুলোচাইট কাউণ্ট গাইড. Figshare।. https://doi.org/10.6084/m9.figshare.31333819. Related author records may be located through ৰিচাৰ্চগেট আৰু Academia.edu.
Kantesti LTD. (2026)।. উপবাসৰ পিছত ডায়েৰিয়া, মলত ক'লা দাগ আৰু জিআই গাইড ২০২৬. Figshare।. https://doi.org/10.6084/m9.figshare.31438111. Related author records may be located through ৰিচাৰ্চগেট আৰু Academia.edu.
These publications are not evidence for diagnosing HLA-B27-associated disease and should not replace the rheumatology and ophthalmology references cited above. They are listed as Kantesti research records for transparency.
সঘনাই সোধা প্ৰশ্ন
HLA-B27 পজিটিভ মানেই কি এঙ্কাইলোজিং স্পন্ডিলাইটিস আছে?
নহয়। HLA-B27 ইতিবাচক ফলাফলৰ অৰ্থ হৈছে আপুনি এংকাইলজিং স্পণ্ডিলাইটিচ আৰু সংশ্লিষ্ট ৰোগৰ সৈতে জড়িত এটা জেনেটিক মাৰ্কাৰ বহন কৰে, কিন্তু বহু বাহকে জীৱনজুৰি সুস্থ থাকে। ৰেডিঅ'গ্ৰাফিক এংকাইলজিং স্পণ্ডিলাইটিচ থকা দলত, প্ৰায় 80% ৰ পৰা 95% HLA-B27 ইতিবাচক হয়, কিন্তু বিপৰীতটো সত্য নহয়: অধিকাংশ ইতিবাচক ব্যক্তিক এই ৰোগ নহয়। ৰোগ নিৰ্ণয়ৰ বাবে উপযুক্ত লক্ষণ, পৰীক্ষা, ইমেজিং, আৰু অন্যান্য কাৰণ বাদ দিয়াৰ প্ৰয়োজন।.
HLA-B27-সম্পর্কিত প্রদাহৰ কোনবোৰ পিঠিৰ বিষৰ লক্ষণত দেখা যায়?
চুটিৰ বিষ अक्षीय स्पॉन्डिलोआर्थराइटिसৰ দ্বাৰা অধিক পৰামৰ্শ দিয়া হয় যেতিয়া ই 45 বছৰ বয়সৰ আগতে আৰম্ভ হয়, লাহে লাহে বিকশিত হয়, 3 মাহতকৈ বেছি সময় থাকে, গতিৰ লগত উন্নতি লাভ কৰে, আৰু 30 মিনিটৰ অধিক স্থায়ী পুৱাৰ খটুৱা সৃষ্টি কৰে। নিশাৰ দ্বিতীয় ভাগত বাৰম্বাৰ সাৰ পোৱা আৰু বিকল্প আঠাৰ বিষ উপযোগী সূত্ৰ যোগ কৰে। HLA-B27 ইতিবাচক ফলাফল এই ধৰণৰ মূল্য বৃদ্ধি কৰে, কিন্তু এজন চিকিৎসকে মেকানিকাল কাৰণ আৰু লাল পৰ্দা মূল্যায়ন কৰিব লাগিব।.
HLA-B27 এ ইউভাইটিস হ’ব পাৰেনে?
HLA-B27 प्रत्यक्ष रूपमा हरेक आँखाको समस्याको कारण बन्दैन, तर यो तीव्र एन्टेरियर यूभेटिस (acute anterior uveitis) सँग दृढतापूर्वक सम्बन्धित छ। यूभेटिसको यो प्रकारले सामान्यतया अचानक एक आँखाको रातोपन, गहिरो दुखाइ, प्रकाश संवेदनशीलता, र धमिलो दृष्टि निम्त्याउँछ; यसको लागि आँखा विशेषज्ञबाट सोही दिन मूल्याङ्कन आवश्यक छ। धेरै युरोपेली मूलका समूहहरूमा तीव्र एन्टेरियर यूभेटिस (acute anterior uveitis) का लगभग आधा केसहरू HLA-B27 सकारात्मक हुन्छन्, यद्यपि यसको व्यापकता जनसंख्या अनुसार फरक हुन्छ र वैकल्पिक कारणहरूलाई विचार गर्नुपर्छ।.
মই যদি HLA-B27 পজিটিভ হওঁ কিন্তু মোৰ কোনো লক্ষণ নাথাকে তেন্তে মই ৰিউমাটোলজিস্টক দেখুওৱা উচিতনে?
যদিও বহু লক্ষণবিহীন HLA-B27-পজিটিভ লোকৰ নিয়মীয়া ৰিউমাটোলজিৰ ফொলো-আপ বা প্ৰতিৰোধমূলক চিকিৎসাৰ প্ৰয়োজন নহয়, তথাপিও যদি chronic back pain 45 বছৰ বয়সৰ আগতে আৰম্ভ হয়, recurrent uveitis, psoriasis, persistent bowel symptoms, enthesitis-ৰ পৰা হোৱা গোটাত বিষ, joints-ৰ ফুলা, বা পৰিয়ালত এই ইতিহাস ওলায়, তেন্তে পৰ্যালোচনা কৰা যুক্তিসংগত। HLA-B27 পৰীক্ষাৰ পুনৰাবৃত্তিৰ কোনো ব্যৱহাৰ নাই কাৰণ উত্তৰাধিকাৰসূত্ৰে লাভ কৰা HLA স্থিতি সময়ৰ লগত সলনি নহয়।.
এঙ্কাইলosing spondylitis ত CRP আৰু ESR স্বাভাৱিক হ'ব পাৰে নে?
হয়। CRP সাধাৰণতে বহু পৰীক্ষাগাৰত 5 mg/L তকৈ কম হ’লে স্বাভাৱিক বুলি গণ্য কৰা হয়, কিন্তু স্বাভাৱিক CRP আৰু ESR এ এক্সিয়াল স্পণ্ডিলোআৰ্থৰাইটিচ বা সক্ৰিয় ইউভাইটিছক বাদ নিদিয়ে। এই মাৰ্কাৰবোৰে শৰীৰৰ সাধাৰণ প্ৰদাহৰ কাৰ্য্যকলাপক প্ৰতিফলিত কৰে আৰু ই স্বাভাৱিক থাকিব পাৰে যেতিয়া প্ৰদাহটো চ্যাকৰোইলিয়াক জয়েন্ট বা চকুৰ মাজত সীমিত থাকে। এমআৰআই, লক্ষণৰ ধৰণ, শাৰীৰিক পৰীক্ষা, আৰু বিশেষজ্ঞৰ মূল্যায়ন এটা সাধাৰণ প্ৰদাহৰ ফলাফলতকৈ অধিক তথ্যপূৰ্ণ হ’ব পাৰে।.
HLA-B27 পৰীক্ষা তেজৰ পৰা কৰা হয় নে?
HLA-B27 টাইপিং সাধাৰণতে আণৱিক বা ফ্লো-সাইটোমেট্ৰি-ভিত্তিক পদ্ধতি ব্যৱহাৰ কৰি এটা লেবৰেটৰী নমুনাৰ পৰা কৰা হয়, আৰু বহুতো লেবৰেটৰীয়ে তেজৰ নমুনা ব্যৱহাৰ কৰে। পৰীক্ষাটো গুণগত, এটা ঘনত্বৰ পৰিৱৰ্তে ডিটেক্টেড বা ডিটেক্টেড নহয় বুলি ৰিপৰ্ট কৰা হয়। HLA-B27 এক প্ৰকাৰৰ উত্তৰাধিকাৰ সূত্ৰে পোৱা লক্ষণ হোৱাৰ বাবে, ইয়াৰ পৰিণাম খাদ্য, ব্যায়াম আৰু ৰোগৰ কাৰ্য্যকলাপৰ দ্বাৰা পৰিৱৰ্তন নহয়।.
আজিয়েই AI-চালিত তেজ পৰীক্ষাৰ বিশ্লেষণ লাভ কৰক
বিশ্বজুৰি ২ মিলিয়নতকৈ অধিক ব্যৱহাৰকাৰীয়ে বিশ্বাস কৰা Kantesti-ত যোগদান কৰক—তাৎক্ষণিক আৰু সঠিক লেব পৰীক্ষাৰ বিশ্লেষণৰ বাবে। আপোনাৰ তেজ পৰীক্ষাৰ ফলাফল আপলোড কৰক আৰু কেইছেকেণ্ডমানৰ ভিতৰতে 15,000+ বায়’মাৰ্কাৰৰ সম্পূৰ্ণ ব্যাখ্যা লাভ কৰক।.
📚 উদ্ধৃত গৱেষণা প্ৰকাশনা
Klein, T., Mitchell, S., & Weber, H. (2026)।. B নেগেটিভ তেজৰ ৰক্তৰ ধৰণ, LDH তেজ পৰীক্ষা আৰু ৰেটিকুল’চাইট কাউণ্ট গাইড.। Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026)।. উপবাসৰ পিছত ডায়েৰিয়া, মলত ক'লা দাগ আৰু জিআই গাইড ২০২৬.। Kantesti AI Medical Research.
📖 বাহ্যিক চিকিৎসা সম্পৰ্কীয় উৎসসমূহ
⚕️ চিকিৎসা অস্বীকাৰ
এই লেখাটো কেৱল শিক্ষামূলক উদ্দেশ্যৰ বাবে, আৰু ই চিকিৎসাজনিত পৰামৰ্শ নহয়। ৰোগ নিৰ্ণয় আৰু চিকিৎসাৰ সিদ্ধান্তৰ বাবে সদায় যোগ্য স্বাস্থ্যসেৱা বিশেষজ্ঞৰ সৈতে পৰামৰ্শ কৰক।.
E-E-A-T বিশ্বাস সংকেত
অভিজ্ঞতা
চিকিৎসক-নিৰ্দেশিত লেব ব্যাখ্যা কাৰ্যপ্ৰবাহৰ ক্লিনিকেল পৰ্যালোচনা।.
বিশেষজ্ঞতা
ক্লিনিকেল পৰিপ্ৰেক্ষিতত বায়’মাৰ্কাৰসমূহ কেনেকৈ আচৰণ কৰে—সেই বিষয়ে লেবৰেটৰী মেডিচিনৰ গুৰুত্ব।.
কৰ্তৃত্বশীলতা
ড° থমাছ ক্লেইনৰ দ্বাৰা লিখিত; ড° ছাৰাহ মিচেল আৰু প্ৰফ. ড° হান্স ৱেবাৰৰ দ্বাৰা পৰ্যালোচনা।.
বিশ্বাসযোগ্যতা
স্পষ্ট অনুসৰণ পথৰ সৈতে প্ৰমাণ-ভিত্তিক ব্যাখ্যা—আতংক কমাবলৈ।.