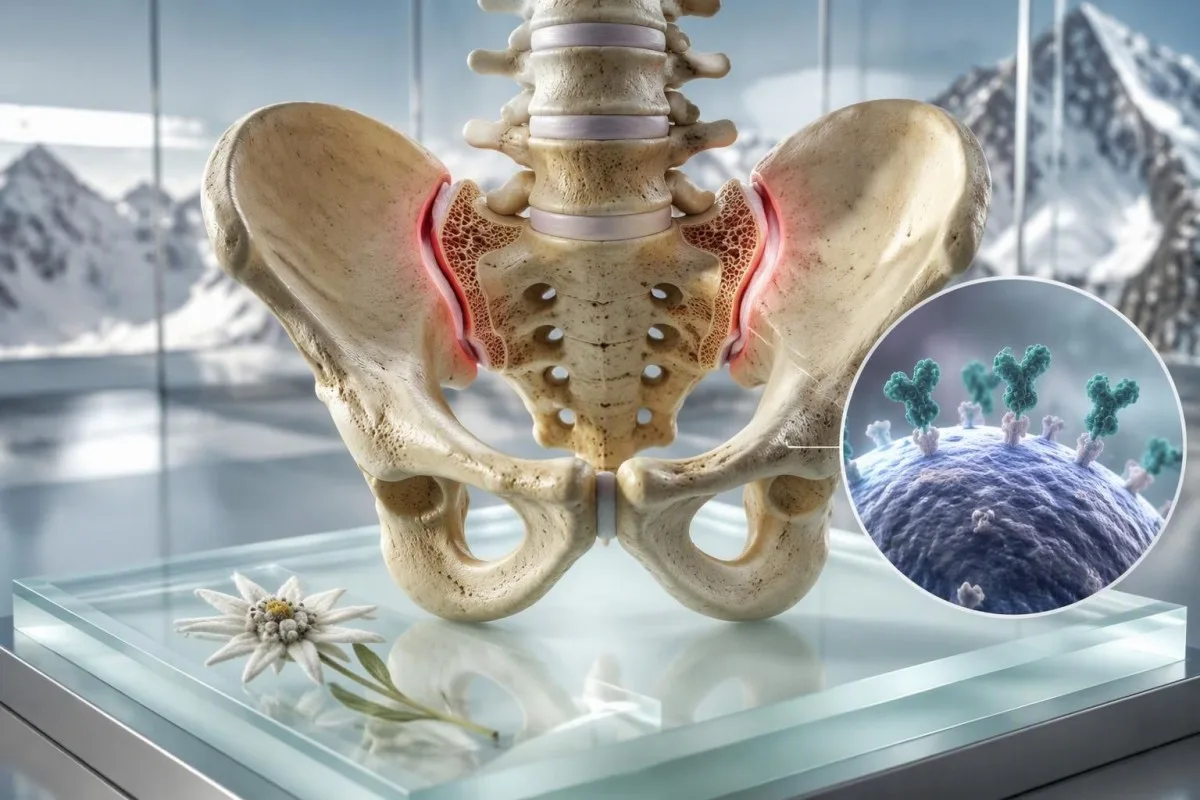
HLA-B27-ის დადებითი შედეგი მიუთითებს მემკვიდრეობით იმუნური სისტემის მარკერზე, დიაგნოზზე არა. ის ყველაზე მნიშვნელოვანია, როდესაც თან ახლავს 45 წლამდე დაწყებული ზურგის ტკივილი, თვალის ანთების შემაწუხებელი, ფსორიაზი, ნაწლავების ანთება ან სპონდილოართრიტის ოჯახური ისტორია.


- HLA-B27 დადებითი ნიშნავს, რომ თქვენ ატარებთ გენეტიკურ მარკერს; ბევრი ჯანმრთელი მატარებელი არასდროს უვითარდება ანთებითი დაავადება.
- ანთებითი ზურგის ტკივილი ჩვეულებრივ იწყება 45 წლამდე, გრძელდება 3 თვეზე მეტხანს, უმჯობესდება მოძრაობით და ხშირად არღვევს ძილს ღამის მეორე ნახევარში.
- მწვავე წინა უვეიტი იწვევს თვალის სიწითლეს, ტკივილს, სინათლის მიმართ მგრძნობელობას, ბუნდოვან მხედველობას და საჭიროებს ოფთალმოლოგიურ შეფასებას იმავე დღეს.
- ნორმალური CRP არ გამორიცხავს ღერძულ სპონდილოართრიტს; CRP-ის დონე მომატებულია აქტიური დაავადების მქონე ადამიანების მხოლოდ ნაწილში.
- მენჯ-ბარძაყის სახსრების MRI შეუძლია აჩვენოს აქტიური ქსოვილის რეაქცია, სანამ მარტივი რენტგენი არ აჩვენებს სტრუქტურულ ცვლილებას.
- ოჯახური ისტორია ანკილოზური სპონდილიტის, უვეიტის, ფსორიაზის ან ანთებითი ნაწლავის დაავადების ზრდის რისკი ზრდის მიზანმიმართული რევმატოლოგიური მიმართვის ღირებულებას.
- HLA-B27 ტესტირება უნდა პასუხობდეს კლინიკურ კითხვას; ეს არ არის სასარგებლო სკრინინგ ტესტი გაურთულებელი მექანიკური წელის ტკივილისთვის.
- თვალის გადაუდებელი სიმპტომები აღემატება ლაბორატორიულ შედეგებს: არ დაელოდოთ HLA-B27 ტესტს თვალის ტკივილის ან მხედველობის ცვლილებისთვის სამედიცინო დახმარების მიღებამდე.
რას ნიშნავს HLA-B27-ის დადებითი შედეგი
HLA-B27 დადებითი ნიშნავს, რომ ადამიანი ატარებს კონკრეტულ HLA კლასის I გენეტიკურ ვარიანტს; ეს არ ნიშნავს, რომ მას აქვს ანკილოზებელი სპონდილიტი ან განუვითარდება ის. ტესტი კლინიკურად სასარგებლო ხდება მხოლოდ მაშინ, როდესაც სიმპტომები და გამოკვლევის შედეგები მიუთითებს სპონდილოართრიტის სპექტრის მდგომარეობაზე. ჩემს პრაქტიკაში ყველაზე მავნე გაუგებრობა არის დადებითი შედეგის პროგნოზად მიჩნევა და არა ალბათობაზე დაფუძნებული მტკიცებულებების ერთი ნაწილის.
HLA-B27 გვხვდება დაახლოებით 6.1% აშშ-ს ზრდასრულთა შორის, თუმცა გავრცელება მკვეთრად განსხვავდება წარმოშობისა და გეოგრაფიის მიხედვით. ის უფრო ხშირია ზოგიერთ ჩრდილოეთ ევროპულ და ადგილობრივ პოპულაციებში და ნაკლებად ხშირი სხვებში, ამიტომ შედეგს განსხვავებული წინასწარმეტყველებითი ღირებულება აქვს სხვადასხვა თემში. უარყოფითი შედეგი ამცირებს HLA-B27-ასოცირებული დაავადების ალბათობას, მაგრამ ვერ გამორიცხავს აქსალურ სპონდილოართრიტს.
HLA-B27 ტესტის მნიშვნელობა ბინარულია: აღმოჩენილი ან არ არის აღმოჩენილი, არა მაღალი ან დაბალი. ლაბორატორიები ჩვეულებრივ იყენებენ მოლეკულურ ტიპირებას ლაბორატორიული ნიმუშიდან, და შედეგი არ იცვლება ძილის, დიეტის, გამწვავების ან მედიკამენტების მიხედვით. ეს ფუნდამენტურად განსხვავდება ანთებითი მარკერებისგან, როგორიცაა ედს, რომლებიც შეიძლება შეიცვალოს დღეებიდან კვირებამდე.
კანტესტი არის AI სისხლის ტესტის ანალიზატორი რომელიც ათავსებს იმპორტირებულ HLA შედეგს შესაბამის ანთებით მარკერებთან ერთად, მაგრამ მას არ შეუძლია სპონდილოართრიტის დიაგნოსტირება მხოლოდ გენეტიკური მარკერის საფუძველზე. Thomas Klein, MD, ურჩევს პაციენტებს დაუსვან უფრო მარტივი კითხვა: რა კლინიკური პრობლემის გადასაჭრელად შეუკვეთეს ტესტი? ჩვენი ბიომარკერის სახელმძღვანელო ხსნის, თუ რატომ საჭიროებს და flagged ან დადებითი შედეგი ყოველთვის თავის ლაბორატორიულ მეთოდს და კლინიკურ კონტექსტს.
რატომ შეიძლება დადებითი შედეგი უფრო შემზარავი იყოს, ვიდრე სინამდვილეშია
HLA-B27-დადებითი ადამიანების უმეტესობას არასდროს უვითარდება ანკილოზებელი სპონდილიტი. მარკერი მონაწილეობს ანტიგენის პრეზენტაციაში, თუმცა ბიოლოგიური გზა მისი ტარებიდან დაავადების განვითარებამდე არასრული რჩება; ნაწლავის მიკრობები, იმუნური რეგულაცია და სხვა გენები, როგორც ჩანს, წვლილს შეაქვთ. ეს გაურკვევლობა რეალურია და კლინიცისტებმა არ უნდა გადააქციონ გენეტიკური ასოციაცია პროგნოზად.
HLA-B27 და ანკილოზური სპონდილიტი: ასოციაცია დიაგნოზთან შედარებით
რადიოგრაფიული ანკილოზებელი სპონდილიტის მქონე ადამიანების დაახლოებით 80%-დან 95%-მდე HLA-B27 დადებითია ბევრი ჩრდილოეთ ევროპის კოჰორტში, მაგრამ მარკერი არც აუცილებელია და არც საკმარისი დიაგნოზისთვის. ექიმები აქსალურ სპონდილოართრიტს დიაგნოსტირებენ მთელი სურათის საფუძველზე: სიმპტომები, ფიზიკური აღმოჩენები, გამოსახულება, ლაბორატორიული შედეგები და კონკურენტული ახსნა.
დადებით HLA-B27 შედეგს აქვს უდიდესი დიაგნოსტიკური ღირებულება იმ ადამიანში, ვისაც აქვს ქრონიკული წელის ტკივილი, რომელიც დაიწყო 45 წლამდე. 55 წლის ადამიანისთვის, ვისაც პირველი წელის ტკივილი 52 წლის ასაკში ავეჯის აწევის შემდეგ დაეწყო, იგივე შედეგი ხშირად ძალიან მცირე ცვლილებას იწვევს. ამიტომ ტესტმა, რომელიც შეკვეთილია კლინიკური წინასწარი ტესტის ალბათობის გარეშე, შეიძლება გამოიწვიოს მეტი შფოთვა, ვიდრე სიცხადე.
ASAS კლასიფიკაციის ჩარჩო იძლევა საშუალებას HLA-B27-დადებით ადამიანს ქრონიკული წელის ტკივილით, რომელიც დაიწყო 45 წლამდე, დაუკავშირდეს აქსალური სპონდილოართრიტის გზას, როდესაც არსებობს მინიმუმ ორი სხვა სპონდილოართრიტის მახასიათებელი, როგორიცაა უვეიტი, ფსორიაზი, ანთებითი ნაწლავის დაავადება, ართრიტი, ენტეზიტი ან ოჯახური ისტორია (Rudwaleit et al., 2009). კლასიფიკაციის კრიტერიუმები ეხმარება კვლევის თანმიმდევრულობას; ისინი არ არიან სახლის დიაგნოსტიკური ჩეკლისტი.
რადიოგრაფიული ანკილოზებელი სპონდილიტი აღწერს საკროილიაკური სახსრის დადგენილ სტრუქტურულ ცვლილებას რენტგენზე, ხოლო არარადიოგრაფიულ აქსალურ სპონდილოართრიტს შეიძლება ჰქონდეს ნორმალური რენტგენი. MRI can identify active bone-marrow tissue response earlier, although athletic loading, pregnancy-related changes, and degenerative disease can also make MRI interpretation tricky. A focused unexplained pain work-up დაგეხმარებათ დიფერენციალური დიაგნოზის ფართო სპექტრის ჩამოყალიბებაში.
The risk number patients usually want
First-degree relatives of a person with HLA-B27-associated ankylosing spondylitis have a higher risk than the general population, but family risk is not destiny. Risk estimates differ substantially by sex, ancestry, and whether the affected relative has radiographic disease. I do not recommend testing healthy children or siblings merely to settle worry unless a specialist identifies a specific clinical reason.
რით განსხვავდება ანთებითი ზურგის ტკივილი ჩვეულებრივი ზურგის ტკივილისგან
Inflammatory back pain typically begins gradually before age 45, persists for more than 3 months, improves with exercise, and does not improve reliably with rest. Mechanical pain more often follows a strain, worsens predictably with loading, and settles when the provoking movement stops.
Waking in the second half of the night because of back or buttock pain is a useful clue when it occurs repeatedly, not once after a poor mattress. Alternating buttock pain, morning stiffness lasting longer than 30 minutes, and marked improvement after getting moving add weight to the inflammatory pattern. None is individually diagnostic; together, they are more persuasive.
I often see a 32-year-old runner who says, I loosen up after the first kilometre. That is not proof of inflammation—many musculoskeletal problems warm up—but pain that returns after sitting, wakes them near 4 a.m., and has continued for 9 months deserves more than generic stretching advice. Pain severity is less informative than the pattern over time.
NICE advises rheumatology referral for back pain beginning before 45 and lasting more than 3 months when several spondyloarthritis features coexist; HLA-B27 testing can support referral when exactly three features are present. New bowel or bladder dysfunction, saddle numbness, fever, unexplained weight loss, cancer history, or rapidly progressive weakness requires urgent assessment for causes beyond spondyloarthritis. Review the practical distinction between inflammation and injury in our psoriasis laboratory guide, particularly if skin disease is also present.
A useful two-week symptom record
Record wake time, stiffness duration, exercise response, buttock location, and anti-inflammatory medicine response for 14 days before an appointment. This produces more diagnostic value than a generic pain score from 0 to 10, because rheumatologists are looking for a reproducible inflammatory rhythm.
როდესაც HLA-B27-თან დაკავშირებულ წითელ თვალს ესაჭიროება იმავე დღის მკურნალობა
A painful red eye with light sensitivity, blurred vision, or a smaller-looking pupil can be acute anterior uveitis and needs same-day assessment by an eye specialist or emergency eye service. HLA-B27-associated uveitis often starts suddenly in one eye and can recur, sometimes in the other eye at a later date.
Acute anterior uveitis is not the same as conjunctivitis. Conjunctivitis commonly causes discharge or gritty discomfort; uveitis more often causes deep aching pain, photophobia, reduced visual clarity, and redness concentrated around the iris. A normal-looking external eye does not reliably exclude it, especially early on.
Roughly half of acute anterior uveitis cases in many European-derived cohorts are HLA-B27 positive, but eye doctors still consider infection, sarcoidosis, Behçet disease, inflammatory bowel disease, trauma, and medication effects. Do not use leftover steroid eye drops without an examination, because steroid drops can worsen undiagnosed corneal infection and raise eye pressure. ჩვენი გზამკვლევი Behçet eye symptoms covers another condition where oral ulcers and eye symptoms change the urgency.
Treatment commonly uses prescription topical corticosteroid drops plus pupil-dilating drops, with a taper directed by ophthalmology. Follow-up matters because pressure elevation and swelling at the back of the eye can occur even when pain improves. A recurrent episode should trigger communication between ophthalmology and rheumatology rather than parallel, disconnected care.
სიმპტომები, რომლებიც არ უნდა დაელოდონ რუტინულ შეხვედრას
Sudden vision loss, a curtain or shower of new floaters, severe headache with nausea, halos around lights, or severe eye pain needs emergency evaluation immediately. These features can signal diagnoses other than uveitis, including acute angle-closure glaucoma or retinal disease, where delay can threaten sight.
სხვა სიმპტომები, რომლებიც HLA-B27-ს უფრო მნიშვნელოვანს ხდის
HLA-B27 becomes more clinically meaningful when back or eye symptoms occur with psoriasis, inflammatory bowel disease, heel enthesitis, swollen joints, or a close relative with related disease. This cluster is called the spondyloarthritis spectrum because different tissues may be involved at different times.
Enthesitis is inflammation where a tendon or ligament attaches to bone, commonly causing focal pain at the Achilles insertion or bottom of the heel. It differs from diffuse foot ache because the tenderness is usually sharply localized and may be worst after rest. Ultrasound can help, but body weight, sports loading, and footwear can produce similar symptoms.
Psoriasis-related nail pitting, separation of the nail plate, or a whole swollen finger or toe can be particularly helpful diagnostic clues. A person does not need widespread psoriasis for this to count; a small scalp patch or a long history of flaky plaques behind the ears may matter. Photographing an intermittent rash before it fades can save a surprising amount of time at review.
Chronic diarrhoea, nocturnal stool urgency, rectal bleeding, or unintended weight loss should prompt bowel evaluation rather than being attributed to stress. Faecal calprotectin is useful for detecting intestinal tissue response but is not specific for Crohn disease or ulcerative colitis; our calprotectin comparison explains its limitations. The connection matters because bowel inflammation can steer both imaging choices and treatment selection.
Symptoms that do not fit neatly
Fatigue is common in active inflammatory disease but is too non-specific to establish a diagnosis. Iron deficiency, sleep disruption, thyroid dysfunction, mood disorders, medications, and prolonged pain can all contribute, so I look for a coherent pattern rather than assigning fatigue to HLA-B27.
როგორ ცვლის ოჯახური ისტორია შემდეგ ნაბიჯს
A first-degree relative with ankylosing spondylitis, recurrent uveitis, psoriasis, inflammatory bowel disease, or reactive arthritis increases suspicion when compatible symptoms are present. Family history supports a referral decision; it does not make testing or imaging mandatory in a person with no symptoms.
Ask relatives about diagnoses and major symptoms, not only whether they carry HLA-B27. People may remember being told they had iritis, a stiff spine, Crohn disease, or psoriasis but have never heard the term spondyloarthritis. The age at symptom onset is especially valuable: back pain that began at 22 tells a different story from osteoarthritis diagnosed at 72.
Kantesti AI არის AI სისხლის ანალიზის განმარტების პლატფორმა that can organise family-shared laboratory histories with consent, but family-history patterns still require a clinician to verify diagnoses. A useful record includes affected relative, relationship, condition, age at onset, eye episodes, and relevant imaging. Our ოჯახის ისტორიის ტრეკერი offers a practical template for recording that detail.
Routine HLA-B27 testing in symptom-free relatives usually does not improve outcomes. The result can create false reassurance when negative and unnecessary fear when positive, because no proven preventive treatment is prescribed simply for carrier status. A child with persistent limp, eye symptoms, or swollen joints needs paediatric assessment based on symptoms, whatever the family genotype.
What to bring to a specialist appointment
Bring prior X-ray or MRI reports, eye-clinic letters, medication dates, and a one-page family history. Imaging discs or digital access are often more useful than repeating scans, particularly because sacroiliac-joint MRI requires experienced interpretation.
რატომ არ გამორიცხავს ანთების ნორმალური ტესტები ამას
Normal CRP and ESR do not rule out axial spondyloarthritis or HLA-B27-associated uveitis. These tests measure systemic inflammatory activity indirectly, and localized disease can be clinically active while both results remain within the laboratory reference interval.
CRP is often reported in mg/L, with many laboratories using less than 5 mg/L as a reference threshold, while ESR reference limits vary with age and sex. A CRP of 2 mg/L can coexist with active sacroiliac inflammation on MRI. Conversely, a CRP of 28 mg/L is non-specific and may reflect infection, obesity, dental inflammation, or another inflammatory condition.
A complete blood count, liver profile, kidney profile, CRP, and ESR are baseline context tests rather than diagnostic proof. Anaemia, raised platelets, low albumin, or iron deficiency can suggest persistent inflammation or bowel involvement, but each has alternative explanations. This is one reason inflammatory conditions should not be inferred from a single marker.
კანტესტი არის AI-ზე დაფუძნებული სისხლის ანალიზის (blood test analysis) ხელსაწყო that can compare CRP, platelets, haemoglobin, and albumin across dates, helping users identify a pattern to discuss with their clinician. It cannot see sacroiliitis on an MRI or assess a painful eye. For antibody results that can be over-interpreted in a similar way, see our explanation of ANA ტესტირება.
Medication and test interpretation
NSAIDs can reduce CRP and improve symptoms without proving or disproving the diagnosis. Do not stop prescribed anti-inflammatory medication before testing unless the clinician managing your care specifically asks you to; an artificial flare is not a safe diagnostic strategy.
რომელი სკანირებები გვეხმარება და რა შეიძლება გამოტოვდეს თითოეულმა სკანირებამ
MRI of the sacroiliac joints is the preferred scan when axial spondyloarthritis is suspected but X-rays are normal or inconclusive. X-rays show structural change that often develops slowly, whereas MRI can show active bone-marrow tissue response and other early changes.
A normal lumbar-spine MRI does not replace a dedicated sacroiliac-joint MRI protocol. The relevant joints are lower and more lateral than the area commonly imaged for a slipped disc. I have seen patients reassured by an ordinary lumbar scan that was simply not designed to answer the inflammatory question.
MRI findings require clinical correlation because bone-marrow oedema can occur after intense exercise, childbirth, mechanical stress, and degenerative change. The radiology report should describe location, depth, distribution, erosions, fat change, and structural features; a vague statement of oedema alone is not enough. A rheumatologist may ask for image review when the report and symptom pattern disagree.
Pelvic X-rays remain useful for documenting chronic sacroiliac structural changes, but a normal X-ray does not close the case in a younger person. CT shows structure very clearly but uses ionising radiation and is not generally the first choice for early inflammatory disease. If persistent inflammation affects mobility, bone-health assessment may also be relevant; read our bone loss laboratory guide.
Why the scan report can sound uncertain
Radiologists appropriately use terms such as compatible with or non-specific when the imaging pattern is not definitive. That wording is not evasive; it reflects a real overlap between inflammatory and mechanical findings, and it prevents imaging from being treated as a diagnosis in isolation.
როდის უნდა ითხოვოთ რევმატოლოგთან მიმართვა
Ask for rheumatology evaluation when chronic back pain began before age 45 and is accompanied by inflammatory features, HLA-B27 positivity, recurrent uveitis, psoriasis, bowel symptoms, heel enthesitis, or a relevant family history. A positive test plus one convincing clinical feature is more useful than a positive test discovered during broad screening.
A referral is reasonable even when CRP is normal and X-rays are unremarkable if the clinical pattern is compelling. The 2019 ACR/SAA/SPARTAN guideline recommends treatment decisions based on disease activity, function, comorbidities, and patient preferences rather than a genetic result alone (Ward et al., 2019). This approach prevents both delayed diagnosis and reflexive overtreatment.
At the appointment, expect questions about age at onset, morning stiffness, night waking, response to NSAIDs, eye attacks, skin lesions, bowel symptoms, infection preceding arthritis, and family history. A rapid and clear response to a full-dose NSAID may support suspicion, but it is not a diagnostic test. NSAIDs also improve ordinary back pain.
Thomas Klein, MD, recommends making a dated timeline rather than trying to remember every symptom in the consulting room. Include medication dose and duration, especially if using ibuprofen, naproxen, or diclofenac, because kidney function, blood pressure, ulcer risk, and anticoagulant use alter the safety calculation. Our medication trend guide explains why repeat kidney and liver results may matter during longer courses.
When an orthopaedic or physiotherapy assessment may be better first
Back pain starting after age 45 following a specific injury, with clear load-related triggers and no inflammatory features, more often benefits initially from musculoskeletal care. That is a probability statement, not a dismissal; persistent uncertainty or new eye, skin, bowel, or joint symptoms warrants reassessment.
როგორია მკურნალობა, თუ დადასტურებულია ღერძული სპონდილოართრიტი
Confirmed axial spondyloarthritis is treated with education, regular movement, targeted physiotherapy, and anti-inflammatory medicines; biologic or targeted synthetic medicines are reserved for persistent active disease. HLA-B27 status does not determine treatment by itself.
Exercise is treatment, not a test of willpower. A programme that maintains spinal extension, hip mobility, chest expansion, and aerobic capacity is generally more sustainable than sporadic intense workouts. Most patients find short daily mobility work of 10 to 20 minutes easier to keep than a single ambitious weekend session.
NSAIDs are usually considered first-line when safe, but dose and duration must be individualised. Naproxen 500 mg twice daily is a common adult anti-inflammatory dose, yet it may be unsuitable with chronic kidney disease, prior ulcer bleeding, heart failure, uncontrolled hypertension, anticoagulants, or pregnancy. Gastroprotection may be appropriate for some people, but it does not remove kidney or cardiovascular risk.
Biologic medicines such as TNF inhibitors and IL-17 inhibitors require screening and specialist monitoring because infection risk and comorbidities affect selection. Recurrent uveitis, psoriasis, and inflammatory bowel disease influence which agent best fits the whole person. This is one reason a diagnosis based only on an HLA-B27 result can lead to the wrong treatment conversation.
Avoid the supplement trap
No supplement has been shown to prevent HLA-B27-associated spondyloarthritis in healthy carriers. Correcting a documented vitamin D, iron, or B12 deficiency can improve general health, but it is not a substitute for assessment of inflammatory back pain or a painful red eye.
როგორ ვადევნოთ თვალი შედეგებს, არ გავხდეთ მათი ტყვე
The most useful record combines symptoms, function, medications, eye episodes, imaging, and laboratory trends rather than repeatedly retesting HLA-B27. Once accurately typed, HLA-B27 status does not need serial monitoring because your inherited marker does not change.
Track functional measures that mean something to you, such as minutes until morning stiffness eases, uninterrupted sleep, walking tolerance, or ability to turn while driving. These details show treatment response more honestly than a single good or bad day. Note whether an eye flare preceded a back-pain change by days or weeks.
Kantesti can organise imported laboratory reports across time and flag changes for discussion, but it should not be used to self-start or stop prescription treatment. Our clinical framework is described in the AI ტექნოლოგიის გზამკვლევი: results are interpreted as context for professional care, not as a replacement for examination or imaging.
Repeating CRP during a flare can be useful when a clinician is also following symptoms and treatment response, but routine weekly testing is rarely helpful. In my experience, a symptom record every day and blood work at clinically meaningful intervals yields less noise and fewer false alarms. Laboratory trends only become informative when collection dates, infections, exercise, and medicines are documented.
A note about privacy and family data
Genetic information can affect relatives as well as the person tested, so share reports deliberately. Keep the original laboratory report, remove unrelated identifiers when appropriate, and obtain consent before adding another adult's results to a shared family record.
გავრცელებული მცდარი შეხედულებები HLA-B27-ის დადებითობის შესახებ
HLA-B27 positivity does not mean your immune system is attacking your spine, that you are contagious, or that you need treatment while symptom-free. It is a common inherited allele whose significance depends on the clinical setting.
Myth: a positive HLA-B27 test explains every ache. Fact: mechanical back pain remains common among HLA-B27 carriers. Strain, disc disease, hip disorders, hypermobility, fibromyalgia, kidney stones, and pelvic conditions still deserve a normal differential diagnosis. The marker should sharpen clinical reasoning, not end it.
Myth: a negative HLA-B27 test rules out ankylosing spondylitis. Fact: HLA-B27-negative axial spondyloarthritis occurs, especially across populations with lower background carrier frequency. When imaging and clinical features are persuasive, a negative result should not be used to deny specialist review.
Myth: genes are the same as destiny. Fact: genetics influence risk, but no preventive biologic therapy is indicated for a well HLA-B27 carrier. This is conceptually similar to the limits of MTHFR result interpretation: genetic information is medically useful only when the result changes an evidence-based decision.
Can stress cause a flare?
Stress can worsen pain, sleep, fatigue, and coping, but it does not explain away objective uveitis or inflammatory arthritis. Treating sleep and stress is worthwhile alongside medical care; it should never delay eye assessment or replace a work-up for persistent inflammatory symptoms.
კითხვები, რომლებიც უფრო სასარგებლოს გახდის პირველ მიღებას
The best first appointment questions focus on probability, alternative diagnoses, and the next decision—not on whether HLA-B27 is good or bad. A clinician should be able to explain what finding would increase or decrease their suspicion and what test would change management.
Ask whether your symptoms meet an inflammatory-back-pain pattern and which features argue against it. Then ask whether dedicated sacroiliac MRI is appropriate, whether an ophthalmology referral is needed, and whether psoriasis or bowel symptoms warrant coordinated review. This approach respects uncertainty without letting it become inaction.
Ask how long to try a treatment, what outcome defines success, and which adverse effects need a call. For NSAIDs, the specific safety discussion should include kidney function, blood pressure, gastrointestinal history, pregnancy plans, and interacting drugs. For biologics, ask about screening, vaccines, infection precautions, and how uveitis or bowel disease changes the choice.
Kantesti's clinical content is medically reviewed with structured quality controls; readers can examine our სამედიცინო ვალიდაციის მიდგომა და ჩვენი სამედიცინო საკონსულტაციო საბჭოს. A laboratory interpretation is most valuable when it helps you ask a better question of the clinician who can examine you.
A concise appointment script
Say: My back pain started at age 29, has lasted 14 months, wakes me at 4 a.m., improves after 30 minutes of movement, and I had a painful light-sensitive eye last spring. That one sentence gives a rheumatologist more usable information than stating only that an HLA-B27 result was positive.
გადაუდებელი სიმპტომები და უსაფრთხო შემდეგი ნაბიჯების გეგმა
Seek same-day urgent eye care for eye pain, light sensitivity, red eye with blurred vision, or any sudden visual change; seek emergency care for new weakness, bladder or bowel dysfunction, saddle numbness, high fever, or severe unremitting back pain. Do not wait for repeat blood work, an MRI booking, or a rheumatology appointment when these red flags occur.
For non-urgent symptoms, book a primary-care review within weeks if back pain has lasted more than 3 months and began before age 45, especially with HLA-B27 positivity or family history. Bring your HLA report, symptom timeline, medication list, eye-clinic letters, and prior images. A targeted referral is generally faster and more useful than repeating broad autoimmune panels.
As of September 27, 2026, the central clinical principle remains unchanged: HLA-B27 is a risk marker, not a diagnosis. Thomas Klein, MD, has found that patients do best when they treat a positive result as a prompt to notice patterns—then obtain the right eye, primary-care, or rheumatology assessment rather than catastrophising or ignoring symptoms.
კანტესტი არის AI ლაბორატორიული ტესტის ინტერპრეტაციის სერვისზე built to explain laboratory reports in plain language while preserving the boundary between information and diagnosis. Learn how our organisation approaches this work on our „About Us“ გვერდზე and find further patient education in the კანტესტის ბლოგი.
კვლევითი პუბლიკაციის სექცია
Kantesti LTD. (2026). B ნეგატიური სისხლის ჯგუფი, LDH სისხლის ანალიზი და რეტიკულოციტების რაოდენობის სახელმძღვანელო. Figshare. https://doi.org/10.6084/m9.figshare.31333819. Related author records may be located through კვლევის კარიბჭე და Academia.edu.
Kantesti LTD. (2026). შიმშილის შემდეგ დიარეა, შავი ლაქები განავალში და კუჭ-ნაწლავის ტრაქტის სახელმძღვანელო 2026. Figshare. https://doi.org/10.6084/m9.figshare.31438111. Related author records may be located through კვლევის კარიბჭე და Academia.edu.
These publications are not evidence for diagnosing HLA-B27-associated disease and should not replace the rheumatology and ophthalmology references cited above. They are listed as Kantesti research records for transparency.
ხშირად დასმული კითხვები
ნიშნავს თუ არა HLA-B27-ის დადებითი შედეგი, რომ მაქვს ანკილოზური სპონდილიტი?
არა. HLA-B27-ის დადებითი შედეგი ნიშნავს, რომ თქვენ გაქვთ გენეტიკური მარკერი, რომელიც ასოცირდება ანკილოზურ სპონდილიტთან და მასთან დაკავშირებულ დაავადებებთან, თუმცა ბევრი მატარებელი სიცოცხლის განმავლობაში ჯანმრთელი რჩება. რადიოგრაფიული ანკილოზური სპონდილიტის მქონე ჯგუფებში, დაახლოებით 80%-დან 95%-მდე არის HLA-B27-ის მატარებელი, თუმცა საპირისპირო არ მართლდება: პოზიტიური ადამიანების უმეტესობას არ აქვს ეს დაავადება. დიაგნოზი მოითხოვს თავსებად სიმპტომებს, გამოკვლევას, გამოსახულებას და სხვა მიზეზების გამორიცხვას.
რა სიმპტომები მიუთითებს HLA-B27-თან ასოცირებულ ანთებაზე?
ზურგის ტკივილი უფრო მეტყველებს ღერძულ სპონდიлоართრიტზე, როდესაც ის იწყება 45 წლამდე ასაკში, ვითარდება თანდათანობით, გრძელდება 3 თვეზე მეტხანს, უმჯობესდება მოძრაობით და იწვევს დილის შებოჭილობას, რომელიც გრძელდება 30 წუთზე მეტხანს. ღამის მეორე ნახევარში განმეორებითი გამოღვიძება და დუნდულოების მონაცვლეობითი ტკივილი ამატებს სასარგებლო მინიშნებებს. HLA-B27-ის დადებითი შედეგი ზრდის ამ სურათის მნიშვნელობას, მაგრამ კლინიცისტს კვლავ სჭირდება მექანიკური მიზეზების და წითელი დროშების შეფასება.
იწვევს თუ არა HLA-B27-ის ქონა უვეიტს?
HLA-B27 პირდაპირ არ იწვევს თვალის ყველა პრობლემას, მაგრამ მტკიცედ არის დაკავშირებული მწვავე წინა უვეიტთან. უვეიტის ეს ტიპი, როგორც წესი, იწვევს თვალის ერთ მხარეს სიწითლეს, ძლიერ ტკივილს, სინათლის მიმართ მგრძნობელობას და მხედველობის დაბინდვას; ის მოითხოვს თვალის სპეციალისტის მიერ იმავე დღეს შეფასებას. მწვავე წინა უვეიტის შემთხვევების დაახლოებით ნახევარი HLA-B27 დადებითია ევროპული წარმოშობის მრავალ ჯგუფში, თუმცა გავრცელება მოსახლეობის მიხედვით იცვლება და ალტერნატიული მიზეზები უნდა იქნას გათვალისწინებული.
უნდა მივმართო რევმატოლოგს, თუ HLA-B27 პოზიტიური ვარ, მაგრამ სიმპტომები არ მაქვს?
სიმპტომების გარეშე მყოფ HLA-B27-დადებით პირებს, როგორც წესი, არ სჭირდებათ რევმატოლოგის რეგულარული მეთვალყურეობა ან პრევენციული მკურნალობა. დათვალიერება მიზანშეწონილია, თუ ქრონიკული ზურგის ტკივილი 45 წლამდე დაიწყო, განვითარდა განმეორებითი უვეიტი, ფსორიაზი, ნაწლავების მუდმივი სიმპტომები, ქუსლის ტკივილი ენტეზიტის გამო, სახსრების შეშუპება ან ძლიერი ოჯახური ანამნეზი. HLA-B27-ის განმეორებითი ტესტირება უსარგებლოა, რადგან მემკვიდრეობით მიღებული HLA სტატუსი არ იცვლება დროთა განმავლობაში.
შეიძლება თუ არა CRP და ESR ნორმალური იყოს ანკილოზური სპონდილიტის დროს?
დიახ. CRP ხშირად ნორმად ითვლება 5 მგ/ლ-ზე ნაკლებად ბევრ ლაბორატორიაში, მაგრამ CRP-ის და ESR-ის ნორმალური მაჩვენებლები არ გამორიცხავს ღერძულ სპონდილოართრიტს ან აქტიურ უვეიტს. ეს მარკერები ასახავს სისტემურ ანთებით აქტივობას და შეიძლება ნორმად დარჩეს, როდესაც ანთება ლოკალიზებულია საკროილიალურ სახსრებში ან თვალში. MRI, სიმპტომების ნიმუში, ფიზიკური გამოკვლევა და სპეციალისტის შეფასება შეიძლება უფრო ინფორმატიული იყოს, ვიდრე ანთების ერთი ნორმალური შედეგი.
ტარდება თუ არა HLA-B27 სისხლის ანალიზი?
HLA-B27-ის ტიპის განსაზღვრა ჩვეულებრივ ხორციელდება ლაბორატორიული ნიმუშიდან მოლეკულური ან ნაკადის ციტომეტრიის მეთოდების გამოყენებით, და ბევრი ლაბორატორია იყენებს სისხლის ნიმუშს. ტესტი არის ხარისხობრივი, შედეგი ფიქსირდება როგორც გამოვლენილი ან არა-გამოვლენილი, კონცენტრაციის ან ნორმალური დიაპაზონის ნაცვლად. დიეტა, ვარჯიში და დაავადების აქტივობა არ ცვლის შედეგს, რადგან HLA-B27 მემკვიდრეობითია და არა ანთებითი მარკერი.
მიიღეთ AI-ით გაძლიერებული სისხლის ანალიზის განმარტება დღეს
შეუერთდით 2 მილიონზე მეტ მომხმარებელს მთელ მსოფლიოში, რომლებიც ენდობიან Kantesti-ს ლაბორატორიული ანალიზების მყისიერ და ზუსტ განმარტებაში. ატვირთეთ თქვენი სისხლის ანალიზის შედეგები და მიიღეთ 15,000+ ბიომარკერების ყოვლისმომცველი ინტერპრეტაცია წამებში.
📚 მითითებული კვლევითი პუბლიკაციები
კლაინი, ტ., მიტჩელი, ს., და ვებერი, ჰ. (2026). B უარყოფითი სისხლის ჯგუფი, LDH სისხლის ანალიზი და რეტიკულოციტების რაოდენობის სახელმძღვანელო. Kantesti AI სამედიცინო კვლევა.
კლაინი, ტ., მიტჩელი, ს., და ვებერი, ჰ. (2026). შიმშილის შემდეგ დიარეა, შავი ლაქები განავალში და კუჭ-ნაწლავის ტრაქტის სახელმძღვანელო 2026. Kantesti AI სამედიცინო კვლევა.
📖 გარე სამედიცინო წყაროები
⚕️ სამედიცინო პასუხისმგებლობის შეზღუდვა
ეს სტატია მხოლოდ საგანმანათლებლო მიზნებისთვისაა და არ წარმოადგენს სამედიცინო რჩევას. დიაგნოზისა და მკურნალობის გადაწყვეტილებებისთვის ყოველთვის მიმართეთ კვალიფიციურ ჯანდაცვის სპეციალისტს.
E-E-A-T სანდოობის სიგნალები
გამოცდილება
ექიმის ხელმძღვანელობით კლინიკური მიმოხილვა ლაბორატორიული ინტერპრეტაციის სამუშაო პროცესებზე.
ექსპერტიზა
ლაბორატორიული მედიცინის აქცენტი იმაზე, როგორ იქცევიან ბიომარკერები კლინიკურ კონტექსტში.
ავტორიტეტულობა
დაწერილია დოქტორ თომას კლაინის მიერ, მიმოხილვა: დოქტორ სარა მიტჩელისა და პროფესორ დოქტორ ჰანს ვებერის მიერ.
სანდოობა
მტკიცებულებებზე დაფუძნებული ინტერპრეტაცია, მკაფიო შემდგომი ნაბიჯებით, რათა შემცირდეს განგაშის დონე.