Et positivt antistoffresultat kan gjenspeile tidligere eksponering snarere enn aktuell sykdom. Symptomer, reisehistorikk, immunstatus og prøvematerialet som er testet, avgjør hvilken bekreftelse som er nødvendig.

Viktige punkter
- Positive antistoffer viser en immunrespons mot Leishmania-antigener; de fastslår ikke i seg selv aktiv leishmaniasis.
- Tre hovedformer—visceral, kutan og mukosal leishmaniasis—krever ulike kliniske vurderinger og strategier for prøvetaking.
- Bekreftelse av visceral leishmaniasis kan kombinere forenlig sykdom med serologi, PCR, mikroskopi eller dyrkning; enkelte programmer i endemiske områder godtar positiv hurtigserologi innenfor en definert klinisk algoritme.
- Bekreftelse av kutan leishmaniasis krever vanligvis prøvemateriale fra et berørt hudområde til PCR, mikroskopi eller dyrkning; antistofftesting har dårlig ytelse ved lokalisert sykdom.
- Testytelsen varierer regionalt En Cochrane-gjennomgang anslo sensitiviteten for rK39 til rundt 97 % på det indiske subkontinentet mot 85% i Øst-Afrika blant personer med mistanke om visceral sykdom.
- Immunsuppresjon kan svekke antistoffresponsen og tillate reaktivering flere år etter eksponering; et negativt antistoffresultat utelukker ikke sykdommen på en trygg måte hos en pasient med høy risiko.
- Varseltegn som krever akutt hjelp omfatter forvirring, alvorlig tungpust, betydelig blødning eller feber med et absolutt nøytrofiltall under 0.5 × 10^9/L.
- Neste time bør omfatte den fullstendige laboratorierapporten, reisemål og datoer, tidligere behandling for leishmaniasis og en liste over immundempende legemidler.
Hva betyr et positivt antistoffresultat for leishmaniasis egentlig?
A positivt antistoff mot leishmaniasis betyr at analysen påviste antistoffer som reagerer med Leishmania-antigener – ikke nødvendigvis aktiv sykdom. Tidligere infeksjon, asymptomatisk eksponering eller kryssreaktivitet kan gi et positivt resultat; aktiv sykdom krever vurdering av symptomer, eksponering og immunstatus, samt påvisning av parasitter når det er relevant.

Leishmaniasis har 3 hovedformer: visceral sykdom som rammer indre organer, kutan sykdom som rammer huden, og mukosal sykdom som rammer strukturer som nesen eller munnen. Et antistoffresultat kan ikke pålitelig fastslå hvilken form en person har, lokalisere det berørte vevet eller avgjøre hvilken art som er ansvarlig; disse forskjellene påvirker både neste undersøkelse og behandlingsdiskusjonen.
Antileishmaniale antistoffer kan fortsatt påvises i årevis etter vellykket behandling, så et resultat som fås 2 år etter tilfriskning, kan fortsatt være positivt uten å bevise tilbakefall. Omvendt trenger en person med nyoppstått vedvarende feber og forstørret milt vurdering selv om antistoffverdien bare ligger litt over laboratoriets grenseverdi – kliniske funn veier tyngre enn hvor høyt utslaget er.
Kantesti er en AI-blodprøveanalysator som kan bidra til å forklare ledsagende laboratoriefunn, men en positiv antistoffrapport gir ikke de undersøkelses- eller vevsfunnene som trengs for å stille diagnosen. Vår organisasjon og kliniske formål skiller mellom støtte til tolkning og medisinsk behandling; ta med den fullstendige rapporten, inkludert minst metode, referanseintervall og prøvemateriale, til klinikeren som organiserer oppfølgingen.
Hvilken leishmaniasetest utførte laboratoriet ditt?
Betydningen av en positiv leishmaniasisprøve avhenger av metoden: rK39-hurtigtester, ELISA, indirekte fluorescerende antistofftesting og direkte agglutinasjonstesting påviser antistoffer, mens PCR påviser parasitt-DNA. Resultatene fra disse metodene kan ikke sammenlignes direkte, og ingen universell antistoffgrense fastslår aktiv sykdom.
En rapport kan vise et kvalitativt resultat, en indeksverdi eller en antistofftiter uttrykt som en fortynning, for eksempel 1:160. I en tydelig hypotetisk analyse der positivitet begynner ved en indeks på 1.1, betyr et resultat på 1.4 at signalet overskred grenseverdien for den analysen – ikke at sykdommen er mild eller at et bestemt antall parasitter er til stede; vår kvalitativ versus kvantitativ veiledning forklarer dette skillet i rapporteringen.
rK39-analyser påviser antistoffer mot et rekombinant Leishmania-antigen, men sensitiviteten varierer geografisk og etter produkt. Boelaert et al.s Cochrane-oversikt fra 2014 anslo sensitiviteten for rK39-hurtigtester til omtrent 97.0% på det indiske subkontinentet og 85.3% i Øst-Afrika blant personer som ble undersøkt for mistenkt visceral leishmaniasis; disse estimatene bør ikke brukes på asymptomatisk screening eller kutan sykdom.
Ulike laboratorier kan bruke forskjellige antigener, fortynningsserier og definisjoner av grensetilfeller, selv når begge rapportene sier 'Leishmania-antistoff'. Å sammenligne en titer på 1:160 fra én metode med en indeks på 1.4 fra en annen kan ikke fastslå en trend; spør om et referanselaboratorium bør gjennomgå et avvikende resultat før den tilsynelatende tallmessige endringen tolkes som biologisk forverring.
Hvorfor kan et positivt antistoffresultat være misvisende?
Et positivt antistoffresultat kan være misvisende fordi tidligere eksponering, kryssreaktivitet og lav forhåndssannsynlighet reduce its ability to identify active illness. The same assay result carries different diagnostic weight in a symptomatic person from an endemic area and an asymptomatic person without plausible exposure.
Some Leishmania antibody assays cross-react with antibodies to Trypanosoma cruzi, the parasite responsible for Chagas disease, although the extent depends on the antigen and method. A person with exposure in Latin America and 2 reactive parasite antibody tests may need reference-laboratory clarification rather than an assumption of two active infections; our Chagas confirmation pathway explains why assay selection matters.
Consider a hypothetical group of 1,000 people in which 1% have active disease, using an imaginary test with 90% sensitivity and 95% specificity: approximately 9 true-positive and 50 false-positive results would occur, making only about 15% of positive results true positives. These are teaching assumptions, not performance figures for a particular leishmaniasis assay, but they show why testing people without exposure can generate confusing alarms.
Now keep the same hypothetical assay but increase disease prevalence to 30%: approximately 270 true positives and 35 false positives would occur, so about 89% of positives would identify disease. The individual estimate still depends on symptoms, past infection, and immune status; our veiledning for tolkning av positive antistoffprøver helps separate evidence of immune recognition from evidence that treatment is needed.
Hvilke funn gjør visceral leishmaniasis mer sannsynlig?
Visceral leishmaniasis becomes more concerning when prolonged fever, weight loss, and an enlarged spleen accompany compatible exposure, particularly with low blood-cell counts. Antibodies strengthen that clinical pattern but do not explain every fever, anemia, or abnormal protein result.
Visceral leishmaniasis can lower all 3 major blood-cell lines: red cells, white cells, and platelets, producing pancytopenia. Bone-marrow involvement, inflammatory effects, and trapping of cellular elements in an enlarged spleen can contribute together; our forklaring av hemoglobin og hematokrit helps readers understand anemia without mistaking a single low value for a parasite diagnosis.
For example, a hypothetical traveler with 3 weeks of fever, hemoglobin 8.5 g/dL, white-cell count 2.2 × 10^9/L, platelets 70 × 10^9/L, and splenomegaly needs prompt investigation regardless of the antibody index. This combination supports a serious systemic process, but malaria, hematologic disease, disseminated fungal infection, and other conditions remain possible; diagnostic testing should address those alternatives rather than stop at serology.
Visceral disease may also produce polyclonal hypergammaglobulinemia and low albumin, so a hypothetical total protein of 9.0 g/dL with albumin 2.8 g/dL warrants contextual interpretation rather than a reflex assumption of a monoclonal disorder. Our veileder for tolkning av serumproteiner explains the pattern; ultrasound can assess spleen size, but spleen enlargement itself cannot establish the cause.
Hvordan bekreftes diagnosen visceral leishmaniasis?
Visceral leishmaniasis diagnosis uses a compatible clinical syndrome plus laboratory evidence chosen for the setting. PCR, microscopy, and culture can detect the parasite; in some endemic treatment programs, positive rK39 serology with a defined clinical case pattern supports diagnosis without invasive sampling.

Det 2016 IDSA/ASTMH guideline recommends combining diagnostic approaches and using molecular testing when available rather than relying on a single assay in every patient (Aronson et al., 2016). Peripheral blood or buffy-coat PCR may be useful, especially with immune suppression, but bone marrow or other tissue may still be needed when suspicion remains high; a negative result from 1 compartment does not guarantee absence elsewhere.
Aronson et al. report microscopy sensitivities of approximately 52–85% for bone marrow aspirates and 93–99% for splenic aspirates, with yield affected by expertise and parasite burden. Splenic aspiration has a potentially serious bleeding risk and belongs only in appropriately selected patients at experienced centers; the highest-yield specimen is not automatically the safest first choice, particularly when platelet counts or coagulation are abnormal.
A clinician may investigate other causes of the same syndrome while obtaining confirmatory samples, especially if antibody and PCR findings disagree. Our Histoplasma antigen follow-up guide describes another systemic illness that can overlap clinically; obtaining specimens before antiparasitic therapy is useful when feasible, but a critically ill person should not wait several days solely to complete an ideal diagnostic sequence.
Beviser en positiv PCR-test for leishmaniasis en aktiv infeksjon?
A positive leishmaniasis PCR test establishes detection of Leishmania DNA in the tested specimen, assuming a valid assay and appropriate contamination controls. It supports active disease strongly when the specimen and symptoms fit, but DNA detection alone does not prove parasite viability or explain every symptom.

PCR can detect low-level or asymptomatic parasitemia in some exposed populations, and residual genetic material may complicate interpretation after treatment. A hypothetical weakly positive blood PCR in a well person is therefore different from a positive bone-marrow PCR in someone with fever and pancytopenia; clinicians consider at least 3 variables together—clinical syndrome, specimen source, and previous treatment—before interpreting detection as disease requiring therapy.
Cycle-threshold values are not a universal Leishmania parasite-count scale, and a Ct of 35 from 1 laboratory cannot be compared directly with Ct 35 from another assay. Extraction volume, genetic target, calibration, and detection limits differ; our Babesia antibody and infection guide illustrates a related diagnostic distinction, although the organisms and recommended testing pathways are not interchangeable.
Kantesti er en Tjeneste for tolkning av laboratorieprøver med AI that can explain why antibody results, DNA detection, and accompanying CBC findings answer different questions, rather than collapsing them into a single diagnosis. Our AI-tolkningsteknologi-veiledning describes the interpretation approach; no AI analysis can recover the missing specimen source or assay validation details from a report that contains only 1 word: 'positive.'
Hvorfor krever kutan leishmaniasis en hudprøve?
Cutaneous leishmaniasis is usually confirmed by testing material from an affected skin site, not by measuring antibodies in blood. Localized disease may generate little detectable circulating antibody, while skin PCR, microscopy, or culture can directly investigate the area causing concern.

The active raised edge of a persistent affected area often provides useful material, but the optimal sampling method depends on its age, appearance, and the laboratory protocol. Clinicians may use scraping, aspiration, or a biopsy; requesting at least 2 diagnostic approaches, such as PCR and histology, can be useful because one assesses parasite material while the other also evaluates alternative explanations.
A hypothetical person with a single painless forearm sore persisting for 8 weeks after travel may need lesion-directed testing even if Leishmania antibodies are negative and the CBC is normal. Fungal disease, atypical mycobacteria, inflammatory disorders, and skin cancer can resemble cutaneous leishmaniasis; sending appropriate tissue for broader evaluation prevents a parasite-focused request from overlooking another treatable cause.
Species identification matters because some Leishmania species, particularly members of the Viannia subgenus acquired in the Americas, carry a greater concern for later mucosal involvement. Our skin-site PCR testing guide explains why material must come from the relevant affected site, although the exact collection requirements differ; ask before sampling whether the laboratory can identify species from the submitted specimen.
Hvordan påvirker immunsuppresjon tolkningen av testresultater?
Immunsuppresjon can reduce antibody production, increase the risk of visceral disease, and permit reactivation after remote exposure. A negative antibody result is therefore less reassuring in someone with HIV, a transplant, or substantial immune-suppressing treatment; PCR and direct parasite detection become particularly valuable.

HIV-associated risk cannot be judged from viral load alone: CD4-tall describes a different aspect of immune function, and counts below 200 cells/µL indicate advanced immunodeficiency. Our HIV viral-load interpretation guide explains the distinction; even a person with suppressed HIV RNA may need careful evaluation if immune recovery is incomplete and compatible symptoms or exposure are present.
Leishmania can persist after apparent recovery, so immune-suppressing treatment begun 5 years after travel can still make that older exposure clinically relevant. Corticosteroids, transplant medicines, some biologic therapies, and disorders affecting immune function may alter the diagnostic strategy, but risk varies by drug and intensity; patients should provide medication names and doses without stopping prescribed treatment on their own.
A low total IgG concentration offers 1 possible explanation for unreliable antibody-based screening, but normal immunoglobulin levels do not guarantee normal parasite-specific responses. Our immunoglobulin result interpretation separates these measurements; when symptoms remain concerning, repeating the same antibody assay without changing the diagnostic approach may add little compared with testing an appropriate specimen for parasite DNA or organisms.
Hvilke reiseopplysninger endrer betydningen av et positivt resultat?
Reisehistorikk changes both the probability of leishmaniasis and the most useful diagnostic pathway. Exact destinations, rural or outdoor exposure, dates, and previous residence matter more than a continent name because Leishmania species, clinical forms, and antibody-test performance vary within regions.

Leishmaniasis is usually transmitted through the bite of an infected female phlebotomine sand fly, and transmission can occur in parts of the Mediterranean as well as tropical regions. A traveler who visited southern Europe for 2 weeks may have a relevant exposure despite never visiting a destination they considered tropical; absence of a remembered bite does not exclude exposure because these insects are small.
Cutaneous disease often appears weeks to months after exposure, whereas visceral disease may emerge months later or reactivate years afterward, particularly with immune suppression. Record all relevant destinations over more than the last 12 months if your clinician requests them; our travel-associated parasite antibody guide illustrates why an exposure timeline can remain useful long after the journey has ended.
Kantesti AI can help organize the distinction between exposure evidence and routine laboratory abnormalities, but the travel history must come from the person or their records—not from a positive assay. For an appointment, write a 4-part timeline covering destination, dates, onset of symptoms, and immune-suppressing treatment; this can help the clinician choose a geographically appropriate assay and determine whether species identification would change management.
Hvorfor kan riktig test på feil prøvemateriale overse sykdom?
Specimen choice and handling affect sensitivity because Leishmania distribution differs between visceral and localized skin disease. Blood PCR may help investigate visceral disease, while an affected skin specimen is usually more informative for cutaneous disease; collection medium, storage, and transport must match the laboratory method.

Reference laboratories may request EDTA whole blood, buffy coat, fresh tissue, or another specific preparation for PCR, depending on the validated assay. Serum used for an antibody test is not automatically a substitute for every molecular protocol; our PCR sample timing guide explains the general principle of matching collection to the test, although disease-specific instructions must come from the receiving laboratory.
Formalin-fixed tissue supports histology and sometimes validated PCR, but it cannot be used for parasite culture because fixation destroys viability. Before a skin biopsy, the clinician may need to divide material into 2 separately handled portions, one for histopathology and another for fresh-tissue testing; requesting culture only after all material has entered formalin can require an avoidable second procedure.
A negative result obtained after 5 days of treatment may reflect reduced detectable parasite burden rather than an incorrect original diagnosis, although the size of that effect depends on method and specimen. Tell the laboratory and clinician the treatment start date, previous medicines, and sample collection date; if suspicion remains high, the next step may be a different compartment or method rather than repeating an inadequately matched sample.
Hvilke symptomer eller laboratoriefunn krever rask helsehjelp?
Confusion, severe breathlessness, fainting, significant bleeding, or rapidly worsening illness require emergency evaluation, regardless of the antibody result. Persistent fever with weight loss or spleen enlargement needs prompt medical review; new nose, mouth, or throat symptoms after compatible exposure need assessment for mucosal disease.
Feber med en absolute neutrophil count below 0.5 × 10^9/L is an emergency because serious infection can progress rapidly, even before its cause is known. Platelets below 20 × 10^9/L generally warrant urgent clinician-directed assessment, with greater urgency if bleeding occurs; abnormal coagulation and falling counts may need parallel investigation, as explained in our Veiledning til laboratoriemønster ved DIC.
Visceral leishmaniasis can trigger hemophagocytic lymphohistiocytosis, an excessive immune-activation syndrome that may resemble severe infection or hematologic disease. A ferritin value above 500 ng/mL is only one component of established HLH criteria and is far too nonspecific to diagnose the syndrome alone; our HScore interpretation guide explains why fever, cytopenias, organ findings, and additional measurements must be considered together.
Persistent nasal blockage, recurrent nosebleeds, mouth changes, or hoarseness can indicate mucosal involvement, sometimes years after a skin lesion has healed; breathing difficulty is an emergency. Do not wait 2 weeks for a routine antibody repeat if systemic or airway symptoms are progressing, and tell the assessing team about exposure; fever after travel to a malaria-endemic area also requires urgent evaluation for malaria rather than attribution to Leishmania antibodies.
Hvordan vurderer klinikere ulike positive testresultater?
Clinicians interpret a positive leishmaniasis result by asking whether exposure, symptoms, immune status, and parasite evidence agree. The following 3 hypothetical examples show why identical antibody positivity can lead to reassurance with follow-up, lesion-directed testing, or urgent systemic investigation.
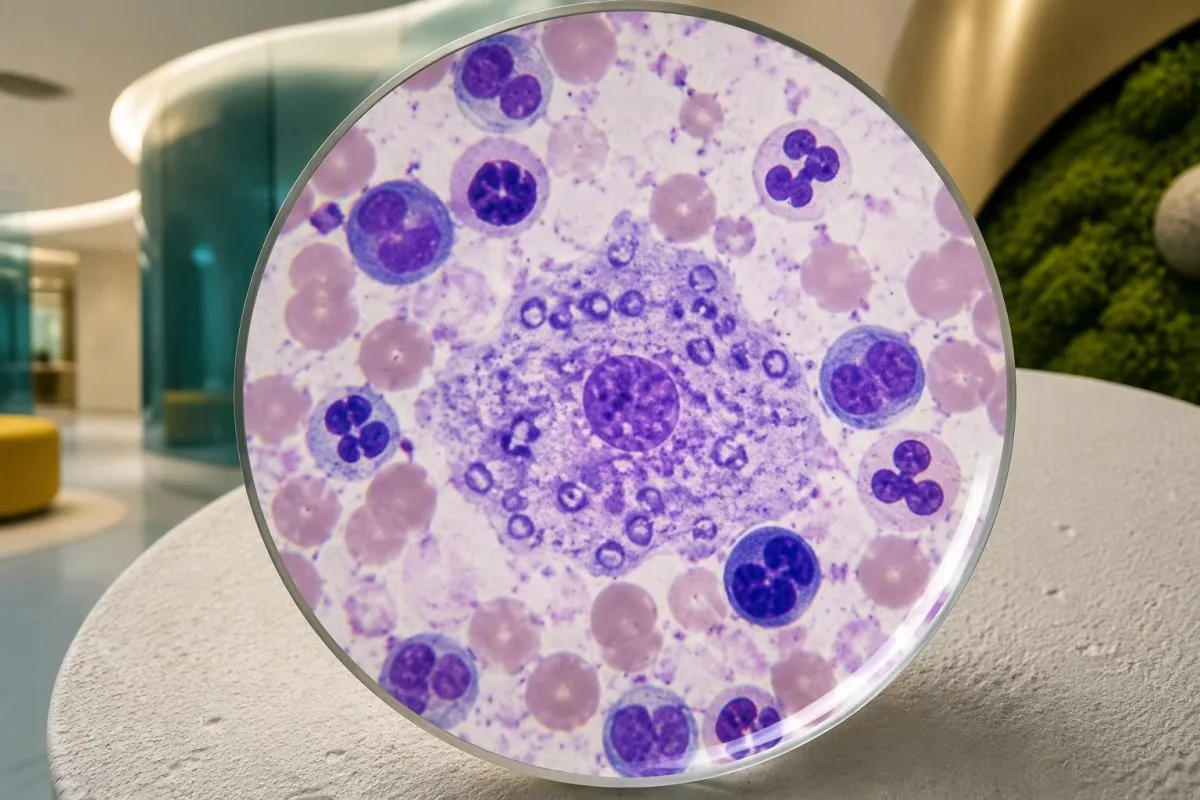
Example 1: a hypothetical 42-year-old completed treatment for visceral leishmaniasis 3 years ago, feels well, and has stable blood counts but a persistently positive antibody assay. Persistent antibodies are plausible, so the result alone does not establish relapse or justify retreatment; new fever, weight loss, or immune suppression would change the assessment and might justify direct parasite testing rather than simply checking another antibody titer.
Example 2: a hypothetical 29-year-old has an 8-week skin lesion after travel, normal routine blood tests, and a weakly positive antibody result. The affected skin still needs appropriate PCR, microscopy, or histology because serology neither confirms its cause nor identifies the species; our limits of fever antibody tests describes a parallel diagnostic pitfall, not a reason to apply typhoid testing rules to leishmaniasis.
Example 3: a hypothetical 58-year-old taking transplant medicines develops fever, spleen enlargement, platelets of 45 × 10^9/L, and a negative antibody test. At Kantesti, we explain why that negative result cannot cancel the clinical concern: immune suppression can impair antibody responses, and prompt clinician-led PCR or tissue evaluation may be necessary; these examples are teaching scenarios, not patient encounters or substitutes for individualized medical advice.
Betyr et positivt resultat at behandling eller ny testing er nødvendig?
A positive result does not automatically mean treatment, and successful treatment does not require antibodies to become negative. Confirmed visceral disease generally needs systemic therapy; cutaneous management depends on species, site, lesion burden, mucosal risk, immune status, and the likelihood of spontaneous healing.

Untreated visceral leishmaniasis can be life-threatening, so compatible illness with convincing diagnostic evidence needs specialist management rather than watchful waiting based on a low antibody index. By contrast, some uncomplicated cutaneous presentations may be observed or treated locally, while others need systemic treatment; a single 1-cm lesion on a cosmetically sensitive site can require a different approach from a similarly sized lesion elsewhere.
When systemic therapy is selected, safety monitoring may include at least 3 groups of measurements: kidney function, electrolytes, and liver tests, alongside the CBC when indicated by the medicine and illness. Liposomal amphotericin B, for example, can affect renal function and potassium or magnesium; our veileder for medikamentsikkerhetstrender explains why changes from baseline can matter even before an isolated value crosses a reference limit.
Kantesti er en AI-blodprøvetolkningsplattform that can help explain these follow-up trends, but treatment success is assessed through clinical recovery and clinician-selected testing rather than AI confirmation of cure. The IDSA/ASTMH guideline recommends monitoring treated cutaneous lesions for 6–12 måneder for evidence of therapeutic failure (Aronson et al., 2016); visceral follow-up and relapse surveillance must be individualized, especially when immune suppression increases ongoing risk.
Forskningspublikasjoner og grensene for AI-tolkning
AI interpretation supports explanation; it does not confirm leishmaniasis or validate a parasite assay. Disease-specific diagnostic recommendations come from clinical guidelines and test-accuracy evidence, while technical research about an interpretation engine answers separate questions about structured output, evaluation methods, and oversight.

The Kantesti technical benchmark listed below evaluates the blood-test interpretation engine using 100 000 syntetiske testtilfeller, as stated in its publication title. Synthetic-case performance must not be presented as prospective diagnostic accuracy for leishmaniasis, proof of PCR sensitivity, or evidence that treatment decisions are safe without a clinician; our rammeverk for medisinsk validering describes the evaluation and oversight context rather than replacing disease-specific evidence.
Det Klinisk valideringsrammeverk v2.0 publication describes a framework for assessment and clinical oversight; it is not, by its title or purpose, a clinical trial demonstrating leishmaniasis outcomes. Our standarder for medisinsk innhold separate technical validation, clinical evidence, and educational writing, so readers can judge each claim against the type of evidence actually supporting it rather than treating a DOI as a guarantee of clinical utility.
For a positive leishmaniasis report, the most useful next step is a clinician-led review of 4 nødvendige opplysninger: the assay, the specimen, the exposure history, and the current clinical picture. Kantesti can help explain routine laboratory patterns during that process, but an urgent symptom takes priority over any upload or repeat antibody test; the references below distinguish external leishmaniasis guidance from publications about our interpretation methodology.
Ofte stilte spørsmål
Betyr en positiv antistofftest for leishmaniasis at jeg har aktiv leishmaniasis?
Et positivt antistoffresultat for leishmaniasis fastslår ikke i seg selv at det foreligger aktiv leishmaniasis, fordi antistoffer kan vedvare etter en tidligere infeksjon eller forekomme ved asymptomatisk eksponering eller kryssreaktivitet. Et resultat som fortsatt er positivt 2 år etter vellykket behandling, kan derfor gjenspeile immunologisk hukommelse snarere enn tilbakefall. Klinikere vurderer symptomer, reisehistorikk, immunstatus og den nøyaktige testen, og bruker deretter PCR, mikroskopi, dyrkning eller vevsundersøkelser når det er hensiktsmessig. Vedvarende feber, vekttap eller forstørret milt bør vurderes raskt av lege.
Hvor nøyaktig er rK39-testen for leishmaniasis?
Nøyaktigheten til hurtigtester for rK39 varierer med geografi, produkt og pasientgruppe. En Cochrane-oversikt fra 2014 anslo sensitiviteten til rundt 97,0 % på det indiske subkontinentet og 85,3 % i Øst-Afrika blant personer som ble undersøkt for mistanke om visceral leishmaniasis. Disse tallene beskriver ikke ytelsen ved asymptomatisk screening, lokalisert kutan sykdom eller i alle immunsupprimerte pasientgrupper. En negativ test bør ikke avslutte utredningen når den kliniske mistanken fortsatt er høy.
Kan en PCR-test for leishmaniasis være positiv uten symptomer?
En PCR-test for leishmaniasis kan påvise parasitt-DNA hos noen personer uten symptomer, så et positivt resultat bekrefter ikke automatisk symptomgivende sykdom eller et behov for behandling. Tolkningen avhenger av minst 3 faktorer: prøvemateriale, aktuelle kliniske funn og tidligere behandling eller eksponering. PCR påviser DNA i stedet for å bevise at parasitten er levedyktig. Klinikere kan innhente ytterligere dokumentasjon når påvisningen er svak, uventet eller ikke stemmer overens med det kliniske bildet.
Kan en blodprøve diagnostisere kutan leishmaniasis?
En blodantistofftest er vanligvis ikke tilstrekkelig til å bekrefte kutan leishmaniasis, fordi en lokalisert hudsykdom kan føre til at det produseres lite sirkulerende antistoff. En vedvarende hudlesjon – for eksempel en som varer i 8 uker etter en relevant reise – må vanligvis undersøkes ved testing av materiale fra det berørte området. PCR, mikroskopi, dyrkning eller histologi kan gi mer direkte bevis og bidra til å vurdere alternative årsaker. Artsbestemmelse kan også påvirke behandlingen og vurderingen av senere risiko for slimhinneaffeksjon.
Kan antistoffer mot leishmaniasis forbli positive etter behandling?
Antistoffer mot leishmaniasis kan forbli positive i flere år etter vellykket behandling, så det er ikke et pålitelig krav for helbredelse at antistoffene forsvinner. Et positivt resultat 3 år etter behandling kan ikke fastslå tilbakefall uten forenlige symptomer eller ytterligere holdepunkter. Klinisk bedring og laboratorieprøver eller parasittundersøkelser valgt av legen ligger til grunn for oppfølgingen. Personer som senere blir immunsupprimerte, kan trenge en annen vurdering av tilbakefall fordi tidligere eksponering fortsatt kan være relevant.
Når bør et positivt leishmaniasisresultat føre til at man oppsøker lege umiddelbart?
Et positivt leishmaniasisresultat krever en snarlig medisinsk vurdering dersom det ledsages av vedvarende feber, vekttap, forstørret milt eller betydelig fall i blodcelletallene. Forvirring, alvorlig tungpust, besvimelse, betydelig blødning eller problemer med luftveiene krever en akutt medisinsk vurdering uavhengig av prøveresultatet. Feber med et absolutt nøytrofiltall under 0.5 × 10^9/L er en akuttsituasjon, og blodplatetall under 20 × 10^9/L krever vanligvis snarlig vurdering av helsepersonell. Nye, vedvarende symptomer fra nese, munn eller svelg etter en forenlig eksponering bør også undersøkes med tanke på slimhinnesykdom.
Få forklart blodprøveresultatene dine
Last opp laboratorierapporten din, så forklarer AI-en til Kantesti hver biomarkør på et lettfattelig språk i løpet av sekunder. Brukt av mer enn 2 millioner mennesker verden over.
References
- Klein, T., Mitchell, S., & Weber, H. (2026). En forhåndsregistrert, rubrikkbasert automatisert teknisk benchmark av Kantesti-blodprøvetolkningsmotoren på 100 000 syntetiske testtilfeller. Kantesti AI medisinsk forskning. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Klinisk valideringsrammeverk v2.0 (side for medisinsk validering). Kantesti AI medisinsk forskning. DOI
- Aronson N et al. (2016). Diagnosis and Treatment of Leishmaniasis: Clinical Practice Guidelines by the Infectious Diseases Society of America (IDSA) and the American Society of Tropical Medicine and Hygiene (ASTMH). Clinical Infectious Diseases. DOI
- Boelaert M et al. (2014). Rapid tests for the diagnosis of visceral leishmaniasis in patients with suspected disease. Cochrane Database of Systematic Reviews. DOI
- 2M+Analyserte prøver
- 127+Countries
- 100+Språk
Om det medisinske teamet


E-E-A-T tillitssignaler
Experience
Klinisk gjennomgang ledet av lege av arbeidsflyter for laboratorietolkning.
Expertise
Fagområde laboratoriemedisin med fokus på hvordan biomarkører oppfører seg i klinisk kontekst.
Authoritativeness
Medisinsk gjennomgått av Dr. Thomas Klein, med bidrag fra Dr. Sarah Mitchell og Prof. Dr. Hans Weber.
Trustworthiness
Evidensbasert tolkning med tydelige oppfølgingsveier for å redusere uro.






Medisinsk ansvarsfraskrivelse
Denne artikkelen er kun for informasjonsformål og utgjør ikke medisinsk rådgivning. Rådfør deg alltid med en kvalifisert helsepersonell for beslutninger om diagnose og behandling.
Publisert · Kontakt redaksjonen
Publisert av Kantesti Ltd, registrert i England og Wales, selskapsnr. 17090423, London, Storbritannia.
