Low seven-day SeHCAT retention supports bile acid diarrhea: commonly used bands are below 5% severe, 5–under 10% moderate, and 10–under 15% mild. These percentages guide treatment discussions, but do not measure symptom severity or identify the underlying cause on their own.

Pokok-pokok penting
- Low retention below 15% at seven days commonly supports bile acid diarrhea in someone with compatible symptoms; the reporting center's cutoff takes priority.
- Jalur tingkat keparahan commonly classify below 5% as severe, 5–under 10% as moderate, and 10–under 15% as mild bile acid loss—not necessarily mild or severe symptoms.
- Normal retention of 15% or above usually makes significant bile acid loss less likely, but does not exclude microscopic colitis, celiac disease, pancreatic problems, or other diarrhea causes.
- Pangobatan usually involves clinician-supervised bile acid sequestrants; cholestyramine may start at 2–4 g daily and requires individualized adjustment.
- Serum C4 means 7α-hydroxy-4-cholesten-3-one when investigating diarrhea; it is not complement C4, the immune-system protein.
- Alternative testing includes fasting serum C4 and specialist fecal bile acid measurement, often collected over 48 hours where SeHCAT is unavailable.
- Cholestasis testing uses a different pathway: ALP, GGT, bilirubin, and sometimes serum total bile acids investigate impaired bile flow rather than intestinal bile acid loss.
- Keamanan depends on medication spacing, triglyceride review, and the extent of ileal surgery; a very low percentage alone is not an emergency.
What low SeHCAT retention means for your symptoms
Low SeHCAT retention means your body retained less of a radiolabeled bile acid tracer after seven days. A result below 15% commonly supports bile acid diarrhea when persistent watery stools fit the clinical picture; lower percentages indicate greater tracer loss, not automatically a more dangerous illness.
Bile acid diarrhea develops when excess bile acids reach the colon and increase fluid secretion and movement through the bowel. A seven-day retention result of 4%, for example, supports substantial bile acid loss, but cannot distinguish impaired ileal absorption from excessive bile acid production without the clinical history.
For a hypothetical adult with six watery stools daily and 8% retention, the result gives a clinician a plausible treatment target rather than simply another abnormal number. Recording stool consistency with the Bagan feses Bristol helps separate fewer bowel movements from genuinely firmer stools, reduced urgency, and improved ability to leave home.
Kantesti iku sawijining Analisa tes getih AI that can help explain accompanying laboratory results, while a seven-day SeHCAT scan requires interpretation by the nuclear medicine and gastroenterology teams. Our lan tujuan are separate from that diagnostic service: we do not perform SeHCAT scans, establish the underlying cause, or prescribe treatment.
How the seven-day SeHCAT percentage is measured
SeHCAT retention compares an initial measurement of a swallowed selenium-75-labeled bile acid tracer with a repeat measurement approximately seven days later. Nuclear medicine staff correct the readings for background activity and radioactive decay, so the reported percentage estimates biological retention rather than simple scanner counts.

SeHCAT is not a blood test. Most protocols involve swallowing a capsule, taking an initial measurement after a locally specified interval, and returning seven days later; the camera detects emitted radiation rather than taking a conventional photograph of the bowel, and a colonoscopy or stool collection is not normally part of this particular test.
A hypothetical corrected baseline of 10,000 counts and a corrected day-seven measurement of 800 counts would produce 8% retention: 800 divided by 10,000, multiplied by 100. The word corrected matters—dividing two raw numbers from a report can give the wrong answer if background, acquisition duration, positioning, or decay adjustments differ.
Bile acid sequestrants can interfere with tracer recycling, so the testing center may ask for a temporary pause before the capsule and during the seven-day interval. Follow its exact instructions rather than stopping medicines independently; share your pola gejala pencernaan, previous intestinal surgery, pregnancy possibility, and breastfeeding status before testing.
SeHCAT retention percentages: common severity thresholds
Common seven-day SeHCAT thresholds are below 5% for severe loss, 5–under 10% for moderate loss, and 10–under 15% for mild loss. Retention of 15% or above is generally not supportive of significant bile acid loss, although diagnostic boundaries and reporting terminology vary between centers.
Ing British Society of Gastroenterology guideline describes the familiar 5%, 10%, and 15% boundaries and their relationship to treatment response (Arasaradnam et al., 2018). These thresholds are practical categories drawn from clinical evidence, not biological cliffs; there is no abrupt switch in bowel function between an otherwise comparable result of 9.9% and 10.1%.
A hypothetical 12% result commonly falls in the mild-loss band, while 3% falls in the severe-loss band. Someone at 12% may still experience disabling urgency or incontinence, whereas another person at 3% may report fewer stools because diet, bowel anatomy, medication, and other conditions modify how tracer loss translates into symptoms.
Exactly 5%, 10%, or 15% may be handled differently if a center uses inclusive boundaries or reports rounded percentages. Ask which cutoff your service applies and whether the displayed number was rounded; our explanation of asil sing ngluwihi wates shows why a laboratory flag and a clinical diagnosis are not interchangeable.
| Tingkat | Rentang | Tegesé |
|---|---|---|
| Generally not supportive | ≥15% retained at seven days | Significant bile acid loss is less likely under commonly used criteria; other diarrhea causes may still need investigation. |
| Mild bile acid loss | 10% to <15% retained | Supports mild loss in a compatible clinical setting; symptoms can still be substantial. |
| Moderate bile acid loss | 5% to <10% retained | Supports a bile acid contribution and a clinician-supervised treatment discussion. |
| Severe bile acid loss—not an emergency category | <5% retained | Indicates marked tracer loss; assess the cause, nutritional context, and suitability of bile acid-binding treatment. |
What a low or normal SeHCAT result cannot prove
A low SeHCAT result supports abnormal bile acid handling, but does not prove that bile acids explain every symptom. A result of 15% or above usually argues against substantial bile acid loss under common criteria, yet it cannot rule out other causes of persistent diarrhea.
Two conditions can coexist: an adult might have 7% retention and microscopic colitis, celiac disease, or a medication-related problem. Improvement with a sequestrant can identify a treatable bile acid component without resolving the second condition; persistent symptoms therefore deserve reassessment rather than an assumption that the original scan must have been wrong.
A normal 22% result does not explain greasy, bulky stools, especially when weight loss or pancreatic risk factors accompany them. A fecal fat assessment addresses fat malabsorption rather than bile acid retention, and clinicians may add fecal elastase or imaging when the history suggests pancreatic insufficiency.
Rapid transit can alter stool appearance without proving a bile acid disorder; visible food fragments and yellow stool are not substitutes for a seven-day retention measurement. Our guide to panganan sing durung dicerna ing tinja explains when appearance is nonspecific and when associated weight loss, nutritional abnormalities, or persistent changes make further investigation more useful.
Why bile acid retention can be low
Low SeHCAT retention can result from terminal ileal disease or surgery, disturbed feedback that increases bile acid production, or secondary changes after other gastrointestinal conditions. A result below 5% does not identify which mechanism applies; the operative history and associated symptoms often provide the most useful clues.
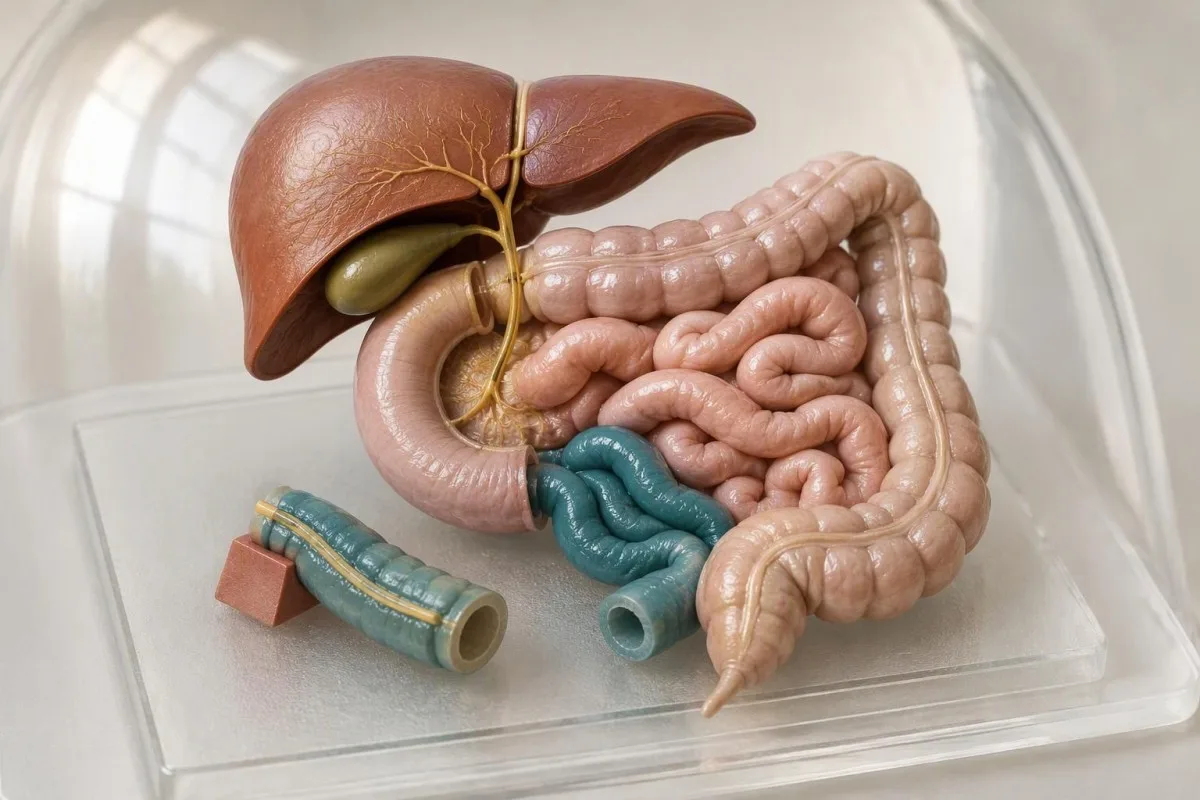
Primary bile acid diarrhea can occur without visible ileal damage because feedback signals fail to restrain liver bile acid synthesis adequately. Wedlake et al. (2009) found abnormal SeHCAT retention below 10% in about 32% of selected diarrhea-predominant IBS study participants; that pooled estimate describes investigated populations, not a screening probability for every person with loose stools.
Terminal ileal Crohn's disease or removal of that segment can reduce recycling directly, whereas diarrhea after gallbladder removal may reflect altered bile delivery and handling rather than intestinal damage. For a hypothetical person with 6% retention after surgery, the clinician should establish whether the operation removed the gallbladder, the terminal ileum, or both before selecting treatment.
Extensive ileal resection—often discussed around lengths exceeding 100 cm—can deplete the bile acid pool and cause fat malabsorption, making sequestrants counterproductive in some patients. The operative details matter more than a rigid length rule; vitamin B12 ing wates deserves attention because the terminal ileum also has a distinct role in B12 absorption.
Which other tests belong in a bile acid diarrhea workup?
A bile acid diarrhea diagnosis usually requires a symptom history, medication review, and targeted checks for other causes—not SeHCAT alone. Persistent watery diarrhea lasting more than four weeks commonly prompts consideration of celiac testing, stool inflammation markers, and selected infection tests, with endoscopy determined by the clinical picture.
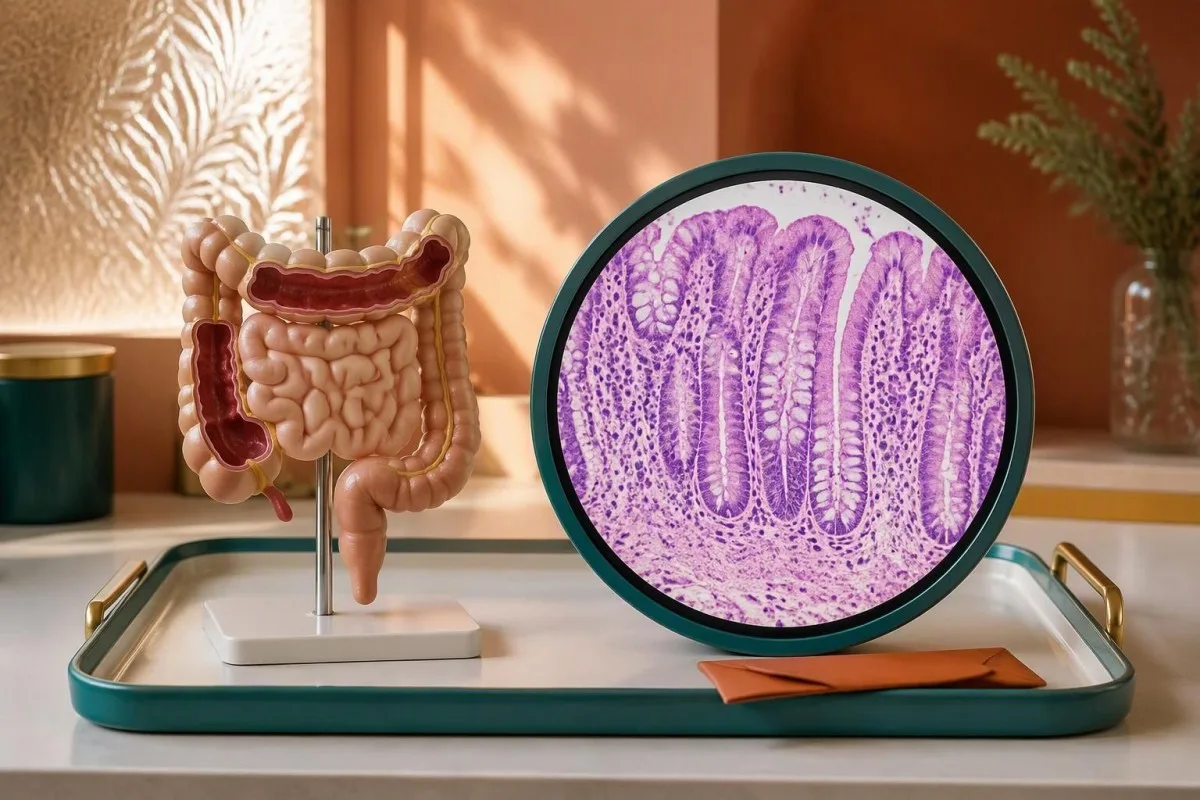
Fecal calprotectin and lactoferrin assess intestinal inflammatory activity; neither measures bile acid loss. A hypothetical adult with 8% retention and elevated stool inflammation markers may need assessment for an accompanying inflammatory condition, while normal markers do not reliably exclude microscopic colitis; our stool inflammation test comparison nerangake bedane kasebut.
Celiac screening commonly combines tissue transglutaminase IgA with total IgA while the person is eating gluten, because a restricted diet or IgA deficiency can undermine interpretation. The BSG guideline also recommends right- and left-sided colon samples when excluding microscopic colitis in chronic diarrhea, even if the colon looks normal during examination (Arasaradnam et al., 2018).
Travel, untreated water exposure, or a relevant outbreak may justify targeted infection testing rather than an indiscriminate panel. In a hypothetical person with four weeks of diarrhea after camping, a Giardia antigen result could change the treatment plan; a low SeHCAT percentage should not distract from a second, independently treatable explanation.
Serum C4 for diarrhea is not complement C4
Serum C4 for bile acid diarrhea means 7α-hydroxy-4-cholesten-3-one, a marker of liver bile acid synthesis. Complement C4 is a different immune-system protein, usually reported in g/L or mg/dL; a complement C4 result cannot substitute for the specialized diarrhea investigation.

Sing luwih dhuwur 7α-hydroxy-4-cholesten-3-one result supports increased bile acid synthesis, which can accompany excessive intestinal bile acid loss. The BSG guideline discusses a threshold above 47.1 ng/mL, while some laboratories use approximately 52.5 ng/mL or their own validated boundaries; these are assay-specific decision limits, not a universal normal range (Arasaradnam et al., 2018).
Sampling usually requires a morning fasting specimen because C4 varies with meals and time of day; liver disease and medicines affecting bile acid metabolism can also complicate interpretation. A report saying only C4 0.22 g/L is more consistent with complement testing, so verify the full analyte name with the laboratory and consult our complement C4 explanation.
Kantesti iku sawijining platform interpretasi hasil tes getih AI that explains reported analyte names, units, and reference intervals, rather than treating two tests called C4 as interchangeable. When reviewing a value such as 55 ng/mL, match it to the laboratory's method and fasting instructions; our nuduhake sawetara tandha sing relevan kanggo kinerja ora tau dijaluk. provides context but does not establish bile acid diarrhea.
Alternatives when SeHCAT testing is unavailable
Where SeHCAT is unavailable, fasting serum C4 and specialist fecal bile acid measurement are the main objective alternatives. SeHCAT is not routinely available in the United States; selected laboratories instead offer stool collections over 48 hours, while access to all these investigations varies internationally.

Fecal bile acid testing measures bile acids excreted in stool, not the percentage of a swallowed tracer remaining in the body. One established laboratory approach considers total bile acids above 2,337 µmol/48 hours supportive, with additional criteria based on primary bile acid proportions; use the receiving laboratory's current criteria rather than importing a cutoff from another assay.
Some protocols require approximately 100 g of dietary fat daily for four days, with stool collected during the final 48 hours; this standardized intake can be difficult for someone whose symptoms worsen after fatty meals. Discuss suitability before beginning, because an incomplete collection or a substantially different diet can weaken interpretation and the protocol is not a treatment recommendation.
The Canadian guideline favors objective testing over an empirical sequestrant trial when suitable testing is available, but acknowledges access limitations (Sadowski et al., 2020). FGF19 testing is less standardized for routine care, and a commercial gut microbiome report does not replace SeHCAT, serum C4, or fecal bile acid measurement—even if it lists bile-related organisms.
Bile acid diarrhea testing differs from cholestasis testing
SeHCAT and specialist serum C4 investigate intestinal bile acid handling; cholestasis testing investigates impaired bile formation or flow. ALP, GGT, bilirubin, and sometimes serum total bile acids address the liver-and-bile-duct pathway, so a normal liver panel does not rule out bile acid diarrhea.
A hypothetical adult with 4% SeHCAT retention and normal ALP, GGT, and bilirubin can still have clinically significant bile acid diarrhea. Conversely, an elevated total bile acids result in someone with generalized itching raises different questions; concentration in serum does not tell a clinician how much tracer remains after seven days.
Serum total bile acids are usually reported in µmol/L, whereas specialist serum C4 is commonly reported in ng/mL. These units help reveal that the investigations measure different substances, not different versions of the same result; substituting total bile acids for C4 can send a diarrhea workup down the wrong diagnostic pathway.
A raised ALP accompanied by raised GGT makes a hepatobiliary source more likely than an isolated bone-related ALP rise, but blood tests alone do not locate an obstruction. Our cholestasis laboratory pattern guide explains the next steps; jaundice with fever or severe abdominal pain needs urgent assessment regardless of a previous 8% SeHCAT result.
How SeHCAT results guide clinician-supervised treatment
Low SeHCAT retention often leads to a supervised trial of a bile acid sequestrant, adjusted to symptom response and tolerability. Cholestyramine is commonly started at 2–4 g daily in guideline-described practice; colesevelam or colestipol may be considered when the first option is unsuitable, unavailable, or poorly tolerated.

Bile acid sequestrants bind bile acids in the intestine rather than repairing the ileum. A hypothetical person with 7% retention might begin a clinician-selected low dose and adjust it over subsequent weeks, using stool consistency and urgency as outcomes; immediately escalating because the percentage is low can produce constipation without improving the person's overall function.
The BSG guideline cites historical pooled cholestyramine responses of approximately 96% at retention below 5% and 70% below 15% (Arasaradnam et al., 2018). Those groups overlap and the underlying studies differ, so these figures are not modern head-to-head comparisons or personal success probabilities; the Canadian guideline also emphasizes the generally limited certainty of treatment evidence (Sadowski et al., 2020).
Kantesti AI does not choose a sequestrant or recommend changing a prescribed dose based on a result such as 3% retention. Keeping a dated medicine and symptom record supports a safer follow-up discussion, while our medication monitoring workflow explains how accompanying laboratory trends can inform questions for the prescribing clinician.
Medication spacing, side effects, and treatment safety
Bile acid sequestrants can cause constipation, bloating, and reduced absorption of other medicines. Cholestyramine labeling commonly advises taking other oral medicines at least one hour before or four to six hours afterward; the correct spacing depends on the specific product and the medicine being protected.

Colesevelam does not eliminate interaction risk. Certain interacting medicines and vitamin supplements should be taken at least four hours before it according to product labeling; a pharmacist should review the complete list, especially levothyroxine, warfarin, oral contraceptives, and medicines where modest absorption changes could matter, rather than applying one timing rule to everything.
Sequestrants can raise triglycerides, which is why a lipid review can be relevant even though treatment targets diarrhea rather than cholesterol. Colesevelam is contraindicated by US labeling when triglycerides exceed 500 mg/dL or there is a history of hypertriglyceridemia-induced pancreatitis; our pandhuan tes ulang trigliserida explains how fasting and context affect interpretation.
A typical cholestyramine sachet contains 4 g of active resin, but products and prescribed amounts differ; dry powder should be mixed exactly as instructed rather than swallowed directly. Long-term treatment may justify selective assessment of fat-soluble vitamins, particularly with malabsorption, while persistent constipation, swallowing difficulty, or severe abdominal symptoms should prompt a medication review instead of further dose escalation.
Can diet help when SeHCAT retention is low?
Reducing large fat loads can lessen bile acid diarrhea symptoms in some people, but diet does not replace investigation or supervised treatment. A hypothetical 14-day food-and-symptom record can show whether meal size or fat distribution affects urgency; no single fat target is appropriate for every person with low retention.

Dietary fat stimulates bile delivery, so a large high-fat meal can expose the colon to a greater bile acid load in susceptible people. Small clinical studies suggest that lower-fat approaches can improve symptoms, but evidence for a universal prescription is limited; spreading intake across three meals may be more practical than eliminating every source of fat.
A hypothetical adult with 11% retention might compare two weeks of usual meals with two weeks of smaller, less fatty meals while keeping prescribed treatment stable. That comparison can help identify a personal pattern, but it does not prove the diagnosis, and the high-fat preparation used for some 48-hour fecal tests should not be confused with dietary symptom management.
Extensive ileal disease, restricted intake, and prolonged sequestrant use can increase nutritional concerns, although a low result such as 4% does not automatically mean vitamin deficiency. A dietitian can protect energy and essential fat intake; when vitamin D is actually low, our vitamin D recheck guidance explains why repeat testing follows the deficiency and treatment plan, not the SeHCAT percentage.
Follow-up after treatment and signs that need urgent care
Follow-up should assess stool consistency, urgency, hydration, side effects, and whether another diagnosis remains untreated. A very low SeHCAT result alone is not an emergency; fainting, confusion, severe dehydration, bloody or black tarry stools, or severe abdominal pain require prompt assessment independently of the retention percentage.

A hypothetical change from six watery stools daily to three formed stools is a useful treatment response, even if SeHCAT retention is never remeasured. Routine repeat scanning is usually unnecessary once the diagnosis and treatment direction are established; persistent urgency or nighttime diarrhea matters because a lower stool count can conceal ongoing impairment or a second gastrointestinal condition.
Continued watery losses can disturb sodium, potassium, magnesium, and kidney function, particularly in older adults or people taking diuretics. A hypothetical creatinine rise after three days of poor intake deserves assessment for dehydration rather than automatic labeling as chronic kidney disease; our pandhuan dehidrasi lan eGFR explains why reassessment after recovery may change interpretation.
Kantesti AI can help explain accompanying electrolyte or kidney results, but a previous 6% scan cannot make new warning symptoms safe to ignore. Use our stool color warning guide to understand why visible blood, black tarry stool, or bleeding with dizziness needs clinical attention; oral rehydration solution can help replace losses while appropriate care is arranged.
Research publications and boundaries of AI interpretation
Clinical SeHCAT thresholds and treatment decisions should come from relevant gastroenterology evidence, not from AI performance reports. The 2018 BSG and 2020 Canadian guidelines underpin this article's diagnostic discussion; the two organizational publications listed below describe separate aspects of our blood-test interpretation work.

The two Zenodo references are organizational publications, not independent demonstrations that an AI system can diagnose bile acid diarrhea or interpret nuclear medicine scans accurately. Our validasi lan pengawasan klinis information should be read with that distinction in mind: a technical framework cannot replace the seven-day measurement, the reporting center's method, or a clinician's assessment of competing diagnoses.
Kantesti iku sawijining Piranti analisis tes getih berbasis AI intended to support understanding of laboratory reports, not to replace specialist interpretation of a 5%, 10%, or 15% retention boundary. Our standar konten medis describe the editorial approach behind explanations such as this one, including clear separation of established guidance, hypothetical examples, and areas where evidence remains uncertain.
For a useful appointment, bring five items: the complete SeHCAT report, a current medicine list, details of ileal or gallbladder surgery, a stool-and-urgency record, and any relevant laboratory results. Ask which retention cutoff the service uses, whether testing suggests an underlying condition, how medicines should be spaced, and what response would justify continuing or changing treatment; those questions are more actionable than interpreting the percentage in isolation.
Pitakon sing kerep ditakoni
Pira asil tes SeHCAT sing normal?
Retensi SeHCAT pitung dina 15% utawa luwih umume dianggep ora ndhukung anané ilange asam empedu sing signifikan miturut kriteria sing umum digunakake. Sawetara pusat nggunakake wates diagnostik sing béda, mula interpretasi sing dicithak ing laporan kedokteran nuklir luwih diutamakake. Asil normal ora nyingkirake kolitis mikroskopis, penyakit celiac, insufisiensi pankreas, utawa panyebab diare sing terus-terusan liyane. Gejala sing isih berlangsung tetep mbutuhake pemeriksaan klinis sing cocog.
Apa tegesé asil SeHCAT 3%?
Asil retensi SeHCAT pitung dina 3% kalebu kategori kelangan asam empedu abot sing umum digunakake, yaiku kurang saka 5%. Asil iki ndhukung diagnosis diare asam empedu nalika gejalane cocog, nanging ora ngenali apa penyebabe penyakit ileum, operasi, utawa produksi asam empedu sing owah. Angka iki dhewe dudu kahanan darurat lan ora mesthi nuduhake sepira abote gejala. Perawatan kudu nimbang obat-obatan, status nutrisi, lan sepira amba reseksi ileum sing ditindakake.
Apa malabsorpsi asam empedu ringan bisa menyebabkan diare berat?
0 Ya—retensi ing rentang kehilangan entheng sing umum digunakake, yaiku 10% nganti kurang saka 15%, bisa diiringi diare encer sing abot, rasa kebelet BAB, utawa ora bisa ngendhaleni BAB. Rentang SeHCAT nggambarake retensi tracer, dudu skala beban gejala sing wis divalidasi. Pola mangan, transit usus, obat-obatan, lan kahanan sing kedadeyan bebarengan mengaruhi sepira parah wong kasebut kena dampake. Klinisi kudu netepake fungsi saben dina lan tanggepan marang perawatan, dudu nyepelekake gejala amarga laporan kasebut nyebut entheng.
Apa serum C4 padha karo komplemen C4?
No—serum C4 used for bile acid diarrhea is 7α-hydroxy-4-cholesten-3-one, whereas complement C4 is an immune-system protein. The diarrhea marker is commonly reported in ng/mL, with assay-specific thresholds such as 47.1 or approximately 52.5 ng/mL used by some services. Complement C4 is commonly reported in g/L or mg/dL and cannot diagnose intestinal bile acid loss. Check the full analyte name, fasting instructions, and laboratory reference interval.
What test can replace SeHCAT if it is unavailable?
Fasting serum C4 and specialist fecal bile acid measurement are the main objective alternatives when SeHCAT is unavailable. Some fecal protocols use a 48-hour collection and laboratory-specific criteria, including total bile acids above 2,337 µmol/48 hours. Preparation and interpretation depend on the receiving laboratory, and no alternative matches SeHCAT perfectly. A supervised treatment trial may be considered when suitable testing cannot be accessed, but lack of response does not reliably exclude bile acid diarrhea.
Does cholestyramine not working mean I do not have bile acid diarrhea?
Failure to improve with cholestyramine does not reliably exclude bile acid diarrhea, even after a low SeHCAT result such as 7%. Poor tolerability, an unsuitable dose or schedule, interactions, inconsistent use, and another coexisting diarrhea cause can all affect response. Cholestyramine commonly requires other oral medicines to be taken at least one hour before or four to six hours afterward, subject to product-specific advice. A clinician should review these possibilities before abandoning the diagnosis or changing treatment.
Can normal liver blood tests rule out bile acid diarrhea?
Normal ALP, GGT, and bilirubin do not rule out bile acid diarrhea because liver testing and SeHCAT assess different processes. A person can have normal liver tests and only 4% SeHCAT retention at seven days. Serum total bile acids, usually reported in µmol/L, are also not interchangeable with specialist serum C4 in ng/mL. Itching, jaundice, dark urine, or pale stools may require a separate cholestasis assessment rather than a diarrhea-focused interpretation.
Entuk penjelasan babagan asil tes getih sampeyan
Unggah laporan laboratorium sampeyan lan AI Kantesti bakal nerangake saben biomarker nganggo basa sing prasaja sajrone sawetara detik. Digunakake luwih saka 2 yuta wong ing saindenging donya.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). Clinical Validation Framework v2.0 (Halaman Validasi Medis). Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2.5M Tes Didhaptar | Laporan Kesehatan Global 2026. Riset Medis AI Kantesti. DOI
- Arasaradnam RP et al. (2018). Guidelines for the investigation of chronic diarrhoea in adults: British Society of Gastroenterology, 3rd edition. Gut. DOI PubMed
- Sadowski DC et al. (2020). Canadian Association of Gastroenterology Clinical Practice Guideline on the Management of Bile Acid Diarrhea. Clinical Gastroenterology and Hepatology.
- Wedlake L et al. (2009). Systematic review: the prevalence of idiopathic bile acid malabsorption as diagnosed by SeHCAT scanning in patients with diarrhoea-predominant irritable bowel syndrome. Alimentary Pharmacology & Therapeutics.
- 2M+Tes sing dianalisis
- 127+negara-negara
- 100+Basa
Babagan tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis sing dipimpin dokter babagan alur kerja interpretasi lab.
Keahlian
Fokus kedokteran laboratorium babagan carane biomarker tumindak ing konteks klinis.
Kewibawaan
Ditinjau sacara medis dening Dr. Thomas Klein, kanthi kontribusi saka Dr. Sarah Mitchell lan Prof. Dr. Hans Weber.
Kapercayan
Interpretasi adhedhasar bukti kanthi tindak lanjut sing cetha kanggo nyuda rasa kaget.






Sanggahan medis
Artikel iki mung kanggo tujuan edukasi lan ora dadi saran medis. Tansah konsultasi karo panyedhiya layanan kesehatan sing mumpuni kanggo keputusan diagnosis lan perawatan.
Diterbitake · Hubungi tim editorial
Diterbitake dening Kantesti Ltd, kadhaptar ing Inggris & Wales, nomer perusahaan. 17090423, London, Britania Raya.
