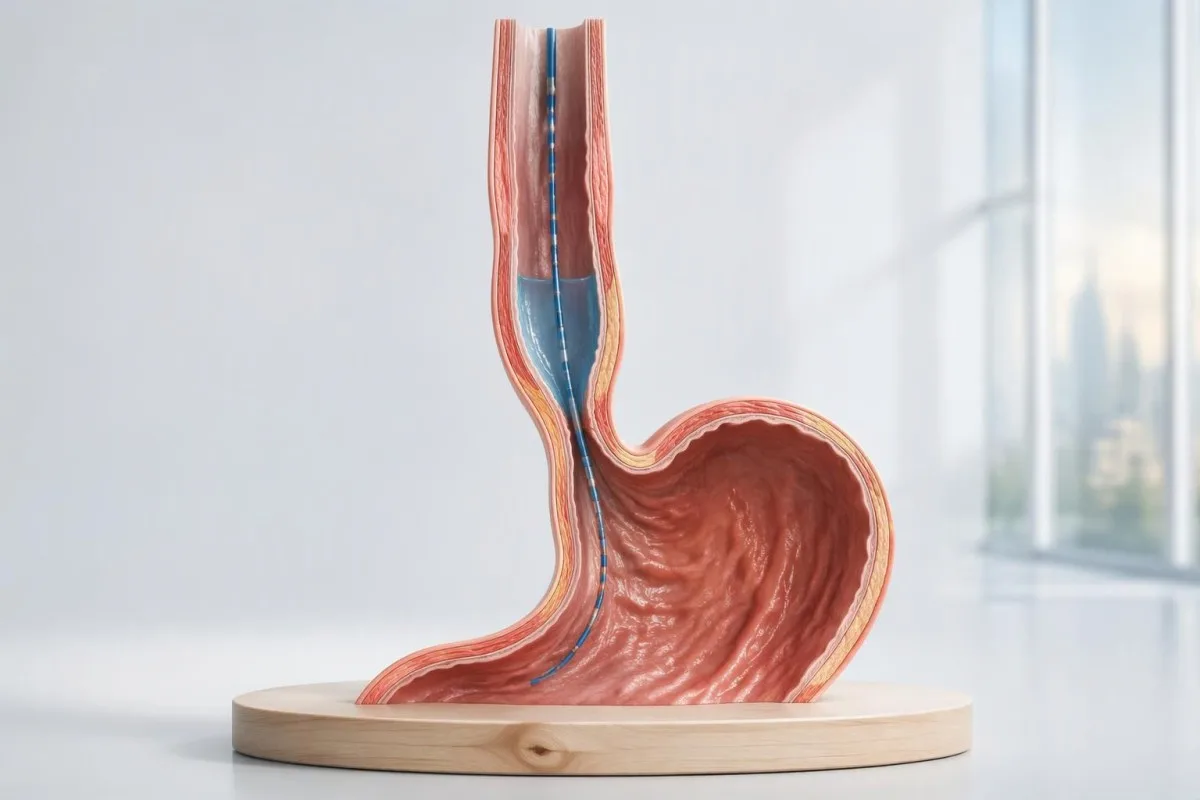
A high pressure reading alone does not establish achalasia. The diagnosis depends on how the esophageal outlet relaxes, whether swallows generate coordinated contractions, and whether another condition explains the pattern.

要点
- Achalasia diagnosis usually requires high-resolution manometry showing impaired outlet relaxation and no normal esophageal peristalsis; endoscopy checks for a mechanical explanation.
- Integrated relaxation pressure measures outlet relaxation over a 4-second window, but its upper limit depends on the equipment and body position.
- Type I achalasia shows 100% failed peristalsis without the panesophageal pressurization required for type II.
- Type II achalasia shows 100% failed peristalsis and panesophageal pressurization in at least 20% of test swallows.
- Type III achalasia shows premature contractions in at least 20% of swallows, impaired outlet relaxation, and no normal peristalsis.
- Premature contraction generally means distal latency below 4.5 seconds with sufficient contraction strength; rapid-looking colors alone do not prove spasm.
- Borderline findings may require a timed barium esophagram or FLIP assessment; an isolated elevated pressure is not enough to justify an irreversible treatment.
- Treatment discussions differ by subtype: type III often favors a longer, tailored myotomy, while types I and II have several effective options.
- 血液検査 can assess dehydration, anemia, or nutritional complications, but no routine laboratory panel confirms or excludes achalasia.
How is achalasia diagnosed with high-resolution manometry?
Achalasia diagnosis usually rests on high-resolution manometry showing impaired esophageal outlet relaxation and absent normal peristalsis. Type I has failed contractions, type II adds whole-esophagus pressurization in at least 20% of swallows, and type III adds premature contractions in at least 20%; endoscopy helps exclude an obstruction.
High-resolution manometry, or HRM, measures pressure rather than directly filming food movement. Its 2 central questions are whether the esophagogastric junction opens appropriately during swallowing and whether the esophageal body generates an organized wave; a high resting sphincter pressure by itself answers neither question and does not establish achalasia.
The Chicago Classification version 4.0 defines the manometric patterns used to identify the 3 achalasia subtypes, while symptoms and other investigations establish their clinical meaning (Yadlapati et al., 2021). A report that simply says motility disorder is less informative than one documenting integrated relaxation pressure, peristaltic findings, testing position, and the final classification.
カンテスティは AI血液検査分析装置 that can help explain laboratory consequences of poor intake, but none of the 3 achalasia subtypes can be diagnosed from a blood panel. Information about 組織では should be read separately from the specialist assessment needed to interpret manometry and exclude structural disease.
Which swallowing symptoms should prompt achalasia testing?
Difficulty swallowing both solids and liquids, regurgitation of retained food, and unexplained weight loss should prompt evaluation for achalasia. Symptoms alone cannot determine the diagnosis or distinguish its 3 subtypes; even a convincing history needs testing because obstruction, reflux-related disease, and other swallowing disorders can overlap.
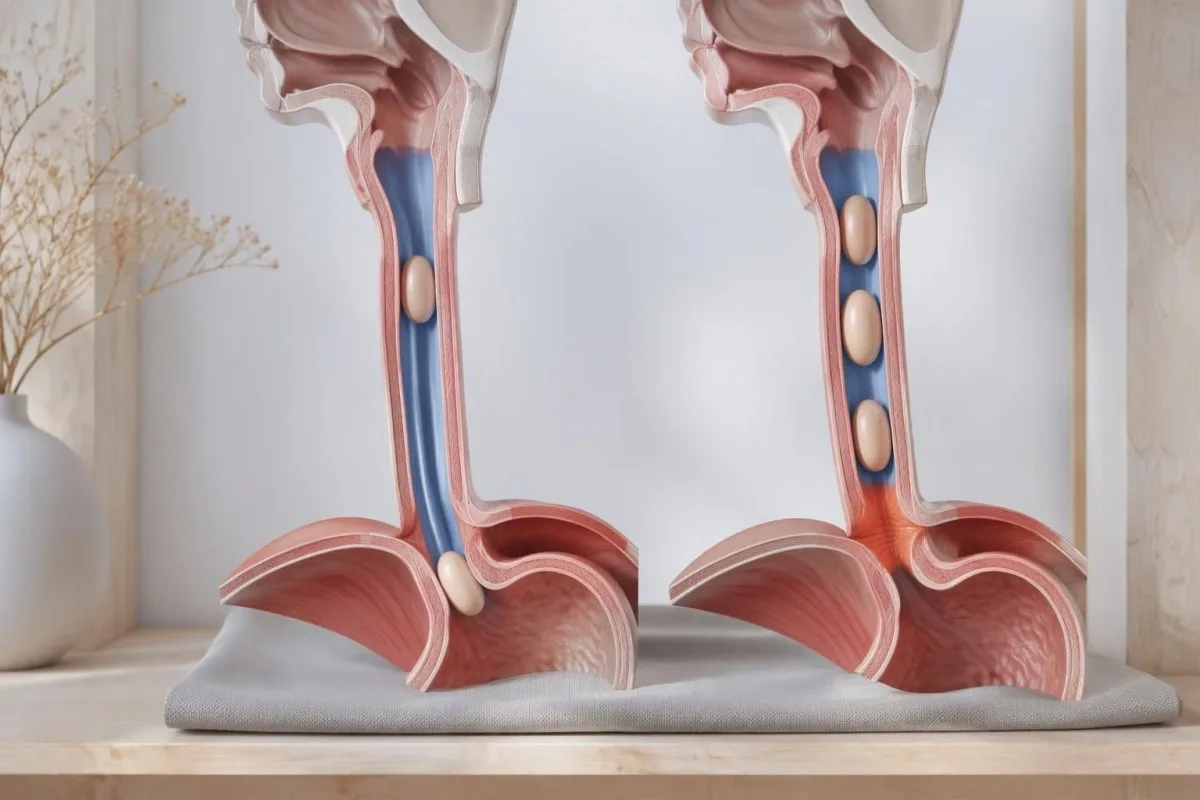
Regurgitation in achalasia can contain food eaten several hours earlier, whereas acid reflux more often brings sour fluid upward. This distinction helps explain why prolonged treatment for reflux-like symptoms may not resolve swallowing trouble; however, these 2 processes can coexist, and symptom descriptions cannot reliably separate them without investigation.
Difficulty initiating a swallow points toward a different location than food sticking several seconds after swallowing. Coughing immediately with a sip, a nasal voice, or fatigable swallowing can warrant an oropharyngeal or neurological assessment; 重症筋無力症検査の限界 are relevant when weakness accompanies symptoms, not as a routine achalasia screening panel.
An inability to swallow saliva or a suspected food impaction requires urgent assessment rather than waiting for elective manometry. Repeated nighttime regurgitation also raises concern for aspiration; for a hypothetical person losing 6 kg while meals become progressively slower, the weight trajectory and swallowing history both deserve attention even if routine laboratory results remain within range.
What happens during an esophageal manometry test?
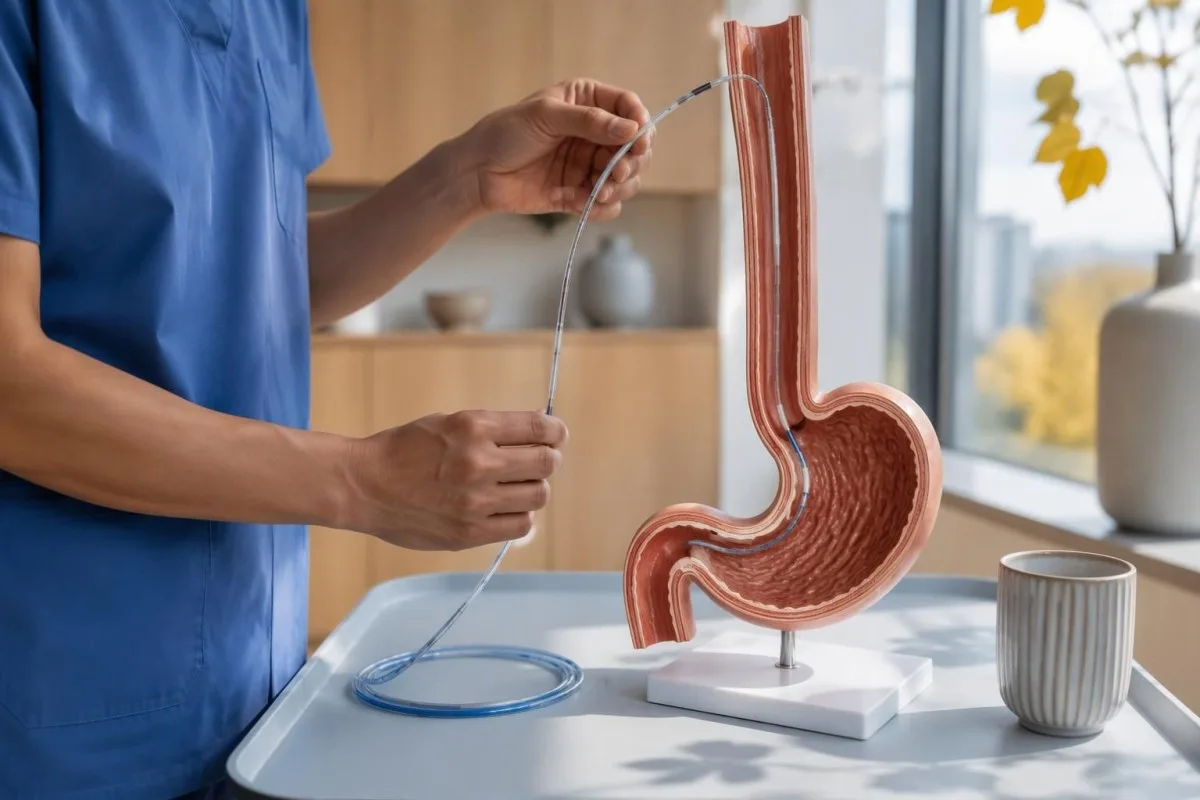
Esophageal manometry usually involves passing a thin pressure-sensing catheter through the nose into the stomach while the patient is awake. A standard Chicago Classification version 4.0 protocol commonly includes 10 supine and 5 upright water swallows, with additional maneuvers that test whether an apparent abnormality persists under different conditions.
Preparation commonly includes at least 6 hours without food, but achalasia can leave material in the esophagus despite ordinary fasting. The testing center may therefore give a longer fasting or modified-diet plan; follow its instructions rather than assuming that an empty stomach guarantees an empty esophagus, especially if retained food was seen during endoscopy.
Medication review matters because opioids can produce impaired junction relaxation or spastic patterns that resemble type III achalasia. Provide the exact medicine, dose, and last-dose time; medication-related laboratory effects are a separate issue, but a single accurate medication list helps both investigations, and prescribed medicines should not be stopped without guidance.
Provocative testing may include 5 closely spaced 2 mL swallows or a rapid drink challenge of about 200 mL, if safe and appropriate. These maneuvers test different aspects of relaxation and contraction reserve; when standard swallows conflict with symptoms, their results can reveal a reproducible obstruction pattern or expose an artifact that disappears after changing position.
Which esophageal manometry results matter most?
最も有用なのは esophageal manometry results are median integrated relaxation pressure, the presence or absence of peristalsis, panesophageal pressurization, and distal latency. These measurements answer different questions: outlet opening, coordinated propulsion, pressure trapped within the esophagus, and contraction timing; none should be interpreted as an isolated severity score.
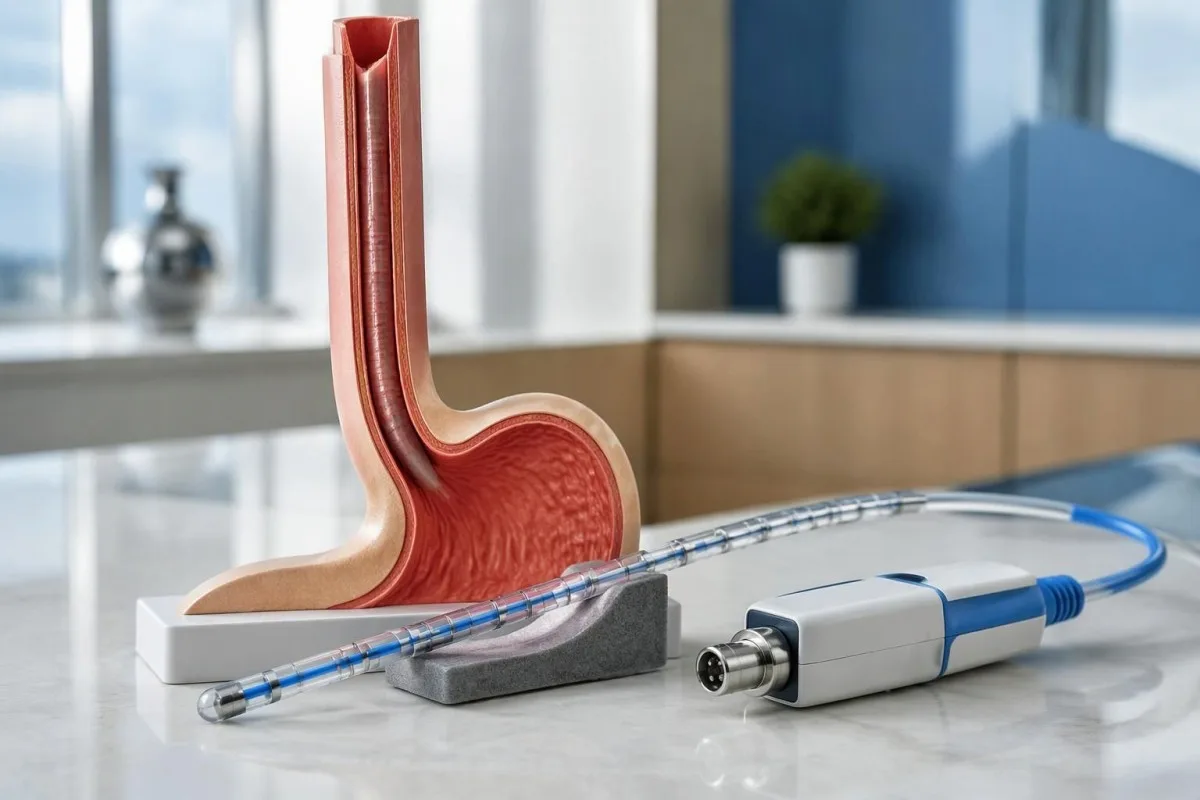
Integrated relaxation pressure, or IRP, summarizes junction pressure over a 4-second relaxation window within the post-swallow assessment period. It is not simply the lowest pressure reached, and its threshold changes with catheter system and posture; Chicago Classification version 4.0 gives different reference limits for commonly used systems rather than one universal 15 mmHg rule (Yadlapati et al., 2021).
Distal contractile integral, or DCI, combines contraction strength, duration, and length, using mmHg·s·cm. A failed swallow has DCI below 100 mmHg·s·cm; a sufficiently strong premature contraction generally requires DCI of at least 450 mmHg·s·cm, so a faint, early pressure blip should not automatically be classified as the spasm needed for type III.
Kantesti separates measurement units from clinical conclusions: a value in mmHg cannot be compared with a laboratory concentration in ng/mL. Our blood biomarker directory addresses a different measurement category; ask the manometry service which equipment-specific reference limit applies before treating a result such as IRP 17 mmHg as definitely abnormal.
| レベル | 範囲 | 意味 |
|---|---|---|
| Medtronic-system supine IRP | Upper reference limit approximately 15 mmHg | Chicago Classification version 4.0 reference; verify the laboratory's validated system and protocol. |
| Medtronic-system upright IRP | Upper reference limit approximately 12 mmHg | A lower positional limit applies; do not compare an upright result with a supine cutoff. |
| Laborie/Diversatek-system supine IRP | Upper reference limit approximately 22 mmHg | Different equipment can legitimately use a higher reference limit. |
| Laborie/Diversatek-system upright IRP | Upper reference limit approximately 15 mmHg | Interpret alongside peristalsis, symptoms, and supportive testing. |
| Premature contraction timing | Distal latency below 4.5 seconds | Supports a premature contraction when contraction strength is sufficient; does not independently diagnose achalasia. |
| Panesophageal pressurization | Uniform pressure contour at approximately 30 mmHg or above | Whole-esophagus pressurization in at least 20% of swallows helps define type II when the other achalasia criteria are met. |
What does type I achalasia show on manometry?
Type I achalasia shows an abnormal median IRP and 100% failed peristalsis, without the panesophageal pressurization pattern required for type II. The esophageal body does not generate an effective propulsive wave; the absence of strong pressure does not mean that food passes normally or that the condition is mild.
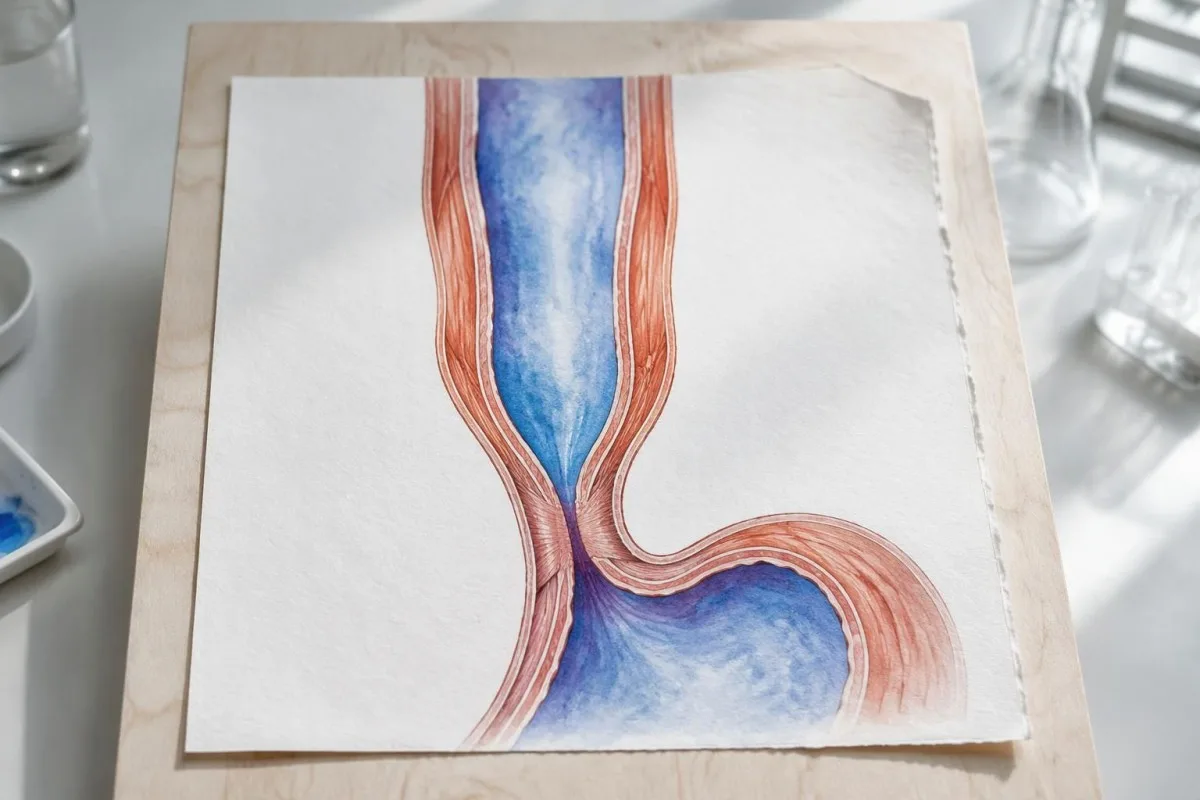
A flat-looking pressure plot can be misleading because failed contractions are not equivalent to successful relaxation. In a technically adequate study, 10 failed supine swallows combined with an elevated median IRP support type I, but the specialist still checks catheter placement, structural findings, and whether pressurization occurred frequently enough to meet type II criteria.
Esophageal dilation can reduce the ability to generate pressure, but type I is not a validated chronological stage that every person reaches after type II. The 3 subtypes describe current physiology rather than a guaranteed disease sequence; duration, esophageal shape, and previous treatment can affect the tracing without providing a reliable clock for when achalasia began.
Nutritional consequences depend on actual intake, not subtype alone. A hypothetical person with type I, declining weight, and ferritin 11 ng/mL needs attention to swallowing treatment and iron-deficiency symptoms; low iron stores do not prove achalasia, while a normal ferritin would not establish that nutrition or esophageal emptying is adequate.
What makes type II achalasia different?
Type II achalasia combines an abnormal median IRP, 100% failed peristalsis, and panesophageal pressurization in at least 20% of swallows. Instead of a coordinated traveling contraction, pressure rises across much of the esophagus at once because swallowed material is compressed against an outlet that does not open adequately.
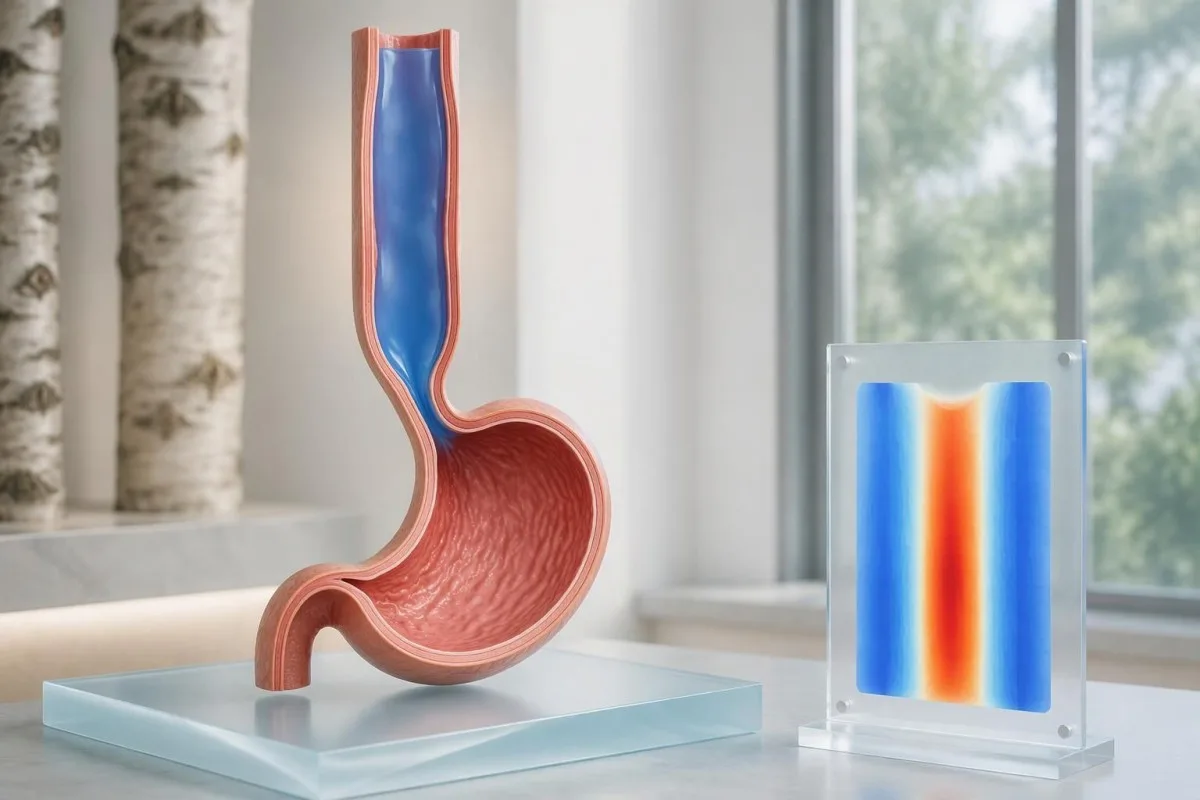
With 10 evaluable swallows, panesophageal pressurization in 2 swallows reaches the 20% threshold. That arithmetic is useful when reading a report, but it should not encourage self-classification from a screenshot: the interpreter must distinguish true pressure trapping from closely spaced swallows, movement artifacts, and pressure attributable to adjacent anatomy.
「 panesophageal pressurization usually refers to a simultaneous pressure contour reaching approximately 30 mmHg across the esophageal body. A bright vertical band on a color map can represent this trapped pressure rather than a strong muscle wave; reading medical report explanations safely means checking the written interpretation rather than assuming warmer colors equal better propulsion.
Type II often has favorable outcomes after pneumatic dilation, Heller myotomy, or POEM, according to the ACG guideline (Vaezi et al., 2020). Nevertheless, the 20% diagnostic threshold is not a treatment-success percentage, and response still depends on anatomy, treatment technique, prior procedures, and follow-up; a subtype should inform discussion, not function as a personal guarantee.
How does manometry identify type III achalasia?
Type III achalasia shows impaired junction relaxation, premature contractions in at least 20% of swallows, and no normal peristalsis. A premature contraction generally has distal latency below 4.5 seconds with adequate DCI; other swallows may fail, so type III does not require every swallow to produce a spasm.

The absence of normal peristalsis separates conclusive type III achalasia from some other spastic patterns. If premature contractions coexist with otherwise preserved peristalsis and junction obstruction, the report may instead describe esophagogastric junction outflow obstruction with spastic features; the same 4.5-second timing cutoff does not erase that diagnostic distinction.
Chest pain can accompany spastic contractions, but it should not automatically be attributed to the esophagus. New severe chest pain, especially with breathlessness, sweating, or exertional onset, needs urgent assessment; chest-pain testing priorities differ from elective manometry, and no single esophageal measurement rules out a cardiac emergency.
Opioid exposure deserves particular scrutiny before an irreversible procedure for an apparent type III pattern. Chicago Classification version 4.0 recommends considering testing off opioids when feasible, with timing based on the medicine's half-life (Yadlapati et al., 2021); a fixed 24-hour pause is not appropriate for every drug, and any change requires the prescribing team's supervision.
How would three hypothetical manometry reports compare?
Hypothetical manometry examples show why an elevated IRP cannot determine the subtype by itself. Using a laboratory with a validated supine upper limit of 15 mmHg, the same median IRP of 24 mmHg could accompany type I, II, or III; the esophageal-body pattern supplies the distinguishing information.

Example 1: a fictional report records median IRP 24 mmHg, DCI below 100 mmHg·s·cm in all 10 swallows, and no panesophageal pressurization. Assuming adequate technique, no structural explanation, and consistent symptoms, this is a type I pattern; the conclusion comes from failed propulsion plus impaired relaxation, not from the pressure value alone.
Example 2: another fictional report records IRP 24 mmHg, failed peristalsis in all 10 swallows, and panesophageal pressurization in 6 swallows. The pressurization frequency is 60%, exceeding the 20% threshold for type II; this does not mean the condition is three times more severe than a report with pressurization in 2 swallows.
Example 3: a fictional study records IRP 24 mmHg, 4 premature contractions with distal latency 3.8 seconds and DCI 900 mmHg·s·cm, and 6 failed swallows, with no normal peristalsis. This supports type III; Kantesti is an AI血液検査の読み方プラットフォーム, そして私たちの 例の解釈ワークフロー concern laboratory information rather than automated classification of these hypothetical motility tracings.
What if the IRP is normal, borderline, or inconsistent?
A normal or borderline IRP does not always exclude achalasia, particularly when peristalsis is absent and symptoms strongly suggest impaired emptying. Conversely, elevated IRP with preserved peristalsis is not automatically achalasia; Chicago Classification version 4.0 requires careful separation of inconclusive achalasia, artifacts, and esophagogastric junction outflow obstruction.
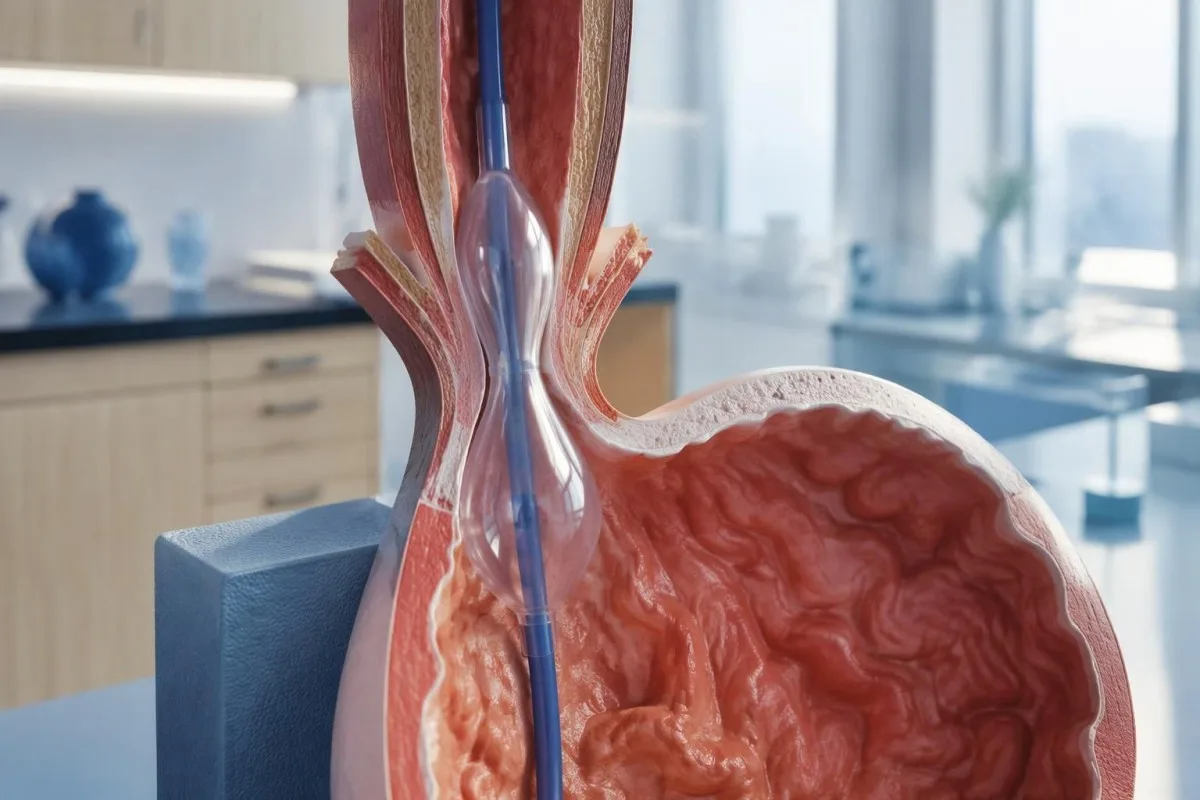
An elevated supine IRP that normalizes upright can reflect catheter contact or distortion around a hiatal hernia. This is one reason the standard protocol uses 2 positions: a reproducible obstruction pattern is more convincing than one abnormal posture-dependent number, although positional disagreement still needs specialist interpretation rather than an automatic normal label.
Esophagogastric junction outflow obstruction, or EGJOO, requires more than a high median IRP. Its manometric criteria include elevated IRP in both positions, preserved peristalsis, and elevated supine intrabolus pressure in at least 20% of swallows; clinically meaningful EGJOO also requires relevant symptoms and supportive evidence of obstruction on timed barium testing or FLIP.
Absent contractility with normal relaxation can occur in systemic sclerosis and is not the same as achalasia; scleroderma-related antibody clues cannot replace motility testing. Kantesti's 臨床的妥当性確認の範囲 should not be extended to these 2 distinct pressure disorders, and an irreversible sphincter procedure should not follow from an unexplained borderline result alone.
Why is endoscopy needed before calling it achalasia?
Upper endoscopy helps exclude a mechanical obstruction or pseudoachalasia, including an obstructing growth at the esophagogastric junction. Manometry can demonstrate an achalasia-like pressure pattern without proving its cause; the ACG guideline recommends endoscopy in suspected achalasia because treatment decisions depend on distinguishing primary motility disease from structural disease (Vaezi et al., 2020).
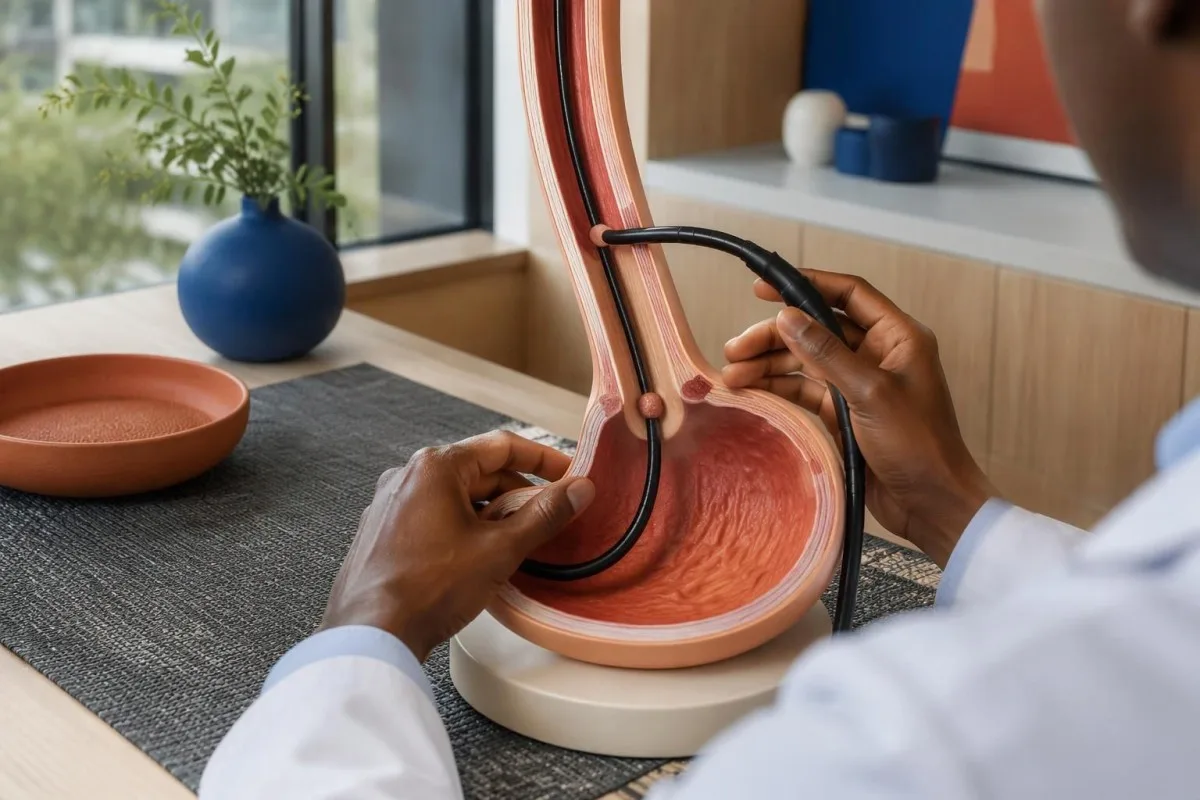
Retained saliva, retained food, and a tight-looking junction can support suspicion of achalasia, but none is diagnostic by itself. Early disease may have an almost normal endoscopic appearance; equally, resistance to passing the scope should not be dismissed as ordinary achalasia without considering whether a second test is needed to inspect the junction more closely.
Rapidly progressive symptoms, substantial short-term weight loss, older age at presentation, and unusual resistance at the junction increase concern for pseudoachalasia. There is no single age or kilogram cutoff that safely excludes it; a hypothetical 68-year-old with 3 months of progressive dysphagia and 9 kg weight loss warrants particular attention to the possibility of a structural cause.
A normal-looking mucosal surface does not always exclude a deeper or externally compressing growth, so CT or endoscopic ultrasound may be appropriate when suspicion persists. Normal CA 19-9 results cannot rule out this concern; ordering 1 tumor marker is not an alternative to imaging, endoscopy, or targeted tissue examination when clinically indicated.
What do timed barium swallowing and FLIP add?
A timed barium esophagram measures esophageal emptying, while FLIP assesses how widely the esophagogastric junction opens under controlled distension. These tests provide information that pressure measurements alone cannot supply; a commonly used timed protocol obtains images at 1, 2, and 5 minutes after a standardized barium swallow.

A standardized upright timed study often uses about 236 mL of barium; column heights above 5 cm at 1 minute or 2 cm at 5 minutes suggest impaired emptying in commonly used protocols. These are protocol-dependent abnormal-emptying thresholds, not stand-alone proof of achalasia, and the classic bird-beak appearance can be absent in early disease.
A 13 mm barium tablet can help reveal restricted passage when liquid contrast empties relatively well, provided the imaging team considers it appropriate. FLIP distensibility index expresses junction cross-sectional area divided by pressure in mm²/mmHg, but balloon volume, sedation, device protocol, and maximum opening diameter affect interpretation; treating every value below 2 as an interchangeable diagnosis would oversimplify the test.
An achalasia-like dilated esophagus does not establish that the disorder is idiopathic. In someone with relevant exposure history, confirmatory Chagas testing may be appropriate because chronic Trypanosoma cruzi infection can affect esophageal innervation; imaging and infection testing answer 2 different questions, namely how the esophagus empties and why its function may be impaired.
How do achalasia manometry types inform treatment?
Achalasia manometry types help clinicians choose how best to reduce resistance at the esophageal outlet. Pneumatic dilation, laparoscopic Heller myotomy, and POEM are established options for types I and II; type III often favors a longer, tailored myotomy that addresses the spastic segment as well as the junction.
The ACG guideline considers pneumatic dilation, Heller myotomy, and POEM comparably effective options for appropriate patients with types I and II, while supporting tailored POEM or Heller myotomy over dilation for type III (Vaezi et al., 2020). The 3 procedures differ in anesthesia needs, recovery, retreatment possibilities, and reflux risk; local expertise and patient preference belong in the decision.
A randomized trial of 221 patients found clinical success at 2 years in 83.0% after POEM and 81.7% after Heller myotomy with Dor fundoplication (Werner et al., 2019). These overall results support both approaches but do not establish identical outcomes for every subtype; type III participants form a much smaller subgroup than the full trial population.
Reflux esophagitis at 2 years occurred in 44% after POEM versus 29% after Heller myotomy in that trial, illustrating a trade-off rather than a reason to reject POEM automatically. Acid-suppression treatment may subsequently affect gastrin blood results; meanwhile, pneumatic dilation carries a perforation risk of roughly 2% in experienced practice and requires an appropriate rescue pathway.
What can follow-up and blood tests show after treatment?
Follow-up assesses swallowing, weight, esophageal emptying, and reflux, not just whether symptoms improve. Blood tests can identify nutritional or hydration complications but cannot confirm that the junction opens normally; the ACG guideline recommends timed barium esophagram as the first-line objective test when symptoms persist or recur after treatment (Vaezi et al., 2020).

の Eckardt score adds dysphagia, regurgitation, chest pain, and weight loss, each scored from 0 to 3, for a total of 0–12. Trials often define success as a score of 3 or below, but symptom scores alone can miss retained material; reduced discomfort does not necessarily mean that esophageal clearance has normalized.
カンテスティは AIバイオマーカー解釈プラットフォーム that can help explain a clinician-requested complete blood count, electrolytes, and iron studies alongside reduced intake. Ferritin below 15 ng/mL strongly supports depleted iron stores in adults without a confounding context; our 完全な鉄研究ガイド explains why ferritin and transferrin saturation should be considered together rather than used to infer an achalasia subtype.
Albumin commonly has an adult reference interval around 35–50 g/L, but a normal value does not exclude inadequate intake and a low value is not specific for malnutrition. Our 血清タンパク質解釈ガイド explains those limitations; magnesium deserves separate attention when poor intake or long-term acid suppression is present, as discussed in 低マグネシウムの原因.
What should you ask next, and which evidence applies?
Your next discussion should connect the manometry classification, structural assessment, and evidence of impaired emptying before selecting treatment. Ask 3 practical questions: which findings establish the subtype, whether obstruction or medication effects have been excluded, and how the proposed procedure's expected benefit compares with its reflux and retreatment risks.
Request the full manometry report rather than only its conclusion, including the catheter system, body positions, median IRP, swallow counts, and any supportive tests. If you cannot swallow liquids or saliva, develop severe chest pain, or have respiratory difficulty, seek urgent care; waiting another 2 weeks for a routine report review is not an appropriate response to those warning signs.
The achalasia evidence cited here comes from Chicago Classification version 4.0, the ACG achalasia guideline, and the randomized POEM-versus-Heller trial. Kantesti's 医療コンテンツ基準 distinguish evidence-based explanations from individualized diagnosis; the 2 Zenodo publications listed below concern coagulation and serum proteins, not studies validating manometry or achalasia treatment.
The serum-protein publication is relevant only to the laboratory-support discussion, while the coagulation publication provides separate background if a clinician requests clotting tests before a procedure. Neither DOI should be used to choose among types I, II, and III; when laboratory values change during recovery, blood-test timeline effects help explain why intake, illness, hydration, and medicines may alter results without indicating recurrent outlet obstruction.
よくある質問
アカラシアはどのように診断されますか?
アカラシアは通常、高解像度食道内圧検査で食道胃接合部の弛緩障害と正常な蠕動運動の欠如を確認して診断されます。続いて、圧力パターンによってI型、II型、III型を区別します。上部内視鏡検査は器質的閉塞の除外に役立ち、時間経過を追ったバリウム嚥下検査またはFLIPは不確かな所見を明確にするのに役立ちます。3つのサブタイプのいずれも、通常の血液検査で確定することはできません。.
アカラシアでは食道内圧検査で何が示されますか?
食道内圧検査では、嚥下後に食道胃接合部がどのように弛緩するか、また食道体部が協調した収縮を生じるかを示す。統合弛緩圧は4秒間のウィンドウで流出路の弛緩を評価し、収縮のタイミングと圧分布はサブタイプの特定に役立つ。II型では嚥下の少なくとも20%で全食道内圧上昇を認める必要があり、III型では少なくとも20%で早期収縮を認める必要がある。機器によって基準値が異なるため、機器固有の基準値を用いなければならず、すべてに共通するIRPカットオフ値は適切ではない。.
I型、II型、III型アカラシアの違いは何ですか?
I型アカラシアでは蠕動が消失しており、II型に必要な全食道内圧上昇は認められません。II型では、蠕動の消失に加えて、嚥下の少なくとも20%で全食道内圧上昇が認められます。III型では、正常な蠕動がなく、嚥下の少なくとも20%で早期収縮が認められ、接合部の弛緩も障害されています。これらは生理学的パターンであり、疾患進行の確実な段階を示すものではありません。.
IRPが正常でもアカラシアが起こることはありますか?
アカラシアは、統合弛緩圧が正常または境界域であっても、蠕動が消失し排出が障害されている場合には、依然として懸念されることがあります。そのような状況では、マノメトリーは明らかに正常というより、判定不能となる場合があります。通常、1、2、5分後の画像を含む時間指定バリウム検査、またはFLIPが補助的な根拠となります。専門医は、収縮性の欠如、技術的な限界、および過去の治療についても検討する必要があります。.
アカラシアがあっても内視鏡検査が正常なことはありますか?
0 Endoscopyは、嚥下圧を直接測定するのではなく、構造や粘膜を調べるため、早期のアカラシアではほぼ正常に見えることがあります。食物や唾液の貯留、または狭窄した接合部は疑いを高めることがありますが、診断を確定するものではありません。マノメトリーは特徴的な圧パターンを特定し、3つのサブタイプを鑑別します。粘膜表面が正常に見える場合でも、偽性アカラシアへの懸念が続く場合は、CTまたは超音波内視鏡が必要となることがあります。.
治療に最もよく反応するアカラシアの病型はどれですか?
Type II achalasia generally has favorable responses to pneumatic dilation, Heller myotomy, and POEM, but subtype alone cannot predict an individual's result. Type III often benefits from a longer myotomy tailored to the spastic segment. A randomized trial reported 2-year success of 83.0% after POEM and 81.7% after Heller myotomy with fundoplication across its overall study population. Reflux, anatomy, prior treatment, and procedural expertise also influence the choice.
Do you need sedation for esophageal manometry?
Standard esophageal manometry is usually performed awake, often with local nasal anesthetic rather than intravenous sedation. Patients complete a structured swallowing protocol, commonly 10 supine and 5 upright water swallows. Difficult catheter placement sometimes requires endoscopic assistance, but any sedation and recovery interval must be considered when interpreting the subsequent measurements. Follow the testing center's fasting instructions because achalasia can retain food despite an ordinary fast.
血液検査結果の見方を確認しましょう
検査報告書をアップロードすると、KantestiのAIが数秒で各バイオマーカーを平易な言葉で説明します。世界中で200万人以上が利用しています。.
参考文献
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTTの基準範囲:Dダイマー、プロテインC、血液凝固ガイド。. Kantesti AI医学研究。. 掲載日
- Klein, T., Mitchell, S., & Weber, H. (2026). 血清タンパク質ガイド:グロブリン、アルブミン、A/G比の血液検査。. Kantesti AI医学研究。. 掲載日
- Yadlapati R et al. (2021). Esophageal motility disorders on high-resolution manometry: Chicago classification version 4.0. Neurogastroenterology & Motility. 掲載日
- Vaezi MF et al. (2020). ACG Clinical Guidelines: Diagnosis and Management of Achalasia. The American Journal of Gastroenterology。. 掲載日
- Werner YB et al. (2019). Endoscopic or Surgical Myotomy in Patients with Idiopathic Achalasia. The New England Journal of Medicine. 掲載日
- 200万以上分析対象の検査
- 127+国
- 100+言語
医療チームについて


E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
Thomas Klein医師による医学的レビュー。Sarah Mitchell医師およびHans Weber教授の協力。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.





医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
公開 · 編集チームにお問い合わせください
Kantesti Ltdが発行。イングランドおよびウェールズで登録、会社番号. 17090423, 、英国ロンドン。.
