A parainfluenza PCR positive result means the test detected viral genetic material, usually from a respiratory swab. Parainfluenza is contagious and commonly causes a cold-like illness, but it can cause croup or pneumonia; PCR alone cannot show how serious the illness is or whether you remain infectious.

मुख्य निष्कर्ष
- पॉज़िटिव पीसीआर detects parainfluenza genetic material, not a measured quantity of live virus; 1 positive swab cannot establish severity or clearance.
- Different from influenza: human parainfluenza includes 4 main virus types, and influenza antivirals such as oseltamivir do not treat parainfluenza.
- संक्रामकता is generally greatest early in illness; symptoms commonly begin about 2–6 days after exposure, but shedding varies between people.
- Community precautions can usually ease after symptoms improve overall and fever has been absent for at least 24 hours without fever-reducing medicine; use additional precautions for the next 5 days.
- Croup risk is greatest in young children, especially around 6 months to 3 years; a barking cough with noisy inhalation needs clinical assessment.
- Croup treatment may include clinician-prescribed dexamethasone, commonly 0.6 mg/kg once; a positive PCR alone is not a reason to take steroids.
- साँस लेने में परेशानी के आपात संकेत include stridor at rest, chest pulling inward, blue or grey lips, pauses in breathing, or inability to drink; do not wait for another test.
- Infant fever of 38°C or higher in a baby younger than 3 months needs urgent medical assessment, even when a respiratory panel identifies a virus.
What does a parainfluenza PCR positive result mean?
A parainfluenza PCR positive result means the laboratory detected genetic material from a human parainfluenza virus in the submitted sample. It supports a current or recent respiratory infection, but 1 result cannot establish pneumonia, croup severity, or ongoing contagiousness.
Most respiratory panels test a nasal or nasopharyngeal swab rather than a blood sample. Human parainfluenza viruses contain RNA, so testing generally includes reverse transcription before amplification; reports may still use the simpler term PCR. Our explanation of गुणात्मक बनाम मात्रात्मक परिणाम clarifies why a detected/not-detected answer is not a numerical disease score.
Reports may name parainfluenza type 1, 2, 3, or 4, or combine several types into one result line. Those laboratory choices affect what the report tells you, not necessarily how unwell you are. Check the specimen collection date: a result released today may describe a sample obtained several days earlier, before symptoms improved or worsened.
Kantesti is an AI blood test analyzer that helps explain accompanying laboratory findings, while a respiratory PCR needs its own specimen and symptom context. Our संगठन और उद्देश्य are separate from the laboratory that performed your swab. Keep 3 details with the report: when symptoms began, when the sample was collected, and whether breathing or drinking has changed.
Parainfluenza vs influenza: are they the same infection?
Parainfluenza and influenza are different viruses, despite their similar names. Human parainfluenza has 4 main types and belongs to the Paramyxoviridae family; influenza belongs to the Orthomyxoviridae family, so flu vaccines and flu-specific antivirals do not provide parainfluenza-specific treatment.
Both illnesses can cause fever, cough, sore throat, fatigue, and muscle aches, so symptoms alone may not separate them reliably. Influenza often starts abruptly, whereas parainfluenza frequently resembles a cold before a child's barking cough appears. Neither pattern is diagnostic; a panel that separately reports influenza A, influenza B, and parainfluenza provides more useful evidence than the word flu in a conversation.
Oseltamivir targets influenza, not parainfluenza. Influenza treatment is often most beneficial when started within 48 hours, although severe illness and higher-risk patients can warrant later treatment; those rules should not be transferred to a parainfluenza-only result. Our influenza treatment explanation covers the separate decision pathway when influenza is also detected.
A panel can detect 2 respiratory pathogens at once, and one positive result does not cancel the other. If both influenza and parainfluenza are reported, influenza treatment may still be appropriate according to age, risk, and illness duration. There is no routinely available licensed vaccine specifically against human parainfluenza, but routine influenza vaccination still protects against its intended influenza targets.
Why PCR cannot tell whether you are still infectious
PCR detects viral RNA, not whether every detected particle can reproduce and spread. A positive result can occur during active illness or while genetic material remains detectable afterward; there is no validated parainfluenza PCR cutoff that certifies a person is noncontagious.

Some molecular assays report a cycle threshold, or Ct, but many respiratory panels provide only a qualitative result. Within the same validated assay, a lower Ct generally reflects more starting target material; swab technique, sample dilution, transport, and assay design also affect it. A hypothetical Ct of 30 from one laboratory cannot be treated as equivalent to 30 from another.
Kantesti separates 2 questions that patients often combine: whether the target was detected and whether that person can transmit infection now. Viral culture can help demonstrate replication-capable virus in specialized settings, but it is not a routine return-to-school test. Henrickson's review describes variable shedding, including prolonged shedding in some children and immunocompromised people (Henrickson, 2003).
A recovering person with no fever and improving energy has a different practical risk profile from someone with a new fever and frequent coughing, even if both reports say detected. Our adenovirus shedding explanation illustrates the broader distinction between molecular detection and clinical recovery. Its virus-specific timelines should not be used as parainfluenza clearance rules.
Is parainfluenza contagious, and how does it spread?
Parainfluenza is contagious and spreads through respiratory secretions, close contact, and contaminated hands or objects that carry secretions to the eyes, nose, or mouth. Symptoms commonly develop about 2–6 days after exposure, and transmission risk is generally greatest early in the illness.
A household exposure does not mean everyone will become sick on the same day. For example, a child who develops a cough on Monday could have been exposed several days earlier, while a sibling exposed later may develop symptoms toward the end of the week. The 2–6-day incubation range explains why an apparently well household member is not automatically free of risk.
Young children may shed virus beyond the first week, and immune suppression can extend shedding further; a universal 7-day or 10-day cutoff is therefore misleading. Frequent coughing, close face-to-face care, and shared indoor air increase opportunities for transmission. A small amount of detectable RNA does not translate into a measurable probability that one particular hug or conversation will cause infection.
Wash hands with soap and water for at least 20 seconds, improve ventilation, and avoid sharing cups or utensils while ill. Clean frequently touched items after contact with respiratory secretions, but do not treat surface cleaning as a substitute for reducing close exposure. Our post-illness contagiousness guide discusses why recovery and detection can diverge, although norovirus transmission and exclusion rules are different.
When can you return to school, nursery, or work?
Return decisions should usually follow symptoms and local policy, not repeat PCR alone. For community respiratory illnesses, CDC guidance allows normal activities when symptoms improve overall and fever has been absent for at least 24 hours without fever-reducing medicine, followed by 5 days of added precautions.

The CDC respiratory illness guidance is a general community framework, not a parainfluenza-specific proof of clearance. During the next 5 days, cleaner air, distancing where practical, and a well-fitting mask for people who can safely wear one reduce exposure. Do not put masks on children younger than 2 years or anyone unable to remove one safely.
Nurseries, schools, employers, hospitals, and transplant units may apply different policies. A child also needs enough energy to participate and enough hydration to manage the day; meeting a 24-hour fever rule does not make a struggling child ready for nursery. If fever returns or symptoms worsen after resuming activities, stay home again and reassess rather than counting the previous recovery period as permanent clearance.
For a hypothetical family with a recovering preschooler and a grandparent receiving chemotherapy, postponing close indoor contact may be sensible even after the child meets nursery criteria. Share only the information the school or employer actually needs; a complete laboratory report can reveal unrelated health details. Our privacy and data approach explains this distinction for health information handled through our service.
Who is more likely to develop serious parainfluenza illness?
Most otherwise healthy people develop a self-limited respiratory illness, but infants, older adults, immunocompromised people, and those with significant lung or heart disease have greater risk of complications. Severity depends on airway involvement and physiological function, not which of the 4 virus types appears on the report.
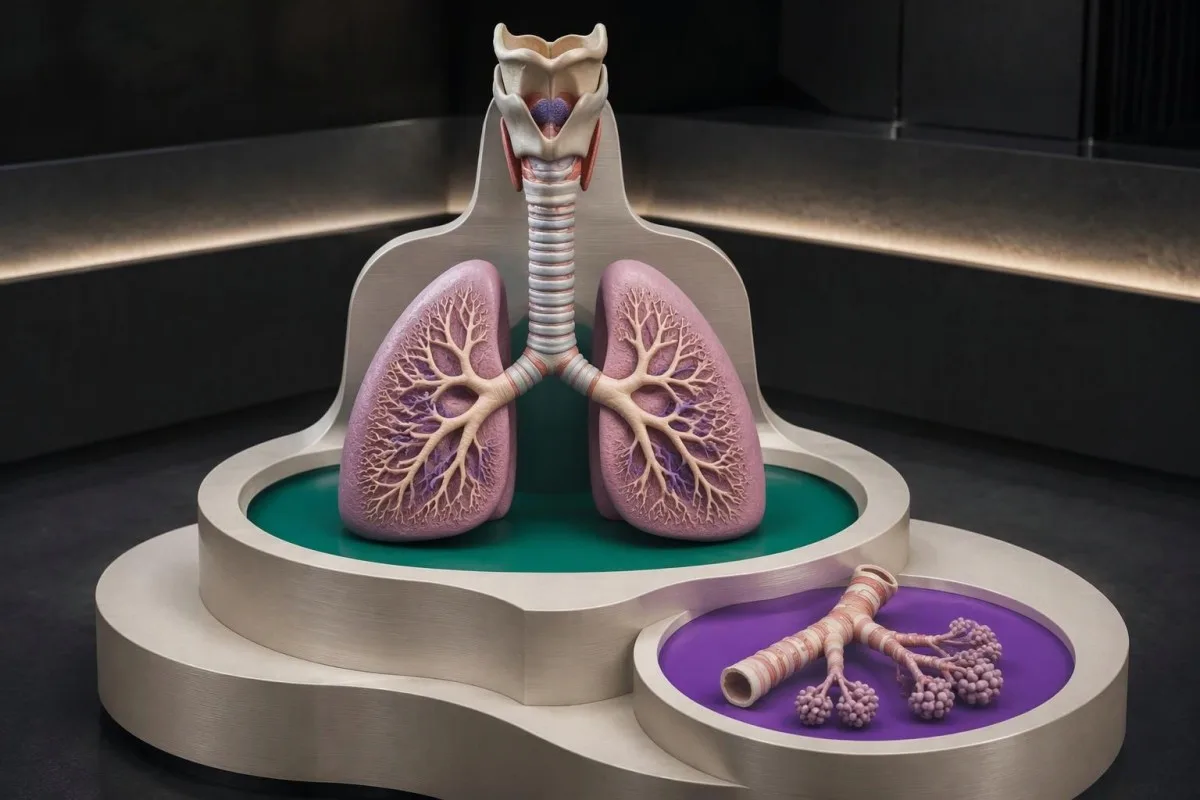
Parainfluenza types 1 and 2 are particularly associated with croup, while type 3 is often associated with bronchiolitis and pneumonia; these are tendencies, not guarantees. Henrickson's Clinical Microbiology Reviews article describes these clinical associations across the 4 types (Henrickson, 2003). A type 3 result in a comfortable adult does not establish pneumonia, and type 1 does not guarantee a mild course.
A hypothetical 35-year-old drinking normally with a runny nose and mild cough may need only home care, while an 8-month-old with chest retractions needs prompt assessment despite having the same detected virus. Smaller airways tolerate less swelling before airflow becomes difficult. Feeding difficulty in babies also matters because breathing and sucking compete for effort, allowing dehydration to develop before an obvious laboratory abnormality appears.
Older adults may show reduced appetite, confusion, or worsening breathlessness rather than a striking fever. People with asthma or COPD can develop exacerbations requiring their existing action plan and medical review, not an automatic new antibiotic. Our adult respiratory warning signs cover similar assessment principles for RSV, another distinct virus that can affect vulnerable adults.
How does parainfluenza cause croup and noisy breathing?
Parainfluenza can cause croup by producing swelling around the larynx and the airway just below the vocal cords. Croup is most common around 6 months to 3 years and typically causes a barking cough, hoarseness, and sometimes a harsh sound when breathing in called stridor.
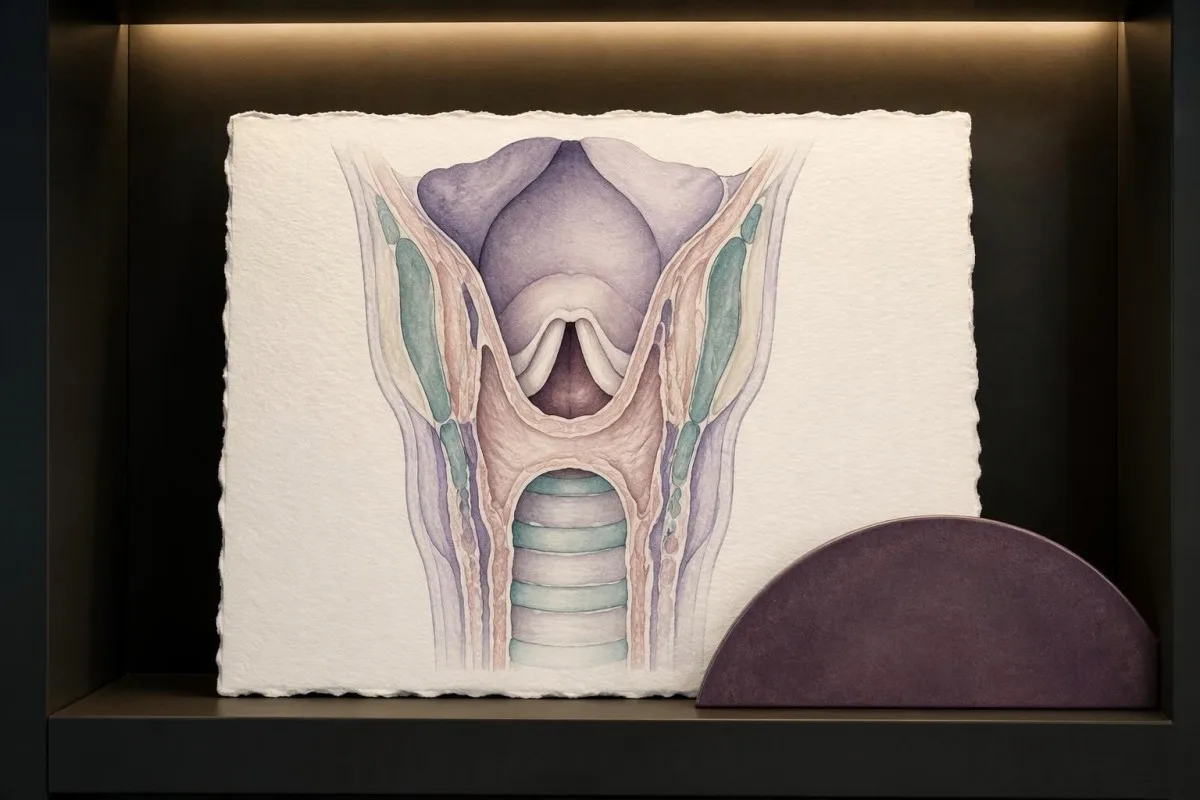
Stridor and wheeze are different sounds. Stridor is usually a harsh upper-airway sound during inhalation; wheeze is commonly a musical chest sound during exhalation. A short recording can help describe an intermittent sound to a clinician, but recording for 30 seconds must never delay seeking help when a child has stridor at rest or is visibly working to breathe.
Croup often becomes more noticeable at night, and agitation can make breathing noise worse. Keep an upset child calm and comfortably upright while arranging advice; assess the sound when the child is settled, not only during crying. A hypothetical 2-year-old who barks when coughing but breathes quietly between coughs has a different urgency level from a child with continuous stridor while sitting calmly.
Drooling, inability to swallow, sudden onset during eating, a muffled voice, or an unusually ill appearance are not reasons to assume ordinary croup. They can signal another airway problem and need urgent assessment, even with 1 positive viral result. Our guidance on बच्चों की AI व्याख्या की सीमाएँ explains why laboratory interpretation cannot replace direct pediatric airway assessment.
When does croup need dexamethasone or nebulized treatment?
Clinically diagnosed croup may benefit from a single corticosteroid dose, even when symptoms are mild. Dexamethasone 0.6 mg/kg once is a common regimen; clinicians may use lower doses under local protocols, while moderate or severe croup may also require nebulized epinephrine and observation.
In a randomized trial of 720 children with mild croup, return visits for medical care within 7 days occurred in 7.3% after dexamethasone versus 15.3% after placebo (Bjornson et al., 2004). This demonstrates benefit for the croup syndrome, not for every parainfluenza-positive cough. Corticosteroids are not routine treatment for an uncomplicated parainfluenza cold without another indication.
The 2023 Cochrane review by Aregbesola et al. supports glucocorticoids for croup, while comparisons between doses leave some uncertainty about the best regimen for every presentation. For a hypothetical 12 kg child, 0.6 mg/kg calculates to 7.2 mg; the clinician selects the formulation and applicable maximum dose. Parents should not use leftover steroid medicine or copy another child's prescribed volume.
Nebulized epinephrine provides temporary improvement, so discharge decisions commonly include at least 2 hours of observation after treatment, with longer observation depending on the clinical course and local protocol. Kantesti is an AI blood test interpretation platform, not a service that determines whether a child can safely leave emergency care. Our AI तकनीक का स्पष्टीकरण distinguishes report analysis from an examination, medication decision, or monitored treatment response.
What supportive care helps uncomplicated parainfluenza?
Uncomplicated parainfluenza usually needs fluids, rest, nasal comfort measures, and symptom relief rather than antibiotics. Honey may help cough in people older than 1 year, but it must not be given to infants younger than 12 months because of the risk of infant botulism.

For adults who can take paracetamol, a common dose is 500–1,000 mg with at least 4 hours between doses; follow the local product's daily maximum and never exceed 4,000 mg from all products combined. Lower limits may apply with low body weight, liver disease, or alcohol-related risk. Our acetaminophen overdose explanation explains why combining cold remedies can unintentionally duplicate paracetamol, the same medicine under another name.
Children need weight- and formulation-specific dosing rather than an adult schedule, and aspirin should not be used for a child's viral illness unless a specialist specifically prescribes it. Offer smaller, more frequent drinks or feeds; saline drops and gentle nasal suction before feeding may help a congested infant. Never dilute infant formula beyond its instructions, and do not use 1 adult medicine dose as a shortcut for pediatric treatment.
Hot steam is not a proven croup treatment and can cause burns; a steamy bathroom should not delay assessment for noisy breathing. Antibiotics do not treat parainfluenza, and no established routine antiviral treatment is available for an otherwise healthy outpatient. If poor intake becomes significant, clinicians may assess hydration and electrolytes, as described in our इलेक्ट्रोलाइट परिणाम गाइड, rather than assuming every recovering person needs laboratory tests.
Which breathing signs require urgent or emergency care?
Stridor at rest, marked chest retractions, blue or grey lips, pauses in breathing, severe breathlessness, or reduced responsiveness require urgent assessment, often emergency care. A normal-looking PCR report or oxygen reading must not overrule these signs; a baby younger than 3 months with a temperature of 38°C or higher also needs urgent assessment.
Call local emergency services if the person cannot speak normally because of breathlessness, has blue or grey lips, becomes difficult to wake, or has breathing pauses. In children, pulling inward between or below the ribs and persistent stridor while calm are concerning. Do not spend another 10 minutes arranging a repeat swab, uploading a report, or trying home remedies when these signs are present.
Home pulse oximeters are imperfect, particularly with movement, cold fingers, poor fit, and differences in skin pigmentation. At usual low-altitude conditions, a persistent resting saturation of 92% or lower generally warrants urgent medical evaluation; a reading of 90% or lower is an emergency signal unless an individualized clinical plan says otherwise. Severe upper-airway obstruction can initially occur with a reassuring saturation, as our सांस फूलने की जाँच संबंधी मार्गदर्शिका बताता है।.
A hypothetical child with loud stridor and a displayed oxygen saturation of 97% still needs urgent airway assessment because oxygenation is not the same as easy airflow. Clinicians assess respiratory effort, alertness, hydration, and trends, sometimes using additional tests when lower-airway disease is suspected. Our arterial blood gas explanation describes why oxygen and carbon dioxide measurements answer different questions.
What if the cough persists or fever returns?
A lingering cough can outlast the most infectious phase, but worsening breathing or a returning fever needs reassessment. Many uncomplicated respiratory symptoms improve over roughly 7–10 days, while cough can last longer; neither a fixed day count nor a persistent positive PCR proves an uncomplicated recovery.
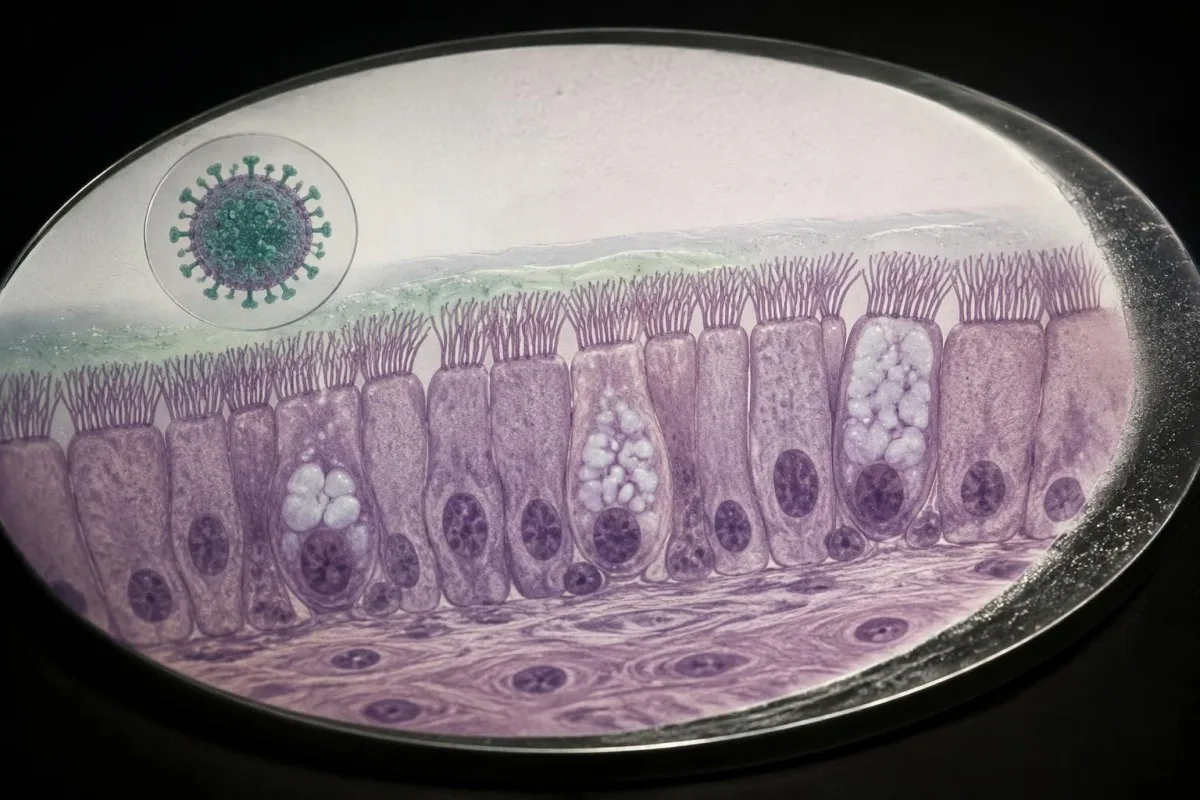
Postviral airway irritation can maintain cough after energy and appetite recover. The more useful distinction is improving versus worsening: a cough that is gradually less frequent differs from a new fever with chest pain, fast breathing, or reduced activity. If a cough lasts beyond about 3 weeks, or sooner if troublesome or worsening, arrange assessment rather than repeatedly checking the same viral target.
A positive parainfluenza result does not exclude bacterial pneumonia or another infection. Pertussis can cause coughing fits, vomiting after cough, or breathing pauses in infants, and testing has a time-dependent diagnostic window; our whooping cough testing guide explains that distinction. A hypothetical child who develops repeated coughing fits in week 2 deserves a fresh symptom review, not automatic attribution to the earlier panel.
Multiplex panels may detect more than 1 organism, but they do not necessarily test every relevant cause of pneumonia. If a clinician orders Mycoplasma antibody testing, timing and antibody persistence create a different interpretation problem from respiratory RNA detection. Our Mycoplasma antibody result guide explains why a positive IgM result is not interchangeable with a positive parainfluenza PCR.
Can blood tests show whether parainfluenza is serious?
Blood tests can reveal complications or support an assessment, but no CBC, CRP, or procalcitonin value can independently grade parainfluenza severity. For 2 people with the same positive swab, respiratory effort, oxygenation, hydration, and underlying health may lead to entirely different care decisions.

White cell count and CRP describe aspects of the immune response, not whether the airway is safely open. A hypothetical adult with a WBC of 8.0 × 10^9/L can still have pneumonia, while an elevated WBC may reflect stress or steroid treatment rather than bacterial infection. Our WBC और CRP तुलना explains why disagreement between these markers needs context.
Procalcitonin sometimes supports antibiotic decisions in selected settings, but a low value cannot independently exclude early or localized bacterial pneumonia. For example, a hypothetical procalcitonin of 0.08 ng/mL must not override new hypoxia, focal chest findings, or clinical deterioration. Our प्रोकैल्सिटोनिन व्याख्या मार्गदर्शक separates a probability-shifting biomarker from a definitive bacterial rule-out test.
Kantesti AI helps explain accompanying blood-test patterns, but those patterns cannot certify that a person with 1 positive respiratory swab is safe for home care or no longer contagious. Chest imaging, examination, and repeat observations may matter more when lower respiratory disease is suspected. Our clinical methodology and oversight describe the boundaries of AI interpretation; do not order extra panels solely to obtain reassurance about an otherwise comfortable cold.
How should families and immunocompromised people follow up?
Families should match precautions and follow-up to each person's vulnerability rather than treating every positive result alike. Transplant recipients, people receiving chemotherapy, and others with substantial immune suppression should contact their treating team promptly about new respiratory symptoms or a positive panel, even on illness day 1.

For a hypothetical household with a 3-year-old with croup and an adult taking transplant immunosuppression, prioritize cleaner air, less close contact when feasible, and advice from the transplant team. Do not independently reduce immunosuppressant doses or start leftover antivirals. Severe parainfluenza in immunocompromised patients may require specialist-directed management, but evidence for specific drug approaches is limited and does not establish a routine home regimen.
Specialist units may use repeat respiratory PCR for infection-control decisions, especially when prolonged shedding is plausible; this differs from routine community test-of-cure testing. A positive result after 2 weeks can have greater practical significance on a transplant ward than in a fully recovered healthy adult. Follow the unit's instructions about appointments and isolation rather than applying a general school-return rule to a high-risk clinical setting.
For families using Kantesti, keep each person's results and symptom timeline separate; one child's positive panel does not diagnose every household member. A single parainfluenza episode does not establish immune deficiency, but repeated severe or unusual infections may justify targeted assessment. Our बार-बार होने वाले संक्रमणों की जाँच के लिए मार्गदर्शिका explains why the pattern across multiple illnesses is more informative than 1 isolated detection.
Putting the result in context: research and AI limits
Use the respiratory result alongside symptoms, specimen timing, and clinical risk—not as a stand-alone severity or clearance certificate. The 2 DOI-linked educational resources below address accompanying blood-test interpretation; they are not parainfluenza treatment trials and should not be cited as evidence about contagiousness.

A CBC may include RDW, MCV, and MCHC, but these red-cell indices do not identify parainfluenza or measure its infectiousness. A hypothetical MCV of 78 fL raises a separate question about small red cells, not a reason to label the respiratory illness severe. Our RDW और लाल-रक्त कोशिका गाइड provides background for results that may appear alongside a respiratory illness assessment.
Kidney measurements can become relevant when poor intake, dehydration, or medication concerns accompany illness. A hypothetical BUN/creatinine ratio of 25:1 may fit reduced fluid intake in some settings, but the ratio alone cannot diagnose dehydration, and calculation depends on the reporting units. Our BUN और क्रिएटिनिन गाइड explains this separate interpretation problem.
Kantesti is an AI-powered blood test analysis tool that supports understanding of laboratory information without replacing examination or emergency triage. Our चिकित्सा सामग्री मानक require us to distinguish established guidance, hypothetical examples, and uncertain evidence. Before acting on 1 detected result, ask the practical questions: Is breathing comfortable, is hydration adequate, are symptoms improving, and does this person have a reason to seek earlier medical review?
अक्सर पूछे जाने वाले प्रश्न
यदि पीसीआर पॉज़िटिव हो, तो क्या पैराइन्फ्लुएंज़ा संक्रामक होता है?
पैराइन्फ्लुएंज़ा संक्रामक है, लेकिन केवल पॉज़िटिव PCR से यह साबित नहीं होता कि परिणाम पढ़े जाने के समय व्यक्ति अभी भी संक्रामक है। PCR वायरल आनुवंशिक सामग्री का पता लगाता है, जो लक्षणों में सुधार होने के बाद भी पता चल सकती है। लक्षण आमतौर पर संपर्क में आने के लगभग 2–6 दिन बाद शुरू होते हैं, और संक्रमण फैलने का जोखिम आम तौर पर बीमारी की शुरुआत में सबसे अधिक होता है। लक्षणों के आधार पर सावधानियाँ बरतें और स्थानीय निर्देशों का पालन करें, विशेष रूप से शिशुओं और प्रतिरक्षा-दुर्बल लोगों के आसपास।
मुझे पैराइन्फ्लुएंज़ा होने पर कितने समय तक घर पर रहना चाहिए?
0 सामुदायिक श्वसन संबंधी बीमारियों के लिए, CDC के दिशानिर्देश आम तौर पर तब तक घर पर रहने की सलाह देते हैं, जब तक लक्षणों में कुल मिलाकर सुधार न हो जाए और बुखार कम करने वाली दवा के बिना कम से कम 24 घंटे तक बुखार न रहा हो। इसके बाद के 5 दिनों तक अतिरिक्त सावधानियाँ बरतने की सलाह दी जाती है, क्योंकि सुधार का मतलब यह नहीं है कि संक्रमण फैलने का जोखिम शून्य है। स्कूल, नर्सरी, स्वास्थ्य सेवा और कार्यस्थल की नीतियाँ अलग-अलग हो सकती हैं। सामान्य गतिविधियों में लौटने वाले अन्यथा स्वस्थ व्यक्ति के लिए पैराइन्फ्लुएंज़ा PCR का दोबारा नेगेटिव होना आम तौर पर आवश्यक नहीं है।
क्या पैराइन्फ्लुएंज़ा और इन्फ्लुएंज़ा एक ही हैं, और क्या टैमीफ्लू से मदद मिलती है?
पैराइन्फ्लुएंज़ा, इन्फ्लुएंज़ा नहीं है, और ओसेल्टामिविर, जिसे टैमीफ्लू भी कहा जाता है, पैराइन्फ्लुएंज़ा का इलाज नहीं करता। मानव पैराइन्फ्लुएंज़ा के 4 मुख्य प्रकार हैं, जो इन्फ्लुएंज़ा से अलग विषाणु परिवार के हैं। इन्फ्लुएंज़ा के टीके पैराइन्फ्लुएंज़ा से विशिष्ट सुरक्षा प्रदान नहीं करते। यदि श्वसन पैनल में इन्फ्लुएंज़ा भी पाया जाता है, तो चिकित्सक इन्फ्लुएंज़ा के उपचार पर विचार कर सकते हैं, जो अक्सर 48 घंटों के भीतर सबसे अधिक लाभकारी होता है, लेकिन बाद में भी कुछ चुनिंदा उच्च-जोखिम वाले या गंभीर मामलों में दिया जाता है।
क्या पैराइन्फ्लुएंज़ा वायरस का पता चलने का मतलब है कि मेरे बच्चे को क्रूप है?
Parainfluenza virus detected means the test found viral genetic material; it does not establish that a child has croup. Croup is diagnosed from features such as a barking cough, hoarseness, and stridor, and is most common around 6 months to 3 years. A child with these symptoms may benefit from clinician-prescribed corticosteroid treatment. Stridor while resting calmly, marked chest retractions, drooling, or difficulty swallowing needs urgent assessment rather than waiting for another test.
Do I need antibiotics or another PCR after parainfluenza?
Uncomplicated parainfluenza usually does not require antibiotics or repeat PCR testing. Antibiotics treat bacteria, not the parainfluenza virus, and a lingering positive molecular result does not by itself justify treatment. If fever returns after improvement, breathing worsens, or cough remains troublesome beyond about 3 weeks, seek reassessment for complications or another cause. Immunocompromised patients may need different testing and follow-up instructions from their specialist team.
When is a positive parainfluenza result serious?
A positive parainfluenza result becomes clinically concerning when accompanied by difficult breathing, stridor at rest, marked chest retractions, blue or grey lips, breathing pauses, reduced responsiveness, or significant dehydration. A baby younger than 3 months with a temperature of 38°C or higher needs urgent medical assessment even when a virus has been identified. A persistent oxygen saturation of 92% or lower at usual low-altitude conditions generally warrants urgent evaluation, but a normal reading does not exclude dangerous upper-airway narrowing. Call emergency services for severe symptoms rather than waiting for a repeat PCR or an AI interpretation.
अपनी रक्त जांच रिपोर्ट समझें
अपनी लैब रिपोर्ट अपलोड करें और Kantesti का AI कुछ ही सेकंड में प्रत्येक बायोमार्कर को सरल भाषा में समझाएगा। दुनिया भर में 2 मिलियन से अधिक लोगों द्वारा इस्तेमाल किया जाता है।.
संदर्भ
- क्लाइन, टी., मिशेल, एस., & वेबर, एच. (2026)।. RDW रक्त जांच: RDW-CV, MCV और MCHC के लिए संपूर्ण मार्गदर्शिका।. Kantesti AI चिकित्सा अनुसंधान।. डीओआई
- क्लाइन, टी., मिशेल, एस., & वेबर, एच. (2026)।. BUN/क्रिएटिनिन अनुपात समझाया गया: किडनी फ़ंक्शन टेस्ट गाइड।. Kantesti AI चिकित्सा अनुसंधान।. डीओआई
- Henrickson KJ (2003). Parainfluenza viruses. Clinical Microbiology Reviews। डीओआई PubMed
- Aregbesola A et al. (2023). Glucocorticoids for croup in children. Cochrane Database of Systematic Reviews. डीओआई
- Bjornson CL et al. (2004). A randomized trial of a single dose of oral dexamethasone for mild croup. द न्यू इंग्लैंड जर्नल ऑफ़ मेडिसिन।. डीओआई PubMed
- 2एम+विश्लेषित परीक्षण
- 127+देशों
- 100+बोली
चिकित्सा दल के बारे में


E-E-A-T भरोसा संकेत
अनुभव
चिकित्सक-नेतृत्व वाली लैब व्याख्या वर्कफ़्लो की क्लिनिकल समीक्षा।.
विशेषज्ञता
लैबोरेटरी मेडिसिन का फोकस इस पर कि बायोमार्कर क्लिनिकल संदर्भ में कैसे व्यवहार करते हैं।.
अधिकारिता
डॉ. Thomas Klein द्वारा चिकित्सकीय समीक्षा, जिसमें डॉ. Sarah Mitchell और प्रो. डॉ. Hans Weber का योगदान शामिल है।.
विश्वसनीयता
साक्ष्य-आधारित व्याख्या, जिसमें अलार्म कम करने के लिए स्पष्ट फॉलो-अप मार्ग शामिल हैं।.




चिकित्सकीय अस्वीकरण
यह लेख केवल शैक्षिक उद्देश्यों के लिए है और चिकित्सा सलाह का गठन नहीं करता। निदान और उपचार संबंधी निर्णयों के लिए हमेशा किसी योग्य स्वास्थ्य सेवा प्रदाता से परामर्श करें।.
प्रकाशित · संपादकीय दल से संपर्क करें
Kantesti Ltd द्वारा प्रकाशित, इंग्लैंड और वेल्स में पंजीकृत, कंपनी संख्या. 17090423, लंदन, यूनाइटेड किंगडम।.
