
A weak neutrophil response is not always chronic granulomatous disease. The fluorescence pattern, healthy control, and sample journey determine what the result can actually establish.



- Abnormal DHR test results indicate reduced or uneven neutrophil oxidation of dihydrorhodamine 123; they require pattern-based interpretation, not an automatic CGD diagnosis.
- Near-absent response in almost all neutrophils, with a satisfactory healthy control, strongly supports a severe NADPH oxidase defect.
- Two neutrophil populations can indicate an X-linked CGD carrier, but granulocyte transfusion or transplant-related chimerism can produce a similar mixture.
- Carrier fractions below 10% functioning neutrophils have been associated with substantially greater CGD-type infection risk; 50% is not a required carrier result.
- Residual oxidative activity can occur in genuine CGD, so a dim response is not necessarily reassuring.
- Laginaren denbora matters: collection-to-analysis targets are commonly around 24 hours, while longer windows require the performing laboratory's validation.
- Myeloperoxidase deficiency can reduce DHR fluorescence despite preserved NADPH oxidase activity; a second functional method may distinguish the conditions.
- Normal PMA stimulation does not exclude every rare phagocyte disorder, particularly defects better demonstrated with particle-based stimulation.
- Sintoma larrigarriak override repeat-test plans: fever with breathing difficulty, rapidly progressive illness, or a new deep infection needs prompt clinical assessment.
What do abnormal DHR test results actually mean?
Abnormal DHR test results mean neutrophils produced less—or a different distribution of—fluorescence after stimulation. A nearly absent response supports chronic granulomatous disease, 2 distinct populations may suggest X-linked carrier status, and weak responses with poor controls can reflect handling problems; none should be interpreted from the flagged number alone.

Gaixotasun granulomatoso kronikoa, or CGD, impairs the phagocyte NADPH oxidase system rather than simply lowering the neutrophil count. A patient can have an absolute neutrophil count of 4.0 × 10^9/L and still have a profound functional defect; counting cells and testing their antimicrobial machinery answer different questions.
Consider a 7-year-old with recurrent deep bacterial infections and an almost flat stimulated DHR trace. That combination raises a different level of concern from one borderline response in an otherwise well adult; the initial immune investigation should establish which infections occurred, where, and whether organisms were identified.
I’m Thomas Klein, Kantesti’s Chief Medical Officer, and my first reading rule is to separate 3 questions: is the specimen valid, is the response abnormal, and what mechanism explains it? Those questions belong in that order, because a convincing-looking graph can still come from compromised cells.
Kantesti is an AI blood test analyzer that can explain the written terminology in a DHR report alongside accompanying laboratory findings. Our enpresaren atzeko plana describes the service; an explanation generated in approximately 60 seconds does not replace specialist review of flow-cytometry data or establish CGD.
How does the DHR oxidative burst test work?
The DHR oxidative burst test uses flow cytometry to measure conversion of dihydrorhodamine 123 into fluorescent rhodamine after neutrophil stimulation. NADPH oxidase generates superoxide, which contributes to hydrogen peroxide formation; the DHR readout also depends on downstream oxidation chemistry, including myeloperoxidase, so fluorescence is not a direct superoxide measurement.

PMA, or phorbol myristate acetate, is a strong laboratory stimulus used in many DHR protocols. It activates intracellular signaling without requiring normal microbial recognition at the cell surface, which makes it useful for many CGD defects but less revealing for certain receptor-dependent or particle-dependent abnormalities.
A standard interpretation compares at least 2 patient conditions: unstimulated cells and stimulated cells. The laboratory usually also examines a healthy control; whether that control traveled with the patient specimen matters, because a freshly collected local control cannot fully reproduce damage sustained during a prolonged courier journey.
The neutrophil gate selects the cellular population being evaluated, and inappropriate inclusion of other granulocytes can distort the apparent pattern. Eosinofiloak are especially relevant when distinguishing myeloperoxidase deficiency; this is a laboratory-level issue that cannot be resolved from a CBC percentage or an isolated screenshot.
Normal neutrophil numbers do not prove normal neutrophil function. An adult ANC within a laboratory interval such as 1.5–7.5 × 10^9/L answers a counting question, not an oxidative-burst question; our neutrophil count guide explains why age, pregnancy, and reporting conventions affect that separate result.
Which DHR numbers and fluorescence patterns matter?
DHR interpretation requires both the proportion of responding neutrophils and the strength of their response. A report showing 98% positive cells can still conceal reduced fluorescence intensity, while 2 separated populations can be clinically significant even when their combined average appears acceptable; laboratory-specific gates and controls determine the meaning.

Mean fluorescence intensity, often abbreviated MFI, measures signal strength in a defined population. An illustrative MFI of 200 on one instrument cannot be compared directly with 200 on another; detector settings, reagents, stimulation time, and whether the laboratory averages all neutrophils or only responding cells affect the value.
Stimulation index is commonly calculated as stimulated fluorescence divided by baseline fluorescence, although laboratories may define the calculation differently. If stimulated MFI remains 100 but baseline rises from 1 to 5, the ratio falls from 100 to 20 without any change in the stimulated signal itself.
A histogram preserves information that a single summary number loses. The reason to request the full plot is similar to the reasoning behind flow-cytometry population analysis: the distribution can distinguish one uniformly dim population from 2 populations with very different behavior.
There is no universal DHR MFI or stimulation-index cutoff for CGD. A laboratory may also report a qualitative conclusion alongside quantitative measurements; our explanation of emaitza kualitatiboak eta kuantitatiboak helps separate a categorical flag from the underlying data used to assign it.
Does a weak oxidative burst always indicate severe CGD?
A nearly absent oxidative burst in almost all neutrophils strongly supports severe NADPH oxidase dysfunction when controls are satisfactory, but CGD can also produce a partial response. A uniformly dim population is not equivalent to 2 separate carrier populations, and measurable activity does not automatically exclude clinically significant disease.

Residual oxidase activity has prognostic relevance in CGD. Kuhns et al. studied 287 patients and found that residual reactive-oxygen-intermediate production was associated with survival, beyond the affected gene alone; their 2010 New England Journal of Medicine paper supports measuring function rather than treating every abnormal response as equally severe.
An illustrative response at 5% of a concurrent control is different from an undetectable response, but that comparison is not a universal treatment threshold. A specialist must consider the assay's reproducibility, the genotype, and the patient's infection history before translating a small remaining signal into a prediction about future health.
Rare severe G6PD deficiency can affect neutrophil oxidative function, although ordinary G6PD deficiency is not synonymous with CGD. A low DHR response combined with episodes of oxidant-triggered hemolysis may justify a separate enzyme investigation; our G6PD interpretation guide explains why red-cell enzyme results need their own context.
Kantesti AI can help organize the distinction between an absent response, a partial response, and a mixed response when those descriptions appear in the report. The useful output is a set of follow-up questions—not a claim that 1 percentage or a particular shade of fluorescence establishes disease severity.
Why do X-linked CGD carriers show two populations?
X-linked CGD carriers often show 2 neutrophil populations because different cells keep different X chromosomes active. Cells expressing a functioning CYBB copy can respond strongly, while cells expressing the affected copy respond poorly; this is cellular mosaicism, not every neutrophil operating at approximately 50% capacity.

A 50:50 split is not required for X-linked carrier status. A carrier might have an illustrative 70:30 or 20:80 distribution, and the proportion can change over time; the brighter population's intensity and the dim population's behavior should be evaluated separately rather than compressed into one average.
The mechanistic distinction is useful when comparing a carrier with partial CGD. In a carrier example, 30% of cells may respond approximately like control neutrophils while 70% respond poorly; in a partial-deficiency example, almost all cells may respond weakly together, producing a shifted but largely single distribution.
DHR cannot identify every genetic carrier. Carriers of autosomal-recessive CGD commonly have a normal functional response because 1 functioning gene copy is sufficient; molecular testing is usually required to establish that status, and normal DHR should not be presented as a universal negative carrier screen.
Carrier terminology also differs across inherited conditions. Our genetic carrier screening explanation addresses why carrier labels require disease-specific interpretation; for CGD, the immediate questions are inheritance pattern, neutrophil function, and whether the person has symptoms—not simply whether a variant was found.
When can an X-linked CGD carrier become symptomatic?
X-linked CGD carriers can develop infections or inflammatory complications, particularly when X-inactivation leaves very few functioning neutrophils. Fractions below 10% DHR-positive cells were strongly associated with CGD-type infections in a published carrier cohort, but no single percentage predicts every person's outcome or explains all autoimmune symptoms.

Marciano et al.'s 2018 Journal of Allergy and Clinical Immunology study connected low functioning-neutrophil fractions with CGD-type infection risk in X-linked carriers. Below 10% was a particularly concerning pattern; clinicians may also use a fraction below 20% to prompt closer assessment, but neither figure should become a stand-alone diagnostic rule.
Inflammatory and autoimmune manifestations do not track perfectly with the DHR-positive fraction. A carrier with 60% responding cells can still have clinically meaningful mouth sores, photosensitive rashes, or joint symptoms, so a reassuring percentage should not end the investigation when those complaints persist or recur.
A change from 35% to 18% functioning neutrophils deserves scrutiny, not an automatic conclusion that X-inactivation has worsened. First compare sample age, gating, stimulus, and the performing laboratory; repeat measurements under comparable conditions help distinguish a biological change from a technical difference.
Cellular mosaicism and chromosome mosaicism are different concepts. X-inactivation can create 2 functional neutrophil groups without 2 different chromosome counts; our chromosome mosaicism guide provides a useful contrast, although the diagnostic tests and inheritance counseling are not interchangeable.
Can myeloperoxidase deficiency mimic an abnormal DHR?
Myeloperoxidase deficiency can produce an abnormal DHR response despite preserved NADPH oxidase activity. Because dihydrorhodamine 123 fluorescence depends on downstream oxidation, a weak signal does not uniquely identify CGD; an experienced laboratory may use direct superoxide testing, nitroblue tetrazolium testing, or cellular MPO assessment to investigate the discrepancy.

Preserved superoxide production argues against a classic NADPH oxidase defect. If a patient's DHR is low but a second method demonstrates satisfactory superoxide generation, the 2 results should be reconciled rather than forcing both into a CGD diagnosis; MPO deficiency is one recognized explanation discussed in Holland's 2010 clinical review.
The laboratory may inspect eosinophil behavior because eosinophil peroxidase can preserve a different response pattern in MPO deficiency. That distinction requires correctly identified cellular populations; asking whether at least 2 granulocyte groups were considered is more useful than trying to infer the answer from total eosinophil percentage alone.
A circulating MPO concentration is not a neutrophil MPO-deficiency assessment. A result reported in ng/mL for vascular-risk evaluation addresses a different question; our MPO test limitations explain why identical enzyme names on 2 reports do not make those tests interchangeable.
Kantesti is an AI blood test interpretation platform that can distinguish the purpose of these differently named or differently measured MPO tests in a written report. When 2 functional assays disagree, our explanation should preserve that uncertainty and direct attention to the performing laboratory rather than assigning a premature inherited-disease label.
How can sample handling cause a falsely low burst?
Delayed processing, unsuitable temperatures, an incorrect collection tube, or poor cell viability can weaken a DHR response. Many laboratories aim to analyze specimens within approximately 24 hours; acceptance at 48 hours or beyond depends on their validated protocol, and a weak transported control makes an immediate CGD diagnosis unreliable.

The correct tube is laboratory-specific, although sodium-heparin specimens are commonly requested for DHR testing. Before collection, confirm the anticoagulant, minimum volume, transport temperature, and arrival deadline; a tube suitable for 1 routine chemistry panel may be unsuitable for a living-cell functional assay.
A healthy control collected and shipped alongside the patient's specimen can reveal transport-related loss of function. If both samples show reduced fluorescence after a 36-hour journey, that pattern supports investigating the shipment; a satisfactory control is reassuring, but it cannot exclude every patient-specific viability or gating problem.
An elevated hemolysis index does not measure neutrophil viability. A chemistry sample and a functional-cell specimen can fail for different reasons, even when collected at the same appointment; our sample artifact explanation illustrates why a quality flag must be interpreted for the particular assay.
Ask for 4 pieces of documentation: collection time, analysis time, transport conditions, and the laboratory's control assessment. Do not refrigerate or freeze a DHR specimen merely because another test required cold transport; handling instructions are assay-specific, and the performing laboratory should decide whether a redraw is necessary.
When should an abnormal oxidative burst be repeated?
Repeat DHR testing is appropriate when controls fail, handling is uncertain, results are borderline, or the pattern conflicts with the clinical picture. An almost absent response with a strong healthy control and characteristic infections warrants prompt immunology assessment; arranging a second specimen should not delay evaluation of an active infection.

There is no universal waiting period for a repeat DHR. A transport problem can justify a fresh specimen at the next practical opportunity, while severe illness or treatment-related changes may require an individualized interval; repeating after 2 weeks without fixing the original handling issue adds little confidence.
A useful repeat controls the variables that were uncertain the first time. Arrange at least 2 appropriately identified specimens if the laboratory requests a patient sample and transported healthy control, confirm same-day dispatch, and ask whether the laboratory can reserve a processing slot before collection.
DHR generally does not require fasting by itself. Preparation should focus on assay instructions and recent treatment history rather than skipping breakfast; our guía de preparación de primera extracción helps distinguish general appointment preparation from requirements specific to a living-cell test.
Granulocyte transfusions can introduce functioning donor neutrophils and create 2 populations, while stem-cell transplantation can produce mixed donor-recipient responses. Routine leukoreduced red-cell transfusion is not usually the same confounder; tell the laboratory exactly which product was given and when, rather than reporting only that a transfusion occurred.
Which clinical findings make abnormal DHR more concerning?
An abnormal DHR becomes more concerning when paired with recurrent deep infections, unusual organisms, granulomatous complications, or inflammatory bowel symptoms. An illustrative history of 2 liver abscess episodes carries more diagnostic weight than 2 uncomplicated colds; fever with breathing difficulty or rapidly worsening illness requires immediate assessment, not online interpretation.
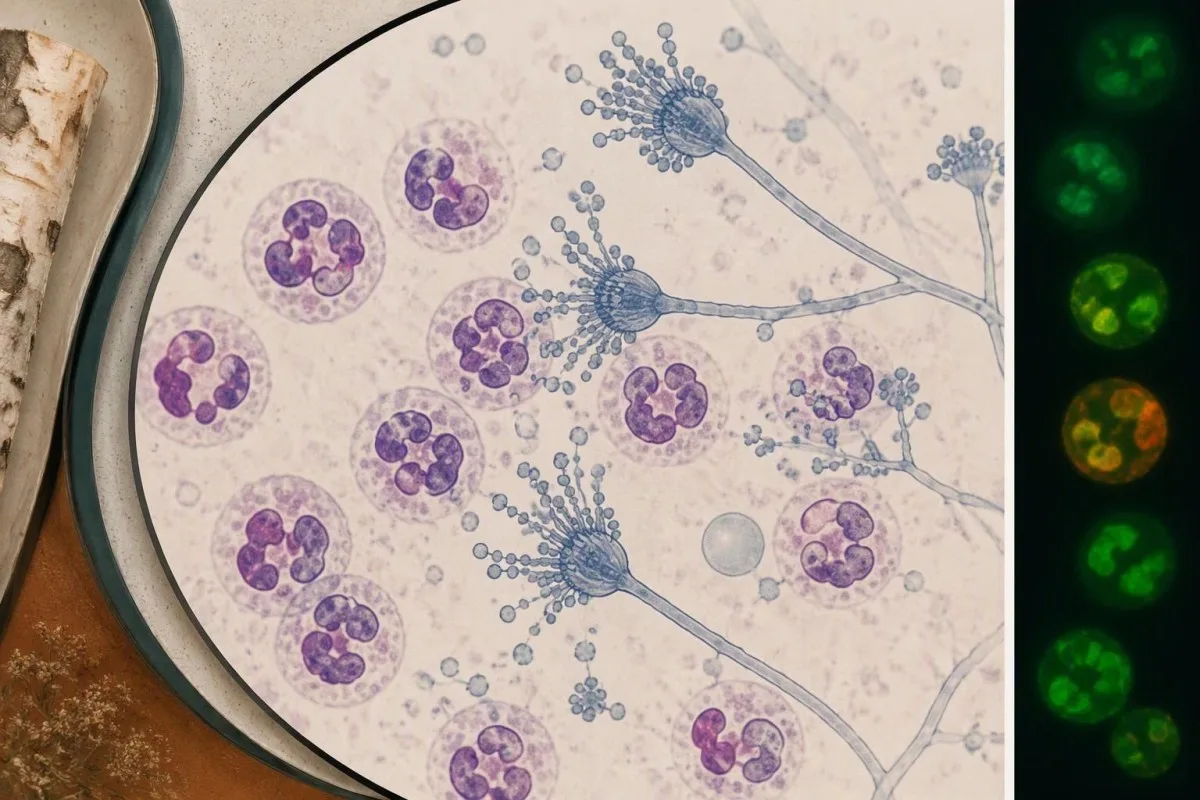
Aspergillus, Serratia, Burkholderia cepacia complex, Nocardia, and Staphylococcus aureus are recognized organisms in CGD, although none is exclusive to it. Holland's 2010 review describes the infection and inflammatory spectrum; the useful clinical question is whether 1 identified organism appeared in an unusual site or caused unexpectedly persistent disease.
An organism-specific test cannot measure oxidative burst function. Our fungal antigen interpretation illustrates the separate task of establishing fungal disease; a positive antigen and an abnormal DHR require different confirmation pathways, even when both are part of one patient's investigation.
CGD-related bowel inflammation can resemble inflammatory bowel disease. Persistent diarrhea, weight loss, or bloody stool warrants gastroenterology assessment, particularly alongside recurrent infections; a stool inflammatory marker measures intestinal inflammation, not neutrophil oxidase function, as our stool inflammation comparison -ek azaltzen duen moduan.
A temperature of 38.0°C or higher in someone with suspected or confirmed CGD deserves a low threshold for contacting the treating team, especially with new respiratory or focal symptoms. Emergency assessment is appropriate for breathing difficulty, confusion, rapidly progressive illness, or inability to maintain hydration; prophylactic medication should not be assumed to exclude infection.
What confirms a chronic granulomatous disease diagnosis?
Chronic granulomatous disease diagnosis combines a compatible functional defect with clinical assessment and usually molecular confirmation. Testing may examine at least 6 established CGD-associated genes—CYBB, CYBA, NCF1, NCF2, NCF4, and CYBC1—while broader panels can assess overlapping phagocyte disorders; a genetic variant of uncertain significance is not confirmation by itself.

CYBB-related CGD is X-linked; several other CGD forms are autosomal recessive. Gene identity influences inheritance counseling, but the DHR trace cannot reliably assign every molecular subtype; 2 patients with different genetic causes can produce similarly reduced responses, and variants within 1 gene can preserve different amounts of activity.
Genetic confirmation may require deletion-duplication analysis or specialized methods in addition to sequencing. NCF1 has closely related pseudogenes, which can complicate analysis; a negative generic panel should be reviewed for coverage and technical limitations before the clinician concludes that a convincing functional defect has no genetic explanation.
Normal PMA-stimulated DHR does not exclude every relevant phagocyte disorder. Some NCF4-related defects are better demonstrated with particulate stimulation, and other signaling disorders can affect receptor-mediated responses; when clinical suspicion remains high after 1 apparently normal test, the stimulus used becomes a critical detail.
Kantesti can explain why a functional test, gene panel, and clinical history sometimes disagree, but that disagreement belongs with an immunologist and the laboratory. The principle resembles borderline functional-test follow-up: neither 1 equivocal functional result nor 1 uncertain DNA variant should be stretched into a definitive diagnosis.
Who else in the family may need DHR or genetic testing?
Family testing should follow the confirmed inheritance pattern rather than an indiscriminate laboratory bundle. A person carrying a CYBB variant has a 50% chance of transmitting that X chromosome in each pregnancy; when both parents carry variants for the same autosomal-recessive condition, each pregnancy has a 25% chance of an affected child.

Those inheritance percentages apply independently to each pregnancy. For X-linked CYBB disease, the clinical consequence of inheriting the affected X differs according to the child's chromosome complement and X-inactivation; counseling should discuss affected sons, carrier daughters, and the possibility that a carrier can also develop significant symptoms.
A child with 1 affected CYBB variant may have inherited it or developed a new variant. Testing the mother can clarify family risk, but a normal maternal DHR does not exclude all forms of carrier mosaicism; targeted molecular testing is often needed once the child's causative variant is known.
Normal DHR usually cannot identify autosomal-recessive carriers. An unaffected sibling may still carry 1 familial variant, which matters for future reproductive counseling; targeted DNA testing answers that question more directly than repeating an oxidative-burst test that is expected to be normal in many such carriers.
A risk-based family testing plan should prioritize the relatives for whom the result changes care or reproductive decisions. For an illustrative family with 3 siblings, that might mean prompt evaluation of a symptomatic child, targeted testing of the others, and separate consent-based counseling for adults.
How should you prepare for specialist review of DHR?
Bring the complete DHR report, histogram, collection details, and infection history to specialist review. At least 4 elements should be clear: stimulus used, responding-cell fraction, fluorescence intensity or index, and healthy-control performance; a PDF containing only the word abnormal leaves too much unresolved for a reliable interpretation.

Kantesti is an AI-powered blood test analysis tool that can explain written DHR findings alongside CBC results and other uploaded laboratory information. Across a service used in 127+ countries, assay terminology may differ; our teknologiaren azalpena describes the interpretation workflow, not a substitute for direct inspection of raw cytometry files.
General interpretation performance does not establish DHR-specific diagnostic accuracy. A result delivered in approximately 60 seconds should still identify missing data and uncertainty; our validation and oversight information should be read for the actual evaluation scope rather than assumed to validate every rare functional assay.
The 3 questions I, Thomas Klein, would prioritize are practical: did the control pass, does the pattern suggest one deficient population or a mixture, and what confirmation will resolve the uncertainty? Our aholku-batzorde medikoa provides organizational clinical context; a treating immunologist remains responsible for individualized diagnosis and management.
A family-history tool cannot replace Mendelian genetic counseling, even if it helps organize affected relatives. Before sharing 1 report, remove unnecessary identifiers and preserve the assay comments and reference information; our AI txostenen segurtasun-gidak explains why source verification matters more than the confidence of an automated explanation.
Research publications and the limits of this interpretation
The evidence supporting DHR interpretation comes from CGD and phagocyte-function research, not unrelated digestive or hormonal publications. As of October 25, 2026, the 3 clinical references listed below support the disease mechanism, residual-function interpretation, and carrier discussion; this article does not claim that a new 2026 universal DHR cutoff exists.

Two additional publications are included as publisher-supplied background resources, not evidence for CGD diagnosis. The formal citations below reproduce the supplied titles and DOI identifiers; authorship and publication metadata have not been independently verified here, and ResearchGate and Academia.edu links are discovery searches rather than confirmed publication listings.
The citation beginning “Diarrhea After Fasting, Black Specks in Stool & GI Guide 2026” relates to broader digestive education, not oxidative-burst validation. Its associated digestive guide may help with symptom terminology, but it cannot establish whether 1 abnormal DHR result represents CGD-associated bowel disease.
The citation beginning “Women's Health Guide: Ovulation, Menopause & Hormonal Symptoms” is also separate from phagocyte-function evidence. Its associated hormonal health guide should not be used to explain carrier-related infection risk or to infer the significance of 2 neutrophil populations.
Kantesti educational content should distinguish verified clinical evidence from contextual publishing resources. Gure eduki medikoaren estandarrak describe that boundary; the safest next step after an abnormal DHR is a documented laboratory interpretation and an appropriate clinical plan, not a diagnosis based on 1 flagged value.
Maiz egiten diren galderak
DHR proba anormal batek esan nahi al du gaixotasun granulomatoso kronikoa dudala?
0 DHR proba anormal batek ez du automatikoki gaixotasun granulomatoso kronikoa baieztatzen. Erantzuna ia erabat falta izateak, kontrol osasuntsu egokia izanik, oxidasa-akats bat dagoela iradokitzen du indar handiz; hala ere, mieloperoxidasa-gabeziak, hondatutako laginek eta beste egoera batzuek ere fluoreszentzia murriztu dezakete. Neutrofiloen bi populazio bereizik X-ri lotutako eramaile-egoera edo emailearen eta hartzailearen zelula-nahasketak adieraz ditzakete, erantzun urritua uniformea dela baino. Baieztapena, normalean, espezialista baten ebaluazioaren, emaitza funtzional osoaren berrikuspenaren eta proba molekularren konbinazioaren bidez egiten da.
Zein da DHR probaren emaitzen balio-tarte normala?
DHR proben emaitzek ez dute laborategi guztietan balio duen erreferentzia-tarte numeriko unibertsalik. Erantzuten duten zelulen ehunekoa, fluoreszentziaren intentsitatea eta estimulazio-indizea saiakuntzaren eta haren kontrolen araberakoak dira. Adibidez, 98% neutrofiloek erantzuten dutela ikusteak ez du frogatzen haien fluoreszentziaren intentsitatea normala denik. Erabili proba egin duen laborategiaren erreferentzia-informazioa, eta interpretatu ehunekoa histogramarekin eta erantzunaren indarrarekin batera.
Zergatik izango lituzke CGD-eramaile batek bi gailur DHR proban?
An X-linked CGD carrier can have two DHR peaks because X-inactivation creates 2 neutrophil populations expressing different CYBB copies. One population may respond strongly while the other responds poorly. The proportions do not have to be 50:50, and a low functioning fraction can have clinical significance. Genetic testing and clinical history help distinguish carrier mosaicism from other causes of mixed populations.
Can a delayed specimen cause abnormal DHR test results?
A delayed or improperly handled specimen can produce a falsely weak DHR response because the test depends on viable neutrophils. Many laboratories target processing within approximately 24 hours, while acceptance at 48 hours or longer depends on validated local procedures. A healthy control transported alongside the patient sample can help identify shipping-related loss of function. If handling or control performance is unsatisfactory, the laboratory may recommend a fresh specimen rather than a disease diagnosis.
Can myeloperoxidase deficiency look like CGD on DHR testing?
Myeloperoxidase deficiency can reduce dihydrorhodamine 123 fluorescence even when NADPH oxidase still produces superoxide. A second functional method, such as direct superoxide measurement or appropriately performed nitroblue tetrazolium testing, may help distinguish it from classic CGD. Cellular MPO assessment and detailed granulocyte-pattern analysis can provide additional evidence. A circulating MPO concentration reported in ng/mL is not a substitute for this functional investigation.
Can a normal DHR test rule out CGD or carrier status?
A normal DHR result makes many classic CGD defects less likely, but it does not exclude every relevant phagocyte disorder or genetic carrier state. Some NCF4-related defects can show a satisfactory response to PMA while responding poorly to particulate stimulation. Autosomal-recessive carriers with 1 functioning gene copy commonly have normal DHR responses. Persistent clinical suspicion or a known familial variant should prompt specialist advice about additional functional or molecular testing.
Lortu gaur AI bidezko odol-analisien analisia
Batu mundu osoko 2 milioi erabiltzaile baino gehiagok Kantesti-n konfiantza dutenak, laborategiko analisiak berehala eta zehaztasunez aztertzeko. Igo zure odol-analisien emaitzak eta jaso 15,000+ biomarkatzaileen interpretazio integrala segundo gutxitan.
📚 Erreferentziatutako ikerketa-argitalpenak
Klein, T., Mitchell, S., & Weber, H. (2026). Baraualdiaren ondoren beherakoa, gorotzetan orban beltzak eta GI gida 2026. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Emakumeen Osasun Gida: Obulazioa, Menopausia eta Sintoma Hormonalak. Kantesti AI Medical Research.
📖 Kanpoko erreferentzia medikoak
Holland SM. (2010). Gaixotasun granulomatoso kronikoa. Clinical Reviews in Allergy & Immunology.
Kuhns DB et al. (2010). Residual NADPH oxidase and survival in chronic granulomatous disease. New England Journal of Medicine.
Marciano BE et al. (2018). X-linked carriers of chronic granulomatous disease: Illness, lyonization, and stability. Allergy and Clinical Immunology aldizkaria.



⚕️ Ohar medikoa
Artikulu hau hezkuntza-helburuetarako da soilik eta ez du mediku-aholkurik ematen. Diagnostiko- eta tratamendu-erabakietarako, beti kontsultatu osasun-profesional kualifikatu bati.
E-E-A-T Konfiantza-seinaleak
Esperientzia
Medikuek gidatutako berrikuspen klinikoa laborategiko interpretazioaren lan-fluxuei buruz.
Espezializazioa
Laborategiko medikuntzaren ikuspegia biomarkatzaileek testuinguru klinikoan nola jokatzen duten aztertzean.
Autoritatea
Dr. Thomas Klein-ek idatzia, eta Dr. Sarah Mitchell eta Prof. Dr. Hans Weber-ek berrikusia.
Fidagarritasuna
Ebidentzian oinarritutako interpretazioa, alarma murrizteko jarraipen-bide argiekin.
