After high-dose cancer treatment, a falling drug concentration is only part of the story. Infusion timing, kidney changes, and the rescue protocol explain why another laboratory check may mean another hospital night.

Vigtigste pointer
- Methotrexate levels after high-dose treatment are interpreted against the infusion clock, not a universal laboratory normal range.
- High-dose methotrexate generally means at least 500 mg/m²; monitoring differs fundamentally from low-dose weekly treatment for inflammatory conditions.
- Serial sampling commonly includes 24-, 48-, and 72-hour measurements, but some protocols require additional 36- or 42-hour checks.
- Nyrefunktion can deteriorate before symptoms appear; a creatinine increase of 0.3 mg/dL within 48 hours meets one standard criterion for acute kidney injury.
- Leucovorin rescue often runs every 6 hours, with dose and route adjusted to the treatment protocol, timed methotrexate concentration, and clinical condition.
- Urine alkalinization commonly targets a urine pH of at least 7 because methotrexate is less soluble in acidic urine.
- Glucarpidase may be needed for severe delayed elimination with kidney injury; consensus guidance emphasizes assessment early enough for treatment within approximately 48–60 hours of infusion start.
- Hospital discharge depends on the local protocol, kidney recovery, hydration, rescue arrangements, and follow-up—not a single methotrexate cutoff applied to everyone.
What do methotrexate levels mean after cancer treatment?
Methotrexate levels measure how much drug remains in plasma after treatment; clinicians interpret each result using the exact time since infusion, the cancer regimen, and kidney function. Delayed clearance can require longer IV hydration and stronger or prolonged leucovorin rescue, extending hospitalization without necessarily indicating treatment failure.

High-dose methotrexate generally refers to doses of at least 500 mg/m², although individual cancer protocols use substantially different doses and infusion durations. The same concentration can be expected early in treatment and concerning much later. That distinction is why a result labeled high by a laboratory cannot, by itself, establish toxicity or determine whether someone should stay in hospital.
A hypothetical patient receiving 3 g/m² over 24 hours needs a different interpretation from someone receiving 12 g/m² over 4 hours. Their end-of-infusion concentrations are not interchangeable, even if both reports use µmol/L. Clinicians compare results with the expected elimination curve for the actual regimen rather than borrowing a threshold from another cancer protocol.
Kantesti er en AI blodprøveanalysator for educational report explanations, not a replacement for the oncology team's time-specific rescue instructions. Our organisation og formål help distinguish that role from bedside monitoring. When a report contains 24- and 48-hour results, the useful question is whether the timestamps, infusion duration, and creatinine trend are available together.
How is high-dose monitoring different from weekly methotrexate?
High dose methotrexate monitoring measures serial drug concentrations after cancer treatment, whereas routine low-dose weekly monitoring usually checks blood counts, liver tests, and kidney function. A patient taking 15 mg once weekly for arthritis ordinarily does not need a cancer-treatment clearance curve.

Low-dose methotrexate commonly uses approximately 7.5–25 mg once weekly in adults with inflammatory disease; the prescribed dose and monitoring schedule vary. A complete blood count can reveal marrow suppression, while creatinine and liver enzymes assess factors affecting safety. These tests monitor consequences and risk, not a target plasma methotrexate concentration that should be maintained between weekly doses.
Accidentally taking a weekly prescription every day is an urgent medication error, even when a measured methotrexate concentration is low or undetectable. Repeated exposure can produce serious toxicity that a single plasma result does not exclude. Someone who took a 15 mg weekly dose on several consecutive days should seek immediate medical or poison-service advice rather than wait for routine laboratory testing.
Kantesti can help explain the difference between a drug concentration and the accompanying safety panel, but our explanations cannot establish that a dosing error is safe. Other medicines have their own monitoring logic: kidney-related levetiracetam monitoring illustrates why one drug's sampling rules cannot be transferred to another. Record both the prescribed weekly dose and the last administration date.
Why do sampling time and units change the interpretation?
Methotrexate concentrations need a clearly defined sampling clock: many protocols count hours from infusion start, while others include measurements timed from infusion completion. A 48-hour result cannot be interpreted correctly without knowing which clock the treatment team uses and whether the infusion lasted 4 or 24 hours.

Common sampling schedules include 24, 48, and 72 hours after infusion start, with extra measurements when elimination is delayed or the regimen requires them. Some rescue decisions specifically use 36- or 42-hour concentrations. A sample collected late should be interpreted at its actual collection time, not simply renamed as the scheduled 48-hour draw.
Methotrexate has a molecular mass of approximately 454.44 g/mol, so 1 µmol/L equals about 454 ng/mL. Likewise, 0.1 µmol/L equals approximately 45.4 ng/mL—not 0.1 ng/mL. Laboratories may report µmol/L, micromolar, or µM, which are equivalent concentration units; mixing these with mass units can create a several-hundred-fold interpretation error.
For a hypothetical 24-hour infusion starting Monday at 10:00, a Wednesday 10:00 sample is 48 hours from start but only 24 hours from completion. That arithmetic can change which rescue chart applies. Our guide to blood test timing differences explains broader timing effects, but chemotherapy records need the actual start, stop, collection, and result-release times.
Why does kidney injury delay methotrexate clearance?
Methotrexate clearance depends heavily on renal elimination, so acute kidney injury can leave high concentrations circulating longer and increase further toxicity. A creatinine rise of at least 0.3 mg/dL within 48 hours meets one standard acute kidney injury criterion, even if the final value remains inside the laboratory's reference interval.
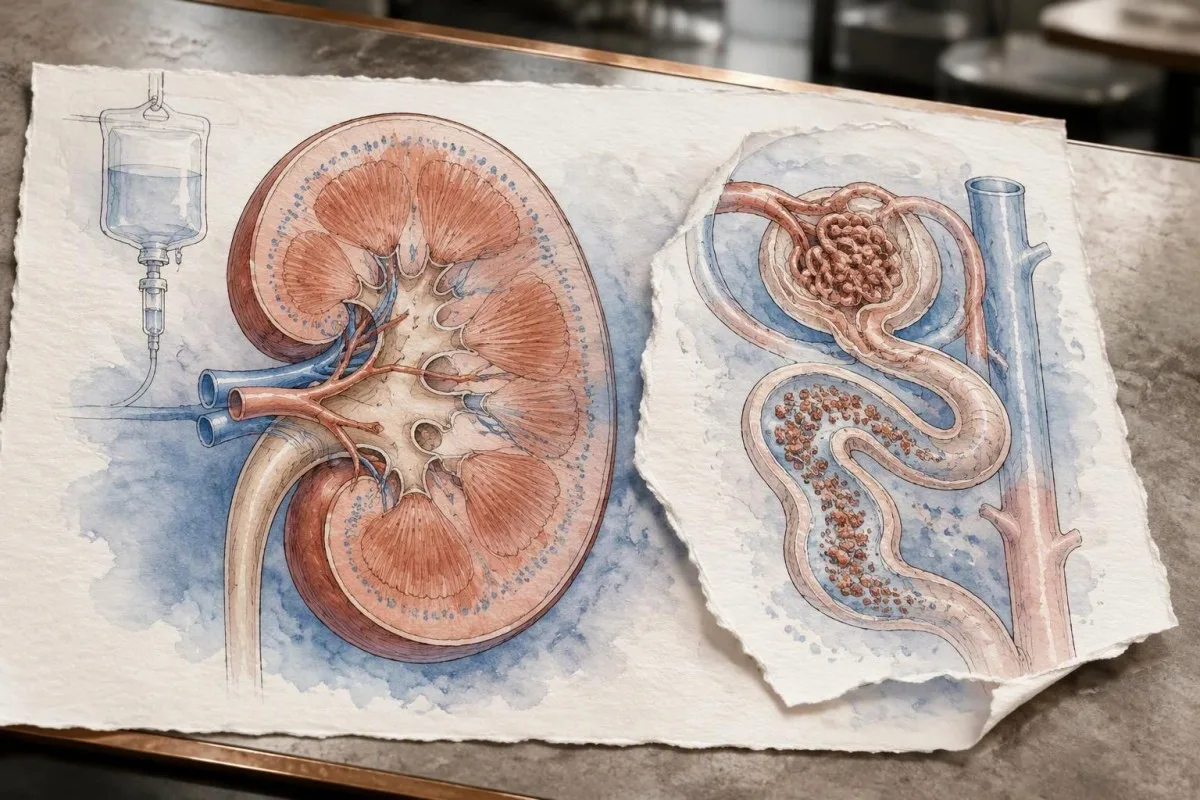
Methotrexate and its metabolites can precipitate in renal tubules, especially when urine is acidic or drug concentrations are high. The resulting kidney injury slows elimination and increases exposure—a self-reinforcing problem. Howard et al. reported acute kidney injury in approximately 2–12% of high-dose treatment recipients across heterogeneous settings, so that range is not an individual patient's predicted risk.
A hypothetical creatinine change from 0.7 to 1.1 mg/dL represents a 57% increase and exceeds the 0.3 mg/dL criterion. The significance comes from the change, not whether 1.1 mg/dL is flagged. Kantesti AI's educational explanations should therefore treat the baseline as relevant context; our BUN versus creatinine explanation clarifies why these markers are not interchangeable.
Reported eGFR becomes less dependable when creatinine is changing quickly because conventional equations assume a relatively steady state. During the first 24–48 hours of kidney injury, clinicians also assess urine output, fluid balance, electrolytes, and the drug elimination curve. The BUN- og kreatininratio guider provides background, but a reassuring ratio cannot rule out methotrexate-associated kidney injury.
How do hydration, urine pH, and medicines affect elimination?
IV hydration and urine alkalinization reduce the risk of methotrexate precipitation and support renal elimination; many high-dose protocols require urine pH of at least 7 before infusion. Clinicians also review interacting medicines, because increasing fluids alone may not correct a drug-related clearance problem.

Hydration regimens often use approximately 100–200 mL/m²/hour, but the prescribed rate depends on the cancer protocol, age, cardiac status, kidney function, and fluid balance. Urine pH is rechecked because a satisfactory initial result can fall during treatment. A dipstick color is not a methotrexate concentration; our urin dæksel fortolkning separates these measurements.
NSAIDs, some penicillins, proton pump inhibitors, and other medicines can interfere with renal elimination or increase toxicity risk. Management of trimethoprim-sulfamethoxazole prophylaxis varies by protocol, so patients should not independently stop an antimicrobial prescribed for cancer care. Give the oncology pharmacist a complete list before each infusion, including occasional ibuprofen and medicines taken during the previous 48 hours.
More fluid is not automatically safer when kidney function deteriorates or a patient develops fluid overload. Clinicians balance urine output against weight change, respiratory status, and sodium, potassium, and bicarbonate trends; a 2 kg short-term weight increase can reflect roughly 2 liters of retained fluid. Our elektrolytpanel-guide explains why these accompanying results may change the hydration plan.
What does leucovorin rescue actually protect?
Leucovorin rescue supplies reduced folate that helps normal cells bypass methotrexate's inhibition of folate metabolism; it does not directly remove methotrexate from plasma. Rescue often starts 24–42 hours after infusion begins, according to the regimen, and should not be postponed while waiting for a delayed laboratory result.
Methotrexate inhibits dihydrofolate reductase, limiting reduced folates needed for DNA synthesis and other cellular processes. Leucovorin, also called folinic acid, enters the folate pathway downstream of that blockade. The timing matters: giving rescue too early can interfere with intended anticancer exposure, while excessive delay increases normal-tissue toxicity; Howard et al. describe why rescue should not be delayed beyond 42–48 hours.
Folic acid and folinic acid are not interchangeable in high-dose rescue. A patient cannot substitute a 400 microgram dietary folic acid tablet for the prescribed leucovorin regimen, even though both relate to folate metabolism. Our low folate explanation addresses nutritional deficiency, which is a different problem from protecting cells during chemotherapy.
Leucovorin is commonly administered every 6 hours, but the actual dose, route, and duration follow the treatment protocol and measured elimination pattern. Mouth or gastrointestinal problems can make oral administration unreliable, and larger rescue doses generally require IV delivery. Ask whether rescue remains scheduled overnight: an extra laboratory draw does not replace a dose that was due at its prescribed time.
How do clinicians adjust rescue using time-specific levels?
Leucovorin doses are adjusted using the regimen's time-specific rescue table or nomogram, with kidney injury and clinical status adding urgency. A concentration of 5 µmol/L at 24 hours means something different from 5 µmol/L at 48 hours, so a universal dose-by-level chart would be misleading.

Some regimens begin leucovorin at 15 mg/m² every 6 hours, but that is an example rather than a prescription for every patient. For a hypothetical body surface area of 1.8 m², 15 mg/m² corresponds to 27 mg per dose before protocol-specific rounding. A delayed 42-hour result may trigger a substantially higher dose; the oncology pharmacist applies the relevant chart rather than extrapolating this example.
Oral leucovorin absorption becomes less reliable at higher doses, with saturation commonly discussed above approximately 25–40 mg. That is one reason a team may change from tablets to IV rescue despite a patient feeling well. Dose escalation protects normal tissues during prolonged exposure; it does not imply that the original methotrexate dose was necessarily wrong or that the cancer treatment has failed.
Kantesti er en AI blodprøvefortolkningsplatform, not a leucovorin dose calculator or a 24-hour infusion-monitoring service. Our kliniske valideringsoplysninger describes the distinction between educational interpretation and treatment decisions. The safest question is specific: which infusion clock and rescue table were used for this result, and has the prescribed dose already been adjusted?
When might glucarpidase be needed instead of rescue alone?
Glucarpidase may be indicated when markedly delayed methotrexate elimination occurs with kidney injury and concentrations exceed regimen-specific thresholds. Ramsey et al.'s 2018 consensus guidance emphasizes early assessment, ideally allowing administration within approximately 48–60 hours of infusion start when indicated.
For certain 24-hour infusion regimens, the consensus guideline identifies concentrations above 30 µmol/L at 36 hours, 10 µmol/L at 42 hours, or 5 µmol/L at 48 hours, together with a significant creatinine increase, as potential glucarpidase triggers. These are not universal toxicity boundaries or discharge targets. Shorter infusions and different doses require their own criteria, and a specialist must confirm the applicable pathway.
Glucarpidase is generally administered as a single IV dose of 50 units/kg and converts circulating methotrexate into metabolites that do not rely on the same renal elimination pathway. It does not remove intracellular methotrexate, so leucovorin remains necessary. Leucovorin should be separated from glucarpidase by at least 2 hours before and after administration because the enzyme can also act on leucovorin.
A patient should not wait until severe mouth problems or low counts develop before the team evaluates a concerning 36- or 42-hour result. Access and transfer arrangements may take time, making early discussion valuable even before every criterion is confirmed. Our salicylate treatment timing guide illustrates a broader principle: time-sensitive drug toxicity decisions cannot be based on symptoms alone.
Why can a methotrexate result look unexpectedly high?
Unexpected methotrexate results can reflect true delayed elimination, an incorrect timestamp, collection from a contaminated infusion line, or assay interference after glucarpidase. For approximately 48 hours after glucarpidase, common immunoassays can overestimate methotrexate because they also detect its breakdown product DAMPA.

A specimen collected from the lumen used for methotrexate infusion may be contaminated by residual drug, especially near infusion completion. An unexpectedly high concentration with stable creatinine can prompt verification using a correctly collected repeat specimen. That repeat does not justify delaying scheduled rescue; clinicians investigate the discrepancy while maintaining appropriate protection.
After glucarpidase, chromatographic methods can distinguish methotrexate from DAMPA more accurately than cross-reacting immunoassays. Hospitals differ in whether chromatography is locally available or must be sent elsewhere, potentially extending result turnaround beyond 24 hours. During this period, clinicians use the treatment history, available assay method, kidney trend, and specialist guidance rather than treating every reported concentration as directly comparable.
Kantesti's report explanations should preserve the laboratory's assay comments and distinguish collection time from result-release time. A 48-hour post-glucarpidase immunoassay result cannot safely be interpreted as though no enzyme treatment occurred. Our guide til prøveinterferens explains another source of laboratory uncertainty, although hemolysis does not explain every unexpectedly high methotrexate result.
Why can delayed clearance prolong hospitalization?
Delayed clearance prolongs hospitalization when safe care still requires IV fluids, alkalinization, repeated testing, or intensified rescue that cannot be delivered reliably outside hospital. A falling 72-hour methotrexate concentration is encouraging, but it does not by itself establish that kidney function, fluid balance, and the discharge plan are safe.
Many protocols continue monitoring or rescue until methotrexate falls below a locally specified endpoint, often somewhere around 0.05–0.1 µmol/L. Those values describe examples of protocol endpoints, not a universal discharge rule. Some services use different criteria or selected outpatient pathways, while others require additional inpatient observation because of kidney injury, symptoms, or practical limitations.
Consider a hypothetical patient whose level falls from 0.4 to 0.15 µmol/L between 72 and 96 hours. Discharge might still be delayed if creatinine continues rising, the patient needs IV rescue, or oral intake cannot maintain the prescribed hydration. Another patient with the same concentration but stable renal function may follow a different local pathway; comparing hospital stays without those details can be misleading.
Safe discharge requires an explicit rescue schedule when applicable, instructions on fluid intake and interacting medicines, a follow-up laboratory appointment, and a reachable oncology contact. Kidney abnormalities can outlast the most intensive concentration monitoring, so a 24- or 48-hour follow-up plan may matter even after discharge. Our post-hospitallaboratorieændringer styrer explains why recovery trends need their own interpretation.
Which symptoms and safety labs matter alongside the level?
Methotrexate toxicity assessment combines drug concentrations with kidney tests, blood counts, liver tests, fluid balance, and symptoms. During cancer treatment, fever of 38°C or higher commonly requires immediate contact with the oncology service, although patients should follow their team's specific fever threshold and emergency instructions.
New mouth soreness, persistent vomiting, inability to drink, marked diarrhea, unusual bruising, reduced urination, or worsening breathlessness should be reported promptly. These symptoms may develop after the highest plasma concentration has passed, so a low later result does not erase earlier exposure. A patient unable to keep down prescribed rescue for 6 hours needs urgent instructions rather than simply waiting for the next scheduled dose.
The absolute neutrophil count is more useful than the neutrophil percentage when assessing infection risk; an ANC below 0.5 × 10⁹/L represents severe neutropenia. Fever during neutropenia can be an emergency regardless of the methotrexate concentration. Our guide til neutrofiltal explains the count-versus-percentage distinction, but it cannot replace the cancer service's emergency pathway.
Potassium, phosphate, calcium, uric acid, and creatinine may also be monitored because other cancer-treatment complications can affect the kidneys. Tumorlysesyndrom is not the same condition as delayed methotrexate clearance, and the 2 problems may require different interventions. Our tumor lysis laboratory guide helps explain why clinicians do not attribute every abnormal renal result to methotrexate.
What should people taking weekly methotrexate monitor?
Weekly methotrexate safety monitoring usually includes a complete blood count, liver enzymes, and creatinine or eGFR rather than serial plasma drug levels. Checks are often more frequent during the first weeks or after dose changes, then commonly every 8–12 weeks once stable, depending on the specialty and local guidance.

A stable 15 mg weekly prescription does not eliminate the need for monitoring when kidney function changes, another medicine is started, or dehydration develops. Reduced renal elimination can increase exposure even without a dose increase. Patients should tell their prescriber about vomiting, diarrhea, new antibiotics, and over-the-counter NSAIDs rather than assuming the previously tolerated dose remains equally safe.
An isolated mild ALT increase and a falling platelet count answer different safety questions, so the whole panel and its trajectory matter. Persistent abnormalities can lead to repeat testing, temporary withholding, dose adjustment, or investigation of another cause, according to local thresholds. Our guide til forkortelser for leverprøver explains why a panel of 4–6 liver-related markers is not one interchangeable result.
Kantesti can help organize the accompanying CBC, liver, and renal trends for a discussion with the prescriber, but our platform cannot authorize the next weekly dose. Folic acid supplementation is commonly prescribed with low-dose treatment; the amount and schedule are not the same as 6-hourly cancer rescue. Keep the methotrexate day visibly distinct from any daily medicines, and confirm instructions whenever a prescription changes.
Does delayed clearance mean methotrexate must be stopped forever?
Delayed clearance does not automatically rule out future methotrexate treatment, but another high-dose cycle requires reassessment of renal recovery, the prior elimination pattern, interacting medicines, and the cancer benefit. A creatinine result checked 7 days later may be useful, yet recovery cannot be judged by elapsed time alone.

Kidney injury after high-dose methotrexate is often reversible with appropriate care, although recovery speed and completeness vary. Howard et al. describe that selected patients can receive subsequent high-dose treatment after renal recovery, including some previously treated with glucarpidase. That observation is not permission to restart; the team may change the dose, supportive measures, or treatment choice after reviewing the entire episode.
Hydration-related improvement in creatinine does not prove that every aspect of renal handling has returned to baseline. A patient whose creatinine changes from 1.4 to 1.0 mg/dL may still differ from a pre-treatment baseline of 0.7 mg/dL. Our guide til dehydrering og eGFR explains reversible influences, while chemotherapy planning also considers the previous timed drug concentrations.
Low albumin, pleural fluid, or ascites can complicate methotrexate pharmacokinetics; fluid collections may act as compartments from which drug returns slowly to the circulation. An albumin of 2.8 g/dL is therefore relevant context, not an independent rescue-dose formula. Our serum protein tolkning guide explains albumin's broader meaning, including why low values can reflect several different underlying processes.
How should patients use AI explanations and the evidence?
AI explanations of methotrexate levels should support questions about the report, not determine rescue doses, glucarpidase eligibility, or discharge. Bring at least the infusion start and stop times, actual sample times, current and baseline creatinine, and rescue record; a lone 48-hour concentration leaves essential clinical context missing.

Kantesti er en AI-drevet værktøj til analyse af blodprøver that supports educational questions about laboratory trends, not time-critical chemotherapy decisions. Our AI-teknologiguide explains the platform's role. A 5 µmol/L result should first prompt verification of the infusion clock and the oncology plan, not an automated instruction to change leucovorin.
Share only the information needed for the explanation and follow the hospital's rules for treatment records. Infusion timestamps and laboratory units are clinically useful, while unrelated identifying details may not be necessary; our oplysninger om privatliv og data explains our approach. If 2 reports disagree, preserve their original assay comments and ask the treating team which result governs the current plan.
The directly relevant evidence below includes Howard et al.'s 2016 toxicity review, Ramsey et al.'s 2018 glucarpidase consensus, and the 2024 European consensus on delayed elimination. The 2 separate Zenodo publications listed below concern complement testing and Nipah diagnosis; they are educational publications, not evidence for methotrexate rescue thresholds. Our AI-forklaringssikkerhedsvejledning helps readers distinguish topic-specific clinical references from broader platform material.
Ofte stillede spørgsmål
Hvad er et sikkert methotrexatniveau før udskrivelse fra hospitalet?
Der findes ikke én universel methotrexatkoncentration, der gør udskrivning sikker ved alle kræftbehandlinger med højdosisregimer. Mange protokoller anvender monitorerings- eller redningsbehandlingsgrænser omkring 0,05–0,1 µmol/L, men disse eksempler kan ikke bruges som enslydende regler for udskrivning. Klinikerne vurderer også nyrefunktionens bedring, væskebalancen, det orale indtag, behovet for redningsbehandling og muligheden for opfølgende prøvetagning. Spørg, hvilken lokal protokol der gælder, og om der stadig er behov for leucovorin eller yderligere laboratorieprøver efter udskrivelsen.
Hvorfor er mit methotrexatniveau stadig højt efter 48 timer?
En høj methotrexatkoncentration efter 48 timer kan afspejle forsinket renal udskillelse, nyreskade, interagerende lægemidler, væskeansamlinger eller et regime, hvor de forventede tidlige koncentrationer er højere. Fortolkningen kræver viden om, hvorvidt de 48 timer måles fra infusionens start eller afslutning. En kreatininstigning på 0,3 mg/dL inden for 48 timer opfylder ét standardkriterium for akut nyreskade og bør tages alvorligt, selv når den endelige værdi ikke er markeret som unormal af laboratoriet. Onkologiteamet kan intensivere redningsbehandlingen, justere den understøttende behandling, kontrollere prøven eller vurdere, om kriterierne for glucarpidasebehandling er opfyldt.
Sænker leucovorin methotrexatniveauet?
Leucovorin beskytter normale celler ved at tilføre reduceret folat, men fjerner ikke methotrexat direkte fra plasmaet. Rescue gives typisk hver 6. time, hvor den præcise dosis og administrationsvej bestemmes af kræftprotokollen og koncentrationsmålingerne på de fastsatte tidspunkter. Hydrering og alkalisering understøtter renal elimination, mens glucarpidase enzymatisk kan nedbryde cirkulerende methotrexat, når det er indiceret. Koncentrationen kan derfor fortsat være forhøjet, selv mens der gives passende leucovorin-rescue.
Hvornår anvendes glucarpidase ved forsinket clearance af methotrexat?
Glukarpidase overvejes ved alvorligt forsinket elimination af methotrexat med nyreskade, når de regimenspecifikke koncentrationsgrænser overskrides. For visse 24-timers infusionsregimer omfatter konsensusretningslinjen fra 2018 koncentrationer over 30 µmol/L efter 36 timer, 10 µmol/L efter 42 timer eller 5 µmol/L efter 48 timer sammen med en signifikant stigning i kreatinin. Specialister skal kontrollere, at disse kriterier gælder for den faktiske dosis og infusionsvarighed. Vejledningen understreger tidlig vurdering, så indiceret behandling ideelt kan finde sted inden for cirka 48–60 timer efter infusionens start.
Har jeg brug for at få målt methotrexatniveauer, hvis jeg tager det én gang om ugen?
Rutinemæssige målinger af methotrexatniveauer i plasma bruges generelt ikke til at overvåge standardbehandling med lave ugentlige doser mod inflammatoriske tilstande. Sikkerhedsovervågning omfatter i stedet normalt en fuldstændig blodtælling, leverenzymer og kreatinin eller eGFR, ofte hver 8.–12. uge, når behandlingen er stabil, i henhold til en lokal protokol. At tage en ugentlig dosis hver dag er en akut doseringsfejl, og en lav målt koncentration kan ikke pålideligt udelukke alvorlig toksicitet efter gentagen eksponering. Kontakt straks en læge eller giftlinje, hvis der er taget ekstra doser.
Kan methotrexatniveauer være misvisende efter glucarpidase?
Methotrexate immunoassays can report falsely elevated concentrations for approximately 48 hours after glucarpidase because they cross-react with the breakdown product DAMPA. Chromatographic methods can distinguish methotrexate from that metabolite more accurately, although availability varies between hospitals. Leucovorin remains necessary because glucarpidase does not remove intracellular methotrexate. The oncology team interprets post-treatment results using the assay method, renal trend, timing, and specialist rescue guidance.
Få dine blodprøveresultater forklaret
Upload din laboratorierapport, så forklarer Kantesti's AI hver biomarkør i et letforståeligt sprog på få sekunder. Bruges af mere end 2 millioner mennesker verden over.
Referencer
- Klein, T., Mitchell, S., & Weber, H. (2026). Guide til C3-, C4- og ANA-titer-blodprøver. Kantesti AI Medicinsk forskning. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Blodprøve for Nipah-virus: Guide til tidlig påvisning og diagnosticering 2026. Kantesti AI Medicinsk forskning. DOI
- Howard SC et al. (2016). Preventing and Managing Toxicities of High-Dose Methotrexate. The Oncologist. DOI PubMed
- Ramsey LB et al. (2018). Consensus Guideline for Use of Glucarpidase in Patients with High-Dose Methotrexate Induced Acute Kidney Injury and Delayed Methotrexate Clearance. The Oncologist. DOI PubMed
- Bielack SS et al. (2024). A European consensus recommendation on the management of delayed methotrexate elimination: supportive measures, leucovorin rescue and glucarpidase treatment. Journal of Cancer Research and Clinical Oncology.
- 2 mio.+Analyserede test
- 127+lande
- 100+Sprog
Om det medicinske team


E-E-A-T Trust Signals
Erfaring
Lægefagligt ledet klinisk gennemgang af arbejdsgange til laboratorietolkning.
Ekspertise
Fokus på laboratoriemedicin på, hvordan biomarkører opfører sig i klinisk kontekst.
Autoritet
Medicinsk gennemgået af Dr. Thomas Klein med bidrag fra Dr. Sarah Mitchell og Prof. Dr. Hans Weber.
Troværdighed
Evidensbaseret fortolkning med klare opfølgningsspor for at reducere alarm.





Medicinsk ansvarsfraskrivelse
Denne artikel er kun til undervisningsformål og udgør ikke lægelig rådgivning. Rådfør dig altid med en kvalificeret sundhedsprofessionel for beslutninger om diagnose og behandling.
Publiceret · Kontakt redaktionen
Udgivet af Kantesti Ltd, registreret i England og Wales, virksomhedsnummer. 17090423, London, Storbritannien.
