After high-dose cancer treatment, a falling drug concentration is only part of the story. Infusion timing, kidney changes, and the rescue protocol explain why another laboratory check may mean another hospital night.

Những điểm chính cần ghi nhớ
- Methotrexate levels after high-dose treatment are interpreted against the infusion clock, not a universal laboratory normal range.
- High-dose methotrexate generally means at least 500 mg/m²; monitoring differs fundamentally from low-dose weekly treatment for inflammatory conditions.
- Serial sampling commonly includes 24-, 48-, and 72-hour measurements, but some protocols require additional 36- or 42-hour checks.
- Chức năng thận can deteriorate before symptoms appear; a creatinine increase of 0.3 mg/dL within 48 hours meets one standard criterion for acute kidney injury.
- Leucovorin rescue often runs every 6 hours, with dose and route adjusted to the treatment protocol, timed methotrexate concentration, and clinical condition.
- Urine alkalinization commonly targets a urine pH of at least 7 because methotrexate is less soluble in acidic urine.
- Glucarpidase may be needed for severe delayed elimination with kidney injury; consensus guidance emphasizes assessment early enough for treatment within approximately 48–60 hours of infusion start.
- Hospital discharge depends on the local protocol, kidney recovery, hydration, rescue arrangements, and follow-up—not a single methotrexate cutoff applied to everyone.
What do methotrexate levels mean after cancer treatment?
Methotrexate levels measure how much drug remains in plasma after treatment; clinicians interpret each result using the exact time since infusion, the cancer regimen, and kidney function. Delayed clearance can require longer IV hydration and stronger or prolonged leucovorin rescue, extending hospitalization without necessarily indicating treatment failure.

High-dose methotrexate generally refers to doses of at least 500 mg/m², although individual cancer protocols use substantially different doses and infusion durations. The same concentration can be expected early in treatment and concerning much later. That distinction is why a result labeled high by a laboratory cannot, by itself, establish toxicity or determine whether someone should stay in hospital.
A hypothetical patient receiving 3 g/m² over 24 hours needs a different interpretation from someone receiving 12 g/m² over 4 hours. Their end-of-infusion concentrations are not interchangeable, even if both reports use µmol/L. Clinicians compare results with the expected elimination curve for the actual regimen rather than borrowing a threshold from another cancer protocol.
Kantesti là một Máy phân tích xét nghiệm máu AI for educational report explanations, not a replacement for the oncology team's time-specific rescue instructions. Our và mục đích của chúng tôi help distinguish that role from bedside monitoring. When a report contains 24- and 48-hour results, the useful question is whether the timestamps, infusion duration, and creatinine trend are available together.
How is high-dose monitoring different from weekly methotrexate?
High dose methotrexate monitoring measures serial drug concentrations after cancer treatment, whereas routine low-dose weekly monitoring usually checks blood counts, liver tests, and kidney function. A patient taking 15 mg once weekly for arthritis ordinarily does not need a cancer-treatment clearance curve.

Low-dose methotrexate commonly uses approximately 7.5–25 mg once weekly in adults with inflammatory disease; the prescribed dose and monitoring schedule vary. A complete blood count can reveal marrow suppression, while creatinine and liver enzymes assess factors affecting safety. These tests monitor consequences and risk, not a target plasma methotrexate concentration that should be maintained between weekly doses.
Accidentally taking a weekly prescription every day is an urgent medication error, even when a measured methotrexate concentration is low or undetectable. Repeated exposure can produce serious toxicity that a single plasma result does not exclude. Someone who took a 15 mg weekly dose on several consecutive days should seek immediate medical or poison-service advice rather than wait for routine laboratory testing.
Kantesti can help explain the difference between a drug concentration and the accompanying safety panel, but our explanations cannot establish that a dosing error is safe. Other medicines have their own monitoring logic: kidney-related levetiracetam monitoring illustrates why one drug's sampling rules cannot be transferred to another. Record both the prescribed weekly dose and the last administration date.
Why do sampling time and units change the interpretation?
Methotrexate concentrations need a clearly defined sampling clock: many protocols count hours from infusion start, while others include measurements timed from infusion completion. A 48-hour result cannot be interpreted correctly without knowing which clock the treatment team uses and whether the infusion lasted 4 or 24 hours.

Common sampling schedules include 24, 48, and 72 hours after infusion start, with extra measurements when elimination is delayed or the regimen requires them. Some rescue decisions specifically use 36- or 42-hour concentrations. A sample collected late should be interpreted at its actual collection time, not simply renamed as the scheduled 48-hour draw.
Methotrexate has a molecular mass of approximately 454.44 g/mol, so 1 µmol/L equals about 454 ng/mL. Likewise, 0.1 µmol/L equals approximately 45.4 ng/mL—not 0.1 ng/mL. Laboratories may report µmol/L, micromolar, or µM, which are equivalent concentration units; mixing these with mass units can create a several-hundred-fold interpretation error.
For a hypothetical 24-hour infusion starting Monday at 10:00, a Wednesday 10:00 sample is 48 hours from start but only 24 hours from completion. That arithmetic can change which rescue chart applies. Our guide to blood test timing differences explains broader timing effects, but chemotherapy records need the actual start, stop, collection, and result-release times.
Why does kidney injury delay methotrexate clearance?
Methotrexate clearance depends heavily on renal elimination, so acute kidney injury can leave high concentrations circulating longer and increase further toxicity. A creatinine rise of at least 0.3 mg/dL within 48 hours meets one standard acute kidney injury criterion, even if the final value remains inside the laboratory's reference interval.
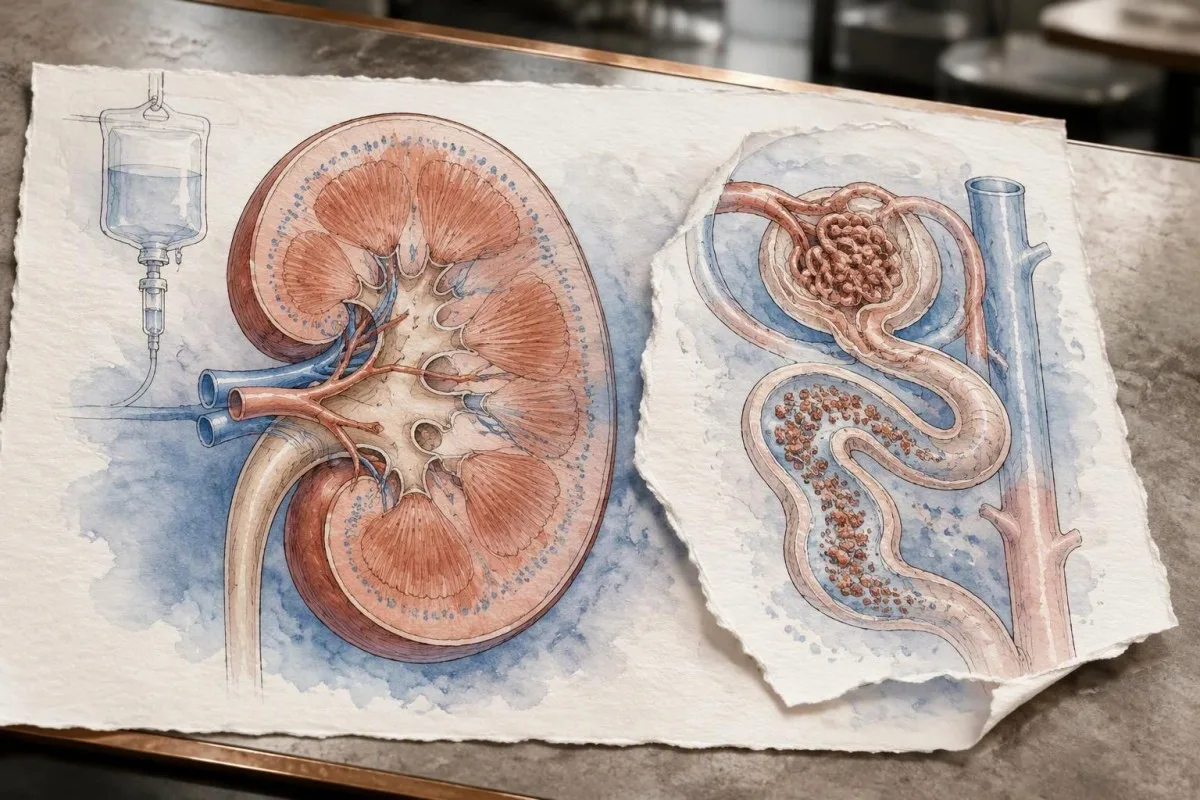
Methotrexate and its metabolites can precipitate in renal tubules, especially when urine is acidic or drug concentrations are high. The resulting kidney injury slows elimination and increases exposure—a self-reinforcing problem. Howard et al. reported acute kidney injury in approximately 2–12% of high-dose treatment recipients across heterogeneous settings, so that range is not an individual patient's predicted risk.
A hypothetical creatinine change from 0.7 to 1.1 mg/dL represents a 57% increase and exceeds the 0.3 mg/dL criterion. The significance comes from the change, not whether 1.1 mg/dL is flagged. Kantesti AI's educational explanations should therefore treat the baseline as relevant context; our BUN versus creatinine explanation clarifies why these markers are not interchangeable.
Reported eGFR becomes less dependable when creatinine is changing quickly because conventional equations assume a relatively steady state. During the first 24–48 hours of kidney injury, clinicians also assess urine output, fluid balance, electrolytes, and the drug elimination curve. The tỷ lệ BUN và creatinine hướng dẫn provides background, but a reassuring ratio cannot rule out methotrexate-associated kidney injury.
How do hydration, urine pH, and medicines affect elimination?
IV hydration and urine alkalinization reduce the risk of methotrexate precipitation and support renal elimination; many high-dose protocols require urine pH of at least 7 before infusion. Clinicians also review interacting medicines, because increasing fluids alone may not correct a drug-related clearance problem.

Hydration regimens often use approximately 100–200 mL/m²/hour, but the prescribed rate depends on the cancer protocol, age, cardiac status, kidney function, and fluid balance. Urine pH is rechecked because a satisfactory initial result can fall during treatment. A dipstick color is not a methotrexate concentration; our diễn giải que thử nước tiểu separates these measurements.
NSAIDs, some penicillins, proton pump inhibitors, and other medicines can interfere with renal elimination or increase toxicity risk. Management of trimethoprim-sulfamethoxazole prophylaxis varies by protocol, so patients should not independently stop an antimicrobial prescribed for cancer care. Give the oncology pharmacist a complete list before each infusion, including occasional ibuprofen and medicines taken during the previous 48 hours.
More fluid is not automatically safer when kidney function deteriorates or a patient develops fluid overload. Clinicians balance urine output against weight change, respiratory status, and sodium, potassium, and bicarbonate trends; a 2 kg short-term weight increase can reflect roughly 2 liters of retained fluid. Our bảng điện giải của chúng tôi explains why these accompanying results may change the hydration plan.
What does leucovorin rescue actually protect?
Leucovorin rescue supplies reduced folate that helps normal cells bypass methotrexate's inhibition of folate metabolism; it does not directly remove methotrexate from plasma. Rescue often starts 24–42 hours after infusion begins, according to the regimen, and should not be postponed while waiting for a delayed laboratory result.
Methotrexate inhibits dihydrofolate reductase, limiting reduced folates needed for DNA synthesis and other cellular processes. Leucovorin, also called folinic acid, enters the folate pathway downstream of that blockade. The timing matters: giving rescue too early can interfere with intended anticancer exposure, while excessive delay increases normal-tissue toxicity; Howard et al. describe why rescue should not be delayed beyond 42–48 hours.
Folic acid and folinic acid are not interchangeable in high-dose rescue. A patient cannot substitute a 400 microgram dietary folic acid tablet for the prescribed leucovorin regimen, even though both relate to folate metabolism. Our low folate explanation addresses nutritional deficiency, which is a different problem from protecting cells during chemotherapy.
Leucovorin is commonly administered every 6 hours, but the actual dose, route, and duration follow the treatment protocol and measured elimination pattern. Mouth or gastrointestinal problems can make oral administration unreliable, and larger rescue doses generally require IV delivery. Ask whether rescue remains scheduled overnight: an extra laboratory draw does not replace a dose that was due at its prescribed time.
How do clinicians adjust rescue using time-specific levels?
Leucovorin doses are adjusted using the regimen's time-specific rescue table or nomogram, with kidney injury and clinical status adding urgency. A concentration of 5 µmol/L at 24 hours means something different from 5 µmol/L at 48 hours, so a universal dose-by-level chart would be misleading.

Some regimens begin leucovorin at 15 mg/m² every 6 hours, but that is an example rather than a prescription for every patient. For a hypothetical body surface area of 1.8 m², 15 mg/m² corresponds to 27 mg per dose before protocol-specific rounding. A delayed 42-hour result may trigger a substantially higher dose; the oncology pharmacist applies the relevant chart rather than extrapolating this example.
Oral leucovorin absorption becomes less reliable at higher doses, with saturation commonly discussed above approximately 25–40 mg. That is one reason a team may change from tablets to IV rescue despite a patient feeling well. Dose escalation protects normal tissues during prolonged exposure; it does not imply that the original methotrexate dose was necessarily wrong or that the cancer treatment has failed.
Kantesti là một nền tảng giải thích kết quả xét nghiệm máu AI, not a leucovorin dose calculator or a 24-hour infusion-monitoring service. Our thông tin xác thực lâm sàng describes the distinction between educational interpretation and treatment decisions. The safest question is specific: which infusion clock and rescue table were used for this result, and has the prescribed dose already been adjusted?
When might glucarpidase be needed instead of rescue alone?
Glucarpidase may be indicated when markedly delayed methotrexate elimination occurs with kidney injury and concentrations exceed regimen-specific thresholds. Ramsey et al.'s 2018 consensus guidance emphasizes early assessment, ideally allowing administration within approximately 48–60 hours of infusion start when indicated.
For certain 24-hour infusion regimens, the consensus guideline identifies concentrations above 30 µmol/L at 36 hours, 10 µmol/L at 42 hours, or 5 µmol/L at 48 hours, together with a significant creatinine increase, as potential glucarpidase triggers. These are not universal toxicity boundaries or discharge targets. Shorter infusions and different doses require their own criteria, and a specialist must confirm the applicable pathway.
Glucarpidase is generally administered as a single IV dose of 50 units/kg and converts circulating methotrexate into metabolites that do not rely on the same renal elimination pathway. It does not remove intracellular methotrexate, so leucovorin remains necessary. Leucovorin should be separated from glucarpidase by at least 2 hours before and after administration because the enzyme can also act on leucovorin.
A patient should not wait until severe mouth problems or low counts develop before the team evaluates a concerning 36- or 42-hour result. Access and transfer arrangements may take time, making early discussion valuable even before every criterion is confirmed. Our salicylate treatment timing guide illustrates a broader principle: time-sensitive drug toxicity decisions cannot be based on symptoms alone.
Why can a methotrexate result look unexpectedly high?
Unexpected methotrexate results can reflect true delayed elimination, an incorrect timestamp, collection from a contaminated infusion line, or assay interference after glucarpidase. For approximately 48 hours after glucarpidase, common immunoassays can overestimate methotrexate because they also detect its breakdown product DAMPA.

A specimen collected from the lumen used for methotrexate infusion may be contaminated by residual drug, especially near infusion completion. An unexpectedly high concentration with stable creatinine can prompt verification using a correctly collected repeat specimen. That repeat does not justify delaying scheduled rescue; clinicians investigate the discrepancy while maintaining appropriate protection.
After glucarpidase, chromatographic methods can distinguish methotrexate from DAMPA more accurately than cross-reacting immunoassays. Hospitals differ in whether chromatography is locally available or must be sent elsewhere, potentially extending result turnaround beyond 24 hours. During this period, clinicians use the treatment history, available assay method, kidney trend, and specialist guidance rather than treating every reported concentration as directly comparable.
Kantesti's report explanations should preserve the laboratory's assay comments and distinguish collection time from result-release time. A 48-hour post-glucarpidase immunoassay result cannot safely be interpreted as though no enzyme treatment occurred. Our Hướng dẫn về nhiễu mẫu của chúng tôi explains another source of laboratory uncertainty, although hemolysis does not explain every unexpectedly high methotrexate result.
Why can delayed clearance prolong hospitalization?
Delayed clearance prolongs hospitalization when safe care still requires IV fluids, alkalinization, repeated testing, or intensified rescue that cannot be delivered reliably outside hospital. A falling 72-hour methotrexate concentration is encouraging, but it does not by itself establish that kidney function, fluid balance, and the discharge plan are safe.
Many protocols continue monitoring or rescue until methotrexate falls below a locally specified endpoint, often somewhere around 0.05–0.1 µmol/L. Those values describe examples of protocol endpoints, not a universal discharge rule. Some services use different criteria or selected outpatient pathways, while others require additional inpatient observation because of kidney injury, symptoms, or practical limitations.
Consider a hypothetical patient whose level falls from 0.4 to 0.15 µmol/L between 72 and 96 hours. Discharge might still be delayed if creatinine continues rising, the patient needs IV rescue, or oral intake cannot maintain the prescribed hydration. Another patient with the same concentration but stable renal function may follow a different local pathway; comparing hospital stays without those details can be misleading.
Safe discharge requires an explicit rescue schedule when applicable, instructions on fluid intake and interacting medicines, a follow-up laboratory appointment, and a reachable oncology contact. Kidney abnormalities can outlast the most intensive concentration monitoring, so a 24- or 48-hour follow-up plan may matter even after discharge. Our thay đổi xét nghiệm sau nhập viện của chúng tôi hướng dẫn explains why recovery trends need their own interpretation.
Which symptoms and safety labs matter alongside the level?
Methotrexate toxicity assessment combines drug concentrations with kidney tests, blood counts, liver tests, fluid balance, and symptoms. During cancer treatment, fever of 38°C or higher commonly requires immediate contact with the oncology service, although patients should follow their team's specific fever threshold and emergency instructions.
New mouth soreness, persistent vomiting, inability to drink, marked diarrhea, unusual bruising, reduced urination, or worsening breathlessness should be reported promptly. These symptoms may develop after the highest plasma concentration has passed, so a low later result does not erase earlier exposure. A patient unable to keep down prescribed rescue for 6 hours needs urgent instructions rather than simply waiting for the next scheduled dose.
The absolute neutrophil count is more useful than the neutrophil percentage when assessing infection risk; an ANC below 0.5 × 10⁹/L represents severe neutropenia. Fever during neutropenia can be an emergency regardless of the methotrexate concentration. Our hướng dẫn về số lượng bạch cầu trung tính explains the count-versus-percentage distinction, but it cannot replace the cancer service's emergency pathway.
Potassium, phosphate, calcium, uric acid, and creatinine may also be monitored because other cancer-treatment complications can affect the kidneys. Hội chứng ly giải khối u is not the same condition as delayed methotrexate clearance, and the 2 problems may require different interventions. Our tumor lysis laboratory guide helps explain why clinicians do not attribute every abnormal renal result to methotrexate.
What should people taking weekly methotrexate monitor?
Weekly methotrexate safety monitoring usually includes a complete blood count, liver enzymes, and creatinine or eGFR rather than serial plasma drug levels. Checks are often more frequent during the first weeks or after dose changes, then commonly every 8–12 weeks once stable, depending on the specialty and local guidance.

A stable 15 mg weekly prescription does not eliminate the need for monitoring when kidney function changes, another medicine is started, or dehydration develops. Reduced renal elimination can increase exposure even without a dose increase. Patients should tell their prescriber about vomiting, diarrhea, new antibiotics, and over-the-counter NSAIDs rather than assuming the previously tolerated dose remains equally safe.
An isolated mild ALT increase and a falling platelet count answer different safety questions, so the whole panel and its trajectory matter. Persistent abnormalities can lead to repeat testing, temporary withholding, dose adjustment, or investigation of another cause, according to local thresholds. Our viết tắt xét nghiệm gan của chúng tôi explains why a panel of 4–6 liver-related markers is not one interchangeable result.
Kantesti can help organize the accompanying CBC, liver, and renal trends for a discussion with the prescriber, but our platform cannot authorize the next weekly dose. Folic acid supplementation is commonly prescribed with low-dose treatment; the amount and schedule are not the same as 6-hourly cancer rescue. Keep the methotrexate day visibly distinct from any daily medicines, and confirm instructions whenever a prescription changes.
Does delayed clearance mean methotrexate must be stopped forever?
Delayed clearance does not automatically rule out future methotrexate treatment, but another high-dose cycle requires reassessment of renal recovery, the prior elimination pattern, interacting medicines, and the cancer benefit. A creatinine result checked 7 days later may be useful, yet recovery cannot be judged by elapsed time alone.

Kidney injury after high-dose methotrexate is often reversible with appropriate care, although recovery speed and completeness vary. Howard et al. describe that selected patients can receive subsequent high-dose treatment after renal recovery, including some previously treated with glucarpidase. That observation is not permission to restart; the team may change the dose, supportive measures, or treatment choice after reviewing the entire episode.
Hydration-related improvement in creatinine does not prove that every aspect of renal handling has returned to baseline. A patient whose creatinine changes from 1.4 to 1.0 mg/dL may still differ from a pre-treatment baseline of 0.7 mg/dL. Our hướng dẫn về mất nước và eGFR explains reversible influences, while chemotherapy planning also considers the previous timed drug concentrations.
Low albumin, pleural fluid, or ascites can complicate methotrexate pharmacokinetics; fluid collections may act as compartments from which drug returns slowly to the circulation. An albumin of 2.8 g/dL is therefore relevant context, not an independent rescue-dose formula. Our hướng dẫn diễn giải protein huyết thanh explains albumin's broader meaning, including why low values can reflect several different underlying processes.
How should patients use AI explanations and the evidence?
AI explanations of methotrexate levels should support questions about the report, not determine rescue doses, glucarpidase eligibility, or discharge. Bring at least the infusion start and stop times, actual sample times, current and baseline creatinine, and rescue record; a lone 48-hour concentration leaves essential clinical context missing.

Kantesti là một Công cụ phân tích xét nghiệm máu dựa trên AI that supports educational questions about laboratory trends, not time-critical chemotherapy decisions. Our hướng dẫn công nghệ AI explains the platform's role. A 5 µmol/L result should first prompt verification of the infusion clock and the oncology plan, not an automated instruction to change leucovorin.
Share only the information needed for the explanation and follow the hospital's rules for treatment records. Infusion timestamps and laboratory units are clinically useful, while unrelated identifying details may not be necessary; our thông tin về quyền riêng tư và dữ liệu explains our approach. If 2 reports disagree, preserve their original assay comments and ask the treating team which result governs the current plan.
The directly relevant evidence below includes Howard et al.'s 2016 toxicity review, Ramsey et al.'s 2018 glucarpidase consensus, and the 2024 European consensus on delayed elimination. The 2 separate Zenodo publications listed below concern complement testing and Nipah diagnosis; they are educational publications, not evidence for methotrexate rescue thresholds. Our Hướng dẫn an toàn giải thích AI của chúng tôi helps readers distinguish topic-specific clinical references from broader platform material.
Câu hỏi thường gặp
Nồng độ methotrexate an toàn trước khi xuất viện là bao nhiêu?
Không có nồng độ methotrexate phổ quát nào bảo đảm xuất viện an toàn cho mọi phác đồ hóa trị ung thư liều cao. Nhiều phác đồ sử dụng các ngưỡng theo dõi hoặc giải cứu vào khoảng 0,05–0,1 µmol/L, nhưng những ví dụ này không thể thay thế cho các quy định xuất viện. Bác sĩ cũng đánh giá khả năng hồi phục của thận, cân bằng dịch, lượng ăn uống qua đường miệng, nhu cầu giải cứu và khả năng tiếp cận các xét nghiệm theo dõi. Hãy hỏi xem phác đồ tại cơ sở nào được áp dụng và liệu sau khi xuất viện có còn cần dùng leucovorin hoặc làm thêm xét nghiệm hay không.
Tại sao nồng độ methotrexate của tôi vẫn cao sau 48 giờ?
Nồng độ methotrexate cao sau 48 giờ có thể phản ánh sự đào thải qua thận bị chậm, tổn thương thận, thuốc tương tác, các ổ dịch hoặc phác đồ có nồng độ dự kiến cao hơn trong giai đoạn sớm. Việc diễn giải cần biết mốc 48 giờ được tính từ lúc bắt đầu hay kết thúc truyền. Mức creatinine tăng 0,3 mg/dL trong vòng 48 giờ đáp ứng một tiêu chí chuẩn về tổn thương thận cấp và cần được lưu ý ngay cả khi giá trị cuối cùng không bị phòng xét nghiệm đánh dấu bất thường. Nhóm ung bướu có thể tăng cường điều trị giải cứu, điều chỉnh chăm sóc hỗ trợ, xác minh mẫu bệnh phẩm hoặc đánh giá khả năng sử dụng glucarpidase.
Leucovorin có làm giảm nồng độ methotrexate không?
Leucovorin bảo vệ các tế bào bình thường bằng cách cung cấp folate dạng khử, nhưng không trực tiếp loại bỏ methotrexate khỏi huyết tương. Liều giải cứu thường được dùng mỗi 6 giờ; liều lượng và đường dùng thực tế được xác định theo phác đồ điều trị ung thư và các nồng độ đo theo thời gian. Bù dịch và kiềm hóa hỗ trợ thải trừ qua thận, trong khi glucarpidase có thể phân hủy methotrexate lưu hành bằng enzym khi có chỉ định. Do đó, nồng độ methotrexate vẫn có thể tăng cao ngay cả khi đang dùng leucovorin giải cứu phù hợp.
Glucarpidase được sử dụng khi nào để xử trí tình trạng thải trừ methotrexate chậm?
Glucarpidase được cân nhắc trong trường hợp thải trừ methotrexate chậm nghiêm trọng kèm tổn thương thận khi nồng độ vượt quá các ngưỡng cụ thể theo phác đồ. Với một số phác đồ truyền trong 24 giờ, hướng dẫn đồng thuận năm 2018 quy định các nồng độ trên 30 µmol/L ở thời điểm 36 giờ, 10 µmol/L ở thời điểm 42 giờ hoặc 5 µmol/L ở thời điểm 48 giờ, đồng thời có mức tăng creatinine đáng kể. Các bác sĩ chuyên khoa phải xác minh rằng những tiêu chí này áp dụng cho liều dùng và thời gian truyền thực tế. Hướng dẫn nhấn mạnh việc đánh giá sớm để, nếu có chỉ định, điều trị có thể được thực hiện trong khoảng 48–60 giờ kể từ khi bắt đầu truyền.
Tôi có cần xét nghiệm nồng độ methotrexate nếu dùng thuốc mỗi tuần một lần không?
Nồng độ methotrexate trong huyết tương thường không được dùng để theo dõi phác đồ điều trị liều thấp hằng tuần tiêu chuẩn cho các tình trạng viêm. Việc theo dõi an toàn thường bao gồm xét nghiệm công thức máu, men gan và creatinine hoặc eGFR, thường là mỗi 8–12 tuần khi tình trạng đã ổn định theo quy trình tại địa phương. Uống liều hằng tuần mỗi ngày là một sai sót về liều dùng cần xử trí khẩn cấp, và nồng độ đo được thấp không thể loại trừ một cách đáng tin cậy độc tính nghiêm trọng sau khi phơi nhiễm lặp lại. Hãy liên hệ ngay với cơ sở y tế hoặc dịch vụ chống độc nếu đã uống thêm liều.
Can methotrexate levels be misleading after glucarpidase?
Methotrexate immunoassays can report falsely elevated concentrations for approximately 48 hours after glucarpidase because they cross-react with the breakdown product DAMPA. Chromatographic methods can distinguish methotrexate from that metabolite more accurately, although availability varies between hospitals. Leucovorin remains necessary because glucarpidase does not remove intracellular methotrexate. The oncology team interprets post-treatment results using the assay method, renal trend, timing, and specialist rescue guidance.
Tìm hiểu cách đọc kết quả xét nghiệm máu của bạn
Tải lên báo cáo xét nghiệm của bạn và AI của Kantesti sẽ giải thích từng dấu ấn sinh học bằng ngôn ngữ dễ hiểu chỉ trong vài giây. Được hơn 2 triệu người trên toàn thế giới sử dụng.
Tài liệu tham khảo
- Klein, T., Mitchell, S., & Weber, H. (2026). Hướng dẫn về xét nghiệm máu C3 C4 bổ thể và hiệu giá ANA. Nghiên cứu y khoa của Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Xét nghiệm máu vi-rút Nipah: Hướng dẫn phát hiện sớm và chẩn đoán năm 2026. Nghiên cứu y khoa của Kantesti AI. DOI
- Howard SC et al. (2016). Preventing and Managing Toxicities of High-Dose Methotrexate. The Oncologist. DOI PubMed
- Ramsey LB et al. (2018). Consensus Guideline for Use of Glucarpidase in Patients with High-Dose Methotrexate Induced Acute Kidney Injury and Delayed Methotrexate Clearance. The Oncologist. DOI PubMed
- Bielack SS et al. (2024). A European consensus recommendation on the management of delayed methotrexate elimination: supportive measures, leucovorin rescue and glucarpidase treatment. Journal of Cancer Research and Clinical Oncology.
- 2 triệu+Các xét nghiệm được phân tích
- 127+Các quốc gia
- 100+Ngôn ngữ
Về đội ngũ y tế


Tín hiệu tin cậy E-E-A-T
Kinh nghiệm
Đánh giá lâm sàng do bác sĩ phụ trách đối với quy trình diễn giải kết quả xét nghiệm.
Chuyên môn
Tập trung vào y học xét nghiệm: cách các chỉ dấu sinh học (biomarker) hoạt động trong bối cảnh lâm sàng.
Tính uy quyền
Được Tiến sĩ Thomas Klein đánh giá về mặt y khoa, với sự đóng góp của Tiến sĩ Sarah Mitchell và Giáo sư, Tiến sĩ Hans Weber.
Độ tin cậy
Diễn giải dựa trên bằng chứng, kèm các lộ trình theo dõi rõ ràng để giảm mức độ báo động.





Tuyên bố miễn trừ trách nhiệm y tế
Bài viết này chỉ nhằm mục đích giáo dục và không cấu thành lời khuyên y tế. Luôn tham khảo ý kiến của nhà cung cấp dịch vụ chăm sóc sức khỏe đủ năng lực để đưa ra quyết định chẩn đoán và điều trị.
Đã xuất bản · Liên hệ với ban biên tập
Xuất bản bởi Kantesti Ltd, đăng ký tại Anh và xứ Wales, số công ty. 17090423, London, Vương quốc Anh.
