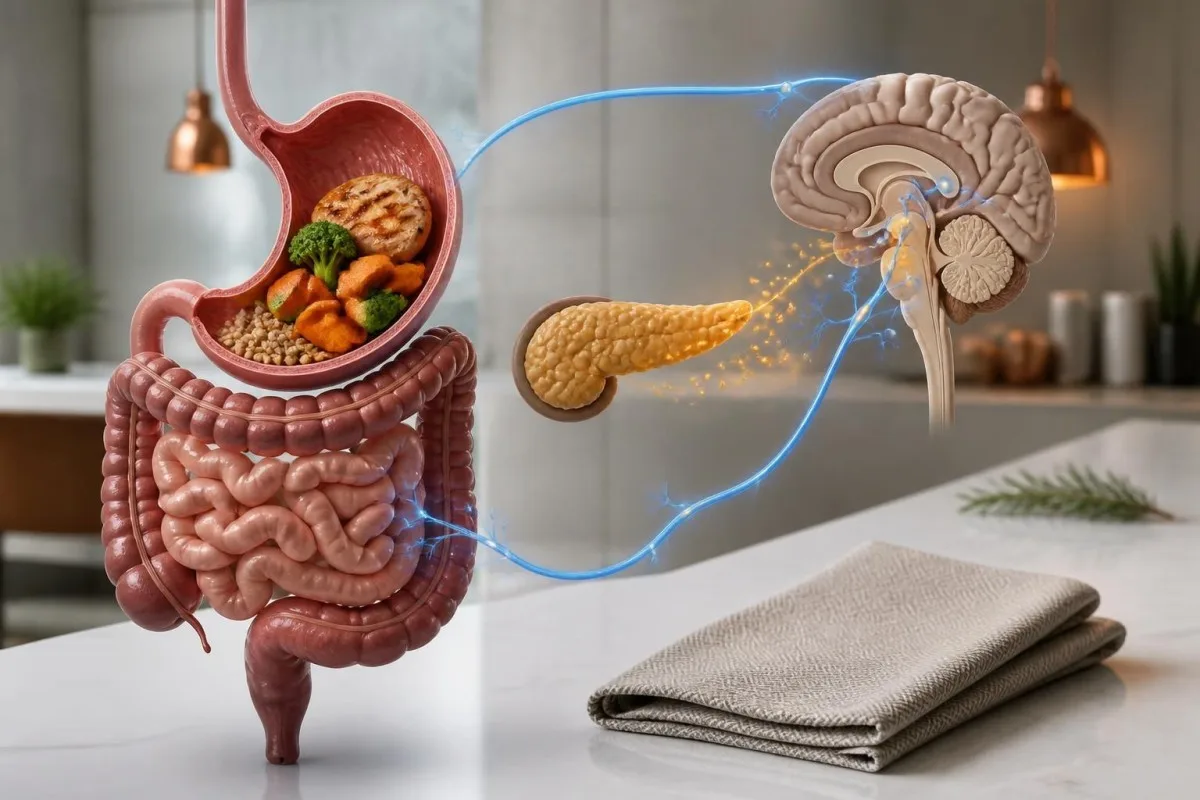
আহাৰ-পৰৱৰ্তী অৱনতি প্ৰায়ে স্বাভাৱিক, কিন্তু বাৰে বাৰে বা তীব্ৰ টোপনি-টোপনি ভাবে টোপনিৰ অভাৱ, ঔষধৰ প্ৰভাৱ, ৰক্ত-গ্লুকোজৰ পৰিৱৰ্তন বা আন কোনো চিকিৎসাযোগ্য সমস্যা প্ৰকাশ কৰিব পাৰে।

মূল কথাসমূহ
- সাধাৰণ ধৰণ: খোৱাৰ পিছত টোপনি লগা সাধাৰণতে মগজুৰ পৰা তেজ আঁতৰাই নিয়াৰ ফল নহয়; ইয়াৰ পৰিৱৰ্তে ই প্ৰায়ে প্ৰাকৃতিক দুপৰীয়াৰ আৰম্ভণিৰ ছাৰ্কাডিয়ান অৱনতিৰ সৈতে মিলি যোৱা বৃহৎ, দ্ৰুতভাৱে হজম হোৱা আহাৰৰ ফল।
- Sleep debt: Adults generally need at least 7 hours of sleep; repeated nights below that amount can make an ordinary meal feel disproportionately sedating.
- Glucose clue: A laboratory fasting glucose of 100-125 mg/dL (5.6-6.9 mmol/L) falls in the prediabetes range, while 126 mg/dL (7.0 mmol/L) or higher requires confirmation unless clear symptoms are present.
- Possible low glucose: কাৰ্বহাইড্ৰেট-সমৃদ্ধ আহাৰৰ 2-4 ঘণ্টা পিছত হোৱা লক্ষণে আহাৰৰ পিছত গ্লুকোজ 70 mg/dL (3.9 mmol/L)-ৰ তললৈ নামি যোৱাটো সূচাব পাৰে, যদিও মিটাৰ বা নিৰন্তৰ মনিটৰ সঠিক নহ'ব পাৰে।
- ঔষধৰ প্ৰভাৱ: Sedating antihistamines, opioids, sleep medicines, some anti-anxiety drugs and gabapentinoids can intensify post-meal drowsiness; do not stop them without prescriber advice.
- কেতিয়া ব্যৱস্থা ল'ব: পিয়াহ, সঘনাই প্ৰস্ৰাৱ হোৱা, দৃষ্টিশক্তি অস্পষ্ট হোৱা, অজ্ঞান হোৱা, বিভ্ৰান্তি, অনিচ্ছাকৃত ওজন হ্ৰাস বা তীব্ৰ দুৰ্বলতাৰ সৈতে পুনৰাবৃত্তিমূলক টোপনি-টোপনি ভাবৰ চিকিৎসা মূল্যায়ন প্ৰয়োজন।
- Useful first tests: ইতিহাসৰ ওপৰত নিৰ্ভৰ কৰি, চিকিৎসকসকলে fasting glucose, HbA1c, সম্পূৰ্ণ তেজ গণনা, ফেৰিটিন, thyroid-stimulating hormone আৰু ঔষধৰ পৰ্যালোচনা বিবেচনা কৰিব পাৰে।
- সুৰক্ষা: অস্বাভাৱিকভাৱে টোপনি লগা অৱস্থাত গাড়ী নচলাব, যন্ত্ৰপাতি চলাব নালাগে বা বগাব নালাগে, বিশেষকৈ যদি এই পৰ্বটো গ্লুকোজ কমোৱা ঔষধৰ পিছত হয়।
What feeling sleepy after eating usually means
খোৱাৰ পিছত তন্দ্ৰা সাধাৰণতে আহাৰৰ পৰিমাণ, দ্ৰুতভাৱে শোষিত হোৱা কাৰ্ব’হাইড্ৰেট, দুপৰীয়াৰ আৰম্ভণিৰ স্বাভাৱিক চাৰ্কেডিয়ান অৱনতি, অথবা অপৰ্যাপ্ত টোপনিৰ বাবে হয়; বিপজ্জনক পাচনজনিত সমস্যাৰ বাবে নহয়। অধিক পৰিমাণৰ দুপৰীয়াৰ আহাৰৰ পিছত হোৱা এটা মৃদু পৰ্যায় সাধাৰণতে নিৰীহ; বাৰে বাৰে, হঠাৎ হোৱা বা দৈনন্দিন কামত বাধা দিয়া পৰ্যায়সমূহ অধিক ভালদৰে পৰীক্ষা কৰা উচিত। আমাৰ ৰক্ত-পৰীক্ষাৰ বায়োমাৰ্কাৰসমূহৰ গাইড একক ফলাফলে কিয় লক্ষণ-সম্পৰ্কীয় প্ৰশ্নৰ উত্তৰ খুব কমেই দিয়ে সেয়া ব্যাখ্যা কৰে।

The strongest everyday pattern is a combination of meal load and timing: a 1,000-calorie lunch rich in refined starch can produce more drowsiness than a 500-calorie meal containing vegetables, protein and fibre. The effect often peaks 30-120 minutes later, when digestion, insulin release and the body’s daytime alertness rhythm overlap.
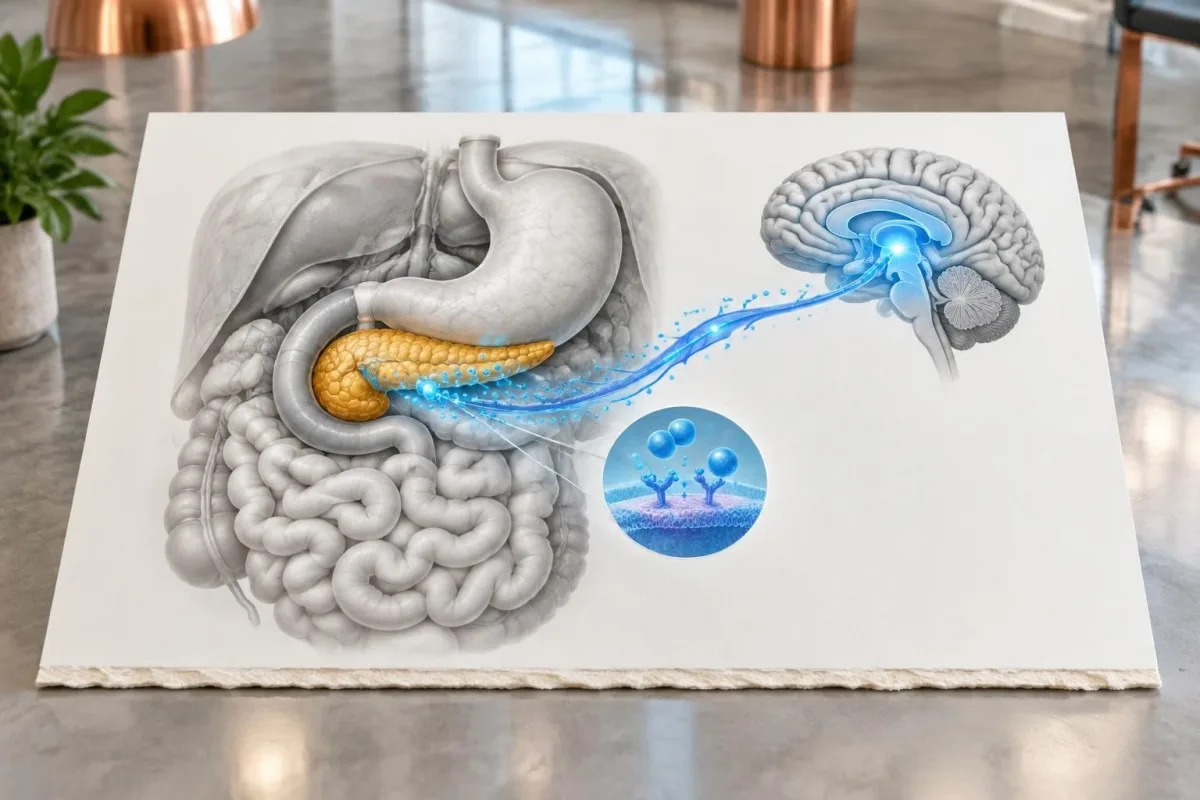
Post-meal sleepiness does not usually mean that digestion steals so much blood from the brain that the brain becomes under-supplied. Blood flow is tightly regulated; the more useful explanation is interacting signals from the gut, pancreas, brain and circadian clock, with individual responses varying substantially.
এটা ব্যৱহাৰিক পাৰ্থক্য হৈছে স্থায়িত্ব। মাজে-সময়ে হোৱা অধিক পৰিমাণৰ আহাৰ খোৱাৰ ৩০-৯০ মিনিটৰ ভিতৰত কমি যোৱা টোপনি-টোপনি ভাব সাধাৰণতে কেইবা ঘণ্টা ধৰি চলা পুনৰাবৃত্তিমূলক পৰ্যায়, হঠাৎ টোপনি অহা, বিভ্ৰান্তি বা নিম্ন ৰক্ত-গ্লুকোজৰ লক্ষণৰ পৰা পৃথক; পিছৰ ধৰণসমূহত সুসংগঠিত ৰোগ-ইতিহাস আৰু সম্ভৱতঃ পৰীক্ষাৰ প্ৰয়োজন হয়।
How digestion can promote post-meal sleepiness
অন্ত্ৰ-মগজুৰ সংকেত প্ৰেৰণ, ইনচুলিন-সম্পৰ্কীয় পৰিৱৰ্তন আৰু আহাৰ-উদ্ভূত শিথিলতাৰ জৰিয়তে পাচনক্ৰিয়াই টোপনি-টোপনি ভাব বৃদ্ধি কৰিব পাৰে, কিন্তু কোনো এটা একক প্ৰক্ৰিয়াই প্ৰতিটো খাদ্যজনিত তন্দ্ৰা সম্পূৰ্ণৰূপে ব্যাখ্যা নকৰে। Hormones such as cholecystokinin rise after meals, while the brain’s arousal systems respond to nutrient availability and the social setting of eating.
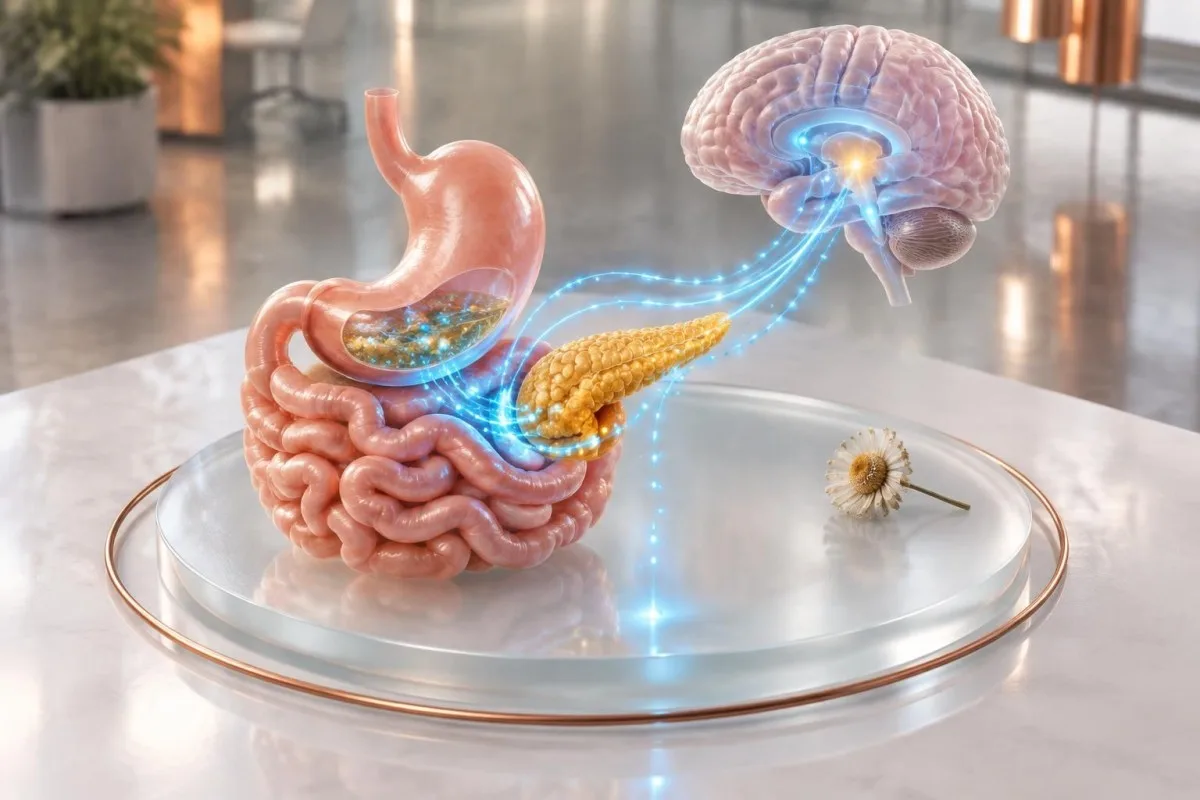
Fat and protein can stimulate ক'লেচিষ্ট'কাইনিন, তৃপ্তি আৰু পৰীক্ষামূলক পৰিৱেশত সজাগতা হ্ৰাসৰ সৈতে জড়িত এটা অন্ত্ৰৰ হৰমোন। তাৰ অৰ্থ এইটো নহয় যে চৰ্বিয়ে স্বয়ংক্ৰিয়ভাৱে অস্বাভাৱিক টোপনি-টোপনি ভাব সৃষ্টি কৰে: এটা আহাৰৰ মুঠ শক্তি, আঁহ, এলকহলৰ পৰিমাণ, জলীয়তা আৰু ব্যক্তিজনৰ আগৰ টোপনিয়ে কোনো এটা পুষ্টি-উপাদানতকৈ অধিক গুৰুত্বপূৰ্ণ ভূমিকা ল'ব পাৰে।
Carbohydrate intake increases insulin secretion, which changes the movement of several amino acids into tissues and may alter the relative availability of tryptophan for brain serotonin and melatonin production. The evidence is honestly mixed, and normal post-meal insulin action should not be confused with insulin resistance.
The phrase “food coma” describes a sensation, not a diagnosis. If a 700-kilocalorie meal causes mild drowsiness for 45 minutes, that is generally less concerning than a repeated 3-hour crash accompanied by tremor, sweating or palpitations.
ৰক্ত কেৱল মগজুৰ পৰা আঁতৰাই দিয়া নহয় কিয়
Human circulation can increase blood delivery to the digestive organs after eating while preserving brain perfusion. A severe light-headed feeling after meals is more suggestive of blood-pressure regulation, dehydration or a glucose problem than of ordinary digestion alone; a blood-pressure review may be useful when symptoms include standing dizziness.
কোনবোৰ আহাৰৰ ধৰণে টোপনি অহাৰ সম্ভাৱনা বঢ়ায়
দ্ৰুতভাৱে শোষিত কাৰ্বহাইড্ৰেট, ছেচুৰেটেড ফেট বা এলকহল অধিক থকা বৃহৎ আহাৰেই আহাৰৰ পিছৰ টোপনিৰ সৈতে জড়িত আটাইতকৈ সাধাৰণ কাৰক। Portion size and carbohydrate quality usually matter more than whether a food is labelled “healthy” or “unhealthy.”
100 grams দ্ৰুতভাৱে শোষিত হোৱা কাৰ্ব’হাইড্ৰেট থকা আহাৰে 40 grams কাৰ্ব’হাইড্ৰেটৰ সৈতে বীন, শাক-পাচলি আৰু প্ৰ’টিন থকা আহাৰতকৈ গ্লুক’জ আৰু ইনচুলিন অধিক তীব্ৰভাৱে বৃদ্ধি কৰিব পাৰে। আঁহে পাকস্থলী খালী হোৱা আৰু গ্লুক’জ শোষণৰ গতি লেহেম কৰে; ই অতিৰিক্ত ডাঙৰ আহাৰৰ শক্তিৰ পৰিমাণ বাতিল নকৰে, কিন্তু ই গ্লুক’জ বৃদ্ধিৰ গতি হ্ৰাস কৰিব পাৰে।
Fat can delay stomach emptying, which sometimes produces a later, longer period of heaviness rather than an immediate crash. Alcohol is different: even one standard drink can worsen alertness and fragment sleep later that night, making the next day’s meal-related drowsiness easier to misinterpret.
এটা স্পষ্ট কাল্পনিক উদাহৰণে সহায় কৰে: ৩৫ বছৰীয়া এজন কাৰ্যালয় কৰ্মীয়ে ৬ ঘণ্টা শুই, ব্ৰেকফাষ্ট বাদ দি, দুপৰীয়া ১ বজাত বগা পাউৰুটিৰ সৈতে এটা ডাঙৰ মিঠা পানীয় গ্ৰহণ কৰে। ৯০ মিনিটীয়া অৱসাদে দৈহিক ছন্দৰ সময় আৰু টোপনিৰ ঋণৰ লগতে আহাৰৰ গঠন প্ৰতিফলিত কৰিব পাৰে; ই অকলে ডায়েবেটিছ প্ৰমাণ নকৰে।
For practical comparisons, record the meal’s approximate portion, carbohydrate source and symptom timing for 7 days rather than banning individual foods after one episode. A উপবাসৰ নিৰ্দেশনাৰ গাইড পিছত যেতিয়া ৰক্ত পৰীক্ষাৰ ব্যৱস্থা কৰা হয়, তেতিয়া বিভ্ৰান্তি ৰোধ কৰাতো সহায় কৰিব পাৰে।
Why the afternoon circadian dip can feel like a food coma
The body’s circadian alertness rhythm commonly dips in the early afternoon, often between about 1 and 3 p.m., even when a person has not just eaten. A midday meal can amplify that predictable reduction in wakefulness.

Alertness is not a flat line across the day. The central circadian clock coordinates sleep pressure, body temperature, melatonin timing and cortisol rhythms; in many adults, wakefulness decreases after midday while the biological night remains the strongest sleep window.
Meal timing can interact with this clock. The American Heart Association’s scientific statement on meal timing describes links between irregular eating, circadian biology and cardiometabolic health, although it does not establish one universal “safe” meal schedule (St-Onge et al., 2017).
A useful experiment is to compare equivalent meals at 11 a.m. and 2 p.m. on separate days, while keeping sleep and caffeine similar. If sleepiness appears at both times, meal composition may dominate; if it appears mainly at 2 p.m., circadian timing is a stronger clue.
People who work rotating shifts or cross time zones may experience the dip at an unusual clock time because their internal rhythm and local schedule disagree. A ৰক্ত-পরীক্ষা সময়সূচী গাইড পালি কৰি কৰা কামে লেবৰেটৰীৰ নমুনা সংগ্ৰহৰ সময়তো প্ৰভাৱ পেলালে উপযোগী।
How sleep debt magnifies sleepy-after-meals symptoms
Sleep debt makes ordinary post-meal drowsiness stronger because sleep pressure has already accumulated before the meal begins. নিয়মিতভাৱে 7 ঘণ্টাতকৈ কম শোৱা প্ৰাপ্তবয়স্কসকলে একঘেয়ে কাম, উমাল কোঠা বা দুপৰীয়াৰ আৰম্ভণিৰ সময়ত এই সমস্যাটো বেছিকৈ লক্ষ্য কৰিব পাৰে।

The American Academy of Sleep Medicine and Sleep Research Society recommend that adults obtain at least 7 hours of sleep regularly for health. Five nights of 6-hour sleep create a 5-hour weekly shortfall compared with that minimum, even if the person feels they have adapted.
In a controlled study, Van Dongen et al. found that chronic restriction to 6 hours or 4 hours per night produced cumulative neurobehavioral impairment, while participants became less accurate at judging their own impairment (Sleep, 2003). That finding matters because “I am used to it” is not a reliable safety test.
A hypothetical 52-year-old marathon runner may feel sleepy after a normal lunch because training, early waking and 6 hours of sleep have increased sleep pressure; the same meal may not cause symptoms after several nights of 8 hours. The pattern points first toward recovery and sleep assessment, not automatically toward a food intolerance.
14 দিন ধৰি শোৱাৰ সময়, সাৰ পোৱাৰ সময়, টোপনি ভঙা, নাক কঁকৰোৱা, মদ্যপান আৰু কেফেইন লিপিবদ্ধ কৰক। জোৰেৰে নাক কঁকৰোৱা, আন লোকে লক্ষ্য কৰা শ্বাস-প্ৰশ্বাস বন্ধ হোৱা বা পুৱাৰ মূৰৰ বিষ থাকিলে কেৱল কাৰ্ব’হাইড্ৰেট কমোৱাতকৈ sleep-apnoea মূল্যায়ন অধিক প্ৰাসংগিক হয়।
How portion size, speed and activity change the crash
সোনকালে খোৱা, অতি ডাঙৰ পৰিমাণৰ খাদ্য গ্ৰহণ কৰা বা দুপৰীয়াৰ আহাৰৰ পিছত স্থিৰ হৈ থকা কথাই খোৱাৰ পিছৰ টোপনি বৃদ্ধি কৰিব পাৰে। A smaller meal eaten slowly, followed by gentle movement, often produces a different response without requiring extreme dietary restriction.

Large meals stretch the stomach and may increase satiety signals, while rapid eating compresses more energy into a shorter period. A 20-minute meal containing 800 calories can therefore feel different from the same food eaten over 45 minutes with water and pauses.
খোৱাৰ পিছত 10-15 মিনিট সহজ খোজ কঢ়াটোৱে পেশীৰ গ্লুকোজ গ্ৰহণ বৃদ্ধি কৰি কিছুমান লোকৰ আহাৰৰ পিছত গ্লুকোজ বৃদ্ধিৰ উচ্চতা কমাব পাৰে। ই ডায়েবেটিছৰ চিকিৎসা নহয়, আৰু ভাৰসাম্যৰ সমস্যা, বুকুৰ উপসৰ্গ বা ব্যায়ামৰ নিষেধাজ্ঞা থকা লোকসকলে তেওঁলোকৰ চিকিৎসকৰ পৰামৰ্শ অনুসৰণ কৰিব লাগে।
প্ৰাসংগিক তুলনাটো সাৰ্বজনীন নহয়, ব্যক্তিগত: ৩৫ গ্ৰাম আঁহযুক্ত কাৰ্বহাইড্ৰেট থকা ৬০০-কেলৰিৰ দুপৰীয়াৰ আহাৰ ৩৫০-কেলৰিৰ পেষ্ট্ৰি আৰু মিঠা পানীয়ৰ সংমিশ্ৰণতকৈ ভালদৰে সহ্য হ’ব পাৰে। ওজন হ্ৰাসৰ লক্ষ্য, ঔষধ গ্ৰহণৰ সময় আৰু গ্লুক’জ কমোৱা চিকিৎসাই আটাইতকৈ নিৰাপদ পৰিকল্পনা সলনি কৰিব পাৰে।
Try changing one variable at a time for 5-7 days: portion size, meal speed, refined carbohydrate, or a short walk. The AI nutrition and lab context guide explains why dietary suggestions should be interpreted alongside biomarkers rather than as a diagnosis.
আহাৰ খোৱাৰ পিছত টোপনি লগা পৰ্ব অধিক বেয়া কৰিব পৰা কোনবোৰ ঔষধ
Sedating medicines and alcohol can make a normal post-meal dip feel excessive, and meal timing can make their peak effects more noticeable. সাধাৰণতে অৰিহণা যোগোৱা কাৰকসমূহৰ ভিতৰত প্ৰথম প্ৰজন্মৰ এণ্টিহিষ্টামিন, অপিঅইড, নিদ্ৰাৰ ঔষধ, বেঞ্জ’ডায়াজেপিন, কিছুমান এণ্টিচাইক’টিক, গাবাপেণ্টিনয়েড আৰু টোপনি অনা এণ্টিডিপ্ৰেছেণ্ট অন্তৰ্ভুক্ত।
Diphenhydramine আৰু প্ৰথম-প্ৰজন্মৰ অন্যান্য এণ্টিহিষ্টামিনে সজাগতা হ্ৰাস কৰিব পাৰে; অপিঅইড আৰু বেঞ্জ’ডায়াজেপিনেও শ্বাস-প্ৰশ্বাসৰ উদ্দীপনা আৰু প্ৰতিক্ৰিয়াৰ গতি হ্ৰাস কৰিব পাৰে। পুৱা 8 বজাত গ্ৰহণ কৰা ঔষধে ইয়াৰ অৰ্ধ-জীৱন, মাত্ৰা, বৃক্কৰ কাৰ্যক্ষমতা আৰু পাৰস্পৰিক ক্ৰিয়াৰ ওপৰত নিৰ্ভৰ কৰি দুপৰীয়াৰ এটা পৰ্বৰ ক্ষেত্ৰতো এতিয়াও অৱদান আগবঢ়াব পাৰে।
Some medicines influence glucose rather than sedation directly. Insulin and sulfonylureas can cause hypoglycaemia, especially after eating less than planned, exercising more than usual or drinking alcohol; symptoms may include sweating, shaking, hunger, palpitations and confusion rather than simple sleepiness.
Never stop a prescribed medicine abruptly because of drowsiness. Ask a pharmacist or prescriber whether timing, dose, an alternative or kidney-function review is appropriate, and avoid driving if the reaction is unpredictable.
Bring a complete list of prescriptions, over-the-counter products, supplements and recreational substances to the review. A ঔষধ-সুৰক্ষা ধাৰা-কাৰ্যপ্ৰণালী পৰীক্ষাগাৰৰ প্ৰৱণতাসমূহ সংগঠিত কৰাত সহায় কৰিব পাৰে, কিন্তু ই ঔষধ প্ৰদানৰ সিদ্ধান্তৰ বিকল্প হ’ব নোৱাৰে।
When glucose regulation may explain post-meal fatigue
Glucose regulation becomes more concerning when sleepiness is persistent, disproportionate or accompanied by thirst, frequent urination, blurred vision, recurrent infections or unexplained weight change. High glucose can cause fatigue through dehydration and altered cellular fuel use, while low glucose can cause neuroglycopenic drowsiness.

American Diabetes Association-এ HbA1c 6.5% বা তাতকৈ অধিক, উপবাসৰ প্লাজমা গ্লুক’জ 126 mg/dL (7.0 mmol/L) বা তাতকৈ অধিক, অথবা 2-ঘণ্টীয়া মৌখিক গ্লুক’জ সহনশীলতা পৰীক্ষাৰ ফল 200 mg/dL (11.1 mmol/L) বা তাতকৈ অধিক হোৱাৰ দৰে পৰীক্ষাগাৰৰ মাপকাঠিৰে ডায়েবেটিছ নিৰ্ধাৰণ কৰে; সাধাৰণতে লক্ষণ নাথাকিলে ফল নিশ্চিত কৰা হয় (American Diabetes Association Professional Practice Committee, 2024)।
Kantesti is an AI blood test interpretation platform that places glucose, HbA1c, triglycerides, liver markers and kidney markers into a connected context rather than treating a single post-meal sensation as proof of diabetes. Our platform can explain reported values, but diagnosis still depends on validated testing and clinical assessment.
A home glucose value after an ordinary meal is not equivalent to a diagnostic oral glucose tolerance test. Capillary meters can differ from laboratory plasma glucose, and continuous glucose monitors measure interstitial fluid with a delay; a surprising result should be repeated or confirmed rather than overinterpreted.
If thirst and urination occur with repeated drowsiness, arrange medical review rather than merely switching foods. The উচ্চ ৰক্তশৰ্কৰাৰ লক্ষণ-নিৰ্দেশিকা describes warning patterns that should not be dismissed as a routine food coma.
| স্তৰ | পৰিসৰ | ইয়াৰ অৰ্থ |
|---|---|---|
| স্বাভাৱিক উপবাস গ্লুক’জ | <100 mg/dL (<5.6 mmol/L) | Usually within the normal diagnostic range; one result does not explain every symptom. |
| প্ৰিডায়েবেটিছ ৰেঞ্জ | ১০০-১২৫ মিলিগ্রাম/ডেসিলিটাৰ (৫.৬-৬.৯ মিলিমোল/লিটাৰ) | ই ডায়েবেটিছৰ বৰ্ধিত আশংকাৰ ইংগিত দিয়ে আৰু সাধাৰণতে পুনৰ পৰীক্ষা বা HbA1c মূল্যায়নৰ প্ৰয়োজন হয়। |
| ডায়েবেটিছ-ৰেঞ্জৰ ফলাফল | ১২৬-১৯৯ মিলিগ্রাম/ডেসিলিটাৰ (৭.০-১১.০ মিলিমোল/লিটাৰ) | নিশ্চিতকৰণ বা লক্ষণ-ভিত্তিক ক্লিনিকেল ব্যাখ্যাৰ প্ৰয়োজন; কেৱল সাধাৰণ আহাৰ-পৰৱৰ্তী টোপনিৰ দ্বাৰা ইয়াক ব্যাখ্যা কৰিব নোৱাৰি। |
| স্পষ্ট hyperglycaemia | ≥200 mg/dL (≥11.1 mmol/L) with symptoms | তৎক্ষণাত চিকিৎসাগত মূল্যায়নৰ প্ৰয়োজন, বিশেষকৈ বমি, পানীশূন্যতা, গভীৰ উশাহ লোৱা বা বিভ্ৰান্তিৰ সৈতে। |
Could a glucose drop cause sleepiness 2 to 4 hours later
খোৱাৰ 2-4 ঘণ্টাৰ পিছত গ্লুক’জ কমি গ’লে টোপনি, দুৰ্বলতা, ঘাম, কঁপনি, ভোক বা বিভ্ৰান্তিৰ সৃষ্টি হ’ব পাৰে, বিশেষকৈ অধিক কাৰ্ব’হাইড্ৰেটযুক্ত আহাৰ খোৱাৰ পিছত বা গ্লুক’জ কমোৱা ঔষধ গ্ৰহণ কৰিলে। প্ৰকৃত আহাৰ-পৰৱৰ্তী হাইপোগ্লাইচেমিয়া কেৱল ভাগৰ অনুভৱৰ ওপৰত অনুমান নকৰি, লক্ষণ দেখা দিয়াৰ সময়ত প্ৰদৰ্শন কৰিব লাগে।
Clinicians commonly use a glucose below 70 mg/dL (3.9 mmol/L) as an alert level, while below 54 mg/dL (3.0 mmol/L) indicates clinically significant hypoglycaemia requiring urgent attention. The number matters most when symptoms occur at the same time and improve after glucose is corrected.
The diagnostic logic is often called Whipple’s triad: compatible symptoms, a documented low glucose during those symptoms, and improvement when glucose rises. A person who feels sleepy at 2 p.m. but has a glucose of 98 mg/dL (5.4 mmol/L) has not demonstrated hypoglycaemia.
মিঠা পানীয় খোৱাৰ পিছত লক্ষণ হোৱা 28 বছৰীয়া ব্যক্তিৰ ক্ষেত্ৰত গ্লুক’জ দ্ৰুতগতিত বৃদ্ধি আৰু হ্ৰাস পাব পাৰে, কিন্তু ঘৰুৱা মিটাৰত 62 mg/dL (3.4 mmol/L) দেখা গ’লে সম্ভৱ হ’লে সেয়া নিশ্চিত কৰা উচিত, কাৰণ ঘৰুৱা যন্ত্ৰৰ ফলাফলত বিশ্লেষণজনিত ভুল থাকিব পাৰে। উপবাস, সুৰাপান, ব্যায়াম আৰু ঔষধে বেলেগ ধৰণৰ পৰিৱৰ্তন ঘটাব পাৰে।
নিৰ্ধাৰিত ইনচুলিন বা ছালফ'নাইলইউৰিয়া ব্যৱহাৰকাৰীসকলে ব্যক্তিগত rescue plan অনুসৰণ কৰি দ্ৰুত কাৰ্বহাইড্ৰেটৰ এটা উৎস লগত ৰাখিব লাগে। ডায়েবেটিছ নথকা লোকসকলে বাৰে বাৰে কম মান লিপিবদ্ধ কৰিলে পুনৰাবৃত্তি কৰি নিজে চিকিৎসা কৰাৰ সলনি চিকিৎসাগত মূল্যায়ন কৰাব লাগে; আমাৰ কম-গ্লুক’জৰ কাৰণসমূহৰ নিৰ্দেশিকাই for testing context.
আহাৰৰ পিছৰ তন্দ্ৰাৰ লক্ষণৰ দৰে দেখা দিব পৰা আন অৱস্থা
ৰক্তহীনতা, লোহাৰ অভাৱ, থাইৰইডৰ ৰোগ, স্লিপ এপনিয়া, বিষণ্ণতা, দীৰ্ঘস্থায়ী ৰোগ আৰু কিছুমান সংক্ৰমণে দিনৰ ভাগত হোৱা টোপনি-টোপনি ভাব সৃষ্টি কৰিব পাৰে, যি কেৱল আহাৰৰ পিছতহে স্পষ্ট হৈ পৰে। আহাৰটো অন্তৰ্নিহিত কাৰণ নহৈ ক্লান্তি লক্ষ্য কৰাৰ এক উদ্দীপক হ'ব পাৰে।

A complete blood count can identify anaemia, but ferritin interpretation requires context because inflammation can raise ferritin while iron stores are limited. There is no single ferritin threshold that explains sleepiness for everyone; a low ferritin with low transferrin saturation is more informative than an isolated borderline value.
Hypothyroidism may cause fatigue, cold intolerance, constipation, dry skin and slowed thinking, although symptoms are nonspecific. Many laboratories use a TSH upper reference limit near 4.0-4.5 mIU/L, but ranges differ by assay, age, pregnancy and local practice; some European laboratories use different limits.
আহাৰৰ গঠন যিয়েই নহওক, স্লীপ এপনিয়াই দিনৰ ভাগত তীব্ৰ টোপনিৰ সৃষ্টি কৰিব পাৰে। নাক বজোৱা, প্ৰত্যক্ষ কৰা বিৰতি, পুৱা হোৱা মূৰৰ বিষ বা প্ৰতিৰোধী উচ্চ ৰক্তচাপে টোপনিৰ মূল্যায়নৰ সূচনা কৰিব লাগে, বিশেষকৈ যেতিয়া কোনো ব্যক্তিৰ কথোপকথন বা গাড়ী চলোৱাৰ সময়ত অনিচ্ছাকৃতভাৱে টোপনি আহে।
Kantesti AI can organise a CBC, ferritin, thyroid markers and glucose into a readable pattern, but a normal panel does not exclude sleep disorders or depression. Relevant background reading includes কম ferritinৰ লক্ষণসমূহ আৰু subclinical thyroid results.
খোৱাৰ পিছৰ টোপনিৰ ক্ষেত্ৰত খাদ্য-প্ৰতিক্ৰিয়া কেতিয়া প্ৰাসংগিক
Food intolerance can cause bloating, abdominal pain or diarrhoea after eating, but isolated sleepiness is not a reliable sign of intolerance or allergy. যেতিয়া টোপনিৰ সৈতে চকা, ফুলা, শোঁ-শোঁ শব্দেৰে উশাহ লোৱা, ডিঙি টান লাগা, বাৰে বাৰে বমি বা মূৰ্ছা যোৱা থাকে, তেতিয়া প্ৰকৃত এলাৰ্জিক প্ৰতিক্ৰিয়াৰ সম্ভাৱনা অধিক।

Lactose or fructose malabsorption can produce gastrointestinal symptoms several hours after exposure, but neither condition should be diagnosed from tiredness alone. A lactose-intolerance testing guide explains why breath-test preparation and symptom timing matter.
Drowsiness with wheezing, facial or tongue swelling, blue lips, collapse or rapidly worsening symptoms is an emergency because severe allergic reactions can impair breathing and blood pressure. Do not perform a home food challenge after a suspected serious reaction.
খাদ্য-ডায়েৰীত কমেও 7 দিনৰ বাবে উপাদান, পৰিমাণ, সময়, লক্ষণ আৰু ব্যায়াম লিপিবদ্ধ কৰিব লাগে; বহুতো খাদ্য বাদ দিয়া এলিমিনেচন ডায়েটে পুষ্টিজনিত সমস্যা সৃষ্টি কৰিব পাৰে আৰু প্ৰকৃত উদ্দীপকটো অস্পষ্ট কৰি তুলিব পাৰে। ব্যৱহাৰিক প্ৰশ্নটো হ’ল, কোনো নিৰ্দিষ্ট সংস্পৰ্শৰ সৈতে লক্ষণসমূহ নিৰ্ভৰযোগ্যভাৱে পুনৰ দেখা দিয়ে নেকি।
Blood allergy panels are not universal screens for food intolerance, and a positive sensitisation test does not prove that a food causes sleepiness. Ask a clinician or allergy specialist to interpret results alongside the history.
খোৱাৰ পিছত টোপনি অহাৰ পৰ্বসমূহৰ বাবে উপযোগী ৭ দিনীয়া পৰীক্ষা
সাত দিনৰ লক্ষণৰ ডায়েৰীয়ে আহাৰৰ প্ৰভাৱক টোপনিৰ ঘাটি, চাৰ্কাডিয়ান সময়, ঔষধ আৰু গ্লুক’জৰ পৰিৱৰ্তনৰ পৰা পৃথক কৰাত সহায় কৰিব পাৰে। Record the time of eating, approximate portion, sleep duration, caffeine, medication timing, activity and symptom severity from 0 to 10.
Measure only what you can interpret safely. If you have diabetes, use the monitoring plan prescribed for you; if not, occasional glucose checks may provide clues but cannot diagnose reactive hypoglycaemia or diabetes on their own.
A useful pattern is reproducibility: symptoms beginning 45 minutes after a large sweet drink on four of five days suggest a meal-related trigger, while symptoms at 2 p.m. after different meals suggest circadian timing. Symptoms after poor sleep but not after 8-hour nights point toward sleep pressure.
Include posture and blood pressure if episodes involve light-headedness, blurred vision or near-fainting. A blood pressure drop after eating can be more relevant than food composition, particularly in older adults or people taking antihypertensive medicines.
At the appointment, bring the diary and packaging or names of supplements. আমাৰ ভিত্তিমূলক ৰক্ত-পৰীক্ষাৰ প্ৰস্তুতিৰ নিৰ্দেশিকা পৰিকল্পিত মূল্যায়নৰ ঠিক আগতে কেইবাটাও পৰিৱৰ্তন একেলগে নকৰিবলৈ পাঠকসকলক সহায় কৰে।
Which blood tests may help explain repeated drowsiness
The most useful tests depend on the symptom pattern, but clinicians commonly consider HbA1c, fasting glucose, a complete blood count, ferritin, thyroid-stimulating hormone and kidney or liver markers. No blood panel can diagnose every cause of sleepiness.
HbA1c-এ প্ৰায় 2-3 মাহৰ গড় গ্লাইচেমিয়া প্ৰতিফলিত কৰে আৰু সাধাৰণতে 5.7%-ৰ তলত স্বাভাৱিক, 5.7-6.4%-ত প্ৰিডায়েবেটিছ আৰু 6.5% বা তাতকৈ অধিকত ডায়েবেটিছ হিচাপে ব্যাখ্যা কৰা হয়। শেহতীয়া ৰক্ত সঞ্চালন, হিম’লাইছিছ, কিছুমান হিম’গ্ল’বিন ভেৰিয়েণ্ট, গৰ্ভাৱস্থা আৰু পৰিৱৰ্তিত ৰক্তকণিকাৰ আয়ুসে HbA1c-ৰ ফলাফল বিভ্ৰান্তিকৰ কৰি তুলিব পাৰে।
Fasting glucose measures one moment and may be normal despite post-meal symptoms. A clinician may instead use a supervised oral glucose tolerance test, targeted monitoring or medication review when episodes occur predictably after eating.
A CBC can identify anaemia or macrocytosis, while ferritin and transferrin saturation help assess iron status; TSH with free T4 evaluates thyroid signalling. B12, folate, kidney function, liver enzymes or inflammatory markers are selected when history and examination support them, not automatically for everyone.
Kantesti’ৰ AI ৰক্ত পৰীক্ষা বিশ্লেষকে আপলোড কৰা পৰীক্ষাগাৰৰ প্ৰতিবেদন প্ৰায় ৬০ ছেকেণ্ডত পঢ়িব পাৰে আৰু বিভিন্ন পেনেলৰ মাজৰ সম্পৰ্কসমূহ উজ্জ্বল কৰি তুলিব পাৰে, লগতে চিহ্নিত ফলাফল আৰু ৰোগনিৰ্ণয়ৰ মাজৰ পাৰ্থক্য অক্ষুণ্ণ ৰাখে। ইয়াৰ ব্যাখ্যা পৰীক্ষাগাৰৰ নিজা প্ৰসংগ পৰিসৰ আৰু চিকিৎসকৰ মূল্যায়নৰ সৈতে মিলাই পৰীক্ষা কৰা উচিত।
| স্তৰ | পৰিসৰ | ইয়াৰ অৰ্থ |
|---|---|---|
| HbA1c সাধাৰণতে স্বাভাৱিক | <5.7% | Usually below the laboratory threshold for prediabetes, though symptoms can have other causes. |
| Prediabetes HbA1c | 5.7-6.4% | Higher future diabetes risk; confirm context and discuss lifestyle or follow-up testing. |
| ডায়েবেটিছৰ পৰিসৰৰ HbA1c | ≥6.5% | লক্ষণ আৰু পুনৰাবৃত্ত পৰীক্ষাৰ সৈতে ক্লিনিকেল নিশ্চিতকৰণ বা ব্যাখ্যাৰ প্ৰয়োজন। |
| অতি উচ্চ গ্লুক'জৰ সৈতে হোৱা লক্ষণসমূহ | Often ≥300 mg/dL (≥16.7 mmol/L) | জৰুৰিতা কিটোন, পানীশূন্যতা, বমি, শ্বাস-প্ৰশ্বাসৰ পৰিৱৰ্তন আৰু মানসিক অৱস্থাৰ ওপৰত নিৰ্ভৰ কৰে; শীঘ্ৰে চিকিৎসা লওক। |
চিকিৎসকৰ সাক্ষাতৰ পূৰ্বে আপুনি নিৰাপদভাৱে চেষ্টা কৰিব পৰা বিষয়সমূহ
সুৰক্ষিত প্ৰথম পদক্ষেপসমূহৰ ভিতৰত আছে নিয়মীয়া টোপনি, কম পৰিমাণৰ সুষম আহাৰ, পৰ্যাপ্ত পানী খোৱা, লাহে লাহে খোৱা আৰু উপযুক্ত হ’লে অলপ সময়ৰ কোমল খোজকঢ়া। These measures may reduce ordinary post-meal sleepiness but should not delay care for recurrent low glucose, severe symptoms or suspected diabetes.

Aim for meals that combine vegetables or other fibre sources with protein and a measured carbohydrate portion rather than relying on sugary drinks or refined snacks. A 10-15 minute walk can be reasonable for many adults, but people with chest pain, severe breathlessness, fainting or exercise restrictions need medical guidance first.
পৰিৱৰ্তন পৰীক্ষা কৰি থকা সময়ত কেফেইন গ্ৰহণৰ সময় একে ৰাখক; দুপৰীয়াৰ আহাৰত 300 mg কেফেইন যোগ কৰিলে নিদ্ৰাৰ ঋণ লুকুৱাব পাৰে আৰু সেই নিশা নিদ্ৰা বেয়া কৰিব পাৰে। এলকহলে অৱসাদ বৃদ্ধি কৰিব পাৰে আৰু উদ্বেগ বা টোপনি নিয়ন্ত্ৰণ কৰিবলৈ ইয়াক ব্যৱহাৰ কৰা উচিত নহয়।
Do not intentionally skip meals if you use insulin or a sulfonylurea. Do not start a very low-carbohydrate diet, supplement plan or fasting schedule without considering pregnancy, kidney disease, eating-disorder history and glucose-lowering medicines.
এটা এটা উপযোগী লক্ষ্য নহয় যে “খোৱাৰ পিছত কেতিয়াও ভাগৰুৱা অনুভৱ নকৰা।” বৰং লক্ষ্য হৈছে মনোযোগ অক্ষুণ্ণ থকা আৰু কোনো সতৰ্কতামূলক লক্ষণ নথকা অৱস্থাত পৰ্ববোৰ কম আৰু মৃদু হোৱা; 1-2 সপ্তাহৰ ভিতৰত ইয়াৰ উন্নতি হয় নে নহয় লিখি ৰাখক।
খোৱাৰ পিছৰ টোপনিৰ বাবে কেতিয়া চিকিৎসা মূল্যায়নৰ প্ৰয়োজন
যেতিয়া বেছিভাগ আহাৰৰ পিছতে টোপনি আহে, কেইবা সপ্তাহ ধৰি থাকে, কাম বা গাড়ী চলোৱাত বাধা দিয়ে, অথবা পিয়াহ, প্ৰস্ৰাৱ, মূৰ্চ্ছা যোৱা যেন লগা, হৃদস্পন্দন বাঢ়ি যোৱা, ওজনৰ পৰিৱৰ্তন বা স্নায়ৱিক লক্ষণৰ সৈতে দেখা দিয়ে, তেতিয়া চিকিৎসা মূল্যায়নৰ ব্যৱস্থা কৰক। হঠাৎ বিভ্ৰান্তি, জগাব নোৱাৰা, খিঁচুনি, তীব্ৰ শ্বাস-প্ৰশ্বাসৰ কষ্ট বা ঢলি পৰা অৱস্থাত জৰুৰী চিকিৎসা সেৱা ল'ব লাগে।

Seek urgent help for confusion, seizure, loss of consciousness, one-sided weakness, chest pain, severe shortness of breath or a suspected glucose below 54 mg/dL (3.0 mmol/L). These signs can indicate severe hypoglycaemia, stroke, heart disease, respiratory compromise or another emergency rather than a routine food coma.
লক্ষণ ২-৪ সপ্তাহ পুনৰাবৃত্তি হ’লে, কথোপকথনৰ সময়ত অনিচ্ছাকৃতভাৱে টোপনি আহিলে, অথবা নাক বজোৱা আৰু প্ৰত্যক্ষ কৰা শ্বাস-প্ৰশ্বাসৰ বিৰতি হ’লে নিয়মীয়া সাক্ষাতৰ সময় নিৰ্ধাৰণ কৰক। চিকিৎসকে সেই ক্ৰমত ঔষধ, ৰক্তচাপ, টোপনি, গ্লুক’জৰ ধৰণ আৰু লক্ষ্যভিত্তিক পৰীক্ষাগাৰৰ পৰীক্ষাসমূহ পৰ্যালোচনা কৰিব পাৰে।
গৰ্ভাৱস্থা, অধিক বয়স, বৃক্কৰ ৰোগ, যকৃতৰ ৰোগ আৰু ডায়েবেটিছে পৰ্যালোচনাৰ নিম্ন সীমা হ্ৰাস কৰে, কাৰণ ঔষধৰ প্ৰভাৱ আৰু গ্লুকোজৰ পৰিৱৰ্তন কম পূৰ্বানুমানযোগ্য হ'ব পাৰে। বাৰে বাৰে আহাৰ-পৰৱৰ্তী টোপনি-টোপনি ভাব হোৱা শিশু আৰু কিশোৰ-কিশোৰীৰ ক্ষেত্ৰতো প্ৰাপ্তবয়স্কৰ ৰেফাৰেন্স পৰিসৰৰ সলনি বয়স-উপযোগী মূল্যায়ন প্ৰয়োজন।
Kantesti হৈছে এক AI বায়োমাৰ্কাৰ ব্যাখ্যা প্লেটফৰ্ম, যিয়ে যোগ্য চিকিৎসকৰ সৈতে আলোচনাৰ পূৰ্বে ফলাফলসমূহ সুশৃংখলিত কৰাত সহায় কৰিব পাৰে; আমাৰ চিকিৎসা বৈধতাৰ তথ্য কাৰিকৰী ব্যাখ্যা আৰু ক্লিনিকেল নিৰ্ণয়ৰ মাজৰ পাৰ্থক্য বুজাই দিয়ে।
How to use laboratory results without overdiagnosing yourself
Laboratory results can clarify glucose, anaemia or thyroid clues, but they cannot prove that a meal caused sleepiness without timing and clinical context. Use results to form better questions, not to replace examination, medication review or sleep assessment.
Kantesti AI-য়ে আপলোড কৰা ৰক্ত-পৰীক্ষাৰ PDF বা ফটোগ্ৰাফ বিশ্লেষণ কৰে আৰু বৰ্তমানৰ মানসমূহ প্ৰকাশিত প্ৰসংগ পৰিসৰ আৰু পূৰ্বৰ ধাৰাসমূহৰ সৈতে তুলনা কৰিব পাৰে। 108 mg/dL (6.0 mmol/L)-ৰ উপবাসী গ্লুক’জে প্ৰিডায়েবেটিছৰ সম্ভাৱনাৰ ইংগিত দিব পাৰে, কিন্তু ই অকলে এটা দুপৰীয়াৰ একক পৰ্বৰ ব্যাখ্যা নিদিয়ে বা ৰোগনিৰ্ণয় প্ৰতিষ্ঠা নকৰে।
আমাৰ AI-য়ে আলোচনাৰ যোগ্য সংযোজনসমূহ চিহ্নিত কৰিব পাৰে, যেনে HbA1c 6.1%ৰ সৈতে উপবাসী গ্লুক'জ 112 mg/dL (6.2 mmol/L), অথবা কম হিম'গ্ল'বিনৰ সৈতে কম ফেৰিটিন। ইয়াৰ দ্বাৰা অপ্ৰমাণিত ঘৰুৱা ৰিডিঙৰ পৰা কাৰণ-ফল সম্পৰ্ক অনুমান কৰা উচিত নহয়, আৰু ই নাক কটা, শ্বাস-প্ৰশ্বাস বন্ধ হোৱা, মেজাজ বা গাড়ী চলোৱাৰ সুৰক্ষা মূল্যায়ন কৰিব নোৱাৰে।
সম্ভৱ হ'লে সম্পূৰ্ণ প্ৰতিবেদন আপলোড কৰক, য'ত একক, সংগ্ৰহৰ তাৰিখ, উপবাসৰ অৱস্থা, পৰীক্ষাগাৰৰ পৰিসৰ আৰু ঔষধৰ প্ৰসংগ অন্তৰ্ভুক্ত থাকে। আংশিক স্ক্ৰীণশ্বটে চিকিৎসাগতভাৱে প্ৰাসংগিক সহযোগী ফলাফল লুকুৱাব পাৰে, আনহাতে বিভিন্ন পৰীক্ষাগাৰে বিভিন্ন assay আৰু reference interval ব্যৱহাৰ কৰিব পাৰে।
Kantesti 127খন দেশৰ 2 millionৰো অধিক লোকে ব্যৱহাৰ কৰে, কিন্তু ব্যাপক উপলব্ধতাই কোনো ব্যাখ্যাক ব্যক্তিগত ৰোগনিৰ্ণয়ত পৰিণত নকৰে। আপোনাৰ ইতিহাস জনা আৰু নিশ্চিতকৰণমূলক পৰীক্ষাৰ ব্যৱস্থা কৰিব পৰা স্থানীয় স্বাস্থ্যসেৱা পেছাদাৰৰ সৈতে উদ্বেগজনক ফলাফলসমূহ আলোচনা কৰক।
Questions to take to a clinician or pharmacist
The most useful appointment questions connect the episode to timing, medicines, sleep and measurable symptoms. Ask whether the pattern suggests glucose testing, sleep assessment, medication adjustment, blood-pressure review or another targeted investigation.
Bring answers to four questions: How soon after eating does drowsiness begin? How long does it last? Does it happen after different meals? What was your sleep duration the night before? A pattern beginning 2-4 hours after meals differs clinically from a predictable 1-3 p.m. dip.
সুধক, “যোৱা 6 ঘণ্টাত লোৱা কোনো ঔষধ বা পৰিপূৰকে তন্দ্ৰা আনিব পাৰে নে বা গ্লুক’জ কমাব পাৰে নে?” লগতে সুধক, বৃক্ক বা যকৃতৰ কাৰ্যক্ষমতাই ঔষধ নিষ্কাশনৰ পৰিৱৰ্তন ঘটাব পাৰে নে; অসুস্থতা, পানীশূন্যতা বা নতুন ঔষধি পাৰস্পৰিক ক্ৰিয়াৰ পিছত স্থিৰ মাত্ৰাৰ ঔষধেও বেলেগ অনুভৱ হ’ব পাৰে।
যদি গ্লুকোজৰ সন্দেহ হয়, কোনটো পৰীক্ষা উপযুক্ত আৰু কোনটো ফলাফল পৰীক্ষাগাৰত নিশ্চিত কৰিব লাগে সুধক। ৰক্তহীনতা বা থাইৰয়ড ৰোগৰ সন্দেহ হ'লে, সীমাহীন পেনেল অৰ্ডাৰ কৰাৰ সলনি CBC, ফেৰিটিন, TSH বা free T4 কিয় বাছি লোৱা হৈছে সুধক।
For reliable privacy and service information, readers can review Kantesti’ৰ Trust Center. Bring the actual laboratory report and your seven-day diary rather than relying on memory.
সাৰাংশ: স্বাভাৱিক অৱনতি নে অনুসন্ধানৰ সংকেত
Most sleepy-after-eating episodes are explained by meal size, rapidly absorbed carbohydrate, circadian timing or insufficient sleep; repeated or severe episodes need evaluation for medication effects, glucose dysregulation, sleep disorders and other illness. The timing and accompanying symptoms are more informative than the word “food coma.”
Start with a 7-day diary and safe, modest changes rather than eliminating many foods. If drowsiness is accompanied by thirst, frequent urination, blurred vision, sweating, tremor, fainting or unintentional weight loss, arrange testing sooner.
স্বাভাৱিক HbA1c-এ আহাৰৰ পিছত হোৱা প্ৰতিটো গ্লুকোজৰ ধৰণ নুই নকৰে, আৰু সামান্য অস্বাভাৱিক গ্লুকোজৰ ফলাফলে গ্লুকোজে উপসৰ্গটো ঘটাইছে বুলি প্ৰমাণ নকৰে। এইটো এনে এটা ক্ষেত্ৰ য'ত কেৱল সংখ্যাটোৰ তুলনাত প্ৰসংগ অধিক গুৰুত্বপূৰ্ণ।
Use laboratory interpretation as a preparation tool: compare dates, units, reference ranges, fasting status and trends. Kantesti’s AI blood test interpretation can help turn a confusing report into focused questions, while the final clinical decision remains with an appropriately qualified healthcare professional.
যদি আপোনাৰ ইমান টোপনি লাগে যে মূৰ দুপিয়াই আহে, তেন্তে গাড়ী নচলাব বা যন্ত্ৰপাতি চলাব নালাগে। পৰ্বটো নিৰাপদভাৱে পৰ্যালোচনা কৰক, জৰুৰী সতৰ্কসংকেত থাকিলে তাৎক্ষণিক সহায় লওক, আৰু এই ধৰণটো অব্যাহত থাকিলে নিয়মীয়া মূল্যায়নৰ ব্যৱস্থা কৰক।
সাধাৰণতে সোধা প্ৰশ্ন
খোৱাৰ পিছত টোপনি টোপনি লগাটো স্বাভাৱিক নেকি?
ডাঙৰ আহাৰ খোৱাৰ পিছত সামান্য টোপনি অহা সাধাৰণ কথা আৰু ই প্ৰায়ে আহাৰৰ পৰিমাণ, দ্ৰুতভাৱে শোষিত হোৱা কাৰ্বহাইড্ৰেট, সাধাৰণ 1-3 p.m. সময়ৰ দৈহিক ঘড়ীৰ অৱনতি, অথবা অপৰ্যাপ্ত টোপনিৰ প্ৰতিফলন। ই সাধাৰণতে 30-90 মিনিটৰ ভিতৰত কমি যায় আৰু দেহৰ সকলো তেজ মগজুৰ পৰা আঁতৰাই পঠিওৱাৰ ফলত নহয়। কেইবা ঘণ্টা ধৰি চলি থকা, বাৰে বাৰে হোৱা এনে পৰ্বই গাড়ী চলোৱাত বাধা দিলে বা পিয়াহ, মূৰ্চ্ছা যাব যেন লগা, ঘাম ওলোৱা অথবা বিভ্ৰান্তিৰ সৈতে দেখা দিলে চিকিৎসা মূল্যায়ন কৰোৱা উচিত।
গ্লুক’জ স্বাভাৱিক হৈ থকাৰ পাছতো আহাৰ খোৱাৰ পিছত মোৰ টোপনি কিয় লাগে?
গ্লুক’জৰ মাত্ৰা স্বাভাৱিক হ’লেও দৈহিক-ছন্দজনিত টোপনি, টোপনিৰ অভাৱ, ঔষধৰ প্ৰভাৱ, স্লিপ এপনিয়া বা বৃহৎ আহাৰৰ টোপনি-অনুভৱ কৰোৱা প্ৰভাৱ নুই কৰা নাযায়। প্ৰাপ্তবয়স্কসকলক সাধাৰণতে কমেও ৭ ঘণ্টা টোপনিৰ প্ৰয়োজন হয়, আৰু একেৰাহে কেইবাটাও নিশা ইয়াতকৈ কম টোপনি হ’লে আহাৰৰ পিছত হোৱা সাধাৰণ টোপনিৰ ভাব অধিক তীব্ৰ হ’ব পাৰে। লক্ষণ দেখা দিয়াৰ সময়ত গ্লুক’জৰ মাত্ৰা 98 mg/dL (5.4 mmol/L) পোৱাটোৱে সেই মুহূৰ্তত হাইপ’গ্লাইছেমিয়াৰ সম্ভাৱনা কমায়, কিন্তু আন কাৰণসমূহৰ ৰোগনিৰ্ণয় নকৰে।
ডায়েবেটিছে খোৱাৰ পিছত আপোনাক টোপনি লগাব পাৰেনে?
ৰক্তত গ্লুক’জৰ মাত্ৰা ধাৰাবাহিকভাৱে অধিক থাকিলে বা চিকিৎসাৰ বাবে অত্যধিক কমি গ’লে Diabetes-এ আহাৰ গ্ৰহণৰ পিছৰ ক্লান্তিত অৰিহণা যোগাব পাৰে। Diabetes-ৰ পৰিসৰৰ পৰীক্ষাগাৰৰ মানদণ্ডসমূহৰ ভিতৰত আছে খালী পেটৰ গ্লুক’জ 126 mg/dL (7.0 mmol/L) বা তাতকৈ অধিক, HbA1c 6.5% বা তাতকৈ অধিক, অথবা 2-ঘণ্টাৰ গ্লুক’জ 200 mg/dL (11.1 mmol/L) বা তাতকৈ অধিক; সাধাৰণতে লক্ষণ নথকা অৱস্থাত এই ফলাফল নিশ্চিত কৰা হয়। অত্যধিক পিয়াহ, ঘনাই প্ৰস্ৰাৱ হোৱা, দৃষ্টিশক্তি অস্পষ্ট হোৱা, ওজন কমি যোৱা, বমি বা বিভ্ৰান্তিয়ে চিকিৎসকৰ পৰামৰ্শ অধিক জৰুৰী কৰি তোলে।
খোৱাৰ পিছত reactive hypoglycaemia কেনে অনুভৱ হয়?
প্ৰতিক্ৰিয়াশীল হাইপ'গ্লাইচেমিয়াই আহাৰ গ্ৰহণৰ প্ৰায় 2-4 ঘণ্টাৰ পিছত টোপনি, দুৰ্বলতা, ঘাম, কঁপনি, ভোক, হৃদস্পন্দন জোৰেৰে অনুভৱ হোৱা বা বিভ্ৰান্তিৰ সৃষ্টি কৰিব পাৰে, বিশেষকৈ দ্ৰুতগতিত শোষিত কাৰ্বহাইড্ৰেটৰ পিছত। লক্ষণসমূহৰ সময়ত 70 mg/dL (3.9 mmol/L)-ৰ তলৰ গ্লুকোজ এটা সতৰ্কতা স্তৰ, আনহাতে 54 mg/dL (3.0 mmol/L)-ৰ তলৰ মান ক্লিনিকেলভাৱে গুৰুত্বপূৰ্ণ। উপযুক্ত পৰীক্ষাৰ জৰিয়তে এই ধৰণটো নিশ্চিত কৰা উচিত, কাৰণ কেৱল ক্লান্তিয়ে হাইপ'গ্লাইচেমিয়া প্ৰমাণ নকৰে।
Which blood tests should I ask for if I am always sleepy after eating?
Common targeted tests include fasting glucose, HbA1c, a complete blood count, ferritin and thyroid-stimulating hormone, with kidney, liver, B12 or other tests selected from the history. HbA1c of 5.7-6.4% falls in the prediabetes range, while a low haemoglobin or low iron-store pattern may suggest anaemia or iron deficiency. A clinician may also prioritise medication review, blood pressure measurement or sleep-apnoea assessment because blood tests cannot detect every cause.
When should I worry about being sleepy after meals?
Seek urgent help for inability to wake, confusion, seizure, collapse, severe breathing difficulty, chest pain, one-sided weakness or suspected glucose below 54 mg/dL (3.0 mmol/L). Arrange a routine appointment when sleepiness follows most meals, lasts 2-4 weeks, causes unintentional daytime sleep or occurs with thirst, frequent urination, faintness, palpitations or unintentional weight loss. Do not drive or operate machinery while unusually drowsy.
আপোনাৰ তেজ পৰীক্ষাৰ ফলাফল কেনেকৈ পঢ়িব
আপোনাৰ পৰীক্ষাগাৰৰ প্ৰতিবেদন আপল’ড কৰক আৰু Kantesti-ৰ AI-এ কেইছেকেণ্ডৰ ভিতৰতে প্ৰতিটো বায়’মাৰ্কাৰ সহজ ভাষাত বুজাই দিয়ে। বিশ্বজুৰি 2 নিযুততকৈও অধিক লোকে ব্যৱহাৰ কৰে।.
তথ্যসূত্ৰ
- ক্লেইন, টি., মিচেল, এস., ও ওয়েবার, এইচ. (২০২৬)।. Kantesti Blood-Test Interpretation Engine ৰ 100,000 টা Synthetic Test Case ত এটা Pre-Registered, Rubric-Based Automated Technical Benchmark।. Kantesti AI চিকিৎসা গৱেষণা।. DOI
- ক্লেইন, টি., মিচেল, এস., ও ওয়েবার, এইচ. (২০২৬)।. Clinical Validation Framework v2.0 (Medical Validation Page)।. Kantesti AI চিকিৎসা গৱেষণা।. DOI
- St-Onge MP et al. (2017). Meal Timing and Frequency: Implications for Cardiovascular Disease Prevention. Circulation।. DOI
- Van Dongen HPA et al. (2003). The Cumulative Cost of Additional Wakefulness: Dose-Response Effects on Neurobehavioral Functions and Sleep Physiology From Chronic Sleep Restriction and Total Sleep Deprivation. Sleep. DOI পাবমেড
- American Diabetes Association Professional Practice Committee (2024). 2. ডায়েবেটিছৰ নিৰ্ণয় আৰু শ্ৰেণীবিভাজন: ডায়েবেটিছৰ যত্নৰ মানদণ্ড—2024।. ডায়েবেটিছ কেয়াৰ।. DOI
- ২M+বিশ্লেষণ কৰা পৰীক্ষাসমূহ
- 127+দেশসমূহ
- 100+ভাষাসমূহ
চিকিৎসা দলৰ বিষয়ে


E-E-A-T বিশ্বাস সংকেত
অভিজ্ঞতা
চিকিৎসক-নিৰ্দেশিত লেব ব্যাখ্যা কাৰ্যপ্ৰবাহৰ ক্লিনিকেল পৰ্যালোচনা।.
বিশেষজ্ঞতা
ক্লিনিকেল পৰিপ্ৰেক্ষিতত বায়’মাৰ্কাৰসমূহ কেনেকৈ আচৰণ কৰে—সেই বিষয়ে লেবৰেটৰী মেডিচিনৰ গুৰুত্ব।.
কৰ্তৃত্বশীলতা
ডাঃ Thomas Klein-এ চিকিৎসা পৰ্যালোচনা কৰিছে; ডাঃ Sarah Mitchell আৰু অধ্যাপক ডাঃ Hans Weber-ৰ অৱদান আছে।.
বিশ্বাসযোগ্যতা
স্পষ্ট অনুসৰণ পথৰ সৈতে প্ৰমাণ-ভিত্তিক ব্যাখ্যা—আতংক কমাবলৈ।.




চিকিৎসা-সম্পৰ্কীয় অস্বীকাৰোক্তি
এই লেখাটো কেৱল শিক্ষামূলক উদ্দেশ্যৰ বাবে, আৰু ই চিকিৎসাজনিত পৰামৰ্শ নহয়। ৰোগ নিৰ্ণয় আৰু চিকিৎসাৰ সিদ্ধান্তৰ বাবে সদায় যোগ্য স্বাস্থ্যসেৱা বিশেষজ্ঞৰ সৈতে পৰামৰ্শ কৰক।.
প্ৰকাশিত · সম্পাদকীয় দলৰ সৈতে যোগাযোগ কৰক
Kantesti Ltd-ৰ দ্বাৰা প্ৰকাশিত, ইংলেণ্ড আৰু ৱেলছত পঞ্জীয়নভুক্ত, কোম্পানী নং।. 17090423, লণ্ডন, যুক্তৰাজ্য।.
