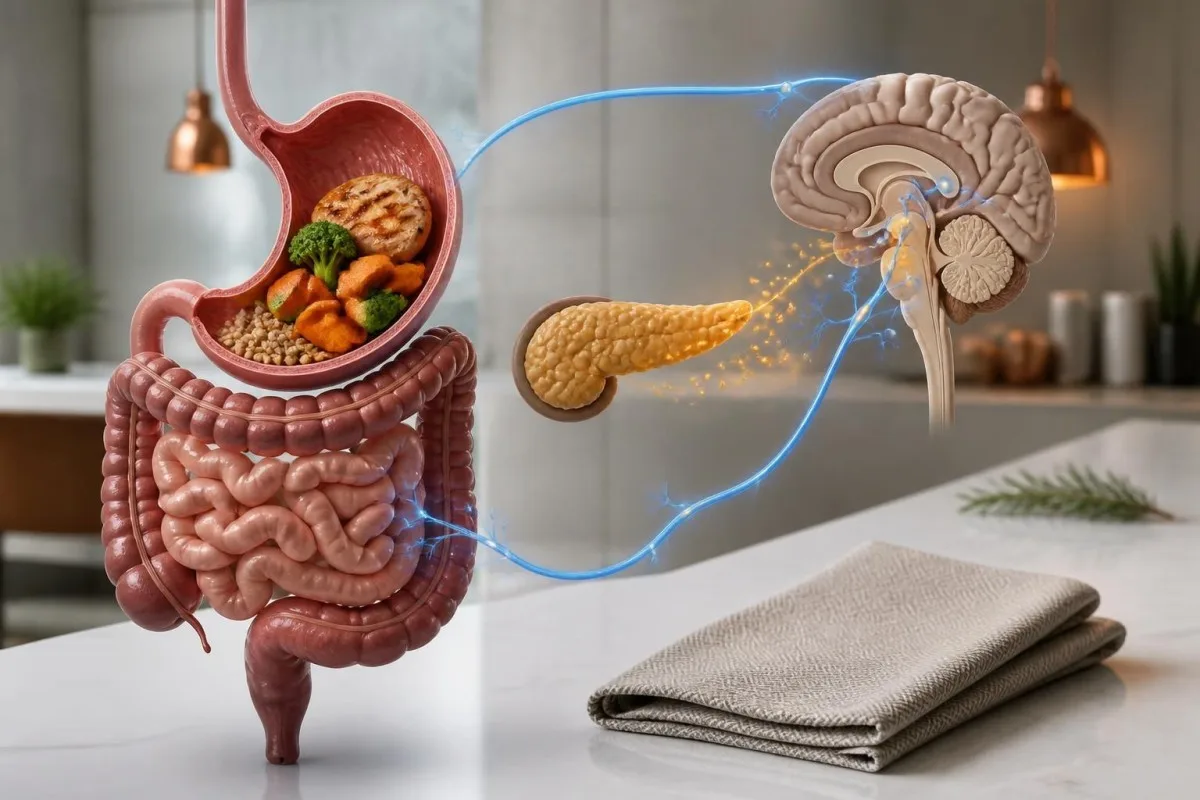
A post-meal dip is often normal, but repeated or severe drowsiness can reveal sleep loss, medication effects, blood-glucose changes or another treatable problem.

Ključne ugotovitve
- Common pattern: Feeling sleepy after eating usually reflects a large, rapidly digested meal combined with the natural early-afternoon circadian dip, not blood being diverted away from the brain.
- Sleep debt: Adults generally need at least 7 hours of sleep; repeated nights below that amount can make an ordinary meal feel disproportionately sedating.
- Glucose clue: A laboratory fasting glucose of 100-125 mg/dL (5.6-6.9 mmol/L) falls in the prediabetes range, while 126 mg/dL (7.0 mmol/L) or higher requires confirmation unless clear symptoms are present.
- Possible low glucose: Symptoms occurring 2-4 hours after a carbohydrate-heavy meal may reflect post-meal glucose falling below 70 mg/dL (3.9 mmol/L), although a meter or continuous monitor can be inaccurate.
- Učinek zdravila: Sedating antihistamines, opioids, sleep medicines, some anti-anxiety drugs and gabapentinoids can intensify post-meal drowsiness; do not stop them without prescriber advice.
- When to act: Recurrent sleepiness with thirst, frequent urination, blurred vision, fainting, confusion, unintentional weight loss or severe weakness deserves medical assessment.
- Useful first tests: Depending on the history, clinicians may consider fasting glucose, HbA1c, complete blood count, ferritin, thyroid-stimulating hormone and medication review.
- Varnost: Do not drive, operate machinery or climb while unusually drowsy, especially if the episode follows a glucose-lowering medicine.
What feeling sleepy after eating usually means
Sleepiness after eating is usually caused by meal size, rapidly absorbed carbohydrate, the normal early-afternoon circadian dip, or inadequate sleep rather than a dangerous digestive problem. A single mild episode after a large lunch is usually benign; repeated, sudden or disabling episodes deserve a closer look. Our blood-test biomarkers guide explains why isolated results rarely answer a symptom question.

The strongest everyday pattern is a combination of meal load and timing: a 1,000-calorie lunch rich in refined starch can produce more drowsiness than a 500-calorie meal containing vegetables, protein and fibre. The effect often peaks 30-120 minutes later, when digestion, insulin release and the body’s daytime alertness rhythm overlap.
Post-meal sleepiness does not usually mean that digestion steals so much blood from the brain that the brain becomes under-supplied. Blood flow is tightly regulated; the more useful explanation is interacting signals from the gut, pancreas, brain and circadian clock, with individual responses varying substantially.
A practical distinction is duration. Drowsiness that fades within 30-90 minutes after an occasional large meal is usually different from recurrent episodes lasting several hours, sleep attacks, confusion or symptoms of low glucose; the latter patterns warrant a structured history and possibly testing.
How digestion can promote post-meal sleepiness
Digestion can promote drowsiness through gut-brain signalling, insulin-related changes and meal-induced relaxation, but no single mechanism explains every food coma. Hormones such as cholecystokinin rise after meals, while the brain’s arousal systems respond to nutrient availability and the social setting of eating.
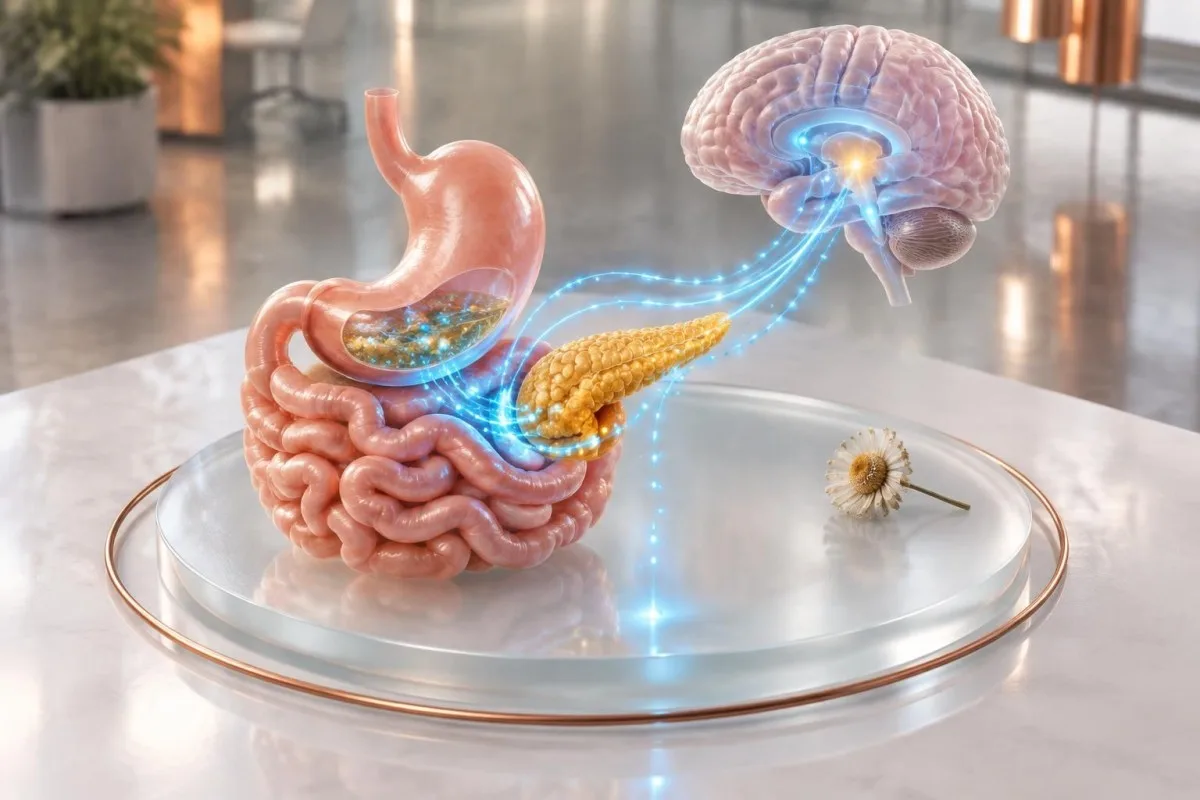
Fat and protein can stimulate cholecystokinin, a gut hormone associated with satiety and reduced arousal in experimental settings. That does not mean fat automatically causes abnormal sleepiness: a meal’s total energy, fibre, alcohol content, hydration and the person’s prior sleep can matter more than one nutrient.
Carbohydrate intake increases insulin secretion, which changes the movement of several amino acids into tissues and may alter the relative availability of tryptophan for brain serotonin and melatonin production. The evidence is honestly mixed, and normal post-meal insulin action should not be confused with insulin resistance.
The phrase “food coma” describes a sensation, not a diagnosis. If a 700-kilocalorie meal causes mild drowsiness for 45 minutes, that is generally less concerning than a repeated 3-hour crash accompanied by tremor, sweating or palpitations.
Why blood is not simply diverted from the brain
Human circulation can increase blood delivery to the digestive organs after eating while preserving brain perfusion. A severe light-headed feeling after meals is more suggestive of blood-pressure regulation, dehydration or a glucose problem than of ordinary digestion alone; a blood-pressure review may be useful when symptoms include standing dizziness.
Which meal patterns make sleepiness more likely
Large meals high in rapidly absorbed carbohydrate, saturated fat or alcohol are the most common meal-related contributors to post-meal sleepiness. Portion size and carbohydrate quality usually matter more than whether a food is labelled “healthy” or “unhealthy.”
A meal containing 100 grams of rapidly absorbed carbohydrate can raise glucose and insulin more sharply than one containing 40 grams of carbohydrate plus beans, vegetables and protein. Fibre slows gastric emptying and glucose absorption; it does not cancel the energy content of an oversized meal, but it can reduce the speed of the glucose rise.
Fat can delay stomach emptying, which sometimes produces a later, longer period of heaviness rather than an immediate crash. Alcohol is different: even one standard drink can worsen alertness and fragment sleep later that night, making the next day’s meal-related drowsiness easier to misinterpret.
A clearly hypothetical example helps: a 35-year-old office worker sleeps 6 hours, skips breakfast and eats a large sweetened drink with white bread at 1 p.m. A 90-minute slump could reflect circadian timing plus sleep debt and meal composition; it does not by itself prove diabetes.
For practical comparisons, record the meal’s approximate portion, carbohydrate source and symptom timing for 7 days rather than banning individual foods after one episode. A guide to fasting instructions can also prevent confusion when later blood testing is arranged.
Why the afternoon circadian dip can feel like a food coma
The body’s circadian alertness rhythm commonly dips in the early afternoon, often between about 1 and 3 p.m., even when a person has not just eaten. A midday meal can amplify that predictable reduction in wakefulness.

Alertness is not a flat line across the day. The central circadian clock coordinates sleep pressure, body temperature, melatonin timing and cortisol rhythms; in many adults, wakefulness decreases after midday while the biological night remains the strongest sleep window.
Meal timing can interact with this clock. The American Heart Association’s scientific statement on meal timing describes links between irregular eating, circadian biology and cardiometabolic health, although it does not establish one universal “safe” meal schedule (St-Onge et al., 2017).
A useful experiment is to compare equivalent meals at 11 a.m. and 2 p.m. on separate days, while keeping sleep and caffeine similar. If sleepiness appears at both times, meal composition may dominate; if it appears mainly at 2 p.m., circadian timing is a stronger clue.
People who work rotating shifts or cross time zones may experience the dip at an unusual clock time because their internal rhythm and local schedule disagree. A vodnik za čas testiranja krvi is useful when shift work also affects the timing of laboratory samples.
How sleep debt magnifies sleepy-after-meals symptoms
Sleep debt makes ordinary post-meal drowsiness stronger because sleep pressure has already accumulated before the meal begins. Adults who routinely sleep below 7 hours may notice the problem most during monotonous tasks, warm rooms or the early afternoon.

The American Academy of Sleep Medicine and Sleep Research Society recommend that adults obtain at least 7 hours of sleep regularly for health. Five nights of 6-hour sleep create a 5-hour weekly shortfall compared with that minimum, even if the person feels they have adapted.
In a controlled study, Van Dongen et al. found that chronic restriction to 6 hours or 4 hours per night produced cumulative neurobehavioral impairment, while participants became less accurate at judging their own impairment (Sleep, 2003). That finding matters because “I am used to it” is not a reliable safety test.
A hypothetical 52-year-old marathon runner may feel sleepy after a normal lunch because training, early waking and 6 hours of sleep have increased sleep pressure; the same meal may not cause symptoms after several nights of 8 hours. The pattern points first toward recovery and sleep assessment, not automatically toward a food intolerance.
Track bedtime, wake time, awakenings, snoring, alcohol and caffeine for 14 days. Loud snoring, witnessed breathing pauses or morning headaches make sleep-apnoea assessment more relevant than simply reducing carbohydrates.
How portion size, speed and activity change the crash
Eating quickly, consuming a very large portion or remaining still after lunch can intensify post-meal sleepiness. A smaller meal eaten slowly, followed by gentle movement, often produces a different response without requiring extreme dietary restriction.

Large meals stretch the stomach and may increase satiety signals, while rapid eating compresses more energy into a shorter period. A 20-minute meal containing 800 calories can therefore feel different from the same food eaten over 45 minutes with water and pauses.
A 10-15 minute easy walk after eating may reduce the height of the post-meal glucose rise in some people by increasing muscle glucose uptake. It is not a treatment for diabetes, and people with balance problems, chest symptoms or exercise restrictions should follow their clinician’s advice.
The relevant comparison is personal, not universal: a 600-calorie lunch with 35 grams of fibre-containing carbohydrate may be tolerated better than a 350-calorie pastry-and-sweet-drink combination. Weight-loss goals, medication timing and glucose-lowering treatment can change the safest plan.
Try changing one variable at a time for 5-7 days: portion size, meal speed, refined carbohydrate, or a short walk. The AI nutrition and lab context guide explains why dietary suggestions should be interpreted alongside biomarkers rather than as a diagnosis.
Which medicines can worsen sleepy-after-meals episodes
Sedating medicines and alcohol can make a normal post-meal dip feel excessive, and meal timing can make their peak effects more noticeable. Common contributors include first-generation antihistamines, opioids, sleep medicines, benzodiazepines, some antipsychotics, gabapentinoids and sedating antidepressants.
Diphenhydramine and other first-generation antihistamines can impair alertness; opioids and benzodiazepines can also reduce breathing drive and reaction speed. A medicine taken at 8 a.m. may still contribute to a noon episode depending on its half-life, dose, kidney function and interactions.
Some medicines influence glucose rather than sedation directly. Insulin and sulfonylureas can cause hypoglycaemia, especially after eating less than planned, exercising more than usual or drinking alcohol; symptoms may include sweating, shaking, hunger, palpitations and confusion rather than simple sleepiness.
Never stop a prescribed medicine abruptly because of drowsiness. Ask a pharmacist or prescriber whether timing, dose, an alternative or kidney-function review is appropriate, and avoid driving if the reaction is unpredictable.
Bring a complete list of prescriptions, over-the-counter products, supplements and recreational substances to the review. A potek dela za spremljanje trendov varnosti zdravil can help organise laboratory trends, but it cannot replace a prescribing decision.
When glucose regulation may explain post-meal fatigue
Glucose regulation becomes more concerning when sleepiness is persistent, disproportionate or accompanied by thirst, frequent urination, blurred vision, recurrent infections or unexplained weight change. High glucose can cause fatigue through dehydration and altered cellular fuel use, while low glucose can cause neuroglycopenic drowsiness.

The American Diabetes Association defines diabetes using laboratory criteria such as HbA1c of 6.5% or higher, fasting plasma glucose of 126 mg/dL (7.0 mmol/L) or higher, or a 2-hour oral glucose tolerance result of 200 mg/dL (11.1 mmol/L) or higher, usually confirmed when symptoms are absent (American Diabetes Association Professional Practice Committee, 2024).
Kantesti is an AI blood test interpretation platform that places glucose, HbA1c, triglycerides, liver markers and kidney markers into a connected context rather than treating a single post-meal sensation as proof of diabetes. Our platform can explain reported values, but diagnosis still depends on validated testing and clinical assessment.
A home glucose value after an ordinary meal is not equivalent to a diagnostic oral glucose tolerance test. Capillary meters can differ from laboratory plasma glucose, and continuous glucose monitors measure interstitial fluid with a delay; a surprising result should be repeated or confirmed rather than overinterpreted.
If thirst and urination occur with repeated drowsiness, arrange medical review rather than merely switching foods. The vodnik po simptomih visokega krvnega sladkorja describes warning patterns that should not be dismissed as a routine food coma.
| Raven | Razpon | Kaj pomeni |
|---|---|---|
| normalna glukoza na tešče | <100 mg/dL (<5,6 mmol/L) | Usually within the normal diagnostic range; one result does not explain every symptom. |
| Razpon za prediabetes | 100–125 mg/dL (5,6–6,9 mmol/L) | Suggests increased diabetes risk and usually calls for repeat testing or HbA1c assessment. |
| Rezultat v območju za sladkorno bolezen | 126–199 mg/dL (7,0–11,0 mmol/L) | Requires confirmation or symptom-based clinical interpretation; it is not explained by ordinary post-meal sleepiness alone. |
| Izrazita hiperglikemija | ≥200 mg/dL (≥11.1 mmol/L) with symptoms | Needs prompt medical assessment, especially with vomiting, dehydration, deep breathing or confusion. |
Could a glucose drop cause sleepiness 2 to 4 hours later
A glucose fall 2-4 hours after eating can cause sleepiness, weakness, sweating, tremor, hunger or confusion, particularly after a high-carbohydrate meal or with glucose-lowering medicine. True post-meal hypoglycaemia should be demonstrated during symptoms rather than assumed from fatigue alone.
Clinicians commonly use a glucose below 70 mg/dL (3.9 mmol/L) as an alert level, while below 54 mg/dL (3.0 mmol/L) indicates clinically significant hypoglycaemia requiring urgent attention. The number matters most when symptoms occur at the same time and improve after glucose is corrected.
The diagnostic logic is often called Whipplova triada: compatible symptoms, a documented low glucose during those symptoms, and improvement when glucose rises. A person who feels sleepy at 2 p.m. but has a glucose of 98 mg/dL (5.4 mmol/L) has not demonstrated hypoglycaemia.
A 28-year-old with episodes after sweet drinks may have a rapid rise and fall, but a meter reading of 62 mg/dL (3.4 mmol/L) should be confirmed when feasible because home devices have analytical error. Fasting, alcohol use, exercise and medicines can create different patterns.
For prescribed insulin or sulfonylurea users, follow the personal rescue plan and carry a rapid carbohydrate source. People without diabetes who repeatedly record low values need medical evaluation rather than repeated self-treatment; see our vodnik po vzrokih nizke glukoze for testing context.
Other conditions that can mimic sleepy-after-meals symptoms
Anaemia, iron deficiency, thyroid disease, sleep apnoea, depression, chronic illness and some infections can cause daytime sleepiness that merely becomes noticeable after meals. The meal may be a trigger for noticing fatigue, not the underlying cause.

A complete blood count can identify anaemia, but ferritin interpretation requires context because inflammation can raise ferritin while iron stores are limited. There is no single ferritin threshold that explains sleepiness for everyone; a low ferritin with low transferrin saturation is more informative than an isolated borderline value.
Hypothyroidism may cause fatigue, cold intolerance, constipation, dry skin and slowed thinking, although symptoms are nonspecific. Many laboratories use a TSH upper reference limit near 4.0-4.5 mIU/L, but ranges differ by assay, age, pregnancy and local practice; some European laboratories use different limits.
Sleep apnoea can produce severe daytime somnolence regardless of meal composition. Snoring, witnessed pauses, morning headaches or resistant hypertension should prompt sleep evaluation, especially when an individual unintentionally dozes during conversations or driving.
Kantesti AI can organise a CBC, ferritin, thyroid markers and glucose into a readable pattern, but a normal panel does not exclude sleep disorders or depression. Relevant background reading includes simptomi nizkega feritina in subclinical thyroid results.
When food reactions are relevant to post-meal drowsiness
Food intolerance can cause bloating, abdominal pain or diarrhoea after eating, but isolated sleepiness is not a reliable sign of intolerance or allergy. A true allergic reaction is more likely when drowsiness occurs with hives, swelling, wheezing, throat tightness, repeated vomiting or faintness.

Lactose or fructose malabsorption can produce gastrointestinal symptoms several hours after exposure, but neither condition should be diagnosed from tiredness alone. A lactose-intolerance testing guide explains why breath-test preparation and symptom timing matter.
Drowsiness with wheezing, facial or tongue swelling, blue lips, collapse or rapidly worsening symptoms is an emergency because severe allergic reactions can impair breathing and blood pressure. Do not perform a home food challenge after a suspected serious reaction.
A food diary should record ingredients, portion, timing, symptoms and exercise for at least 7 days; an elimination diet that removes many foods can create nutritional problems and obscure the actual trigger. The practical question is whether symptoms reproduce reliably with a specific exposure.
Blood allergy panels are not universal screens for food intolerance, and a positive sensitisation test does not prove that a food causes sleepiness. Ask a clinician or allergy specialist to interpret results alongside the history.
A useful 7-day test for sleepy-after-meals episodes
A seven-day symptom diary can separate meal effects from sleep debt, circadian timing, medicines and glucose changes. Record the time of eating, approximate portion, sleep duration, caffeine, medication timing, activity and symptom severity from 0 to 10.
Measure only what you can interpret safely. If you have diabetes, use the monitoring plan prescribed for you; if not, occasional glucose checks may provide clues but cannot diagnose reactive hypoglycaemia or diabetes on their own.
A useful pattern is reproducibility: symptoms beginning 45 minutes after a large sweet drink on four of five days suggest a meal-related trigger, while symptoms at 2 p.m. after different meals suggest circadian timing. Symptoms after poor sleep but not after 8-hour nights point toward sleep pressure.
Include posture and blood pressure if episodes involve light-headedness, blurred vision or near-fainting. A blood pressure drop after eating can be more relevant than food composition, particularly in older adults or people taking antihypertensive medicines.
At the appointment, bring the diary and packaging or names of supplements. Our baseline blood-test preparation guide helps readers avoid changing several variables immediately before a planned assessment.
Which blood tests may help explain repeated drowsiness
The most useful tests depend on the symptom pattern, but clinicians commonly consider HbA1c, fasting glucose, a complete blood count, ferritin, thyroid-stimulating hormone and kidney or liver markers. No blood panel can diagnose every cause of sleepiness.
HbA1c reflects average glycaemia over roughly 2-3 months and is generally interpreted as normal below 5.7%, prediabetes at 5.7-6.4% and diabetes at 6.5% or higher. Recent transfusion, haemolysis, some haemoglobin variants, pregnancy and altered red-cell survival can make HbA1c misleading.
Fasting glucose measures one moment and may be normal despite post-meal symptoms. A clinician may instead use a supervised oral glucose tolerance test, targeted monitoring or medication review when episodes occur predictably after eating.
A CBC can identify anaemia or macrocytosis, while ferritin and transferrin saturation help assess iron status; TSH with free T4 evaluates thyroid signalling. B12, folate, kidney function, liver enzymes or inflammatory markers are selected when history and examination support them, not automatically for everyone.
Kantesti’s AI blood test analyzer can read uploaded laboratory reports in about 60 seconds and highlight relationships across panels, while preserving the distinction between a flagged result and a diagnosis. Its interpretation should be checked against the laboratory’s own reference range and a clinician’s assessment.
| Raven | Razpon | Kaj pomeni |
|---|---|---|
| HbA1c commonly normal | <5.7% | Usually below the laboratory threshold for prediabetes, though symptoms can have other causes. |
| Prediabetes HbA1c | 5.7-6.4% | Higher future diabetes risk; confirm context and discuss lifestyle or follow-up testing. |
| HbA1c v območju za sladkorno bolezen | ≥6.5% | Requires clinical confirmation or interpretation with symptoms and repeat testing. |
| Symptoms with very high glucose | Often ≥300 mg/dL (≥16.7 mmol/L) | Urgency depends on ketones, dehydration, vomiting, breathing changes and mental status; seek prompt care. |
What you can safely try before a medical visit
Safe first steps include regular sleep, smaller balanced meals, adequate water, slower eating and a brief gentle walk when appropriate. These measures may reduce ordinary post-meal sleepiness but should not delay care for recurrent low glucose, severe symptoms or suspected diabetes.

Aim for meals that combine vegetables or other fibre sources with protein and a measured carbohydrate portion rather than relying on sugary drinks or refined snacks. A 10-15 minute walk can be reasonable for many adults, but people with chest pain, severe breathlessness, fainting or exercise restrictions need medical guidance first.
Keep caffeine timing consistent while testing changes; adding 300 mg of caffeine at lunch can hide sleep debt and worsen sleep that night. Alcohol can intensify sedation and should not be used to manage anxiety or sleepiness.
Do not intentionally skip meals if you use insulin or a sulfonylurea. Do not start a very low-carbohydrate diet, supplement plan or fasting schedule without considering pregnancy, kidney disease, eating-disorder history and glucose-lowering medicines.
A useful target is not “never feel tired after eating.” It is fewer, milder episodes with preserved concentration and no warning symptoms; record whether that improves over 1-2 weeks.
When post-meal drowsiness needs medical evaluation
Arrange medical evaluation when sleepiness occurs after most meals, lasts for weeks, interferes with work or driving, or comes with thirst, urination, faintness, palpitations, weight change or neurological symptoms. Sudden confusion, inability to wake, seizure, severe breathing difficulty or collapse requires emergency care.

Seek urgent help for confusion, seizure, loss of consciousness, one-sided weakness, chest pain, severe shortness of breath or a suspected glucose below 54 mg/dL (3.0 mmol/L). These signs can indicate severe hypoglycaemia, stroke, heart disease, respiratory compromise or another emergency rather than a routine food coma.
Book a routine appointment if symptoms recur for 2-4 weeks, if you unintentionally fall asleep during conversations, or if snoring and witnessed breathing pauses occur. A clinician may review medicines, blood pressure, sleep, glucose patterns and targeted laboratory tests in that order.
Pregnancy, older age, kidney disease, liver disease and diabetes lower the threshold for review because medication effects and glucose changes may be less predictable. Children and adolescents with repeated post-meal sleepiness also need age-appropriate assessment rather than adult reference ranges.
Kantesti is an AI biomarker interpretation platform that can help organise results before a discussion with a qualified clinician; our informacije o medicinski validaciji explains the difference between technical interpretation and clinical diagnosis.
How to use laboratory results without overdiagnosing yourself
Laboratory results can clarify glucose, anaemia or thyroid clues, but they cannot prove that a meal caused sleepiness without timing and clinical context. Use results to form better questions, not to replace examination, medication review or sleep assessment.
Kantesti AI analyses uploaded blood-test PDFs or photographs and can compare current values with reported reference ranges and previous trends. A fasting glucose of 108 mg/dL (6.0 mmol/L) may suggest prediabetes risk, but it does not explain a single afternoon episode or establish a diagnosis by itself.
Our AI can flag combinations that merit discussion, such as HbA1c 6.1% with fasting glucose 112 mg/dL (6.2 mmol/L), or low haemoglobin with low ferritin. It should not infer causation from an unvalidated home reading, and it cannot assess snoring, breathing pauses, mood or the safety of driving.
Upload the complete report when possible, including units, collection date, fasting status, laboratory ranges and medication context. Partial screenshots can hide clinically relevant companion results, while different laboratories may use different assays and reference intervals.
Kantesti is used by more than 2 million people across 127 countries, but broad availability does not make an interpretation a personal diagnosis. Discuss concerning findings with a local healthcare professional who knows your history and can arrange confirmatory testing.
Questions to take to a clinician or pharmacist
The most useful appointment questions connect the episode to timing, medicines, sleep and measurable symptoms. Ask whether the pattern suggests glucose testing, sleep assessment, medication adjustment, blood-pressure review or another targeted investigation.
Bring answers to four questions: How soon after eating does drowsiness begin? How long does it last? Does it happen after different meals? What was your sleep duration the night before? A pattern beginning 2-4 hours after meals differs clinically from a predictable 1-3 p.m. dip.
Ask, “Could any medicine or supplement taken in the last 6 hours be sedating or lower glucose?” Also ask whether kidney or liver function could change drug clearance; even a stable dose can feel different after illness, dehydration or a new interaction.
If glucose is suspected, ask which test is appropriate and what result should be confirmed in a laboratory. If anaemia or thyroid disease is suspected, ask why CBC, ferritin, TSH or free T4 is being chosen rather than ordering an unrestricted panel.
For reliable privacy and service information, readers can review Kantesti’s Trust Center. Bring the actual laboratory report and your seven-day diary rather than relying on memory.
Bottom line: normal dip or signal to investigate
Most sleepy-after-eating episodes are explained by meal size, rapidly absorbed carbohydrate, circadian timing or insufficient sleep; repeated or severe episodes need evaluation for medication effects, glucose dysregulation, sleep disorders and other illness. The timing and accompanying symptoms are more informative than the word “food coma.”
Start with a 7-day diary and safe, modest changes rather than eliminating many foods. If drowsiness is accompanied by thirst, frequent urination, blurred vision, sweating, tremor, fainting or unintentional weight loss, arrange testing sooner.
A normal HbA1c does not rule out every post-meal glucose pattern, and a mildly abnormal glucose result does not prove that glucose caused the symptom. This is one of those areas where context matters more than the number alone.
Use laboratory interpretation as a preparation tool: compare dates, units, reference ranges, fasting status and trends. Kantesti’s AI blood test interpretation can help turn a confusing report into focused questions, while the final clinical decision remains with an appropriately qualified healthcare professional.
If you are sleepy enough to nod off, do not drive or operate machinery. Review the episode safely, seek urgent help for emergency warning signs, and arrange a routine assessment when the pattern persists.
Pogosta vprašanja
Ali je normalno, da se po jedi počutite zaspano?
Blaga zaspanost po obilnem obroku je pogosta in je pogosto povezana z velikostjo obroka, hitro absorbirajočimi se ogljikovimi hidrati, običajnim cirkadianim upadom med 1. in 3. uro popoldne ali nezadostnim spanjem. Običajno se izboljša v 30–90 minutah in ni posledica tega, da bi bila vsa kri v telesu preusmerjena stran od možganov. Ponavljajoče se epizode, ki trajajo več ur, ovirajo vožnjo ali se pojavljajo z žejo, občutkom omedlevice, potenjem ali zmedenostjo, zahtevajo zdravniško oceno.
Zakaj se po obrokih počutim zaspano, čeprav je moja raven glukoze normalna?
Normalna raven glukoze ne izključuje zaspanosti zaradi cirkadianega ritma, pomanjkanja spanja, učinkov zdravil, spalne apneje ali sedativnih učinkov obilnega obroka. Odrasli običajno potrebujejo vsaj 7 ur spanja, več zaporednih noči s krajšim spanjem pa lahko okrepi običajen padec budnosti po obroku. Vrednost glukoze 98 mg/dL (5,4 mmol/L) med simptomi pomeni, da je hipoglikemija takrat manj verjetna, vendar ne potrjuje drugih vzrokov.
Ali vas lahko sladkorna bolezen po jedi uspava?
Sladkorna bolezen lahko prispeva k utrujenosti po obroku, kadar je raven glukoze vztrajno visoka ali zaradi zdravljenja pade prenizko. Laboratorijska merila za sladkorno bolezen vključujejo glukozo na tešče 126 mg/dL (7,0 mmol/L) ali več, HbA1c 6,5% ali več ali glukozo po 2 urah 200 mg/dL (11,1 mmol/L) ali več; če simptomov ni, je treba rezultate običajno potrditi. Žeja, pogosto uriniranje, zamegljen vid, izguba telesne teže, bruhanje ali zmedenost zahtevajo čimprejšnji zdravniški pregled.
Kako se občuti reaktivna hipoglikemija po jedi?
Reaktivna hipoglikemija lahko povzroči zaspanost, šibkost, potenje, tremor, lakoto, palpitacije ali zmedenost približno 2–4 ure po obroku, pogosto po zaužitju hitro absorbirajočih se ogljikovih hidratov. Raven glukoze pod 70 mg/dL (3,9 mmol/L) med simptomi je opozorilna vrednost, medtem ko je raven pod 54 mg/dL (3,0 mmol/L) klinično pomembna. Ta vzorec je treba potrditi z ustreznim testiranjem, saj sama utrujenost ne dokazuje hipoglikemije.
Katere krvne preiskave naj opravim, če sem po jedi vedno zaspan/-a?
Pogosti ciljno usmerjeni testi vključujejo glukozo na tešče, HbA1c, kompletno krvno sliko, feritin in ščitnico stimulirajoči hormon, pri čemer se ledvični, jetrni, B12 ali drugi testi izberejo na podlagi anamneze. Vrednost HbA1c 5.7-6.4% spada v območje prediabetesa, medtem ko lahko nizka raven hemoglobina ali vzorec nizkih zalog železa kaže na anemijo ali pomanjkanje železa. Zdravnik lahko da prednost tudi pregledu zdravil, merjenju krvnega tlaka ali oceni spalne apneje, saj krvni testi ne morejo odkriti vsakega vzroka.
Kdaj naj me skrbi zaspanost po obrokih?
Seek urgent help for inability to wake, confusion, seizure, collapse, severe breathing difficulty, chest pain, one-sided weakness or suspected glucose below 54 mg/dL (3.0 mmol/L). Arrange a routine appointment when sleepiness follows most meals, lasts 2-4 weeks, causes unintentional daytime sleep or occurs with thirst, frequent urination, faintness, palpitations or unintentional weight loss. Do not drive or operate machinery while unusually drowsy.
Poskrbite, da vam razložijo rezultate krvnih preiskav
Naložite svoj laboratorijski izvid in AI Kantesti bo v nekaj sekundah preprosto razložil vsak biomarker. Uporablja ga več kot 2 milijona ljudi po vsem svetu.
Reference
- Klein, T., Mitchell, S., & Weber, H. (2026). Predregistrirana, na rubrikah zasnovana avtomatizirana tehnična primerjava (benchmark) interpretacijskega motorja Kantesti za analizo krvnih testov na 100.000 sintetičnih testnih primerih. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Klinični okvir validacije v2.0 (stran za medicinsko validacijo). Kantesti AI Medical Research. DOI
- St-Onge MP et al. (2017). Meal Timing and Frequency: Implications for Cardiovascular Disease Prevention. Circulation. DOI
- Van Dongen HPA et al. (2003). The Cumulative Cost of Additional Wakefulness: Dose-Response Effects on Neurobehavioral Functions and Sleep Physiology From Chronic Sleep Restriction and Total Sleep Deprivation. Sleep. DOI PubMed
- Strokovni odbor za klinično prakso Ameriškega združenja za sladkorno bolezen (2024). 2. Diagnostika in klasifikacija sladkorne bolezni: standardi oskrbe pri sladkorni bolezni—2024. Diabetes Care. DOI
- 2 milijona+Analizirani testi
- 127+Države
- 100+Jeziki
O zdravstveni ekipi


E-E-A-T zaupanja vredni signali
Izkušnje
Zdravniški klinični pregled delovnih postopkov za interpretacijo laboratorijskih izvidov.
Strokovno znanje
Laboratorijska medicina s poudarkom na tem, kako se biomarkerji obnašajo v kliničnem kontekstu.
Avtoritativnost
Zdravstveno pregledal dr. Thomas Klein, s prispevki dr. Sarah Mitchell in prof. dr. Hansa Webra.
Zanesljivost
Interpretacija na podlagi dokazov z jasnimi nadaljnjimi potmi za zmanjšanje alarmiranja.




Zdravstvena omejitev odgovornosti
Ta članek je namenjen izobraževalnim namenom in ne predstavlja medicinskega nasveta. Za odločitve o diagnozi in zdravljenju se vedno posvetujte z usposobljenim izvajalcem zdravstvenih storitev.
Objavljeno · Obrnite se na uredniško ekipo
Izdala družba Kantesti Ltd, registrirana v Angliji in Walesu, matična št. 17090423, London, Združeno kraljestvo.
