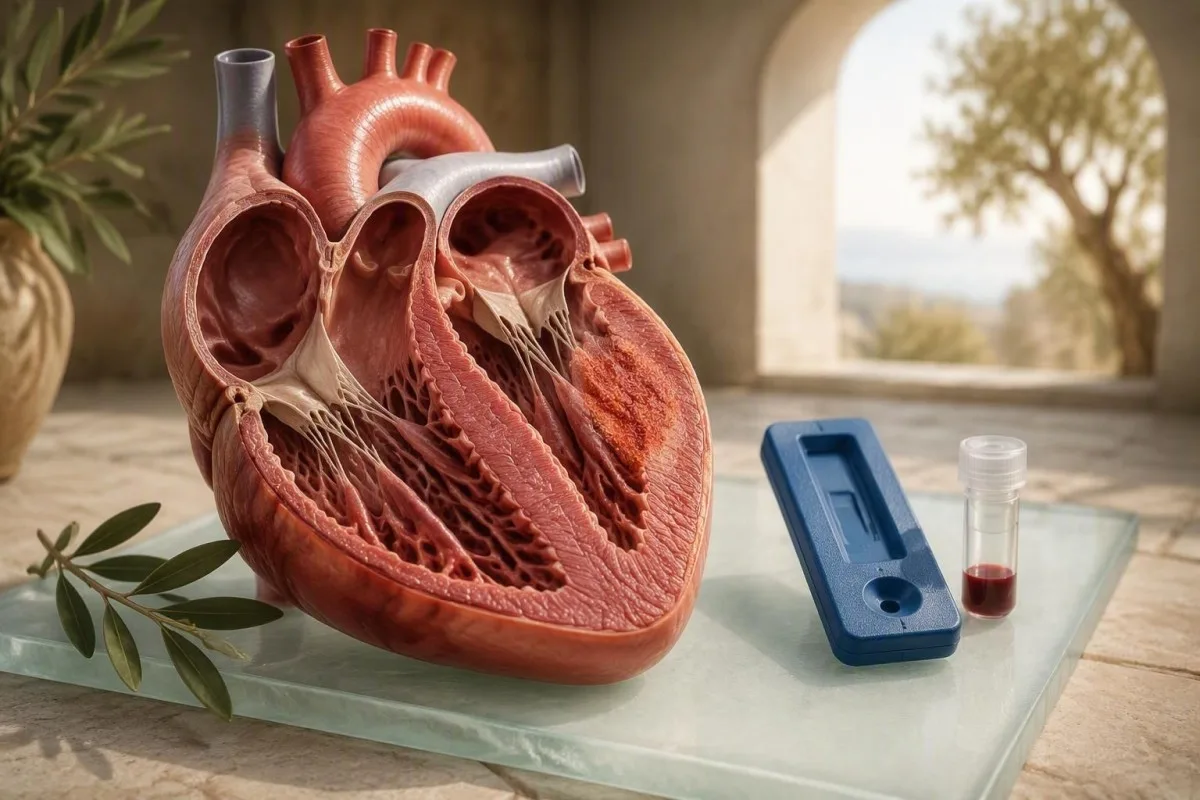
ട്രോപോണിൻ ഹൃദയപേശികൾക്ക് സംഭവിച്ച ക്ഷതം തിരിച്ചറിയാൻ സഹായിക്കുമെങ്കിലും, മയോകാർഡൈറ്റിസ് ആണ് അതിന് കാരണമെന്ന് അത് തെളിയിക്കില്ല. രക്തപരിശോധനാ ഫലങ്ങളും രോഗലക്ഷണങ്ങളും, ഇസിജി കണ്ടെത്തലുകളും, എക്കോകാർഡിയോഗ്രാഫിയും, സാധാരണയായി കാർഡിയാക് എംആർഐയും താരതമ്യം ചെയ്യുന്നതിലൂടെയാണ് രോഗനിർണയം നടത്തുന്നത്.


- ട്രോപോണിൻ ലബോറട്ടറിയുടെ 99-ാം പെർസന്റൈൽ അപ്പർ റെഫറൻസ് ലിമിറ്റിന് മുകളിലുള്ളത് മയോകാർഡിയൽ ക്ഷതത്തെ സൂചിപ്പിക്കുന്നു, മയോകാർഡൈറ്റിസിന്റെ ഒരു പ്രത്യേക രോഗനിർണയം അല്ല.
- ഹൈ-സെൻസിറ്റിവിറ്റി ട്രോപോണിൻ നേരിയ അല്ലെങ്കിൽ വൈകി വരുന്ന മയോകാർഡൈറ്റിസിൽ സാധാരണയായിരിക്കാം, അതിനാൽ സാധാരണ ഫലം പൂർണ്ണമായി തള്ളിക്കളയുന്നില്ല.
- സി.ആർ.പി. 10 mg/L ന് മുകളിലുള്ളത് സജീവമായ സിസ്റ്റമിക് വീക്കത്തെ പിന്തുണയ്ക്കുന്നു, എന്നാൽ ഹൃദയത്തിലെ വീക്കം പ്രത്യേകമായി തിരിച്ചറിയാൻ കഴിയില്ല.
- സീരിയൽ പരിശോധന പ്രധാനം: 1-3 മണിക്കൂറിനുള്ളിൽ ഉയരുന്നതോ താഴുന്നതോ ആയ ട്രോപോണിൻ പാറ്റേൺ ഒറ്റ ഫലത്തേക്കാൾ കൂടുതൽ വിവരങ്ങൾ നൽകുന്നു.
- കാർഡിയാക് MRI രോഗലക്ഷണങ്ങൾ, ഇസിജി, ട്രോപോണിൻ എന്നിവ ആശങ്ക വർദ്ധിപ്പിക്കുമ്പോൾ മയോകാർഡൈറ്റിസിന് പിന്തുണ നൽകുന്നതിനായി ഉപയോഗിക്കുന്ന പ്രധാന നോൺ-ഇൻവേസിവ് പരിശോധനയാണ്.
- കൊറോണറി രോഗം നെഞ്ചുവേദനയും ഉയർന്ന ട്രോപോണിനും ഉള്ള മുതിർന്നവരിൽ, പ്രത്യേകിച്ച് 40 വയസ്സിന് ശേഷം അല്ലെങ്കിൽ വാസ്കുലർ റിസ്ക് ഘടകങ്ങളുള്ളവരിൽ പരിഗണിക്കണം.
- അടിയന്തര വിലയിരുത്തൽ നെഞ്ചിൽ അമർച്ച, വിശ്രമിക്കുമ്പോൾ ശ്വാസംമുട്ടൽ, തലകറങ്ങൽ, നിലനിൽക്കുന്ന ഹൃദമിടിപ്പ്, അല്ലെങ്കിൽ ആശങ്കയുളവാക്കുന്ന ലക്ഷണങ്ങളോടെ ഉയർന്ന ട്രോപോണിൻ എന്നിവയ്ക്ക് ആവശ്യമാണ്.
മയോകാർഡൈറ്റിസ് രക്തപരിശോധനയ്ക്ക് ഹൃദയത്തിലെ വീക്കം കണ്ടെത്താൻ കഴിയുമോ?
മയോകാർഡൈറ്റിസ് നിർണ്ണയിക്കാനോ തള്ളിക്കളയാനോ ഒറ്റ രക്തപരിശോധനയില്ല. ട്രോപ്പോണിൻ ഹൃദയപേശികൾക്ക് സംഭവിക്കുന്ന കേടുപാടുകൾ കണ്ടെത്തുന്നു, അതേസമയം CRP, ESR എന്നിവ ശരീരത്തിൽ എവിടെയെങ്കിലും വീക്കം കണ്ടെത്തുന്നു; ഇവയൊന്നും കാരണം സ്ഥാപിക്കുന്നില്ല. ഡോ. തോമസ് ക്ലൈൻ എന്ന നിലയിൽ, രക്തപരിശോധന അന്വേഷണം ആരംഭിക്കുന്നു, എന്നാൽ കാർഡിയാക് MRI, ക്ലിനിക്കൽ ചിത്രം എന്നിവ സാധാരണയായി അത് സ്ഥിരീകരിക്കുന്നു എന്ന് ഞാൻ രോഗികളോട് പറയുന്നു.
A മയോകാർഡൈറ്റിസ് രക്തപരിശോധന ഇത് സഹായകമായ തെളിവാണ്, അന്തിമ വിധി നിയമമല്ല. മയോകാർഡൈറ്റിസ്, ഹൃദയാഘാതം, വേഗതയേറിയ താളം തെറ്റൽ, പൾമണറി എംബോളിസം, ഗുരുതരമായ ഉയർന്ന രക്തസമ്മർദ്ദം, വൃക്കരോഗം, സെപ്സിസ്, അല്ലെങ്കിൽ കഠിനമായ നീണ്ടുനിൽക്കുന്ന വ്യായാമം എന്നിവ കാരണം ട്രോപ്പോണിൻ ഉയരാം. 2013 ലെ യൂറോപ്യൻ സൊസൈറ്റി ഓഫ് കാർഡിയോളജി പൊസിഷൻ സ്റ്റേറ്റ്മെന്റ്, ഒരു ലബോറട്ടറി മൂല്യത്തിൽ നിന്ന് നിർണ്ണയിക്കുന്ന ഒരു രോഗനിർണയത്തേക്കാൾ മയോകാർഡൈറ്റിസിനെ ഒരു ക്ലിനിക്കോപാത്തോളജിക്കൽ അവസ്ഥയായി വിവരിക്കുന്നു (Caforio et al., 2013). അസ്സേ വ്യത്യാസങ്ങളെക്കുറിച്ചുള്ള ലളിതമായ ഭാഷയിലുള്ള അവലോകനത്തിനായി കാണുക ട്രോപ്പോണിൻ I, T ഫലങ്ങൾ.
എന്റെ ക്ലിനിക്കൽ അനുഭവത്തിൽ, ഏറ്റവും തെറ്റിദ്ധരിപ്പിക്കുന്ന സാഹചര്യം ഒരു വൈറൽ അസുഖത്തിന് ശേഷം കഠിനമായ നെഞ്ചുവേദന അനുഭവിക്കുന്ന ഒരു യുവ വ്യക്തിയും മിതമായ അളവിൽ ഉയർന്ന ട്രോപ്പോണിനും ആണ്. ആ പാറ്റേൺ മയോകാർഡൈറ്റിസിന് യോജിച്ചേക്കാം, എന്നാൽ അത് പെരികാർഡൈറ്റിസ്, കൊറോണറി സ്പാസം, അല്ലെങ്കിൽ കഠിനമായ വർക്ക്ഔട്ടിന് ശേഷമുള്ള അപ്രസക്തമായ ട്രോപ്പോണിൻ ഉയർച്ചയും ആകാം. മാരത്തണിന് ശേഷം hs-cTnT 38 ng/L ഉള്ള 52 വയസ്സുള്ള ഒരു ഓട്ടക്കാരന്, പനി, പുതിയ ശ്വാസംമുട്ടൽ, ഇസിജി മാറ്റങ്ങൾ എന്നിവയോടെ 38 ng/L ഉള്ള 22 വയസ്സുള്ള ഒരാളിൽ നിന്ന് വ്യത്യസ്തമായ സംഭാഷണം ആവശ്യമാണ്.
കാന്റേസ്റ്റി ഒരു AI രക്ത പരിശോധന അനലൈസർ വൃക്കകളുടെ പ്രവർത്തനം, വീക്കം സൂചകങ്ങൾ, കരൾ എൻസൈമുകൾ, മുൻ ഫലങ്ങൾ എന്നിവയോടൊപ്പം ട്രോപ്പോണിൻ വായിക്കുന്നതും ഒരു ഫ്ലാഗ് ചെയ്ത മൂല്യത്തെ രോഗനിർണയമായി കണക്കാക്കുന്നതിനേക്കാളും മികച്ചതാണ്. ഒരു ക്ലിനീഷ്യനായി പാറ്റേൺ ക്രമീകരിക്കാൻ ഞങ്ങളുടെ സിസ്റ്റത്തിന് കഴിയും, എന്നാൽ അടിയന്തര വിലയിരുത്തൽ, ഇസിജി, അല്ലെങ്കിൽ ഇമേജിംഗ് എന്നിവയ്ക്ക് പകരമാവില്ല. ഒരു പ്രായോഗിക നിയമം: നെഞ്ചിലെ ലക്ഷണങ്ങൾ നിലവിലുണ്ടെങ്കിൽ, ഓൺലൈൻ വ്യാഖ്യാനത്തിനായി കാത്തിരിക്കരുത്.
മയോകാർഡൈറ്റിസിൽ ട്രോപോണിൻ അളവ് യഥാർത്ഥത്തിൽ എന്താണ് അർത്ഥമാക്കുന്നത്?
അസ്സേ-നിർദ്ദിഷ്ട ഉയർന്ന റഫറൻസ് പരിധിക്ക് മുകളിലുള്ള ട്രോപ്പോണിൻ എന്നാൽ ഹൃദയപേശികൾക്ക് കേടുപാടുകൾ സംഭവിക്കുന്നു, പക്ഷേ അത് മയോകാർഡൈറ്റിസ് കാരണമാണെന്ന് തിരിച്ചറിയുന്നില്ല. മിക്ക ഉയർന്ന സംവേദനക്ഷമതയുള്ള അസ്സേകളും സാധാരണയായി ആരോഗ്യകരമായ റഫറൻസ് ജനസംഖ്യയുടെ 99-ാമത്തെ പെർസന്റൈൽ ഉപയോഗിക്കുന്നു, സാധാരണയായി hs-cTnT-ക്ക് ഏകദേശം 14 ng/L ഉം, നിർമ്മാതാവിനെ ആശ്രയിച്ച് hs-cTnI-ക്ക് ഏകദേശം 4-20 ng/L ഉം ആണ്.
ഒരു മൂല്യം hs-cTnT 16 ng/L ഒരു ലബോറട്ടറിയുടെ കട്ട്-ഓഫിനേക്കാൾ അല്പം കൂടുതലായിരിക്കാം, അതേസമയം hs-cTnI 1,500 ng/L വ്യക്തമായി ഉയർന്നതാണ്; ഒരു സംഖ്യ മാത്രം മയോകാർഡൈറ്റിസിന്റെ തീവ്രത അളക്കുന്നില്ല. അവരുടെ അസ്സേകൾ വ്യത്യസ്ത ആന്റിബോഡികൾ, കാലിബ്രേഷനുകൾ, റഫറൻസ് പരിധികൾ എന്നിവ ഉപയോഗിക്കുന്നതിനാൽ ലബോറട്ടറികൾക്ക് ട്രോപ്പോണിൻ I, T മൂല്യങ്ങൾ സുരക്ഷിതമായി പരസ്പരം മാറ്റാൻ കഴിയില്ല. ലബോറട്ടറി റിപ്പോർട്ടിന്റെ സ്വന്തം ഉയർന്ന റഫറൻസ് പരിധി പരിഗണിക്കേണ്ട സംഖ്യയാണ്.
പീക്ക് ചെയ്യുന്നതിനേക്കാൾ കൂടുതൽ ക്ലിനിക്കൽ വിവരങ്ങൾ പലപ്പോഴും സമയക്രമം നൽകുന്നു. ട്രോപ്പോണിൻ സാധാരണയായി അക്യൂട്ട് പരിക്ക് സംഭവിച്ച് 2-4 മണിക്കൂറിനുള്ളിൽ ഉയരാൻ തുടങ്ങുന്നു, കൂടാതെ ക്ലിനീഷ്യൻമാർ പലപ്പോഴും എമർജൻസി പാതകളിൽ 1-3 മണിക്കൂറിനു ശേഷം ഇത് ആവർത്തിക്കുന്നു. വ്യക്തമായ വർദ്ധനവോ കുറവോ ഒരു അക്യൂട്ട് പ്രക്രിയയെ പിന്തുണയ്ക്കുന്നു; വിട്ടുമാറാത്ത വൃക്കരോഗം, ഘടനാപരമായ ഹൃദ്രോഗം, അല്ലെങ്കിൽ ദീർഘകാല മയോകാർഡിയൽ സ്ട്രെയിൻ എന്നിവയിൽ സ്ഥിരമായ നേരിയ വർദ്ധനവ് സംഭവിക്കാം. നെഞ്ചുവേദന രക്തപരിശോധന ഗൈഡ് സീരിയൽ സാമ്പിളുകൾ എന്തിനാണ് ഉപയോഗിക്കുന്നതെന്ന് വിശദീകരിക്കുന്നു.
സാധാരണ ട്രോപ്പോണിൻ മയോകാർഡൈറ്റിസിനെ വിശ്വസനീയമായി ഒഴിവാക്കുന്നില്ല. ടിഷ്യൂ പ്രതികരണത്തിന്റെ ചെറിയ കേന്ദ്രീകൃത ഭാഗങ്ങൾ, പീക്കിന് ശേഷമുള്ള കാലതാമസം, കുറഞ്ഞ സംവേദനക്ഷമതയുള്ള അസ്സേകൾ എന്നിവ സാധാരണ ഫലം നൽകാം. തിരിച്ചും, വളരെ ഉയർന്ന മൂല്യങ്ങൾ സ്വയം തിരിച്ചെടുക്കാനാവാത്ത നാശത്തെ അർത്ഥമാക്കുന്നില്ല - അക്യൂട്ട് മയോകാർഡൈറ്റിസ് ഉള്ള ചില രോഗികൾക്ക് ശ്രദ്ധേയമായ വർദ്ധനവ് ഉണ്ട്, എന്നിട്ടും സാധാരണ പമ്പിംഗ് പ്രവർത്തനം വീണ്ടെടുക്കുന്നു.
മയോകാർഡൈറ്റിസിലും മറ്റ് അവസ്ഥകളിലും ട്രോപോണിൻ ഉയരാനുള്ള കാരണം
ട്രോപോണിൻ ഉയരുന്നത് ഹൃദയപേശികളിലെ കോശങ്ങൾക്ക് പരിക്ക് അല്ലെങ്കിൽ കഠിനമായ സെല്ലുലാർ സമ്മർദ്ദം കാരണം ഇൻട്രാസെല്ലുലാർ പ്രോട്ടീനുകൾ പുറത്തുവിടുമ്പോഴാണ്. മയോകാർഡൈറ്റിസ് ഒരു കാരണമാണ്, എന്നാൽ കൊറോണറി തടസ്സം ഹൃദയവേദനയും ട്രോപോണിൻ ഉയർന്ന് കാണപ്പെടുമ്പോൾ ക്ലിനീഷ്യൻമാർ അടിയന്തിരമായി ഒഴിവാക്കേണ്ട രോഗനിർണയമായി തുടരുന്നു.
മയോകാർഡൈറ്റിസിൽ, മയോകാർഡിയത്തിനുള്ളിലെ രോഗപ്രതിരോധ പ്രവർത്തനങ്ങൾക്ക് കോശസ്തരങ്ങളെ തകർക്കാനും പുറത്തുവിടാനും കഴിയും കാർഡിയാക് ട്രോപോണിൻ I അല്ലെങ്കിൽ T രക്തചംക്രമണത്തിലേക്ക്. ഹൃദയാഘാതത്തിൽ, കൊറോണറി ഒഴുക്ക് തടയുന്നത് വ്യത്യസ്ത സംവിധാനത്തിലൂടെ ഇതേ ലബോറട്ടറി സിഗ്നൽ ഉണ്ടാക്കുന്നു. ആ ഓവർലാപ്പ് കാരണം, 40 വയസ്സിന് മുകളിലുള്ളവരിലോ പ്രമേഹം, പുകവലി, അല്ലെങ്കിൽ ഉയർന്ന ApoB ഉള്ളവരിലോ കൊറോണറി രോഗം പരിഗണിക്കാതെ വർദ്ധിച്ച ട്രോപോണിനെ “വൈറൽ മയോകാർഡൈറ്റിസ്” എന്ന് അശ്രദ്ധമായി ലേബൽ ചെയ്യാൻ പാടില്ല.
ലക്ഷണങ്ങൾ സഹായിക്കും, പക്ഷേ അവ പൂർണ്ണമല്ല. മയോകാർഡൈറ്റിസ് നെഞ്ചിൽ വേദന, ശ്വാസം മുട്ടൽ, വ്യായാമ ശേഷി കുറയുക, ഹൃദയമിടിപ്പ് തെറ്റുക, അല്ലെങ്കിൽ ലക്ഷണങ്ങളൊന്നും ഇല്ലാതിരിക്കുക എന്നിവയ്ക്ക് കാരണമാകാം. നെഞ്ചിലെ ഭിത്തിയിൽ അമർത്തുമ്പോൾ വേദനയും സാധാരണ ഇസിജിയും ഉള്ള ഒരാൾക്ക് മയോകാർഡിയൽ പരിക്ക് സംഭവിക്കാനുള്ള സാധ്യത കുറവാണ്, എന്നിരുന്നാലും ഇത് വിദൂരമായി സ്ഥിരീകരിക്കാൻ കഴിയില്ല. വിയർപ്പ്, ഓക്കാനം, ശ്വാസം മുട്ടൽ, അല്ലെങ്കിൽ ബോധം കെടൽ എന്നിവയോടൊപ്പമുള്ള പുതിയ നെഞ്ചിലെ അസ്വസ്ഥത അടിയന്തര പരിചരണത്തിന് അർഹതയുണ്ട്.
Kantesti’s രക്തപരിശോധന ബയോമാർക്കറുകൾക്കുള്ള ഗൈഡ് ട്രോപോണിൻ ഫലം അതിൻ്റെ അസ്സേ യൂണിറ്റുകൾക്കുള്ളിലും റഫറൻസ് ഇൻ്റർവലിനുള്ളിലും സ്ഥാപിക്കുന്നു, ഇത് ഒരു സാധാരണ പിശക് ഒഴിവാക്കാൻ സഹായിക്കുന്നു: ng/L ലെ ഒരു മൂല്യം ng/mL ൽ റിപ്പോർട്ട് ചെയ്ത ഇൻ്റർനെറ്റ് കട്ട്ഓഫുമായി താരതമ്യം ചെയ്യുന്നു. ഒരു ng/mL എന്നാൽ 1,000 ng/L ന് തുല്യമാണ്; യൂണിറ്റ് ആശയക്കുഴപ്പം ഒരു ഫലം അതിനേക്കാൾ ആയിരം മടങ്ങ് ഭയങ്കരമായി കാണാൻ ഇടയാക്കും.
CRP, ESR, അല്ലെങ്കിൽ CBC എന്നിവയ്ക്ക് മയോകാർഡൈറ്റിസ് കാണിക്കാനാകുമോ?
CRP, ESR, വെളുത്ത രക്താണുക്കളുടെ എണ്ണം എന്നിവ വീക്കം സംബന്ധമായ രോഗങ്ങൾക്ക് പിന്തുണ നൽകാൻ കഴിയും, എന്നാൽ ഹൃദയത്തിൽ വീക്കം കണ്ടെത്താൻ ഇതിൽ ഒന്നിനും കഴിയില്ല. സാധാരണ രീതിയിൽ 10 mg/L ന് മുകളിലുള്ള CRP യെ ഉയർത്തിയതായി കണക്കാക്കുന്നു, എങ്കിലും ജലദോഷം, പല്ലുവേദന, ഓട്ടോ ഇമ്മ്യൂൺ വർദ്ധനവ്, അമിതവണ്ണം, അല്ലെങ്കിൽ സമീപകാല കഠിനമായ വ്യായാമം എന്നിവയിൽ നിന്ന് ഫലം ഉയരാം.
മയോകാർഡൈറ്റിസ് CRP സാധാരണമായോ, ചെറുതായി ഉയർന്നതോ, അല്ലെങ്കിൽ ഗണ്യമായി ഉയർന്നതോ ആകാം. വീക്കം ഉണ്ടാകുന്ന സിഗ്നലിംഗിന് ഏകദേശം 6-12 മണിക്കൂറിനുള്ളിൽ CRP ഉയരുന്നു, ട്രിഗർ ശരിയായി വന്നാൽ ESR നേക്കാൾ വേഗത്തിൽ കുറയുന്നു. പനിയോടും നെഞ്ചിലെ ലക്ഷണങ്ങളോടും കൂടിയ 48 mg/L CRP വീക്കം സംബന്ധമായ രോഗനിർണയത്തിന് ഊന്നൽ നൽകുന്നു, എന്നാൽ ഇത് മയോകാർഡൈറ്റിസിനെ ന്യുമോണിയ, ഇൻഫ്ലുവൻസ, അല്ലെങ്കിൽ ബാക്ടീരിയ അണുബാധ എന്നിവയിൽ നിന്ന് വേർതിരിച്ചറിയുന്നില്ല. ലക്ഷണങ്ങളുടെ പശ്ചാത്തലത്തെക്കുറിച്ച് കൂടുതൽ വായിക്കുക ഉയർന്ന hs-CRP ഫലങ്ങൾ.
ESR വളരെ സാവധാനത്തിലാണ്, അത്ര വ്യക്തവുമല്ല. 20-30 mm/ മണിക്കൂറിൽ കൂടുതലുള്ള ESR ഫൈബ്രനോജൻ, വിളർച്ച, പ്രായം, ഗർഭം, ഇമ്മ്യൂണോഗ്ലോബുലിൻ അളവുകൾ എന്നിവയുടെ സ്വാധീനം കാരണം ദിവസങ്ങൾ മുതൽ ആഴ്ചകൾ വരെ നിലനിൽക്കാം. സംശയാസ്പദമായ മയോകാർഡൈറ്റിസിനെക്കുറിച്ച് തീരുമാനമെടുക്കാൻ ഞാൻ അപൂർവ്വമായി ESR മാത്രം ഉപയോഗിക്കാറുണ്ട്; മൊത്തത്തിലുള്ള വീക്കം പാറ്റേൺ കാലക്രമേണ നിലനിൽക്കുന്നുണ്ടോ എന്ന് പരിശോധിക്കുമ്പോൾ ഇത് കൂടുതൽ ഉപയോഗപ്രദമാണ്.
ഒരു CBC ക്ക് നേരിയ ല്യൂക്കോസൈറ്റോസിസ്, ലിംഫോസൈറ്റ് മാറ്റങ്ങൾ, അല്ലെങ്കിൽ സാധാരണ കണ്ടെത്തലുകൾ എന്നിവ കാണാൻ കഴിയും. 11.0 × 10⁹/L ന് മുകളിലുള്ള വെളുത്ത രക്താണുക്കൾ അണുബാധയോ സമ്മർദ്ദമോ കൊണ്ട് ഉണ്ടാകാം, എന്നിരുന്നാലും സ്ഥിരീകരിച്ച മയോകാർഡൈറ്റിസ് കേസുകളിൽ പലതിലും സാധാരണ അളവുകളാണ് ഉള്ളത്. ഉപയോഗപ്രദമായ ക്ലിനിക്കൽ ചോദ്യം ഇതാണ്: CRPയും WBCയും തമ്മിൽ യോജിക്കുന്നില്ലേ— ഞങ്ങളുടെ WBC vs CRP ഗൈഡ്— ൽ വിശദീകരിച്ച ഒരു പാറ്റേൺ—ഒന്നുകിൽ ഏതെങ്കിലും ഹൃദയത്തെ ബാധിക്കുന്നു എന്ന് അനുമാനിക്കുന്നതിനു പകരം.
CK-MB, CK, LDH, എന്നിവയും മയോഗ്ലോബിനും ഇപ്പോഴും സഹായകമാണോ?
CK-MB, മൊത്തം CK, LDH, മൈോഗ്ലോബിൻ എന്നിവ ഹൃദയപേശികൾക്ക് കേടുപാടുകൾ സംഭവിക്കുന്നതിൽ ട്രോപോണിനേക്കാൾ കുറവ് വ്യക്തമാണ്, മയോകാർഡൈറ്റിസ് നിർണ്ണയിക്കാൻ കഴിയില്ല. കഠിനമായ വ്യായാമം അല്ലെങ്കിൽ പൊതുവായ അസ്ഥിപേശി പരിക്ക് അസാധാരണമായ ഫലത്തിന് കാരണമാകുന്നുണ്ടോ എന്ന് വ്യക്തമാക്കാൻ അവ ഇടയ്ക്കിടെ സഹായിച്ചേക്കാം.
സികെ-എംബി ഹൃദയ ടിഷ്യൂവിലും അസ്ഥിപേശികളിലും കാണപ്പെടുന്നു, അതിനാൽ കഠിനമായ വ്യായാമം, പരിക്ക്, അല്ലെങ്കിൽ പേശി വീക്കം എന്നിവയ്ക്ക് ശേഷം ഉയർന്ന ഫലം ഉണ്ടാകാം. ചില ലബോറട്ടറികൾ മൊത്തം CK യുമായി താരതമ്യപ്പെടുത്തി കണക്കാക്കുന്ന CK-MB സൂചിക റിപ്പോർട്ട് ചെയ്യുന്നു, എന്നാൽ ഉയർന്ന സംവേദനക്ഷമതയുള്ള ട്രോപോണിൻ പ്രധാനമായും അക്യൂട്ട് മയോകാർഡിയൽ പരിക്ക് വിലയിരുത്തലിന് ഇതിനെ മാറ്റിസ്ഥാപിച്ചിരിക്കുന്നു. വിശദീകരണം CK-MB എന്നാൽ എന്താണ് അതിന്റെ ശേഷിക്കുന്ന സാധ്യത ഉൾക്കൊള്ളുന്നു.
മൊത്തം ക്രിയാറ്റിൻ കൈനേസ് പ്രതിരോധ പരിശീലനം, സ്റ്റാറ്റിൻ-അസോസിയേറ്റഡ് പേശി പരിക്ക്, അപസ്മാരം, അല്ലെങ്കിൽ റാബ്ഡോമയോളിസിസ് എന്നിവയ്ക്ക് ശേഷം നാടകീയമായി വർദ്ധിക്കാൻ സാധ്യതയുണ്ട്. അപരിചിതമായ ഓട്ടം പരിശീലനത്തിന് ശേഷം 2,000 IU/L ആയ CK, ട്രോപോണിന്റെ ചെറിയ വർദ്ധനവിന് തുല്യമാകാം, കൂടാതെ ഇത് അസ്ഥി പേശികളുടെ സമ്മർദ്ദം സൂചിപ്പിക്കാം, എന്നാൽ ലക്ഷണങ്ങൾ ഉണ്ടെങ്കിൽ ഹൃദയത്തിന്റെ പരിക്ക് ഇല്ലെന്ന് ഡോക്ടർമാർ ഉറപ്പാക്കണം. 5,000 IU/L ന് മുകളിലുള്ള CK മൂല്യങ്ങൾ പേശി തകർച്ചയും വൃക്ക സമ്മർദ്ദവും സൂചിപ്പിക്കാം.
LDH, മയോഗ്ലോബിൻ എന്നിവ ടിഷ്യൂ ടേൺഓവറിനെ സൂചിപ്പിക്കുന്ന വിശാലമായ അടയാളങ്ങളാണ്. എന്റെ പ്രയോഗത്തിൽ, AST, പൊട്ടാസ്യം, ക്രിയാറ്റിൻ, മൂത്രപരിശോധന എന്നിവയും ഉൾപ്പെടുമ്പോൾ അവ ഏറ്റവും സഹായകമാകും - പ്രത്യേകിച്ച് വ്യായാമത്തിന് ശേഷം. ഒരു ഉയർന്ന ക്രിയാറ്റിൻ കൈനേസ് പാറ്റേൺ പേശി സുരക്ഷാ പ്രശ്നമായി വ്യാഖ്യാനിക്കണം, മയോകാർഡിറ്റിസിലേക്ക് നിസ്സാരമായി ബന്ധിപ്പിക്കരുത്.
സംശയിക്കുന്ന മയോകാർഡൈറ്റിസിൽ BNP, NT-proBNP എന്നിവ എന്താണ് കൂട്ടിച്ചേർക്കുന്നത്
BNP, NT-proBNP എന്നിവ ഹൃദയത്തിന്റെ മതിൽ സമ്മർദ്ദവും ഹൃദയസ്തംഭനവും സൂചിപ്പിക്കുന്നു; അവ വീക്കം അല്ലെങ്കിൽ മയോകാർഡിറ്റിസ് തെളിയിക്കുന്നില്ല. സ്ഥിരതയുള്ള ഔട്ട്പേഷ്യന്റ് മുതിർന്നവരിൽ വിട്ടുമാറാത്ത ഹൃദയസ്തംഭനം കുറയ്ക്കാൻ 125 ng/L ൽ താഴെയുള്ള NT-proBNP സാധാരണയായി ഉപയോഗിക്കുന്നു, അതേസമയം അക്യൂട്ട് കെയർ പരിധികൾ ഉയർന്നതും പ്രായത്തിനനുസരിച്ചുള്ളതുമാണ്.
മയോകാർഡിറ്റിസ് ഹൃദയത്തിന്റെ പമ്പിംഗ് അല്ലെങ്കിൽ വിശ്രമ പ്രവർത്തനത്തെ തടസ്സപ്പെടുത്താം, ഇത് ഉണ്ടാകാൻ കാരണമാകും BNP അല്ലെങ്കിൽ NT-proBNP ഹൃദയ അറകൾ വികസിക്കുമ്പോൾ വർദ്ധിക്കുന്നു. ശ്വാസംമുട്ടൽ, കണങ്കാലിലെ വീക്കം, വേഗതയേറിയ ഹൃദയമിടിപ്പ്, അസാധാരണമായ എക്കോകാർഡിയോഗ്രാം എന്നിവയോടൊപ്പം വർദ്ധിച്ച NT-proBNP, ഒറ്റപ്പെട്ട മൂല്യത്തേക്കാൾ കൂടുതൽ ആശങ്കയുളവാക്കുന്നു. വൃക്ക തകരാർ, ഏട്രിയൽ ഫൈബ്രിലേഷൻ, പ്രായം, പൾമോണറി എംബോളിസം എന്നിവയും NT-proBNP വർദ്ധിപ്പിക്കാം.
താഴ്ന്ന നാട്രിയൂറിറ്റിക് പെപ്റ്റൈഡ് ആശ്വാസകരമാണ്, പക്ഷേ പൂർണ്ണമല്ല. വളരെ നേരത്തെയുള്ള മയോകാർഡിറ്റിസ്, ഫോക്കൽ വീക്കം, അമിതവണ്ണം, സംരക്ഷിക്കപ്പെട്ട ഹൃദയ പ്രവർത്തനം എന്നിവയെല്ലാം സാധാരണ മൂല്യം നൽകാം. സംഖ്യാ പരിധി ക്രമീകരണവുമായി പൊരുത്തപ്പെടണം: എമർജൻസി ഡിപ്പാർട്ട്മെന്റിൽ അക്യൂട്ട് ശ്വാസംമുട്ടലുള്ള ഒരാളെ തള്ളിക്കളയാൻ ഔട്ട്പേഷ്യന്റ് സ്ക്രീനിംഗ് പരിധി ഉപയോഗിക്കരുത്.
Kantesti AI ഒരു AI ബയോമാർക്കർ വ്യാഖ്യാന പ്ലാറ്റ്ഫോം വ്യത്യസ്ത പരിശോധനകളിൽ NT-proBNP, ക്രിയാറ്റിൻ, സോഡിയം, ട്രോപോണിൻ എന്നിവ എങ്ങനെ ഒരുമിച്ച് മാറുന്നു എന്ന് കാണാൻ കഴിയും. ആ ലോഗിറ്റ്യൂഡിനൽ കാഴ്ച ഉപയോഗപ്രദമാണ്, കാരണം ദിവസങ്ങളായി NT-proBNP കുറയുന്നത് മെച്ചപ്പെട്ട ഹീമോഡൈനാമിക്സ് പ്രതിഫലിപ്പിക്കാം, അതേസമയം വർദ്ധിച്ചു വരുന്ന പ്രവണത അടിയന്തര ക്ലിനിക്കൽ അവലോകനം ആവശ്യമാക്കുന്നു. കാണുക NT-proBNP കട്ട്ഓഫുകളും ലക്ഷണങ്ങളും ഫലത്തിനനുസരിച്ചുള്ള സന്ദർഭത്തിനായി.
വൃക്ക, കരൾ, ഇലക്ട്രോലൈറ്റ് ഫലങ്ങൾ എങ്ങനെയാണ് അളവുകളെ മാറ്റുന്നത്
ക്രിയാറ്റിൻ, eGFR, പൊട്ടാസ്യം, AST, ALT, സോഡിയം എന്നിവ ഒരു വർദ്ധിപ്പിച്ച ട്രോപോണിൻ എങ്ങനെ വ്യാഖ്യാനിക്കണം എന്ന് മാറ്റാൻ കഴിയും. വൃക്കരോഗം കാരണം നിലവിൽ കുറഞ്ഞ അളവിലുള്ള ട്രോപോണിൻ ഉയർച്ച ഉണ്ടാകാം, അതേസമയം പൊട്ടാസ്യം അസാധാരണതകൾ മയോകാർഡിറ്റിസിനെ അനുകരിക്കുന്ന അല്ലെങ്കിൽ സങ്കീർണ്ണമാക്കുന്ന താളത്തകരാറുകൾക്ക് കാരണമാകും.
60 mL/min/1.73 m² ൽ താഴെയുള്ള eGFR, പ്രത്യേകിച്ച് ട്രോപോണിൻ T യ്ക്ക്, ഇടയ്ക്കിടെയുള്ള ബേസ്ലൈൻ hs-troponin എലിവേഷനുമായി ബന്ധപ്പെട്ടിരിക്കുന്നു. ഇതിനർത്ഥം ഫലം അവഗണിക്കണം എന്നല്ല; ഡോക്ടർമാർ കൂടുതൽ ശ്രദ്ധയോടെ പരിശോധിക്കുന്നത് ഡെൽറ്റ, ലക്ഷണങ്ങൾ, ECG, കൂടാതെ മുൻ ബേസ്ലൈൻ എന്നിവയാണ്. വൃക്കകളുടെ പ്രവർത്തനം കുറഞ്ഞാലും ഒരു ഡൈനാമിക് വർദ്ധനവ് ക്ലിനിക്കലി അർത്ഥവത്താണ്.
3.0 mmol/L ൽ താഴെയുള്ള അല്ലെങ്കിൽ 6.0 mmol/L ൽ കൂടുതലുള്ള പൊട്ടാസ്യം അരിത്മിയയുടെ അപകടസാധ്യത വർദ്ധിപ്പിക്കുകയും, പ്രത്യേകിച്ച് വിറയൽ അല്ലെങ്കിൽ ബലഹീനത എന്നിവയുണ്ടെങ്കിൽ അടിയന്തര വൈദ്യസഹായം ആവശ്യമാവുകയും ചെയ്യും. 20 mmol/L ൽ താഴെയുള്ള സോഡിയം, ശ്വാസംമുട്ടലുള്ള വ്യക്തിയിൽ, ഗണ്യമായ ദ്രാവക അസന്തുലിതാവസ്ഥയോ ഹൃദയസ്തംഭനമോ സൂചിപ്പിക്കാം, എന്നിരുന്നാലും നിരവധി നോൺ-കാർഡിയാക് രോഗങ്ങൾ ഇതിന് കാരണമാകാം. ബേസിക് മെറ്റബോളിക് പാനൽ ഗൈഡ് ഈ പരിശോധനകൾ ലളിതമായ ഭാഷയിൽ വിശദീകരിക്കുന്നു.
AST ഹൃദയത്തിന്റെയോ അസ്ഥി പേശിയുടെയോ പരിക്കോടുകൂടി ഉയരാം, അതേസമയം ALT കൂടുതൽ കരൾ-നിർദ്ദിഷ്ടമാണ്. ഒരു ഓട്ടത്തിനു ശേഷം AST യുടെ അനുപാതമില്ലാത്ത വർദ്ധനവ് പേശികളുമായി ബന്ധപ്പെട്ടതാകാം; മഞ്ഞപ്പിത്തം, ബിലിറുബിൻ മാറ്റങ്ങൾ, അല്ലെങ്കിൽ മരുന്ന് സംബന്ധമായ പ്രശ്നങ്ങൾ എന്നിവയോടുകൂടിയ AST, ALT എലിവേഷനുകൾക്ക് കൂടുതൽ വിപുലമായ കരൾ പരിശോധന ആവശ്യമാണ്. സന്ദർഭം ഇവിടെ വളരെ പ്രധാനമാണ്—ഒറ്റപ്പെട്ട ഒരു എൻസൈം ഒരിക്കലും പൂർണ്ണമായ കഥ പറയില്ല.
വൈറൽ ആന്റിബോഡികൾ അല്ലെങ്കിൽ ഓട്ടോഇമ്മ്യൂൺ രക്തപരിശോധനകൾ ഓർഡർ ചെയ്യേണ്ടതുണ്ടോ?
സാധാരണ വൈറൽ ആൻ്റിബോഡി പാനലുകൾ മയോകാർഡിറ്റിസിന്റെ കാരണം അപൂർവ്വമായി സ്ഥിരീകരിക്കുന്നു, കൂടാതെ പോസിറ്റീവ് ആൻ്റിബോഡികൾ സജീവമായ ഹൃദയ അണുബാധയേക്കാൾ പഴയ എക്സ്പോഷർ കാണിക്കുന്നു. ശരീരത്തിലെ വീക്കം സംബന്ധമായ രോഗങ്ങളെ സൂചിപ്പിക്കുന്ന ചരിത്രം, പരിശോധന, അല്ലെങ്കിൽ മറ്റ് അവയവങ്ങൾ എന്നിവ പരിഗണിച്ച് സ്വയം രോഗപ്രതിരോധ പരിശോധനകൾ ലക്ഷ്യമിടുന്നു.
Most adults have antibodies to common viruses such as Epstein-Barr virus, cytomegalovirus, and coxsackievirus. A positive IgG usually reflects previous exposure; it does not prove that a virus is affecting the heart now. Even IgM can be falsely positive or persist longer than expected. The EBV antibody pattern guide shows why antibody timing is tricky.
Clinicians may order ANA, ENA antibodies, ANCA, rheumatoid factor, complement levels, thyroid testing, or eosinophil counts when there are clues such as rash, joint swelling, asthma, sinus disease, kidney changes, recurrent inflammation, or drug exposure. Eosinophilic myocarditis is uncommon but clinically important because it may need urgent specialist-directed treatment.
Cardiac MRI and, in selected unstable or treatment-changing cases, endomyocardial tissue examination are better tools for characterising myocardial involvement than broad viral serology. The evidence is honestly mixed on exactly which ancillary tests every patient needs; the work-up should follow the phenotype, not a fixed shopping list.
മയോകാർഡൈറ്റിസ് സ്ഥിരീകരിക്കാനോ ശക്തമായി പിന്തുണയ്ക്കാനോ കഴിയുന്ന പരിശോധനകൾ ഏവയാണ്?
Cardiac MRI is the leading non-invasive test for supporting myocarditis because it can show oedema and non-ischaemic tissue injury patterns. ECG, echocardiography, coronary assessment when appropriate, and sometimes endomyocardial biopsy complete the diagnostic pathway.
The updated Lake Louise cardiac MRI criteria use at least one T2-based marker of oedema and one T1-based marker of non-ischaemic injury, such as late gadolinium enhancement or abnormal T1 mapping. Ferreira and colleagues reported that combining these tissue markers improves diagnostic assessment compared with older MRI approaches (Ferreira et al., 2018). MRI is strongest when performed close to the symptomatic period, although timing depends on stability and local access.
An ECG may show ST-T changes, PR depression, conduction delay, or rhythm disturbance, but a normal ECG does not exclude myocarditis. Echocardiography evaluates ejection fraction, chamber size, valve function, and pericardial fluid; it can be entirely normal in mild focal disease. A reduced left-ventricular ejection fraction below 50% changes urgency and follow-up planning.
Endomyocardial biopsy is not routine for everyone. It becomes more relevant with cardiogenic shock, rapidly worsening heart failure, high-grade heart block, sustained ventricular arrhythmia, or suspicion of a subtype that would alter treatment. This distinction matters: blood tests can raise suspicion, but only carefully selected tissue analysis can directly identify myocardial inflammatory cell patterns.
മയോകാർഡൈറ്റിസ് രക്തപരിശോധനകൾ എപ്പോൾ ആവർത്തിക്കണം?
Repeat troponin timing depends on symptoms and setting: emergency pathways commonly repeat high-sensitivity troponin after 1-3 hours, while outpatient follow-up may occur over days or weeks. Repeating a test without a clinical plan can create noise rather than clarity.
For acute chest symptoms, clinicians commonly use an immediate sample and a second sample at 1 or 2 hours, depending on the local validated algorithm. The absolute change in ng/L matters more than a percentage change when starting values are low. Do not use a home-timed repeat test to manage active chest pain—emergency teams need the ECG and vital signs at the same time.
After confirmed or probable myocarditis, troponin may normalise within days to weeks, but recovery is uneven. CRP often improves earlier than MRI abnormalities, and symptoms can improve before electrical irritability has fully settled. I advise patients to record the date, symptoms, exercise level, medications, and illness around each blood draw; our ലാബ് ടൈംലൈൻ ഗൈഡ് explains why those details matter.
Dr. Thomas Klein’s practical rule is that a repeat result should answer a specific question: “Is injury continuing?”, “Is this baseline elevation?”, or “Is recovery on track?” A troponin test repeated after heavy exercise, dehydration, or a different assay method may be difficult to compare. Ideally, follow-up uses the same laboratory and assay.
മയോകാർഡൈറ്റിസ് കൂടാതെ വ്യായാമം ട്രോപോണിൻ ഉയർത്താൻ കാരണമാകുമോ?
Yes, prolonged strenuous exercise can cause a temporary troponin rise without clinical myocarditis, particularly after marathons, ultradistance events, or intense cycling. Symptoms, ECG changes, recovery kinetics, and imaging determine whether the elevation is benign exertional release or true myocardial injury.
Post-exercise troponin elevations often peak within 2-6 hours and fall toward baseline within 24-48 hours, whereas sustained or rising values are more concerning. The overlap is not perfect, so symptoms matter enormously. Chest pain, collapse, unusual shortness of breath, or persistent palpitations after exercise should never be dismissed as “just training.”
During suspected myocarditis, vigorous exercise is usually restricted because inflamed myocardium may be more vulnerable to dangerous arrhythmias. Many sports-cardiology protocols reassess athletes after 3-6 മാസം with symptoms, biomarkers, ECG monitoring, ventricular function, and sometimes MRI guiding return. The exact timeline varies with severity and residual findings.
A high CK after exercise can muddy the picture, especially when AST rises too. Our എൻഡ്യൂറൻസ് കായികതാരങ്ങൾക്കുള്ള രക്തപരിശോധന മാർഗ്ഗദർശി helps distinguish training-related lab shifts from patterns that need medical review. Rest is not merely cautious advice here—it is part of risk reduction while the diagnosis is unresolved.
ഉയർന്ന ട്രോപോണിൻ അടിയന്തര പരിചരണം ആവശ്യമുള്ളപ്പോൾ
A raised troponin with active chest pressure, breathlessness at rest, fainting, confusion, sustained palpitations, or new weakness needs emergency assessment now. The result may reflect myocarditis, heart attack, pulmonary embolism, severe arrhythmia, or another condition that cannot be safely sorted out online.
Call emergency services rather than driving yourself if chest symptoms are severe, persistent beyond 10-15 minutes, accompanied by collapse, or associated with blue lips, severe breathlessness, or a racing irregular heartbeat. Troponin is not a measure of pain intensity; a person can have a dangerous condition with a modest elevation or little pain.
There are quieter warning patterns too: resting heart rate persistently above 120 beats per minute, new inability to climb one flight of stairs, swelling, reduced urine output, or palpitations with dizziness. A recent viral illness does not make a cardiac cause less urgent. In fact, it can increase suspicion for myocarditis while coronary and pulmonary causes still require consideration.
If you have a result but no current emergency symptoms, contact the clinician who ordered it the same day when possible. The high troponin urgent-care guide lists common non-heart-attack causes, but it should not be used to self-triage dangerous symptoms.
മയോകാർഡൈറ്റിസ് രക്തപരിശോധന ഫലങ്ങൾ അമിതമായി വ്യാഖ്യാനിക്കാതെ എങ്ങനെ വായിക്കാം
The safest way to read blood tests for heart inflammation is to look for a pattern: troponin trajectory, CRP, kidney function, electrolytes, symptoms, timing, and prior values. A single red flag on a report is a prompt for clinical context, not a final diagnosis.
കാന്റേസ്റ്റി ഒരു AI-ശക്തിയുള്ള രക്തപരിശോധന വിശകലന ഉപകരണം designed to compare laboratory values across time and highlight combinations that deserve clinician follow-up. For suspected myocarditis, our AI does not label someone with the condition from troponin alone; it identifies myocardial-injury markers, inflammatory context, and potentially relevant kidney or electrolyte confounders. That is deliberately conservative.
Before reviewing any report, confirm four details: the test name, units, laboratory upper reference limit, and sampling date. Then note whether strenuous exercise, fever, dehydration, kidney disease, supplements, or a recent hospital visit could affect the result. The രക്ത താരതമ്യ ഉപകരണം is particularly useful when comparing values obtained by the same laboratory.
A healthy-looking CRP or normal CBC should not overrule concerning symptoms, and a flagged troponin should not be interpreted without an ECG. This is one of those areas where context matters more than the number. If you use Kantesti, treat the report as a structured conversation starter for your doctor, not clearance to continue normal activity.
അസാധാരണമായ മയോകാർഡൈറ്റിസ് രക്തപരിശോധനയ്ക്ക് ശേഷം ചോദിക്കേണ്ട ചോദ്യങ്ങൾ
After abnormal cardiac blood work, ask what the result means for you today, what dangerous alternatives have been excluded, and what test will change management next. A precise question often gets a more useful answer than asking whether the number is simply “bad.”
Useful questions include: “Which troponin assay was used?”, “What is my change between samples in ng/L?”, “Could my kidney function explain part of this?”, “Do I need ECG, echocardiography, coronary assessment, or cardiac MRI?”, and “What exercise restriction applies while we investigate?” These questions work because they focus on decisions rather than trying to force a diagnosis from a number.
Ask whether repeat testing should occur in the same laboratory and whether any medications or supplements need review. Non-steroidal anti-inflammatory drugs, stimulants, decongestants, bodybuilding products, cocaine, and some cancer therapies can be relevant in selected cases. Never stop prescribed medication without the clinician managing your care.
Kantesti’s clinical content is reviewed with physician oversight; you can read about those standards in our മെഡിക്കൽ വാലിഡേഷൻ സമീപനം. As of September 22, 2026, the most reliable approach remains unchanged: troponin identifies injury, while expert clinical assessment and cardiac imaging establish whether myocarditis is the explanation.
ഗവേഷണം, മെഡിക്കൽ അവലോകനം, ഓൺലൈൻ വ്യാഖ്യാനത്തിന്റെ പരിമിതികൾ
Online information can explain a myocarditis blood test, but it cannot assess your ECG, blood pressure, oxygen level, rhythm, or cardiac imaging. Those missing data are exactly why troponin should be interpreted as a clinical signal rather than a standalone diagnosis.
The core evidence base is clear on one point: myocardial injury and myocarditis are not synonyms. Caforio et al. (2013) emphasised the need for integrated clinical assessment, while Ferreira et al. (2018) established modern MRI tissue-characterisation criteria that improve non-invasive diagnosis. Neither paper supports diagnosing myocarditis from CRP, CK-MB, or troponin alone.
For related laboratory context, our research library includes the സീറം പ്രോട്ടീനുകളുടെ റഫറൻസ് ഗൈഡ് ഒപ്പം കോംപ്ലിമെന്റ് һәм ANA മാർഗ്ഗനിർദ്ദേശം. These tests may be relevant when clinicians suspect systemic immune disease, but they are not screening tests for every person with chest pain or an elevated troponin.
At Kantesti, we aim to make laboratory language less opaque while retaining the uncertainty that safe medicine requires. Our മെഡിക്കൽ അഡ്വൈസറി ബോർഡ് helps guide clinical review standards. If your symptoms are active or worsening, seek in-person care rather than relying on any article, app, or uploaded report.
പതിവ് ചോദ്യങ്ങൾ
രക്തപരിശോധന വഴി മയോകാർഡൈറ്റിസ് നിർണ്ണയിക്കാൻ കഴിയുമോ?
Blood work cannot diagnose myocarditis by itself. Troponin above the assay-specific 99th-percentile upper reference limit shows myocardial injury, while CRP above about 10 mg/L supports systemic inflammation, but neither identifies the cause or location of inflammation. Clinicians combine symptoms, ECG, echocardiography, coronary assessment when appropriate, and cardiac MRI to support the diagnosis. Endomyocardial biopsy is reserved for selected severe or treatment-changing cases.
മയോകാർഡൈറ്റിസ് സൂചിപ്പിക്കുന്നത് എന്ത് ട്രോപോണിൻ ലെവലാണ്?
No troponin cutoff specifically indicates myocarditis because the same value can occur with heart attack, pulmonary embolism, rapid arrhythmia, kidney disease, or exercise. Many hs-cTnT assays use approximately 14 ng/L as the 99th-percentile upper reference limit, while hs-cTnI cutoffs vary widely by assay and sometimes by sex. A rise or fall over 1-3 hours is more informative than one isolated result. Chest symptoms and ECG findings determine urgency.
സാധാരണ ട്രോപോണിൻ നിലയിൽ മയോകാർഡൈറ്റിസ് വരാമോ?
Yes, myocarditis can occur with normal troponin, particularly when inflammation is mild, focal, late in its course, or tested after the biomarker peak. A normal troponin makes substantial ongoing myocardial injury less likely at that sampling time, but it does not fully rule out myocarditis. Persistent chest pain, palpitations, fainting, or breathlessness still require medical assessment. Cardiac MRI can detect tissue changes that blood tests miss.
മയോകാർഡൈറ്റിസിൽ CRP കൂടുതലാണോ?
CRP can be high in myocarditis, but it is neither sensitive nor specific for cardiac inflammation. A CRP above 10 mg/L commonly reflects active inflammation and values of 30-100 mg/L can occur in many infections or autoimmune conditions. Some people with MRI-supported myocarditis have normal CRP. CRP is most useful when considered alongside symptoms, troponin, ECG, and changes over time.
മയോകാർഡൈറ്റിസിൽ ട്രോപോണിൻ എത്രത്തോളം ഉയർന്ന നിലയിൽ തുടരും?
Troponin may remain elevated for several days and occasionally longer in myocarditis, depending on the degree and persistence of myocardial injury. High-sensitivity troponin often rises within hours of acute injury, but the exact timing differs between troponin I and T assays and between patients. A falling result usually suggests injury is settling, although it does not by itself confirm recovery of heart function. Follow-up may include ECG, echocardiography, rhythm monitoring, and cardiac MRI.
ഒരു വൈറൽ അസുഖത്തിന് ശേഷം ട്രോപോണിൻ കൂടുതലാണെങ്കിൽ ഞാൻ വ്യായാമം ചെയ്യണോ?
You should avoid strenuous exercise and seek medical advice if troponin is elevated after a viral illness, especially with chest pain, palpitations, fainting, or breathlessness. Sports-cardiology practice commonly restricts competitive or vigorous exercise for 3-6 months after confirmed myocarditis, with return guided by symptoms, biomarkers, cardiac function, and rhythm assessment. Exercise can transiently raise troponin after endurance events, but that cannot be assumed without evaluation. Active chest symptoms require urgent in-person assessment.
ഇന്ന് തന്നെ AI-ശക്തിയുള്ള രക്ത പരിശോധന വിശകലനം നേടൂ
തൽക്ഷണവും കൃത്യവുമായ ലാബ് പരിശോധന വിശകലനത്തിനായി Kantesti-നെ വിശ്വസിക്കുന്ന ലോകമെമ്പാടുമുള്ള 2 മില്യണിലധികം ഉപയോക്താക്കളിൽ ചേരൂ. നിങ്ങളുടെ രക്ത പരിശോധന ഫലങ്ങൾ അപ്ലോഡ് ചെയ്ത് സെക്കൻഡുകൾക്കുള്ളിൽ 15,000+ ബയോമാർക്കറുകളുടെ സമഗ്രമായ വ്യാഖ്യാനം നേടൂ.
📚 റഫറൻസ് ചെയ്ത ഗവേഷണ പ്രസിദ്ധീകരണങ്ങൾ
Klein, T., Mitchell, S., & Weber, H. (2026). സെറം പ്രോട്ടീൻ ഗൈഡ്: ഗ്ലോബുലിൻ, ആൽബുമിൻ & എ/ജി അനുപാത രക്തപരിശോധന. Kantesti AI മെഡിക്കൽ റിസർച്ച്.
Klein, T., Mitchell, S., & Weber, H. (2026). C3 C4 കോംപ്ലിമെന്റ് രക്ത പരിശോധന & ANA ടൈറ്റർ ഗൈഡ്. Kantesti AI മെഡിക്കൽ റിസർച്ച്.
📖 ബാഹ്യ മെഡിക്കൽ റഫറൻസുകൾ
Caforio ALP et al. (2013). Current state of knowledge on aetiology, diagnosis, management, and therapy of myocarditis: a position statement of the European Society of Cardiology Working Group on Myocardial and Pericardial Diseases.CBC മാർക്കർ ലാബ് വ്യാഖ്യാനം 2026 അപ്ഡേറ്റ് രോഗിക്ക് സൗഹൃദമായത് അല്പം അസാധാരണമായ ചുവന്ന രക്തകോശങ്ങളുടെ എണ്ണം പലപ്പോഴും കോൺടെക്സ്റ്റിനെ ആശ്രയിച്ചിരിക്കും,...
⚕️ മെഡിക്കൽ നിരാകരണം
ഈ ലേഖനം വിദ്യാഭ്യാസ ആവശ്യങ്ങൾക്കായി മാത്രമാണ്; ഇത് മെഡിക്കൽ ഉപദേശം എന്ന നിലയിൽ കണക്കാക്കരുത്. രോഗനിർണയത്തിനും ചികിത്സാ തീരുമാനങ്ങൾക്കും വേണ്ടി എപ്പോഴും യോഗ്യതയുള്ള ആരോഗ്യപരിചരണ വിദഗ്ധനെ സമീപിക്കുക.
E-E-A-T വിശ്വാസ സൂചനകൾ
അനുഭവം
ലാബ് ഫലം വ്യാഖ്യാനിക്കുന്ന പ്രവാഹങ്ങളുടെ വൈദ്യനേതൃത്വത്തിലുള്ള ക്ലിനിക്കൽ അവലോകനം.
വൈദഗ്ദ്ധ്യം
ക്ലിനിക്കൽ സാഹചര്യത്തിൽ ബയോമാർക്കറുകൾ എങ്ങനെ പെരുമാറുന്നു എന്നതിൽ ലബോറട്ടറി മെഡിസിൻ കേന്ദ്രീകരിക്കുന്നു.
ആധികാരികത
ഡോ. തോമസ് ക്ലൈൻ എഴുതിയത്; ഡോ. സാറ മിച്ചൽയും പ്രൊഫ്. ഡോ. ഹാൻസ് വെബറും.
വിശ്വാസ്യത
അലാറം കുറയ്ക്കാൻ വ്യക്തമായ തുടർനടപടി മാർഗങ്ങളോടെയുള്ള തെളിവാധിഷ്ഠിത വ്യാഖ്യാനം.