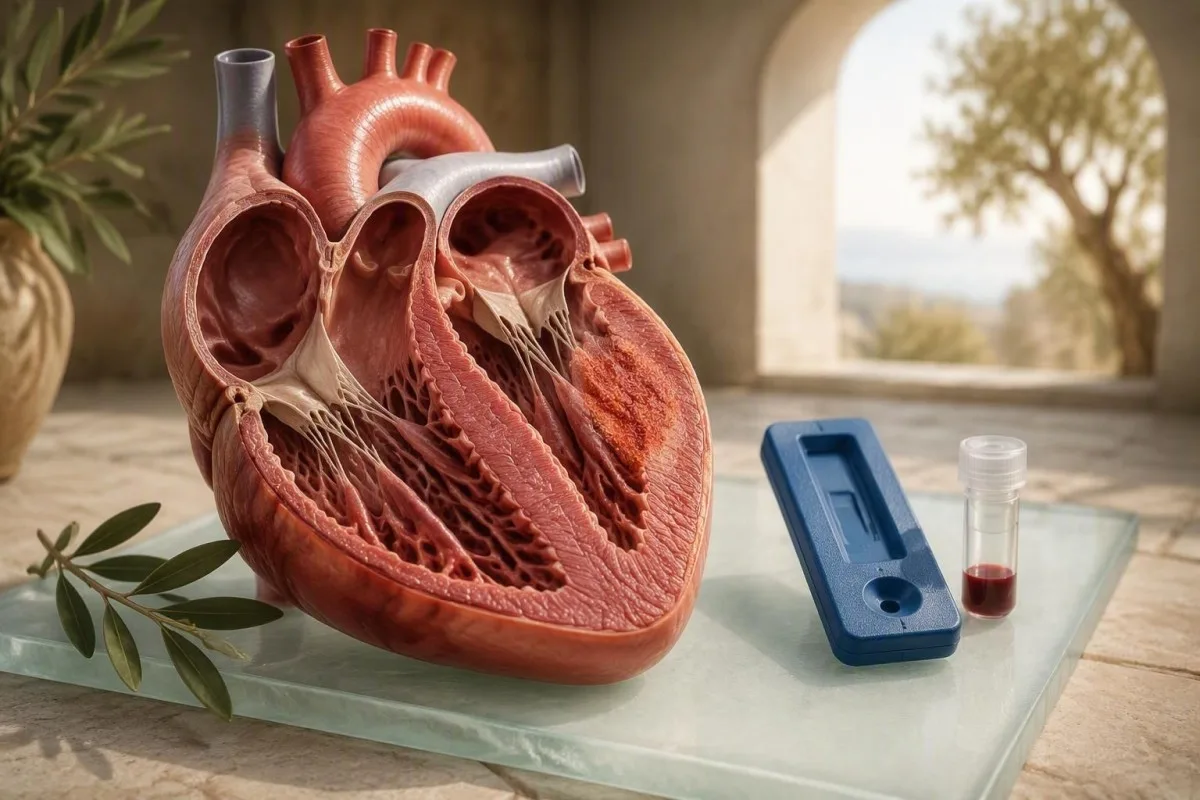
Trópónín getur greint hjartavöðvaskaða, en það getur ekki sannað að hjartavöðvabólga sé orsökin. Greiningin felst í því að passa saman blóðúrslit við einkenni, hjartalínuritum, hjartaómskoðun og venjulega hjartavöðvasvörun.


- Trópónín yfir 99. hundraðshluta efri viðmiðunarmörkum rannsóknarstofunnar gefur til kynna skaða á hjartavöðva, ekki sérstaka greiningu á hjartavöðvabólgu.
- Há-næmni troponin getur verið eðlilegt við væga eða seint fram komna hjartavöðvabólgu, svo eðlilegur niðurstaða útilokar ekki að fullu.
- CRP yfir 10 mg/L styður virka kerfisbundna bólgu en getur ekki sérstaklega greint bólgu í hjarta.
- Raðmælingar skiptir máli: stigandi eða lækkandi trópónínmynstur yfir 1-3 klukkustundir er upplýsandi en ein einangruð niðurstaða.
- Hjartavöðvaskönnun er aðal óífarandi prófið sem notað er til að styðja hjartavöðvabólgu þegar einkenni, hjartalínurit og trópónín vekja áhyggjur.
- Kransæðasjúkdómur verður að hafa í huga hjá fullorðnum með brjóstverk og hækkað trópónín, sérstaklega eftir 40 ára aldur eða með æðasjúkdómaáhættuþætti.
- Bráð mat er nauðsynlegt við þrýstingi í brjósti, andnauð í hvíld, yfirlið, viðvarandi hjartsláttarónot eða hækkað trópónín með áhyggjuefnum einkennum.
Getur blóðpróf fyrir hjartavöðvabólgu greint hjartabólgu?
Ekkert eitt blóðpróf fyrir hjartavöðvabólgu getur greint eða útilokað hjartavöðvabólgu. Trópónín greinir skaða á hjartavöðva, en CRP og ESR greina bólgu einhvers staðar í líkamanum; hvorugt ákvarðar orsökina. Sem dr. Thomas Klein, segi ég sjúklingum að blóðrannsóknir hefji rannsóknina, en hjarta-segulómun og klínísk mynd ráða oft úrslitum.
A blóðpróf fyrir hjartavöðvabólgu er styðjandi vísbending, ekki dómur. Trópónín getur hækkað vegna hjartavöðvabólgu, hjartaáfalls, hraðra hjartsláttartruflana, lungnasegarekis, alvarlegs háþrýstings, nýrnasjúkdóms, blóðsýkingar eða mikillar þrekþjálfunar. Evrópska hjartalæknafélagsins ályktun frá 2013 lýsir hjartavöðvabólgu sem klínísk-lífeðlisfræðilegu ástandi frekar en greiningu úr einni rannsóknarniðurstöðu (Caforio o.fl., 2013). Fyrir einfalda úttekt á munum milli mælinga, sjá niðurstöður trópóníns I og T.
Í klínískri reynslu minni er villandi aðstæður þegar ungur fullorðinn einstaklingur finnur fyrir miklum brjóstverkjum eftir veirusjúkdóm og hefur hóflega hækkað trópónín. Það mynstur getur passað við hjartavöðvabólgu, en það getur líka verið hjartahimnubólga, kransæðaspasmi eða óskyld hækkuð trópónín eftir erfiða líkamsrækt. 52 ára hlaupari með hs-cTnT 38 ng/L eftir maraþon þarf að ræða við annan hátt en 22 ára gamall með 38 ng/L, hita, nýja mæði og hjartalínuritsbreytingar.
Kantesti er AI blóðprufugreiningartæki sem les trópónín ásamt nýrnastarfsemi, bólguþáttum, lifrarensímum og fyrri niðurstöðum frekar en að meðhöndla eina merkt gildi sem greiningu. Kerfið okkar getur hjálpað til við að skipuleggja mynstur fyrir lækni, en það getur ekki komið í stað bráðrar mats, hjartalínurits eða myndgreiningar. Hagnýt regla: ef brjóstverkur er til staðar, ekki bíða eftir nettúlkun.
Hvað þýða trópónínmagn í hjartavöðvabólgu í raun og veru?
Trópónín yfir mörkum mælingarinnar þýðir skaða á hjartavöðva, en það greinir ekki hjartavöðvabólgu sem orsök. Flestar mjög næmar mælingar nota 99. hundraðshluta heilbrigðra samanburðarhópa, oft um 14 ng/L fyrir hs-cTnT og gróflega 4-20 ng/L fyrir hs-cTnI eftir framleiðanda.
Gildi hs-cTnT 16 ng/L getur verið aðeins örlítið yfir mörkum eins rannsóknarstofu, en hs-cTnI 1.500 ng/L er greinilega hátt; hvorug tala ein og sér mælir alvarleika hjartavöðvabólgu. Rannsóknarstofur geta ekki á öruggan hátt skipt á milli trópóníns I og T vegna þess að mælingar þeirra nota mismunandi mótefni, kvarðun og viðmiðunarmörk. Mörk rannsóknarstofunnar sjálfrar eru það gildi sem skiptir máli.
Tímaferillinn ber oft meiri klínískan upplýsingagildi en hámarksgildi. Trópónín byrjar venjulega að hækka 2-4 klukkustundum eftir bráðan skaða, og læknar endurtaka það oft eftir 1-3 klukkustundir í bráðum aðgerðum. Skýr hækkun eða lækkun styður bráða ferli; stöðug væg hækkun getur komið fram við langvarandi nýrnasjúkdóm, hjartasjúkdóm eða langvarandi hjartastreitu. leiðbeiningar um blóðpróf fyrir brjóstverk útskýrir hvers vegna röð sýna eru notuð.
Eðlilegt trópónín útilokar ekki áreiðanlega hjartavöðvabólgu. Lítil staðbundin bólguviðbrögð, seint próf eftir hámarksgildi og minna næmar mælingar geta allt gefið eðlilega niðurstöðu. Aftur á móti þýða mjög há gildi ekki sjálfkrafa varanlegan skaða - sumir sjúklingar með bráða hjartavöðvabólgu hafa sláandi hækkun en ná eðlilegri dæluvirkni.
Af hverju hækkar trópónín við hjartavöðvabólgu og önnur skilyrði
Troponin rises when cardiac muscle cells release intracellular proteins after injury or intense cellular stress. Myocarditis is one cause, but coronary blockage remains the diagnosis clinicians must urgently exclude when chest pain and raised troponin occur together.
In myocarditis, immune activity within the myocardium can disrupt cell membranes and release cardiac troponin I or T into circulation. In a heart attack, blocked coronary flow causes the same laboratory signal through a different mechanism. That overlap is why an elevated troponin should never be casually labelled “viral myocarditis” without considering coronary disease, particularly in people over 40 or those with diabetes, smoking exposure, or high ApoB.
Symptoms help but are imperfect. Myocarditis may cause central chest ache, breathlessness, reduced exercise capacity, skipped beats, or no symptoms at all. A person with reproducible pain when pressing the chest wall and a normal ECG is less likely to have myocardial injury, yet this cannot be confirmed remotely. New chest discomfort plus sweating, nausea, breathlessness, or fainting warrants emergency care.
Kantesti’s blóðrannsóknarvísar places a troponin result within its assay units and reference interval, which helps avoid a common error: comparing a value in ng/L with an internet cutoff reported in ng/mL. One ng/mL equals 1,000 ng/L; unit confusion can make a result look a thousand-fold more alarming than it is.
Getur CRP, ESR eða CBC sýnt hjartavöðvabólgu?
CRP, ESR, and white-cell counts can support an inflammatory illness, but none can locate inflammation in the heart. A CRP above 10 mg/L is often considered elevated in routine practice, although the result can rise from a cold, dental infection, autoimmune flare, obesity, or recent intense exercise.
Myocarditis CRP may be normal, mildly raised, or substantially elevated. CRP rises within about 6-12 hours after inflammatory signalling and usually falls faster than ESR when the trigger settles. A CRP of 48 mg/L with fever and chest symptoms adds weight to an inflammatory diagnosis, but it does not distinguish myocarditis from pneumonia, influenza, or bacterial infection. Read more about symptom context in high hs-CRP results.
ESR is slower and less specific. An ESR above 20-30 mm/hour may persist for days to weeks because it is influenced by fibrinogen, anaemia, age, pregnancy, and immunoglobulin levels. I rarely use ESR alone to make a decision about suspected myocarditis; it is more useful when checking whether a broad inflammatory pattern has persisted across time.
A CBC can show mild leukocytosis, lymphocyte changes, or normal findings. White cells above 11.0 × 10⁹/L can accompany infection or stress, yet many confirmed myocarditis cases have normal counts. The useful clinical question is whether CRP and WBC disagree—a pattern explored in our WBC versus CRP guide—rather than assuming either confirms cardiac involvement.
Hjálpa CK-MB, CK, LDH og myóglóbín ennþá?
CK-MB, total CK, LDH, and myoglobin are less specific than troponin for heart-muscle injury and cannot diagnose myocarditis. They can occasionally clarify whether strenuous exercise or generalized skeletal-muscle injury is contributing to an abnormal result.
CK-MB is found in cardiac tissue but also in skeletal muscle, so a raised result can occur after vigorous exercise, trauma, or muscle inflammation. Some laboratories report a CK-MB index, calculated relative to total CK, but high-sensitivity troponin has largely replaced it for acute myocardial injury assessment. Our explanation of what CK-MB means covers its remaining niche.
Heildar kreatínkínasi can rise dramatically after resistance training, statin-associated muscle injury, seizures, or rhabdomyolysis. A CK of 2,000 IU/L after an unfamiliar endurance event can coexist with a small troponin rise and may point toward skeletal-muscle stress, but clinicians still need to rule out cardiac injury if symptoms are present. CK values above 5,000 IU/L raise concern for significant muscle breakdown and kidney stress.
LDH and myoglobin are even broader markers of tissue turnover. In my practice, they are most helpful when the panel also includes AST, potassium, creatinine, and urine findings—especially after exertion. A high creatine kinase pattern should be interpreted as a muscle-safety issue, not casually attributed to myocarditis.
Hvað bæta BNP og NT-proBNP við grun um hjartavöðvabólgu
BNP and NT-proBNP indicate cardiac wall stress and possible heart failure; they do not prove inflammation or myocarditis. NT-proBNP below 125 ng/L is often used in stable outpatient adults to make chronic heart failure less likely, while acute-care thresholds are higher and age-dependent.
Myocarditis can impair the heart’s pumping or relaxation function, causing BNP eða NT-proBNP to rise as cardiac chambers stretch. A raised NT-proBNP alongside breathlessness, ankle swelling, a fast heart rate, and an abnormal echocardiogram is more concerning than the same value in isolation. Kidney impairment, atrial fibrillation, older age, and pulmonary embolism can also raise NT-proBNP.
A low natriuretic peptide is reassuring but not absolute. Very early myocarditis, focal inflammation, obesity, and preserved heart function can all yield a normal value. The numerical cutoff must match the setting: an outpatient screening threshold should not be used to dismiss someone with acute breathlessness in an emergency department.
Kantesti AI er AI lífmerkjatúlkunarvettvangur that can show how NT-proBNP, creatinine, sodium, and troponin move together across separate draws. That longitudinal view is useful because a falling NT-proBNP over days may reflect improving haemodynamics, whereas a rising trend merits prompt clinical review. See NT-proBNP cutoffs and symptoms fyrir samhengi sem tengist niðurstöðu.
Hvers vegna nýra-, lifur- og raflausnauppgjör breyta lestrinum
Creatinine, eGFR, potassium, AST, ALT, and sodium can change how clinicians interpret a raised troponin. Kidney disease can produce chronic low-level troponin elevation, while potassium abnormalities can trigger rhythm problems that mimic or complicate myocarditis.
An eGFR below 60 mL/min/1.73 m² is associated with more frequent baseline hs-troponin elevation, especially for troponin T. This does not mean the result should be ignored; clinicians look harder at the delta, symptoms, ECG, and prior baseline. A dynamic increase remains clinically meaningful even when kidney function is reduced.
Potassium below 3.0 mmol/L or above 6.0 mmol/L can increase arrhythmia risk and needs prompt medical attention, especially with palpitations or weakness. Sodium below 130 mmol/L in a person with breathlessness may signal significant fluid imbalance or heart failure, though many non-cardiac illnesses can cause it. The leiðarvísinn um grunnlífefnapróf í blóði explains these tests in plain language.
AST can rise with cardiac or skeletal-muscle injury, whereas ALT is more liver-specific. A disproportionate AST rise after a race may be muscular; AST and ALT elevations with jaundice, bilirubin changes, or medication exposure need a broader liver work-up. Context is everything here—one isolated enzyme almost never tells the whole story.
Ætti að panta veiruveirur eða sjálfónæmisblóðrannsóknir?
Routine viral antibody panels rarely confirm the cause of myocarditis, and positive antibodies often show past exposure rather than active cardiac infection. Autoimmune testing is targeted when the history, examination, or other organs suggest systemic inflammatory disease.
Most adults have antibodies to common viruses such as Epstein-Barr virus, cytomegalovirus, and coxsackievirus. A positive IgG usually reflects previous exposure; it does not prove that a virus is affecting the heart now. Even IgM can be falsely positive or persist longer than expected. The EBV antibody pattern guide shows why antibody timing is tricky.
Clinicians may order ANA, ENA antibodies, ANCA, rheumatoid factor, complement levels, thyroid testing, or eosinophil counts when there are clues such as rash, joint swelling, asthma, sinus disease, kidney changes, recurrent inflammation, or drug exposure. Eosinophilic myocarditis is uncommon but clinically important because it may need urgent specialist-directed treatment.
Cardiac MRI and, in selected unstable or treatment-changing cases, endomyocardial tissue examination are better tools for characterising myocardial involvement than broad viral serology. The evidence is honestly mixed on exactly which ancillary tests every patient needs; the work-up should follow the phenotype, not a fixed shopping list.
Hvaða próf geta staðfest eða stutt hjartavöðvabólgu?
Cardiac MRI is the leading non-invasive test for supporting myocarditis because it can show oedema and non-ischaemic tissue injury patterns. ECG, echocardiography, coronary assessment when appropriate, and sometimes endomyocardial biopsy complete the diagnostic pathway.
The updated Lake Louise cardiac MRI criteria use at least one T2-based marker of oedema and one T1-based marker of non-ischaemic injury, such as late gadolinium enhancement or abnormal T1 mapping. Ferreira and colleagues reported that combining these tissue markers improves diagnostic assessment compared with older MRI approaches (Ferreira et al., 2018). MRI is strongest when performed close to the symptomatic period, although timing depends on stability and local access.
An ECG may show ST-T changes, PR depression, conduction delay, or rhythm disturbance, but a normal ECG does not exclude myocarditis. Echocardiography evaluates ejection fraction, chamber size, valve function, and pericardial fluid; it can be entirely normal in mild focal disease. A reduced left-ventricular ejection fraction below 50% changes urgency and follow-up planning.
Endomyocardial biopsy is not routine for everyone. It becomes more relevant with cardiogenic shock, rapidly worsening heart failure, high-grade heart block, sustained ventricular arrhythmia, or suspicion of a subtype that would alter treatment. This distinction matters: blood tests can raise suspicion, but only carefully selected tissue analysis can directly identify myocardial inflammatory cell patterns.
Hvenær á að endurtaka blóðrannsóknir vegna hjartavöðvabólgu?
Repeat troponin timing depends on symptoms and setting: emergency pathways commonly repeat high-sensitivity troponin after 1-3 hours, while outpatient follow-up may occur over days or weeks. Repeating a test without a clinical plan can create noise rather than clarity.
For acute chest symptoms, clinicians commonly use an immediate sample and a second sample at 1 or 2 hours, depending on the local validated algorithm. The absolute change in ng/L matters more than a percentage change when starting values are low. Do not use a home-timed repeat test to manage active chest pain—emergency teams need the ECG and vital signs at the same time.
After confirmed or probable myocarditis, troponin may normalise within days to weeks, but recovery is uneven. CRP often improves earlier than MRI abnormalities, and symptoms can improve before electrical irritability has fully settled. I advise patients to record the date, symptoms, exercise level, medications, and illness around each blood draw; our tímalínuleiðarvísir rannsóknarstofunnar okkar explains why those details matter.
Dr. Thomas Klein’s practical rule is that a repeat result should answer a specific question: “Is injury continuing?”, “Is this baseline elevation?”, or “Is recovery on track?” A troponin test repeated after heavy exercise, dehydration, or a different assay method may be difficult to compare. Ideally, follow-up uses the same laboratory and assay.
Getur hreyfing hækkað trópónín án hjartavöðvabólgu?
Yes, prolonged strenuous exercise can cause a temporary troponin rise without clinical myocarditis, particularly after marathons, ultradistance events, or intense cycling. Symptoms, ECG changes, recovery kinetics, and imaging determine whether the elevation is benign exertional release or true myocardial injury.
Post-exercise troponin elevations often peak within 2-6 hours and fall toward baseline within 24-48 hours, whereas sustained or rising values are more concerning. The overlap is not perfect, so symptoms matter enormously. Chest pain, collapse, unusual shortness of breath, or persistent palpitations after exercise should never be dismissed as “just training.”
During suspected myocarditis, vigorous exercise is usually restricted because inflamed myocardium may be more vulnerable to dangerous arrhythmias. Many sports-cardiology protocols reassess athletes after 3-6 mánuðum with symptoms, biomarkers, ECG monitoring, ventricular function, and sometimes MRI guiding return. The exact timeline varies with severity and residual findings.
A high CK after exercise can muddy the picture, especially when AST rises too. Our fyrir blóðpróf hjá þolíþróttamönnum helps distinguish training-related lab shifts from patterns that need medical review. Rest is not merely cautious advice here—it is part of risk reduction while the diagnosis is unresolved.
Hvenær þarf hækkað trópónín neyðaraðstoð
A raised troponin with active chest pressure, breathlessness at rest, fainting, confusion, sustained palpitations, or new weakness needs emergency assessment now. The result may reflect myocarditis, heart attack, pulmonary embolism, severe arrhythmia, or another condition that cannot be safely sorted out online.
Call emergency services rather than driving yourself if chest symptoms are severe, persistent beyond 10-15 minutes, accompanied by collapse, or associated with blue lips, severe breathlessness, or a racing irregular heartbeat. Troponin is not a measure of pain intensity; a person can have a dangerous condition with a modest elevation or little pain.
There are quieter warning patterns too: resting heart rate persistently above 120 beats per minute, new inability to climb one flight of stairs, swelling, reduced urine output, or palpitations with dizziness. A recent viral illness does not make a cardiac cause less urgent. In fact, it can increase suspicion for myocarditis while coronary and pulmonary causes still require consideration.
If you have a result but no current emergency symptoms, contact the clinician who ordered it the same day when possible. The high troponin urgent-care guide lists common non-heart-attack causes, but it should not be used to self-triage dangerous symptoms.
Hvernig á að lesa blóðrannsóknir vegna hjartavöðvabólgu án þess að ofskilja það
The safest way to read blood tests for heart inflammation is to look for a pattern: troponin trajectory, CRP, kidney function, electrolytes, symptoms, timing, and prior values. A single red flag on a report is a prompt for clinical context, not a final diagnosis.
Kantesti er AI-knúið blóðprófunargreiningartól designed to compare laboratory values across time and highlight combinations that deserve clinician follow-up. For suspected myocarditis, our AI does not label someone with the condition from troponin alone; it identifies myocardial-injury markers, inflammatory context, and potentially relevant kidney or electrolyte confounders. That is deliberately conservative.
Before reviewing any report, confirm four details: the test name, units, laboratory upper reference limit, and sampling date. Then note whether strenuous exercise, fever, dehydration, kidney disease, supplements, or a recent hospital visit could affect the result. The blóðsamanburðartæki is particularly useful when comparing values obtained by the same laboratory.
A healthy-looking CRP or normal CBC should not overrule concerning symptoms, and a flagged troponin should not be interpreted without an ECG. This is one of those areas where context matters more than the number. If you use Kantesti, treat the report as a structured conversation starter for your doctor, not clearance to continue normal activity.
Spurningar til að spyrja eftir óeðlilegar blóðrannsóknir vegna hjartavöðvabólgu
After abnormal cardiac blood work, ask what the result means for you today, what dangerous alternatives have been excluded, and what test will change management next. A precise question often gets a more useful answer than asking whether the number is simply “bad.”
Useful questions include: “Which troponin assay was used?”, “What is my change between samples in ng/L?”, “Could my kidney function explain part of this?”, “Do I need ECG, echocardiography, coronary assessment, or cardiac MRI?”, and “What exercise restriction applies while we investigate?” These questions work because they focus on decisions rather than trying to force a diagnosis from a number.
Ask whether repeat testing should occur in the same laboratory and whether any medications or supplements need review. Non-steroidal anti-inflammatory drugs, stimulants, decongestants, bodybuilding products, cocaine, and some cancer therapies can be relevant in selected cases. Never stop prescribed medication without the clinician managing your care.
Kantesti’s clinical content is reviewed with physician oversight; you can read about those standards in our læknisfræðilega staðfestingarleið okkar. As of September 22, 2026, the most reliable approach remains unchanged: troponin identifies injury, while expert clinical assessment and cardiac imaging establish whether myocarditis is the explanation.
Rannsóknir, læknisfræðileg endurskoðun og takmarkanir á netinu túlkun
Online information can explain a myocarditis blood test, but it cannot assess your ECG, blood pressure, oxygen level, rhythm, or cardiac imaging. Those missing data are exactly why troponin should be interpreted as a clinical signal rather than a standalone diagnosis.
The core evidence base is clear on one point: myocardial injury and myocarditis are not synonyms. Caforio et al. (2013) emphasised the need for integrated clinical assessment, while Ferreira et al. (2018) established modern MRI tissue-characterisation criteria that improve non-invasive diagnosis. Neither paper supports diagnosing myocarditis from CRP, CK-MB, or troponin alone.
For related laboratory context, our research library includes the leiðarvísir um viðmið fyrir sermi-prótein og leiðbeiningar um komplement og ANA. These tests may be relevant when clinicians suspect systemic immune disease, but they are not screening tests for every person with chest pain or an elevated troponin.
At Kantesti, we aim to make laboratory language less opaque while retaining the uncertainty that safe medicine requires. Our Læknisfræðileg ráðgjafarnefnd helps guide clinical review standards. If your symptoms are active or worsening, seek in-person care rather than relying on any article, app, or uploaded report.
Algengar spurningar
Getur blóðrannsókn greint hjartavöðvabólgu?
Blood work cannot diagnose myocarditis by itself. Troponin above the assay-specific 99th-percentile upper reference limit shows myocardial injury, while CRP above about 10 mg/L supports systemic inflammation, but neither identifies the cause or location of inflammation. Clinicians combine symptoms, ECG, echocardiography, coronary assessment when appropriate, and cardiac MRI to support the diagnosis. Endomyocardial biopsy is reserved for selected severe or treatment-changing cases.
Hvað bendir hjartavöðvabólgu til?
No troponin cutoff specifically indicates myocarditis because the same value can occur with heart attack, pulmonary embolism, rapid arrhythmia, kidney disease, or exercise. Many hs-cTnT assays use approximately 14 ng/L as the 99th-percentile upper reference limit, while hs-cTnI cutoffs vary widely by assay and sometimes by sex. A rise or fall over 1-3 hours is more informative than one isolated result. Chest symptoms and ECG findings determine urgency.
Getur maður fengið hjartavöðvabólgu með eðlilegu troponin?
Yes, myocarditis can occur with normal troponin, particularly when inflammation is mild, focal, late in its course, or tested after the biomarker peak. A normal troponin makes substantial ongoing myocardial injury less likely at that sampling time, but it does not fully rule out myocarditis. Persistent chest pain, palpitations, fainting, or breathlessness still require medical assessment. Cardiac MRI can detect tissue changes that blood tests miss.
Er CRP hátt við hjartavöðvabólgu?
CRP can be high in myocarditis, but it is neither sensitive nor specific for cardiac inflammation. A CRP above 10 mg/L commonly reflects active inflammation and values of 30-100 mg/L can occur in many infections or autoimmune conditions. Some people with MRI-supported myocarditis have normal CRP. CRP is most useful when considered alongside symptoms, troponin, ECG, and changes over time.
Hversu lengi er troponin hækkað við hjartavöðvabólgu?
Troponin may remain elevated for several days and occasionally longer in myocarditis, depending on the degree and persistence of myocardial injury. High-sensitivity troponin often rises within hours of acute injury, but the exact timing differs between troponin I and T assays and between patients. A falling result usually suggests injury is settling, although it does not by itself confirm recovery of heart function. Follow-up may include ECG, echocardiography, rhythm monitoring, and cardiac MRI.
Ætti ég að hreyfa mig ef troponin er hátt eftir veirusjúkdóm?
You should avoid strenuous exercise and seek medical advice if troponin is elevated after a viral illness, especially with chest pain, palpitations, fainting, or breathlessness. Sports-cardiology practice commonly restricts competitive or vigorous exercise for 3-6 months after confirmed myocarditis, with return guided by symptoms, biomarkers, cardiac function, and rhythm assessment. Exercise can transiently raise troponin after endurance events, but that cannot be assumed without evaluation. Active chest symptoms require urgent in-person assessment.
Fáðu AI-knúna greiningu á blóðprufum í dag
Vertu með yfir 2 milljónir notenda um allan heim sem treysta Kantesti fyrir tafarlausa og nákvæma greiningu á blóðprufum. Hladdu upp niðurstöðum blóðrannsókna þinna og fáðu yfirgripsmikla túlkun á 15,000+ lífmerkjum á sekúndum.
📚 Tilvísuð rannsóknarútgáfa
Klein, T., Mitchell, S., & Weber, H. (2026). Leiðbeiningar um sermisprótein: Blóðprufa um glóbúlín, albúmín og A/G hlutfall. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Leiðarvísir fyrir C3- og C4-komplement blóðpróf og ANA-títra. Kantesti AI Medical Research.
📖 Ytri læknisfræðilegar heimildir
⚕️ Fyrirvari vegna læknisfræðilegra mála
Þessi grein er eingöngu til fræðslu og felur ekki í sér læknisráðgjöf. Leitaðu alltaf til hæfs heilbrigðisstarfsmanns vegna ákvarðana um greiningu og meðferð.
E-E-A-T traustmerki
Reynsla
Læknastýrð klínísk yfirferð á vinnuferlum við túlkun rannsóknarniðurstaðna.
Sérþekking
Áhersla á rannsóknarstofulækningar: hvernig lífmarkarar hegða sér í klínísku samhengi.
Yfirvald
Skrifað af Dr. Thomas Klein með yfirferð Dr. Sarah Mitchell og próf. Dr. Hans Weber.
Traustleiki
Rökstudd túlkun byggð á gögnum með skýrum eftirfylgnileiðum til að draga úr ávörun.