
Choose a hydrogen breath test when you need objective evidence of lactose malabsorption; choose a supervised elimination-and-rechallenge trial when your main question is whether ordinary portions cause symptoms. A lactose tolerance blood test is an alternative when breath testing is unavailable, but glucose regulation can complicate interpretation.

Key takeaways
- Best objective option: A lactose hydrogen breath test measures fermentation after a lactose drink, usually containing 25 g in adults.
- Positive hydrogen result: A rise of at least 20 parts per million above baseline commonly supports lactose malabsorption, not automatically symptomatic intolerance.
- Blood-test alternative: A lactose tolerance test commonly considers a glucose rise below 20 mg/dL, or 1.1 mmol/L, suggestive of malabsorption; laboratory protocols differ.
- Practical symptom trial: A clinician or dietitian may suggest 10–14 days of lactose reduction followed by a measured rechallenge; this duration is pragmatic, not a universal diagnostic standard.
- Genetic limitation: Common genetic panels assess inherited lactase persistence, but cannot detect acquired lactase loss after intestinal injury or prove that lactose causes symptoms.
- Preparation matters: Breath-testing guidance commonly recommends avoiding antibiotics for 4 weeks and fasting for 8–12 hours, subject to the testing centre's instructions.
- Portion size matters: Many people with lactose malabsorption tolerate approximately 12 g of lactose, roughly one 240–250 mL glass of milk, particularly with food.
- Safety first: Blood in stool, weight loss, persistent fever, dehydration or possible milk allergy require medical assessment rather than an unsupervised dairy challenge.
Which lactose intolerance test should you choose first?
A lactose hydrogen breath test is usually the most useful objective option when the diagnosis is uncertain. A supervised dietary trial may be sufficient for straightforward, portion-related symptoms without warning signs; a lactose tolerance test is an alternative when breath testing is unavailable.

The choice depends on the question: are you trying to demonstrate poor digestion, identify your comfortable serving size, or investigate symptoms that happen even without dairy? These are 3 different clinical tasks, and the most technical test is not necessarily the most useful one for each.
For example, a hypothetical adult who develops bloating after 500 mL of milk but comfortably eats yogurt may benefit first from a measured dietary trial. Someone with persistent symptoms after several foods, or an inconclusive trial, has more to gain from objective testing and assessment for other digestive conditions.
A challenge dose can exceed normal eating habits. An adult breath test using 25 g of lactose represents roughly the lactose in 500 mL of milk; a reaction to that dose does not establish that a splash of milk in tea needs to disappear from your diet.
Kantesti is an AI blood test analyzer that can help explain laboratory glucose results, but it does not replace a breath-testing service or diagnose lactose intolerance from routine blood work. Our company background explains the organization behind these educational resources; the 3 diagnostic approaches here still require clinical context.
Why lactose malabsorption does not always cause symptoms
Lactose malabsorption means that some lactose escapes digestion in the small intestine. Lactose intolerance means that consuming lactose causes symptoms; a person can have a positive malabsorption test and still tolerate ordinary servings without discomfort.
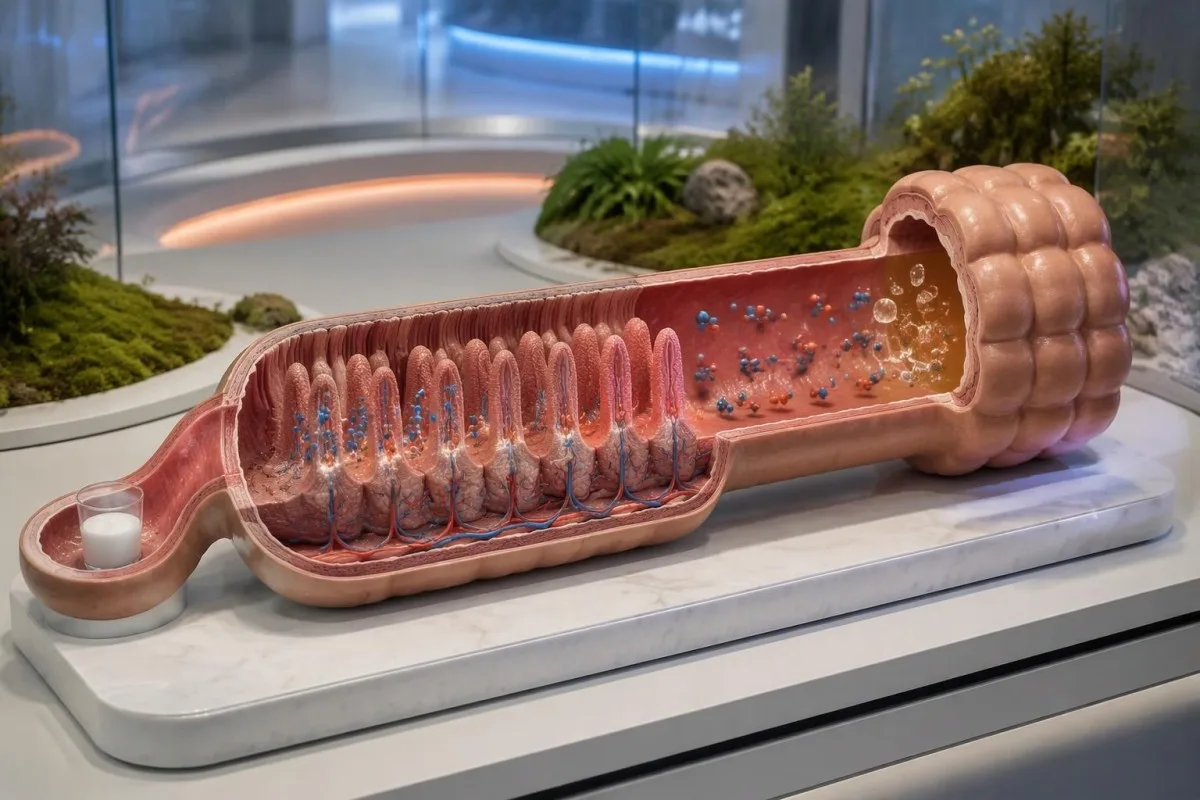
Lactase splits lactose into 2 absorbable sugars: glucose and galactose. When lactase activity is insufficient for the amount consumed, lactose reaches the colon, where microbial fermentation produces gases and other metabolites; unabsorbed carbohydrate also draws water into the intestinal contents.
Symptoms depend on more than the amount of gas. Intestinal sensitivity, transit speed, meal composition and the microbial community influence whether a 12 g serving causes nothing, mild bloating or troublesome diarrhea; this distinction is central to the review by Misselwitz et al. in Gut, 2019.
Consider a hypothetical breath test showing a 30 ppm hydrogen rise without discomfort during a 25 g challenge. That result supports malabsorption under test conditions, but does not establish symptomatic intolerance; permanent avoidance based only on the number could remove foods the person comfortably enjoys.
Stool changes also need a reproducible pattern, not a single unusual bowel movement. Recording the serving size, timing and stool form for 1–2 weeks is more informative than writing only 'dairy upset me'; our stool consistency guide explains how to describe those changes consistently.
How does a lactose hydrogen breath test work?
A lactose hydrogen breath test measures exhaled gas before and after a measured lactose drink. Adult testing commonly uses 25 g of lactose, repeated breath samples and simultaneous symptom recording to distinguish malabsorption from clinically relevant intolerance.
Hydrogen produced by intestinal microbes enters the circulation and is exhaled through the lungs. The North American Consensus recommends a 25 g lactose dose and testing for at least 3 hours, while the European guideline describes 3–5-hour testing depending on the clinical question and protocol (Rezaie et al., 2017; Hammer et al., 2022).
Sampling commonly occurs every 15–30 minutes, although centres differ. End-expiratory collection matters: a poorly collected sample can dilute intestinal gas with ordinary room air, so some analyzers measure carbon dioxide or oxygen to check sample quality rather than relying on the hydrogen value alone.
The European guideline distinguishes the purpose of the challenge: 25 g is recommended for assessing intolerance in adults, whereas malabsorption protocols may use 25–50 g. A larger challenge is more likely to exceed someone's digestive capacity, which is why the administered dose belongs on the report.
Ask whether the appointment records symptoms alongside gas measurements and whether methane is measured. A report containing only 'positive' loses useful information; our qualitative versus quantitative results guide explains why the actual values and their timing can change the interpretation.
How should you prepare for lactose breath testing?
Breath-test preparation commonly includes avoiding antibiotics for 4 weeks, limiting fermentable foods the preceding day and fasting for 8–12 hours. Follow your testing centre's written instructions, because medication, bowel preparation and dietary rules differ between protocols.

Antibiotics can change gas-producing microbes long after the final dose. The North American Consensus recommends a 4-week interval before breath testing; European guidance also advises waiting at least 2 weeks after colonic cleansing, such as bowel preparation, because the baseline fermentation pattern may be altered.
Laxatives and prokinetic medicines can change transit and sometimes bring lactose to fermenting microbes unusually quickly. North American guidance suggests withholding these for 1 week if tolerated, whereas local protocols may differ; never stop prescribed treatment without checking with the clinician responsible for it.
Smoking and vigorous exercise can affect breath measurements, so testing instructions generally restrict both around the procedure. An 8–12-hour fast is common, but people taking insulin or medicines that can cause hypoglycemia need an individualized plan rather than simply skipping meals and continuing every dose unchanged.
A high starting hydrogen value may prompt repeat sampling or rescheduling rather than immediate diagnosis. Oral fermentation, incomplete preparation and small-intestinal fermentation can all contribute; our SIBO breath testing guide explains overlapping pitfalls, although lactose and SIBO tests answer different questions.
What do hydrogen and methane results actually mean?
A hydrogen rise of at least 20 ppm above baseline commonly supports lactose malabsorption when the test is properly performed. Symptoms must be interpreted separately; methane of at least 10 ppm identifies methane positivity under North American criteria, not a stand-alone diagnosis of lactose intolerance.

For a hypothetical result, baseline hydrogen of 6 ppm rising to 31 ppm represents a 25 ppm increase—not a 31 ppm increase. The 20 ppm criterion refers to the change from baseline and helps distinguish a meaningful substrate-associated rise from smaller fluctuations; it is not a boundary between mild and severe symptoms.
Methane-producing microbes consume hydrogen, which can complicate hydrogen-only testing. A methane concentration of at least 10 ppm at any time is used by the North American Consensus to define methane positivity, but there is no universally accepted methane-only threshold that establishes symptomatic lactose intolerance (Rezaie et al., 2017).
A flat hydrogen curve does not always settle the question. Poor collection, recent antibiotics, slow transit beyond a 3-hour window or microbial gas-production patterns can reduce the measured response; an unusually early rise can instead raise questions about oral fermentation, rapid transit or small-intestinal fermentation.
Gas concentration cannot identify every organism responsible or predict precisely how a person will feel after 12 g of lactose at dinner. A commercial microbiome profile is not a validated replacement for this challenge; our microbiome testing limitations guide separates descriptive microbial findings from clinically established diagnostic uses.
| Level | Range | What it means |
|---|---|---|
| No qualifying hydrogen rise | Hydrogen rise <20 ppm | Does not demonstrate malabsorption by this criterion; review preparation, sampling and clinical context. |
| Malabsorption without symptoms | Hydrogen rise ≥20 ppm; no reproduced symptoms | Supports malabsorption under test conditions, but does not establish symptomatic intolerance. |
| Malabsorption with symptoms | Hydrogen rise ≥20 ppm; compatible symptoms reproduced | Supports lactose intolerance when the timing and clinical history also fit. |
| Methane-positive pattern | Methane ≥10 ppm at any time | Identifies methane positivity under North American criteria; not an independent lactose intolerance cutoff. |
When is a lactose tolerance blood test useful?
A lactose tolerance test measures the blood glucose response after drinking lactose. It can be useful when breath testing is unavailable, but diabetes, altered glucose regulation and sample handling can make the result harder to interpret than a properly performed breath test.

Protocols commonly use 25–50 g of lactose, with fasting glucose followed by samples over approximately 2 hours. Because digestion releases glucose, an inadequate rise suggests poor lactose digestion; a commonly used criterion is a maximum increase below 20 mg/dL, equivalent to approximately 1.1 mmol/L.
For example, a hypothetical fasting glucose of 88 mg/dL with a maximum post-lactose value of 101 mg/dL gives a rise of 13 mg/dL. That supports possible malabsorption under a laboratory using the 20 mg/dL criterion, but should not be treated as confirmation without checking the protocol, symptoms and possible confounders.
Some laboratories use a 20–25 mg/dL threshold or different sampling times, and glucose metabolism varies between people. Delayed sample processing can also lower measured glucose through glycolysis; our fasting sample preparation guide explains why preparation and laboratory handling belong in the interpretation.
This test is not an oral glucose tolerance test for diagnosing diabetes, even though both use timed glucose measurements. Anyone taking glucose-lowering medicines should discuss the 8–12-hour fast and challenge drink beforehand; our fasting hypoglycemia causes resource explains why medication-related low glucose needs a separate safety plan.
Why genetic testing cannot detect every cause
Genetic testing can identify selected variants associated with inherited lactase persistence or non-persistence. It cannot diagnose acquired lactase loss after intestinal injury, measure current digestive capacity or establish whether a person's symptoms are caused by lactose.
Many panels examine the −13910 C/T variant, rs4988235, in a regulatory region within MCM6 near the lactase gene. This marker is particularly informative in populations of European ancestry, but other lactase-persistence variants occur in African and Middle Eastern populations; the panel's variant coverage matters more than its marketing label.
A result associated with lactase persistence cannot exclude secondary malabsorption from celiac disease, gastroenteritis or other small-intestinal injury. Conversely, a non-persistence-associated genotype does not prove that 12 g of lactose causes symptoms; age, remaining enzyme activity, portion size and intestinal sensitivity still influence the clinical picture.
Congenital lactase deficiency is a separate, rare condition that usually presents in early infancy. A common adult persistence panel is not equivalent to sequencing LCT for that disorder, so 2 reports both described as 'lactose genetic tests' may be looking for fundamentally different explanations.
Kantesti, an AI biomarker interpretation platform, can help distinguish a genetic association from a measured laboratory response, but neither establishes symptoms without a compatible history. Our laboratory marker guide explains different result types; for genetic testing, ask which variants are covered and whether the interpretation accounts for ancestry.
How to test with supervised elimination and rechallenge
A supervised elimination-and-rechallenge trial tests whether reducing lactose improves symptoms and reintroducing it reproduces them. A clinician or dietitian may use approximately 10–14 days of reduction, followed by measured servings, but there is no single universally validated home-trial duration.

The cleanest practical comparison changes lactose while keeping other factors stable. Replacing ordinary milk with lactose-free milk preserves milk proteins and a similar meal structure; removing dairy, gluten, onions and several other foods together for 2 weeks makes it difficult to know which change affected symptoms.
Rechallenge should begin with a portion relevant to your diet rather than copying a laboratory's largest dose. A hypothetical plan might compare 100–125 mL of ordinary milk, approximately 5–6 g of lactose, with a similar lactose-free serving on another day, then consider a larger portion if the clinician recommends it.
Record symptoms on a 0–10 scale before the serving and over the following several hours, plus stool changes during the next 24 hours. Improvement during elimination alone is weak evidence: ordinary fluctuation, expectation, reduced meal size and changes in fat intake can all create an apparent response.
Reproducibility matters more than a single bad afternoon. A clinician may recommend 2 comparable exposures or, when uncertainty persists, a blinded lactose-versus-placebo challenge; our digestive symptom tracking resource helps separate lactose timing from fasting, meal-size and other digestive triggers.
What if test results and symptoms disagree?
When gas results, glucose results and symptoms disagree, review the dose, preparation, timing and alternative causes before labeling the test wrong. A positive malabsorption result without symptoms usually calls for portion-based advice, while persistent symptoms despite lactose reduction require a broader assessment.
A positive 25 g breath challenge and a comfortable 6 g serving at home are not contradictory findings. The first tests digestive capacity under a defined load; the second shows that a smaller exposure may fall below the person's symptom threshold, particularly when consumed as part of a meal.
Symptoms during a negative breath test can reflect intestinal sensitivity, another ingredient, expectation or a technical false negative. A report with inadequate preparation or only 2 hours of collection deserves scrutiny, but repeating tests indefinitely is less useful than deciding which specific uncertainty another test would resolve.
A lactose-free milk reaction points away from lactose as the sole explanation, although it does not by itself diagnose milk allergy. Milk proteins, fat content, accompanying foods and functional digestive symptoms remain possibilities; 2 well-matched servings provide more useful evidence than comparing unrelated dairy products.
We write Kantesti guidance to separate a measurable abnormality from a causal diagnosis: a 20 ppm rise is evidence about fermentation, not proof that every digestive symptom comes from lactose. Our DAO testing limitations article illustrates a related pitfall—substituting a loosely associated laboratory result for a reproducible symptom assessment.
When should you investigate secondary lactase deficiency?
Secondary lactase deficiency should be considered when lactose-related symptoms begin after gastrointestinal illness, occur with persistent diarrhea or accompany weight loss or nutritional deficiencies. Treating the underlying small-intestinal problem may restore tolerance; genetic testing cannot detect these acquired causes.

Lactase sits at the brush border of intestinal villi, making its activity vulnerable when the surface lining is disrupted. Recovery after gastroenteritis can take several weeks and varies with the cause; our Giardia recovery guidance explains one illness that can produce lingering digestive symptoms and secondary lactose difficulty.
Celiac testing commonly begins with tissue-transglutaminase IgA and total IgA while the person is still eating gluten. Starting both a lactose-free and gluten-free diet for 2 weeks can obscure the investigation; our celiac testing preparation resource explains why gluten exposure must be discussed before changing the diet.
Low ferritin, anemia or multiple nutrient deficiencies suggest that a narrow lactose explanation may be incomplete. Ferritin below 15 µg/L strongly supports depleted iron stores in an otherwise healthy adult, although inflammation complicates higher values; our iron studies interpretation guide explains how companion results refine that assessment.
Persistent diarrhea with nighttime symptoms, visible blood or weight loss warrants evaluation beyond a 25 g carbohydrate challenge. Depending on the history, clinicians may use stool inflammatory markers, infection testing or endoscopy; our stool inflammation test choices guide explains why these assess a different problem from lactose malabsorption.
How do you distinguish lactose intolerance from milk allergy?
Milk allergy is an immune reaction to milk proteins; lactose intolerance is difficulty digesting a sugar. Hives, wheezing, throat swelling or collapse after dairy require urgent assessment, and suspected allergy makes an unsupervised milk rechallenge inappropriate.

Immediate IgE-mediated milk reactions often begin within minutes to about 2 hours, although non-IgE reactions can be delayed. Lactose symptoms more typically involve gas, bloating, cramps or diarrhea after digestion and fermentation; timing helps, but overlap means that timing alone cannot safely rule allergy in or out.
Lactose-free milk still contains milk proteins and is not a safe substitute for someone with confirmed cow's-milk protein allergy. When the history suggests allergy, targeted testing is interpreted alongside the reaction pattern; our component allergy testing guide explains why sensitization on a laboratory panel does not automatically establish clinical allergy.
Visible blood or black, tar-like stool should not be attributed to lactose intolerance. A 20 ppm hydrogen rise cannot explain away these findings, and a positive lactose test does not protect against a second condition; our blood in stool guidance explains when urgent care is appropriate.
Severe localized abdominal pain, persistent fever, repeated vomiting or dehydration also takes priority over dietary experimentation. If a person cannot keep fluids down or becomes faint, do not wait through a 10–14-day elimination trial; new symptoms deserve assessment even when lactose intolerance was previously diagnosed.
Do children, pregnancy or diabetes change the test choice?
Children need age-appropriate assessment and clinician-selected lactose doses; pregnancy and diabetes require attention to fasting, hydration and nutrition. None of these groups should automatically copy an adult 25–50 g challenge or start a prolonged restrictive diet without a clinical plan.

Pediatric breath-testing protocols are less standardized than adult protocols. The European guideline describes doses ranging from 0.5–2 g/kg with maximum doses of 25–50 g across protocols, rather than one universally accepted schedule; these are laboratory protocol ranges, not instructions for parents to conduct a challenge.
Acidic stool can occur when unabsorbed carbohydrates are fermented, but it does not identify lactose as the specific cause. A stool pH below approximately 5.5 has traditionally suggested carbohydrate malabsorption, yet sensitivity and specificity are limited; our children's stool pH results guide explains the interpretive limitations.
Stool reducing substances also lack the specificity needed to diagnose lactose intolerance alone. Results depend on diet, age, handling and the assay's reporting scale; our stool carbohydrate screening resource explains why even a positive result needs clinical correlation rather than a blanket milk ban.
For pregnancy or diabetes, discuss the 8–12-hour fast before booking and ask how prescribed medicines should be managed. A breath test avoids using the glucose rise as the diagnostic signal, but the lactose drink still provides carbohydrate and can provoke diarrhea; maintaining adequate nutrition is part of choosing the safest approach.
How much lactose can you eat after a positive test?
A positive test usually calls for finding your comfortable lactose dose, not eliminating every dairy food. Many people with malabsorption tolerate approximately 12 g of lactose, roughly one glass of milk, especially with food; individual tolerance can be lower or higher.

Misselwitz et al. in Gut, 2019 describe substantial variation in symptom thresholds, including the influence of intestinal sensitivity and meal context. A 25 g test reaction therefore should not be translated automatically into 'zero lactose'; splitting smaller amounts across meals may work better than taking the same total in one drink.
Hard cheeses generally contain little lactose, while yogurt may be better tolerated because of its cultures and food matrix. Lactose-free dairy retains protein and calcium, but plant alternatives vary; check the actual fortification and protein content rather than assuming that 250 mL of every milk substitute is nutritionally equivalent.
Adult calcium recommendations differ internationally: the UK reference intake is 700 mg/day, while US recommendations are generally 1,000 mg/day, increasing to 1,200 mg/day for women over 50 and men over 70. These are total dietary targets, not automatic supplement doses; long-term restriction can make achieving them harder.
Vitamin D also deserves attention if food intake is limited, but a positive lactose test is not itself a reason for repeated vitamin D blood tests. UK public advice commonly uses 10 µg, or 400 IU, daily in relevant circumstances; our vitamin D retesting guide explains when measurement and follow-up are actually useful.
After testing: follow-up and research transparency
After testing, review the actual dose, gas or glucose response, reproduced symptoms and the smallest diet change needed. Arrange reassessment if symptoms persist despite appropriate lactose reduction; a positive result should not end the investigation when warning signs or nutritional abnormalities remain.
Bring 4 pieces of information to the follow-up: the laboratory protocol, numerical results with units, symptom timing and your response to ordinary portions. A report saying only 'lactose positive' is less useful than one documenting a 25 g dose, a 24 ppm hydrogen increase and whether the familiar symptoms actually occurred.
Kantesti is an AI blood test interpretation platform that can help organize timed glucose values and related findings such as ferritin, but routine panels cannot establish lactose intolerance. Our AI interpretation technology explains the support workflow; a glucose change of 13 mg/dL still requires the laboratory's protocol and a clinician's judgment.
Our clinical explanations distinguish 3 evidence layers: test performance, symptom causation and safe management. Kantesti does not replace diagnostic breath equipment, supervised food challenges or medical assessment; our technical and clinical standards describe oversight, but should not be read as validation of a stand-alone lactose diagnostic test.
The 3 external medical references below directly support this article's breath-testing and intolerance discussion. The 2 repository publications listed separately cover other laboratory topics and are included for publication transparency—not as evidence for lactose testing; a DOI identifies a publication but does not by itself establish peer review or diagnostic accuracy.
Frequently asked questions
What is the most useful test for lactose intolerance?
A lactose hydrogen breath test is usually the most useful objective test when lactose intolerance is uncertain, provided symptoms are recorded alongside gas measurements. Adult testing commonly uses 25 g of lactose, and a hydrogen rise of at least 20 ppm above baseline supports malabsorption. A positive gas result without symptoms does not establish symptomatic intolerance. A supervised elimination-and-rechallenge trial may be sufficient for straightforward symptoms without warning signs.
How can I test for lactose intolerance at home?
A clinician-guided lactose reduction followed by measured reintroduction can assess whether lactose reproducibly causes symptoms in ordinary meals. A practical trial may use 10–14 days of reduction, but there is no universally validated home-test duration. Keeping the rest of the diet stable and comparing ordinary milk with a similar lactose-free serving makes the result easier to interpret. Do not perform a home milk challenge if there is a history suggesting milk allergy, such as hives, wheezing or throat swelling.
Can a normal blood test rule out lactose intolerance?
Normal routine blood tests cannot rule out lactose intolerance because standard panels do not measure lactose digestion. A dedicated lactose tolerance test examines timed glucose changes after lactose, commonly using a rise below 20 mg/dL, or 1.1 mmol/L, as suggestive of malabsorption. Glucose regulation, laboratory handling and protocol differences can complicate that result. A properly performed breath test or supervised symptom trial may answer the question more directly.
Does a positive lactose breath test mean I must stop all dairy?
A positive lactose breath test does not mean that all dairy must be avoided. A hydrogen rise of at least 20 ppm supports malabsorption under the test conditions, but symptoms depend on dose and individual sensitivity. Many people with malabsorption tolerate approximately 12 g of lactose, especially with a meal. Smaller servings, hard cheese, yogurt or lactose-free dairy can help preserve nutrition while reducing symptoms.
Can genetic testing miss lactose intolerance?
Genetic testing can miss acquired lactose intolerance because common panels assess inherited lactase regulation rather than current intestinal enzyme activity. Many panels test rs4988235, the −13910 C/T marker, which does not capture every lactase-persistence variant across ancestry groups. Intestinal injury from conditions such as celiac disease or gastroenteritis can reduce lactase activity despite a persistence-associated result. A genotype also cannot establish whether a 12 g serving actually produces symptoms.
How long does a lactose hydrogen breath test take?
A lactose hydrogen breath test generally involves at least 3 hours of sampling, with some European protocols extending to 5 hours. Breath samples are commonly collected every 15–30 minutes after a measured lactose drink. Preparation often includes an 8–12-hour fast and a 4-week interval after antibiotics, subject to the testing centre's instructions. Ask about the full appointment length and medication instructions before booking.
Get your blood test results explained
Upload your lab report and Kantesti's AI explains each biomarker in plain language within seconds. Used by more than 2 million people worldwide.
References
- Klein, T., Mitchell, S., & Weber, H. (2026). Nipah Virus Blood Test: Early Detection & Diagnosis Guide 2026. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). B Negative Blood Type, LDH Blood Test & Reticulocyte Count Guide. Kantesti AI Medical Research. DOI
- Rezaie A et al. (2017). Hydrogen and Methane-Based Breath Testing in Gastrointestinal Disorders: The North American Consensus. American Journal of Gastroenterology. DOI PubMed
- Hammer HF et al. (2022). European guideline on indications, performance, and clinical impact of hydrogen and methane breath tests in adult and pediatric patients: European Association for Gastroenterology, Endoscopy and Nutrition, European Society of Neurogastroenterology and Motility, and European Society for Paediatric Gastroenterology Hepatology and Nutrition consensus. United European Gastroenterology Journal. DOI
- Misselwitz B et al. (2019). Update on lactose malabsorption and intolerance: pathogenesis, diagnosis and clinical management. Gut. DOI
- 2M+Tests analysed
- 127+Countries
- 100+Languages
About the medical team


E-E-A-T Trust Signals
Experience
Physician-led clinical review of lab interpretation workflows.
Expertise
Laboratory medicine focus on how biomarkers behave in clinical context.
Authoritativeness
Medically reviewed by Dr. Thomas Klein, with contributions from Dr. Sarah Mitchell and Prof. Dr. Hans Weber.
Trustworthiness
Evidence-based interpretation with clear follow-up pathways to reduce alarm.




Medical disclaimer
This article is for educational purposes only and does not constitute medical advice. Always consult a qualified healthcare provider for diagnosis and treatment decisions.
Published · Contact the editorial team
Published by Kantesti Ltd, registered in England & Wales, company no. 17090423, London, United Kingdom.
