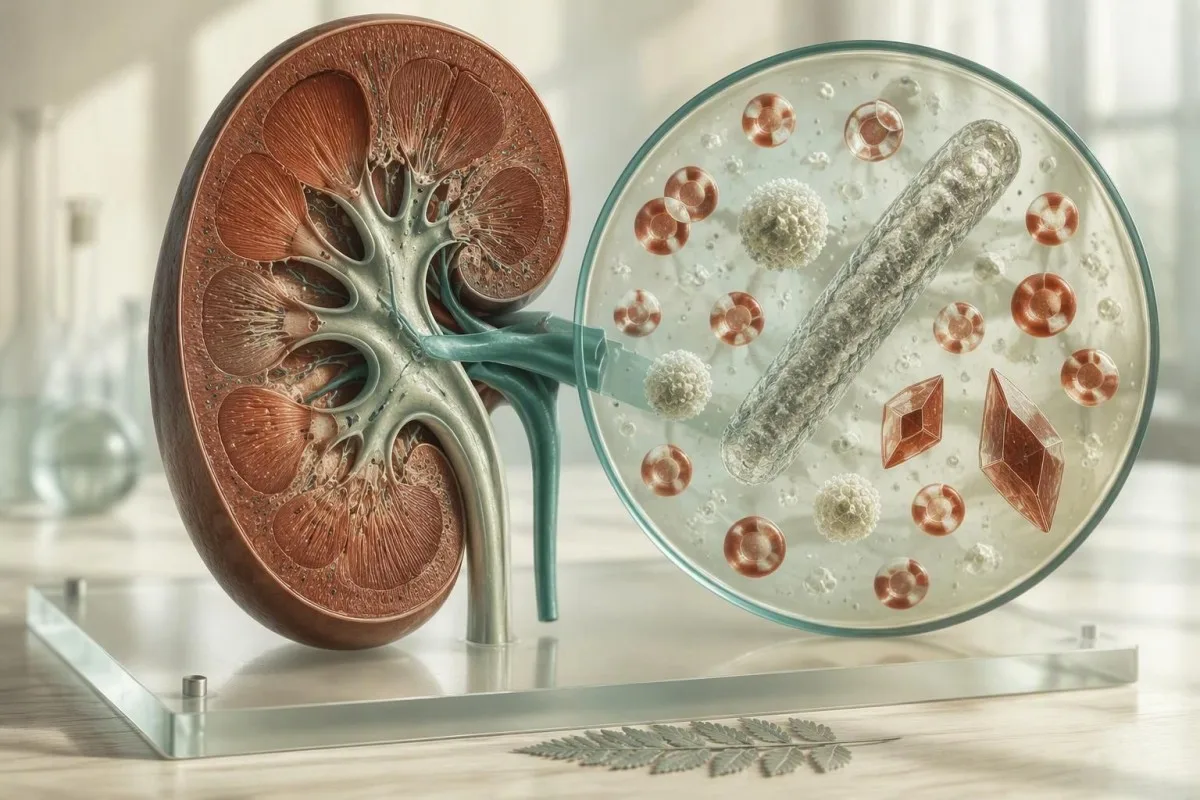
Urine microscopy is most useful when you read the whole pattern: collection quality, symptoms, dipstick findings, cells, casts, and crystals. A single flagged particle rarely tells the full story.


- Red blood cells above 3 per high-power field in a properly collected sample meet the AUA definition of microscopic hematuria and need risk-based follow-up.
- កោសិកាឈាមស (white blood cells) above 5 per high-power field indicate pyuria, but pyuria alone does not prove a urinary infection.
- កោសិកាអេពីថេលիyam ស្កuação usually come from skin or genital-surface contamination; abundant cells often justify repeating a clean-catch sample.
- កោសិកាអេពីថេលիyam នៃបំពង់តម្រងនោម are uncommon in uncomplicated contamination and deserve timely review when paired with protein, casts, or rising creatinine.
- គ្រីស្តាល់ Calcium oxalate are common and do not diagnose a kidney stone, although recurrent crystals plus symptoms merit a stone-risk assessment.
- Hexagonal cystine crystals are a specific clue to cystinuria and should trigger prompt specialist evaluation.
- Red-cell casts suggest glomerular bleeding rather than bleeding from the bladder and warrant urgent clinical assessment.
- ការកែច្នៃយឺតយ៉ាវ can create crystals and break down cells; urine should ideally be examined within 2 hours or refrigerated.
What urine sediment actually shows under the microscope
Urine sediment is the concentrated material left after urine is spun and examined under a microscope, including cells, casts, crystals, organisms, and debris. Most isolated minor findings are harmless or collection-related; the combinations that matter are red cells with protein, white cells with symptoms, or renal cells and casts with impaired kidney function.
A dipstick is a chemical screen, whereas urine microscopy asks what physical material is actually present. A positive blood pad can reflect intact red cells, free haemoglobin, myoglobin after severe muscle injury, or even menstrual contamination; microscopy separates these possibilities. Our ការណែនាំពេញលេញអំពីការវិភាគទឹកនោម explains why a dipstick and sediment can legitimately disagree.
In my 15 years of clinical practice, I have found the sample story nearly as valuable as the count: first morning versus late afternoon, exercise within 24 hours, menstruation, fever, recent intercourse, and whether the specimen sat on a warm counter. Urine pH may drift upward after collection, cells can lyse, and new crystals can precipitate within hours.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគឈាម AI that places kidney-related blood markers such as creatinine, eGFR, bicarbonate, calcium, and urate alongside a reported urine sediment. That context matters because a few hyaline casts with normal kidney function are a very different clinical situation from casts plus a rapidly rising creatinine.
How laboratories report the field of view
Most laboratories report formed elements as cells per high-power field (HPF), while automated systems may report cells per microlitre. A result of 8 RBC/HPF cannot be compared directly with 8 RBC/µL without the laboratory's conversion method, so use that lab's reference interval rather than an internet-wide “normal.”
Red blood cells: when microscopic hematuria needs a plan
More than 3 red blood cells per high-power field on one properly collected urine sample is microscopic hematuria under the American Urological Association definition. It is not a cancer diagnosis, but persistent hematuria should not be dismissed as “just a UTI” without evidence.
The 2025 amendment to the AUA/SUFU microhematuria guideline keeps the threshold at more than 3 RBC/HPF and recommends risk-based evaluation rather than automatic scanning for everyone (Barocas et al., 2020; amended 2025). Age, smoking history, gross visible blood, occupational exposures, and persistence shape the next step far more than whether the count is 4 or 14 RBC/HPF.
Dysmorphic red cells, especially acanthocytes with membrane blebs, point toward a glomerular source; uniformly shaped red cells more often arise downstream in the urinary tract. This distinction is operator-dependent, honestly, and many routine laboratories do not report it reliably. Red-cell casts plus proteinuria are a more persuasive signal of glomerular disease than red-cell shape alone.
A 29-year-old distance runner I saw had 18 RBC/HPF after a trail race and no protein, pain, or urinary symptoms; a repeat sample 72 hours later was clear. Exercise-associated hematuria usually resolves within 48 to 72 hours, but visible red urine, recurrent results, or persistence beyond that window deserves the hematuria follow-up pathway.
White cells in urine: pyuria is not automatically a UTI
More than 5 white blood cells per high-power field is commonly called pyuria, but pyuria alone cannot diagnose a urinary tract infection. Symptoms and, when needed, a properly collected culture determine whether antibiotics are useful.
A symptomatic person with dysuria, frequency, pyuria, and nitrite positivity has a substantially different probability of bacterial cystitis than an asymptomatic person with 10 WBC/HPF. Nitrite can be negative with frequent voiding, low dietary nitrate, or organisms that do not reduce nitrate, so a negative result does not rule out infection. The practical nuances are covered in our guide to leukocyte esterase ជាមួយនីទ្រីតអវិជ្ជមាន.
Sterile pyuria can occur with stones, sexually transmitted infections, tuberculosis in selected risk settings, interstitial nephritis, recent antibiotics, or sample contamination. WBC casts shift concern toward kidney-level inflammation, such as pyelonephritis or interstitial nephritis, particularly when fever, flank discomfort, creatinine change, or eosinophilia is present.
The 2019 IDSA guideline advises against screening for or treating asymptomatic bacteriuria in most non-pregnant adults, including older adults and people with diabetes; pregnancy and invasive urologic procedures are key exceptions (Nicolle et al., 2019). Treating a microscopy result rather than a clinical infection is a common route to side effects and resistant organisms.
When a culture adds value
A urine culture is most useful before antibiotics in pregnancy, suspected kidney infection, recurrent symptoms, complicated illness, or treatment failure. For uncomplicated first-episode cystitis in a non-pregnant adult, clinicians may reasonably treat based on a classic symptom pattern, but a sediment result cannot substitute for history.
Urine epithelial cells: contamination versus kidney injury clues
Squamous epithelial cells usually indicate collection contamination, while renal tubular epithelial cells can indicate tubular injury when they are numerous or occur with granular casts. “Epithelial cells present” is therefore not a diagnosis; the cell type is the clinically useful part.
Squamous cells are broad, flat cells from the outer urethral or genital surface. There is no universal cutoff, though many laboratories flag “many” cells or counts above roughly 5 to 15/HPF; their presence makes bacteria and white-cell findings less trustworthy, not automatically abnormal. A careful midstream repeat after separating the labia or retracting the foreskin often settles the question.
Transitional or urothelial cells come from the bladder and ureters and may rise after catheterisation, stones, inflammation, or instrumentation. They are not equivalent to malignant cells. If a report says “atypical urothelial cells,” that is a cytology finding with a different threshold for action and should be reviewed directly with the ordering clinician.
កោសិកាអេពីថេលիyam នៃបំពង់តម្រងនោម are smaller and more granular, and their presence becomes concerning with brown granular casts, proteinuria, or an acute creatinine increase. I would not diagnose acute kidney injury from a solitary reported cell, but I would review medicines, hydration, blood pressure, and repeat kidney labs promptly. Our detailed guide to epithelial cell types shows why reports should not lump them together.
Urine casts reveal where the sediment formed
Urine casts form inside kidney tubules, so their type often localises a problem to the kidney rather than the bladder. Hyaline casts can be normal; red-cell, white-cell, waxy, and abundant granular casts require much more context and often timely review.
Hyaline casts are largely made of uromodulin protein and 0 to 2 per low-power field can appear after exercise, fever, dehydration, or diuretic use. Their refractive, nearly transparent appearance means they are easily missed. In isolation, they do not establish kidney disease; see the practical distinction in our hyaline cast article.
Granular casts contain degraded cellular material. A few fine granular casts may appear transiently after strenuous exertion, but coarse “muddy brown” granular casts with an acute creatinine rise support acute tubular injury. The combination is stronger than either finding alone because it links tubular debris to reduced filtration.
Red-cell casts strongly support glomerulonephritis, while white-cell casts raise concern for pyelonephritis or interstitial nephritis. These are not home-monitoring findings. If casts accompany new swelling, blood pressure above 180/120 មមបារត, reduced urine output, fever, or an eGFR drop, seek same-day medical assessment.
Why waxy casts deserve attention
Broad waxy casts are associated with slow urine flow in dilated tubules and are often seen in advanced chronic kidney disease. They do not measure kidney function by themselves, yet their appearance should prompt a review of eGFR, urine albumin-creatinine ratio, and prior results.
Granular casts and renal cells: the acute kidney injury pattern
Muddy brown granular casts with renal tubular epithelial cells are a classic urine-sediment pattern of acute tubular injury. This pattern deserves urgent clinical correlation, especially when creatinine rises by at least 0.3 mg/dL (26.5 µmol/L) within 48 hours.
KDIGO defines acute kidney injury as a creatinine increase of 0.3 mg/dL ឬច្រើនជាងនេះ ក្នុងរយៈពេល 48 ម៉ោង, a 1.5-fold rise within 7 days, or low urine output for 6 hours (KDIGO, 2024). Sediment does not replace those criteria, but it may help clinicians distinguish tubular injury from a purely haemodynamic fall in filtration.
កាន់តេស្ទី គឺជា សេវាកម្មបកស្រាយការធ្វើតេស្តរបស់ AI lab that can flag a sediment report for clinician review when it appears alongside creatinine, potassium, bicarbonate, and eGFR changes. Our system does not diagnose the cause of kidney injury; medication exposure, obstruction, infection, contrast exposure, volume status, and baseline kidney function still require a clinician's judgment.
The detail patients often miss is timing. A sediment obtained after intravenous fluids or after creatinine has started falling may look less dramatic than the sample collected at the peak of illness. For a closer discussion of the finding itself, read about granular casts and next steps.
Common urine crystals: what calcium oxalate and uric acid mean
Calcium oxalate and uric acid crystals are common urine findings and do not, by themselves, prove kidney stones. Their value increases when they recur with renal colic, visible blood, low urine volume, or a personal history of stones.
Calcium oxalate crystals may look like envelopes or dumbbells and can occur in acidic, neutral, or alkaline urine. They are often found in otherwise healthy people, particularly when a sample is concentrated. Repeated stones are more usefully assessed with urine volume, calcium, oxalate, citrate, sodium, and uric acid than with one microscopic crystal report.
Uric acid crystals favour acidic urine, often below pH 5.5, and may accompany hyperuricosuria, gout, high cellular turnover, or metabolic syndrome. A serum urate concentration can be normal in a person who forms uric acid stones; urine pH is frequently the more actionable clue. Our guide to high urine calcium and stone risk explains why a 24-hour collection is sometimes needed.
I caution against “flushing out crystals” with extreme water intake. For most stone formers, a practical target is urine output of at least 2.0 to 2.5 litres daily, adjusted for climate and medical conditions. Heart failure, advanced kidney disease, and hyponatraemia risk change that advice, so personalise it.
Struvite, cystine, and drug crystals need faster follow-up
Struvite crystals suggest alkaline urine in the setting of urease-producing bacterial infection, while hexagonal cystine crystals are highly specific for cystinuria. Both patterns warrant more than generic hydration advice.
Struvite crystals have a coffin-lid appearance and tend to occur in alkaline urine, often pH above 7.0, with infection by urease-producing organisms. A culture is necessary because microscopy cannot name the organism, and infection stones can enlarge quickly with surprisingly modest symptoms. Fever, flank pain, vomiting, or reduced urine output requires urgent evaluation.
Hexagonal cystine crystals are uncommon but highly characteristic of cystinuria, an inherited defect in amino-acid transport. They often appear in childhood or young adulthood, though diagnosis can be delayed for years. Confirmation uses quantitative urine cystine testing or genetic evaluation, usually through a stone or nephrology team.
Some medicines can crystallise in urine, especially when urine is concentrated or acidic; examples include older antivirals, sulfonamides, and high-dose methotrexate in specialist settings. The medication list is not a footnote here. A recurrent stone assessment often includes 24-hour urine citrate, as discussed in our low urine citrate guide.
Collection and processing can change a sediment result
A delayed, poorly collected, or highly dilute specimen can create misleading urine sediment results. Fresh midstream urine examined within 2 hours is preferred; if delay is unavoidable, refrigeration at 2–8°C helps preserve formed elements.
The first part of the urine stream carries more skin and urethral material, while the midstream portion better reflects bladder urine. For menstruating patients, a repeat sample after bleeding stops is generally more informative than trying to interpret a heavily contaminated specimen. Catheterised sampling is reserved for situations where a clean answer changes care.
At room temperature, bacteria multiply, pH may rise, cells degrade, and amorphous phosphate crystals may appear. Refrigeration can itself encourage precipitation of some crystals, which is why a laboratory needs to know storage conditions. A report of “crystals present” without collection timing is less persuasive than it looks.
Cloudiness is also not synonymous with infection; it may result from crystals, mucus, cells, semen, or benign phosphate precipitation. The visual causes and warning features are covered in our cloudy urine explanation.
Read urine microscopy with dipstick and protein results
Urine sediment is safest to interpret alongside dipstick blood, protein, leukocyte esterase, nitrite, specific gravity, and pH. A pattern of blood plus protein is more concerning for kidney disease than either isolated result.
Dipstick protein mainly detects albumin and can miss light chains or very dilute samples. A first-morning urine albumin-creatinine ratio below 30 mg/g is considered normal to mildly increased; 30 to 300 mg/g is moderately increased, and above 300 mg/g is severely increased. Persistent albuminuria, not one post-exercise result, is what changes chronic kidney disease classification.
If dipstick blood is positive but microscopy finds zero or very few red cells, clinicians consider haemoglobinuria, myoglobinuria, oxidising contamination, or cell lysis in an old sample. After intense exercise, severe muscle pain, weakness, or cola-coloured urine with this pattern needs urgent testing for creatine kinase and kidney injury.
The combination of albuminuria and hematuria may justify nephrology input even with a preserved eGFR, especially if there is hypertension or family history. Our មគ្គុទេសក៍ protein ក្នុងទឹកនោម gives a practical way to prepare for repeat ACR testing.
Urine pH provides context, not a diagnosis
Urine pH usually ranges from about 4.5 to 8.0, and a single pH result cannot diagnose a UTI or a stone type. Persistent acidity or alkalinity becomes useful when it matches crystals, culture results, diet, and 24-hour urine chemistry.
An acidic pH below 5.5 supports uric acid crystallisation, whereas alkaline urine may favour calcium phosphate or struvite formation. Vegetarian diets, vomiting, medications such as acetazolamide, and delayed testing can all shift pH. That is why I avoid assigning a stone composition from pH alone.
Persistent alkaline urine with recurrent calcium phosphate stones may lead clinicians to look for distal renal tubular acidosis, particularly if serum bicarbonate is low or potassium is abnormal. Conversely, acidic urine can be an important treatable risk in uric acid stone disease. These distinctions are developed in our urine pH results guide.
Kantesti AI interprets kidney-related laboratory patterns by comparing pH-associated sediment findings with serum bicarbonate, potassium, calcium, phosphate, and creatinine when those data are available. It can identify questions to take to a clinician, not determine stone chemistry or replace imaging.
Sediment patterns that need same-day clinical assessment
Red-cell casts, heavy protein with blood, white-cell casts plus fever, or sediment abnormalities with rapidly reduced urine output need same-day medical assessment. The urgency comes from the clinical pattern, not from a single “abnormal” laboratory flag.
Seek emergency care for visible blood with clots or inability to pass urine, fever with flank pain and vomiting, confusion, severe weakness, or markedly reduced urine output. These symptoms can indicate obstruction, kidney infection, severe dehydration, or systemic illness even before a final sediment report is available.
New swelling, breathlessness, blood pressure above 180/120 មមបារត, or an eGFR that drops by more than 25% from a known baseline should also prompt urgent clinician contact. The reason we worry about hematuria combined with albumin is that together they can indicate a glomerular process, whereas a few red cells alone often do not.
Thomas Klein, MD, advises patients to photograph or download the complete report before a repeat test; laboratory comments, collection time, and the exact units often disappear in portal summaries. If repeated kidney markers differ sharply, our guide to meaningful blood test changes can help frame the conversation.
When to repeat urine microscopy and what to ask for
A repeat clean-catch urinalysis is reasonable within days to weeks for a minor unexpected finding when you have no red-flag symptoms. Persistent abnormalities should be repeated with targeted testing rather than endlessly rechecking the same uncontextualised sample.
Wait at least 48 ទៅ 72 ម៉ោង after vigorous exercise before repeating a sample for unexplained blood, and avoid collection during menstrual bleeding when possible. For suspected infection, collect before the first antibiotic dose if you are stable enough to do so. If symptoms are severe, treatment should not be delayed to obtain a perfect specimen.
Useful follow-up questions include: Were red cells dysmorphic? Were casts seen? Is protein quantified by ACR or protein-creatinine ratio? Was culture performed, and was the sample contaminated? For recurrent crystals or stones, clinicians may add imaging and one or two 24-hour collections rather than relying on spot microscopy.
Kantesti, Our វេទិកាបកស្រាយសូចនាករជីវសាស្ត្រដោយ AI, helps users organise serial blood results and identify whether kidney-function values changed around an abnormal urine report. Methodology and clinical oversight are described in our ទិដ្ឋភាពទូទៅនៃការធ្វើឱ្យមានសុពលភាពផ្នែកវេជ្ជសាស្ត្រ; interpretation should still be reviewed with the clinician responsible for your care.
Pregnancy, children, and older adults need different context
Pregnancy, childhood, catheter use, and older age alter the threshold for follow-up because the risks and common causes differ. The same 10 WBC/HPF finding can call for a culture in pregnancy and observation in an asymptomatic non-pregnant adult.
Pregnancy deserves a lower threshold for culture because asymptomatic bacteriuria is associated with pyelonephritis and adverse pregnancy outcomes if untreated. Squamous cells remain a contamination clue, however, so a mixed-growth culture should often be repeated rather than automatically treated. Persistent protein or red cells in pregnancy needs obstetric review because blood pressure changes alter the differential.
In children, crystals can reflect low intake during fever but recurrent stones, hexagonal crystals, growth concerns, or a family history of kidney disease should lead to paediatric assessment. Older adults frequently have pyuria or bacteriuria without urinary symptoms; neither finding alone explains delirium, falls, or chronic fatigue.
As of September 24, 2026, I would encourage families to keep prior creatinine, ACR, culture, and imaging reports together rather than relying on memory. Kantesti's clinicians and reviewers are introduced through our ក្រុមប្រឹក្សាប្រឹក្សាវេជ្ជសាស្ត្រ, which supports careful interpretation rather than automatic treatment.
A practical checklist before you act on urine sediment
Before acting on urine sediment, confirm sample quality, symptoms, timing, dipstick results, kidney function, and whether the finding persists. This five-part check prevents both missed kidney disease and unnecessary antibiotics or scans.
First, ask whether the specimen was midstream, fresh, and collected away from menstruation or hard exercise. Second, match the sediment to symptoms: burning and frequency, colicky flank pain, fever, swelling, or no symptoms at all. Third, check dipstick protein and blood, ACR, creatinine, eGFR, pH, and culture where appropriate.
Fourth, look for a pattern that changes urgency: RBC casts, WBC casts with fever, renal tubular cells with rising creatinine, cystine crystals, or visible blood with clots. Fifth, arrange a repeat or referral that answers a specific question rather than simply repeating a panel. For culture decisions, our ការណែនាំការវិភាគទឹកនោមធៀបនឹងការបណ្ដុះទឹកនោម គឺជាដៃគូដ៏មានប្រយោជន៍។.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគតេស្តឈាមដោយ AI that helps connect blood chemistry trends to a urine report, but it cannot see your symptoms, examine you, or replace imaging and culture. For the technical approach behind our result interpretation, see the មគ្គុទេសក៍បច្ចេកវិទ្យា AI.
សំណួរដែលសួរញឹកញាប់
លទ្ធផលសំណល់ទឹកនោមធម្មតាគឺជាអ្វី?
លទ្ធផលទឹកនោមធម្មតាមានកោសិកាឈាមក្រហមពី ០ ទៅ ២ ក្នុងមួយវាលថាមពលខ្ពស់ 0 to 2 red blood cells per high-power field, កោសិកាឈាមសពី ០ ទៅ ៥ ក្នុងមួយវាលថាមពលខ្ពស់ 0 to 5 white blood cells per high-power field, និងអវត្តមានឬមានតែការលេចចេញដោយចៃដន្យនៃសារធាតុ hyaline casts absent or only occasional hyaline casts, អាស្រ័យលើមន្ទីរពិសោធន៍. ចំនួនតូចនៃកោសិកាអេពីថេលប្រភេទស្កuação squamous epithelial cells ឬគ្រីស្តាល់អុកសាឡាតកាល់ស្យូម calcium oxalate crystals អាចកើតមានក្នុងមនុស្សដែលមានសុខភាពល្អ. ចំនួនធម្មតាប្រែប្រួលតាមវិធីប្រមូលសំណាកនិងឧបករណ៍វិភាគរបស់មន្ទីរពិសោធន៍, ដូច្នេះចន្លោះនៃរបាយការណ៍ផ្ទាល់គឺជាការប្រៀបធៀបចម្បង. ការវិភាគទឹកនោមធម្មតាមិនរាប់បញ្ចូលគ្រប់ជំងឺតម្រងនោមឬផ្លូវទឹកនោមទេប្រសិនបើរោគសញ្ញាមានសារៈសំខាន់.
តើគ្រីស្តាល់ក្នុងទឹកនោមតែងតែជាសញ្ញានៃគ្រួសក្នុងតម្រងនោមដែរឬទេ?
ទេ គ្រីស្តាល់ក្នុងទឹកនោមមិនតែងតែមានន័យថាមានគ្រួសក្នុងតម្រងនោមទេ។ គ្រីស្តាល់កាល់ស្យូមអុកសាឡាត (calcium oxalate crystals) គឺជារឿងធម្មតាដែលមានទឹកនោមខាប់ ហើយអាចកើតឡើងដោយគ្មានគ្រួសអ្វីទាំងអស់ ខណៈពេលដែលគ្រីស្តាល់អាស៊ីតអ៊ុយរិក (uric acid crystals) ទំនងជាកើតមាននៅពេលដែល pH ទឹកនោមទាបជាងប្រហែល 5.5 ។ គ្រីស្តាល់កើតឡើងវិញរួមជាមួយនិងការឈឺចង្កេះ មានឈាមដែលអាចមើលឃើញ គ្រួសពីមុន ឬបរិមាណទឹកនោមទាប មានអត្ថន័យគ្លីនិកច្រើនជាង។ គ្រីស្តាល់ស៊ីស្ទីន (cystine crystals) រាងប្រាំមួយជ្រុង គឺជាករណីលើកលែង ដោយសារតែវាបង្ហាញពីជំងឺស៊ីស្ទីនយូរី (cystinuria) យ៉ាងខ្លាំង ហើយត្រូវការការវាយតម្លៃពីអ្នកជំនាញ។.
តើមានកោសិកាអេពីថេលក្នុងទឹកនោមប៉ុន្មានទើបជាកម្រិតខ្ពស់?
មិនមានតម្លៃខ្ពស់តែមួយដែលជាសកលសម្រាប់កោសិកាអេពីថេលៀលក្នុងទឹកនោមទេ ប៉ុន្តែមន្ទីរពិសោធន៍ជាច្រើនបានសម្គាល់កោសិកាអេពីថេលៀលរាងស្កuaçãoច្រើនជាងប្រហែល 5 ទៅ 15 កោសិកាក្នុងវាលថាមពលខ្ពស់ថាមានច្រើន។ កោសិកាស្កuaçãoជាធម្មតាបង្ហាញពីការមានការចម្លងរោគពីស្បែកឬផ្ទៃប្រដាប់បន្តពូជជាជាងជំងឺតម្រងនោម។ កោសិកាអេពីថេលៀលបំពង់តម្រងនោមមានសារសំខាន់ជាងជាពិសេសនៅពេលមានគ្រាប់រលាក នោមប្រូតេអ៊ីន ឬការកើនឡើង creatinine ស្រួចស្រាវក៏មានវត្តមានផងដែរ។ ការយកសំណាកបត់កណ្ដាលឡើងវិញជាញឹកញាប់អាចបកស្រាយលទ្ធផលកោសិកាអេពីថេលៀលដែលមិនបានរំពឹងទុក។.
អាចធ្វើឱ្យទឹកនោមមានកំណកខុសប្រក្រតីបានទេ?
បាទ/ចាស៎ ការខ្សោះជាតិទឹកអាចធ្វើឱ្យទឹកនោមប្រមូលផ្តុំ និងបង្កើនភាពមើលឃើញនៃ hyaline casts, crystals, និងកាកសំណល់កោសិកា។ វាក៏អាចបង្កើនទំនាញជាក់លាក់នៃទឹកនោមឱ្យលើសពី 1.020 និងធ្វើឱ្យឈាម ឬប្រូតេអ៊ីនក្នុងបរិមាណតិចងាយស្រួលក្នុងការរកឃើញ។ ការខ្សោះជាតិទឹកមិនអាចពន្យល់ពី red-cell casts, persistent significant proteinuria, ឬ sustained creatinine rise បានទេ។ មនុស្សដែលមានជំងឺបេះដូង ជំងឺតម្រងនោមដំណាក់កាលចុងក្រោយ ឬមានកម្រិតសូដ្យូមទាប គួរតែសួរគ្រូពេទ្យមុនពេលបង្កើនការទទួលទានសារធាតុរាវយ៉ាងច្រើន។.
តើការរកឃើញសំណល់ទឹកនោមអ្វីខ្លះដែលបន្ទាន់?
គ្រាប់ឈាមក្រហម គ្រាប់កោសិកាស ក្នុងករណីមានគ្រុនក្តៅ ឬឈឺចំហៀង ក្រពេញតំរងនោម ជាមួយនឹង ការកើនឡើង creatinine 0.3 mg/dL ក្នុងរយៈពេល 48 ម៉ោង ឬមានឈាមដែលអាចមើលឃើញ រួមជាមួយកំណកឈាម ត្រូវការការវាយតម្លៃពីវេជ្ជបណ្ឌិតជាបន្ទាន់។ ការថយចុះនៃបរិមាណទឹកនោម ក្អួត ឈឺចាប់ខ្លាំង ហើមថ្មី ភាន់ច្រលំ ឬសម្ពាធឈាមខ្ពស់ជាង 180/120 mmHg ធ្វើឱ្យស្ថានភាពកាន់តែបន្ទាន់។ គ្រីស្តាល់ អុកសាឡាតកាល់ស្យូមតែមួយ ឬគ្រាប់កោសិកាស 1 ទៅ 2 គ្រាប់ដោយគ្មានរោគសញ្ញា ជាធម្មតាមិនមែនជាករណីបន្ទាន់ទេ។ ភាពបន្ទាន់អាស្រ័យលើការរួមបញ្ចូលគ្នានៃរោគសញ្ញា ការអនុវត្តមុខងារតម្រងនោម កម្រិតប្រូតេអ៊ីន និងលំនាំ sediment។.
ខ្ញុំគួរប្រើថ្នាំអង់ទីប៊ីយូទិចសម្រាប់កោសិកាឈាមសក្នុងទឹកនោមដែរឬទេ?
កោសិកាឈាមសរ (WBC) ក្នុងទឹកនោម មិនគួរត្រូវបានព្យាបាលដោយថ្នាំអង់ទីប៊ីយទិចទេ លុះត្រាតែស្ថានភាពគ្លីនិកគាំទ្រការឆ្លងមេរោគ។ WBC ច្រើនជាង 5 ក្នុងមួយវាលថាមពលខ្ពស់ បង្ហាញពី pyuria ដែលអាចបណ្តាលមកពី គ្រួស ភាពកខ្វក់ ថ្នាំ ការឆ្លងមេរោគផ្លូវភេទ ការរលាកតម្រងនោម ឬការឆ្លងមេរោគបាក់តេរី។ ការណែនាំរបស់ IDSA ឆ្នាំ 2019 ណែនាំប្រឆាំងនឹងការព្យាបាល bacteriuria ដែលគ្មានរោគសញ្ញាចំពោះមនុស្សពេញវ័យភាគច្រើនដែលមិនមានផ្ទៃពោះ។ ការមានផ្ទៃពោះ និងនីតិវិធី urologic ដែលមានការវះកាត់តាមផែនការ គឺជាករណីលើកលែងដ៏សំខាន់ ដែលការព្យាបាលដោយផ្អែកលើវប្បធម៌ត្រូវបានណែនាំជាទូទៅ។.
ទទួលការវិភាគឈាមដោយ AI ដែលមានថាមពលថ្ងៃនេះ
ចូលរួមជាមួយអ្នកប្រើប្រាស់ជាង 2 លាននាក់នៅទូទាំងពិភពលោក ដែលទុកចិត្ត Kantesti សម្រាប់ការវិភាគលទ្ធផលតេស្តមន្ទីរពិសោធន៍ភ្លាមៗ និងត្រឹមត្រូវ។ ផ្ទុកឡើងលទ្ធផលពិនិត្យឈាមរបស់អ្នក ហើយទទួលការបកស្រាយយ៉ាងទូលំទូលាយនៃសញ្ញាសម្គាល់ (biomarkers) 15,000+ ក្នុងរយៈពេលប៉ុន្មានវិនាទី។.
📚 ឯកសារស្រាវជ្រាវដែលបានយោង
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026) ។ ឧបករណ៍វិភាគឈាមដោយAI៖ វិភាគសំណាកឈាម២.៥លាន | របាយការណ៍សុខភាពសកលឆ្នាំ ២០២៦ ។ Zenodo ។ https://doi.org/10.5281/zenodo.18175532.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). RDW Blood Test: Complete Guide to RDW-CV, MCV & MCHC. Zenodo. https://doi.org/10.5281/zenodo.18202598.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
📖 ឯកសារយោងវេជ្ជសាស្ត្រខាងក្រៅ
Barocas DA និងគ. (2020)។. Microhematuria: គោលការណ៍ណែនាំ AUA/SUFU.។ Journal of Urology។.
Nicolle LE et al. (2019). គោលការណ៍ណែនាំការអនុវត្តគ្លីនិកសម្រាប់ការគ្រប់គ្រងបាក់តេរី Asymptomatic: ការធ្វើបច្ចុប្បន្នភាពឆ្នាំ 2019 ដោយសមាគមជំងឺឆ្លងអាមេរិក.។ Clinical Infectious Diseases។.
KDIGO (2024)។. ប្រការណែនាំអនុវត្តគ្លីនិក KDIGO ឆ្នាំ 2024 ស្ដីពីការវាយតម្លៃ និងការគ្រប់គ្រងជំងឺតម្រងនោមរ៉ាំរ៉ៃ.។ Kidney International.
⚕️ ការបដិសេធផ្នែកវេជ្ជសាស្ត្រ
អត្ថបទនេះមានគោលបំណងសម្រាប់ការអប់រំប៉ុណ្ណោះ ហើយមិនមែនជាការផ្តល់ដំបូន្មានផ្នែកវេជ្ជសាស្ត្រទេ។ សូមពិគ្រោះជាមួយអ្នកផ្តល់សេវាសុខភាពដែលមានសមត្ថភាពជានិច្ច សម្រាប់ការសម្រេចចិត្តអំពីការធ្វើរោគវិនិច្ឆ័យ និងការព្យាបាល។.
សញ្ញាទុកចិត្ត E-E-A-T
បទពិសោធន៍
ការពិនិត្យព្យាបាលដោយវេជ្ជបណ្ឌិតលើដំណើរការការបកស្រាយលទ្ធផលមន្ទីរពិសោធន៍។.
ជំនាញ
ផ្តោតលើវិទ្យាសាស្ត្រមន្ទីរពិសោធន៍ថា សញ្ញាសម្គាល់ (biomarkers) មានឥរិយាបថយ៉ាងដូចម្តេចក្នុងបរិបទព្យាបាល។.
ភាពមានសិទ្ធិអំណាច
សរសេរដោយវេជ្ជបណ្ឌិត Thomas Klein ជាមួយការពិនិត្យឡើងវិញដោយវេជ្ជបណ្ឌិត Sarah Mitchell និងសាស្ត្រាចារ្យវេជ្ជបណ្ឌិត Hans Weber។.
ភាពគួរឱ្យទុកចិត្ត
ការបកស្រាយដោយផ្អែកលើភស្តុតាង ជាមួយផ្លូវបន្តតាមដានច្បាស់លាស់ ដើម្បីកាត់បន្ថយការភ័យខ្លាច។.