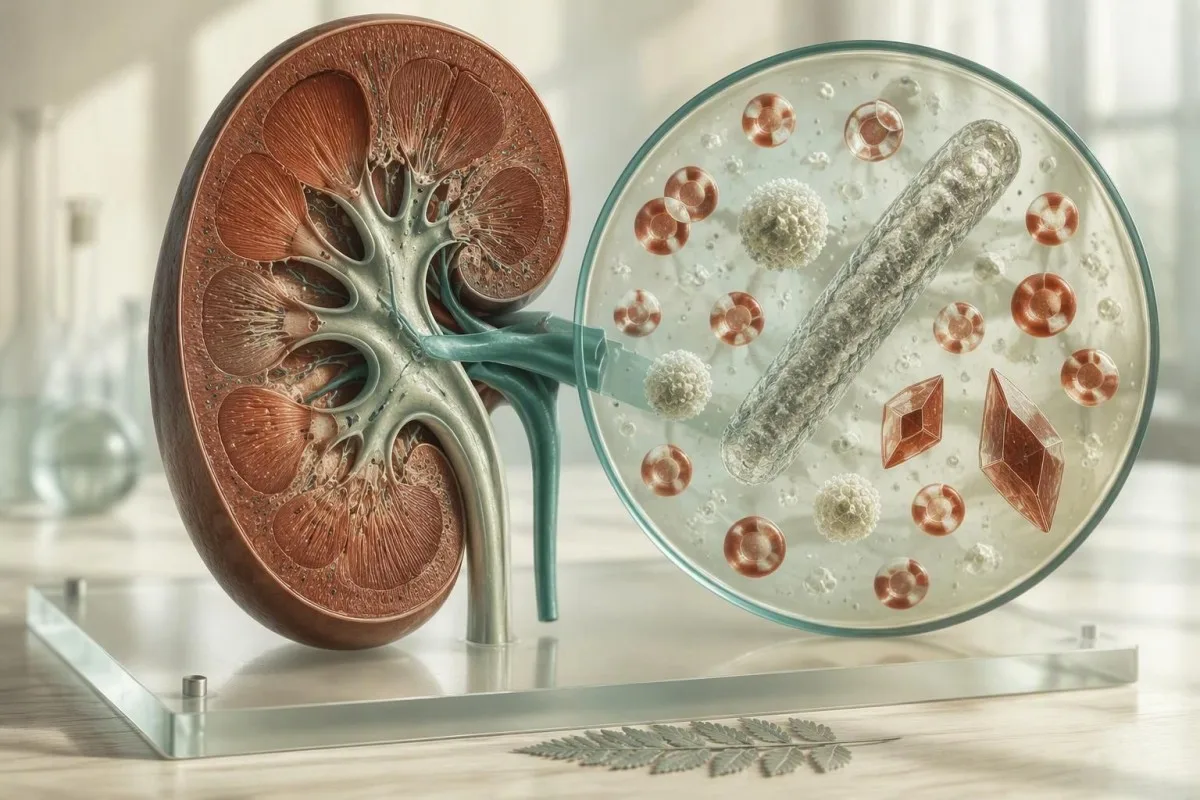
پيشاب جي خوردبيني ان وقت تمام گھڻي مفيد آھي جڏھن توھان س settingي نموني کي پڙھو: گڏ ڪرڻ جي معيار، علامتون، ڊپ اسٽڪ نتيجا، سيل، ڪاسٽ، ۽ ڪرسٽل. ھڪڙو اڪيلو پرچم ٿيل ذررو ڪڏهن به مڪمل ڪھاڻي نه ٻڌائيندو آھي.


- رت جا سيل صحيح طريقي سان گڏ ڪيل نموني ۾ اعليٰ پاور فيلڊ ۾ 3 کان مٿي AUA جي خوردبيني رت جي تعريف سان ملن ٿا ۽ انھن کي خطري جي بنياد تي فالو اپ جي ضرورت آھي.
- اڇا رت جا سيل اعليٰ پاور فيلڊ ۾ 5 کان مٿي پيوريا کي ظاھر ڪن ٿا، پر اڪيلي پيوريا پيشاب جي انفيڪشن کي ثابت نه ڪندو آھي.
- Unugyada epithelial ee squamous عام طور تي جلد يا جنيٽل مٿاڇري جي آلودگي مان ايندا آھن؛ گهڻا سيل اڪثر ڪري صاف-ڪيچ نموني ورجائڻ جي حقدار آھن.
- Unugyada epithelial ee tubular ee kelyaha غير معقوول آلودگي ۾ عام آھن ۽ پروٽين، ڪاسٽ، يا وڌندڙ ڪريٽينين سان گڏ ھجڻ تي وقت سر جائزي جي لائق آھن.
- ڪلسيم آڪسالٽ ڪرسٽلز عام آھن ۽ گردي جي پٿري جي تشخيص نه ڪندا آھن، جيتوڻيڪ بار بار ٿيندڙ ڪرسٽل ۽ علامتون پٿري جي خطري جي تشخيص جي لائق آھن.
- سڪل سيسٽين ڪرسٽل سيسٽينوريا جا مخصوص اشارا آھن ۽ انھن کي فوري طور تي ماھر جي تشخيص کي تيز ڪرڻ گھرجي.
- رت جي سيل جا ڪاسٽ گلوڪيولر رت وهڪڻ جو مشورو ڏئي ٿو، مثاني مان رت وهڻ جي بدران، ۽ فوري ڪلينڪل تشخيص جي ضرورت آهي.
- دير سان پروسيسنگ ڪرسٽل ٺاهي سگھن ٿا ۽ سيلز کي ٽوڙي سگھن ٿا؛ پيشاب کي مثالي طور تي 2 ڪلاڪن اندر جانچيو وڃي يا ريفريجريٽ ڪيو وڃي.
خوردبيني هيٺ پيشاب جي تائيندو ۾ اصل ۾ ڇا ڏيکاري ٿو
پيشاب جو رسيڊيم اھو مرڪوز مادو آھي جيڪو پيشاب کي گھمائڻ کان پوءِ باقي بچي ٿو ۽ خوردبين جي ھيٺان جانچيو وڃي ٿو، جنھن ۾ سيلز، ڪاسٽس، ڪرسٽل، جاندار ۽ ملبہ شامل آھن. اڪثر اڪيلو ننڍا نتيجا بي ضرر يا گڏ ڪرڻ سان لاڳاپيل هوندا آهن. جيڪي مجموعا اهم آهن اھي آھن پروٽين سان ڳاڙهي سيلز، علامتن سان اڇا سيلز، يا خراب ڪِڊني فنڪشن سان گردي جي سيلز ۽ ڪاسٽس.
ڊپ اسٽڪ هڪ ڪيميائي اسڪرين آهي، جڏهن ته پيشاب جي خوردبيني پڇي ٿو ته ڪهڙو جسماني مادو اصل ۾ موجود آهي. هڪ مثبت رت پيڊ ۾ ڳاڙهي سيلز، مفت هيموگلوبن، سخت عضلاتي زخم کان پوءِ مايوگلوبن، يا حتي حيض جي آلودگي پڻ ٿي سگهي ٿي؛ خوردبيني انهن امڪانن کي الڳ ڪري ٿي. اسان جو پيشاب جي چڪاس جي مڪمل گائيڊ بيان ڪري ٿو ته ڊپ اسٽڪ ۽ رسيڊيم جائز طور تي متفق ڇو نه ٿي سگھن.
منهنجي 15 سالن جي ڪلينڪل عمل ۾، مون نموني جي ڪهاڻي کي ڳڻتيءَ جيترو ئي قيمتي سمجهيو آهي: پهرين صبح جو يا دير سانپوءِ، 24 ڪلاڪن اندر ورزش، حيض، بخار، تازو جماع، ۽ ڇا نمونو گرم ڪائونٽر تي ويٺو هو. پيشاب جو pH گڏ ڪرڻ کان پوءِ مٿي وڃي سگهي ٿو، سيلز ليز ٿي سگهن ٿا، ۽ ڪلاڪن اندر نوان ڪرسٽل ٺهي سگهن ٿا.
ڪينٽيسٽي هڪ آهي اي آءِ بلڊ ٽيسٽ اينالائيزر جيڪا گردي سان لاڳاپيل رت جي مارڪرز جهڙوڪ ڪريٽينين، eGFR، بائي ڪاربونيٽ، ڪلسيم، ۽ يوريٽ کي رپورٽ ٿيل پيشاب جي رسيڊيم سان گڏ رکي ٿي. اھو تناظر اھم آھي ڇو ته ڪجھ ھائي لائن ڪاسٽس معمول جي گردي جي فنڪشن سان گڏ ڪاسٽس پلس تيزي سان وڌندڙ ڪريٽينين جي صورتحال کان تمام مختلف آھي.
ليبارٽريز فيلڊ آف وييو کي ڪيئن رپورٽ ڪن ٿا
اڪثر ليبارٽريز ٺهيل عنصرن کي في اعليِ پاور فيلڊ (HPF) سيلز جي طور تي رپورٽ ڪن ٿا، جڏهن ته خودڪار سسٽم في مائڪرولائٽر سيلز رپورٽ ڪري سگهن ٿا. 8 RBC/HPF جو نتيجو 8 RBC/µL سان سڌو سنئون ڀيٽ نه ٿو ڪري سگهجي ليبارٽري جي تبديليءَ واري طريقي کان سواءِ، تنهنڪري انٽرنيٽ جي وسيع “معمول” بدران ان ليبارٽري جي ريفرنس انٽروَل استعمال ڪريو.”
رت جا سيل: جڏهن خوردبيني جي رت کي منصوبي جي ضرورت هجي
امريڪي يورولوجيڪل ايسوسي ايشن جي تعريف موجب هڪ صحيح طريقي سان گڏ ڪيل پيشاب جي نموني تي في اعليِ پاور فيلڊ 3 کان وڌيڪ ڳاڙهي رت جي سيلز مائڪروسڪوپڪ هيماٽوريا آهن. اها ڪينسر جي تشخيص ناهي، پر مستقل هيماٽوريا کي ثبوت کان سواءِ “صرف UTI” جي طور تي رد نه ڪيو وڃي.
AUA/SUFU مائڪرو هيماٽوريا گائيڊ لائن ۾ 2025 جي ترميم ۾ حد مقرر ڪئي وئي آهي 3 RBC/HPF کان وڌيڪ ۽ سڀني لاءِ خودڪار اسڪيننگ جي بدران خطري تي ٻڌل تشخيص جي سفارش ڪري ٿي (Barocas et al., 2020؛ ترميم 2025). عمر، سگريٽ نوشي جي تاريخ، ظاهري رت، پيشي ۾ نمائش، ۽ مستقل مزاجي اڳتي وڌڻ جو ڪيترو طريقو طئي ڪن ٿا، ڳڻتي 4 يا 14 RBC/HPF هجڻ کان گهڻو وڌيڪ.
ڊسمورفڪ ڳاڙهي سيلز، خاص طور تي جھاگ وارا جھاگ، گلوڪيولر ذريعن ڏانهن اشارو ڪن ٿا؛ يونيفارم شڪل وارا ڳاڙهي سيلز وڌيڪ اڪثر پيشاب جي رستي ۾ هيٺان نڪرندا آهن. اها فرق آپريٽر تي منحصر آهي، ايمانداري سان، ۽ ڪيترائي معمول جا ليبارٽريز ان کي قابل اعتماد طور تي رپورٽ نٿا ڪن. ريڊ-سيل ڪاسٽس پلس پروٽينوريا ريڊ-سيل جي شڪل کان وڌيڪ، گلوڪيولر بيماري جو هڪ وڌيڪ قائل ڪندڙ سگنل آهن.
مان ڏٺل 29 سالن جي هڪ فاصلي واري ڊوڙندڙ ۾ ٽريل ريس کان پوءِ 18 RBC/HPF ۽ ڪو پروٽين، درد، يا پيشاب جي علامت نه هئي؛ 72 ڪلاڪن بعد ٻيهر ورتو ويو نمونو صاف هو. ورزش سان لاڳاپيل هيماٽوريا عام طور تي 48 کان 72 ڪلاڪن اندر ٺيڪ ٿي وڃي ٿو، پر ظاهري ڳاڙهي پيشاب، بار بار نتيجا، يا ان ونڊو کان پوءِ مستقل مزاجي مستحق آهي هيماٽوريا فالو اپ رستي.
پيشاب ۾ اڇا سيل: پيوريا پاڻمرادو UTI ناهي
More than 5 white blood cells per high-power field is commonly called pyuria, but pyuria alone cannot diagnose a urinary tract infection. Symptoms and, when needed, a properly collected culture determine whether antibiotics are useful.
A symptomatic person with dysuria, frequency, pyuria, and nitrite positivity has a substantially different probability of bacterial cystitis than an asymptomatic person with 10 WBC/HPF. Nitrite can be negative with frequent voiding, low dietary nitrate, or organisms that do not reduce nitrate, so a negative result does not rule out infection. The practical nuances are covered in our guide to ليڪوسائيٽ ايسٽريز منفي نائيٽرائٽ سان.
Sterile pyuria can occur with stones, sexually transmitted infections, tuberculosis in selected risk settings, interstitial nephritis, recent antibiotics, or sample contamination. WBC casts shift concern toward kidney-level inflammation, such as pyelonephritis or interstitial nephritis, particularly when fever, flank discomfort, creatinine change, or eosinophilia is present.
The 2019 IDSA guideline advises against screening for or treating asymptomatic bacteriuria in most non-pregnant adults, including older adults and people with diabetes; pregnancy and invasive urologic procedures are key exceptions (Nicolle et al., 2019). Treating a microscopy result rather than a clinical infection is a common route to side effects and resistant organisms.
When a culture adds value
A urine culture is most useful before antibiotics in pregnancy, suspected kidney infection, recurrent symptoms, complicated illness, or treatment failure. For uncomplicated first-episode cystitis in a non-pregnant adult, clinicians may reasonably treat based on a classic symptom pattern, but a sediment result cannot substitute for history.
پيشاب جي ايپيٿيل سيل: آلودگي بمقابله گردي جي زخم جا اشارا
Squamous epithelial cells usually indicate collection contamination, while renal tubular epithelial cells can indicate tubular injury when they are numerous or occur with granular casts. “Epithelial cells present” is therefore not a diagnosis; the cell type is the clinically useful part.
Squamous cells are broad, flat cells from the outer urethral or genital surface. There is no universal cutoff, though many laboratories flag “many” cells or counts above roughly 5 to 15/HPF; their presence makes bacteria and white-cell findings less trustworthy, not automatically abnormal. A careful midstream repeat after separating the labia or retracting the foreskin often settles the question.
Transitional or urothelial cells come from the bladder and ureters and may rise after catheterisation, stones, inflammation, or instrumentation. They are not equivalent to malignant cells. If a report says “atypical urothelial cells,” that is a cytology finding with a different threshold for action and should be reviewed directly with the ordering clinician.
Unugyada epithelial ee tubular ee kelyaha are smaller and more granular, and their presence becomes concerning with brown granular casts, proteinuria, or an acute creatinine increase. I would not diagnose acute kidney injury from a solitary reported cell, but I would review medicines, hydration, blood pressure, and repeat kidney labs promptly. Our detailed guide to epithelial cell types shows why reports should not lump them together.
پيشاب جي ڪاسٽ ظاھر ڪن ٿا ته تائيندو ڪٿي ٺھيو
Urine casts form inside kidney tubules, so their type often localises a problem to the kidney rather than the bladder. Hyaline casts can be normal; red-cell, white-cell, waxy, and abundant granular casts require much more context and often timely review.
Hyaline casts are largely made of uromodulin protein and 0 to 2 per low-power field can appear after exercise, fever, dehydration, or diuretic use. Their refractive, nearly transparent appearance means they are easily missed. In isolation, they do not establish kidney disease; see the practical distinction in our hyaline cast article.
Granular casts contain degraded cellular material. A few fine granular casts may appear transiently after strenuous exertion, but coarse “muddy brown” granular casts with an acute creatinine rise support acute tubular injury. The combination is stronger than either finding alone because it links tubular debris to reduced filtration.
Red-cell casts strongly support glomerulonephritis, while white-cell casts raise concern for pyelonephritis or interstitial nephritis. These are not home-monitoring findings. If casts accompany new swelling, blood pressure above 180/120 ملي ميٽر پارا (mmHg), reduced urine output, fever, or an eGFR drop, seek same-day medical assessment.
Why waxy casts deserve attention
Broad waxy casts are associated with slow urine flow in dilated tubules and are often seen in advanced chronic kidney disease. They do not measure kidney function by themselves, yet their appearance should prompt a review of eGFR, urine albumin-creatinine ratio, and prior results.
دانه دار ڪاسٽ ۽ گردي جا سيل: تيز گردي جي زخم جو نمونو
Muddy brown granular casts with renal tubular epithelial cells are a classic urine-sediment pattern of acute tubular injury. This pattern deserves urgent clinical correlation, especially when creatinine rises by at least 0.3 mg/dL (26.5 µmol/L) within 48 hours.
KDIGO defines acute kidney injury as a creatinine increase of 48 ڪلاڪن اندر 0.3 mg/dL يا وڌيڪ, a 1.5-fold rise within 7 days, or low urine output for 6 hours (KDIGO, 2024). Sediment does not replace those criteria, but it may help clinicians distinguish tubular injury from a purely haemodynamic fall in filtration.
ڪينٽيسٽي هڪ آهي AI ليب ٽيسٽ جي تشريح واري سروس that can flag a sediment report for clinician review when it appears alongside creatinine, potassium, bicarbonate, and eGFR changes. Our system does not diagnose the cause of kidney injury; medication exposure, obstruction, infection, contrast exposure, volume status, and baseline kidney function still require a clinician's judgment.
The detail patients often miss is timing. A sediment obtained after intravenous fluids or after creatinine has started falling may look less dramatic than the sample collected at the peak of illness. For a closer discussion of the finding itself, read about granular casts and next steps.
عام پيشاب جي ڪرسٽل: ڇا ڪلسيم اوڪسيليٽ ۽ يورڪ ائسڊ مطلب
Calcium oxalate and uric acid crystals are common urine findings and do not, by themselves, prove kidney stones. Their value increases when they recur with renal colic, visible blood, low urine volume, or a personal history of stones.
Calcium oxalate crystals may look like envelopes or dumbbells and can occur in acidic, neutral, or alkaline urine. They are often found in otherwise healthy people, particularly when a sample is concentrated. Repeated stones are more usefully assessed with urine volume, calcium, oxalate, citrate, sodium, and uric acid than with one microscopic crystal report.
Uric acid crystals favour acidic urine, often below pH 5.5, and may accompany hyperuricosuria, gout, high cellular turnover, or metabolic syndrome. A serum urate concentration can be normal in a person who forms uric acid stones; urine pH is frequently the more actionable clue. Our guide to high urine calcium and stone risk explains why a 24-hour collection is sometimes needed.
I caution against “flushing out crystals” with extreme water intake. For most stone formers, a practical target is urine output of at least 2.0 to 2.5 litres daily, adjusted for climate and medical conditions. Heart failure, advanced kidney disease, and hyponatraemia risk change that advice, so personalise it.
اسٽروائيٽ، سيسٽين، ۽ دوا جي ڪرسٽل کي تيز فالو اپ جي ضرورت آھي
Struvite crystals suggest alkaline urine in the setting of urease-producing bacterial infection, while hexagonal cystine crystals are highly specific for cystinuria. Both patterns warrant more than generic hydration advice.
Struvite crystals have a coffin-lid appearance and tend to occur in alkaline urine, often pH above 7.0, with infection by urease-producing organisms. A culture is necessary because microscopy cannot name the organism, and infection stones can enlarge quickly with surprisingly modest symptoms. Fever, flank pain, vomiting, or reduced urine output requires urgent evaluation.
Hexagonal cystine crystals are uncommon but highly characteristic of cystinuria, an inherited defect in amino-acid transport. They often appear in childhood or young adulthood, though diagnosis can be delayed for years. Confirmation uses quantitative urine cystine testing or genetic evaluation, usually through a stone or nephrology team.
Some medicines can crystallise in urine, especially when urine is concentrated or acidic; examples include older antivirals, sulfonamides, and high-dose methotrexate in specialist settings. The medication list is not a footnote here. A recurrent stone assessment often includes 24-hour urine citrate, as discussed in our low urine citrate guide.
گڏ ڪرڻ ۽ پروسيسنگ تائيندو جي نتيجي کي تبديل ڪري سگھي ٿي
A delayed, poorly collected, or highly dilute specimen can create misleading urine sediment results. Fresh midstream urine examined within 2 hours is preferred; if delay is unavoidable, refrigeration at 2–8°C helps preserve formed elements.
The first part of the urine stream carries more skin and urethral material, while the midstream portion better reflects bladder urine. For menstruating patients, a repeat sample after bleeding stops is generally more informative than trying to interpret a heavily contaminated specimen. Catheterised sampling is reserved for situations where a clean answer changes care.
At room temperature, bacteria multiply, pH may rise, cells degrade, and amorphous phosphate crystals may appear. Refrigeration can itself encourage precipitation of some crystals, which is why a laboratory needs to know storage conditions. A report of “crystals present” without collection timing is less persuasive than it looks.
Cloudiness is also not synonymous with infection; it may result from crystals, mucus, cells, semen, or benign phosphate precipitation. The visual causes and warning features are covered in our cloudy urine explanation.
ڊپ اسٽڪ ۽ پروٽين جي نتيجن سان پيشاب جي خوردبيني پڙھو
Urine sediment is safest to interpret alongside dipstick blood, protein, leukocyte esterase, nitrite, specific gravity, and pH. A pattern of blood plus protein is more concerning for kidney disease than either isolated result.
Dipstick protein mainly detects albumin and can miss light chains or very dilute samples. A first-morning urine albumin-creatinine ratio below 30 mg/g is considered normal to mildly increased; 30 to 300 mg/g is moderately increased, and above 300 mg/g is severely increased. Persistent albuminuria, not one post-exercise result, is what changes chronic kidney disease classification.
If dipstick blood is positive but microscopy finds zero or very few red cells, clinicians consider haemoglobinuria, myoglobinuria, oxidising contamination, or cell lysis in an old sample. After intense exercise, severe muscle pain, weakness, or cola-coloured urine with this pattern needs urgent testing for creatine kinase and kidney injury.
The combination of albuminuria and hematuria may justify nephrology input even with a preserved eGFR, especially if there is hypertension or family history. Our پيشاب ۾ پروٽين جي گائيڊ gives a practical way to prepare for repeat ACR testing.
پيشاب جو pH تشخيص نه، پر حوالي سان مهيا ڪري ٿو
Urine pH usually ranges from about 4.5 to 8.0, and a single pH result cannot diagnose a UTI or a stone type. Persistent acidity or alkalinity becomes useful when it matches crystals, culture results, diet, and 24-hour urine chemistry.
An acidic pH below 5.5 supports uric acid crystallisation, whereas alkaline urine may favour calcium phosphate or struvite formation. Vegetarian diets, vomiting, medications such as acetazolamide, and delayed testing can all shift pH. That is why I avoid assigning a stone composition from pH alone.
Persistent alkaline urine with recurrent calcium phosphate stones may lead clinicians to look for distal renal tubular acidosis, particularly if serum bicarbonate is low or potassium is abnormal. Conversely, acidic urine can be an important treatable risk in uric acid stone disease. These distinctions are developed in our urine pH results guide.
Kantesti AI interprets kidney-related laboratory patterns by comparing pH-associated sediment findings with serum bicarbonate, potassium, calcium, phosphate, and creatinine when those data are available. It can identify questions to take to a clinician, not determine stone chemistry or replace imaging.
تائيندو جا نمونا جن کي ساڳئي ڏينھن جي ڪلينڪل تشخيص جي ضرورت آھي
Red-cell casts, heavy protein with blood, white-cell casts plus fever, or sediment abnormalities with rapidly reduced urine output need same-day medical assessment. The urgency comes from the clinical pattern, not from a single “abnormal” laboratory flag.
Seek emergency care for visible blood with clots or inability to pass urine, fever with flank pain and vomiting, confusion, severe weakness, or markedly reduced urine output. These symptoms can indicate obstruction, kidney infection, severe dehydration, or systemic illness even before a final sediment report is available.
New swelling, breathlessness, blood pressure above 180/120 ملي ميٽر پارا (mmHg), or an eGFR that drops by more than 25% from a known baseline should also prompt urgent clinician contact. The reason we worry about hematuria combined with albumin is that together they can indicate a glomerular process, whereas a few red cells alone often do not.
Thomas Klein, MD, advises patients to photograph or download the complete report before a repeat test; laboratory comments, collection time, and the exact units often disappear in portal summaries. If repeated kidney markers differ sharply, our guide to meaningful blood test changes can help frame the conversation.
پيشاب جي خوردبيني کي ڪڏهن ورجائڻو آھي ۽ ڇا پڇڻو آھي
A repeat clean-catch urinalysis is reasonable within days to weeks for a minor unexpected finding when you have no red-flag symptoms. Persistent abnormalities should be repeated with targeted testing rather than endlessly rechecking the same uncontextualised sample.
Wait at least 48 کان 72 ڪلاڪن کان پوءِ after vigorous exercise before repeating a sample for unexplained blood, and avoid collection during menstrual bleeding when possible. For suspected infection, collect before the first antibiotic dose if you are stable enough to do so. If symptoms are severe, treatment should not be delayed to obtain a perfect specimen.
Useful follow-up questions include: Were red cells dysmorphic? Were casts seen? Is protein quantified by ACR or protein-creatinine ratio? Was culture performed, and was the sample contaminated? For recurrent crystals or stones, clinicians may add imaging and one or two 24-hour collections rather than relying on spot microscopy.
Kantesti، اسان AI بايو مارڪر تشريحي پليٽ فارم, helps users organise serial blood results and identify whether kidney-function values changed around an abnormal urine report. Methodology and clinical oversight are described in our طبي توثيق جو جائزو; interpretation should still be reviewed with the clinician responsible for your care.
حمل، ٻارن، ۽ وڏي عمر وارن کي مختلف حوالي سان ضرورت آھي
Pregnancy, childhood, catheter use, and older age alter the threshold for follow-up because the risks and common causes differ. The same 10 WBC/HPF finding can call for a culture in pregnancy and observation in an asymptomatic non-pregnant adult.
Pregnancy deserves a lower threshold for culture because asymptomatic bacteriuria is associated with pyelonephritis and adverse pregnancy outcomes if untreated. Squamous cells remain a contamination clue, however, so a mixed-growth culture should often be repeated rather than automatically treated. Persistent protein or red cells in pregnancy needs obstetric review because blood pressure changes alter the differential.
In children, crystals can reflect low intake during fever but recurrent stones, hexagonal crystals, growth concerns, or a family history of kidney disease should lead to paediatric assessment. Older adults frequently have pyuria or bacteriuria without urinary symptoms; neither finding alone explains delirium, falls, or chronic fatigue.
As of September 24, 2026, I would encourage families to keep prior creatinine, ACR, culture, and imaging reports together rather than relying on memory. Kantesti's clinicians and reviewers are introduced through our طبي صلاحڪار بورڊ, which supports careful interpretation rather than automatic treatment.
پيشاب جي تائيندو تي عمل ڪرڻ کان اڳ ھڪڙو عملي چيڪ لسٽ
Before acting on urine sediment, confirm sample quality, symptoms, timing, dipstick results, kidney function, and whether the finding persists. This five-part check prevents both missed kidney disease and unnecessary antibiotics or scans.
First, ask whether the specimen was midstream, fresh, and collected away from menstruation or hard exercise. Second, match the sediment to symptoms: burning and frequency, colicky flank pain, fever, swelling, or no symptoms at all. Third, check dipstick protein and blood, ACR, creatinine, eGFR, pH, and culture where appropriate.
Fourth, look for a pattern that changes urgency: RBC casts, WBC casts with fever, renal tubular cells with rising creatinine, cystine crystals, or visible blood with clots. Fifth, arrange a repeat or referral that answers a specific question rather than simply repeating a panel. For culture decisions, our يوريناليسس بمقابله يورين ڪلچر گائيڊ هڪ مفيد ساٿي آهي.
ڪينٽيسٽي هڪ آهي AI-powered رت جي ٽيسٽ تجزيي جو اوزار that helps connect blood chemistry trends to a urine report, but it cannot see your symptoms, examine you, or replace imaging and culture. For the technical approach behind our result interpretation, see the AI ٽيڪنالاجي گائيڊ.
وچان وچان سوال ڪرڻ
پيشاب جي عام نتيجن جو ڇا مطلب آهي؟
هڪ عام پيشاب جي تري جو نتيجو اعليٰ پاور فيلڊ ۾ 0 کان 2 ڳاڙها رت جا خليا، اعليٰ پاور فيلڊ ۾ 0 کان 5 سفيد رت جا خليا، ۽ ليبارٽري تي منحصر ڪري، غائب يا صرف ڪڏهن ڪڏهن هائلين کاسٽس کي ظاهر ڪري ٿو. صحت مند ماڻهن ۾ squamous epithelial خلين يا calcium oxalate بلورز جا ننڍا تعداد ٿي سگهن ٿا. عام حدون گڏ ڪرڻ جي طريقي ۽ ليبارٽري تجزيي ڪندڙ سان مختلف ٿين ٿيون، تنهنڪري رپورٽ جي پنهنجي وقفي جو مقابلو بنيادي آهي. علامتون اهم هجڻ جي صورت ۾ هڪ عام تري هر گردي يا پيشاب جي حالت کي رد نٿو ڪري.
ڇا پيشاب ۾ بلور هميشه گردن جي پٿرن جي نشاني آهن؟
نه، پيشاب ۾ ڳالهيون هجڻ جو مطلب هميشه گردن جي پٿري ناهي. گهڻي پيشاب ۾ ڪلسيم اوڪساليٽ ڳالهيون عام آهن ۽ بغير ڪنهن پٿري جي پڻ ٿي سگهن ٿيون، جڏهن ته پيشاب جي pH 5.5 کان گهٽ هجڻ تي يورڪ ايسڊ ڳالهيون وڌيڪ ممڪن آهن. بار بار ڳالهيون، پاسي ۾ درد، نظر ايندڙ رت، اڳوڻيون پٿريون، يا پيشاب جي گهٽ مقدار سان گڏ وڌيڪ طبي طور تي معنيٰ رکن ٿيون. سونهري سسٽين ڳالهيون هڪ استثنا آهن ڇاڪاڻ ته اهي سسٽينوريا جو زور سان مشورو ڏين ٿيون ۽ ماهرن جي تشخيص جي ضرورت آهي.
پيشاب ۾ ڪيتريون ايپيٿيليئل سيل اعليٰ سمجهيون وينديون آهن؟
پيشاب جي اپيٿيليئل سيلز لاءِ ڪو به واحد عالمگير اعليٰ ڪٽ آف ناهي، پر ڪيترائي ليبارٽريز 5 کان 15 اسڪوامس ايپيٿيليئل سيلز في هاءِ پاور فيلڊ کان وڌيڪ کي گهڻي تعداد ۾ سمجهن ٿا. اسڪوامس سيلز عام طور تي گردن جي بيماري بدران جلد يا جنيٽل سطحن مان آلودگي جي نشاندهي ڪن ٿا. رينل ٽيوبلر ايپيٿيليئل سيلز وڌيڪ اهم آهن، خاص طور تي جڏهن گرينولر ڪاسٽس، پروٽينوريا، يا ڪريٽينائن ۾ تيز اضافو پڻ موجود هجي. هڪ ٻي مڊ اسٽريم نموني اڪثر غير متوقع ايپيٿيليئل سيلز جي نتيجي کي واضح ڪري ٿي.
ڇا پاڻي گهٽجڻ ڪري پيشاب جي تري ۾ غير معمولي تبديليون اچي سگهن ٿيون؟
ها، dehydration پيشاب کي ڳاڙهو ڪري سگھي ٿو ۽ hyaline casts، crystals، ۽ cellular debris جي ڏسڻ واري صلاحيت کي وڌائي سگھي ٿو. اها پيشاب جي مخصوص ثقالت کي 1.020 کان مٿي وڌائي سگھي ٿي ۽ رت يا پروٽين جي ٿوري مقدار کي ڳولهڻ آسان بڻائي سگھي ٿي. Dehydration red-cell casts، مسلسل اهم proteinuria، يا creatinine ۾ مسلسل اضافو کي نٿي سمجهائي. دل جي ناڪامي، گردي جي بيماري، يا گهٽ سوڊيم وارن ماڻهن کي گهڻو پاڻي پيئڻ کان پهريان ڊاڪٽر کان پڇڻ گهرجي.
پيشاب ۾ ڪهڙا جز ڊاڪٽر کي فوراً ڏسڻ گهرجن؟
بخار يا پاسي جي درد سان گڏ ريڊ-سيل ڪاسٽ، وائيٽ-سيل ڪاسٽ، 48 ڪلاڪن اندر 0.3 mg/dL جي ڪريٽينين جي اضافي سان رينل ٽيوبلر سيلز، يا ڪلٽس سان ظاهر ٿيندڙ رت کي فوري طبي تشخيص جي ضرورت آهي. پيشاب جي گهٽتائي، الٽي، شديد درد، نئين سوزش، مونجهارو، يا 180/120 mmHg کان مٿي بلڊ پريشر صورتحال کي وڌيڪ ايمرجنسي بڻائي ٿو. اڪيلو ڪلسيم آڪسليٽ ڪرسٽل يا 1 کان 2 هائلين ڪاسٽ بغير علامتن جي عام طور تي ايمرجنسي ناهي. ايمرجنسي علامتن جي ميلاپ، گردن جي ڪم، پروٽين جي سطح، ۽ سيڊيمٽ پيٽرن تي منحصر آهي.
پيشاب ۾ سفيد رت جي سيلن لاءِ مون کي اينٽي بايوٽڪس وٺڻ گهرجن؟
پيشاب ۾ سفيد رت جا خانا (WBC) اينٽي بايوٽڪس سان علاج نه ڪيا وڃن جيستائين ڪلينڪل تصوير انفيڪشن جي حمايت نه ڪري. اعليٰ طاقت واري فيلڊ في (field) 5 WBC کان وڌيڪ پيوريا (pyuria) جي نشاندهي ڪري ٿو، جيڪا پٿري، آلودگي، دوائن، جنسي طور تي منتقل ٿيندڙ انفيڪشن، گردن جي سوزش، يا بيڪٽيريا جي انفيڪشن کان ٿي سگهي ٿي. 2019 IDSA گائيڊ لائن گهڻي ڀاڱي غير حامله بالغن ۾ بي سمپٽوميٽڪ بيڪٽيريوريا (asymptomatic bacteriuria) جي علاج جي خلاف تجويز ڪري ٿو. حمل ۽ منصوبابندي يوورولوجيڪل (urologic) طريقا اهم استثنا آهن جتي ڪلچر-گائيڊڊ علاج عام طور تي تجويز ڪيو ويندو آهي.
اڄ ئي AI-طاقتور خون جي جاچ جو تجزيو حاصل ڪريو
دنيا ڀر ۾ 2 ملين کان وڌيڪ استعمال ڪندڙن ۾ شامل ٿيو جيڪي فوري ۽ درست ليب ٽيسٽ تجزيو لاءِ Kantesti تي ڀروسو ڪن ٿا. پنهنجا خون جي جاچ جا نتيجا اپلوڊ ڪريو ۽ سيڪنڊن ۾ 15,000+ بائيو مارڪرز جي جامع تشريح حاصل ڪريو.
📚 حوالا ڏنل تحقيقي اشاعتون
ڪلين، ٽي.، مچل، ايس.، ۽ ويبر، ايڇ. (2026). Kantesti LTD. (2026). AI بلڊ ٽيسٽ تجزيه نگار: 2.5M ٽيسٽ جو تجزيو ڪيو ويو | گلوبل هيلٿ رپورٽ 2026. Zenodo. https://doi.org/10.5281/zenodo.18175532. Kantesti AI Medical Research.
ڪلين، ٽي.، مچل، ايس.، ۽ ويبر، ايڇ. (2026). Kantesti LTD. (2026). RDW بلڊ ٽيسٽ: RDW-CV، MCV ۽ MCHC جو مڪمل گائيڊ. Zenodo. https://doi.org/10.5281/zenodo.18202598. Kantesti AI Medical Research.
📖 ٻاهرين طبي حوالا
⚕️ طبي دستبرداري
هي آرٽيڪل صرف تعليمي مقصدن لاءِ آهي ۽ طبي مشورو نٿو بڻجي. تشخيص ۽ علاج جي فيصلن لاءِ هميشه ڪنهن قابل صحت فراهم ڪندڙ سان صلاح ڪريو.
E-E-A-T اعتماد جا سگنل
تجربو
ڊاڪٽر جي نگرانيءَ هيٺ ليبارٽري نتيجن جي تشريح واري عمل جو جائزو.
ماهر
ليبارٽري دوائن جو ڌيان ان ڳالهه تي ته بايو مارڪرز ڪلينڪل حوالي سان ڪيئن رويو ڏيکارين ٿا.
اختيار
ڊاڪٽر ٿامس ڪلين لکيو، ۽ ڊاڪٽر ساره مچل ۽ پروف. ڊاڪٽر هانس ويبر طرفان جائزو ورتل.
اعتبار
ثبوتن تي ٻڌل تشريح، جنهن سان خبرداري گهٽائڻ لاءِ واضح پيرويءَ جا رستا موجود هجن.