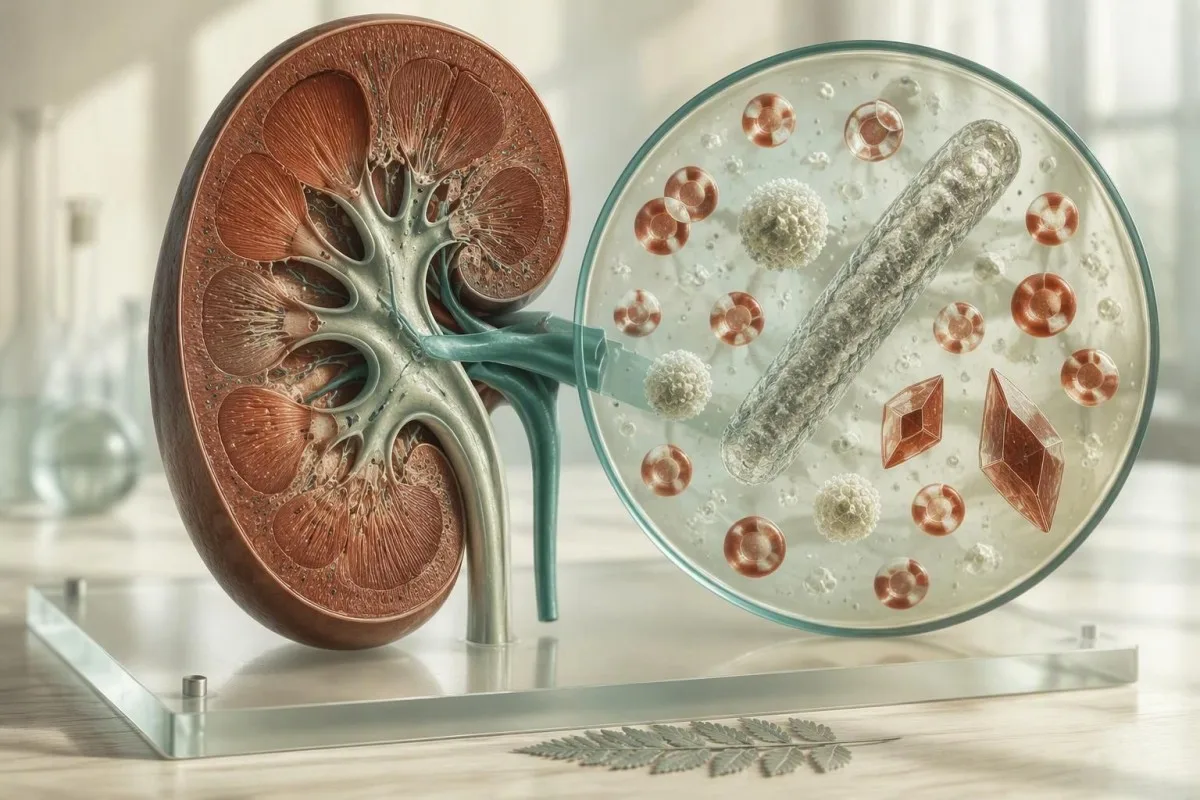
ဆီး၏အဏုကြည့်မှန်ပြောင်းဖြင့်စစ်ဆေးခြင်းသည် အလုံးစုံပုံစံကိုဖတ်ရှုသောအခါ အလွန်အသုံးဝင်ပါသည်- စုဆောင်းမှုအရည်အသွေး၊ လက္ခဏာများ၊ dipstick တွေ့ရှိချက်များ၊ ဆဲလ်များ၊ casts နှင့် crystals များ။ အလံပြထားသော အမှုန်တစ်စုံတစ်ရာသည် အပြည့်အဝ ဇာတ်လမ်းကို တစ်ခါတစ်ရံမှသာ ပြောပြပါသည်။.


- သွေးနီဥဆဲလ်များ မှန်ကန်စွာ စုဆောင်းထားသော နမူနာတွင် high-power field တစ်ခုလျှင် 3 ထက်ပိုနေပါက အဏုကြည့်မှန်ပြောင်းဖြင့် သွေးပါသောဆီး၏ AUA အဓိပ္ပာယ်ဖွင့်ဆိုချက်နှင့် ကိုက်ညီပြီး အန္တရာယ်အပေါ် အခြေခံသော နောက်ဆက်တွဲ လိုအပ်ပါသည်။.
- အဖြူရောင်သွေးဆဲလ်များ (white blood cells) high-power field တစ်ခုလျှင် 5 ထက်ပိုနေပါက pyuria ကို ညွှန်ပြပါသည်၊ သို့သော် pyuria တစ်ခုတည်းက ဆီးလမ်းကြောင်းပိုးဝင်ခြင်းကို မပြပါ။.
- Squamous epithelial ဆဲလ်များ အများအားဖြင့် အရေပြား သို့မဟုတ် မိန်းမ/ယောက်ျား ကိုယ်အင်္ဂါ မျက်နှာပြင် ညစ်ညမ်းမှုမှ လာပါသည်။ အများအပြားရှိသောဆဲလ်များသည် clean-catch နမူနာကို ပြန်လည်ပြုလုပ်ရန် အကြောင်းပြချက်ပေးလေ့ရှိပါသည်။.
- ကျောက်ကပ်ပြွန် epithelial ဆဲလ်များ ပုံမှန်မဟုတ်သော ညစ်ညမ်းမှုများတွင် မကြာခဏတွေ့ရလေ့မရှိပါ။ ပရိုတင်း၊ casts သို့မဟုတ် creatinine မြင့်တက်လာခြင်းနှင့် တွဲဖက်ပါက အချိန်မီ ပြန်လည်စစ်ဆေးသင့်ပါသည်။.
- ကယ်လ်စီယမ် အောက်ဆလိတ် (Calcium oxalate) ပုံဆောင်ခဲများ ကျောက်ကပ် ကျောက်ခဲကို ရောဂါမရှာဖွေသော်လည်း မကြာခဏဆိုသလို crystals များ နှင့် လက္ခဏာများ တွဲဖက်ပါက ကျောက်ခဲဖြစ်နိုင်ခြေကို အကဲဖြတ်သင့်ပါသည်။.
- Hexagonal cystine crystals cystinuria အတွက် အတိအကျ အရိပ်အမြွက်ဖြစ်ပြီး အထူးကုဆရာဝန်မှ အမြန်ဆုံး စစ်ဆေးသင့်ပါသည်။.
- Red-cell casts ဆီးအိမ်မှ သွေးထွက်ခြင်းထက် ကျောက်ကပ်လုံးဆိုင်ရာ သွေးထွက်ခြင်းကို အကြံပြုပြီး အရေးပေါ်ဆေးဘက်ဆိုင်ရာ အကဲဖြတ်ရန် လိုအပ်ပါသည်။.
- နောက်ကျပြီး လုပ်ဆောင်ခြင်း (Delayed processing) ကျောက်ခဲများဖြစ်ပေါ်စေပြီး ဆဲလ်များကို ပျက်စီးစေနိုင်သည်; ဆီးကို အကောင်းဆုံးအနေဖြင့် ၂ နာရီအတွင်း စစ်ဆေးသင့်သည် သို့မဟုတ် ရေခဲသေတ္တာတွင် ထည့်သင့်သည်။.
အဏုကြည့်မှန်ပြောင်းအောက်တွင် ဆီး sediment သည် တကယ်တမ်းတွင် အဘယ်အရာကို ပြသနေသနည်း
ဆီး sediment ဆိုသည်မှာ ဆီးကို လှည့်ပြီး အဏုကြည့်မှန်ပြောင်းဖြင့် ကြည့်ရှုပြီးနောက် ကျန်ရှိသော စုစည်းထားသော ပစ္စည်းများဖြစ်ပြီး ဆဲလ်များ၊ ပုံစံများ၊ ကျောက်ခဲများ၊ သက်ရှိများနှင့် အမှိုက်များ ပါဝင်သည်။. သီးခြားတွေ့ရှိမှု အများစုမှာ အန္တရာယ်ကင်းသည် သို့မဟုတ် စုဆောင်းမှုနှင့် ဆက်စပ်နေသည်၊ ပရိုတင်းနှင့်အတူ သွေးနီဥဆဲလ်များ၊ ရောဂါလက္ခဏာများနှင့်အတူ သွေးဖြူဥဆဲလ်များ၊ သို့မဟုတ် ကျောက်ကပ်လုပ်ငန်းဆောင်တာ ထိခိုက်မှုနှင့်အတူ ကျောက်ကပ်ဆဲလ်များနှင့် ပုံစံများ ပေါင်းစပ်မှုများသည် အရေးကြီးသည်။.
Dipstick ဆိုသည်မှာ ဓာတ်ခွဲစစ်ဆေးမှုတစ်ခုဖြစ်ပြီး ဆီး microscopy အမှန်တကယ်ပါဝင်သော ရုပ်ပိုင်းဆိုင်ရာ ပစ္စည်းကား အဘယ်နည်းဟု မေးသည်။ သွေး pad အပြုသဘောဆောင်ခြင်းသည် ကျန်းမာသော သွေးနီဥဆဲလ်များ၊ အခမဲ့ ဟီမိုဂလိုဘင်၊ ပြင်းထန်သော ကြွက်သားထိခိုက်ဒဏ်ရာရပြီးနောက် မိုင်ယိုဂလိုဘင်၊ သို့မဟုတ် ရာသီလာခြင်းညစ်ညမ်းမှုပင်လျှင် ထင်ဟပ်စေနိုင်သည်၊ microscopy သည် ဤဖြစ်နိုင်ခြေများကို ခွဲခြားသည်။ ကျွန်ုပ်တို့၏ ဆီးစစ်ခြင်းလမ်းညွှန်အပြည့်အစုံ dipstick နှင့် sediment တို့သည် အဘယ်ကြောင့် တရားဝင် မတူညီနိုင်သည်ကို ရှင်းပြသည်။.
ကျွန်ုပ်၏ဆေးဘက်ဆိုင်ရာ အလေ့အကျင့် ၁၅ နှစ်အတွင်း၊ ကျွန်ုပ်သည် နမူနာပုံပြင်သည် အရေအတွက်အတိုင်းပင် တန်ဖိုးရှိသည်ကို တွေ့ရှိခဲ့သည်- ပထမနံနက်နှင့် ညနေနောက်ပိုင်း၊ ၂၄ နာရီအတွင်း လေ့ကျင့်ခန်း၊ ရာသီလာခြင်း၊ ကိုယ်ပူခြင်း၊ မကြာသေးမီက လိင်ဆက်ဆံခြင်း၊ နှင့် နမူနာသည် ပူသော ကောင်တာပေါ်တွင် ထိုင်နေခဲ့သလား။ ဆီး pH သည် စုဆောင်းပြီးနောက် မြင့်တက်နိုင်သည်၊ ဆဲလ်များသည် ကွဲထွက်နိုင်သည်၊ နှင့် နာရီအနည်းငယ်အတွင်း အသစ်သော ကျောက်ခဲများ ကျဆင်းနိုင်သည်။.
ကန်တက်စတီသည် AI သွေးစမ်းသပ်မှုခွဲခြမ်းစိတ်ဖြာ ကျောက်ကပ်နှင့် ဆက်စပ်သော သွေးအမှတ်အသားများဖြစ်သည့် creatinine, eGFR, bicarbonate, calcium, နှင့် urate တို့ကို ဆီး sediment အစီရင်ခံစာနှင့်အတူ ထားရှိသည်။ ထိုအခြေအနေသည် အရေးကြီးသည်၊ အဘယ်ကြောင့်ဆိုသော် ပုံမှန်ကျောက်ကပ်လုပ်ငန်းဆောင်တာနှင့်အတူ hyaline casts အနည်းငယ်သည် ပုံစံများနှင့်အတူ ပုံမှန်မဟုတ်သော creatinine နှင့်အတူ အလွန်ကွဲပြားသော ဆေးဘက်ဆိုင်ရာ အခြေအနေဖြစ်သောကြောင့်ဖြစ်သည်။.
ဓာတ်ခွဲခန်းများသည် ကွင်းပြင်ကို မည်သို့ အစီရင်ခံသည်
ဓာတ်ခွဲခန်း အများစုသည် အလွန်အင်အားကြီးသော ကွင်းပြင် (HPF) အတွက် ဆဲလ်များအဖြစ် ပုံစံရှိသော ဒြပ်စင်များကို အစီရင်ခံကြသည်၊ အော်တိုမေးရှင်းစနစ်များသည် မைக்ခရိုလီတာအတွက် ဆဲလ်များကို အစီရင်ခံကြသည်။ 8 RBC/HPF ၏ ရလဒ်သည် ဓာတ်ခွဲခန်း၏ ပြောင်းလဲမှု နည်းလမ်းမပါဘဲ 8 RBC/µL နှင့် တိုက်ရိုက် နှိုင်းယှဉ်၍ မရနိုင်ပါ၊ ထို့ကြောင့် အင်တာနက်ကျယ်ပြန့်သော “ပုံမှန်” ထက် ထိုဓာတ်ခွဲခန်း၏ ကိုးကားချက် ကြားကာလကို အသုံးပြုပါ။”
သွေးနီဥဆဲလ်များ- အဏုကြည့်မှန်ပြောင်းဖြင့် သွေးပါသောဆီးသည် အစီအစဥ်တစ်ခု လိုအပ်သောအခါ
အမေရိကန် ကျောက်ကပ်ဆိုင်ရာ ခွဲစိတ်ဆရာဝန်များ အသင်း၏ အဓိပ္ပါယ်ဖွင့်ဆိုချက်အရ မှန်ကန်စွာ စုဆောင်းထားသော ဆီးနမူနာ တစ်ခုတွင် အလွန်အင်အားကြီးသော ကွင်းပြင်တစ်ခုလျှင် သွေးနီဥဆဲလ် 3 ခုထက် ပိုနေခြင်းသည် မိုက်ခရိုစကုပ် ဟေမိုတူးရီးယား ဖြစ်သည်။. ၎င်းသည် ကင်ဆာရောဂါကို အတည်ပြုခြင်း မဟုတ်သော်လည်း၊ ပ persistent ဟေမိုတူးရီးယားကို အထောက်အထားမပါဘဲ “UTI သာ” ဟု ပယ်ချသင့်သည် မဟုတ်ပါ။.
AUA/SUFU မိုက်ခရိုဟေမိုတူးရီးယား လမ်းညွှန်ချက်၏ 2025 ပြင်ဆင်ချက်သည် အကန့်ကို 3 RBC/HPF ထက် ပိုများသည်။ နှင့် အားလုံးအတွက် အလိုအလျောက် စကန်ဖတ်ခြင်းထက် အန္တရာယ်အပေါ် အခြေခံ၍ အကဲဖြတ်ခြင်းကို အကြံပြုသည် (Barocas et al., 2020; 2025 ပြင်ဆင်သည်)။ အသက်၊ ဆေးလိပ်သောက်သည့် ရာဇဝင်၊ သိသာသော သွေး၊ အလုပ်အကိုင်နှင့် ထိတွေ့မှု၊ နှင့် ပ persistent ဖြစ်မှုသည် အရေအတွက် 4 သို့မဟုတ် 14 RBC/HPF ဖြစ်သည်ထက် နောက်တစ်ဆင့်ကို ပိုမိုပုံဖော်သည်။.
Dysmorphic သွေးနီဥဆဲလ်များ၊ အထူးသဖြင့် membrane blebs ပါသော acanthocytes များသည် glomerular အရင်းအမြစ်ကို ညွှန်ပြသည်၊ တစ်ပုံစံတည်းဖြစ်သော သွေးနီဥဆဲလ်များသည် ဆီးလမ်းကြောင်းတွင် အောက်ပိုင်းမှ ပို၍ဖြစ်ပေါ်သည်။ ဤခွဲခြားမှုသည် လည်ပတ်သူပေါ် မူတည်သည်၊ ရိုးသားစွာပြောရလျှင်၊ နှင့် ပုံမှန်ဓာတ်ခွဲခန်းများစွာသည် ၎င်းကို ယုံကြည်စိတ်ချရစွာ မဖော်ပြပါ။. သွေးနီဥဆဲလ်-ပုံစံများ နှင့် ပရိုတင်းနူရီးယား သည် သွေးနီဥဆဲလ်ပုံစံထက် ကျောက်ကပ်လုံးဆိုင်ရာ ရောဂါကို ပိုမိုယုံကြည်စိတ်ချရသော အချက်ပြမှုဖြစ်သည်။.
ကျွန်ုပ်တွေ့ခဲ့သော အသက် 29 နှစ်အရွယ် အဝေးပြေးသမားတစ်ဦးသည် trail race တစ်ခုပြီးနောက် 18 RBC/HPF ရှိခဲ့ပြီး ပရိုတင်း၊ နာကျင်ခြင်း သို့မဟုတ် ဆီးရောဂါလက္ခဏာများ မရှိခဲ့ပါ။ 72 နာရီအကြာတွင် ပြန်လည်စစ်ဆေးသော နမူနာသည် ပျောက်ကင်းသွားသည်။ လေ့ကျင့်ခန်းနှင့် ဆက်စပ်သော ဟေမိုတူးရီးယားသည် ပုံမှန်အားဖြင့် 48 မှ 72 နာရီအတွင်း ပျောက်ကင်းသွားသော်လည်း၊ ထင်ရှားသော ဆီးနီရောင်၊ ထပ်တလဲလဲ ရလဒ်များ၊ သို့မဟုတ် ထိုအချိန်ထက် ကျော်လွန်၍ ပ persistent ဖြစ်နေခြင်းသည် ဟေမိုတူးရီးယား လိုက်နာဆောင်ရွက်မှု လမ်းကြောင်း.
ဆီးထဲတွင် သွေးဖြူဥဆဲလ်များ- pyuria သည် အလိုအလျောက် UTI မဟုတ်ပါ။
More than 5 white blood cells per high-power field is commonly called pyuria, but pyuria alone cannot diagnose a urinary tract infection. Symptoms and, when needed, a properly collected culture determine whether antibiotics are useful.
A symptomatic person with dysuria, frequency, pyuria, and nitrite positivity has a substantially different probability of bacterial cystitis than an asymptomatic person with 10 WBC/HPF. Nitrite can be negative with frequent voiding, low dietary nitrate, or organisms that do not reduce nitrate, so a negative result does not rule out infection. The practical nuances are covered in our guide to leukosye esterase နှင့် negative nitrite.
Sterile pyuria can occur with stones, sexually transmitted infections, tuberculosis in selected risk settings, interstitial nephritis, recent antibiotics, or sample contamination. WBC casts shift concern toward kidney-level inflammation, such as pyelonephritis or interstitial nephritis, particularly when fever, flank discomfort, creatinine change, or eosinophilia is present.
The 2019 IDSA guideline advises against screening for or treating asymptomatic bacteriuria in most non-pregnant adults, including older adults and people with diabetes; pregnancy and invasive urologic procedures are key exceptions (Nicolle et al., 2019). Treating a microscopy result rather than a clinical infection is a common route to side effects and resistant organisms.
When a culture adds value
A urine culture is most useful before antibiotics in pregnancy, suspected kidney infection, recurrent symptoms, complicated illness, or treatment failure. For uncomplicated first-episode cystitis in a non-pregnant adult, clinicians may reasonably treat based on a classic symptom pattern, but a sediment result cannot substitute for history.
ဆီးမှ အကျဉ်းဆဲလ်များ- ညစ်ညမ်းမှုနှင့် ကျောက်ကပ်ဒဏ်ရာ အရိပ်အမြွက်များ
Squamous epithelial cells usually indicate collection contamination, while renal tubular epithelial cells can indicate tubular injury when they are numerous or occur with granular casts. “Epithelial cells present” is therefore not a diagnosis; the cell type is the clinically useful part.
Squamous cells are broad, flat cells from the outer urethral or genital surface. There is no universal cutoff, though many laboratories flag “many” cells or counts above roughly 5 to 15/HPF; their presence makes bacteria and white-cell findings less trustworthy, not automatically abnormal. A careful midstream repeat after separating the labia or retracting the foreskin often settles the question.
Transitional or urothelial cells come from the bladder and ureters and may rise after catheterisation, stones, inflammation, or instrumentation. They are not equivalent to malignant cells. If a report says “atypical urothelial cells,” that is a cytology finding with a different threshold for action and should be reviewed directly with the ordering clinician.
ကျောက်ကပ်ပြွန် epithelial ဆဲလ်များ are smaller and more granular, and their presence becomes concerning with brown granular casts, proteinuria, or an acute creatinine increase. I would not diagnose acute kidney injury from a solitary reported cell, but I would review medicines, hydration, blood pressure, and repeat kidney labs promptly. Our detailed guide to epithelial cell types shows why reports should not lump them together.
ဆီး casts များသည် sediment မည်သည့်နေရာတွင် ဖြစ်ပေါ်ကြောင်းကို ဖော်ပြပါသည်။
Urine casts form inside kidney tubules, so their type often localises a problem to the kidney rather than the bladder. Hyaline casts can be normal; red-cell, white-cell, waxy, and abundant granular casts require much more context and often timely review.
Hyaline casts are largely made of uromodulin protein and 0 to 2 per low-power field can appear after exercise, fever, dehydration, or diuretic use. Their refractive, nearly transparent appearance means they are easily missed. In isolation, they do not establish kidney disease; see the practical distinction in our hyaline cast article.
Granular casts contain degraded cellular material. A few fine granular casts may appear transiently after strenuous exertion, but coarse “muddy brown” granular casts with an acute creatinine rise support acute tubular injury. The combination is stronger than either finding alone because it links tubular debris to reduced filtration.
Red-cell casts strongly support glomerulonephritis, while white-cell casts raise concern for pyelonephritis or interstitial nephritis. These are not home-monitoring findings. If casts accompany new swelling, blood pressure above 180/120 mmHg, reduced urine output, fever, or an eGFR drop, seek same-day medical assessment.
Why waxy casts deserve attention
Broad waxy casts are associated with slow urine flow in dilated tubules and are often seen in advanced chronic kidney disease. They do not measure kidney function by themselves, yet their appearance should prompt a review of eGFR, urine albumin-creatinine ratio, and prior results.
Granular casts နှင့် ကျောက်ကပ်ဆဲလ်များ- အဆုတ်ရောင်ကျောက်ကပ်ဒဏ်ရာ ပုံစံ
Muddy brown granular casts with renal tubular epithelial cells are a classic urine-sediment pattern of acute tubular injury. This pattern deserves urgent clinical correlation, especially when creatinine rises by at least 0.3 mg/dL (26.5 µmol/L) within 48 hours.
KDIGO defines acute kidney injury as a creatinine increase of ၄၈ နာရီအတွင်း 0.3 mg/dL သို့မဟုတ် ထိုထက်ပို, a 1.5-fold rise within 7 days, or low urine output for 6 hours (KDIGO, 2024). Sediment does not replace those criteria, but it may help clinicians distinguish tubular injury from a purely haemodynamic fall in filtration.
ကန်တက်စတီသည် AI ဓာတ်ခွဲခန်း စစ်ဆေးမှု အနက်ဖွင့် ဝန်ဆောင်မှု that can flag a sediment report for clinician review when it appears alongside creatinine, potassium, bicarbonate, and eGFR changes. Our system does not diagnose the cause of kidney injury; medication exposure, obstruction, infection, contrast exposure, volume status, and baseline kidney function still require a clinician's judgment.
The detail patients often miss is timing. A sediment obtained after intravenous fluids or after creatinine has started falling may look less dramatic than the sample collected at the peak of illness. For a closer discussion of the finding itself, read about granular casts and next steps.
ဆီး crystals များ- ကယ်လ်စီယမ် oxalate နှင့် ယူရစ်အက်ဆစ်တို့၏ အဓိပ္ပာယ်
Calcium oxalate and uric acid crystals are common urine findings and do not, by themselves, prove kidney stones. Their value increases when they recur with renal colic, visible blood, low urine volume, or a personal history of stones.
Calcium oxalate crystals may look like envelopes or dumbbells and can occur in acidic, neutral, or alkaline urine. They are often found in otherwise healthy people, particularly when a sample is concentrated. Repeated stones are more usefully assessed with urine volume, calcium, oxalate, citrate, sodium, and uric acid than with one microscopic crystal report.
Uric acid crystals favour acidic urine, often below pH 5.5 အောက်, and may accompany hyperuricosuria, gout, high cellular turnover, or metabolic syndrome. A serum urate concentration can be normal in a person who forms uric acid stones; urine pH is frequently the more actionable clue. Our guide to high urine calcium and stone risk explains why a 24-hour collection is sometimes needed.
I caution against “flushing out crystals” with extreme water intake. For most stone formers, a practical target is urine output of at least 2.0 to 2.5 litres daily, adjusted for climate and medical conditions. Heart failure, advanced kidney disease, and hyponatraemia risk change that advice, so personalise it.
Struvite, cystine နှင့် ဆေးဝါး crystals များသည် ပိုမိုမြန်ဆန်သော နောက်ဆက်တွဲ လိုအပ်ပါသည်။
Struvite crystals suggest alkaline urine in the setting of urease-producing bacterial infection, while hexagonal cystine crystals are highly specific for cystinuria. Both patterns warrant more than generic hydration advice.
Struvite crystals have a coffin-lid appearance and tend to occur in alkaline urine, often pH above 7.0, with infection by urease-producing organisms. A culture is necessary because microscopy cannot name the organism, and infection stones can enlarge quickly with surprisingly modest symptoms. Fever, flank pain, vomiting, or reduced urine output requires urgent evaluation.
Hexagonal cystine crystals are uncommon but highly characteristic of cystinuria, an inherited defect in amino-acid transport. They often appear in childhood or young adulthood, though diagnosis can be delayed for years. Confirmation uses quantitative urine cystine testing or genetic evaluation, usually through a stone or nephrology team.
Some medicines can crystallise in urine, especially when urine is concentrated or acidic; examples include older antivirals, sulfonamides, and high-dose methotrexate in specialist settings. The medication list is not a footnote here. A recurrent stone assessment often includes 24-hour urine citrate, as discussed in our low urine citrate guide.
စုဆောင်းခြင်းနှင့် ပြုပြင်ခြင်းသည် sediment ရလဒ်ကို ပြောင်းလဲနိုင်သည်။
A delayed, poorly collected, or highly dilute specimen can create misleading urine sediment results. Fresh midstream urine examined within 2 hours is preferred; if delay is unavoidable, refrigeration at 2–8°C helps preserve formed elements.
The first part of the urine stream carries more skin and urethral material, while the midstream portion better reflects bladder urine. For menstruating patients, a repeat sample after bleeding stops is generally more informative than trying to interpret a heavily contaminated specimen. Catheterised sampling is reserved for situations where a clean answer changes care.
At room temperature, bacteria multiply, pH may rise, cells degrade, and amorphous phosphate crystals may appear. Refrigeration can itself encourage precipitation of some crystals, which is why a laboratory needs to know storage conditions. A report of “crystals present” without collection timing is less persuasive than it looks.
Cloudiness is also not synonymous with infection; it may result from crystals, mucus, cells, semen, or benign phosphate precipitation. The visual causes and warning features are covered in our cloudy urine explanation.
ဆီး dipstick နှင့် ပရိုတင်း ရလဒ်များနှင့်အတူ ဆီး microscopy ကိုဖတ်ရှုပါ။
Urine sediment is safest to interpret alongside dipstick blood, protein, leukocyte esterase, nitrite, specific gravity, and pH. A pattern of blood plus protein is more concerning for kidney disease than either isolated result.
Dipstick protein mainly detects albumin and can miss light chains or very dilute samples. A first-morning urine albumin-creatinine ratio below 30 mg/g is considered normal to mildly increased; 30 to 300 mg/g is moderately increased, and above 300 mg/g is severely increased. Persistent albuminuria, not one post-exercise result, is what changes chronic kidney disease classification.
If dipstick blood is positive but microscopy finds zero or very few red cells, clinicians consider haemoglobinuria, myoglobinuria, oxidising contamination, or cell lysis in an old sample. After intense exercise, severe muscle pain, weakness, or cola-coloured urine with this pattern needs urgent testing for creatine kinase and kidney injury.
The combination of albuminuria and hematuria may justify nephrology input even with a preserved eGFR, especially if there is hypertension or family history. Our ဆီးထဲရှိ ပရိုတိန်း လမ်းညွှန် gives a practical way to prepare for repeat ACR testing.
ဆီး pH သည် ရောဂါရှာဖွေမှုကို မပေးပါ၊ နောက်ခံအခြေအနေကိုသာ ပေးပါသည်။
Urine pH usually ranges from about 4.5 to 8.0, and a single pH result cannot diagnose a UTI or a stone type. Persistent acidity or alkalinity becomes useful when it matches crystals, culture results, diet, and 24-hour urine chemistry.
An acidic pH below 5.5 supports uric acid crystallisation, whereas alkaline urine may favour calcium phosphate or struvite formation. Vegetarian diets, vomiting, medications such as acetazolamide, and delayed testing can all shift pH. That is why I avoid assigning a stone composition from pH alone.
Persistent alkaline urine with recurrent calcium phosphate stones may lead clinicians to look for distal renal tubular acidosis, particularly if serum bicarbonate is low or potassium is abnormal. Conversely, acidic urine can be an important treatable risk in uric acid stone disease. These distinctions are developed in our urine pH results guide.
Kantesti AI interprets kidney-related laboratory patterns by comparing pH-associated sediment findings with serum bicarbonate, potassium, calcium, phosphate, and creatinine when those data are available. It can identify questions to take to a clinician, not determine stone chemistry or replace imaging.
တစ်ရက်တည်း လူနာစစ်ဆေးမှု လိုအပ်သော Sediment ပုံစံများ
Red-cell casts, heavy protein with blood, white-cell casts plus fever, or sediment abnormalities with rapidly reduced urine output need same-day medical assessment. The urgency comes from the clinical pattern, not from a single “abnormal” laboratory flag.
Seek emergency care for visible blood with clots or inability to pass urine, fever with flank pain and vomiting, confusion, severe weakness, or markedly reduced urine output. These symptoms can indicate obstruction, kidney infection, severe dehydration, or systemic illness even before a final sediment report is available.
New swelling, breathlessness, blood pressure above 180/120 mmHg, or an eGFR that drops by more than 25% from a known baseline should also prompt urgent clinician contact. The reason we worry about hematuria combined with albumin is that together they can indicate a glomerular process, whereas a few red cells alone often do not.
Thomas Klein, MD, advises patients to photograph or download the complete report before a repeat test; laboratory comments, collection time, and the exact units often disappear in portal summaries. If repeated kidney markers differ sharply, our guide to meaningful blood test changes can help frame the conversation.
ဆီး microscopy ကို မည်သည့်အခါ ပြန်လည်ပြုလုပ်သင့်သနည်း နှင့် မည်သည့်အရာကို တောင်းဆိုသင့်သနည်း
A repeat clean-catch urinalysis is reasonable within days to weeks for a minor unexpected finding when you have no red-flag symptoms. Persistent abnormalities should be repeated with targeted testing rather than endlessly rechecking the same uncontextualised sample.
Wait at least ကျောက်တုံးတစ်ခု ခဏလေးနဲ့ ဖြတ်သွားပြီး (transient stone pass) နာကျင်မှု လျော့သွားပေမယ့် ဓာတ်ခွဲခန်းရလဒ်တွေက ရက်အနည်းငယ်ကြာ ထူးဆန်းနေတတ်တာကို ကျွန်တော်မြင်ဖူးပါတယ်။ ဒါကြောင့် 48 to 72 hours အကြာမှာ after vigorous exercise before repeating a sample for unexplained blood, and avoid collection during menstrual bleeding when possible. For suspected infection, collect before the first antibiotic dose if you are stable enough to do so. If symptoms are severe, treatment should not be delayed to obtain a perfect specimen.
Useful follow-up questions include: Were red cells dysmorphic? Were casts seen? Is protein quantified by ACR or protein-creatinine ratio? Was culture performed, and was the sample contaminated? For recurrent crystals or stones, clinicians may add imaging and one or two 24-hour collections rather than relying on spot microscopy.
Kantesti, our AI biomarker အဓိပ္ပာယ်ဖော်ခြင်း ပလက်ဖောင်း, helps users organise serial blood results and identify whether kidney-function values changed around an abnormal urine report. Methodology and clinical oversight are described in our ဆေးဘက်ဆိုင်ရာ အတည်ပြုခြင်း ခြုံငုံသုံးသပ်ချက်; interpretation should still be reviewed with the clinician responsible for your care.
ကိုယ်ဝန်ဆောင်များ၊ ကလေးများ နှင့် သက်ကြီးရွယ်အိုများအတွက် မတူညီသော နောက်ခံအခြေအနေများ လိုအပ်ပါသည်။
Pregnancy, childhood, catheter use, and older age alter the threshold for follow-up because the risks and common causes differ. The same 10 WBC/HPF finding can call for a culture in pregnancy and observation in an asymptomatic non-pregnant adult.
Pregnancy deserves a lower threshold for culture because asymptomatic bacteriuria is associated with pyelonephritis and adverse pregnancy outcomes if untreated. Squamous cells remain a contamination clue, however, so a mixed-growth culture should often be repeated rather than automatically treated. Persistent protein or red cells in pregnancy needs obstetric review because blood pressure changes alter the differential.
In children, crystals can reflect low intake during fever but recurrent stones, hexagonal crystals, growth concerns, or a family history of kidney disease should lead to paediatric assessment. Older adults frequently have pyuria or bacteriuria without urinary symptoms; neither finding alone explains delirium, falls, or chronic fatigue.
As of September 24, 2026, I would encourage families to keep prior creatinine, ACR, culture, and imaging reports together rather than relying on memory. Kantesti's clinicians and reviewers are introduced through our ဆေးဘက်ဆိုင်ရာအကြံပေးဘုတ်အဖွဲ့, which supports careful interpretation rather than automatic treatment.
ဆီး sediment အပေါ် အရေးယူဆောင်ရွက်ခြင်း မပြုမီ လက်တွေ့အသုံးပြုနိုင်သော Check list
Before acting on urine sediment, confirm sample quality, symptoms, timing, dipstick results, kidney function, and whether the finding persists. This five-part check prevents both missed kidney disease and unnecessary antibiotics or scans.
First, ask whether the specimen was midstream, fresh, and collected away from menstruation or hard exercise. Second, match the sediment to symptoms: burning and frequency, colicky flank pain, fever, swelling, or no symptoms at all. Third, check dipstick protein and blood, ACR, creatinine, eGFR, pH, and culture where appropriate.
Fourth, look for a pattern that changes urgency: RBC casts, WBC casts with fever, renal tubular cells with rising creatinine, cystine crystals, or visible blood with clots. Fifth, arrange a repeat or referral that answers a specific question rather than simply repeating a panel. For culture decisions, our ဆီးခွဲခြမ်းစိတ် ပုံစံ နှင့် ဆီးခွဲ dilution ၏ နှိုင်းယှဉ်မှု နှင့် နှိုင်းယှဉ်ပါ က အထောက်အကူပြု လမ်းညွှန်တစ်ခုပါ။.
ကန်တက်စတီသည် AI-powered သွေးစစ်ဆေးမှု ခွဲခြမ်းစိတ်ဖြာ ကိရိယာ that helps connect blood chemistry trends to a urine report, but it cannot see your symptoms, examine you, or replace imaging and culture. For the technical approach behind our result interpretation, see the AI နည်းပညာ လမ်းညွှန်.
အမေးများသောမေးခွန်းများ
ပုံမှန်ဆီး sediment ရလဒ်ဆိုတာ ဘာလဲ။
ပုံမှန် ဆီးကျောက်ခဲများ စစ်ဆေးမှုရလဒ်တွင် မြင်ကွင်းကျယ်ရှိသော ဆဲလ်များ (high-power field) အတွက် သွေးနီဥ 0 မှ 2၊ သွေးဖြူဥ 0 မှ 5 နှင့် အဖြစ်နည်းသော hyaline casts များ ပါဝင်လေ့ရှိပြီး ဓာတ်ခွဲခန်းအပေါ်မူတည်ပါသည်။ ကျန်းမာသောသူများတွင် ကျောက်ခဲပြားပုံ အခွေဆဲလ်များ သို့မဟုတ် ကယ်လ်စီယမ် အောက်ဆာလိတ် ပုံဆောင်ခဲများ အနည်းငယ် ပေါ်လာနိုင်ပါသည်။ ပုံမှန်ကန့်သတ်ချက်များသည် စုဆောင်းသည့်နည်းလမ်းနှင့် ဓာတ်ခွဲခန်းသုံး ခွဲခြမ်းစိတ်ဖြာသည့်စက် (analyzer) အပေါ်မူတည်၍ ကွဲပြားနိုင်သောကြောင့် အစီရင်ခံစာ၏ကိုယ်ပိုင် ကန့်သတ်ချက်သည် အဓိက နှိုင်းယှဉ်စရာဖြစ်သည်။ လက္ခဏာများ သိသာထင်ရှားပါက ပုံမှန် sediment သည် ကျောက်ကပ် သို့မဟုတ် ဆီးလမ်းကြောင်းဆိုင်ရာ အခြေအနေတိုင်းကို ပယ်ဖျက်နိုင်မည် မဟုတ်ပါ။.
ကျောက်ကပ်အတွင်း၌ ပုံဆောင်ခဲများဖြစ်ပေါ်ခြင်းသည် ကျောက်ကပ်ကျောက်တည်ခြင်း၏ လက္ခဏာတစ်ရပ် ဟုတ်ပါသလား။
မဟုတ်ပါ၊ ဆီးကျောက်ခရမ်းခန့်များရှိတိုင်း ကျောက်ကပ်ကျောက်များ ဖြစ်သည်ဟု မဆိုလိုပါ။ ကယ်လ်စီယမ် အောက်ဆாலே ခရမ်းခန့်များသည် ဆီးရည်ကျဲပါက အဖြစ်များပြီး ကျောက်လုံးမပါဘဲ ဖြစ်ပေါ်နိုင်သည်၊ အခြားတစ်ဖက်တွင် ယူရစ်အက်ဆစ် ခရမ်းခန့်များသည် ဆီး pH သည် ၅.၅ အောက်ခန့်ရှိသောအခါ ပိုမိုဖြစ်ပေါ်လေ့ရှိပါသည်။ ထပ်ခါထပ်ခါဖြစ်ပေါ်သော ခရမ်းခန့်များသည် ဘေးချင်း နာကျင်မှု၊ သွေးပါဝင်မှု၊ ယခင်က ကျောက်များရှိခဲ့ခြင်း သို့မဟုတ် ဆီးပမာဏ နည်းပါးခြင်းတို့နှင့်အတူ ဖြစ်ပေါ်ပါက ဆေးပညာအရ ပိုမိုအရေးကြီးပါသည်။ ဆ hexagonal cystine crystals သည် ၎င်းတို့သည် cystinuria ကို အကြ sterkly ညွှန်ပြပြီး အထူးကုဆရာဝန်၏ ဆန်းစစ်မှု လိုအပ်သောကြောင့် ခြွင်းချက်တစ်ခုဖြစ်သည်။.
ဆီးထဲတွင် အကျဉ်းအထပ်တစ်ရှူးဆဲလ်အရေအတွက် မည်မျှများလျှင် များသည်ဟု သတ်မှတ်ပါသလဲ။
ဆီးအတွင်းရှိ အကျည်းလမ်းဆဲလ်များအတွက် တစ်ခုတည်းသော စကြဝဠာဆိုင်ရာ အမြင့်ဆုံးကန့်သတ်ချက်မရှိသော်လည်း၊ ဓာတ်ခွဲခန်းအများစုသည် မြင့်မားသောပါဝါနယ်ပယ်တစ်ခုလျှင် ကျန်းမာရေးနှင့်မညီညွတ်သော ဆဲလ် 5 မှ 15 ထက်ပိုသော အကျည်းလမ်းဆဲလ်များကို ပေါများသည်ဟု သတ်မှတ်သည်။ ကျန်းမာရေးနှင့်မညီညွတ်သော ဆဲလ်များသည် ကျောက်ကပ်ရောဂါထက် အရေပြား သို့မဟုတ် မိန်းမကိုယ်၏ မျက်နှာပြင်များမှ ညစ်ညမ်းမှုကို ညွှန်ပြလေ့ရှိသည်။ ကျောက်ကပ်ပြွန်ဆဲလ်များသည် ပို၍အရေးကြီးသည်၊ အထူးသဖြင့် သဲလုံးများ၊ ပရိုတင်းများ သို့မဟုတ် creatinine ၏ သိသာစွာမြင့်တက်မှုနှင့်အတူ ရှိနေသောအခါ။ အံ့သြဖွယ် epithelial-cell ရလဒ်ကို မကြာခဏဆိုသလို ထပ်ခါတလဲလဲ စစ်ဆေးခြင်းဖြင့် ရှင်းလင်းစေပါသည်။.
ရေဓာတ်ခမ်းခြောက်ခြင်းက ပုံမှန်မဟုတ်သော ဆီးအနည်အနှစ်ကို ဖြစ်စေနိုင်သလား။
ဟုတ်ပါသည်၊ ခန္ဓာကိုယ်တွင်းရေဓာတ်ခမ်းခြောက်ခြင်းက ဆီးကို ပိုမိုသိပ်သည်းစေပြီး hyaline casts၊ crystals နှင့် cellular debris များကို ပိုမိုမြင်သာစေနိုင်သည်။ ဆီး၏ specific gravity ကို 1.020 ထက် ပိုများလာစေပြီး သွေး သို့မဟုတ် ပရိုတင်း အနည်းငယ်ကို ပိုမိုလွယ်ကူစွာ ရှာဖွေတွေ့ရှိနိုင်စေနိုင်သည်။ ရေဓာတ်ခန်းခြောက်ခြင်းက red-cell casts၊ ပရိုတင်းများ ဆက်တိုက်များနေခြင်း သို့မဟုတ် creatinine တက်နေခြင်းကို မရှင်းပြနိုင်ပါ။ နှလုံးရောဂါ၊ ကျောက်ကပ်ရောဂါ ပြင်းထန်သူများ သို့မဟုတ် ဆိုဒီယမ်နည်းသူများသည် ရေဓာတ်ကို သိသိသာသာ တိုးမြှင့်သောက်သုံးခြင်း မပြုမီ ဆရာဝန်နှင့် တိုင်ပင်သင့်ပါသည်။.
ဆီးခဲအနည်အထိုင်တွေ့ရှိချက်များတွင် အရေးပေါ်ကုသရန်လိုအပ်သည်များကားအဘယ်နည်း။
အနီရောင်သွေးဥဆဲလ်ခဲများ၊ အဖျား သို့မဟုတ် နံခါးနာခြင်းနှင့်အတူ အဖြူရောင်သွေးဥဆဲလ်ခဲများ၊ ၄၈ နာရီအတွင်း creatinine 0.3 mg/dL တိုးလာခြင်းနှင့်အတူ ကျောက်ကပ်ပြွန်ဆဲလ်များ သို့မဟုတ် သွေးခဲများနှင့်အတူ မြင်နိုင်သော သွေးများသည် အရေးပေါ်ဆေးဘက်ဆိုင်ရာ စစ်ဆေးမှု လိုအပ်ပါသည်။ ဆီးနည်းခြင်း၊ အန်ခြင်း၊ ပြင်းထန်သောနာကျင်ခြင်း၊ ရောင်ရမ်းခြင်းအသစ်၊ စိတ်ရှုပ်ထွေးခြင်း သို့မဟုတ် သွေးပေါင်ချိန် 180/120 mmHg ထက်များခြင်းတို့သည် အခြေအနေကို ပို၍ အရေးပေါ်ဖြစ်စေသည်။ လက္ခဏာမရှိဘဲ ကယ်လ်စီယမ်အောက်ဆாலேခဲတစ်ခဲတည်း သို့မဟုတ် hyaline cast ၁-၂ ခုသည် အများအားဖြင့် အရေးပေါ်မဟုတ်ပါ။ အရေးပေါ်အခြေအနေသည် လက္ခဏာများ၊ ကျောက်ကပ်လုပ်ဆောင်ချက်၊ ပရိုတင်းအဆင့်နှင့် sediment ပုံစံတို့ ပေါင်းစပ်မှုအပေါ် မူတည်ပါသည်။.
ဆီးထဲတွင် သွေးဖြူဥများအတွက် ပဋိဇီဝဆေးများ သောက်သင့်သလား။
ဆီးထဲတွင် သွေးဖြူဥ (WBC) များသည် ကူးစက်ရောဂါကို ခိုင်လုံစေသော ဆေးပညာဆိုင်ရာ ပုံရိပ်မရှိပါက ပဋိဇီဝဆေးများဖြင့် ကုသသင့်သည်မဟုတ်ပါ။ မြင်ကွင်းအကျယ် (high-power field) တစ်ခုလျှင် WBC 5 ထက်ပိုနေခြင်းသည် ကျောက်တည်ခြင်း၊ ညစ်ညမ်းခြင်း၊ ဆေးဝါးများ၊ လိင်ကတဆင့် ကူးစက်သော ရောဂါများ၊ ကျောက်ကပ်ရောင်ခြင်း သို့မဟုတ် ဘက်တီးရီးယားပိုး ကူးစက်ခြင်းတို့ကြောင့် ဖြစ်ပေါ်လာနိုင်သော ဆီးပြည် (pyuria) ကို ညွှန်ပြသည်။ ၂၀၁၉ IDSA လမ်းညွှန်ချက်သည် ကိုယ်ဝန်မရှိသော အများစုသော လူကြီးများတွင် လက္ခဏာမပြသော ဘက်တီးရီးယားပိုးများ (asymptomatic bacteriuria) ကို ကုသရန် အကြံပြုထားခြင်း မရှိပါ။ ကိုယ်ဝန်ဆောင်ခြင်းနှင့် စီစဉ်ထားသော ကျောက်ကပ်ဆိုင်ရာ လုပ်ထုံးလုပ်နည်းများသည် ယဉ်ကျေးမှု အခြေခံသော ကုသမှု (culture-guided treatment) ကို အလွန်အမင်း အကြံပြုလေ့ရှိသော အရေးကြီးသော ဥပမာများဖြစ်သည်။.
AI ပါဝါသုံး သွေးစစ်ဆေးမှု ရလဒ်ကို ယနေ့ စတင် ခွဲခြမ်းစိတ်ဖြာပါ
Kantesti ကို အချိန်မီ၊ တိကျသော ဓာတ်ခွဲခန်း စစ်ဆေးမှု ရလဒ်ခွဲခြမ်းစိတ်ဖြာမှုအတွက် ယုံကြည်သည့် ကမ္ဘာတစ်ဝန်း အသုံးပြုသူ 2 သန်းကျော်နှင့် ပူးပေါင်းပါ။ သင့် သွေးစစ်ဆေးမှု ရလဒ်များကို တင်ပြီး စက္ကန့်ပိုင်းအတွင်း 15,000+ biomarker များ၏ ပြည့်စုံသော အဓိပ္ပာယ်ဖတ်ချက်ကို ရယူပါ။.
📚 ကိုးကားထားသော သုတေသန ထုတ်ဝေမှုများ
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (၂၀၂၆)။ AI Blood Test Analyzer: 2.5M Tests Analyzed | Global Health Report 2026။ Zenodo။ https://doi.org/10.5281/zenodo.18175532. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). RDW Blood Test: RDW-CV, MCV & MCHC အတွက် ပြည့်စုံလမ်းညွှန်။ Zenodo. https://doi.org/10.5281/zenodo.18202598. Kantesti AI Medical Research.
📖 ပြင်ပ ဆေးဘက်ဆိုင်ရာ ကိုးကားချက်များ
⚕️ ဆေးဘက်ဆိုင်ရာ ရှင်းလင်းချက်
ဤဆောင်းပါးသည် ပညာရေးဆိုင်ရာ ရည်ရွယ်ချက်အတွက်သာ ဖြစ်ပြီး ဆေးဘက်ဆိုင်ရာ အကြံဉာဏ် မဟုတ်ပါ။ ရောဂါရှာဖွေခြင်းနှင့် ကုသမှု ဆုံးဖြတ်ချက်များအတွက် အရည်အချင်းပြည့်မီသော ကျန်းမာရေးစောင့်ရှောက်မှုပေးသူနှင့် အမြဲတမ်း တိုင်ပင်ပါ။.
E-E-A-T ယုံကြည်မှု အချက်ပြများ
အတွေ့အကြုံ
ဆရာဝန်ဦးဆောင်သည့် ဓာတ်ခွဲခန်း အဓိပ္ပာယ်ဖတ်ခြင်း လုပ်ငန်းစဉ်များကို ပြန်လည်သုံးသပ်ခြင်း။.
ကျွမ်းကျင်မှု
biomarker များသည် ဆေးဘက်ဆိုင်ရာ အခြေအနေတွင် မည်သို့ ပြုမူနေသည်ကို အာရုံစိုက်သည့် ဓာတ်ခွဲခန်း ဆေးပညာ။.
အခွင့်အာဏာရှိခြင်း
ဒေါက်တာ Thomas Klein မှ ရေးသားပြီး ဒေါက်တာ Sarah Mitchell နှင့် ပါမောက္ခ ဒေါက်တာ Hans Weber တို့က ပြန်လည်သုံးသပ်ထားသည်။.
ယုံကြည်စိတ်ချရမှု
စိတ်ပူစရာများကို လျော့ချရန်အတွက် ရှင်းလင်းသော နောက်ဆက်တွဲ လမ်းကြောင်းများပါဝင်သည့် သက်သေအထောက်အထားအခြေပြု အဓိပ္ပာယ်ဖတ်ချက်။.