
A crossmatch test checks whether a particular donor’s red cells are suitable for a particular recipient. It adds a compatibility check beyond ABO and Rh typing, but it cannot prevent every transfusion complication.



- Crossmatch test checks a specific donor–recipient pairing; a serological crossmatch tests recipient plasma against donor red cells.
- Three different checks—blood typing, antibody screening, and crossmatching—answer different questions and are not interchangeable.
- ABO and RhD matching does not exclude antibodies against other red-cell antigens, including Kell, Kidd, Duffy, and other Rh antigens.
- Incompatible crossmatch usually means the selected unit needs investigation or replacement, not that the patient can never receive a transfusion.
- Historical antibodies still matter even when today’s antibody screen is negative; tell the hospital about every previous antibody identification.
- Electronic crossmatching uses validated laboratory software rather than physically mixing samples; eligibility requires strict laboratory criteria.
- Sample validity is commonly limited to about 72 hours after recent transfusion or pregnancy, although local rules and expiry calculations differ.
- Emergency transfusion can begin before crossmatching is complete when delaying treatment would threaten life; group O red cells are not universally compatible with every antibody.
- New symptoms during transfusion or in the following days—especially breathlessness, fever, back pain, jaundice, or dark urine—need prompt clinical assessment.
What does a crossmatch test actually check?
A crossmatch test checks whether a specific donor’s red cells are compatible with a specific recipient. In a laboratory crossmatch, recipient plasma is tested against donor cells; an incompatible reaction prompts investigation and usually selection of another unit. Matching ABO and RhD types alone cannot exclude antibodies against other red-cell antigens.
Is e an eadar-dhealachadh cudromach this unit for this patient, not simply whether two people share a blood group. A person with A-positive blood may be suitable for one A-positive donor unit but incompatible with another because those donors differ in antigens outside ABO and RhD.
A compatible result means that the required compatibility checks found no disqualifying problem under the method used. It does not mean zero risk: allergic reactions, circulatory overload, and some delayed immune reactions can occur even when red-cell compatibility testing is satisfactory.
Consider an illustrative 58-year-old receiving treatment for severe anemia: the blood bank finds anti-K, an antibody against the Kell K antigen. The practical solution is not merely another unit with the same ABO group; it is an appropriately typed, K-negative unit that passes the required compatibility testing.
My aim as Thomas Klein, MD, is to make the laboratory’s decision understandable without turning a report into permission to transfuse. Kantesti is an organization behind an AI blood test analyzer that can help explain these three test categories; only the treating team and transfusion laboratory can authorize donor-unit selection.
Blood typing vs crossmatching: where does the antibody screen fit?
Blood typing identifies the patient’s ABO group and RhD status; an sgrìonadh antibody dearbhach ann looks for unexpected red-cell antibodies; a antigen assesses a selected donor unit. These are three related safeguards, not three names for the same test.
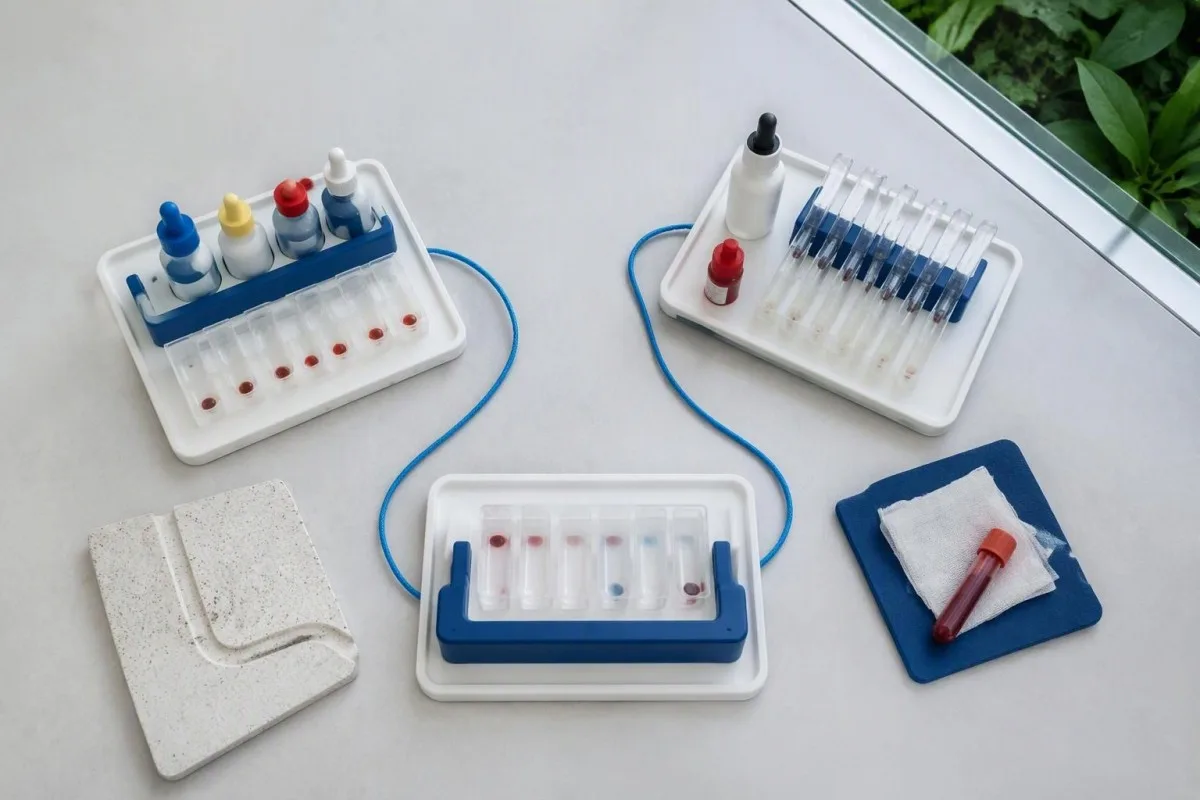
ABO typing usually includes forward grouping, which tests the patient’s cells, and reverse grouping, which tests the patient’s plasma. These two approaches should agree when reverse grouping is appropriate; disagreement can delay blood release while the laboratory resolves the cause.
An antibody screen uses selected reagent red cells, commonly supplied as a two-cell or three-cell set, rather than cells from the intended donor. The reagent cells carry a planned selection of antigens, making the screen an efficient search for clinically significant antibodies rather than a trial of every available unit.
A negative screen cannot exclude every possible antibody. For example, an antibody against a low-frequency antigen may react with a donor who carries that antigen even though none of the screening cells do; this distinction helps explain why different antibody results need different follow-up.
Milkins et al. (2013), in the British compatibility-testing guideline, distinguish grouping, antibody detection, and donor compatibility procedures as separate parts of pretransfusion testing. A request labeled group and screen no seòrsaich agus sgrìon therefore does not automatically mean that one or more donor units have already been crossmatched or reserved.
Why matching ABO and RhD types may not be enough
Matching ABO and RhD does not match every antigen on a red cell. Antibodies against Kell, Kidd, Duffy, or non-D Rh antigens can make otherwise ABO-compatible donor blood unsuitable, particularly after previous transfusions or pregnancy.
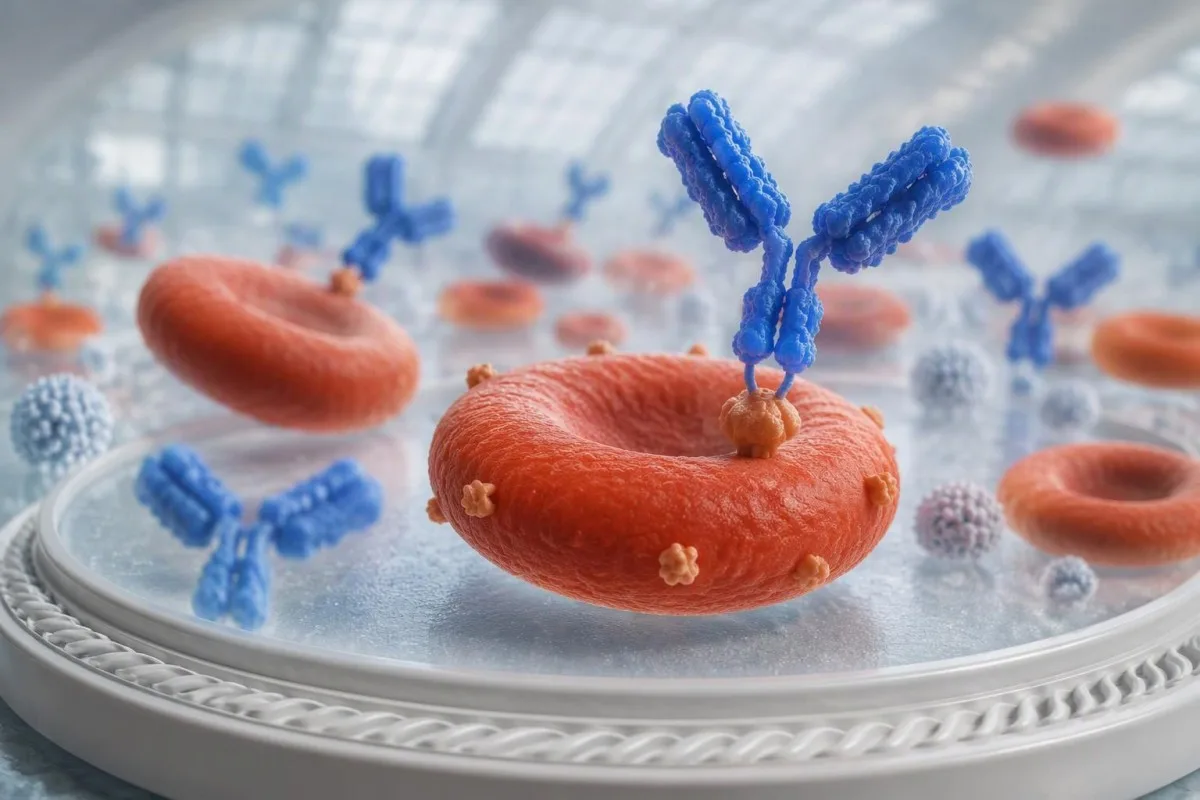
The familiar positive or negative sign refers to RhD, not the entire Rh system. Two D-positive people can differ in C, c, E, and e antigens; a recipient with anti-E may need E-negative red cells even when both recipient and donor are described as positive.
Previous exposure changes the interpretation of today’s results. A transfusion received 12 years ago can still matter if it produced a clinically significant antibody, because antibody concentrations may later fall below the screening method’s detection limit while immune memory remains.
Tormey and Hendrickson (2019), writing in Blood, explain that antibody disappearance and fragmented transfusion records contribute to delayed hemolytic reactions. The dangerous sequence is an apparently negative current screen, re-exposure to the relevant antigen, and a renewed antibody response—not a laboratory result that was necessarily misread.
A blood-group card containing only B-negative leaves out information that may determine donor selection. Our blood groups and hematology guide separates the group label from red-cell turnover markers; neither an LDH value nor a reticulocyte count identifies which donor antigens must be avoided.
How is a laboratory crossmatch performed?
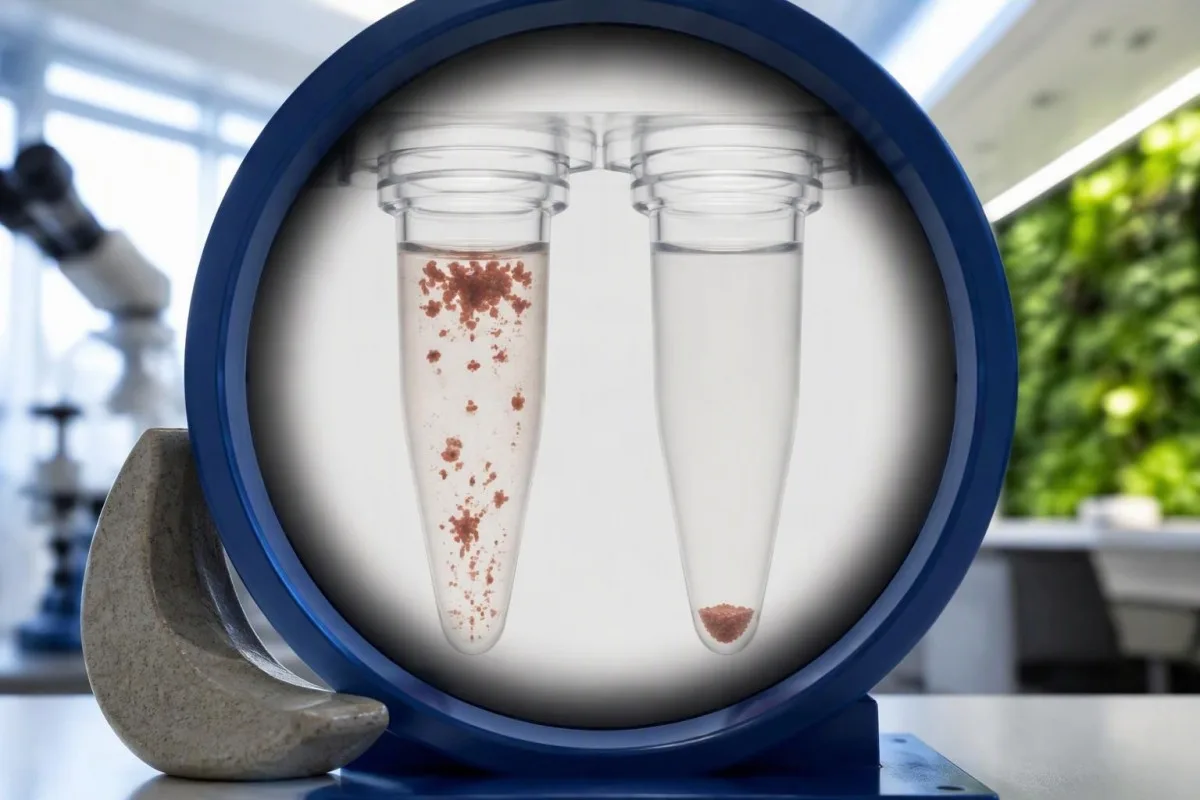
A serological crossmatch tests recipient plasma or serum against red cells from the selected donor unit. Depending on the patient’s antibody findings and laboratory protocol, testing may include a rapid immediate-spin method or an indirect antiglobulin method designed to detect clinically significant antibodies.

The donor cells usually come from an attached, sealed segment of the donation tubing, not from repeatedly opening the transfusion bag. That segment connects the test to one identifiable donor unit, while checks on the patient sample connect the result to the intended recipient.
Immediate-spin crossmatching principally checks for ABO incompatibility and is suitable only under defined laboratory criteria. It is not an adequate substitute for an antiglobulin crossmatch when a clinically significant IgG antibody requires investigation or has previously been identified.
An indirect antiglobulin crossmatch commonly includes incubation at approximately 37°C, close to body temperature. Gel, column-agglutination, solid-phase, and tube methods have different operating characteristics; the laboratory interprets reactions within its validated system rather than treating all methods as interchangeable.
A crossmatch is generally a qualitative compatibility result, not a concentration with a normal range in mg/dL. Reaction strength may be graded, but a weak reaction is not automatically harmless; antibody specificity, temperature of reactivity, and the complete investigation determine its significance.
What is an electronic crossmatch, and when is it allowed?
An electronic crossmatch uses validated blood-bank software to confirm compatibility without physically mixing recipient plasma and donor cells. It is generally restricted to patients with a suitable negative antibody screen, no history of clinically significant antibodies, and satisfactorily verified blood-group results.

Electronic crossmatching is not a shortcut around antibody testing. The software checks the recorded patient group against the selected unit and applies release rules, while laboratory procedures establish whether that patient is eligible; a negative current screen alone does not erase an old anti-K or anti-Jka.
Many services require two independently established ABO results before routine electronic issue when no reliable previous group is available. Whether the second determination requires a separate collection depends on local policy and identification safeguards, so an additional sample request may be a deliberate protection rather than duplication.
Eligible units can sometimes be issued within minutes once the earlier checks are complete. However, this timing describes the release step, not the entire process from sample collection, transport, grouping, screening, discrepancy resolution, and availability of the requested component.
Kantesti’s fiosrachadh dearbhaidh meidigeach againn concerns our interpretation service, not validation of a hospital’s blood-bank system. These are separate responsibilities: explanatory AI cannot perform electronic crossmatching, reserve a unit, or replace the laboratory’s release controls, as our report explanation safety guide also emphasizes.
Incompatible crossmatch meaning: what does the result imply?
An incompatible crossmatch means the selected donor–recipient combination has not passed the required compatibility assessment. It can reflect an ABO problem, an antibody against donor antigens, an autoantibody, medication interference, or another testing issue; it does not by itself identify the cause or prove active hemolysis.

A reaction with one donor unit can point toward an antigen carried by that donor, whereas reactions with several units raise a different set of possibilities. The laboratory compares the antibody screen, antibody-identification panel, patient history, and sometimes an autocontrol to separate these patterns.
An autocontrol tests patient plasma against the patient’s own cells; a deuchainn antiglobulin dhìreach, or DAT, checks whether antibodies or complement are already attached to those cells. Neither is the same as a donor crossmatch, and a toradh dearbhach Coombs dìreach does not automatically establish clinically significant hemolysis.
Reactivity at approximately 37°C is often more relevant to red-cell transfusion than a reaction confined to colder conditions, but temperature alone is not a complete decision rule. A specialist may need additional methods to distinguish a cold-reactive antibody, a warm autoantibody, and an underlying alloantibody.
Not every apparent clump represents immune agglutination. Increased plasma proteins can produce rouleaux on cell examination, and technical problems can also complicate interpretation; this is why the report should lead to an investigation, not a patient attempting to choose the least reactive bag.
How does the blood bank choose another donor unit?
After an incompatible crossmatch, the blood bank identifies the cause and selects red cells that meet the patient’s antigen requirements and compatibility criteria. When a clinically significant alloantibody is responsible, the usual approach is antigen-negative donor blood followed by the appropriate crossmatch.
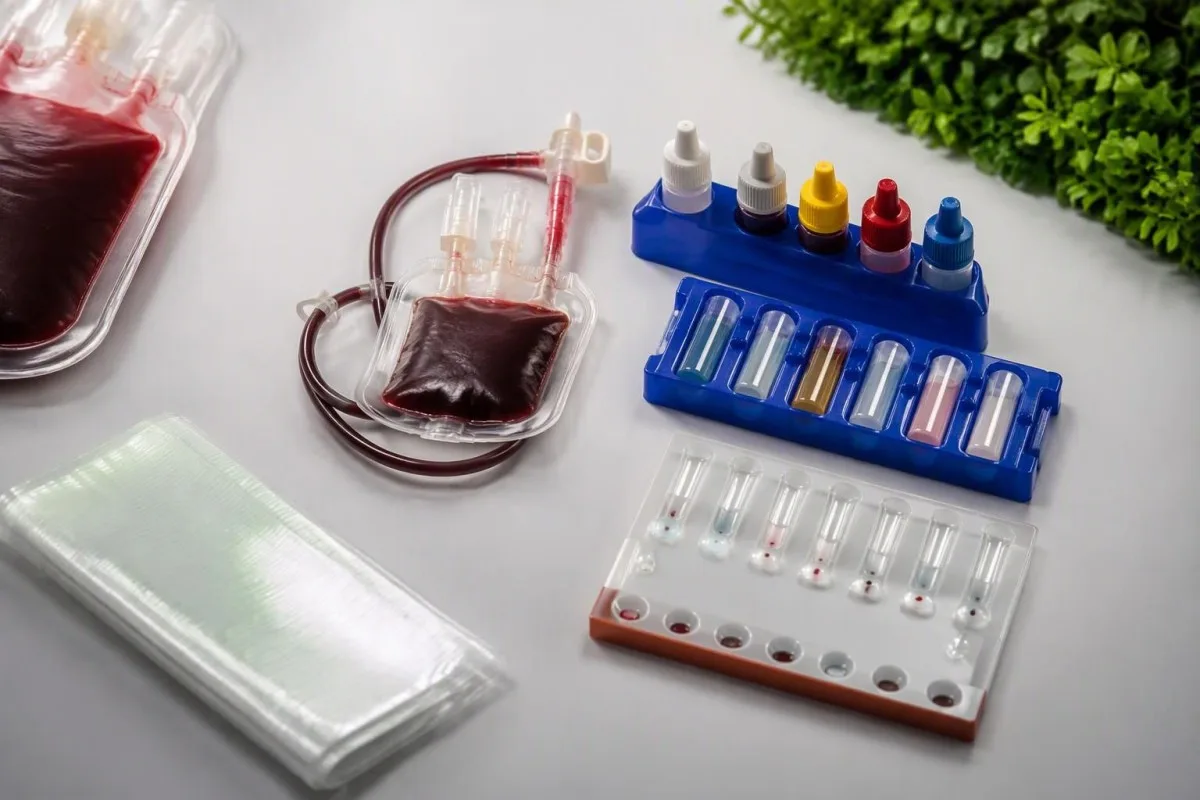
For a recipient with anti-K, the laboratory searches for K-negative units; for anti-Jka, it searches for Jka-negative units. If the patient has two or more clinically significant antibodies, each relevant antigen requirement must be considered, which can shrink the available donor pool substantially.
ABO-compatible blood does not always have to be ABO-identical, but any substitution follows the laboratory’s component-selection rules. Switching an A-positive patient to O-positive red cells does not solve anti-K incompatibility unless the selected O-positive unit also lacks the K antigen.
Patients receiving repeated transfusions may benefit from extended antigen typing or genotyping before future requirements become complicated. Someone with myelodysplastic syndrome who has received 20 units presents a different planning problem from someone needing a first transfusion, although unit count alone cannot predict whether antibodies have formed.
When a warm autoantibody makes many units react, the priority is excluding clinically significant alloantibodies and selecting appropriately matched blood—not simply finding the weakest reaction. The phrase least incompatible can be misleading; urgent release decisions belong to the transfusion specialist and treating clinician, with the residual uncertainty explicitly documented.
How long does crossmatching take, and why might a new sample be needed?
Straightforward compatibility testing may take approximately 30–60 minutes after the laboratory receives a suitable sample, but antibody investigations can take hours or longer. A new sample may be required because identification checks, recent transfusion, pregnancy history, or local sample-expiry rules make the previous sample unsuitable.
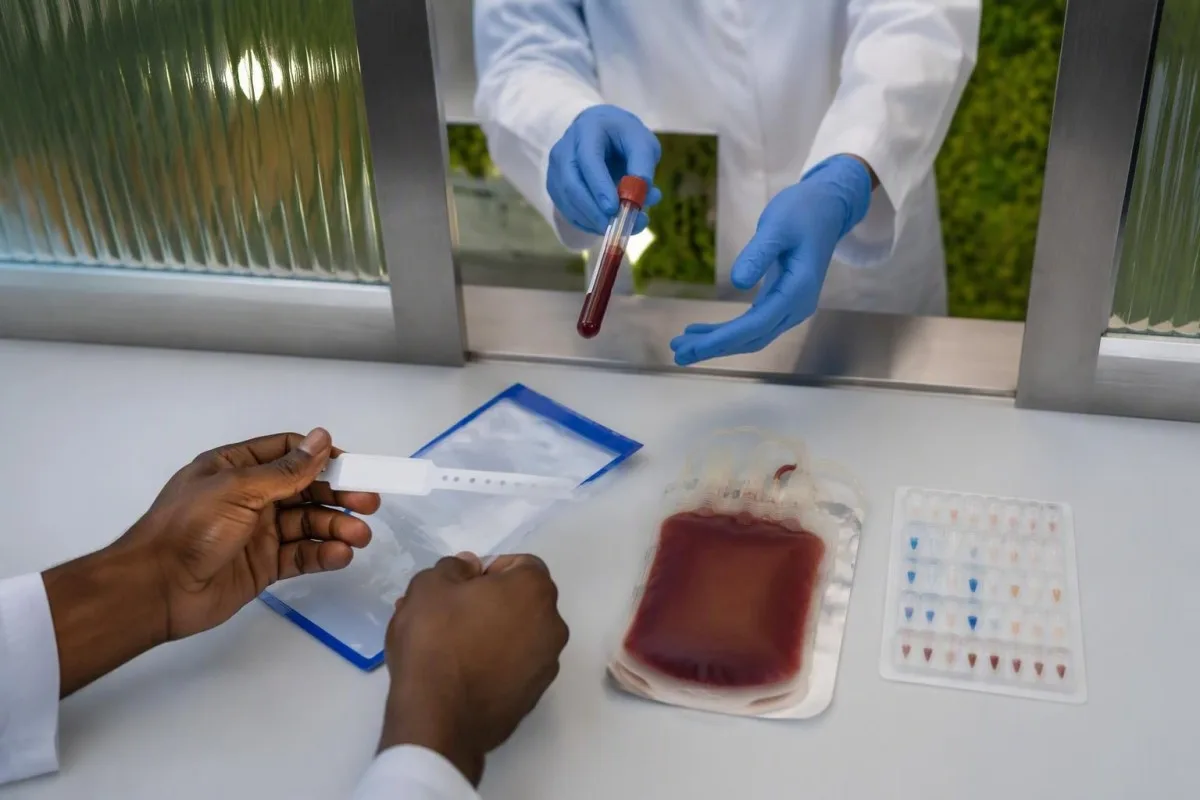
The commonly encountered 72-hour rule is about detecting newly developing antibodies after recent exposure, not about how long a tube can physically remain intact. Milkins et al. (2013) recommend restricted sample validity for patients transfused or pregnant within the preceding three months; exact expiry calculations follow local policy.
Three days and exactly 72 elapsed hours are not always operationally identical. Some services calculate expiry using the collection day and a specified midnight cutoff, while other jurisdictions use different intervals; ask the blood bank for the actual expiry timestamp rather than estimating it yourself.
Identification problems can stop testing even when the laboratory sample looks perfectly usable. A mismatch between the wristband, request, and sample label requires resolution because a technically compatible result from the wrong patient’s sample offers no protection to the intended recipient.
Hemolysis and other sample-quality problems may also trigger recollection, although acceptance depends on the test method and local procedures. Our ath-dheuchainn às deidh sèididh explains why a redraw can protect interpretation; a repeat collection is not evidence that the donor blood itself is incompatible.
What should patients disclose before surgery or a planned transfusion?
Before planned transfusion, tell the team about previous transfusions, pregnancies, known red-cell antibodies, and transfusion reactions. These details can change the sample schedule and donor-unit requirements even when the current antibody screen is negative.

An old antibody card can save hours of investigation if it identifies the antibody precisely. Bring the original report when possible, including the hospital name and approximate year; a statement such as “my blood was difficult to match in 2014” is useful, but “anti-E identified in 2014” is much more actionable.
Pregnancy can expose the maternal immune system to red-cell antigens that differ from her own. A positive pregnancy antibody screen may therefore influence both pregnancy monitoring and future transfusion selection; anti-D following prophylactic immunoglobulin also needs interpretation in its timing and clinical context.
A preoperative group-and-screen sample collected several weeks ahead may identify an antibody early, yet a fresh sample can still be needed close to surgery. These two collections serve different purposes: the first allows planning, and the second meets current compatibility and sample-validity requirements.
Treating the cause of anemia can reduce the likelihood of transfusion, but it does not replace compatibility testing when transfusion becomes necessary. A patient with bleeding trom menstrual trom and hemoglobin of 8.5 g/dL needs assessment of symptoms, ongoing losses, and iron deficiency—not an automatic transfusion based on that number alone.
Can emergency transfusion start before crossmatching is finished?
Emergency red-cell transfusion can begin before crossmatching is complete when waiting would create a greater immediate danger. The team may initially use uncrossmatched group O red cells, then change to appropriately selected group-specific blood as reliable laboratory information becomes available.

Group O red cells lack A and B antigens, but they can still carry Kell, Kidd, Duffy, and Rh antigens. Consequently, an O-negative unit is not universally compatible with every recipient who has an unexpected antibody; the word universal is an oversimplification outside ABO and RhD discussions.
O-negative red cells are often prioritized when avoiding D exposure is especially important, including certain patients with future pregnancy potential. Other patients may receive O-positive emergency red cells under local policy, balancing clinical urgency, sensitization risk, and the finite supply of O-negative donations.
A pretransfusion patient sample should be collected before the first unit when feasible without delaying resuscitation. Donor cells can complicate later grouping or antigen typing, while the pretransfusion sample preserves a clearer view of the recipient’s original cells and antibodies.
Major bleeding may require more than red cells: plasma, platelets, and fibrinogen replacement address different problems. Our pàtrain obair-lann DIC agus stiùireadh deuchainn clotadh againn explain these separate assessments; passing a red-cell crossmatch does not correct a platelet count of 30 × 10⁹/L or a depleted fibrinogen concentration.
Who needs additional matching or specialist compatibility testing?
Euslaintich le sickle cell disease, multiple antibodies, warm autoantibodies, or certain antibody-based treatments may need additional compatibility procedures. Neonates also require a different approach because maternal antibodies and the infant’s age affect which tests are informative.

Chou et al. (2020), in the American Society of Hematology guideline, recommend prophylactic Rh C/E and K matching for patients with sickle cell disease receiving transfusions. An extended antigen profile, preferably obtained before the first transfusion, helps plan sickle cell transfusion care rather than waiting for an antibody to appear.
Recent donor cells can complicate serological phenotyping, so genotyping may provide useful additional information about the recipient’s antigen profile. Transfusion also affects hemoglobin fraction interpretation, meaning an HbS percentage measured after two donor units is not directly comparable with the patient’s untreated baseline.
Daratumumab, an anti-CD38 treatment, can cause widespread reactivity in indirect antiglobulin testing. Laboratories may use methods such as dithiothreitol treatment to reduce interference, but that treatment also affects certain antigens, including Kell; the medication history therefore changes both investigation and donor-selection precautions.
Infants younger than approximately four months often have transfusion-testing procedures that account for maternal antibodies and limited infant antibody production. Kantesti is an AI blood test interpretation platform that can explain these distinctions, but an adult compatibility pathway should never be assumed to apply unchanged to a newborn.
What can still go wrong after a compatible crossmatch?
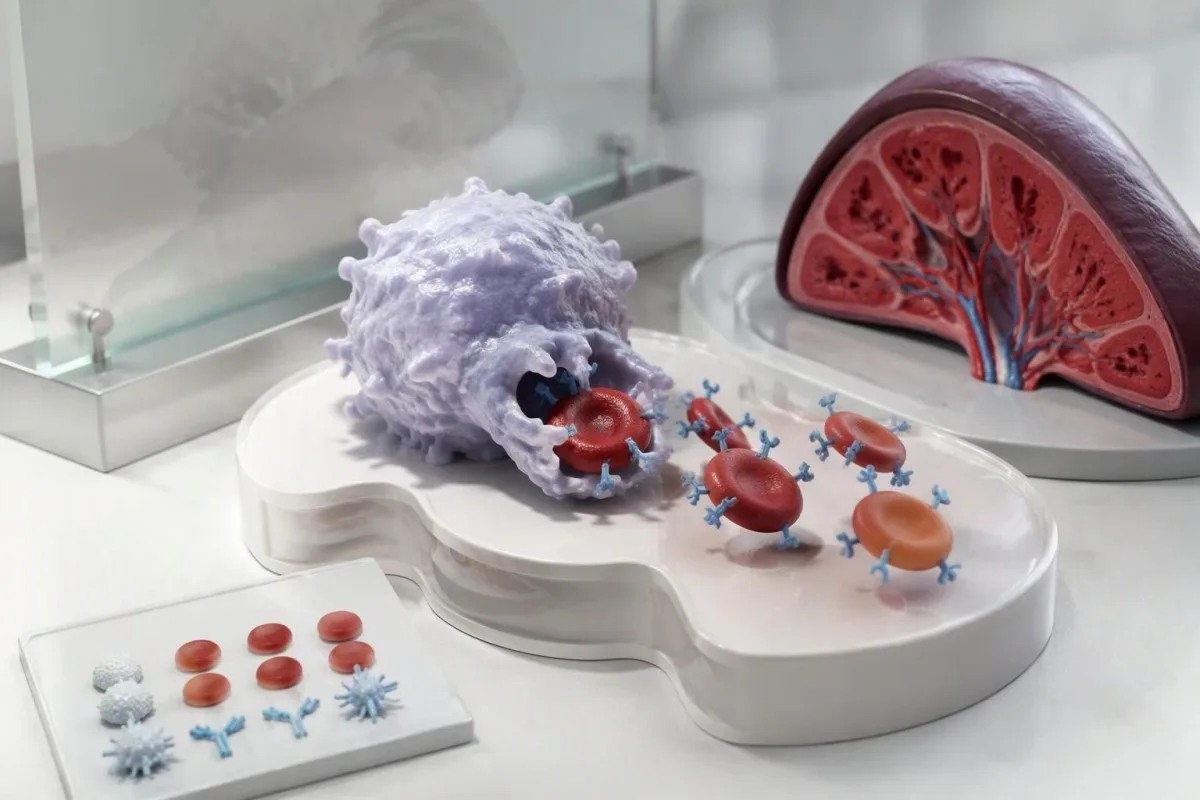
A compatible crossmatch does not rule out every transfusion reaction. It reduces particular red-cell incompatibility risks, but allergic reactions, transfusion-associated circulatory overload, lung injury, and delayed hemolysis require separate clinical monitoring.
Symptoms during transfusion—including fever, chills, breathlessness, chest or back pain, or an unexpected blood-pressure change—should be reported immediately. Staff may stop the transfusion, reassess the patient, recheck identity and component details, and arrange laboratory investigations; a previously compatible result must not dismiss new symptoms.
Delayed hemolytic reactions often become apparent several days after transfusion, although timing varies and can extend over subsequent weeks. Falling hemoglobin, jaundice, dark urine, rising LDH, and reduced haptoglobin can support investigation, but low haptoglobin has other causes and is not diagnostic by itself.
For an adult without ongoing bleeding or major fluid shifts, one red-cell unit commonly raises hemoglobin by about 1 g/dL, co-ionann ri 10 g/L. A smaller increase needs context: continued losses, fluid dilution, sampling timing, or hemolysis can each explain it, so the team should not jump directly to an incompatible-transfusion diagnosis.
LDH is a marker of cell injury rather than a donor-compatibility measurement. An LDH result and its causes must be considered alongside bilirubin, haptoglobin, reticulocytes, DAT findings, and the hemoglobin trend; no single number can reconstruct the entire transfusion reaction.
How should you read your crossmatch report and ask useful questions?
Read a crossmatch report as a decision about a specified donor unit, method, and sample—not as a general certificate that all donor blood is safe for you. Ask whether antibodies were found, whether historical antibodies were checked, and whether the proposed unit meets any antigen-negative requirements.

Three practical questions are: “Was my antibody screen negative?”, “Do I have a clinically significant antibody now or in my history?”, and “Is this unit compatible using the method appropriate for me?” If the report says pending, incompatible, or emergency release, ask the team to explain what remains unresolved and why the chosen timing is appropriate.
Kantesti is an AI-powered blood test analysis tool that can help explain uploaded laboratory wording and associated anemia results. Our stiùireadh teicneòlais AI describes the interpretation process; it does not establish that a donor unit is compatible, verify bedside identity, or make a transfusion-release decision.
Transfusion dates also matter when reviewing later laboratory trends. For example, HbA1c às deidh tar-chuir can be misleading because the measured red-cell population now includes donor cells; recording the date and number of units helps a clinician decide which follow-up measurements remain useful.
My advice here, as Thomas Klein, MD, is to preserve the original transfusion and antibody records rather than relying only on a simplified explanation. If using Kantesti to understand them, consider removing identifiers you do not need to share and read our fiosrachadh mu phrìobhaideachd is dàta; explainable results and responsible handling are separate concerns.
Research publications and the evidence behind compatibility testing
The clinical recommendations in this article are supported by transfusion-specific guidelines and peer-reviewed literature, not by a general blood-test guide alone. As of 25 Dàmhair 2026, the distinction between compatibility testing, antibody history, and clinical monitoring remains fundamental; individual hospitals must apply their current validated procedures.
Milkins et al. (2013) provide the compatibility-testing framework; Tormey and Hendrickson (2019) explain antibody formation, disappearance, and clinical consequences; Chou et al. (2020) address additional matching in sickle cell disease. These three external references directly support the clinical discussion and are listed separately from the two repository publications below.
Nipah virus blood test: Early detection & diagnosis guide 2026. (n.d.). Zenodo. https://doi.org/10.5281/zenodo.18487418. This supplied repository reference concerns a different diagnostic topic and is not evidence for transfusion compatibility; its Rannsachadh ResearchGate agus Rannsachadh tiotal Academia ’s e ceanglaichean lorg a tha annta, chan e lethbhreacan dearbhte den fhoillseachadh.
B negative blood type, LDH blood test & reticulocyte count guide. (n.d.). Figshare. https://doi.org/10.6084/m9.figshare.31333819. This supplied reference offers adjacent blood-group and hematology context rather than a compatibility-testing guideline; its Rannsachadh foillseachaidhean air ResearchGate agus Rannsachadh foillseachaidhean air Academia should likewise be treated as searches rather than confirmed hosted versions.
The two repository entries use title-first APA-style citations because verified author and publication-date metadata were not supplied; readers should check the DOI landing pages before reusing those details. Kantesti’s inbhean susbaint mheidigeach distinguish explanatory material from clinical authorization: an educational article cannot override the blood bank’s compatibility investigation or an urgent bedside decision.
Ceistean Bitheanta
Dè th’ ann an deuchainn co-fhreagarrachd fala mus tèid fuil a ghluasad?
0 Tha deuchainn co-fhreagarrachd a’ measadh a bheil ceallan dearga fala bho thabhartaiche taghte co-chòrdail ri neach-faighinn sònraichte. Bidh deuchainn co-fhreagarrachd seròlach a’ dèanamh deuchainn air plasma an neach-faighinn an aghaidh cheallan an tabhartais, agus bidh deuchainn co-fhreagarrachd dealanach iomchaidh a’ cleachdadh bathar-bog obair-lann dearbhte agus toraidhean deuchainn dearbhte. Mar as trice bidh dòighean antiglubulin a’ gabhail a-steach deuchainn aig mu 37°C gus cuideachadh le lorg antibodies a tha cudromach gu clinigeach. Tha co-fhreagarrachd a’ buntainn ris an aonad a chaidh a thaghadh; chan eil i a’ co-dhùnadh a bheil feum aig euslainteach air tar-chur-fala no a’ cur às do gach cunnart co-cheangailte ri tar-chur-fala.
Dè an diofar eadar seòrsachadh fala, sgrìonadh airson antibodies, agus tar-mhaidseadh?
Tha seòrsachadh fala a’ dearbhadh buidheann ABO agus inbhe RhD, bidh sgrìonadh airson antibodies a’ lorg antibodies ris nach robh dùil an aghaidh cheallan fala dearga, agus bidh tar-mhaidseadh a’ measadh aonad tabhartais a chaidh a thaghadh. Bidh na trì sgrùdaidhean seo a’ freagairt cheistean eadar-dhealaichte agus chan gabh an cur an àite a chèile. Mar as trice bidh sgrìonadh airson antibodies a’ cleachdadh seata ath-ghnìomhaiche dà-cheallach no trì-cheallach seach ceallan bhon tabhartaiche a thathar an dùil a chleachdadh. Mar sin, chan eil toradh seòrsa-agus-sgrìonadh gu riatanach a’ ciallachadh gun deach aonadan tabhartais a thar-mhaidseadh no a ghlèidheadh mar-thà.
What does an incompatible crossmatch mean?
An incompatible crossmatch means the selected donor–recipient pairing has not passed the required compatibility assessment. Possible causes include ABO incompatibility, an antibody against a donor antigen, an autoantibody, medication interference, or a technical issue. Reactivity with one donor unit can have a different explanation from reactivity with several units. The blood bank investigates the pattern and selects appropriately matched blood; the result does not automatically mean the patient can never receive a transfusion.
Can the crossmatch be incompatible even when ABO and Rh types match?
A crossmatch can be incompatible despite matching ABO and RhD types because donor red cells carry additional antigens. For example, an A-positive recipient with anti-K may react with an A-positive donor unit that carries the K antigen. A clinically significant antibody identified 10 years earlier may still affect selection even if today’s screen is negative. Historical antibody records help the blood bank choose antigen-negative units and avoid re-exposure.
How long does a crossmatch take, and how long is the sample valid?
Straightforward compatibility testing may take roughly 30–60 minutes after a suitable sample reaches the laboratory, but antibody investigations can take hours or longer. Electronic release may be quicker once all eligibility checks are complete. Sample validity is commonly restricted to about 72 hours after recent transfusion or pregnancy, although local intervals and expiry calculations differ. The blood bank can confirm the actual expiry timestamp and whether a fresh sample is needed.
Is O-negative blood safe without a crossmatch in an emergency?
Uncrossmatched O-negative red cells can be used in a life-threatening emergency when delaying transfusion would be more dangerous. They lack A, B, and D antigens but may still carry other antigens targeted by a recipient’s antibodies. Emergency O-positive red cells may also be used for selected patients under local policy. A patient sample should be collected before the first unit when feasible without delaying treatment, and compatibility investigations continue during resuscitation.
Faigh Mion-sgrùdadh Deuchainn Fala le Cumhachd AI an-diugh
Thig còmhla ri còrr is 2 mhillean neach air feadh an t-saoghail a tha a’ earbsa Kantesti airson mion-sgrùdadh sa bhad, ceart air deuchainnean obair-lann. Luchdaich suas na toraidhean deuchainn fala agad agus faigh mìneachadh coileanta air biomarcair 15,000+ ann an diogan.
📚 Foillseachaidhean Rannsachaidh le Iomraidhean
Klein, T., Mitchell, S., & Weber, H. (2026). Deuchainn Fuil Bhìoras Nipah: Stiùireadh airson Lorg is Breithneachadh Tràth 2026. Rannsachadh Leigheis AI Kantesti.
Klein, T., Mitchell, S., & Weber, H. (2026). Stuth fala B àicheil, stiùireadh deuchainn fala LDH & cunntas reticulocyte. Rannsachadh Leigheis AI Kantesti.
📖 Iomraidhean Meidigeach Taobh a-muigh
Milkins C et al. (2013). Guidelines for pre-transfusion compatibility procedures in blood transfusion laboratories. Leigheas Tar-chuir.
Tormey CA and Hendrickson JE (2019). Transfusion-related red blood cell alloantibodies: induction and consequences. Blood.
Chou ST et al. (2020). American Society of Hematology 2020 guidelines for sickle cell disease: transfusion support. Blood Advances.




⚕️ Àicheadh Meidigeach
Tha an artaigil seo dìreach airson adhbharan foghlaim agus chan eil e a’ dèanamh comhairle mheidigeach. Cuir fios an-còmhnaidh gu solaraiche cùram slàinte teisteanasach airson co-dhùnaidhean breithneachaidh is leigheis.
Comharran earbsa E-E-A-T
Eòlas
Lèirmheas clionaigeach air a stiùireadh le lighiche air sruthan-obrach mìneachaidh obair-lann.
Eòlas
Fòcas air leigheas obair-lann air mar a bhios bith-chomharraidhean (biomarkers) a’ giùlan ann an co-theacsa clionaigeach.
Ùghdarrasachd
Air a sgrìobhadh le Dr. Thomas Klein le ath-sgrùdadh le Dr. Sarah Mitchell agus Prof. Dr. Hans Weber.
Earbsachd
Mìneachadh stèidhichte air fianais le slighean leanmhainn soilleir gus dragh a lughdachadh.
