Yes—endocarditis can occur despite negative blood cultures. Diagnosis depends on how samples were collected, antibiotic exposure, heart imaging and carefully selected tests for organisms that routine cultures miss.

Основни изводи
- Negative cultures do not exclude endocarditis; a report showing no growth after 24 hours is also different from a final negative result.
- Предходен прием на антибиотици can suppress organism recovery even when an infected valve remains; never stop prescribed treatment to improve culture results yourself.
- Вземането на пробата usually involves 2–3 culture sets, with about 8–10 mL in each adult bottle, before antibiotics when this does not delay urgent care.
- Ехокардиография looks for valve involvement independently of culture growth; a negative first scan may need repeating after 5–7 days if suspicion remains high.
- Targeted serology can identify Coxiella burnetii or Bartonella infection; selected antibody titers around 1:800 have diagnostic significance only in the correct clinical and assay context.
- Molecular testing can detect microbial DNA in blood or valve tissue, but negative PCR does not exclude endocarditis and positive DNA does not necessarily indicate living organisms.
- Спешни симптоми include sudden weakness, speech difficulty, severe breathlessness, collapse or new confusion; call emergency services rather than waiting for another test.
- AI интерпретация can explain accompanying laboratory patterns, but neither an AI report nor a normal CRP result can establish or rule out endocarditis.
Why a negative culture cannot exclude endocarditis
Да, може да имате endocarditis with negative blood cultures. Antibiotics can suppress growth, some organisms need specialized detection, and inadequate sampling can miss organisms; clinicians combine cultures with echocardiography and other evidence rather than treating 1 negative result as an exclusion test.

Blood culture–negative endocarditis describes suspected or established infective endocarditis in which routine cultures do not identify the cause. The American Heart Association statement reports that cultures can be negative in up to 30% of cases, although the proportion varies substantially with antibiotic exposure, referral patterns and laboratory access (DeSimone et al., 2025).
A negative culture means the laboratory did not recover an organism under the conditions used; it does not mean the heart valve was examined. A report issued at 24 hours may simply be preliminary, while an echocardiogram can reveal structural abnormalities regardless of whether microorganisms grow in a bottle.
For example, imagine a 58-year-old with a prosthetic valve, 10 days of unexplained fever and cultures collected after treatment for a presumed chest infection. That combination deserves clinician-led investigation even if the first bottles remain negative; the same negative result in someone without symptoms or valve risk has a different meaning.
Кантести е един AI кръвен анализатор that explains laboratory findings without converting 1 negative culture into reassurance about a heart valve. Our организация и цел explain this educational role: suspected endocarditis requires an examination, microbiology input and cardiac imaging, not an automated laboratory verdict.
How antibiotics before blood cultures reduce detection
Antibiotics before blood cultures can reduce the number of viable organisms available to grow, creating a negative result despite persistent valve involvement. Even 1 dose may affect recovery, but the effect depends on the organism, drug, dose and interval before collection.

Prior antibiotic treatment is a leading cause of culture negative endocarditis in many healthcare settings. The AHA statement separates previously treated patients from those whose cultures are negative without antibiotic exposure, because these 2 groups suggest different likely organisms and different initial treatment considerations (DeSimone et al., 2025).
A medication timeline is more informative than a simple yes-or-no answer about antibiotics. Bring the exact drug name, whether it was oral or intravenous, the first and last doses, and the collection time; a dose given 2 hours before sampling creates a different interpretation problem from a course completed weeks earlier.
Temporarily withholding treatment is an exceptional specialist decision, not a home strategy. The 2023 ESC guideline allows consideration in selected stable patients with subacute symptoms, very short previous exposure and no complications, but there is no universally safe 48-hour or 72-hour washout that patients should attempt themselves.
Treatment must not be delayed in someone with sepsis, shock or rapidly deteriorating valve function merely to obtain better cultures. Our explanation of culture timing in typhoid illustrates the broader sampling principle, but suspected endocarditis has its own urgent imaging and treatment pathway.
What makes blood culture sampling adequate?
Adequate adult sampling generally means 2–3 blood culture sets with sufficient volume, preferably before treatment. A set usually contains aerobic and anaerobic bottles; collection quality, incubation status and laboratory communication all affect how much reassurance a negative result provides.
The AHA statement recommends at least 2 sets, ideally 3, before empirical antibiotics when feasible, with approximately 8–10 mL per adult bottle. Underfilling bottles reduces the amount of material examined, so several small samples do not necessarily provide the same diagnostic opportunity as properly filled sets.
The 2023 ESC guideline recommends 3 sets at approximately 30-minute intervals before antibiotics in the appropriate clinical setting (Delgado et al., 2023). The AHA approach emphasizes adequate volume and prompt collection; neither recommendation means an unstable patient should wait through a prolonged sampling schedule before receiving necessary treatment.
Routine automated cultures commonly reach a final report after about 5 days, although local protocols and organism-specific investigations differ. Ask whether no growth means preliminary, final or final for routine incubation only; specialized cultures may be separate orders rather than an automatic extension of the original test.
Fever spikes are not required for useful sampling because endocarditis often produces sustained bloodstream seeding. Kantesti AI can help distinguish a report's collection date from its reporting date when those details are supplied, while our ръководство за хронологията на лабораторните резултати explains why results taken at different treatment stages are not directly interchangeable.
Why Coxiella and Bartonella need targeted testing
Coxiella burnetii и Bartonella species are major considerations when routine cultures remain negative, particularly without prior antibiotics. Targeted antibody testing and molecular assays can provide evidence that standard culture bottles miss; exposure history helps prioritize these 2 groups.
Coxiella burnetii causes Q fever and can produce persistent infection involving a damaged or prosthetic valve. Exposure to sheep, goats or cattle is useful history, but aerosol spread means direct animal handling is not required; a person may lack an obvious exposure despite months of otherwise unexplained symptoms.
The 2023 Duke-ISCVID criteria recognize Coxiella phase I IgG greater than 1:800 as a major microbiological criterion when the specified testing framework applies. Phase I and phase II results are not interchangeable, and our Q fever antibody guide explains why a generic positive Q fever antibody report is incomplete.
Bartonella henselae is associated with cats and cat fleas, while Bartonella quintana is associated with body lice and circumstances that increase exposure to them. These associations guide testing without establishing a diagnosis; 1 cat scratch or a remote history of cat ownership does not make an antibody result proof of valve involvement.
Bartonella henselae or quintana IgG of at least 1:800 by the specified immunofluorescence method can fulfill a major Duke-ISCVID criterion (Fowler et al., 2023). Our обяснение за титъра на Bartonella addresses antibody interpretation, but endocarditis assessment additionally requires cardiac findings and consideration of cross-reactivity.
Which other organisms can routine cultures miss?
Other causes include Tropheryma whipplei, Brucella and selected fungi, with testing guided by exposures, immune status and valve history. Modern culture systems recover many previously difficult organisms within about 5 days, so culture negativity should not automatically be blamed on slow growth.

HACEK organisms historically required prolonged incubation, but modern automated systems usually detect them during routine incubation. The group contains 5 named categories of oral-associated bacteria; asking for weeks of incubation solely because HACEK is suspected may add less value than reviewing antibiotic exposure, sample volume and the actual laboratory system.
Tropheryma whipplei endocarditis may occur without classic diarrhea or obvious gastrointestinal disease. A history of unexplained joint symptoms over months or years can be a clue, but a stool result alone does not establish valve involvement; targeted PCR on suitable material, especially valve tissue when available, is more informative.
Brucella testing becomes more relevant after unpasteurized dairy consumption, livestock exposure or travel to an endemic area. Our Brucella culture and PCR guide explains these complementary methods, and suspected exposure should be communicated before specimen processing because the laboratory needs appropriate handling precautions.
Aspergillus endocarditis often has negative routine blood cultures, whereas Candida can grow but may still be missed. Tests such as galactomannan or beta-D-glucan are supporting evidence rather than valve-specific confirmation; our galactomannan interpretation guide explains why 1 positive fungal marker requires context and confirmation.
How echocardiography helps when cultures are negative
Ехокардиография can identify vegetations, new valve leakage and complications despite negative cultures. Transthoracic echocardiography, or TTE, is usually the first scan; transesophageal echocardiography, or TEE, provides closer views when TTE is inconclusive or the clinical suspicion remains high.
A vegetation is a valve-associated mass, but its appearance alone does not identify the organism. In a hypothetical 62-year-old with persistent fever and negative cultures, a mobile valve mass plus newly severe regurgitation changes the diagnostic assessment more than an isolated nonspecific rise in an inflammatory marker.
TEE is particularly useful with prosthetic valves, intracardiac devices, limited TTE image quality or concern about an abscess around the valve. The 2023 ESC guideline generally recommends TEE in suspected endocarditis even after a positive TTE, except selected unequivocal right-sided native-valve cases with good-quality images (Delgado et al., 2023).
A negative TTE does not carry the same exclusion value in every patient. For example, a 4 mm abnormality may be harder to visualize than a large mobile mass, and prosthetic material can obscure adjacent structures; clinicians interpret the scan together with valve type, symptoms and the technical quality of the examination.
Endocarditis involves the inner heart lining and valves, not primarily the heart muscle. Our лабораторно ръководство за миокардит explains that distinction: 1 normal troponin result cannot exclude a valve infection, because troponin answers a different question about myocardial injury.
When repeat echo, cardiac CT or PET adds information
If suspicion remains high, the 2023 ESC guideline recommends repeating echocardiography after 5–7 days following an initially normal or inconclusive study. Cardiac CT and selected nuclear imaging can add evidence, especially around prosthetic valves or when complications extend beyond what ultrasound shows.
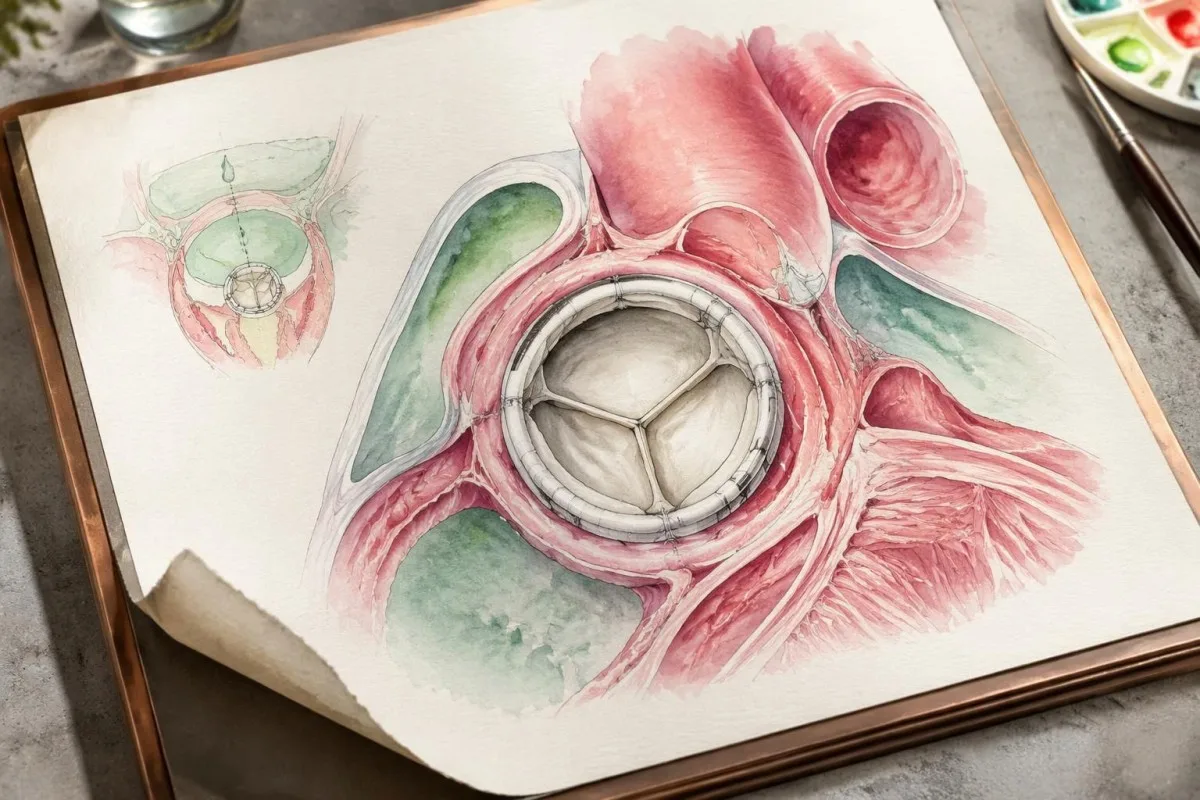
Repeat imaging is not simply repetition for reassurance; a small early abnormality may become visible, or a different imaging angle may clarify an uncertain finding. The 5–7-day interval is a guideline framework, not a reason to wait if breathlessness, conduction abnormalities or hemodynamic deterioration develops sooner.
Cardiac CT is especially useful for evaluating perivalvular anatomy, such as abscesses, pseudoaneurysms or fistulas. TEE can be better for small mobile vegetations and leaflet perforations, so 2 imaging methods may be complementary rather than interchangeable; CT planning also considers kidney function, contrast exposure and radiation.
FDG-PET/CT can support prosthetic-valve or device-associated endocarditis and identify distant sites needing investigation. Recent procedures and sterile tissue responses can also cause uptake; the 2023 ESC and Duke-ISCVID frameworks handle postoperative timing differently, which is why a scan should be interpreted by specialists familiar with the applicable criteria.
There is no single scan that rules out every presentation, particularly early native-valve disease. If chest discomfort accompanies worsening breathlessness, our наръчник за спешни изследвания при болка в гърдите explains why 1 reassuring laboratory result should not replace an immediate clinical assessment.
How to interpret targeted serology without overcalling it
Targeted serology measures antibodies to selected organisms and can help establish culture-negative endocarditis, but antibodies are not a direct image of the valve. The 1:800 thresholds used for Coxiella and Bartonella have specific organism, antibody-phase and assay requirements.

A titer of 1:800 means reactivity remains detectable after the serum has been diluted to that ratio. Coxiella phase I IgG greater than 1:800 and Bartonella IgG at least 1:800 are separate Duke-ISCVID provisions; rounding greater than into greater than or equal to can incorrectly change how a borderline report is classified.
Assay methods and reporting increments differ between laboratories. A result expressed as an index value or units per milliliter cannot automatically be converted to a 1:800 immunofluorescence titer, so clinicians may request reference-laboratory confirmation rather than applying a published cutoff to a non-equivalent test.
Cross-reactivity, previous exposure and delayed antibody formation can complicate interpretation in opposite directions. Our guide to положителни резултати от антитела explains why 1 positive result may not indicate active disease, while an early negative result can also be insufficient when the exposure history and imaging remain concerning.
Broad untargeted panels can generate incidental positives and make the diagnosis less clear. When cultures remain negative at approximately 72 hours, the AHA statement supports expanding the investigation with microbiology input, commonly including Coxiella and Bartonella serology and exposure-directed tests—not treating every detected antibody as a separate infection.
When PCR or sequencing can identify the cause
PCR and sequencing can detect microbial genetic material when cultures cannot recover living organisms. Targeted blood PCR for Coxiella, Bartonella or Tropheryma whipplei has a recognized diagnostic role; valve tissue can also undergo organism-specific PCR, broad-range testing and histological examination.

The 2023 Duke-ISCVID criteria recognize positive blood nucleic-acid tests for these 3 organisms as major microbiological evidence in the specified framework (Fowler et al., 2023). A standard bloodstream multiplex panel may not include them, so a negative panel should not be described as negative testing for all endocarditis organisms.
Valve tissue obtained during clinically indicated surgery can be especially valuable after antibiotic exposure. Broad-range bacterial 16S rRNA gene testing and fungal 18S or ITS testing may detect organisms missed by culture, but neither approach has 100% sensitivity and results still require contamination-aware interpretation.
Specimen handling should be planned before a valve procedure whenever possible. Separate material may be needed for culture, molecular testing and formalin-fixed histology; placing the entire specimen in 1 container can limit later options, and tissue should never be obtained solely because a patient wants a more definitive laboratory answer.
Microbial cell-free DNA sequencing may help selected difficult cases, but access, contamination, cost and clinical interpretation remain variable. Our PCR sample timing explanation illustrates why specimen timing matters; for endocarditis, 1 negative molecular result does not cancel convincing cardiac or pathological evidence.
How clinicians combine evidence for a diagnosis
Blood culture negative endocarditis diagnosis depends on the combination of microbiology, imaging, clinical features and sometimes tissue findings. Under the 2023 Duke-ISCVID clinical criteria, definite endocarditis can be classified by 2 major criteria, 1 major plus 3 minor criteria, or 5 minor criteria.

The Duke-ISCVID criteria standardize evidence; they are not a home scoring tool or a substitute for specialist judgment. Fever above 38°C is 1 minor criterion, but a person can have serious endocarditis without a measured fever, particularly after treatment or when immune responses are altered.
For a hypothetical example, consider a 55-year-old with negative routine cultures, imaging that meets a major endocarditis criterion and Bartonella IgG of 1:1600 by an appropriate assay. Those 2 major criteria can establish the clinical classification, provided specialists verify the findings and assess alternatives; the negative cultures do not erase the other evidence.
Nonbacterial thrombotic endocarditis is an important alternative when a valve mass occurs with negative cultures. Cancer, antiphospholipid syndrome and lupus can produce sterile valve deposits, and echocardiography alone may not distinguish them from infection; antibiotics before sampling can make that distinction harder rather than resolving it.
Kantesti's laboratory explanations should remain separate from claims of diagnostic certainty about endocarditis. Our технически и клинични стандарти describe the boundaries of interpretation: 1 apparently compatible laboratory pattern cannot replace an endocarditis team's assessment of scans, exposures, complications and competing diagnoses.
What CRP, white cells and kidney results can tell you
CRP, white blood cell counts and kidney tests can reveal the body's response and complications, but none can confirm or exclude endocarditis. A CRP of 80 mg/L indicates substantial inflammation in many laboratories; it does not identify a valve source or distinguish every infectious from noninfectious cause.

CRP reference limits commonly fall below 5 mg/L or 10 mg/L, depending on the laboratory, while adult WBC intervals often approximate 4–11 × 10⁹/L. Normal results can occur in subacute or previously treated disease, and our сравнение на WBC и CRP explains why disagreement between these markers is not inherently an error.
Кантести е един Платформа за кръвни изследвания тълкуване с AI that can place a supplied CRP of 80 mg/L alongside the CBC, creatinine and treatment timeline without assigning the inflammation to a valve. A falling CRP may support improvement, but 1 falling marker does not prove that an abscess, vegetation or embolic risk has resolved.
New blood or protein in urine can reflect immune-complex kidney involvement, embolic injury or an unrelated urinary problem. Our Ръководство за уринен седимент explains why microscopy matters: red cell casts, if present, carry different implications from 1 isolated positive dipstick result and warrant clinician assessment.
Reduced complement can support an immune-complex process but is not specific for infection. Our ръководство за C3 и C4 explains that overlap; for example, a creatinine rise from 90 to 140 µmol/L requires assessment for kidney injury, medication effects and other causes rather than attribution to endocarditis alone.
Which symptoms need emergency or same-day assessment?
Sudden neurological symptoms, severe breathlessness, collapse, chest pain or new confusion require emergency assessment, whether cultures are positive or negative. In the UK, call 999 or 112; elsewhere, use the local emergency number rather than waiting for another culture or an AI interpretation.

Sudden facial weakness, arm weakness, speech difficulty, loss of vision or major imbalance can indicate a stroke caused by embolization or another emergency. Our stroke warning sign guide explains immediate action; record the last time the person was known well, even if the symptoms disappear within 10 minutes.
Severe breathlessness at rest, inability to speak comfortably, fainting or rapidly worsening swelling can indicate acute heart failure or circulatory compromise. A home oxygen reading of 98% does not exclude serious valve dysfunction, so a normal pulse oximeter result should not delay emergency help when symptoms are severe.
Persistent unexplained fever with a prosthetic valve, previous endocarditis, an intracardiac device or recent bloodstream infection deserves prompt clinician contact, often the same day. A temperature above 38°C adds concern, but older adults and immunocompromised people may become seriously unwell without reaching that threshold.
Sudden severe abdominal or flank pain, a cold painful limb or rapidly reduced urine output also needs urgent assessment because embolic and kidney complications are possible. Small skin spots or splinter-like nail marks alone are nonspecific; 1 such finding should prompt context-sensitive medical advice, not self-diagnosis from internet photographs.
How treatment proceeds without a positive culture
Treatment can begin before the cause is identified when the clinical situation warrants it. Clinicians select initial therapy using valve type, illness severity, previous antibiotics and exposure history, then adjust it as targeted results arrive; many regimens last approximately 4–6 weeks, with important organism-specific exceptions.

Culture-negative endocarditis does not have 1 universal antibiotic regimen. Previously treated disease may still involve common staphylococci, streptococci or enterococci, whereas genuinely culture-negative disease without treatment can require coverage for different organisms; some causes, such as Coxiella infection, need therapy far longer than 6 weeks.
Drug monitoring targets cannot simply be copied from another infection. Our vancomycin AUC explanation describes the commonly used 400–600 mg·h/L exposure framework for serious MRSA infections under specified assumptions, but the treating team decides whether that framework and that drug apply to the individual endocarditis case.
Aminoglycosides are not required for every presentation and can cause kidney or hearing toxicity. Our gentamicin monitoring guide explains why a level collected 1 hour too early or late may mislead; doses must not be adjusted from a random concentration without the regimen and collection timing.
Kantesti can help explain supplied laboratory trends during prescribed treatment, but medication changes and decisions about surgery remain with the clinical team. Heart failure, uncontrolled infection or selected embolic-risk situations can require a procedure even when cultures are negative; 1 favorable CRP trend cannot overrule those structural or clinical indications.
Using laboratory explanations and research safely
A useful consultation record includes culture dates, antibiotic timing, valve history and imaging reports, not just a list of negative tests. Bring these 4 categories together so clinicians can distinguish an incomplete investigation from genuinely reassuring evidence and avoid repeating tests that answer the wrong question.

Кантести е един Инструмент за анализ на кръвни изследвания с AI that supports understanding of accompanying results, not a replacement for urgent cardiac assessment. Our обяснение на AI технологията describes interpretation workflows; an explanation produced in approximately 60 seconds should never become a reason to postpone emergency or same-day care.
Ask 3 practical questions: Were the cultures collected before antibiotics, was the first echocardiogram sufficient for this valve type, and which targeted organism tests are justified by the history? Our принципи за отговорен ИИ support checking source documents and escalating clinical uncertainty rather than accepting an automated conclusion at face value.
Kantesti's 2 supporting Figshare publications listed below are background educational materials, not endocarditis diagnostic studies or evidence validating detection of this condition. The related hematology marker explanation may help readers understand associated anemia, but blood group, LDH and reticulocytes cannot establish valve infection.
The endocarditis recommendations in this article instead rely on 3 directly relevant clinical publications: the 2023 ESC guideline, the 2023 Duke-ISCVID criteria and the 2025 AHA scientific statement. These sources address different tasks—clinical management, diagnostic classification and culture-negative investigation—so apparent differences should be interpreted within their intended scope.
Често задавани въпроси
Възможно ли е да имате ендокардит, ако всички хемокултури са отрицателни?
Да, ендокардит може да възникне дори когато всички рутинни кръвни култури са отрицателни. Предходното лечение с антибиотици, трудните за откриване микроорганизми и недостатъчното вземане на проби могат да понижат вероятността за изолиране на причинителя, затова клиницистите съчетават културите с образни изследвания на сърцето и целенасочени тестове. Резултатът „няма растеж“ след 24 часа може също да е предварителен, а не окончателен. Отрицателните култури не са основание да се пренебрегват продължаващи симптоми или обезпокоителни находки от клапите.
Колко кръвни култури са необходими при съмнение за ендокардит?
Изследването при възрастни обикновено включва 2–3 комплекта кръвни култури, за предпочитане преди започване на антибиотично лечение, когато това не забавя спешното лечение. Всеки комплект обикновено съдържа аеробна и анаеробна бутилка, с приблизително 8–10 mL кръв във всяка бутилка за възрастни. Насоките на ESC от 2023 г. препоръчват 3 комплекта през интервали от около 30 минути при подходящи обстоятелства, докато становището на AHA подчертава необходимостта от поне 2, в идеалния случай 3 комплекта. При децата са необходими обеми, съобразени с възрастта и теглото, а не целевите обеми за бутилки за възрастни.
Трябва ли да спра антибиотиците преди повторното вземане на кръвни култури?
Не спирайте самостоятелно предписаните антибиотици с цел подобряване на резултатите от кръвните култури. Дори една доза може да повлияе на възстановяването, но при съмнение за ендокардит няма универсално безопасен период на изчакване от 48 или 72 часа. Специалистите могат да обмислят временно прекъсване на лечението само при определени стабилни пациенти с ограничен предходен прием на антибиотици и без усложнения. При сепсис, сърдечна недостатъчност или бързо влошаване забавянето на лечението е особено опасно.
Изключва ли нормалната ехокардиография ендокардит?
Нормалната първа ехокардиография не винаги изключва ендокардит, особено когато изследването е технически ограничено или протезен материал закрива клапата. Трансезофагеалната ехокардиография може да даде допълнителна информация след отрицателно или неубедително трансторакално изследване. Насоките на ESC от 2023 г. препоръчват повторна ехокардиография след 5–7 дни, ако подозрението остава високо. Появата на нови тежки симптоми налага по-ранна оценка, без да се изчаква този интервал.
Which tests diagnose culture negative endocarditis?
Culture negative endocarditis is assessed with echocardiography, adequate cultures, targeted serology and selected molecular tests rather than 1 universal blood test. Coxiella phase I IgG greater than 1:800 and appropriately measured Bartonella IgG of at least 1:800 have defined roles in the 2023 Duke-ISCVID criteria. Targeted blood PCR and testing of valve tissue obtained during clinically indicated surgery can identify some otherwise missed organisms. Results must be interpreted together because antibodies, DNA and valve images each have different limitations.
Can CRP and white blood cells be normal with endocarditis?
CRP and white blood cell counts can be normal in endocarditis, particularly in subacute or previously treated presentations. Many laboratories use CRP limits below 5 or 10 mg/L and adult WBC intervals around 4–11 × 10⁹/L, but values within those intervals do not exclude valve infection. Raised results also cannot identify endocarditis as the source. Persistent fever with valve risk, severe breathlessness or sudden neurological symptoms needs clinician-led assessment regardless of these numbers.
Получете обяснение на резултатите от кръвните си изследвания
Качете лабораторния си доклад и AI на Kantesti ще обясни всеки биомаркер на разбираем език за секунди. Използва се от над 2 милиона души по света.
Референции
- Klein, T., Mitchell, S., & Weber, H. (2026). Ръководство за кръвна група B отрицателна, кръвен тест за LDH и брой на ретикулоцитите. Медицински изследвания с Kantesti AI. ДОИ
- Klein, T., Mitchell, S., & Weber, H. (2026). Диария след гладуване, черни точици в изпражненията и ръководство за стомашно-чревния тракт 2026. Медицински изследвания с Kantesti AI. ДОИ
- Delgado V et al. (2023). 2023 ESC Guidelines for the management of endocarditis. European Heart Journal. ДОИ
- Fowler VG Jr et al. (2023). The 2023 Duke-International Society for Cardiovascular Infectious Diseases Criteria for Infective Endocarditis: Updating the Modified Duke Criteria. Clinical Infectious Diseases. ДОИ
- DeSimone DC et al. (2025). Blood Culture–Negative Endocarditis: A Scientific Statement From the American Heart Association: Endorsed by the International Society for Cardiovascular Infectious Diseases. Journal of the American Heart Association.
- 2 милиона+Анализирани тестове
- 127+Държави
- 100+Езици
За медицинския екип


Сигнали за доверие E-E-A-T
Опит
Медицински преглед, воден от лекар, на работните процеси за интерпретация на лабораторни резултати.
Експертиза
Фокус в лабораторната медицина върху това как се държат биомаркерите в клиничен контекст.
Авторитетност
Медицинска рецензия от д-р Thomas Klein, с принос от д-р Sarah Mitchell и проф. д-р Hans Weber.
Надеждност
Интерпретация, основана на доказателства, с ясни последващи стъпки за намаляване на тревогата.






Медицински отказ от отговорност
Тази статия е само с образователна цел и не представлява медицински съвет. Винаги се консултирайте с квалифициран медицински специалист за решения относно диагностика и лечение.
Публикувано · Свържете се с редакционния екип
Издава се от Kantesti Ltd, регистрирана в Англия и Уелс, дружество №. 17090423, Лондон, Обединено кралство.
