Two disease-causing ALDOB variants can establish the diagnosis—but their classification and location matter. A breath test answers a different question, and a deliberate fructose challenge can cause a medical emergency.

اہم نکات
- تصدیق usually requires 2 pathogenic or likely pathogenic ALDOB variants affecting opposite gene copies, interpreted with the clinical history.
- غیر یقینی متغیرات do not establish hereditary fructose intolerance; 1 pathogenic variant plus 1 VUS still needs specialist interpretation.
- Carrier results usually identify 1 affected ALDOB copy and do not, by themselves, explain hereditary fructose intolerance symptoms.
- Inheritance follows an autosomal recessive pattern: 2 carrier parents have a 25% chance of an affected child in each pregnancy.
- Different conditions need different tests: ALDOB testing investigates inherited fructose metabolism failure, while breath testing investigates intestinal malabsorption.
- Challenge safety means no deliberate fructose exposure at home; oral or intravenous fructose challenges can cause severe hypoglycemia and organ injury.
- Routine chemistry can reveal complications, but even a glucose result of 90 mg/dL cannot exclude hereditary fructose intolerance in someone avoiding fructose.
- علاج requires specialist-guided avoidance of fructose, sucrose, and sorbitol, plus medication-excipient checks and nutritional monitoring.
When does an ALDOB gene test confirm the diagnosis?
A hereditary fructose intolerance test can confirm the condition when it identifies 2 pathogenic or likely pathogenic ALDOB variants on opposite gene copies, consistent with the clinical picture. A variant of uncertain significance does not confirm it. Deliberate fructose challenges can be dangerous and should never be attempted at home.

Hereditary fructose intolerance, or HFI, is an inherited inability to metabolize fructose safely after it enters cells. The diagnostic question is not simply whether a report mentions ALDOB: it is whether both gene copies carry variants capable of causing aldolase B deficiency, rather than 1 incidental or uncertain finding.
Molecular confirmation can avoid older invasive investigations and dangerous exposure-based testing. The review by Ali et al. (1998) describes the metabolic basis and diagnostic hazards of HFI; modern genetic testing investigates the inherited defect without requiring the person to consume fructose or reproduce a previous reaction.
For example, a hypothetical adult who has avoided sweet foods since childhood may have 2 clearly classified disease-causing variants but normal liver enzymes today. That combination is plausible because dietary avoidance reduces exposure; normal current chemistry does not erase a lifelong genetic defect or make an experimental fruit challenge safe.
کنٹیسٹی ایک ہے۔ اے آئی بلڈ ٹیسٹ تجزیہ کار that helps explain routine chemistry alongside a documented genetic diagnosis; we do not perform ALDOB sequencing or independently certify variants. Our کمپنی کا پس منظر explains our role, while the Pompe testing pathway illustrates another condition where molecular and biochemical evidence answer different questions.
What does the ALDOB gene do in fructose metabolism?
ALDOB encodes aldolase B, an enzyme involved in fructose metabolism in the liver, kidney, and small intestine. In HFI, impaired processing allows fructose-1-phosphate to accumulate, trapping phosphate and disrupting energy-dependent processes, including glucose production.

The number in fructose-1-phosphate names the molecule, not a laboratory severity score. Fructokinase can still phosphorylate incoming fructose when aldolase B is deficient, so the pathway continues consuming resources upstream of the blockage; that explains why simply adding more fructose can worsen the problem rather than reveal a harmless intolerance.
Sucrose contains 2 linked sugars: glucose and fructose. Sorbitol can also be converted to fructose, so an exposure history limited to fruit misses table sugar, sweetened medicines, and some sugar-free products; all 3 substances belong in the discussion with a metabolic specialist.
HFI is not an IgE-mediated food allergy, and a conventional allergy panel does not measure aldolase B function. A person can react metabolically without hives or wheezing, while 1 isolated episode of nausea after fruit remains too nonspecific to establish an inherited enzyme disorder.
A routine serum aldolase result is not an ALDOB gene test and cannot confirm HFI. Our explanation of serum aldolase testing concerns a different laboratory use—particularly muscle-related investigation—so neither an elevated result nor a value within range should be substituted for molecular testing.
Who should be assessed for hereditary fructose intolerance?
ALDOB testing is most useful when symptoms or family history suggest HFI, especially vomiting, lethargy, hypoglycemia, or liver abnormalities after fructose-containing foods. A lifelong aversion to sweets can be a useful clue, but it is not diagnostic on its own.

Symptoms often become apparent when fructose or sucrose enters an infant's diet, frequently around complementary feeding at roughly 4–6 months. The exact age depends on actual exposure, including formula ingredients or medicines; age alone cannot distinguish HFI from infection, reflux, or other feeding problems.
A hypothetical 28-year-old who has always refused desserts may report becoming unwell only after a newly introduced sweetened supplement. That history deserves more attention than a generic label of irritable bowel syndrome because longstanding self-protection can conceal HFI until an unfamiliar product bypasses the person's usual food choices.
Document previous exposures rather than recreating them: record the product, approximate amount, timing, symptoms, and any contemporaneous laboratory values. A glucose of 45 mg/dL, approximately 2.5 mmol/L, during illness would be a serious clue, but our guide to کم گلوکوز کی وجوہات explains why other causes still need evaluation.
Family history changes the testing threshold even before symptoms develop. A sibling of an affected child has a different risk from someone with 1 distant relative who dislikes fruit; an asymptomatic at-risk infant should be assessed promptly through clinical genetics or a metabolic service rather than waiting for a dietary reaction.
Which ALDOB genetic test should you request?
A diagnostic ALDOB gene test generally uses sequencing, with deletion and duplication analysis considered according to the laboratory method and initial findings. Testing only a few common variants is narrower than examining the gene more comprehensively and may leave a suspected diagnosis unresolved.

Ask 3 practical questions before testing: does the assay examine the coding regions and relevant splice boundaries, does it assess deletions or duplications, and what does it explicitly not detect? Some laboratories bundle these methods; others offer copy-number testing separately, so identical-looking order names may conceal different coverage.
Targeted familial testing is efficient when a relative's 2 disease-causing variants are already documented. By contrast, a limited common-variant screen may be a poor stopping point in someone with convincing symptoms, especially when their ancestry or family variant spectrum differs from the population used to design the screen.
Testing can use DNA obtained from an appropriately collected clinical sample, sometimes including saliva or a cheek swab if the laboratory accepts it. No fructose loading is required, and fasting is usually unnecessary for DNA analysis itself; check separate preparation instructions if routine chemistry is collected at the same appointment.
A broader metabolic gene panel may be appropriate when the presentation does not fit HFI cleanly, but more genes also create more opportunities for uncertain findings. The Gaucher diagnostic sequence provides a useful comparison: clinicians select tests to answer a specific biological question, not merely to maximize the number of genes reported.
How should you read ALDOB genetic test results?
پڑھیں ALDOB genetic test results by checking the variant classification, zygosity, and whether 2 relevant variants affect opposite gene copies. The words positive, detected, or abnormal are insufficient without those details and the assay's limitations.

Clinical laboratories commonly use 5 variant categories: pathogenic, likely pathogenic, uncertain significance, likely benign, and benign. These categories describe evidence about a variant's relationship to disease; they do not provide a five-step scale of how sick a person is or how much fructose they can tolerate.
A ہوموزائگس result usually means the same variant is present on both copies, whereas compound heterozygous describes 2 different variants affecting opposite copies. A single heterozygous pathogenic finding generally supports carrier status, although a symptomatic person may still need investigation for a second change the assay did not detect.
One report may use an HGVS description such as c.448G>C, p.Ala150Pro; older literature may describe the protein change with different numbering. Compare the DNA change, protein change, and reference transcript together rather than deciding that 2 differently formatted names necessarily represent different variants.
Save the complete report, including methodology, classification date, and limitations—not only the summary page. Our Alport genetic report guide explains the broader reason this matters: inheritance rules and variant interpretation depend on the specific gene, so conclusions from another inherited disorder cannot simply be transferred to ALDOB.
Does an ALDOB variant of uncertain significance mean HFI?
ایک ALDOB variant of uncertain significance, or VUS, does not confirm or exclude HFI. A report containing 1 pathogenic variant and 1 VUS remains diagnostically unresolved unless additional evidence supports reclassification and the variants' arrangement is established.
The ACMG/AMP recommendations state that a VUS should not be used for clinical decision-making as though it were pathogenic (Richards et al., 2015). This does not mean ignoring symptoms: 2 separate questions remain—whether the molecular diagnosis is established, and whether precautionary care is justified while a convincing clinical history is investigated.
Segregation testing asks whether a variant tracks with disease or clarifies which parental copy it occupies. A functional assay asks whether the change disrupts the gene product; these are 2 different evidence types, and neither automatically proves pathogenicity unless the assay or family evidence is sufficiently informative.
For example, a hypothetical child has 1 known pathogenic ALDOB variant and 1 rare missense VUS. Finding the changes on opposite copies improves the inheritance interpretation but does not make the VUS disease-causing; rarity, computer predictions, and an in-trans arrangement must still be weighed within formal classification criteria.
Ask the laboratory or genetics service who manages reanalysis and whether a review after 12–24 months would be useful for your particular result. That is a practical interval, not a universal guideline; our uncertain genetic results guide also explains why updated evidence can change classification without changing the person's DNA.
Can a negative ALDOB test rule out hereditary fructose intolerance?
A negative ALDOB test reduces the likelihood of HFI but does not always exclude it, especially when the assay examined only common variants or did not assess relevant structural changes. The strength of a negative result depends on coverage and the original clinical suspicion.

Zero detected variants means no reportable findings were identified by that method—not that every possible ALDOB change was examined. Coding-region sequencing, copy-number analysis, and assessment of deep intronic or regulatory changes have different capabilities; the report's limitations section should identify which possibilities remain outside the assay.
A hypothetical person with 1 pathogenic variant on a common-variant screen and a strong exposure-linked history should not be reassured solely by a carrier label. The next question is whether comprehensive sequencing and appropriate deletion/duplication analysis could identify a second variant, rather than whether the person can prove symptoms by eating fruit.
A well-covered negative test and a weakly suggestive history may appropriately shift attention toward malabsorption or another diagnosis. There is no single percentage for the residual risk after all negative ALDOB tests; our کیریئر اسکریننگ کی حدود سے متعلق رہنما illustrates why assay-specific blind spots matter.
کنٹیسٹی ایک ہے۔ AI خون کے ٹیسٹ کی رپورٹ کی تشریح, not a genetic testing laboratory, so a normal chemistry panel or AI explanation cannot overrule a specialist's concern about missed variants. Our اے آئی ٹیکنالوجی گائیڈ describes the interpretation workflow; diagnostic DNA coverage remains the issuing laboratory's responsibility.
Why do in-trans and in-cis ALDOB variants matter?
In trans means 2 variants lie on opposite gene copies; سِس میں means they lie together on the same copy. Because HFI is autosomal recessive, 2 pathogenic findings in cis do not by themselves establish that both ALDOB copies are affected.
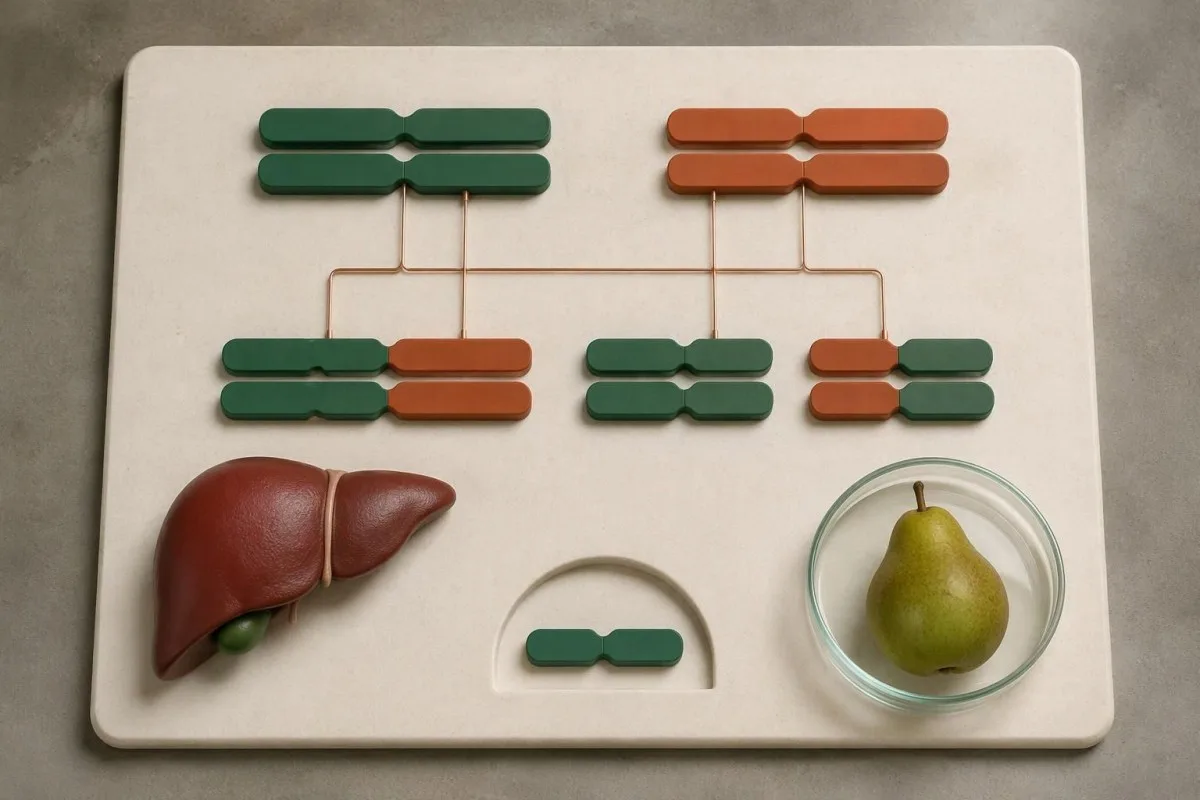
Each person usually has 2 ALDOB copies, one inherited from each biological parent. If variant A and variant B occupy the same inherited copy, the other copy may remain functional; simply counting two variant names can therefore produce the wrong conclusion about an autosomal recessive diagnosis.
Consider a hypothetical report listing 2 heterozygous pathogenic variants but stating that phase is unknown. If parental testing shows A came from one parent and B from the other, the findings support an in-trans arrangement; if both came together from one parent, the interpretation changes and further evaluation may be needed.
Parental testing is not the only way to establish phase: some sequencing methods can resolve it directly when the variants and read structure permit. Ask whether the laboratory has already established phase before paying for 2 additional family tests, and distinguish an experimentally determined result from an assumption based on population data.
Family results must still be interpreted alongside variant classification and symptoms. Our MEFV result interpretation guide highlights another gene where counting findings alone can mislead; for ALDOB, the decisive combination is disease-causing evidence plus the appropriate two-copy arrangement.
What do ALDOB results mean for children and siblings?
HFI follows autosomal recessive inheritance: when both parents carry a disease-causing ALDOB variant, each pregnancy has a 25% chance of an affected child, a 50% chance of a carrier, and a 25% chance of a child inheriting neither familial variant.

The 25% risk applies independently to every pregnancy; having 1 unaffected child does not reduce the next child's risk. Full siblings of an affected person should be offered an appropriate genetics discussion, and testing the established familial variants is often more informative than ordering a nonspecific screening panel.
An unaffected sibling of an affected child has a 2-in-3 carrier probability before genetic testing, assuming both parents are carriers and the sibling truly does not have HFI. That conditional figure should not be applied to an infant whose exposure history or disease status has not yet been adequately assessed.
If an affected person has children with a confirmed non-carrier partner, all children are expected to be carriers rather than affected under the usual two-copy model. If the partner is a carrier, each pregnancy has a 50% chance of HFI; a negative partner screen still needs interpretation according to its coverage.
Kantesti can help organize separate relatives' routine laboratory histories, but family-sharing tools do not infer carrier status or replace consent for genetic testing. Our خاندانی جانچ کی ترجیحات explain why a shared household does not mean everyone needs identical tests, particularly when one relative requires targeted ALDOB analysis.
How does HFI differ from fructose malabsorption?
HFI is a cellular fructose-metabolism disorder caused by biallelic disease-causing ALDOB variants; fructose malabsorption is impaired intestinal absorption. Malabsorption usually produces gas, bloating, abdominal discomfort, or diarrhea, rather than the characteristic fructose-triggered hypoglycemia and organ toxicity of HFI.

A fructose breath test measures fermentation-related gases after an ingested substrate; it does not measure aldolase B activity or identify ALDOB variants. The North American Consensus uses a 25 g fructose substrate for adult malabsorption testing and a hydrogen rise of at least 20 ppm above baseline as a positive criterion (Rezaie et al., 2017).
Those breath-test numbers are laboratory protocol details, not instructions for home testing. When HFI is suspected, clinicians should address that risk before administering fructose; our lactose testing explanation shows why different sugar tests cannot be treated as interchangeable.
A positive breath result does not prove that every symptom is caused by fructose, and a negative result does not investigate the ALDOB pathway. Differences in dose, preparation, transit, and gas production affect interpretation; the SIBO سانس ٹیسٹنگ کی رہنما ہدایات explains several overlapping sources of uncertainty.
Sucrose-related gastrointestinal symptoms have another possible explanation: sucrase-isomaltase deficiency, which impairs digestion at the intestinal brush border. Our sucrase-isomaltase testing guide describes that distinction; a response to a low-FODMAP diet or digestive enzyme does not establish or safely exclude HFI.
Which routine blood and urine results can support the workup?
Routine chemistry can identify HFI complications but cannot confirm the genetic diagnosis. Depending on exposure and severity, clinicians may find hypoglycemia, increased lactate or urate, low phosphate, liver abnormalities, or evidence of proximal renal tubular dysfunction.
For perspective, glucose below 54 mg/dL, or 3.0 mmol/L, is a clinically significant hypoglycemia threshold used in diabetes care, but it is not an HFI diagnostic cutoff. In a person without diabetes, symptoms, laboratory confirmation, and context guide assessment; suspected acute HFI toxicity warrants action before every criterion is documented.
An adult phosphate reference interval is often approximately 0.8–1.5 mmol/L, equivalent to 2.5–4.6 mg/dL, but children's intervals are higher and laboratories differ. Phosphate trapping and kidney losses can contribute to low values in HFI; neither a single low phosphate nor a normal result outside an exposure episode identifies the underlying cause.
ALT and AST indicate cellular injury, while bilirubin, albumin, and coagulation results answer additional questions about liver handling or function. A hypothetical ALT of 120 U/L with an upper limit of 40 U/L is 3 times that laboratory's limit, not an HFI-specific pattern; our جگر کے فنکشن کی تفصیل separates these meanings.
Renal tubular problems can produce urinary glucose or other losses even when filtration markers are relatively preserved. Kantesti can help explain reported chemistry and trends, but a creatinine of 0.8 mg/dL does not exclude tubular dysfunction; our kidney chemistry guide explains why filtration and tubular handling are different questions.
Why should fructose challenges never be attempted at home?
Deliberate fructose exposure can cause severe hypoglycemia, metabolic disturbance, and liver or kidney injury in HFI. Do not test suspected HFI by drinking juice, eating sugar, taking sorbitol, or performing a home breath-test challenge; genetic testing does not require any of these exposures.
The older intravenous fructose tolerance test is hazardous and is not a routine recommended route to HFI diagnosis. Ali et al. (1998) describe serious diagnostic-exposure risks; an apparently small dose, 1 symptom-free exposure, or an uncertain genetic report does not establish a universally safe threshold for another trial.
Confusion, marked drowsiness, seizures, collapse, or persistent vomiting after a concerning exposure require urgent medical assessment. Call the local emergency service and say that HFI is known or suspected; do not delay care to collect a fasting sample, arrange a genetics appointment, or complete a symptom diary.
Do not give anything by mouth to a person who is unconscious, seizing, or unable to swallow safely. For an alert adult with an established hypoglycemia plan, that plan may specify 15 g of verified fructose-free glucose or dextrose and a recheck after 15 minutes; children and anyone without a plan need age-appropriate professional guidance.
Emergency clinicians may need to assess glucose, electrolytes, lactate, acid-base status, and organ function while treating the person. Our lactate handling explanation describes measurement limitations, but suspected clinical toxicity must not be dismissed as a sampling artifact or managed by waiting for an AI interpretation.
What changes after hereditary fructose intolerance is confirmed?
Confirmed HFI requires specialist-guided avoidance of fructose, sucrose, and sorbitol, with review of food ingredients, medicines, and nutritional adequacy. There is no single evidence-based gram allowance that patients should use to determine their own safe exposure limit.

A generic low-FODMAP plan is not an HFI prescription, and sugar-free does not mean sorbitol-free. Check the actual ingredient list and preparation rather than relying on a front-of-pack claim; all 3 relevant substances can appear in products that seem suitable for someone with ordinary intestinal fructose malabsorption.
Glucose, lactose, and starch are chemically different from fructose, but packaged foods containing them can still include unsafe additional ingredients. A hypothetical plain-rice meal is not equivalent to rice coated in a sweetened sauce; individualized food lists and manufacturer clarification are safer than assuming every item in a food category is suitable.
Medicines, liquid supplements, dental products, and some medical preparations need formulation-specific checks by a pharmacist or metabolic team. Do not stop treatment or refuse all vaccines based on a generic ingredient warning; the appropriate decision depends on the exact substance, quantity, route, and available alternative, not simply whether 1 unfamiliar ingredient appears.
کنٹیسٹی ایک ہے۔ اے آئی سے چلنے والا خون کے ٹیسٹ کا تجزیہ کا آلہ that can help explain nutritional laboratory follow-up, but our nutrition output is not a substitute for an HFI-specific prescription. Our vitamin needs guide explains why restricted diets merit assessment; our رازداری اور ڈیٹا کے طریقۂ کار also matter before sharing genetic documents involving relatives.
What are the next steps—and the limits of our research?
The next step is to match the full ALDOB report with clinical history through a genetics or metabolic service, not to experiment with fructose. Request clarification of classification, phase, and assay coverage; use routine laboratory interpretation as supporting information rather than molecular confirmation.

Bring 3 items to the appointment: the complete genetic report, a record of previous naturally occurring reactions, and an ingredient list for current medicines and supplements. A confirmed two-copy result, an unresolved VUS combination, and a limited negative screen require different next steps; asking which category applies is more useful than asking only whether the test is positive.
Routine results should retain their original units, reference intervals, and collection dates so changes can be assessed meaningfully. Our تکنیکی توثیق کی معلومات explains the scope of our interpretation work; it should not be read as validation of ALDOB variant classification, genotype-based dietary dosing, or emergency HFI triage.
The Kantesti research publications listed below address 2 different technical topics: multilingual hantavirus decision support involving 50,000 interpreted reports, and an automated benchmark involving 100,000 synthetic cases. Neither publication directly tests HFI diagnosis, ALDOB sequencing accuracy, VUS reclassification, or the safety of a fructose challenge, and their findings should not be generalized to those tasks.
Figshare hosting and DOI registration make a document identifiable; they do not, by themselves, establish peer review or prospective clinical validation. Our ذمہ دار AI کے اصول explain why 1 reassuring generated explanation must never outweigh concerning symptoms, the issuing genetic laboratory's limitations, or advice from a metabolic specialist.
اکثر پوچھے جانے والے سوالات
کیا کوئی جینیاتی ٹیسٹ موروثی فرکٹوز عدم برداشت کی تصدیق کر سکتا ہے؟
0 طبی ALDOB جینیاتی ٹیسٹ موروثی فرکٹوز عدم برداشت کی تصدیق کر سکتا ہے، جب طبی تاریخ کے ساتھ تشریح کرنے پر اس میں جین کی مخالف نقول کو متاثر کرنے والی 2 مرض پیدا کرنے والی یا غالباً مرض پیدا کرنے والی ویرینٹس کی شناخت ہو۔ نتیجہ ہموزائگس یا مرکب ہیٹرو زائگس ہو سکتا ہے۔ عموماً ایک مرض پیدا کرنے والی ویرینٹ کی موجودگی کیریئر ہونے کی نشاندہی کرتی ہے، جبکہ غیر یقینی ویرینٹس کے لیے مزید جائزے کی ضرورت ہوتی ہے۔ جینیاتی ٹیسٹ کے لیے فرکٹوز کا استعمال ضروری نہیں۔
ALDOB کی غیر یقینی طبی اہمیت کی حامل ویریئنٹ کا کیا مطلب ہے؟
ALDOB کا غیر یقینی اہمیت کا حامل ویریئنٹ ہونے کا مطلب ہے کہ دستیاب شواہد کی بنیاد پر اس تبدیلی کو بیماری پیدا کرنے والا یا بے ضرر قرار دینا قابلِ اعتماد طور پر ممکن نہیں۔ 1 بیماری پیدا کرنے والے ویریئنٹ اور 1 VUS پر مشتمل نتیجہ، بذاتِ خود، موروثی فرکٹوز عدم برداشت کی تصدیق نہیں کرتا۔ خاندانی جانچ، توثیق شدہ فعلی شواہد، یا مستقبل میں درجہ بندی کی نظرثانی نتیجے کو واضح کرنے میں مدد دے سکتی ہے۔ طبی تاریخ باعثِ تشویش ہو تو احتیاطی نگہداشت پھر بھی مناسب ہو سکتی ہے، لیکن غیر یقینی کو دور کرنے کے لیے فرکٹوز کا چیلنج محفوظ طریقہ نہیں ہے۔
کیا ALDOB ٹیسٹ کا منفی نتیجہ موروثی فرکٹوز عدم برداشت کو خارج کرتا ہے؟
A negative ALDOB test reduces the likelihood of hereditary fructose intolerance but may not exclude it if the assay has limited coverage. Zero detected variants means no reportable changes were found by that particular method. A common-variant screen and comprehensive sequencing with appropriate copy-number analysis provide different levels of information. Persistent clinical suspicion should prompt specialist review of the report's limitations rather than deliberate fructose exposure.
کیا فرکٹوز بریتھ ٹیسٹ، HFI ٹیسٹ ہی ہوتا ہے؟
فریکٹوز کا سانس کا ٹیسٹ آنتوں میں عدمِ جذب کی جانچ کرتا ہے، جبکہ ALDOB جینیاتی ٹیسٹ موروثی فریکٹوز عدم برداشت کی جانچ کرتا ہے۔ نارتھ امریکن کنسینسس میں بالغوں کے لیے عدمِ جذب کا ایک پروٹوکول بیان کیا گیا ہے جس میں 25 g فریکٹوز اور بنیادی سطح سے کم از کم 20 ppm ہائیڈروجن کا اضافہ استعمال ہوتا ہے، لیکن یہ طبی جانچ کی تفصیلات ہیں، گھر پر عمل کرنے کی ہدایات نہیں۔ سانس کا ٹیسٹ ALDOB کی جینیاتی اقسام کی شناخت یا ایلڈولیز B کے فعل کی پیمائش نہیں کرتا۔ جب تک معالجین میٹابولک خطرے کا جائزہ نہ لے لیں، HFI کا شبہ ہونے پر فریکٹوز نہیں دینا چاہیے۔
کیا ALDOB کے کیریئر میں موروثی فرکٹوز عدم برداشت کی علامات ظاہر ہو سکتی ہیں؟
صرف 1 بیماری پیدا کرنے والا ALDOB ویریئنٹ رکھنے والا شخص عموماً ناقل ہوتا ہے اور صرف اس دریافت کی بنیاد پر اسے موروثی فرکٹوز عدم برداشت ہونے کی توقع نہیں ہوتی۔ علامات کی پھر بھی تحقیق کی جانی چاہیے، کیونکہ ٹیسٹ میں دوسرا ویریئنٹ نظر انداز ہو سکتا ہے یا اس کی وجہ کوئی اور کیفیت ہو سکتی ہے۔ ایک ہی جین کی نقل پر موجود دو ویریئنٹس بھی خودبخود مغلوب تشخیص ثابت نہیں کرتے۔ جینیات کی سروس کو ٹیسٹ کی کوریج، فیز اور طبی تاریخ کے ساتھ نتائج کی مطابقت جانچنی چاہیے۔
Can normal blood tests exclude hereditary fructose intolerance?
Normal routine blood tests cannot exclude hereditary fructose intolerance, especially in someone who avoids fructose-containing foods. A glucose result of 90 mg/dL, approximately 5.0 mmol/L, describes that collection moment rather than the person's ALDOB genotype. Liver and kidney chemistry can also appear normal between exposures or after dietary treatment. Diagnosis relies on appropriate molecular testing and clinical assessment, not on reproducing symptoms with sugar or juice.
اپنے خون کے ٹیسٹ کے نتائج کی وضاحت حاصل کریں
اپنی لیب رپورٹ اپ لوڈ کریں اور Kantesti کا AI چند سیکنڈ میں ہر بائیومارکر کو آسان زبان میں سمجھائے گا۔ دنیا بھر میں 2 ملین سے زیادہ افراد استعمال کرتے ہیں۔.
حوالہ جات
- Klein, T., Mitchell, S., & Weber, H. (2026). ہینٹا وائرس کی ابتدائی ٹرائیج کے لیے کثیر لسانی AI معاون طبی فیصلہ سازی: ڈیزائن، انجینئرنگ کی توثیق، اور 50,000 تشریح شدہ خون کے ٹیسٹ کی رپورٹس پر حقیقی دنیا میں نفاذ۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti Blood-Test Interpretation Engine کی 100,000 مصنوعی ٹیسٹ کیسز پر ایک Pre-Registered، Rubric-Based Automated Technical Benchmark۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Ali M et al. (1998). Hereditary fructose intolerance. Journal of Medical Genetics. ڈی او آئی
- Richards S et al. (2015). سیکوئنس ویریئنٹس کی تشریح کے معیارات اور رہنما اصول: امریکن کالج آف میڈیکل جینیٹکس اینڈ جینومکس اور ایسوسی ایشن فار مالیکیولر پیتھالوجی کی مشترکہ متفقہ سفارش۔. جینیٹکس اِن میڈیسن۔. ڈی او آئی پب میڈ
- Rezaie A et al. (2017). معدے اور آنتوں کے امراض میں ہائیڈروجن اور میتھین پر مبنی سانس کے ٹیسٹ: شمالی امریکا کا اتفاقِ رائے۔. دی امریکن جرنل آف گیسٹرواینٹرولوجی۔. ڈی او آئی پب میڈ
- 2M+تجزیہ کیے گئے ٹیسٹ
- 127+ممالک
- 100+زبانیں
طبی ٹیم کے بارے میں


E-E-A-T اعتماد کے اشارے
تجربہ
معالج کی قیادت میں لیب تشریح کے ورک فلو کا کلینیکل جائزہ۔.
مہارت
لیبارٹری میڈیسن کا فوکس یہ کہ بایومارکرز کلینیکل سیاق میں کیسے برتاؤ کرتے ہیں۔.
مستندیت
ڈاکٹر تھامس کلائن نے طبی جائزہ لیا، جبکہ ڈاکٹر سارہ مچل اور پروفیسر ڈاکٹر ہانس ویبر نے بھی تعاون کیا۔.
امانت داری
شواہد پر مبنی تشریح واضح فالو اپ راستوں کے ساتھ تاکہ گھبراہٹ کم ہو۔.


طبی دستبرداری
یہ مضمون صرف تعلیمی مقاصد کے لیے ہے اور طبی مشورہ نہیں ہے۔ تشخیص اور علاج کے فیصلوں کے لیے ہمیشہ کسی مستند صحت کے ماہر سے رجوع کریں۔.
شائع ہوا۔ · ادارتی ٹیم سے رابطہ کریں
Kantesti Ltd کی جانب سے شائع کردہ، انگلینڈ اور ویلز میں رجسٹرڈ، کمپنی نمبر. 17090423, ، لندن، برطانیہ۔.
