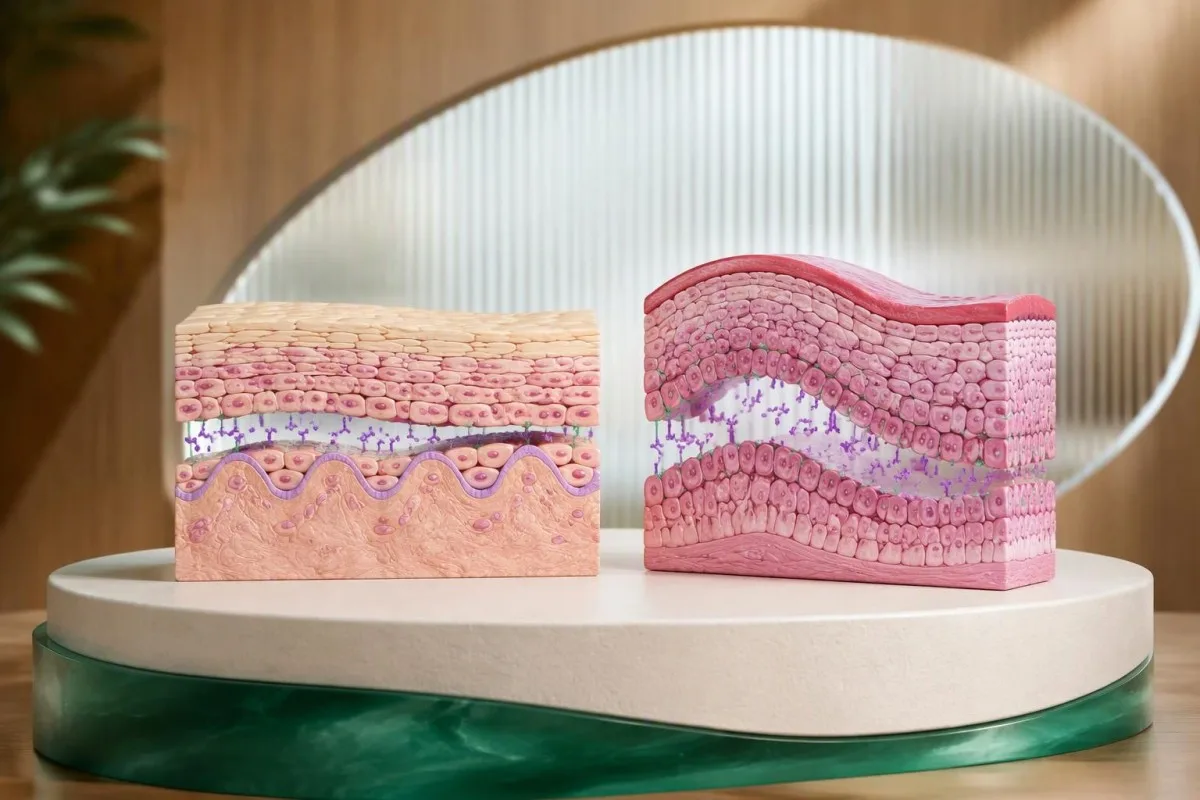
A positive desmoglein antibody test supports pemphigus only when it fits the symptoms and examination. Desmoglein 1 antibodies usually point toward skin involvement; desmoglein 3 antibodies usually point toward mouth involvement. Biopsy with direct immunofluorescence is often needed to confirm the diagnosis, particularly when findings disagree.


- Desmoglein 1 antibodies usually support a skin-predominant pemphigus pattern, especially when desmoglein 3 antibodies are negative.
- Desmoglein 3 antibodies usually support mucosal pemphigus vulgaris; mouth erosions can appear before any skin blisters.
- Both antibodies positive often supports mucocutaneous pemphigus vulgaris, but the examination can differ from the expected pattern.
- Positive cutoffs are assay-specific: some ELISAs use greater than 20 U/mL, while other laboratories use different thresholds or index values.
- A positive result alone does not establish pemphigus and does not justify starting corticosteroids or rituximab without specialist assessment.
- Two tissue specimens are commonly obtained: one from an affected edge for routine histology and one from nearby intact tissue for direct immunofluorescence.
- Direct immunofluorescence looks for antibodies deposited between epithelial cells; the specimen must not be placed in routine formalin.
- Negatibong antibodies do not exclude pemphigus when convincing erosions or fragile blisters persist, particularly after treatment.
- Kailangan ng agarang pagtatasa is needed for trouble swallowing fluids, eye pain, breathing difficulty, fever with spreading affected areas, or rapidly peeling skin.
What does the desmoglein antibody test measure?
Ang desmoglein antibody test measures circulating IgG antibodies against desmoglein 1 and desmoglein 3, proteins that help epithelial cells stick together. A positive result supports autoimmune blistering, but diagnosing pemphigus requires agreement between the antibody pattern, the clinical findings, and usually tissue examination.
Desmoglein 1 and 3 are adhesion proteins, not general markers of inflammation or allergy. They sit within desmosomes—small anchoring structures between neighboring cells—and antibodies that interfere with their function can produce acantholysis, meaning loss of cell-to-cell attachment.
Most laboratories measure these 2 antibodies separately using an enzyme-linked immunosorbent assay, or ELISA. An indirect immunofluorescence test may be ordered alongside them, but it asks a different question: whether serum antibodies recognize a characteristic pattern on a laboratory tissue substrate.
I’m Thomas Klein, MD, writing in my role as Chief Medical Officer. My approach to this result is deliberately cautious: a person with persistent mouth erosions needs a different assessment from someone with a barely positive screening result and no symptoms, even when the laboratory flags both reports.
Si Kantesti ay isang AI blood test analyzer that helps explain desmoglein 1 and 3 results alongside their laboratory ranges and reported symptoms. Our organisasyon at klinikal na pokus provide context for that role; our explanation of positibong resulta ng antibody also distinguishes antibody detection from a confirmed diagnosis.
What does desmoglein 1 antibody positive mean?
A desmoglein 1 antibody positive result most often supports skin involvement in pemphigus. When desmoglein 3 antibodies are negative and the examination shows superficial, fragile blisters or crusted erosions without mouth involvement, the pattern is particularly suggestive of pemphigus foliaceus.
Pemphigus foliaceus usually spares the mouth, despite sometimes extensive skin involvement. Its blisters are so superficial that patients may never see an intact blister; what they notice instead can be persistent scaling, crusting, or patches that seem to rub away too easily.
The scalp, face, upper chest, and back are useful examination sites when this pattern is suspected. A hypothetical 58-year-old with several weeks of crusted scalp and chest changes, desmoglein 1 of 76 U/mL, and negative desmoglein 3 deserves assessment for superficial pemphigus—not a diagnosis made from the 76 alone.
Desmoglein 1 positivity can also occur in pemphigus vulgaris, especially when skin disease accompanies mucosal disease. The distinction between foliaceus and vulgaris comes from the clinical picture and the level of epithelial separation on histology, rather than from the antibody name alone.
Itching is not a reliable sorting tool: pemphigus may itch, burn, or simply feel tender, and several more common conditions produce similar complaints. Our guide to pagsubok para sa makating balat explains why broad laboratory screening cannot replace examination of an actual affected area.
What does desmoglein 3 antibody positive mean?
A desmoglein 3 antibody positive result most often supports mucosal pemphigus vulgaris, particularly with persistent mouth erosions and negative desmoglein 1 antibodies. Mouth involvement can precede skin disease, so an otherwise normal skin examination does not dismiss this antibody pattern.
Oral pemphigus often presents as erosions rather than visible blisters, because the blister roof breaks quickly during eating or brushing. Persistent areas on the inner cheeks, palate, or gums may be mistaken for dental irritation, thrush, or ordinary canker sores before the pattern becomes clear.
Consider a hypothetical 46-year-old with 8 weeks of painful gum peeling, desmoglein 3 of 112 U/mL, and desmoglein 1 below the laboratory cutoff. That combination raises suspicion for mucosal pemphigus vulgaris, but a tissue sample remains valuable because erosive lichen planus and mucous membrane pemphigoid can look surprisingly similar.
Desmoglein 3 positivity does not measure swallowing safety or nutritional status. A patient who is drinking very little needs assessment of hydration, weight change, and possibly electrolytes even if the antibody value is modest; a higher value in someone eating normally does not automatically imply an emergency.
Recurrent discrete mouth ulcers with genital ulcers, eye symptoms, or characteristic skin findings suggest a different diagnostic route. Our discussion of Behçet mouth sore patterns explains those clues; desmoglein testing is not a screening test for Behçet disease.
How do combined desmoglein 1 and 3 patterns help?
Both desmoglein 1 and 3 antibodies positive often supports pemphigus vulgaris affecting both skin and mucosa. The desmoglein compensation model explains this tendency, but it is a useful clinical framework—not a rule that predicts every patient’s examination.
Desmoglein distribution differs between skin and oral mucosa. In skin, desmoglein 1 is abundant toward the surface while desmoglein 3 is concentrated more deeply; oral mucosa relies heavily on desmoglein 3, which helps explain why losing its function can expose the mouth before the skin.
The compensation idea is that one functioning desmoglein can partly preserve adhesion when antibodies interfere with the other. That model fits many cases, but antibody binding site, antibody pathogenicity, treatment, and other adhesion mechanisms can all make the clinical pattern less tidy than a 2-marker diagram suggests.
Murrell et al. (2020), in the international pemphigus recommendations, describe desmoglein 1 and 3 ELISA as useful for diagnosis and follow-up while emphasizing clinical and immunopathological correlation. The practical lesson is simple: antibodies help classify a convincing phenotype; they should not manufacture one in an asymptomatic person.
Total IgG is not a substitute for anti-desmoglein IgG, and a normal total IgG concentration does not exclude pathogenic antibodies against either protein. Our immunoglobulin result guide explains the difference between measuring the size of an antibody class and identifying its particular target.
What are the positive cutoffs and normal ranges?
Desmoglein antibody cutoffs are laboratory-specific, and there is no universal normal range that applies to every assay. Some ELISA systems classify both antibodies as positive above 20 U/mL while using different negative and borderline bands for desmoglein 1 and desmoglein 3.
The table below illustrates one commonly used ELISA reporting convention, not a universal standard. A report using a 20 U/mL threshold, a 30 U/mL threshold, or an index value must be read using its own instructions; apparently identical numbers can have different meanings across assay systems.
A result of 21 U/mL is close to a cutoff of greater than 20 U/mL and deserves more caution than the laboratory’s positive flag may suggest. It does not mean there is a 21% probability of pemphigus, and 100 U/mL does not mean five times as much tissue damage as 20 U/mL.
No desmoglein concentration is a universal emergency threshold. Urgency comes from rapidly spreading skin involvement, inability to drink, eye symptoms, breathing symptoms, or systemic illness; a laboratory report marked high without those findings calls for clinical interpretation, not automatic emergency treatment.
Before comparing 2 reports, check the antibody target, units, laboratory, assay method, and whether either value exceeded the instrument’s measuring range. Our explanation of qualitative at quantitative tests shows why a positive label and a measured concentration carry different kinds of information.
Why does a positive result not establish pemphigus?
A positive desmoglein result does not establish pemphigus because detectable antibodies may be low-level, nonpathogenic, or inconsistent with the patient’s symptoms. The probability that a positive result represents disease also depends on why the test was ordered in the first place.
Pretest probability strongly affects the meaning of antibody positivity. A positive result in someone with months of characteristic mouth erosions is more persuasive than the same result found during broad screening for fatigue, where the clinical picture provides little support for pemphigus.
Here is an illustrative calculation—not an estimate of desmoglein assay performance: if a test has 95% sensitivity and 99% specificity, testing 10,000 people in a population with 1% disease prevalence produces about 95 true positives and 99 false positives. Only about 49% of positive results would represent disease in that hypothetical setting.
Nonpathogenic anti-desmoglein antibodies can recognize parts of the protein that do not meaningfully disrupt adhesion. This helps explain why antibody concentration is not a direct measurement of blister formation, and why specialists sometimes investigate an unexpected positive with another laboratory method rather than simply repeating the same assay.
A similar principle applies to other disease-specific autoantibodies, although the confirmation pathway is different for each condition. Our guide to interpreting MOG antibody positivity illustrates why a recognizable syndrome and an appropriate assay matter; its neurological criteria should not be transferred to pemphigus.
Can pemphigus occur with negative desmoglein antibodies?
Negative desmoglein 1 and 3 results do not completely exclude pemphigus, especially after treatment or when the clinical findings are strongly suggestive. Persistent fragile blisters or mucosal erosions may still require histology and direct immunofluorescence despite negative serum testing.
Serum testing measures circulating antibodies at one time point, not every antibody present within tissue. Low concentrations, assay limitations, or antibodies against additional epithelial targets can help explain a mismatch between the laboratory result and the examination.
Treatment history changes the interpretation of a negative result. If a person began systemic corticosteroids or received B-cell-directed treatment before the sample was collected, a low antibody concentration may reflect treatment effect rather than establish that the original erosions were unrelated to pemphigus.
Repeating serum testing alone is not the best next step when the clinical suspicion is high. A dermatologist may arrange 2 appropriately sited tissue specimens, add indirect immunofluorescence, or request a broader blistering-disease panel while reviewing medication exposures and the original onset of symptoms.
A negative test is most reassuring when the symptoms, examination, and other investigations also point away from the disease. Our discussion of negative autoimmune neuromuscular tests explains the same general reasoning, although the relevant antibodies and confirmatory procedures are entirely different.
When is biopsy with direct immunofluorescence needed?
Biopsy with direct immunofluorescence is usually recommended during the initial assessment of suspected pemphigus, especially with borderline antibodies, atypical symptoms, or disagreement between serum testing and examination. Routine histology and direct immunofluorescence answer different questions, so clinicians commonly obtain 2 separate specimens.
Routine histology identifies where epithelial cells separate, while direct immunofluorescence identifies immunoreactants deposited within the patient’s tissue. International recommendations from Murrell et al. (2020) support combining clinical findings, histology, and immunological evidence rather than relying on serum positivity alone.
The routine histology specimen is usually taken from the edge of a fresh affected area so it includes useful epithelium. The direct immunofluorescence specimen comes from nearby intact tissue; many services use a site a few millimeters from the affected area, with the exact choice adapted for skin, oral mucosa, and local laboratory instructions.
A direct immunofluorescence specimen must not go into routine formalin, because that can compromise the examination. It generally needs the receiving laboratory’s specified transport medium, such as Michel’s medium, or another validated handling pathway; arranging this before sampling prevents an avoidable repeat procedure.
Occasionally, a specialist can establish the diagnosis using a strongly compatible presentation, characteristic histology, and convincing serology when direct immunofluorescence is unavailable. Kantesti’s klinikal na framework ng validation describes our interpretation standards, not a replacement for specialist tissue diagnosis; antibodies and kidney biopsy illustrate how biopsy exceptions differ by disease.
What do pemphigus histology and immunofluorescence show?
Pemphigus direct immunofluorescence typically shows intercellular IgG, often with C3, in a net-like epithelial pattern. Routine histology usually shows suprabasal separation in pemphigus vulgaris and more superficial separation in pemphigus foliaceus, helping distinguish conditions with similar-looking erosions.
The classic pemphigus vulgaris split occurs above the basal epithelial layer. Basal cells may remain attached to the underlying basement membrane, creating the histological appearance often described as a row of tombstones; this is a tissue-level clue, not something a patient can recognize from a photograph.
A linear band along the basement membrane suggests a different family of autoimmune blistering disorders, including pemphigoid conditions. The distinction between an intercellular net and a basement-membrane line can redirect antibody testing toward targets such as BP180 rather than desmoglein 1 or 3.
A negative direct immunofluorescence result is not always definitive if sampling or handling was suboptimal. Sampling an eroded center, obtaining too little intact epithelium, using the wrong medium, or testing after substantial treatment can reduce the diagnostic yield; the specialist may request another specimen if the discrepancy remains convincing.
C3 detected in epithelial tissue is not interchangeable with a serum C3 concentration. Our complement and autoimmune testing guide explains circulating complement measurements; a normal serum C3 result does not cancel an intercellular C3 finding on direct immunofluorescence.
What else can cause mouth erosions and skin blisters?
Pemphigoid disorders, erosive lichen planus, infections, medication reactions, and mechanical injury can resemble pemphigus. A desmoglein-positive result should not stop the differential diagnosis, especially when the distribution, blister firmness, scarring, or onset after a new medicine points elsewhere.
Bullous pemphigoid often produces firmer, tense blisters and prominent itching, whereas pemphigus blisters are generally more fragile. Mucous membrane pemphigoid deserves particular attention with eye symptoms or scarring because protecting vision and other vulnerable mucosal sites may be more urgent than resolving the serum antibody label.
Painful grouped changes in a one-sided distribution suggest a viral cause rather than a typical pemphigus pattern. Our guide to early shingles symptom clues explains that distribution; unusual, widespread, or oral presentations still need examination rather than a photo-based conclusion.
Blisters on sun-exposed hands with skin fragility can suggest porphyria cutanea tarda, which follows a different testing pathway. Our porphyria testing during symptoms article distinguishes biochemical testing from autoimmune antibody testing; urinary porphyrin assessment may be relevant to a blistering porphyria phenotype.
Severe, persistent stomatitis with an unusual widespread eruption can raise concern for paraneoplastic pemphigus, also called paraneoplastic autoimmune multiorgan syndrome. Specialist testing may include antibodies to envoplakin or periplakin and selected indirect immunofluorescence methods; a routine 2-antibody desmoglein panel does not fully assess that possibility.
How should you prepare, and do medicines affect testing?
Desmoglein antibody testing usually does not require fasting, although other tests collected at the same visit may have separate instructions. Tell the clinician about immunosuppressive treatment, recent infusions, and new medicines; do not stop prescribed treatment just to make an antibody test easier to interpret.
The date of treatment initiation matters as much as the medication name. Recording whether the sample preceded corticosteroids, rituximab, or other immunosuppression helps the dermatologist interpret a later negative or falling result; keep the original report even when a newer report appears more reassuring.
Some medicines, including penicillamine and captopril, have been associated with drug-induced pemphigus. A new medication does not automatically explain a blistering eruption, but its start date, dose changes, and the interval before symptoms are useful; never discontinue an essential medicine without a prescribing clinician’s plan.
Infection-risk assessment is separate from confirming pemphigus, but becomes important when immunosuppression is being considered. For people with relevant residence or travel exposure, our guide to Strongyloides bago ang immunosuppression explains why this parasite deserves attention before substantial corticosteroid treatment.
Azathioprine safety assessment commonly includes TPMT and, where appropriate, NUDT15 testing, alongside blood counts and liver monitoring. Our explanation of Pagsusuri sa TPMT bago ang azathioprine covers that preparation; a positive desmoglein result alone is not a reason to start this medication or any other systemic treatment.
Can antibody levels monitor remission or predict relapse?
Desmoglein antibody trends can support pemphigus monitoring, but they cannot define remission or predict every relapse. New affected areas, healing, oral symptoms, and treatment exposure remain central; a persistently positive result in a clinically well patient does not automatically require more immunosuppression.
Desmoglein 1 levels often track skin activity more closely than desmoglein 3 levels track oral activity. The relationship is imperfect, and some patients remain desmoglein 3 positive during clinical remission; Joly et al. (2020), in the EADV management guideline, place serological monitoring within a broader clinical assessment.
Murrell et al. (2020) suggest checking antibodies at treatment initiation, after approximately 3 months, and then every 3–6 months or with relapse, adjusted to the clinical course. That is a follow-up framework for diagnosed pemphigus—not a recommendation to repeatedly screen asymptomatic people with an incidental low-positive result.
A change from 80 to 40 U/mL is a numerical decline, not proof that disease activity has halved. Compare results from the same assay when possible, note whether the original result exceeded the measuring range, and record the timing of treatment; our gabay sa trend ng kaligtasan ng gamot explains why timelines matter.
Si Kantesti ay isang AI blood test interpretation platform that can organize desmoglein results with dates, reference intervals, and other uploaded laboratory findings. Our gabay sa teknolohiya ng AI interpretation explains the workflow, but the platform cannot inspect mucosal surfaces, measure a validated clinical activity score, or authorize a medication taper.
What should you do after a positive desmoglein result?
Arrange clinical review after a positive desmoglein result, with dermatology or oral medicine assessment when erosions or blisters are present. Seek urgent care for inability to swallow fluids, eye pain or vision change, breathing difficulty, fever with spreading skin changes, or rapidly peeling skin; do not wait for repeat antibodies.
An asymptomatic low-positive result and widespread active blistering need different timelines. For an unexpected result without symptoms, contact the ordering clinician to review the indication and assay; for ongoing oral or skin changes, ask specifically whether histology and direct immunofluorescence should be arranged rather than simply repeating the panel.
Bring 2 kinds of evidence: the complete laboratory report and a dated symptom timeline. Photographs of changing affected areas, a current medication list, approximate weight change, and whether eating or drinking has become difficult can help the specialist choose a useful sampling site and assess immediate support needs.
My practical recommendation as Thomas Klein, MD, is to ask: “What finding would confirm or refute pemphigus in my case?” Our medical advisory board describes the physicians involved in clinical oversight; an individual diagnosis still belongs with the clinician who examines you and evaluates the relevant tissue evidence.
Si Kantesti ay isang serbisyo ng AI lab test interpretation that can help translate a desmoglein report into questions for that appointment, not certify pemphigus from a PDF. Our guide to checking AI medical explanations recommends verifying units, source text, and limitations; never let an automated reassurance override difficulty drinking, eye symptoms, or rapid deterioration.
Research publications and the limits of interpretation evidence
Pemphigus diagnostic recommendations come from disease-specific clinical literature, not from general AI interpretation benchmarks. As of October 17, 2026, the international recommendations by Murrell et al. (2020) and the EADV guideline by Joly et al. (2020) remain relevant references for the diagnostic and monitoring principles discussed here.
The 2 publications below describe Kantesti materials and do not establish desmoglein test accuracy or prove pemphigus diagnostic capability. A Zenodo DOI identifies a deposited record; it does not, by itself, show peer review, prospective clinical validation, or reliable performance in autoimmune blistering disease.
Kantesti. (n.d.). Clinical validation framework v2.0 (Medical validation page). Zenodo. https://doi.org/10.5281/zenodo.17993721. The DOI record is the primary reference; the accompanying ResearchGate and Academia.edu links are discovery searches, not claims that this record is hosted or independently reviewed there.
Kantesti. (2026). AI blood test analyzer: 2.5M tests analyzed | Global health report 2026. Zenodo. https://doi.org/10.5281/zenodo.18175532. The test count in the publication title should not be interpreted as the number of confirmed pemphigus cases, desmoglein assays, or diagnostic comparisons.
General laboratory abnormalities can identify complications without confirming pemphigus. Albumin and other proteins may be relevant when extensive skin involvement or restricted intake affects nutrition, but our gabay sa interpretasyon ng serum protein addresses those supportive measurements; histology, immunofluorescence, and appropriate antibody testing remain a separate diagnostic pathway.
Mga Madalas Itanong
Nangangahulugan ba na mayroon akong pemphigus ang positibong pagsusuri para sa mga antibody laban sa desmoglein?
Ang positibong resulta ng pagsusuri para sa desmoglein antibody ay hindi nangangahulugan, sa sarili nito, na mayroon kang pemphigus. Dapat tumugma ang resulta sa mga natuklasan sa pagsusuri, mga sintomas, at karaniwan ay sa mga natuklasan sa tissue mula sa routine histology at direct immunofluorescence. Gumagamit ang ilang ELISA system ng higit sa 20 U/mL bilang positibong cutoff, ngunit nagkakaiba ang mga threshold ng laboratoryo at hindi gaanong kapani-paniwala ang bahagyang positibong resulta kung walang sintomas. Huwag simulan ang immunosuppressive treatment batay lamang sa resulta ng antibody.
What is the difference between desmoglein 1 and desmoglein 3 antibodies?
Desmoglein 1 antibodies usually support skin involvement, while desmoglein 3 antibodies usually support mucosal involvement, especially persistent mouth erosions. Desmoglein 1 positivity with negative desmoglein 3 often fits pemphigus foliaceus, whereas desmoglein 3 positivity alone often fits mucosal pemphigus vulgaris. Positivity for both of these 2 antibodies often fits mucocutaneous pemphigus vulgaris. These patterns guide assessment but do not reliably predict every patient's symptoms.
What desmoglein antibody level is considered positive?
The positive desmoglein antibody level depends on the laboratory and assay. One commonly used ELISA convention classifies values above 20 U/mL as positive, with desmoglein 1 borderline at 14–20 U/mL and desmoglein 3 borderline at 9–20 U/mL. Other assays use different cutoffs or index values, so the range printed on your report takes priority. No antibody concentration is a universal emergency or disease-severity threshold.
Do I need a biopsy if my desmoglein antibodies are positive?
A biopsy is usually recommended when pemphigus is first suspected, especially if symptoms are atypical, antibodies are borderline, or examination and serum testing disagree. Clinicians commonly obtain 2 specimens: an affected edge for routine histology and nearby intact tissue for direct immunofluorescence. The direct immunofluorescence specimen requires the laboratory's specified handling and must not be placed in routine formalin. A specialist may occasionally establish the diagnosis using characteristic clinical findings, histology, and serology when direct immunofluorescence is unavailable.
Can I have pemphigus with negative desmoglein 1 and 3 tests?
Pemphigus can occur despite negative desmoglein 1 and 3 serum tests, particularly after treatment or when antibody concentrations are below assay detection thresholds. Negative results for these 2 antibodies are more reassuring when the examination also points away from pemphigus. Persistent fragile blisters or mouth erosions may still require histology, direct immunofluorescence, or additional specialist antibody testing. Do not postpone assessment of worsening symptoms while waiting for another serum test.
Can desmoglein antibodies stay positive when pemphigus is in remission?
Desmoglein antibodies can remain positive during clinical remission, particularly desmoglein 3 antibodies. International recommendations describe testing at treatment initiation, after approximately 3 months, and then every 3–6 months or with relapse, adjusted to the patient's course. Antibody trends support monitoring but do not replace assessment of new affected areas, healing, eating, and drinking. A persistently positive result alone does not justify increasing treatment.
Do I need to fast before a desmoglein antibody test?
Fasting is usually unnecessary for a desmoglein antibody test, although other tests collected at the same appointment may require it. Report treatment with corticosteroids, rituximab, or other immunosuppressive medicines because these can affect interpretation of the 2 antibody measurements. Record whether the sample was collected before or after treatment began. Do not stop prescribed medicines unless the prescribing clinician gives you a specific plan.
Kumuha ng AI-Powered Blood Test Analysis Ngayon
Sumali sa mahigit 2 milyong user sa buong mundo na nagtitiwala sa Kantesti para sa agarang at tumpak na pagsusuri ng lab test. I-upload ang iyong resulta ng blood test at makakuha ng komprehensibong interpretasyon ng mga biomarker ng 15,000+ sa loob ng ilang segundo.
📚 Mga Sanggunian na Publikasyon sa Pananaliksik
Klein, T., Mitchell, S., & Weber, H. (2026). Clinical Validation Framework v2.0 (Medical Validation Page). Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2.5M na mga pagsusuri ang sinuri | Global Health Report 2026. Kantesti AI Medical Research.
📖 Mga Panlabas na Sanggunian sa Medikal
Murrell DF et al. (2020). Diagnosis and management of pemphigus: Recommendations of an international panel of experts. Journal of the American Academy of Dermatology.
Joly P et al. (2020). Updated S2K guidelines on the management of pemphigus vulgaris and foliaceus initiated by the European Academy of Dermatology and Venereology (EADV). Journal ng European Academy of Dermatology and Venereology.
⚕️ Pagtatanggi sa Medikal
Ang artikulong ito ay para sa mga layuning pang-edukasyon lamang at hindi ito bumubuo ng medikal na payo. Palaging kumonsulta sa isang kwalipikadong tagapagbigay ng pangangalagang pangkalusugan para sa mga desisyon sa diagnosis at paggamot.
Mga Signal ng Tiwala ng E-E-A-T
Karanasan
Pinamumunuan ng manggagamot na klinikal na pagsusuri ng mga daloy ng interpretasyon ng mga pagsusuri sa laboratoryo.
Kadalubhasaan
Pokus sa laboratoryong medisina kung paano kumikilos ang mga biomarker sa kontekstong klinikal.
Pagka-awtoridad
Isinulat ni Dr. Thomas Klein na may pagsusuri ni Dr. Sarah Mitchell at Prof. Dr. Hans Weber.
Pagiging Mapagkakatiwalaan
Interpretasyong nakabatay sa ebidensya na may malinaw na mga susunod na hakbang upang mabawasan ang pag-aalarma.