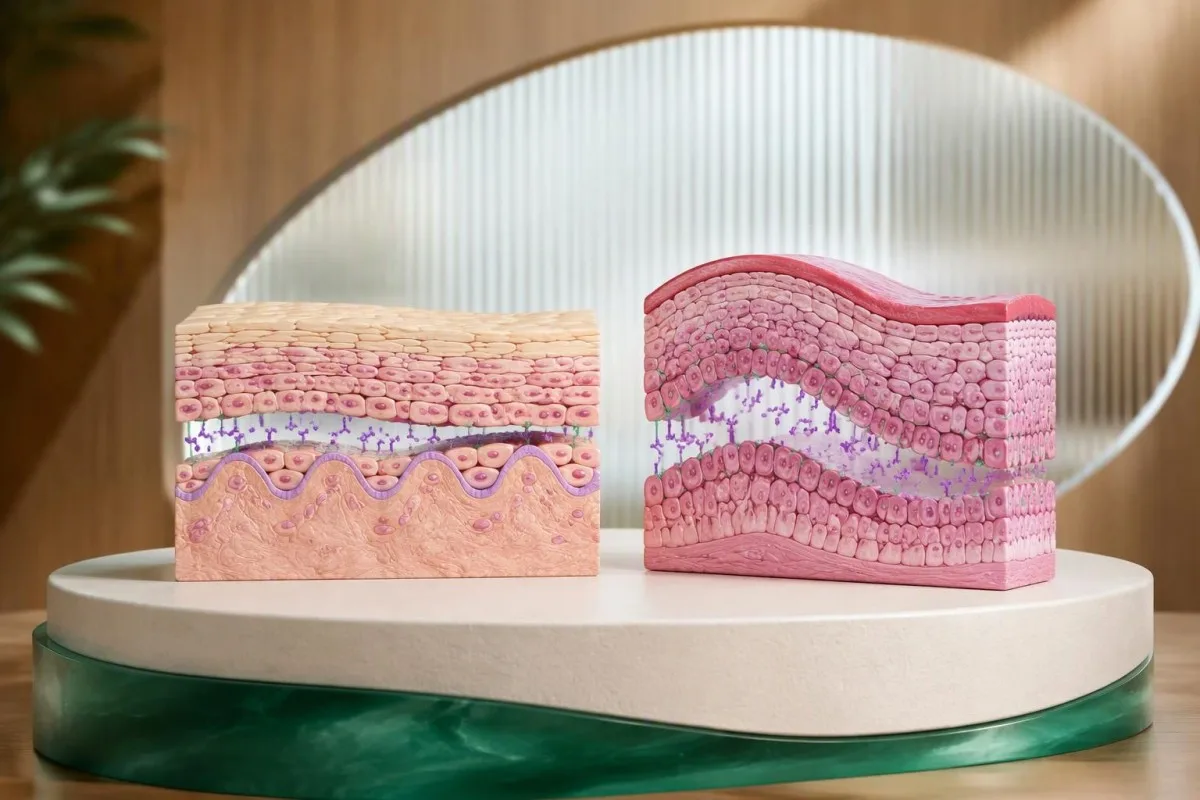
ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষার ফল পজিটিভ হলে তা পেমফিগাসের পক্ষে যায় কেবল তখনই, যখন তা উপসর্গ ও পরীক্ষার ফলাফলের সঙ্গে মেলে। ডেসমোগ্লেইন ১ অ্যান্টিবডি সাধারণত ত্বকের সংশ্লিষ্টতার ইঙ্গিত দেয়; ডেসমোগ্লেইন ৩ অ্যান্টিবডি সাধারণত মুখের সংশ্লিষ্টতার ইঙ্গিত দেয়। রোগনির্ণয় নিশ্চিত করতে প্রায়ই ডাইরেক্ট ইমিউনোফ্লুরোসেন্সসহ বায়োপসি প্রয়োজন হয়, বিশেষত যখন ফলাফলগুলো পরস্পরের সঙ্গে মেলে না।.


- ডেসমোগ্লেইন ১ অ্যান্টিবডি সাধারণত ত্বক-প্রধান পেমফিগাসের ধরনকে সমর্থন করে, বিশেষত যখন ডেসমোগ্লেইন ৩ অ্যান্টিবডি নেগেটিভ থাকে।.
- ডেসমোগ্লেইন ৩ অ্যান্টিবডি সাধারণত মিউকোসাল পেমফিগাস ভালগারিসকে সমর্থন করে; ত্বকে কোনো ফোসকা দেখা দেওয়ার আগেই মুখে ক্ষয় দেখা দিতে পারে।.
- উভয় অ্যান্টিবডি পজিটিভ প্রায়ই মিউকোকিউটেনিয়াস পেমফিগাস ভালগারিসকে সমর্থন করে, তবে পরীক্ষায় প্রত্যাশিত ধরনটি নাও দেখা যেতে পারে।.
- পজিটিভ হওয়ার কাটঅফ পরীক্ষাপদ্ধতিভেদে আলাদা: কিছু ELISA-তে ২০ U/mL-এর বেশি মান ব্যবহার করা হয়, আবার অন্য পরীক্ষাগারগুলো ভিন্ন সীমা বা ইনডেক্স মান ব্যবহার করে।.
- শুধু পজিটিভ ফলাফল পেমফিগাস প্রতিষ্ঠা করে না এবং বিশেষজ্ঞের মূল্যায়ন ছাড়া কর্টিকোস্টেরয়েড বা রিতুক্সিমাব শুরু করার যৌক্তিকতা দেয় না।.
- দুটি টিস্যুর নমুনা সাধারণত সংগ্রহ করা হয়: একটি নিয়মিত হিস্টোলজির জন্য আক্রান্ত স্থানের প্রান্ত থেকে এবং অন্যটি সরাসরি ইমিউনোফ্লুরোসেন্সের জন্য কাছাকাছি অক্ষত টিস্যু থেকে।.
- সরাসরি ইমিউনোফ্লুরোসেন্স এপিথেলিয়াল কোষের মধ্যবর্তী স্থানে জমা হওয়া অ্যান্টিবডি খুঁজে দেখে; নমুনাটি নিয়মিত ফরমালিনে রাখা যাবে না।.
- নেতিবাচক অ্যান্টিবডি জোরালোভাবে সন্দেহজনক ক্ষয় বা ভঙ্গুর ফোস্কা থেকে গেলে, বিশেষ করে চিকিৎসার পর, পেমফিগাস বাদ দেয় না।.
- জরুরি মূল্যায়ন তরল গিলতে অসুবিধা, চোখে ব্যথা, শ্বাসকষ্ট, আক্রান্ত এলাকা ছড়িয়ে পড়ার সঙ্গে জ্বর, অথবা ত্বক দ্রুত উঠে গেলে প্রয়োজন।.
ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষা কী পরিমাপ করে?
দ্য ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষা ডেসমোগ্লেইন ১ ও ডেসমোগ্লেইন ৩-এর বিরুদ্ধে সঞ্চালনশীল IgG অ্যান্টিবডি পরিমাপ করে—এই প্রোটিনগুলো এপিথেলিয়াল কোষগুলোকে পরস্পরের সঙ্গে লেগে থাকতে সাহায্য করে। ইতিবাচক ফল অটোইমিউন ফোস্কা-সৃষ্টিকারী রোগের পক্ষে যায়, কিন্তু পেমফিগাস নির্ণয়ের জন্য অ্যান্টিবডির ধরন, ক্লিনিক্যাল পর্যবেক্ষণ এবং সাধারণত টিস্যু পরীক্ষার ফলের মধ্যে সামঞ্জস্য থাকা প্রয়োজন।.
ডেসমোগ্লেইন ১ ও ৩ হলো সংযুক্তি-প্রোটিন, সাধারণ প্রদাহ বা অ্যালার্জির নির্দেশক নয়। এগুলো ডেসমোসোমের মধ্যে থাকে—পাশাপাশি কোষগুলোর মধ্যকার ছোট নোঙরকারী কাঠামোতে—এবং এদের কার্যকারিতায় বাধা দেয় এমন অ্যান্টিবডি অ্যাকান্থোলাইসিস ঘটাতে পারে, যার অর্থ কোষে-কোষে সংযুক্তি হারিয়ে যাওয়া।.
অধিকাংশ পরীক্ষাগারে এনজাইম-লিঙ্কড ইমিউনোসরবেন্ট অ্যাসে বা ELISA ব্যবহার করে এই দুটি অ্যান্টিবডি আলাদাভাবে মাপা হয়। এগুলোর পাশাপাশি পরোক্ষ ইমিউনোফ্লুরোসেন্স পরীক্ষাও করা হতে পারে, তবে সেটি ভিন্ন একটি প্রশ্নের উত্তর দেয়: সিরামের অ্যান্টিবডি পরীক্ষাগারের টিস্যু সাবস্ট্রেটে একটি বৈশিষ্ট্যপূর্ণ ধরন শনাক্ত করে কি না।.
আমি থমাস ক্লেইন, MD, চিফ মেডিকেল অফিসার হিসেবে আমার ভূমিকায় লিখছি। এই ফলের ক্ষেত্রে আমার দৃষ্টিভঙ্গি ইচ্ছাকৃতভাবেই সতর্ক: মুখে ক্ষয় দীর্ঘস্থায়ী হওয়া ব্যক্তির মূল্যায়ন করতে হবে এমন কারও থেকে ভিন্নভাবে, যার স্ক্রিনিং ফল সামান্য ইতিবাচক এবং কোনো উপসর্গ নেই—যদিও পরীক্ষাগার উভয় রিপোর্টেই চিহ্নিত করে।.
কান্তেস্তি হল একটি এআই রক্ত পরীক্ষা বিশ্লেষক যা ডেসমোগ্লেইন ১ ও ৩-এর ফলকে তাদের পরীক্ষাগার-নির্ধারিত সীমা এবং রিপোর্ট করা উপসর্গের সঙ্গে মিলিয়ে বুঝতে সাহায্য করে। আমাদের সংস্থা এবং ক্লিনিকাল ফোকাস সেই ভূমিকার প্রেক্ষাপট দেয়; আমাদের ব্যাখ্যা পজিটিভ অ্যান্টিবডি ফলাফল অ্যান্টিবডি শনাক্তকরণ ও নিশ্চিত রোগনির্ণয়ের মধ্যকার পার্থক্যও স্পষ্ট করে।.
ডেসমোগ্লেইন ১ অ্যান্টিবডি পজিটিভ হওয়ার অর্থ কী?
A ডেসমোগ্লেইন ১ অ্যান্টিবডি ইতিবাচক ফলটি পেমফিগাসে ত্বকের সম্পৃক্ততার পক্ষে যায়। যখন ডেসমোগ্লেইন ৩ অ্যান্টিবডি নেতিবাচক থাকে এবং পরীক্ষায় মুখের সম্পৃক্ততা ছাড়া উপরিভাগের ভঙ্গুর ফোস্কা বা খোসাযুক্ত ক্ষয় দেখা যায়, তখন এই ধরনটি বিশেষভাবে নির্দেশ করে পেমফিগাস ফোলিয়াসিয়াস.
পেমফিগাস ফোলিয়াসিয়াসে সাধারণত মুখ আক্রান্ত হয় না, যদিও কখনও ত্বকের বিস্তৃত অংশ আক্রান্ত হতে পারে। ফোস্কাগুলো এতটাই উপরিভাগে থাকে যে রোগীরা হয়তো কখনও অক্ষত ফোস্কা দেখতেই পান না; বরং তাঁরা স্থায়ী আঁশ ওঠা, খোসা পড়া বা এমন দাগ লক্ষ্য করতে পারেন, যা খুব সহজেই ঘষে উঠে যায় বলে মনে হয়।.
এই ধরন সন্দেহ হলে মাথার ত্বক, মুখ, বুকের ওপরের অংশ এবং পিঠ পরীক্ষা করার জন্য উপযোগী স্থান। ধরা যাক, ৫৮ বছর বয়সী একজন ব্যক্তির কয়েক সপ্তাহ ধরে মাথার ত্বক ও বুকে খোসাযুক্ত পরিবর্তন রয়েছে, ডেসমোগ্লেইন ১-এর মাত্রা ৭৬ U/mL এবং ডেসমোগ্লেইন ৩ নেতিবাচক—তাঁর উপরিভাগের পেমফিগাসের জন্য মূল্যায়ন প্রয়োজন; শুধু ৭৬-এর ভিত্তিতে রোগনির্ণয় নয়।.
পেমফিগাস ভালগারিসেও ডেসমোগ্লেইন ১ পজিটিভ হতে পারে, especially when skin disease accompanies mucosal disease. The distinction between foliaceus and vulgaris comes from the clinical picture and the level of epithelial separation on histology, rather than from the antibody name alone.
Itching is not a reliable sorting tool: pemphigus may itch, burn, or simply feel tender, and several more common conditions produce similar complaints. Our guide to চুলকানির জন্য পরীক্ষা explains why broad laboratory screening cannot replace examination of an actual affected area.
ডেসমোগ্লেইন ৩ অ্যান্টিবডি পজিটিভ হওয়ার অর্থ কী?
A desmoglein 3 antibody positive result most often supports mucosal pemphigus vulgaris, particularly with persistent mouth erosions and negative desmoglein 1 antibodies. Mouth involvement can precede skin disease, so an otherwise normal skin examination does not dismiss this antibody pattern.
Oral pemphigus often presents as erosions rather than visible blisters, because the blister roof breaks quickly during eating or brushing. Persistent areas on the inner cheeks, palate, or gums may be mistaken for dental irritation, thrush, or ordinary canker sores before the pattern becomes clear.
Consider a hypothetical 46-year-old with 8 weeks of painful gum peeling, desmoglein 3 of 112 U/mL, and desmoglein 1 below the laboratory cutoff. That combination raises suspicion for mucosal pemphigus vulgaris, but a tissue sample remains valuable because erosive lichen planus and mucous membrane pemphigoid can look surprisingly similar.
Desmoglein 3 positivity does not measure swallowing safety or nutritional status. A patient who is drinking very little needs assessment of hydration, weight change, and possibly electrolytes even if the antibody value is modest; a higher value in someone eating normally does not automatically imply an emergency.
Recurrent discrete mouth ulcers with genital ulcers, eye symptoms, or characteristic skin findings suggest a different diagnostic route. Our discussion of Behçet mouth sore patterns explains those clues; desmoglein testing is not a screening test for Behçet disease.
ডেসমোগ্লেইন ১ ও ৩-এর সম্মিলিত ধরনগুলো কীভাবে সহায়তা করে?
Both desmoglein 1 and 3 antibodies positive often supports pemphigus vulgaris affecting both skin and mucosa. The desmoglein compensation model explains this tendency, but it is a useful clinical framework—not a rule that predicts every patient’s examination.
Desmoglein distribution differs between skin and oral mucosa. In skin, desmoglein 1 is abundant toward the surface while desmoglein 3 is concentrated more deeply; oral mucosa relies heavily on desmoglein 3, which helps explain why losing its function can expose the mouth before the skin.
The compensation idea is that one functioning desmoglein can partly preserve adhesion when antibodies interfere with the other. That model fits many cases, but antibody binding site, antibody pathogenicity, treatment, and other adhesion mechanisms can all make the clinical pattern less tidy than a 2-marker diagram suggests.
Murrell et al. (2020), in the international pemphigus recommendations, describe desmoglein 1 and 3 ELISA as useful for diagnosis and follow-up while emphasizing clinical and immunopathological correlation. The practical lesson is simple: antibodies help classify a convincing phenotype; they should not manufacture one in an asymptomatic person.
Total IgG is not a substitute for anti-desmoglein IgG, and a normal total IgG concentration does not exclude pathogenic antibodies against either protein. Our immunoglobulin result guide explains the difference between measuring the size of an antibody class and identifying its particular target.
পজিটিভ হওয়ার কাটঅফ ও স্বাভাবিক সীমা কত?
Desmoglein antibody cutoffs are laboratory-specific, and there is no universal normal range that applies to every assay. Some ELISA systems classify both antibodies as positive above 20 U/mL while using different negative and borderline bands for desmoglein 1 and desmoglein 3.
The table below illustrates one commonly used ELISA reporting convention, not a universal standard. A report using a 20 U/mL threshold, a 30 U/mL threshold, or an index value must be read using its own instructions; apparently identical numbers can have different meanings across assay systems.
A result of 21 U/mL is close to a cutoff of greater than 20 U/mL and deserves more caution than the laboratory’s positive flag may suggest. It does not mean there is a 21% probability of pemphigus, and 100 U/mL does not mean five times as much tissue damage as 20 U/mL.
No desmoglein concentration is a universal emergency threshold. Urgency comes from rapidly spreading skin involvement, inability to drink, eye symptoms, breathing symptoms, or systemic illness; a laboratory report marked high without those findings calls for clinical interpretation, not automatic emergency treatment.
Before comparing 2 reports, check the antibody target, units, laboratory, assay method, and whether either value exceeded the instrument’s measuring range. Our explanation of গুণগত এবং পরিমাণগত পরীক্ষা shows why a positive label and a measured concentration carry different kinds of information.
পজিটিভ ফল কেন পেমফিগাস নিশ্চিত করে না?
A positive desmoglein result does not establish pemphigus because detectable antibodies may be low-level, nonpathogenic, or inconsistent with the patient’s symptoms. The probability that a positive result represents disease also depends on why the test was ordered in the first place.
Pretest probability strongly affects the meaning of antibody positivity. A positive result in someone with months of characteristic mouth erosions is more persuasive than the same result found during broad screening for fatigue, where the clinical picture provides little support for pemphigus.
Here is an illustrative calculation—not an estimate of desmoglein assay performance: if a test has 95% sensitivity and 99% specificity, testing 10,000 people in a population with 1% disease prevalence produces about 95 true positives and 99 false positives. Only about 49% of positive results would represent disease in that hypothetical setting.
Nonpathogenic anti-desmoglein antibodies can recognize parts of the protein that do not meaningfully disrupt adhesion. This helps explain why antibody concentration is not a direct measurement of blister formation, and why specialists sometimes investigate an unexpected positive with another laboratory method rather than simply repeating the same assay.
A similar principle applies to other disease-specific autoantibodies, although the confirmation pathway is different for each condition. Our guide to interpreting MOG antibody positivity illustrates why a recognizable syndrome and an appropriate assay matter; its neurological criteria should not be transferred to pemphigus.
ডেসমোগ্লেইন অ্যান্টিবডি নেগেটিভ হলেও কি পেমফিগাস হতে পারে?
Negative desmoglein 1 and 3 results do not completely exclude pemphigus, especially after treatment or when the clinical findings are strongly suggestive. Persistent fragile blisters or mucosal erosions may still require histology and direct immunofluorescence despite negative serum testing.
Serum testing measures circulating antibodies at one time point, not every antibody present within tissue. Low concentrations, assay limitations, or antibodies against additional epithelial targets can help explain a mismatch between the laboratory result and the examination.
Treatment history changes the interpretation of a negative result. If a person began systemic corticosteroids or received B-cell-directed treatment before the sample was collected, a low antibody concentration may reflect treatment effect rather than establish that the original erosions were unrelated to pemphigus.
Repeating serum testing alone is not the best next step when the clinical suspicion is high. A dermatologist may arrange 2 appropriately sited tissue specimens, add indirect immunofluorescence, or request a broader blistering-disease panel while reviewing medication exposures and the original onset of symptoms.
A negative test is most reassuring when the symptoms, examination, and other investigations also point away from the disease. Our discussion of negative autoimmune neuromuscular tests explains the same general reasoning, although the relevant antibodies and confirmatory procedures are entirely different.
কখন ডাইরেক্ট ইমিউনোফ্লুরোসেন্সসহ বায়োপসি প্রয়োজন হয়?
Biopsy with direct immunofluorescence is usually recommended during the initial assessment of suspected pemphigus, especially with borderline antibodies, atypical symptoms, or disagreement between serum testing and examination. Routine histology and direct immunofluorescence answer different questions, so clinicians commonly obtain 2 separate specimens.
Routine histology identifies where epithelial cells separate, while direct immunofluorescence identifies immunoreactants deposited within the patient’s tissue. International recommendations from Murrell et al. (2020) support combining clinical findings, histology, and immunological evidence rather than relying on serum positivity alone.
The routine histology specimen is usually taken from the edge of a fresh affected area so it includes useful epithelium. The direct immunofluorescence specimen comes from nearby intact tissue; many services use a site a few millimeters from the affected area, with the exact choice adapted for skin, oral mucosa, and local laboratory instructions.
A direct immunofluorescence specimen must not go into routine formalin, because that can compromise the examination. It generally needs the receiving laboratory’s specified transport medium, such as Michel’s medium, or another validated handling pathway; arranging this before sampling prevents an avoidable repeat procedure.
Occasionally, a specialist can establish the diagnosis using a strongly compatible presentation, characteristic histology, and convincing serology when direct immunofluorescence is unavailable. Kantesti’s ক্লিনিক্যাল ভ্যালিডেশন ফ্রেমওয়ার্ক describes our interpretation standards, not a replacement for specialist tissue diagnosis; antibodies and kidney biopsy illustrate how biopsy exceptions differ by disease.
পেমফিগাসের হিস্টোলজি ও ইমিউনোফ্লুরোসেন্সে কী দেখা যায়?
Pemphigus direct immunofluorescence typically shows intercellular IgG, often with C3, in a net-like epithelial pattern. Routine histology usually shows suprabasal separation in pemphigus vulgaris and more superficial separation in pemphigus foliaceus, helping distinguish conditions with similar-looking erosions.
The classic pemphigus vulgaris split occurs above the basal epithelial layer. Basal cells may remain attached to the underlying basement membrane, creating the histological appearance often described as a row of tombstones; this is a tissue-level clue, not something a patient can recognize from a photograph.
A linear band along the basement membrane suggests a different family of autoimmune blistering disorders, including pemphigoid conditions. The distinction between an intercellular net and a basement-membrane line can redirect antibody testing toward targets such as BP180 rather than desmoglein 1 or 3.
A negative direct immunofluorescence result is not always definitive if sampling or handling was suboptimal. Sampling an eroded center, obtaining too little intact epithelium, using the wrong medium, or testing after substantial treatment can reduce the diagnostic yield; the specialist may request another specimen if the discrepancy remains convincing.
C3 detected in epithelial tissue is not interchangeable with a serum C3 concentration. Our complement and autoimmune testing guide explains circulating complement measurements; a normal serum C3 result does not cancel an intercellular C3 finding on direct immunofluorescence.
মুখের ক্ষয় ও ত্বকের ফোসকার অন্য কারণ কী হতে পারে?
Pemphigoid disorders, erosive lichen planus, infections, medication reactions, and mechanical injury can resemble pemphigus. A desmoglein-positive result should not stop the differential diagnosis, especially when the distribution, blister firmness, scarring, or onset after a new medicine points elsewhere.
Bullous pemphigoid often produces firmer, tense blisters and prominent itching, whereas pemphigus blisters are generally more fragile. Mucous membrane pemphigoid deserves particular attention with eye symptoms or scarring because protecting vision and other vulnerable mucosal sites may be more urgent than resolving the serum antibody label.
Painful grouped changes in a one-sided distribution suggest a viral cause rather than a typical pemphigus pattern. Our guide to early shingles symptom clues explains that distribution; unusual, widespread, or oral presentations still need examination rather than a photo-based conclusion.
Blisters on sun-exposed hands with skin fragility can suggest porphyria cutanea tarda, which follows a different testing pathway. Our porphyria testing during symptoms article distinguishes biochemical testing from autoimmune antibody testing; urinary porphyrin assessment may be relevant to a blistering porphyria phenotype.
Severe, persistent stomatitis with an unusual widespread eruption can raise concern for paraneoplastic pemphigus, also called paraneoplastic autoimmune multiorgan syndrome. Specialist testing may include antibodies to envoplakin or periplakin and selected indirect immunofluorescence methods; a routine 2-antibody desmoglein panel does not fully assess that possibility.
কীভাবে প্রস্তুতি নেবেন, এবং ওষুধ কি পরীক্ষার ফলকে প্রভাবিত করে?
Desmoglein antibody testing usually does not require fasting, although other tests collected at the same visit may have separate instructions. Tell the clinician about immunosuppressive treatment, recent infusions, and new medicines; do not stop prescribed treatment just to make an antibody test easier to interpret.
The date of treatment initiation matters as much as the medication name. Recording whether the sample preceded corticosteroids, rituximab, or other immunosuppression helps the dermatologist interpret a later negative or falling result; keep the original report even when a newer report appears more reassuring.
Some medicines, including penicillamine and captopril, have been associated with drug-induced pemphigus. A new medication does not automatically explain a blistering eruption, but its start date, dose changes, and the interval before symptoms are useful; never discontinue an essential medicine without a prescribing clinician’s plan.
Infection-risk assessment is separate from confirming pemphigus, but becomes important when immunosuppression is being considered. For people with relevant residence or travel exposure, our guide to ইমিউনোসপ্রেশনের আগে স্ট্রংগাইলয়েডস explains why this parasite deserves attention before substantial corticosteroid treatment.
Azathioprine safety assessment commonly includes TPMT and, where appropriate, NUDT15 testing, alongside blood counts and liver monitoring. Our explanation of অ্যাজাথিওপ্রিনের আগে TPMT পরীক্ষা covers that preparation; a positive desmoglein result alone is not a reason to start this medication or any other systemic treatment.
অ্যান্টিবডির মাত্রা কি রোগমুক্তি পর্যবেক্ষণ করতে বা পুনরায় রোগের পূর্বাভাস দিতে পারে?
Desmoglein antibody trends can support pemphigus monitoring, but they cannot define remission or predict every relapse. New affected areas, healing, oral symptoms, and treatment exposure remain central; a persistently positive result in a clinically well patient does not automatically require more immunosuppression.
Desmoglein 1 levels often track skin activity more closely than desmoglein 3 levels track oral activity. The relationship is imperfect, and some patients remain desmoglein 3 positive during clinical remission; Joly et al. (2020), in the EADV management guideline, place serological monitoring within a broader clinical assessment.
Murrell et al. (2020) suggest checking antibodies at treatment initiation, after approximately 3 months, and then every 3–6 months or with relapse, adjusted to the clinical course. That is a follow-up framework for diagnosed pemphigus—not a recommendation to repeatedly screen asymptomatic people with an incidental low-positive result.
A change from 80 to 40 U/mL is a numerical decline, not proof that disease activity has halved. Compare results from the same assay when possible, note whether the original result exceeded the measuring range, and record the timing of treatment; our ওষুধের নিরাপত্তা ট্রেন্ড গাইড explains why timelines matter.
কান্তেস্তি হল একটি AI রক্ত পরীক্ষার ফলাফল বোঝার প্ল্যাটফর্ম that can organize desmoglein results with dates, reference intervals, and other uploaded laboratory findings. Our এআই ব্যাখ্যা প্রযুক্তি গাইড explains the workflow, but the platform cannot inspect mucosal surfaces, measure a validated clinical activity score, or authorize a medication taper.
ডেসমোগ্লেইন পরীক্ষার ফল পজিটিভ হলে কী করা উচিত?
Arrange clinical review after a positive desmoglein result, with dermatology or oral medicine assessment when erosions or blisters are present. Seek urgent care for inability to swallow fluids, eye pain or vision change, breathing difficulty, fever with spreading skin changes, or rapidly peeling skin; do not wait for repeat antibodies.
An asymptomatic low-positive result and widespread active blistering need different timelines. For an unexpected result without symptoms, contact the ordering clinician to review the indication and assay; for ongoing oral or skin changes, ask specifically whether histology and direct immunofluorescence should be arranged rather than simply repeating the panel.
Bring 2 kinds of evidence: the complete laboratory report and a dated symptom timeline. Photographs of changing affected areas, a current medication list, approximate weight change, and whether eating or drinking has become difficult can help the specialist choose a useful sampling site and assess immediate support needs.
My practical recommendation as Thomas Klein, MD, is to ask: “What finding would confirm or refute pemphigus in my case?” Our চিকিৎসা উপদেষ্টা বোর্ড describes the physicians involved in clinical oversight; an individual diagnosis still belongs with the clinician who examines you and evaluates the relevant tissue evidence.
কান্তেস্তি হল একটি AI ল্যাব টেস্ট ইন্টারপ্রিটেশন সার্ভিসে that can help translate a desmoglein report into questions for that appointment, not certify pemphigus from a PDF. Our guide to checking AI medical explanations recommends verifying units, source text, and limitations; never let an automated reassurance override difficulty drinking, eye symptoms, or rapid deterioration.
গবেষণাপত্র এবং ফলাফল ব্যাখ্যার প্রমাণের সীমাবদ্ধতা
Pemphigus diagnostic recommendations come from disease-specific clinical literature, not from general AI interpretation benchmarks. As of October 17, 2026, the international recommendations by Murrell et al. (2020) and the EADV guideline by Joly et al. (2020) remain relevant references for the diagnostic and monitoring principles discussed here.
The 2 publications below describe Kantesti materials and do not establish desmoglein test accuracy or prove pemphigus diagnostic capability. A Zenodo DOI identifies a deposited record; it does not, by itself, show peer review, prospective clinical validation, or reliable performance in autoimmune blistering disease.
Kantesti. (n.d.). Clinical validation framework v2.0 (Medical validation page). Zenodo. https://doi.org/10.5281/zenodo.17993721. The DOI record is the primary reference; the accompanying ResearchGate and Academia.edu links are discovery searches, not claims that this record is hosted or independently reviewed there.
Kantesti. (2026). AI blood test analyzer: 2.5M tests analyzed | Global health report 2026. Zenodo. https://doi.org/10.5281/zenodo.18175532. The test count in the publication title should not be interpreted as the number of confirmed pemphigus cases, desmoglein assays, or diagnostic comparisons.
General laboratory abnormalities can identify complications without confirming pemphigus. Albumin and other proteins may be relevant when extensive skin involvement or restricted intake affects nutrition, but our সিরাম প্রোটিন ব্যাখ্যার নির্দেশিকা addresses those supportive measurements; histology, immunofluorescence, and appropriate antibody testing remain a separate diagnostic pathway.
সচরাচর জিজ্ঞাস্য
ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষার ফল পজিটিভ হলে কি আমার পেমফিগাস হয়েছে বোঝায়?
ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষার ফল পজিটিভ হলেই যে আপনার পেমফিগাস আছে, তা নয়। ফলটি শারীরিক পরীক্ষা, উপসর্গ এবং সাধারণত রুটিন হিস্টোলজি ও ডাইরেক্ট ইমিউনোফ্লুরোসেন্সে পাওয়া টিস্যুর ফলাফলের সঙ্গে মিলতে হবে। কিছু ELISA পদ্ধতিতে 20 U/mL-এর বেশি মাত্রাকে পজিটিভ ধরা হয়, তবে পরীক্ষাগারভেদে সীমামান আলাদা এবং উপসর্গ ছাড়া সামান্য পজিটিভ ফল কম বিশ্বাসযোগ্য। শুধু অ্যান্টিবডি পরীক্ষার ফলের ভিত্তিতে ইমিউনোসাপ্রেসিভ চিকিৎসা শুরু করবেন না।.
ডেসমোগ্লেইন ১ এবং ডেসমোগ্লেইন ৩ অ্যান্টিবডির মধ্যে পার্থক্য কী?
ডেসমোগ্লেইন 1 অ্যান্টিবডি সাধারণত ত্বকের সম্পৃক্ততার পক্ষে প্রমাণ দেয়, আর ডেসমোগ্লেইন 3 অ্যান্টিবডি সাধারণত শ্লৈষ্মিক ঝিল্লির সম্পৃক্ততার পক্ষে প্রমাণ দেয়, বিশেষত মুখের স্থায়ী ক্ষয়ের ক্ষেত্রে। ডেসমোগ্লেইন 1 পজিটিভ এবং ডেসমোগ্লেইন 3 নেগেটিভ হলে তা প্রায়ই পেমফিগাস ফোলিয়াসিয়াসের সঙ্গে মেলে, অন্যদিকে শুধু ডেসমোগ্লেইন 3 পজিটিভ হলে তা প্রায়ই শ্লৈষ্মিক পেমফিগাস ভালগারিসের সঙ্গে মেলে। এই 2টি অ্যান্টিবডিই পজিটিভ হলে তা প্রায়ই মিউকোকিউটেনিয়াস পেমফিগাস ভালগারিসের সঙ্গে মেলে। এই ধরনগুলো মূল্যায়নে দিকনির্দেশনা দেয়, তবে প্রতিটি রোগীর উপসর্গ নির্ভরযোগ্যভাবে পূর্বাভাস দেয় না।.
কোন ডেসমোগ্লেইন অ্যান্টিবডির মাত্রাকে পজিটিভ হিসেবে বিবেচনা করা হয়?
পজিটিভ ডেসমোগ্লেইন অ্যান্টিবডির মাত্রা পরীক্ষাগার ও অ্যাসের ওপর নির্ভর করে। ELISA-তে প্রচলিত একটি নিয়মে ২০ U/mL-এর বেশি মানকে পজিটিভ হিসেবে শ্রেণিবদ্ধ করা হয়; ডেসমোগ্লেইন ১-এর ক্ষেত্রে ১৪–২০ U/mL এবং ডেসমোগ্লেইন ৩-এর ক্ষেত্রে ৯–২০ U/mL-কে বর্ডারলাইন ধরা হয়। অন্য অ্যাসেতে ভিন্ন কাটঅফ বা ইনডেক্স মান ব্যবহৃত হয়, তাই আপনার রিপোর্টে মুদ্রিত রেফারেন্স রেঞ্জকেই অগ্রাধিকার দিন। কোনো অ্যান্টিবডির ঘনত্বই সর্বজনীন জরুরি অবস্থা বা রোগের তীব্রতার সীমা নয়।.
আমার ডেসমোগ্লিন অ্যান্টিবডি পজিটিভ হলে কি আমার বায়োপসি করানো দরকার?
পেমফিগাস প্রথম সন্দেহ হলে সাধারণত বায়োপসি করার পরামর্শ দেওয়া হয়, বিশেষ করে উপসর্গ অস্বাভাবিক হলে, অ্যান্টিবডির মাত্রা সীমান্তবর্তী হলে, অথবা শারীরিক পরীক্ষা ও সিরাম পরীক্ষার ফলের মধ্যে অমিল থাকলে। চিকিৎসকেরা সাধারণত ২টি নমুনা সংগ্রহ করেন: নিয়মিত হিস্টোলজির জন্য আক্রান্ত স্থানের প্রান্ত থেকে একটি এবং প্রত্যক্ষ ইমিউনোফ্লুরোসেন্সের জন্য কাছাকাছি অক্ষত টিস্যু থেকে আরেকটি। প্রত্যক্ষ ইমিউনোফ্লুরোসেন্সের নমুনা পরীক্ষাগারের নির্দিষ্ট নির্দেশনা অনুযায়ী সংরক্ষণ ও প্রেরণ করতে হয় এবং এটি কখনোই নিয়মিত ফরমালিনে রাখা যাবে না। প্রত্যক্ষ ইমিউনোফ্লুরোসেন্সের ব্যবস্থা না থাকলে, কোনো বিশেষজ্ঞ কখনো কখনো বৈশিষ্ট্যপূর্ণ ক্লিনিক্যাল লক্ষণ, হিস্টোলজি ও সেরোলজির ভিত্তিতে রোগনির্ণয় করতে পারেন।.
ডেসমোগ্লেইন ১ ও ৩ পরীক্ষার ফল নেগেটিভ হলেও কি আমার পেমফিগাস হতে পারে?
ডেসমোগ্লেইন ১ ও ৩-এর সিরাম পরীক্ষার ফল নেগেটিভ হলেও পেমফিগাস হতে পারে, বিশেষত চিকিৎসার পরে বা অ্যান্টিবডির ঘনত্ব পরীক্ষায় শনাক্তকরণের সীমার নিচে থাকলে। পরীক্ষায় পেমফিগাসের সম্ভাবনা কম বলে ইঙ্গিত পাওয়া গেলে এই ২টি অ্যান্টিবডির নেগেটিভ ফল আরও আশ্বস্তকারী। স্থায়ী ভঙ্গুর ফোসকা বা মুখের ক্ষতের ক্ষেত্রে এখনও হিস্টোলজি, ডাইরেক্ট ইমিউনোফ্লুরোসেন্স বা বিশেষজ্ঞের মাধ্যমে অতিরিক্ত অ্যান্টিবডি পরীক্ষা প্রয়োজন হতে পারে। আরেকটি সিরাম পরীক্ষার জন্য অপেক্ষা করতে গিয়ে উপসর্গের অবনতির মূল্যায়ন পিছিয়ে দেবেন না।.
0 পেমফিগাস প্রশমিত অবস্থায় থাকলেও কি ডেসমোগ্লেইন অ্যান্টিবডি পজিটিভ থাকতে পারে?
0 ডেসমোগ্লেইন অ্যান্টিবডি ক্লিনিক্যাল রেমিশনের সময়ও পজিটিভ থাকতে পারে, বিশেষ করে ডেসমোগ্লেইন ৩ অ্যান্টিবডি। আন্তর্জাতিক সুপারিশে চিকিৎসা শুরুর সময়, প্রায় ৩ মাস পর এবং এরপর প্রতি ৩–৬ মাস অন্তর বা রোগ পুনরায় দেখা দিলে, রোগীর অবস্থার সঙ্গে সামঞ্জস্য রেখে পরীক্ষা করার কথা বলা হয়েছে। অ্যান্টিবডির প্রবণতা পর্যবেক্ষণে সহায়তা করে, তবে নতুন আক্রান্ত স্থান, নিরাময়, খাওয়া এবং পান করার মূল্যায়নের বিকল্প নয়। শুধু ফলাফল ক্রমাগত পজিটিভ থাকলেই চিকিৎসা বাড়ানোর যুক্তি হয় না।.
ডেসমোগ্লেইন অ্যান্টিবডি পরীক্ষার আগে কি আমাকে উপবাস করতে হবে?
0 উপযুক্ত চিকিৎসকের পরামর্শে নির্দিষ্ট পরিকল্পনা না দেওয়া হলে নির্ধারিত ওষুধ বন্ধ করবেন না। Desmoglein অ্যান্টিবডি পরীক্ষার জন্য সাধারণত উপবাসের প্রয়োজন হয় না, তবে একই অ্যাপয়েন্টমেন্টে সংগৃহীত অন্যান্য পরীক্ষার জন্য উপবাসের প্রয়োজন হতে পারে। কর্টিকোস্টেরয়েড, রিটুক্সিম্যাব বা অন্যান্য ইমিউনোসাপ্রেসিভ ওষুধ দিয়ে চিকিৎসার কথা জানান, কারণ এগুলো 2টি অ্যান্টিবডি পরিমাপের ফল ব্যাখ্যাকে প্রভাবিত করতে পারে। চিকিৎসা শুরু হওয়ার আগে না পরে নমুনা সংগ্রহ করা হয়েছে, তা নথিভুক্ত করুন।.
আজই এআই-চালিত রক্ত পরীক্ষার বিশ্লেষণ পান
বিশ্বজুড়ে 2 মিলিয়নেরও বেশি ব্যবহারকারীকে সাথে নিন যারা তাত্ক্ষণিক ও নির্ভুল ল্যাব টেস্ট বিশ্লেষণের জন্য Kantesti-কে বিশ্বাস করেন। আপনার রক্ত পরীক্ষার রিপোর্ট আপলোড করুন এবং কয়েক সেকেন্ডের মধ্যে 15,000+ বায়োমার্কারগুলোর ব্যাপক ব্যাখ্যা পান।.
📚 উদ্ধৃত গবেষণা প্রকাশনা
Klein, T., Mitchell, S., & Weber, H. (2026)।. ক্লিনিক্যাল ভ্যালিডেশন ফ্রেমওয়ার্ক v2.0 (মেডিক্যাল ভ্যালিডেশন পেজ).। Kantesti এআই মেডিক্যাল রিসার্চ।.
Klein, T., Mitchell, S., & Weber, H. (2026)।. এআই রক্ত পরীক্ষা বিশ্লেষক: 2.5Mটি পরীক্ষা বিশ্লেষণ করা হয়েছে | গ্লোবাল হেলথ রিপোর্ট 2026.। Kantesti এআই মেডিক্যাল রিসার্চ।.
📖 বাহ্যিক চিকিৎসা সংক্রান্ত রেফারেন্স
Murrell DF et al. (2020). Diagnosis and management of pemphigus: Recommendations of an international panel of experts. আমেরিকান একাডেমি অব ডার্মাটোলজির জার্নাল।.
Joly P et al. (2020). Updated S2K guidelines on the management of pemphigus vulgaris and foliaceus initiated by the European Academy of Dermatology and Venereology (EADV). জার্নাল অফ দ্য ইউরোপিয়ান একাডেমি অফ ডার্মাটোলজি অ্যান্ড ভেনেরিওলজি।.
⚕️ মেডিকেল ডিসক্লেমার
এই প্রবন্ধটি কেবল শিক্ষামূলক উদ্দেশ্যে এবং এটি চিকিৎসা পরামর্শ হিসেবে গণ্য হয় না। রোগ নির্ণয় ও চিকিৎসা সিদ্ধান্তের জন্য সর্বদা একজন যোগ্য স্বাস্থ্যসেবা প্রদানকারীর সাথে পরামর্শ করুন।.
E-E-A-T বিশ্বাসযোগ্যতার সংকেত
অভিজ্ঞতা
চিকিৎসক-নেতৃত্বাধীন ল্যাব ব্যাখ্যা কর্মপ্রবাহের ক্লিনিক্যাল পর্যালোচনা।.
দক্ষতা
ক্লিনিকাল প্রেক্ষাপটে বায়োমার্কারগুলো কীভাবে আচরণ করে, সেটির ওপর ল্যাবরেটরি মেডিসিনের ফোকাস।.
কর্তৃত্ব
ড. থমাস ক্লেইন লিখেছেন; পর্যালোচনা করেছেন ড. সারাহ মিচেল এবং প্রফ. ড. হান্স ওয়েবার।.
বিশ্বাসযোগ্যতা
প্রমাণভিত্তিক ব্যাখ্যা, যাতে সতর্কতা কমাতে স্পষ্ট পরবর্তী পদক্ষেপের পথ থাকে।.