
A salicylate level cannot establish safety by itself: clinicians interpret it with symptoms, blood pH, kidney function and repeat measurements. An early low result can miss delayed aspirin absorption, while chronic toxicity can be serious at lower concentrations. Suspected poisoning needs immediate assessment—not a wait for laboratory results.

Mambo muhimu ya kukumbuka
- Immediate assessment is needed for suspected aspirin poisoning; call emergency services for confusion, seizures, collapse or breathing difficulty rather than waiting for a result.
- Salicylate therapeutic range often spans approximately 10–30 mg/dL, depending on indication and laboratory convention; this is not a guarantee against toxicity.
- Ubadilishaji wa vitengo matters: 30 mg/dL equals 300 mg/L and approximately 2.17 mmol/L.
- Early low results cannot exclude poisoning because enteric-coated aspirin and large ingestions can produce delayed concentration peaks, sometimes beyond 12–24 hours.
- Serial measurements are commonly repeated about every 2 hours initially, with the interval adjusted to symptoms, formulation and treatment.
- Chronic toxicity can warrant dialysis consideration around 40 mg/dL when significant neurological or pulmonary manifestations are present.
- Acid–base status can reveal danger despite a near-normal pH; bicarbonate of 12 mmol/L with a carbon dioxide pressure of 20 mmHg can produce a pH near 7.40.
- Dialysis thresholds include a concentration above 100 mg/dL, or above 90 mg/dL with impaired kidney function, under EXTRIP recommendations; severe symptoms can justify treatment below these numbers.
When suspected aspirin poisoning needs immediate care
Suspected salicylate poisoning requires immediate assessment, even before a salicylate level is available. New rapid breathing, repeated vomiting, ringing ears or confusion after aspirin exposure should prompt urgent poison-service or emergency advice; severe breathing difficulty, seizures or collapse require emergency services immediately.

A result is only one part of an emergency assessment. In the UK, call 999 au 112 for severe symptoms; in the United States, call 911, or Poison Control at 1-800-222-1222 for immediate exposure advice when the person is stable.
Bring the medicine packaging, approximate amount, formulation and earliest possible ingestion time. A single product may contain more than one painkiller, which is why clinicians sometimes request an acetaminophen concentration assessment alongside salicylate testing rather than assuming every tablet contained aspirin alone.
Do not induce vomiting, give home charcoal or try to correct acidity with baking soda. While arranging care, avoid further aspirin or salicylate-containing products; if the person becomes drowsy, do not give anything by mouth because swallowing may no longer be safe.
Kantesti ni Mchambuzi wa mtihani wa damu wa AI that can help explain a completed laboratory report, not an emergency poisoning service. A report showing 15 mg/dL cannot establish safety when the ingestion time is uncertain, symptoms are evolving or the first sample was collected before absorption finished.
What a salicylate level measures and which units matter
A salicylate level measures the concentration of salicylate in serum or plasma, usually in mg/dL, mg/L or mmol/L. Laboratory therapeutic intervals commonly cover roughly 10–30 mg/dL, but the intended treatment, timing and symptoms determine whether a particular result is acceptable.

One mg/dL equals 10 mg/L. For salicylate, 1 mg/dL also equals approximately 0.0724 mmol/L, so a result of 30 mg/dL is 300 mg/L or 2.17 mmol/L; mistaking mg/L for mg/dL introduces a tenfold interpretation error.
A salicylate therapeutic range is a treatment reference, not a normal physiological requirement. Analgesic references may use approximately 10–20 mg/dL, while historical anti-inflammatory monitoring often uses 15–30 mg/dL; low-dose aspirin for platelet inhibition does not need to achieve these concentrations.
The laboratory flag cannot grade poisoning on its own. A symptomatic older adult at 35 mg/dL may need more urgent intervention than a clinically stable person with an acute exposure at the same concentration; our explanation of bendera za maabara zilizo nje ya kiwango separates reference intervals from decision thresholds.
For a clearly hypothetical comparison, 280 mg/L and 28 mg/dL describe exactly the same concentration. Neither value answers whether the level is rising, whether the blood is becoming more acidic or whether neurological symptoms have appeared—those questions require time-stamped results and bedside assessment.
| Kiwango | Wigo | Maana yake |
|---|---|---|
| Common treatment reference | Approximately 10–30 mg/dL | Indication-dependent therapeutic interval, not a poisoning clearance threshold; toxicity can occur within or near this interval. |
| Potentially toxic concentration | 30–50 mg/dL | Requires assessment of symptoms, exposure pattern, pH and serial results; chronic toxicity may be clinically significant. |
| Substantial toxic exposure | 50–100 mg/dL | Urgent monitored assessment is needed; serious toxicity and dialysis indications can occur below 100 mg/dL. |
| EXTRIP concentration indication | > 100 mg/dL | EXTRIP recommends extracorporeal treatment; the concentration threshold is lower with impaired kidney function. |
Why an early low salicylate result can be misleading
An early low salicylate level can be misleading because aspirin may still be in the stomach or intestine rather than fully absorbed. Enteric-coated tablets, large ingestions, slowed gastric emptying and tablet concretions can delay the peak, sometimes beyond 12–24 hours.
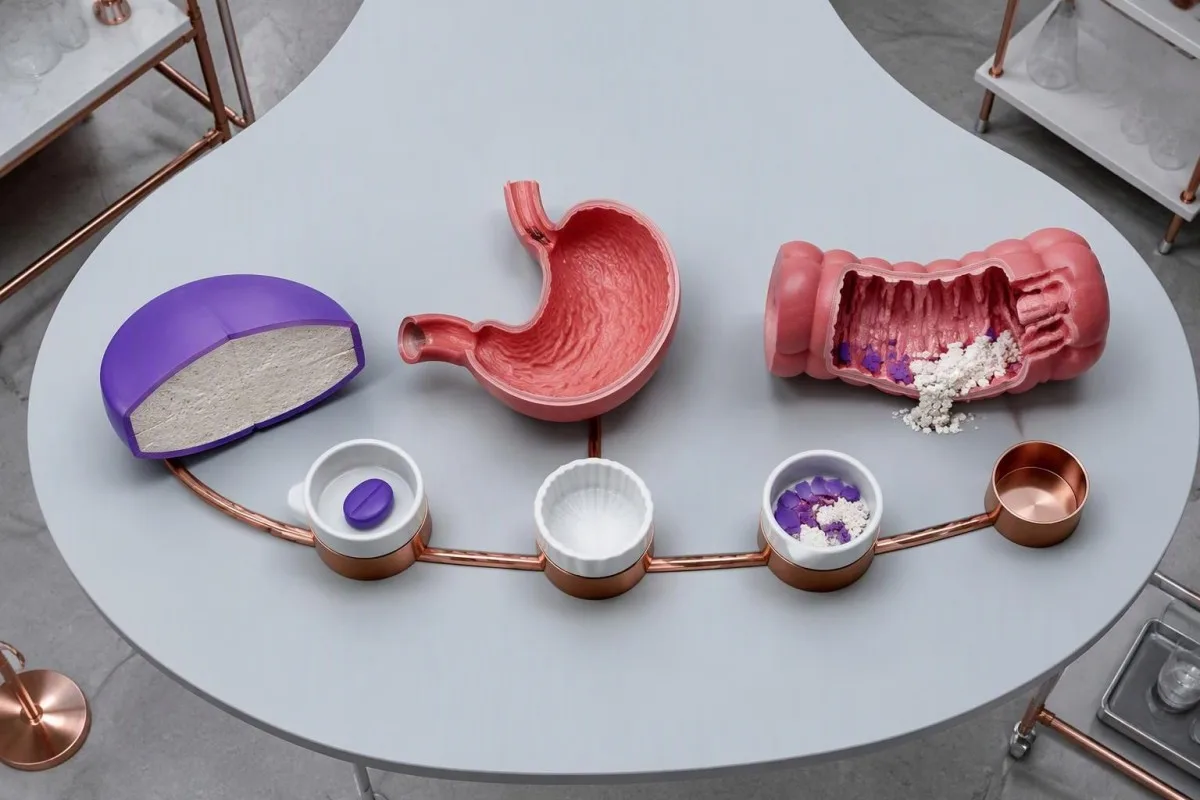
The first sample should be collected promptly, not postponed until an assumed peak time. Clinicians then repeat it according to the exposure; a result collected 1 hour after ingestion is a starting measurement, not evidence that the full dose has already entered the circulation.
Enteric coatings are designed to resist dissolution in the stomach, but overdose absorption is less predictable than ordinary dosing. Other medicines can also slow gut movement; the same need to understand formulation appears in our guide to delayed carbamazepine absorption, although its interpretation rules are different.
Consider a hypothetical sequence: 8 mg/dL at 1 hour, 24 mg/dL at 3 hours and 46 mg/dL at 5 hours. The first result was genuinely low, yet its reassuring appearance disappeared as absorption continued; treatment decisions should not depend on that isolated early number.
There is no universal 4-hour salicylate result that clears every aspirin exposure. The American College of Medical Toxicology recommends serial concentrations until they are clearly declining and ongoing absorption has been excluded; clinical deterioration still overrides an apparently favorable trend (ACMT, 2015).
How acute aspirin overdose differs from chronic toxicity
Acute aspirin overdose follows a discrete large exposure, while chronic salicylate toxicity develops through repeated dosing and accumulation. Chronic toxicity often causes serious illness at lower measured concentrations because the circulating level does not fully represent salicylate already distributed into tissues.

An acute-on-chronic exposure combines both patterns: a person already taking salicylates receives an additional excessive dose. A concentration of 45 mg/dL cannot be assigned the same risk in all three situations, so clinicians ask about medication use over preceding days as well as the most recent dose.
Older adults are particularly vulnerable when dehydration, fever or impaired kidney function reduces clearance. Aspirin-containing pain products may be overlooked during a medicine review; our guide to athari za dawa kwa wazee explains why nonprescription products belong on the same list as prescribed treatment.
Salicylate binding to albumin becomes saturated as concentrations increase, allowing a larger unbound fraction to circulate. Low albumin can further complicate interpretation; albumin and protein binding provide context, but there is no routinely accepted albumin-correction equation that makes a salicylate result safe.
At Kantesti, we distinguish concentration from clinical severity rather than presenting 40 mg/dL as a universal dividing line. ACMT guidance specifically describes significant chronic toxicity around this concentration as a situation where dialysis may deserve consideration, particularly with central nervous system abnormalities or lung involvement (ACMT, 2015).
Which aspirin overdose symptoms change the interpretation
Aspirin overdose symptoms commonly include tinnitus, nausea, vomiting, sweating and unusually fast or deep breathing. Confusion, agitation, reduced alertness, seizures, high temperature or worsening oxygen requirements indicate more serious toxicity and can justify urgent treatment even without a very high salicylate level.
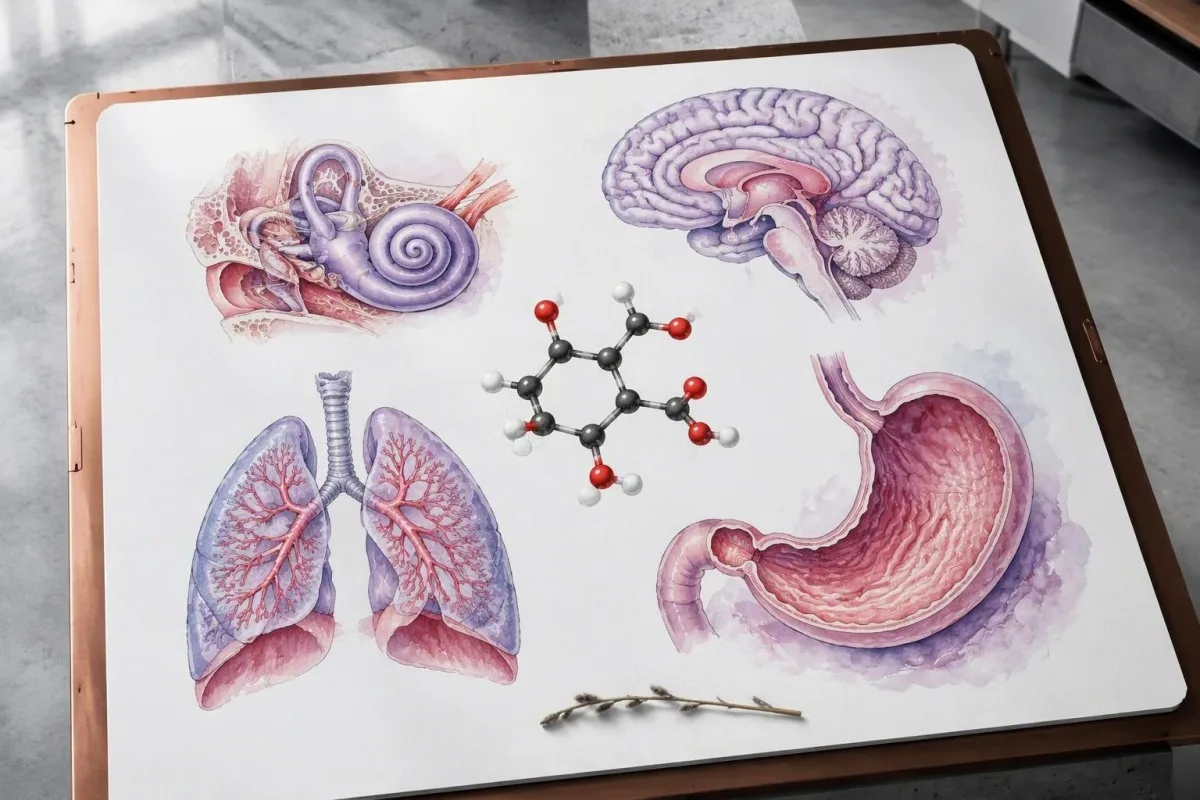
Tinnitus is a useful clue, but its absence does not exclude poisoning. A child, a person with hearing impairment or an adult becoming confused may not report ringing ears reliably; a salicylate level of 32 mg/dL therefore cannot be dismissed solely because tinnitus is absent.
Rapid breathing is partly a direct stimulation of the respiratory center and partly a response to metabolic disturbance. Do not assume it is anxiety, and do not use a paper bag to slow breathing; retaining carbon dioxide can lower blood pH and increase movement of salicylate into the brain.
Normal pulse oximetry does not rule out the metabolic effects of salicylates. Carbon monoxide exposure can also be missed by ordinary oxygen readings, but requires a different test; our carbon monoxide testing explanation helps distinguish two situations where a reassuring oxygen display can be incomplete.
A hypothetical patient with 38 mg/dL, new confusion and a respiratory rate of 32 breaths per minute needs urgent reassessment, not a label of mild poisoning. The combination suggests systemic and neurological involvement, whereas the concentration alone cannot identify tissue exposure or explain why consciousness has changed.
How blood pH and bicarbonate reveal salicylate toxicity
Salicylate toxicity classically causes respiratory alkalosis together with metabolic acidosis. A near-normal blood pH can hide these opposing abnormalities, so clinicians inspect bicarbonate, carbon dioxide pressure and the anion gap rather than reading pH as a standalone safety check.
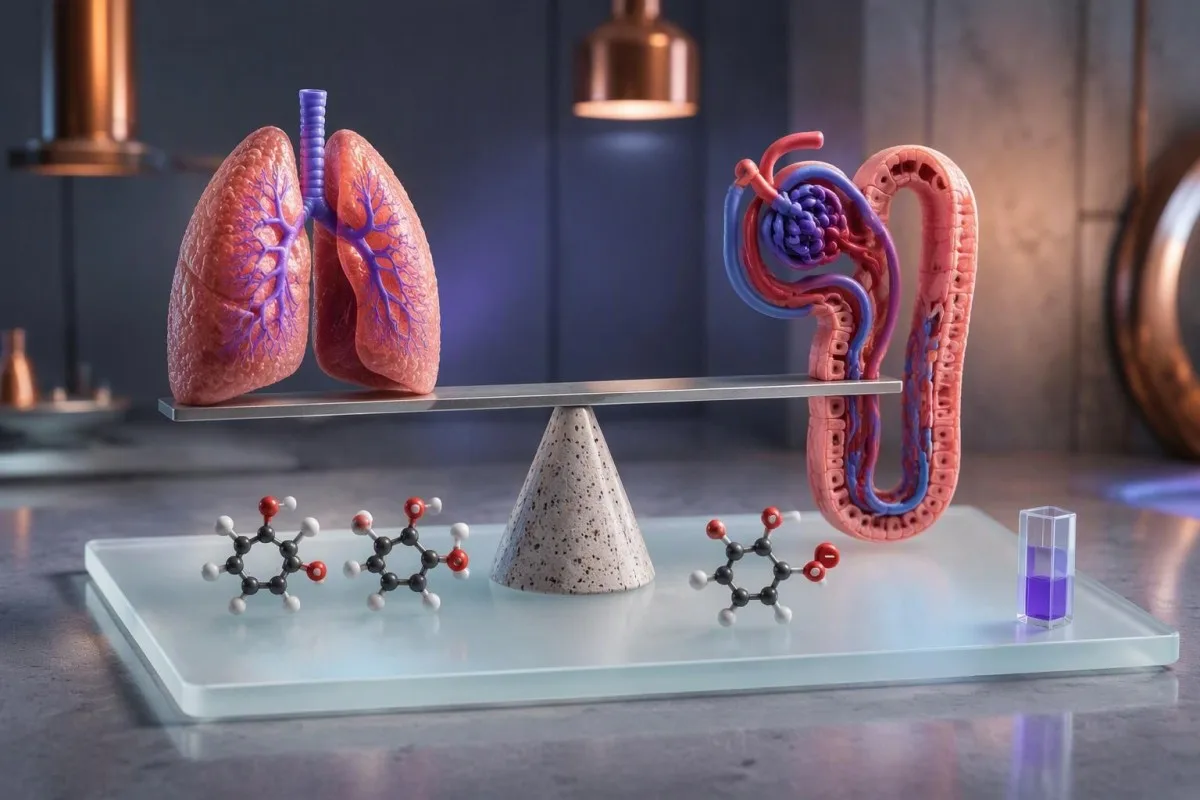
Respiratory alkalosis means carbon dioxide has fallen through increased ventilation; metabolic acidosis means bicarbonate is reduced by accumulating acids. Our arterial gas interpretation guide explains these components, but salicylate poisoning requires their interpretation alongside exposure history and serial drug measurements.
For a hypothetical arterial gas, bicarbonate of 16 mmol/L and PaCO2 of 22 mmHg yield a pH near 7.48. Winter's formula predicts a compensatory PaCO2 of approximately 32 ± 2 mmHg, so 22 mmHg indicates an additional respiratory alkalosis rather than compensation alone.
A pH near 7.40 can still be concerning when bicarbonate is 12 mmol/L and PaCO2 is 20 mmHg. These two major abnormalities nearly cancel numerically; the resulting pH does not mean the underlying metabolic disturbance is small or that treatment can wait.
Acidemia increases the proportion of uncharged salicylic acid, which enters tissues more readily. EXTRIP suggests dialysis for severe acidemia at pH 7.20 or below even without another indication; laboratory interference can also falsely elevate chloride, making a normal-looking anion gap unreliable in some assays (EXTRIP Workgroup, 2015).
What rising or falling serial salicylate levels mean
Rising serial salicylate levels suggest ongoing absorption or inadequate elimination; falling levels are reassuring only when symptoms and acid–base status also improve. Clinicians commonly repeat concentrations about every 2 hours initially, adjusting the interval for severity, formulation and treatment response.

Serial measurements should include the collection time, not just the time a result appeared online. A pair of concentrations reported together may have been collected 3 hours apart; clinicians also need to know whether bicarbonate, charcoal or dialysis began between those samples.
A declining serum concentration does not always mean salicylate is leaving the body safely. If blood pH falls, salicylate can move from the circulation into tissues; ACMT warns that clinical deterioration despite falling concentrations is an ominous pattern requiring reassessment (ACMT, 2015).
A hypothetical decline from 62 to 48 mg/dL over 2 hours is not reassuring if pH falls from 7.46 to 7.28 and confusion appears. For comparison, digoxin sampling and toxicity also require clinical context, but its distribution timing must not be substituted for aspirin rules.
Kantesti ni jukwaa la tafsiri ya vipimo vya damu la AI that can explain recorded trends, not a bedside monitor that confirms poisoning resolution. Two uploaded results omit the patient's current ventilation, fluid balance and neurological examination; discharge decisions require clinicians to establish that absorption has ended and clinical abnormalities have resolved.
Which other laboratory tests clinicians check
Clinicians usually check electrolytes, bicarbonate, kidney function, glucose and a blood gas alongside the salicylate level. Additional testing depends on the presentation, but these measurements identify impaired clearance, potassium depletion, acid–base changes and treatable metabolic problems that a salicylate concentration cannot show.
Potassium depletion can make urinary alkalinization difficult even when bicarbonate is being administered. A potassium result of 2.9 mmol/L therefore changes the treatment plan, not merely the list of abnormal flags; our maelezo ya jopo la elektroliti covers the broader patterns clinicians evaluate.
An anion gap is commonly calculated as sodium minus chloride minus bicarbonate. With sodium 140, chloride 104 and bicarbonate 16 mmol/L, the gap is 20 mmol/L; local reference intervals, albumin and possible chloride-assay interference determine how strongly that finding supports metabolic acidosis.
Kidney impairment reduces salicylate elimination and can limit the ability to give fluids safely. The mwongozo wa tafsiri wa BUN-kwa-kreatini explains hydration-related clues, but calculated eGFR is less dependable when creatinine is changing rapidly during an acute illness.
Glucose and lactate answer different questions: a normal serum glucose does not exclude inadequate glucose availability within the brain during salicylate toxicity. A lactate of 2.0 mmol/L also cannot rule out poisoning, and lactate collection limitations matter when a single result seems inconsistent with the clinical picture.
Which medicines and products can cause salicylate exposure
Salicylate exposure can come from aspirin, bismuth subsalicylate, combination pain products and methyl salicylate preparations. Clinicians ask about swallowed and topical products because the product strength, formulation, amount and route determine how an exposure should be assessed.

A tablet count is meaningless without tablet strength. An 81 mg aspirin tablet and a 325 mg tablet differ roughly fourfold in aspirin content; clinicians need the actual packaging rather than a description such as small tablets or regular painkillers.
Methyl salicylate is not interchangeable with ordinary aspirin tablets and can be highly concentrated in some liniments or oils. An uncertain swallowed amount needs immediate poison-service assessment; do not attempt to estimate safety by converting household teaspoons into aspirin equivalents.
Topical exposure also deserves attention when large areas are treated repeatedly, particularly under occlusive coverings or when the skin barrier is affected. A 2-day history of heavy application may matter more than a denial of aspirin tablet use, especially when unexplained rapid breathing or confusion develops.
Children need exposure-specific assessment, not adult cutoffs scaled casually by age. Our explanation of children's AI interpretation limits reinforces why an uncertain pediatric ingestion should go directly to a poison service or emergency team rather than an automated report review.
Why intravenous bicarbonate helps remove salicylate
Intravenous sodium bicarbonate helps keep salicylate outside sensitive tissues and increases its elimination in urine. Treatment is hospital-based because clinicians must monitor blood pH, urinary pH, potassium, sodium, kidney function and fluid balance while adjusting the infusion.
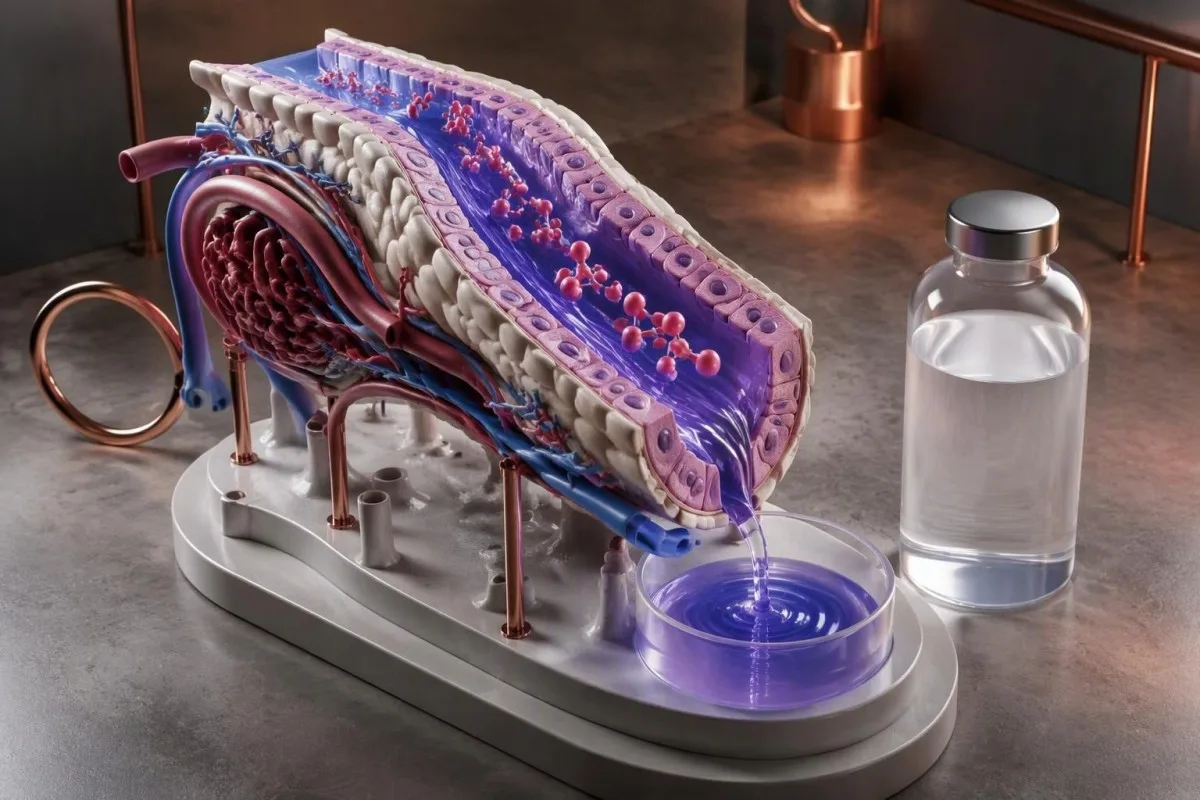
Urinary alkalinization works through ion trapping: salicylate becomes less able to move back across the renal tubule into circulation. ACMT describes a urine pH target of 7.5–8.0 and reports that effective alkalinization can increase urinary salicylate excretion more than tenfold (ACMT, 2015).
Blood and urine pH are separate treatment targets. Some hospital protocols aim for blood pH around 7.50–7.55, while adjusting for the patient's condition; a urine pH of 6.5 may show that bicarbonate treatment has not yet achieved the intended renal effect.
Low potassium encourages the kidneys to retain potassium at the expense of secreting hydrogen ions, keeping urine acidic. Clinicians therefore replace potassium when appropriate; urinary potassium interpretation explains renal handling, although urgent replacement decisions primarily use serum potassium and monitored clinical information.
A hypothetical patient with potassium 2.8 mmol/L and urine pH 6.2 may remain difficult to alkalinize despite bicarbonate administration. Heart failure, lung fluid accumulation or kidney impairment can also restrict treatment; escalating the infusion indefinitely is not a substitute for assessing whether dialysis is needed.
How charcoal, fluids and glucose fit into treatment
Treatment may include activated charcoal, carefully managed intravenous fluids and glucose support, depending on the exposure and clinical condition. These measures complement alkalinization or dialysis; charcoal reduces gastrointestinal absorption but does not remove salicylate that has already entered the circulation.

Activated charcoal is usually most useful early, but delayed absorption can create a later treatment opportunity after some aspirin exposures. A presentation beyond 1 hour does not automatically settle the question; clinicians weigh formulation, ongoing absorption, vomiting and the patient's ability to protect their airway.
Repeat-dose charcoal is not a universal requirement for salicylate poisoning. ACMT describes the evidence as mixed and advises weighing potential benefit against aspiration risk; a drowsy patient with 55 mg/dL cannot safely receive home charcoal simply because the concentration is elevated (ACMT, 2015).
Dextrose may be appropriate for neurological symptoms even when serum glucose looks normal, because central nervous system glucose availability can be inadequate. Ordinary sababu za glukosi ya chini provide useful background, but a result of 100 mg/dL does not exclude this particular salicylate-related concern.
Airway management needs specialist planning because suppressing compensatory hyperventilation can rapidly lower pH. A patient maintaining PaCO2 at 20 mmHg may deteriorate if ventilation falls after sedation; necessary intubation should preserve adequate ventilation and acid–base control rather than being delayed when the airway is failing.
When salicylate toxicity requires hemodialysis
Hemodialysis is indicated when salicylate poisoning is severe, standard treatment is failing or specific concentration thresholds are exceeded. Altered mental status, new hypoxemia requiring supplemental oxygen and failure of supportive treatment are EXTRIP indications regardless of the measured salicylate level.

The EXTRIP Workgroup recommends extracorporeal treatment above 100 mg/dL, or above 90 mg/dL when kidney function is impaired. Its 2015 systematic review in Annals of Emergency Medicine favors intermittent hemodialysis when available, because rapid removal is valuable in a deteriorating patient (EXTRIP Workgroup, 2015).
EXTRIP also suggests treatment above 90 mg/dL without kidney impairment, above 80 mg/dL with impairment, or for pH 7.20 or below when another indication is absent. These recommendation strengths differ because the evidence is largely observational; they are not permission to wait for a patient to cross a number.
Chronic toxicity requires an especially symptom-led approach. ACMT describes significant manifestations around 40 mg/dL as sufficient to consider dialysis; our guide to urgent kidney impairment signs explains associated red flags, but a poisoning decision cannot be reduced to eGFR alone.
A hypothetical older adult at 42 mg/dL with confusion and new oxygen needs may require dialysis sooner than a stable acute-exposure patient at a higher concentration. Preparation should begin early when deterioration is foreseeable, and alkalinization can continue while dialysis is arranged if the treating team considers it appropriate.
What safe recovery and follow-up actually require
Safe recovery requires clinical improvement, stable acid–base status and serial evidence that absorption has ended—not one salicylate level below a chosen cutoff. Kantesti ni Zana ya uchambuzi wa vipimo vya damu inayotumia AI for understanding completed reports; emergency clearance and discharge remain decisions for the treating clinical team.

A discharge result of 18 mg/dL means something different after clearly declining measurements and resolved symptoms than it does after a solitary early sample. Hospitals also consider rebound after dialysis, delayed formulations, kidney recovery and whether bicarbonate treatment has been stopped without renewed clinical or biochemical deterioration.
After discharge, record the hospital's medication instructions rather than restarting every previous product automatically. Our mwongozo wa mwelekeo wa usalama wa dawa explains how to organize follow-up results, but prescribed low-dose aspirin should be resumed, withheld or changed according to the treating clinician's plan.
Kantesti AI's explanations should be checked against the original report, its units and collection timestamps. Our kanuni za AI inayowajibika describe the boundary between information support and clinical decisions; two historical values cannot show whether new tinnitus, vomiting or confusion has developed today.
A useful follow-up record preserves at least 3 details for each result: concentration, collection time and treatment underway. Our maelezo ya teknolojia ya AI describes report interpretation workflows, but renewed symptoms after discharge require medical reassessment rather than another upload.
Research behind salicylate interpretation and treatment
Salicylate treatment recommendations rely heavily on toxicology guidance, pharmacology and observational evidence rather than large randomized trials. The 2015 ACMT guidance and EXTRIP recommendations agree that symptoms, acid–base status and exposure pattern must accompany concentration-based decisions.

Salicylates uncouple oxidative phosphorylation, increasing energy demand and contributing to heat production and metabolic disturbance. This mechanism helps explain why 1 serum concentration cannot summarize organ effects; it does not provide a separate laboratory test that can replace serial salicylate measurements or clinical observation.
Thresholds such as 100 mg/dL are escalation recommendations, not experimentally proven boundaries between safe and unsafe patients. Our mfumo wa uthibitishaji wa matibabu provides context for how interpretation quality should be assessed; clinical guideline evidence must remain separate from technical testing of an AI system.
Kantesti LTD is the organization behind this educational article, as described in our historia ya kampuni. The 2 Zenodo publications listed below cover RDW and BUN/creatinine interpretation; neither is a salicylate poisoning trial, and neither establishes aspirin treatment thresholds.
The kidney-function publication offers background for understanding renal clearance, while the RDW publication concerns red-cell indices rather than aspirin toxicity. Our viwango vya maudhui ya matibabu explain why these 2 educational resources are distinguished from the directly relevant ACMT and EXTRIP medical references.
Maswali ya mara kwa mara
Kiwango gani cha kawaida au cha matibabu cha salisailati?
Kiwango cha matibabu cha salisilati kwa kawaida huwa takriban 10–30 mg/dL, kutegemea matumizi yaliyokusudiwa na maabara, lakini hiki si kiwango cha kawaida kinachohitajika na mwili. Kwa kawaida, watu ambao hawajatumia salisilati huwa na viwango visivyogundulika au vya chini sana. Aspirini ya dozi ndogo inayotumiwa kuzuia mkusanyiko wa chembe sahani haihitaji kufikia kiwango cha kihistoria cha kupunguza maumivu au kuzuia uvimbe. Dalili, pH ya damu, utendaji wa figo na muda tangu kufichuliwa vinaweza kufanya kiwango kilicho ndani ya au karibu na kiwango hicho kitoe sababu ya wasiwasi wa kiafya.
Je, kiwango cha chini cha salisilati katika hatua za awali kinaweza kuondoa uwezekano wa dozi ya kupita kiasi ya aspirini?
Kiwango cha chini cha salisileti kilichopimwa mapema hakiwezi kuondoa uwezekano wa kuzidisha dozi ya aspirini kwa sababu ufyonzwaji unaweza kuwa bado haujakamilika. Vidonge vyenye mipako inayostahimili asidi ya tumbo, kuchelewa kwa utoaji wa yaliyomo tumboni na kumeza kiasi kikubwa vinaweza kuchelewesha kufikia kilele cha kiwango, wakati mwingine zaidi ya saa 12–24. Wahudumu wa afya huchukua sampuli ya awali mara moja na kufanya vipimo vya kurudia hadi ufyonzwaji unaoendelea utakapoondolewa kama uwezekano. Ikiwa sumu inashukiwa, tathmini ya haraka inahitajika badala ya kusubiri nyumbani kupata matokeo ya baadaye.
Madaktari hurudia kupima viwango vya salisilat mara ngapi?
0 Madaktari kwa kawaida hurudia kupima viwango vya salisilati takriban kila baada ya saa 2 mwanzoni kunaposhukiwa kuwa na sumu, lakini muda kati ya vipimo hutegemea ukali, aina ya dawa na matibabu. Vipimo vinavyorudiwa hutafsiriwa pamoja na dalili, gesi za damu, elektroliti na utendaji wa figo. Kupungua kwa kiwango hicho hakutoshi kutoa uhakikisho iwapo pH ya damu inapungua au kuchanganyikiwa kunatokea. Ufuatiliaji huendelea hadi timu inayotoa matibabu itakapothibitisha kuwa ufyonzwaji umekoma na hali zisizo za kawaida za kliniki zinapungua.
Ni kiwango gani cha salisilati kinachohitaji dialysis?
EXTRIP inapendekeza dialysis au matibabu mengine yanayofaa ya nje ya mwili wakati kiwango cha salicylate kinapozidi 100 mg/dL, au 90 mg/dL iwapo utendaji kazi wa figo umeharibika. Mabadiliko ya hali ya fahamu, hypoxemia mpya inayohitaji oksijeni ya ziada au kushindwa kwa matibabu ya kawaida kunaweza kuhalalisha dialysis hata katika viwango vya chini ya hivi. EXTRIP pia inapendekeza dialysis kwa acidemia kali yenye pH ya 7.20 au chini. Sumu sugu yenye kiwango cha takriban 40 mg/dL inaweza kuhitaji kuzingatiwa kwa dialysis ikiwa dalili za neva au mapafu zipo.
Kwa nini sumu ya aspirini ya muda mrefu inaweza kutokea katika kiwango cha chini zaidi?
Sumu ya aspirini ya muda mrefu inaweza kuwa kali hata viwango vya chini vya seramu kwa sababu kuathiriwa mara kwa mara huruhusu salisili kujikusanya kwenye tishu. Upungufu wa maji mwilini, ugonjwa na kuharibika kwa utendaji wa figo vinaweza kupunguza uondoaji wake, hasa kwa watu wazima wenye umri mkubwa. Kwa hiyo, kiwango cha 40 mg/dL kinachoambatana na kuchanganyikiwa au kuathirika kwa mapafu si sawa na matokeo kama hayo kwa mtu aliye katika hali thabiti na aliyeathiriwa hivi karibuni kwa mara ya kwanza. Madaktari hutathmini historia ya matumizi ya dawa katika siku zilizotangulia, wala si dozi ya hivi karibuni tu.
Je, pH ya damu inaweza kuwa ya kawaida wakati wa sumu ya salisailati?
pH ya damu inaweza kuwa karibu na kiwango cha kawaida wakati wa sumu ya salisileti kwa sababu alkalosisi ya upumuaji na asidosisi ya kimetaboliki zinaweza kusawazishana kihesabu. Kwa mfano, bikabonati ya 12 mmol/L pamoja na PaCO2 ya 20 mmHg inaweza kutoa pH iliyo karibu na 7.40 licha ya hitilafu kubwa. Kwa hiyo, wahudumu wa afya huchunguza bikabonati, shinikizo la dioksidi kaboni na pengo la anioni badala ya kutegemea pH pekee. Matokeo ya gesi yanayoonekana kuwa ya kawaida hayaondoi hitaji la vipimo vya mara kwa mara vya salisileti na tathmini ya kliniki.
Nifanye nini nikishuku sumu ya aspirini?
Tafuta tathmini ya haraka kutoka kwa huduma ya sumu au idara ya dharura ikiwa unashuku sumu ya aspirini, hata kama kipimo cha kwanza cha salisilati kiko chini. Piga 999 au 112 nchini Uingereza, au 911 nchini Marekani, ikiwa kuna kuchanganyikiwa, degedege, kuzimia au shida kubwa ya kupumua. Nchini Marekani, Poison Control inapatikana kwa nambari 1-800-222-1222 kwa ushauri wa haraka kuhusu kuathiriwa na sumu. Usijaribu kusababisha kutapika wala kutoa mkaa ulioamilishwa au baking soda ya nyumbani; leta kifungashio cha bidhaa na taarifa za muda ulioathiriwa zinazopatikana.
Pata maelezo ya jinsi ya kusoma matokeo ya vipimo vya damu
Pakia ripoti yako ya maabara na AI ya Kantesti itaeleza kila kiashiria cha kibayolojia kwa lugha rahisi ndani ya sekunde chache. Inatumiwa na zaidi ya watu milioni 2 duniani kote.
Marejeleo
- Klein, T., Mitchell, S., & Weber, H. (2026). Kipimo cha RDW katika Damu: Mwongozo Kamili wa RDW-CV, MCV na MCHC. Utafiti wa Kimatibabu wa AI ya Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Ufafanuzi wa Mbadala wa BUN/Creatinine: Mwongozo wa Kipimo cha Utendaji wa Kifua. Utafiti wa Kimatibabu wa AI ya Kantesti. DOI
- American College of Medical Toxicology (2015). Guidance Document: Management Priorities in Salicylate Toxicity. Journal of Medical Toxicology. DOI
- Juurlink DN et al. (2015). Extracorporeal Treatment for Salicylate Poisoning: Systematic Review and Recommendations From the EXTRIP Workgroup. Annals of Emergency Medicine. DOI
- 2M+Vipimo vilivyochanganuliwa
- 127+Nchi
- 100+Lugha
Kuhusu timu ya matibabu


E-E-A-T Trust Signals
Uzoefu
Mapitio ya kimatibabu inayoongozwa na daktari ya mifumo ya tafsiri ya maabara.
Utaalamu
Kuzingatia dawa za maabara kuhusu jinsi viashiria (biomarkers) vinavyobadilika katika muktadha wa kliniki.
Mamlaka
Imekaguliwa kimatibabu na Dkt. Thomas Klein, kwa michango kutoka kwa Dkt. Sarah Mitchell na Prof. Dkt. Hans Weber.
Uaminifu
Tafsiri inayotegemea ushahidi yenye njia zilizo wazi za ufuatiliaji ili kupunguza tahadhari za hofu.





Kanusho la kimatibabu
Makala haya ni kwa madhumuni ya elimu tu na si ushauri wa kimatibabu. Wasiliana na mtoa huduma aliyehitimu kila wakati kwa maamuzi ya utambuzi na matibabu.
Imechapishwa · Wasiliana na timu ya uhariri
Imechapishwa na Kantesti Ltd, imesajiliwa nchini Uingereza na Wales, nambari ya kampuni. 17090423, London, Uingereza.
