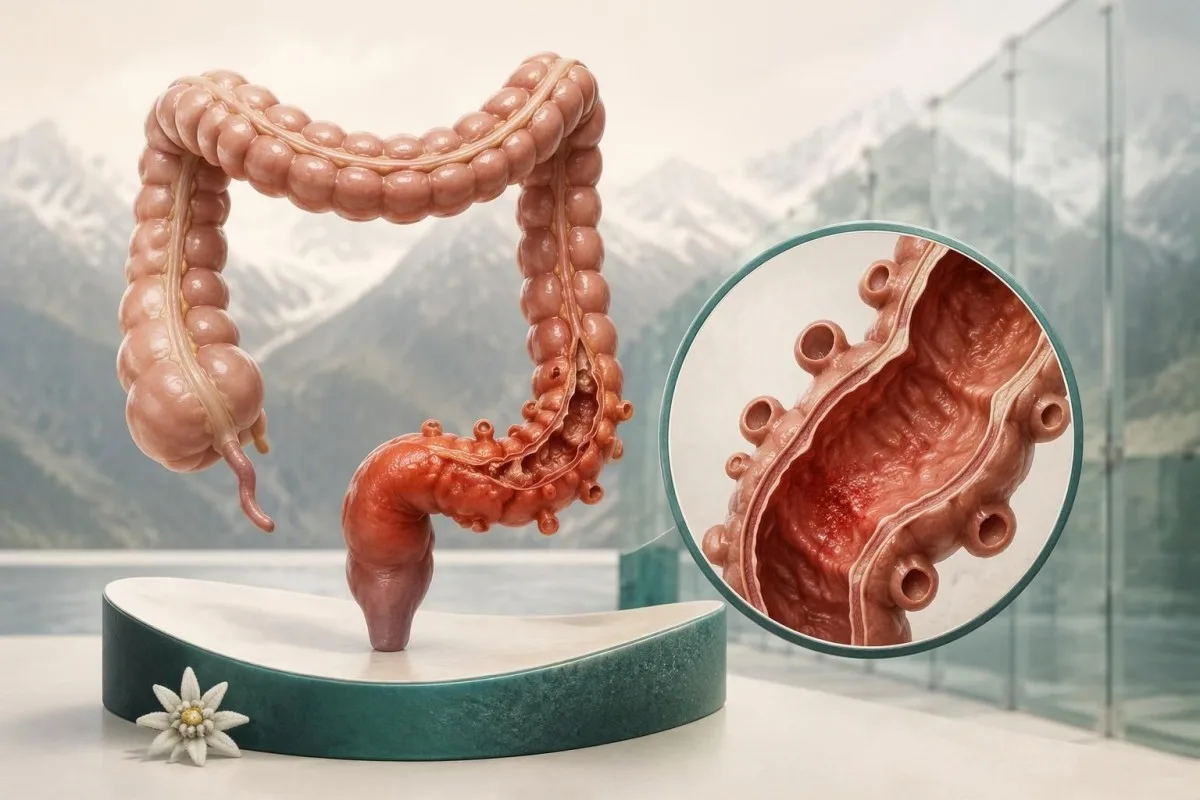
Persistent lower-left abdominal pain with fever or bowel changes needs same-day clinical advice. Seek emergency care for severe or spreading pain, repeated vomiting, fainting or confusion; diverticulitis can occur without fever, and neither symptoms nor blood tests can confirm it.

مهم ټکي
- Persistent lower-left pain with tenderness, fever or new bowel changes warrants same-day assessment; do not wait for all 3 features to appear.
- د بیړني حالت نښې include severe or spreading pain, confusion, fainting, or abdominal swelling with vomiting and inability to pass gas.
- تبه commonly means a temperature of 38°C or above, but a lower temperature does not exclude diverticulitis or its complications.
- د وینې معاینات measure inflammation and illness severity, not the cause; normal WBC and CRP results cannot reliably exclude early diverticulitis.
- CT imaging has approximately 95% sensitivity and specificity for diverticulitis and can identify an abscess, perforation or an alternative diagnosis.
- Higher-risk results such as CRP above 140 mg/L or WBC above 15 × 10⁹/L influence treatment decisions; these are not diagnostic cutoffs.
- انټيبیوټیکونه are not automatic for every episode: selected immunocompetent adults with mild, uncomplicated diverticulitis may recover without them under clinical supervision.
- Follow-up colonoscopy is often delayed for 6–8 weeks after an acute episode, with the need determined by the episode, previous examination and alarm symptoms.
Which diverticulitis symptoms need same-day assessment?
New, persistent lower-left abdominal pain, especially with tenderness, fever or altered bowel habits, needs same-day clinical assessment. Emergency care is appropriate when pain becomes severe or widespread, or when confusion, fainting, repeated vomiting or inability to pass gas suggests a complication—even if the temperature remains below 38°C.

Diverticulitis is inflammation involving a diverticulum, a small pouch projecting through the bowel wall; simply having pouches is called diverticulosis and does not establish the cause of pain. One previous scan showing diverticulosis therefore cannot prove that a new episode of abdominal discomfort is diverticulitis.
Clinical suspicion alone correctly identifies diverticulitis in only about 40–65% of suspected cases, according to the AGA expert review (Peery et al., 2021). The overlap matters: constipation, urinary disease, colitis and pelvic conditions can produce similar pain, while a complication may initially resemble an uncomplicated episode.
For example, a hypothetical 56-year-old with 18 hours of steadily increasing lower-left pain, reduced appetite and constipation needs assessment despite a temperature of 37.4°C. Being able to walk or having a normal-looking laboratory report does not establish safety; the trajectory and examination still matter.
Kantesti د AI وینې ازموینې شنونکی دی that explains laboratory findings without treating a normal CRP result as proof against diverticulitis. Kantesti LTD's سازماني معلومات identifies who provides our educational service; decisions about a first episode of persistent abdominal pain require a clinician, not an automated interpretation.
What are the early signs of diverticulitis?
Early signs of diverticulitis can include a localized abdominal ache that becomes persistent, new tenderness, reduced appetite and constipation or diarrhea. There is no reliable hour-by-hour sequence: symptoms may develop over 1–2 days or appear more abruptly, and fever may emerge later or never occur.
Increasing persistence is more concerning than a brief isolated twinge, although pain behavior cannot diagnose diverticulitis. A useful comparison is your own baseline over the preceding 24 hours: discomfort that no longer settles between cramps, or begins limiting drinking and movement, deserves reassessment rather than another day of observation.
New bowel changes help describe an episode but are not specific enough to identify its cause. Recording whether stool changed from Bristol type 4 to type 1 or type 6 is more useful than writing only 'abnormal'; our د غایطه موادو د قوام لارښود explains those descriptions without assigning a diagnosis.
A hypothetical 44-year-old might initially describe 6 hours of bloating, then develop a fixed lower-left ache and nausea overnight. That sequence is compatible with diverticulitis, but it is also compatible with other abdominal illnesses; improvement after passing stool does not reliably settle the distinction.
There is no validated home symptom score that can confirm an early episode from 2 or 3 symptoms. Before contacting a clinician, note the starting time, whether pain is spreading, your measured temperature and whether you can keep fluids down; these details often change the urgency more than the word 'cramp'.
Where is diverticulitis pain usually located?
Diverticulitis pain location is usually the lower-left abdomen, because the sigmoid colon is commonly affected in Western populations. Right-sided or central pain is possible, however, and the location of 1 painful area cannot reliably distinguish diverticulitis from appendicitis, a urinary problem or another acute abdominal condition.
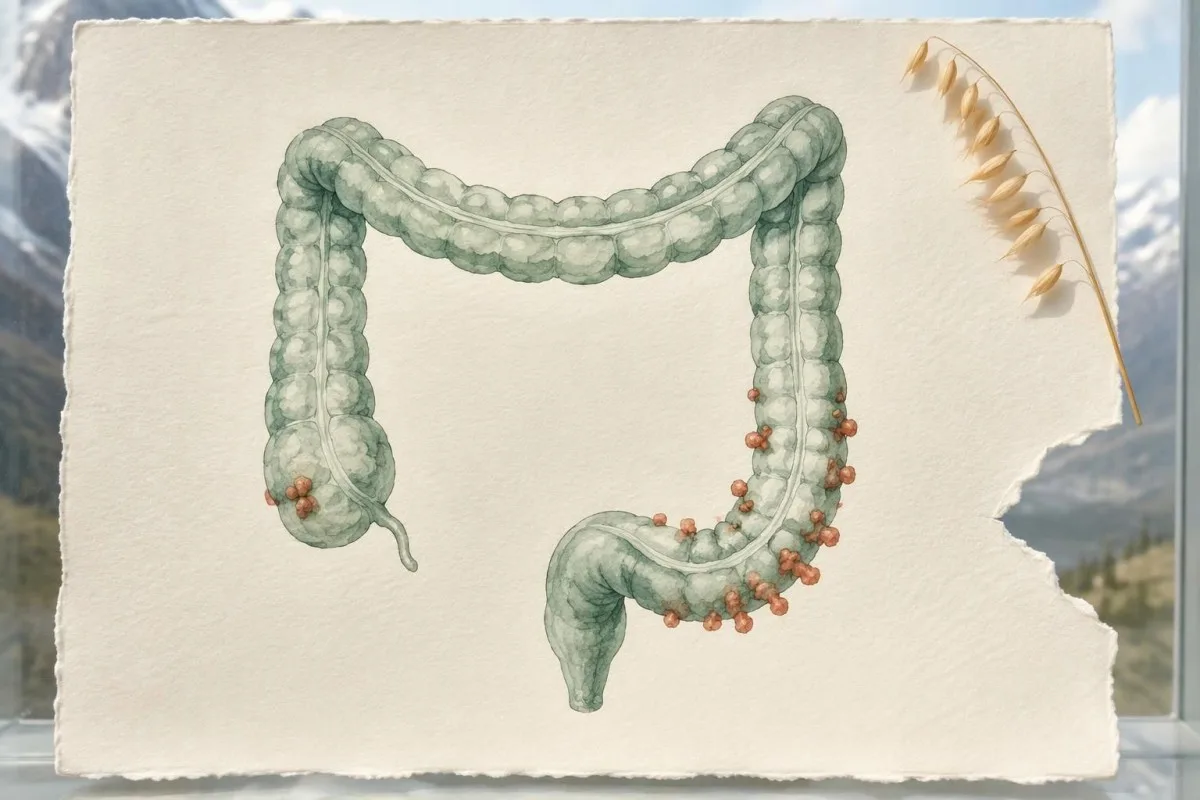
The sigmoid colon has a variable position, so pain may be felt above the pubic area rather than neatly in the left lower quadrant. A pelvic sigmoid segment can also irritate nearby structures; 2 symptoms such as suprapubic discomfort and urinary frequency therefore do not automatically identify a bladder infection.
Right-sided diverticulitis occurs more often in Asian populations than in Western populations, although individual anatomy matters more than nationality. Right-lower abdominal pain still requires assessment for appendicitis; our guide to په اپینډیسایټس کې نورمال ازموینې explains why 1 reassuring CBC cannot safely decide between these possibilities.
Pain that spreads from 1 localized area across the abdomen raises concern for a wider process, especially when accompanied by marked tenderness or systemic illness. Clinicians assess guarding and peritoneal irritation themselves; repeatedly pressing hard on the abdomen at home adds discomfort without providing a dependable diagnostic test.
For a hypothetical 63-year-old, pain just left of the midline and a temperature of 38.2°C might suggest sigmoid diverticulitis, but a scan could reveal a different cause. Point with 1 finger to where the pain began, then describe where it is now; the change in distribution is clinically useful.
Can diverticulitis symptoms occur without fever?
Diverticulitis symptoms without fever are possible, particularly early in an episode, in older adults or in people taking medicines that alter the immune response. A temperature below 38°C does not exclude diverticulitis, and an absent fever must not override worsening pain, inability to drink or other warning signs.

A single temperature reading is a snapshot, not a complete assessment of illness. A hypothetical reading of 36.9°C after paracetamol can coexist with clinically significant abdominal disease; tell the clinician when fever-reducing medicine was taken rather than presenting the number as an untreated baseline.
Older adults may have a less prominent fever response, while corticosteroids can reduce inflammatory symptoms and also change the white-cell count. In a person aged 75 taking prednisolone, 2 reassuring features—no fever and only modest tenderness—should not cancel concern about progressive symptoms; our په زړو خلکو کې د درملو اغیزې guide explains related laboratory pitfalls.
Immunosuppression lowers the threshold for imaging and treatment because symptoms can underestimate the severity of diverticulitis. The AGA review recommends a low threshold for CT in these patients (Peery et al., 2021); a transplant recipient with 1 day of new focal abdominal pain should seek prompt advice rather than wait for a temperature rise.
Feeling generally unwell without fever still matters, especially if accompanied by weakness, reduced urine output or a faster heartbeat. If a home thermometer gives an unexpected result, repeat it using the device instructions—but do not spend another 2 hours checking temperatures while severe pain or confusion is developing.
Which bowel changes support—or challenge—the diagnosis?
Constipation and diarrhea can both accompany diverticulitis, and neither bowel pattern confirms the diagnosis. New mucus, urgency or urinary irritation may occur, but frequent watery stools, recent antibiotics or a shared food exposure should prompt clinicians to consider competing explanations, even when pain has lasted only 1 day.

A change from your baseline is more useful than stool frequency alone: 2 bowel movements daily may be normal for one person and a major change for another. Passing a stool does not rule out diverticulitis; conversely, constipation with localized pain should not automatically be treated with a laxative before an acute abdominal problem is assessed.
Diarrhea with fever and food exposure can indicate intestinal infection, not necessarily diverticulitis. For example, a hypothetical household in which 3 people develop diarrhea after the same meal creates a different diagnostic picture; our explanation of Campylobacter stool PCR describes when organism-specific testing may clarify the cause.
Recent antibiotic use changes the workup when there are په 24 ساعتونو کې 3 یا زیات بېشکله غایطه مواد, a commonly used threshold for considering C. difficile testing in the right context. Our guide to د C. difficile متضادو پایلو explains why even a positive screening component must be interpreted alongside symptoms.
Urinary frequency or discomfort can reflect irritation near the sigmoid colon, but recurrent urinary infections, gas during urination or stool-like material in urine raise concern for a bowel–bladder connection. These are not routine early symptoms; report even 1 such episode promptly, because imaging may be needed to investigate a fistula.
Which warning signs suggest an abscess, perforation or sepsis?
Severe or spreading abdominal pain, a rigid or markedly swollen abdomen, repeated vomiting, confusion, fainting or reduced urine output require urgent assessment. Swelling with vomiting and inability to pass stool or gas can indicate obstruction; no fever cutoff, including 38°C, is required before seeking emergency care.
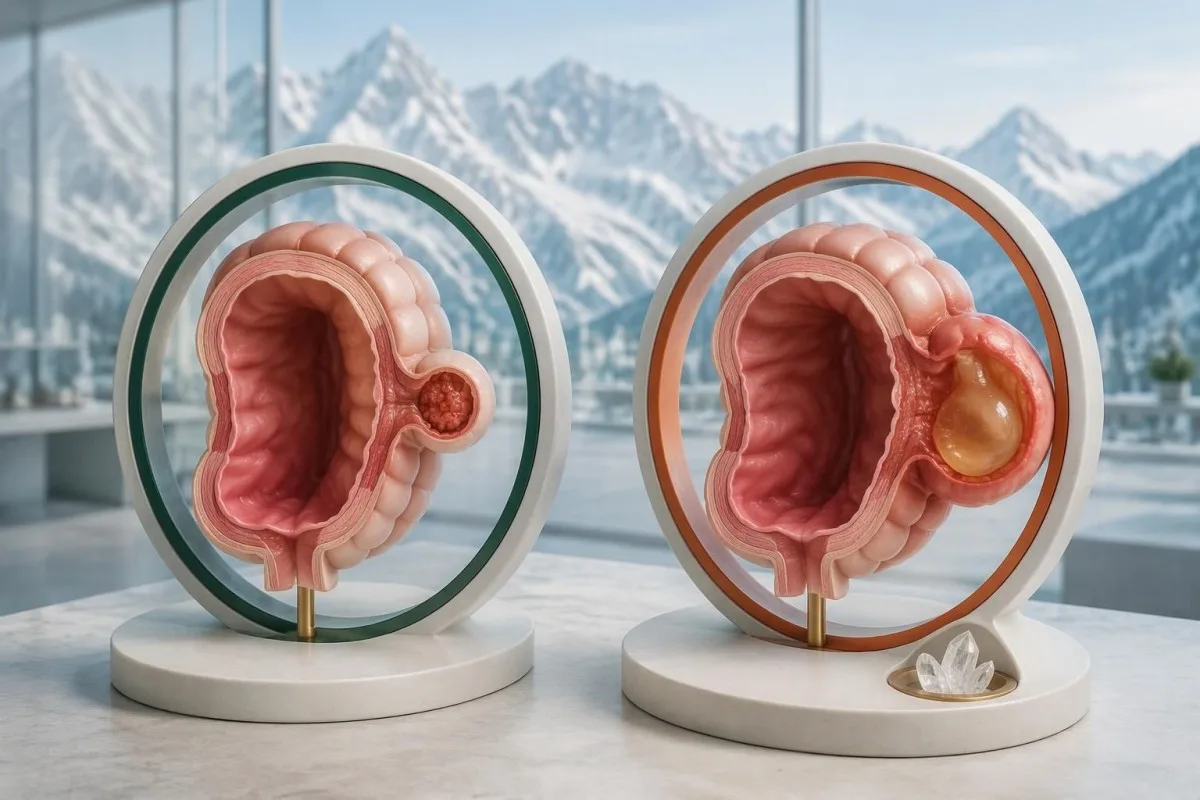
An abscess is a contained collection associated with the affected bowel, while perforation allows material to escape through the bowel wall. Neither can be reliably distinguished by pain intensity or 1 laboratory value; NICE recommends same-day hospital assessment when suspected diverticulitis is accompanied by features suggesting a complication (NICE NG147, 2019).
Sepsis can involve altered mental state, fast breathing, circulatory instability or unexpectedly low urine output, sometimes without a high temperature. Even a procalcitonin below 0.5 ng/mL cannot safely exclude a localized abdominal complication; our د پروکلسیټونین د پایلو د تفسیر لارښود explains why a biomarker must not replace assessment of the person.
Large-volume rectal bleeding is not a typical defining feature of diverticulitis, and diverticular bleeding is often painless. Passing blood with dizziness, fainting or weakness requires urgent care for possible significant blood loss, regardless of whether pain is present; our blood in stool guide separates color clues from emergency symptoms.
CT findings—not a home pain score—help determine how a complication is treated. NICE advises considering drainage or surgery for diverticular abscesses larger than 3 cm when feasible, while smaller collections may be managed differently; do not interpret that size threshold as permission to wait at home with suspected complications.
When do clinicians recommend CT imaging?
CT is often recommended when diverticulitis has not previously been confirmed, the diagnosis is uncertain, symptoms are severe, complications are suspected or recovery is not progressing. Abdominal and pelvic CT has approximately د 95% حساسیت او ځانګړتیا for diverticulitis, but a scan is not automatically necessary for every familiar, mild recurrence.
The AGA expert review emphasizes CT for patients without a prior imaging-confirmed diagnosis and for severe presentations or failure to improve (Peery et al., 2021). The ACP guideline recommends CT when there is diagnostic uncertainty (Qaseem et al., 2022); these approaches overlap but do not mean every person with 1 mild episode receives the same imaging pathway.
Suspected complicated diverticulitis is a hospital assessment problem, not an outpatient waiting-list problem. NICE recommends contrast CT within 24 hours of admission when inflammatory markers are raised and a complication is suspected; this timing follows admission and must not be misread as advice to remain at home for another day.
Intravenous contrast can improve evaluation of the bowel and surrounding tissues, while oral contrast use varies by local protocol. Kidney function and acute dehydration inform the risk–benefit discussion; an eGFR below ۳۰ ملي ليتر/دقيقه/۱.۷۳ متر مربع usually prompts additional consideration rather than an automatic ban, as our kidney tests after dehydration guide explains.
Possible pregnancy changes imaging planning because ultrasound or MRI may be preferred where clinically suitable, although necessary emergency imaging should not be withheld reflexively. A negative urine pregnancy test taken 2 days before an expected period may be too early to settle pregnancy status; our د امیندوارۍ دمخه ازموینې محدودیتونه guide explains that uncertainty.
What can WBC and CRP results actually tell you?
WBC and CRP can support an assessment of inflammation, but neither confirms diverticulitis or reliably excludes it when normal. Many adult laboratories use a WBC interval around 4-11 × 10⁹/L and a CRP upper limit of 5 mg/L; other laboratories use different intervals, including CRP below 10 mg/L.
CRP reflects an inflammatory response rather than a bowel-specific disease, and its rise can lag behind symptoms. A hypothetical CRP of 4 mg/L shortly after pain begins cannot settle the diagnosis; our د WBC او CRP پرتله explains why early timing, medication and the clinical examination can outweigh apparent disagreement between results.
The AGA review identifies CRP above 140 mg/L یا WBC above 15 × 10⁹/L as features supporting antibiotics in patients with otherwise uncomplicated diverticulitis (Peery et al., 2021). These values identify increased concern within a clinical diagnosis; they are not thresholds at which diverticulitis suddenly becomes confirmed or a complication becomes certain.
Kantesti د AI د وینې ازموینې تشریح پلیټ فارم دی that can explain an uploaded CRP of 86 mg/L alongside the laboratory's own interval and other available results. Our interpretation can clarify that the result is elevated, but it cannot determine whether the source is diverticulitis, another infection or noninfectious inflammation without clinical assessment.
Creatinine, electrolytes and hemoglobin answer different questions: dehydration, organ function and possible anemia, rather than confirmation of diverticulitis. A hypothetical creatinine rise from 80 to 125 µmol/L during vomiting needs attention to hydration and kidney function; our BUN او کریټینین لارښود explains why trends are more informative than one ratio.
| کچه | حد | مانا یې څه ده |
|---|---|---|
| Typical adult WBC interval | Approximately 4–11 × 10⁹/L | Laboratory-dependent; a result within range does not rule out diverticulitis. |
| Common CRP reference limit | Below 5 mg/L; some labs use below 10 mg/L | A normal result may be reassuring in context but can miss an early inflammatory response. |
| لوړ شوی CRP | Above the laboratory's upper limit | Indicates inflammation without identifying the cause or locating it. |
| AGA higher-risk treatment features | CRP >140 mg/L or WBC >15 × 10⁹/L | Supports antibiotic treatment in clinically assessed uncomplicated diverticulitis; not a diagnostic rule. |
What else can cause persistent lower-left abdominal pain?
Persistent lower-left pain can come from constipation, colitis, urinary stones, urinary infection, pelvic conditions or bowel cancer—not only diverticulitis. Sudden severe pain, pain with rectal bleeding or pain during possible pregnancy changes the urgency and the diagnostic pathway, even when only 1 symptom initially seems prominent.
Abrupt one-sided pelvic pain with nausea may indicate a time-sensitive pelvic emergency, and blood inflammation markers cannot reliably exclude it. A hypothetical 29-year-old with sudden pain lasting 2 hours needs a different assessment from someone with gradual constipation; our urgent ovarian cyst symptoms guide describes rupture and torsion warning patterns.
A possible ectopic pregnancy requires prompt assessment when lower abdominal pain occurs with a missed period, vaginal bleeding, shoulder-tip pain or faintness. Having 1 early negative home test does not eliminate the possibility; clinicians may use a pregnancy test, serial hCG measurements and ultrasound according to symptoms and timing.
Urinary stones can cause pain radiating toward the groin, while urinary infection can produce frequency, burning and fever. Urine white cells or microscopic blood do not independently identify the cause of abdominal pain; our د ادرار د رسوب د تفسیر لارښود explains why 2 abnormal urine findings can still require imaging or repeat sampling.
Sudden abdominal pain followed by rectal bleeding can indicate ischemic colitis, particularly when circulation is compromised, while persistent bowel changes and weight loss raise different concerns. A hypothetical 68-year-old with new pain and blood in stool should not assume a familiar diverticulitis recurrence merely because a scan 3 years earlier showed diverticulosis.
Does uncomplicated diverticulitis always need antibiotics?
Antibiotics are not required for every episode of mild, uncomplicated diverticulitis, but withholding them is a clinician-led decision for selected patients. The AGA review estimates progression to complicated disease at about 5% among patients with uncomplicated diverticulitis; immunosuppression, systemic illness, vomiting and higher inflammatory markers alter management.

NICE allows a no-antibiotic strategy for people who are systemically well, while recommending antibiotics when patients are systemically unwell, immunosuppressed or have significant comorbidity (NICE NG147, 2019). AGA guidance similarly supports selective use but highlights CRP above 140 mg/L, WBC above 15 × 10⁹/L, frailty and refractory symptoms as reasons for treatment.
Outpatient care requires more than a reassuring scan: pain must be manageable, oral fluids tolerated and follow-up accessible. A hypothetical 58-year-old with uncomplicated CT findings who vomits after every drink over 6 hours may still need hospital care; imaging classification does not erase dehydration or practical barriers to recovery.
Antibiotic selection depends on allergies, kidney function, local resistance and interactions, not just the word 'diverticulitis' on a report. Someone reporting a rash after penicillin 20 years earlier should describe the reaction accurately; our د پنسلین حساسیت د بیا ارزونې لارښود explains supervised reassessment, but acute illness is not a reason to test an allergy yourself.
Pain relief also needs context: paracetamol is commonly considered, while NICE advises avoiding NSAIDs and opioids where possible because of associated risks. If symptoms are not improving over 48–72 ساعتونو, contact the treating clinician sooner than a routine appointment; worsening pain, new vomiting or confusion requires immediate reassessment rather than waiting for that interval.
What should you eat and drink during a suspected episode?
Food and fluid advice depends on symptom severity and the clinician's assessment, not a universal fasting rule. A short clear-liquid phase may improve comfort during confirmed uncomplicated diverticulitis, but inability to tolerate fluids is a warning sign; the AGA advises reassessment if diet cannot advance after 3–5 ورځې.

A liquid diet does not diagnose or cure diverticulitis, and prolonged restriction can reduce energy and protein intake. For a hypothetical person who has eaten little for 3 days, ongoing pain and difficulty advancing food are reasons to contact the clinical team, not evidence that stricter fasting is needed.
Small, frequent drinks may be easier to tolerate than a large glass, but there is no single fluid target suitable for everyone. A person with a prescribed 1.5-liter daily fluid restriction for heart or kidney disease needs individualized advice; vomiting, diarrhea and reduced urine output can require assessment rather than an automatic instruction to drink more.
Temporary diarrhea during recovery should be interpreted alongside pain, fever and medication exposure rather than attributed to food alone. Our د هاضمي نښو لارښود discusses stool changes after restricted eating; 3 watery stools daily after antibiotics call for a different discussion from one softer stool as meals restart.
Routine avoidance of nuts, seeds and popcorn is not supported as a prevention strategy, according to the AGA review (Peery et al., 2021). After recovery, a high-quality dietary pattern and gradual return toward a usual fiber intake—often around 25–30 g/day for adults—can be discussed, but suddenly adding a large fiber supplement during acute pain is not a substitute for assessment.
How should symptoms be monitored after an assessment?
Monitor pain direction, drinking tolerance, temperature, bowel function and urine output after the clinician establishes a care plan. A routine check-in over 48–72 ساعتونو may be appropriate, but deterioration at any point overrides that schedule; a falling CRP does not make worsening abdominal symptoms safe to ignore.

A useful home record needs only a few consistent observations, not hourly measurements of everything. For example, note pain location, measured temperature and fluid tolerance 2–3 times daily while awake, or as advised; repeated measurements without a clear action plan can increase anxiety while failing to address new warning signs.
Clinical improvement and biomarker improvement can occur at different speeds, and repeated blood testing is not mandatory when recovery is straightforward. A hypothetical CRP fall from 110 to 58 mg/L over 2 days is encouraging only if pain and general condition also improve; our د روغتون وروسته لابراتوار بدلونونو guide explains why trends need clinical context.
Pain that remains severe or increasingly localized, new vomiting or inability to advance intake should trigger a fresh examination and possibly CT. Having started antibiotics 24 hours earlier does not protect against every complication; persistent symptoms may reflect an abscess, an alternative diagnosis or a treatment problem rather than simply slow recovery.
Kantesti can help explain why a CRP of 58 mg/L remains elevated after a higher previous result, but our platform is not a continuously monitored emergency service. Share meaningful changes with the treating clinician, and use local emergency services for severe deterioration; uploading another report should never delay urgent assessment.
When is colonoscopy needed after diverticulitis?
Colonoscopy may be recommended after recovery to exclude another bowel condition, especially following complicated diverticulitis or a first uncomplicated episode. The AGA recommends waiting 6–8 اونیو, or until symptoms have fully resolved if longer, and allows deferral in selected people with a recent high-quality colonoscopy within 1 year.

Bowel cancer can occasionally resemble diverticulitis on presentation, which is why follow-up is risk-based rather than a statement that diverticulitis causes cancer. The meta-analysis summarized by AGA found colorectal cancer in 1.9% of patients after diverticulitis, with higher prevalence after complicated episodes (7.9%) than uncomplicated episodes (1.3%) (Peery et al., 2021).
Routine colonoscopy is usually avoided during the acute painful phase, because examination can be technically harder and potentially riskier. The 6–8-week interval is a practical recovery window, not a guarantee that every bowel has healed by a calendar date; ongoing tenderness or systemic symptoms should be discussed before the procedure.
Iron-deficiency anemia, weight loss, persistent rectal bleeding or an ongoing change in bowel habits may alter follow-up urgency. A positive FIT requires its own evaluation and is not cancelled by a diverticulitis label; our مثبت FIT راتلونکي ګامونه guide explains why 1 positive stool screening result needs a defined diagnostic plan.
Persistent discomfort does not always mean continuing diverticulitis: the AGA review notes periodic abdominal pain in approximately 45% of patients at 1 year in a cited trial. Clinicians may investigate ongoing inflammation or another diagnosis with imaging and lower endoscopy before considering visceral hypersensitivity; recurrent severe symptoms should not be assigned that explanation without assessment.
What Kantesti can explain—and what it cannot diagnose
Kantesti د AI په وسیله د وینې ازموینې تحلیل وسیله ده that can help explain CRP, WBC and other laboratory findings, but it cannot confirm diverticulitis or exclude an abscess from a report. A CRP of 3 mg/L or 150 mg/L still requires symptoms, examination and sometimes imaging to determine the cause.
Our platform can explain units and available trends, while the limits of automated interpretation remain explicit. For example, 15 × 10⁹/L او 15,000 cells/µL describe the same WBC count; our د ټیکنالوژۍ توضیحات provides context for how uploaded laboratory information is processed, not evidence that a scan is unnecessary.
Technical performance and clinical diagnosis are different claims, so a software benchmark must not be read as a diverticulitis diagnostic trial. Kantesti's د اعتبارسنجۍ او څارنې معلومات should be interpreted within its stated scope; no general laboratory benchmark establishes that an AI can safely exclude perforation from 1 CBC or CRP result.
The 2 Zenodo publications listed below provide platform reporting and RDW education, respectively; neither is a clinical guideline or direct evidence for diagnosing diverticulitis. Kantesti's Global Health Report describes analysis activity, while the RDW guide concerns red-cell size variation—a high RDW should not be presented as confirmation of an acute bowel disorder.
Use AI explanations to prepare questions, not to postpone care, particularly during a first episode or a worsening recurrence. Our د مصنوعي ځیرکتیا مسؤلانه اصول describe these boundaries; the practical question is not whether 1 number looks reassuring, but whether your symptoms require an examination, imaging or urgent treatment.
پرله پسې پوښتل شوي پوښتنې
د ډایورټیکولایټس لومړنۍ نښې کومې دي؟
د ډایورټیکولایټس په لومړیو پړاوونو کې د نس په لاندې کیڼ اړخ کې موضعي درد پیدا کېدای شي چې دوامدار شي، حساسیت، د اشتها کمښت او قبض یا نس ناستی رامنځته کړي. نښې ښايي په ۱–۲ ورځو کې څرګندې شي، خو کومه باوري ټاکلې لړۍ نه لري او تبه هم ښايي نه وي. نوی، دوامدار او موضعي درد د هماغې ورځې طبي مشورې ته اړتیا لري؛ د ټولو معمول نښو تر څرګندېدو پورې انتظار مه کوئ. شدید یا خپرېدونکی درد، پرلهپسې کانګې، بېهوشي یا ګډوډي بیړنۍ پاملرنې ته اړتیا لري.
ایا له تبې پرته ډایورټیکولایټس لرلای شئ؟
ډایورټیکولایټس له تبې پرته هم رامنځته کېدای شي، او له 38°C څخه ټیټه تودوخه د ناروغۍ حمله یا اختلاط نه ردوي. د ناروغۍ په لومړیو کې، په زړو کسانو کې یا د کورټیکوسټرویډونو او تبهکموونکو درملو د کارولو پر مهال، تبه ښايي لږه څرګنده وي. د تبې نشتوالی باید د درد د زیاتېدو، د مایعاتو د څښلو د زغملو او معاینې له پایلو سره یوځای وارزول شي. که نښې خرابېږي، بېړنۍ ارزونه وغواړئ، که څه هم د ترمامیتر لوست عادي وي.
د ډایورټیکولایټس درد معمولاً په کوم ځای کې وي؟
Diverticulitis usually causes lower-left abdominal pain because the sigmoid colon is commonly affected, but pain can also be central, pelvic or right-sided. The position of 1 painful area cannot confirm the diagnosis, and right-sided pain can resemble appendicitis. New pain that spreads or becomes severe warrants reassessment. Clinicians may recommend imaging when location and examination do not clearly distinguish the cause.
Can normal blood tests rule out diverticulitis?
Normal WBC and CRP results cannot reliably rule out diverticulitis, particularly early in an episode. Many adult laboratories use a WBC range around 4–11 × 10⁹/L and a CRP upper limit of 5 mg/L, but local intervals differ. Elevated results also cannot confirm diverticulitis because many inflammatory conditions raise these markers. Symptoms, examination and sometimes CT are needed to establish the diagnosis and assess complications.
When is left-sided abdominal pain an emergency?
Left-sided abdominal pain needs emergency assessment when it is severe or spreading, or when it occurs with fainting, confusion, repeated vomiting or marked abdominal swelling. Swelling with inability to pass gas or stool can indicate obstruction, while large-volume rectal bleeding with weakness can indicate significant blood loss. A fever of 38°C is not required before seeking emergency care. Do not wait for a blood test result when these warning signs are present.
Do you always need a CT scan for diverticulitis?
Not every mild recurrence of previously confirmed diverticulitis requires CT, but imaging is often recommended for a first uncertain episode, severe symptoms, suspected complications or failure to improve. CT has approximately 95% sensitivity and specificity for diverticulitis and can identify an abscess or an alternative cause of pain. The ACP guideline recommends CT when there is diagnostic uncertainty, while AGA guidance also emphasizes patients without a previous imaging-confirmed diagnosis. Pregnancy, kidney function and local expertise influence the imaging approach.
Does diverticulitis always need antibiotics?
Selected immunocompetent adults with mild, uncomplicated diverticulitis may be treated without antibiotics under a clinician's supervision. Antibiotics are generally recommended when systemic illness, immunosuppression, significant comorbidity or higher-risk features are present. AGA guidance identifies CRP above 140 mg/L or WBC above 15 × 10⁹/L as treatment-relevant risk features, not diagnostic cutoffs. Inability to drink, worsening pain or new emergency symptoms requires reassessment regardless of whether antibiotics have been prescribed.
د وینې ازموینې پایلې څنګه ولولئ
خپل لابراتواري راپور پورته کړئ، او د Kantesti AI به په څو ثانیو کې هر بایومارکر په ساده ژبه تشریح کړي. په ټوله نړۍ کې له 2 میلیونو څخه زیاتو کسانو ترې کار اخیستی.
ماخذونه
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د AI وینې د ازموینې شنونکی: 2.5M ازموینې تحلیل شوې | د نړیوال روغتیا راپور 2026. د Kantesti AI طبي څېړنه. د دفاع وزارت
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د RDW د وینې ازموینه: د RDW-CV، MCV او MCHC بشپړ لارښود. د Kantesti AI طبي څېړنه. د دفاع وزارت
- National Institute for Health and Care Excellence (2019). Diverticular disease: diagnosis and management (NG147). NICE Clinical Guideline.
- Peery AF et al. (2021). AGA Clinical Practice Update on Medical Management of Colonic Diverticulitis: Expert Review. Gastroenterology. د دفاع وزارت پب میډ
- Qaseem A et al. (2022). Diagnosis and Management of Acute Left-Sided Colonic Diverticulitis: A Clinical Guideline From the American College of Physicians. Annals of Internal Medicine. د دفاع وزارت
- ۲ میلیونه+تحلیل شوې ازموینې
- 127+هېوادونه
- 100+ژبې
د طبي ټیم په اړه


د E-E-A-T باور نښې
تجربه
د ډاکټر تر مشرۍ لاندې کلینیکي بیاکتنه د لابراتواري تفسیر د کاري بهیرونو لپاره.
تخصص
د لابراتواري طب تمرکز پر دې چې بایومارکرونه په کلینیکي شرایطو کې څنګه چلند کوي.
واک ورکول
د ډاکټر توماس کلاین له خوا طبي بیاکتنه شوې، د ډاکټر سارا میچل او پروفیسور ډاکټر هانس وېبر په مرسته.
اعتبار
د شواهدو پر بنسټ تفسیر د روښانه تعقیبي لارو چارو سره، تر څو اندیښنه کمه شي.




طبي سلبِ مسئولیت
دا مقاله یوازې د زده کړې لپاره ده او طبي مشوره نه جوړوي. د تشخیص او درملنې د پرېکړو لپاره تل د وړ روغتیايي خدمت وړاندې کوونکي سره سلا وکړئ.
خپور شوی · له تحریري ټیم سره اړیکه ونیسئ
خپروونکی یې Kantesti Ltd دی، چې په انګلستان او وېلز کې ثبت شوی، د شرکت شمېره. 17090423, ، لندن، بریتانیا.
