
Essential tremor is linked to altered brain movement-network activity and inherited susceptibility, not a single proven cause. Stress, stimulants, poor sleep, and certain medicines can amplify shaking; diagnosis depends on the tremor pattern and examination, not one blood test.

Helstu niðurstöður
- Essential tremor causes involve inherited susceptibility and altered movement-network activity; no single gene, chemical imbalance, or laboratory result explains every case.
- Action tremor occurs while holding a posture or moving, such as lifting a cup; essential tremor commonly oscillates at approximately 4–12 Hz.
- Diagnostic criteria classify essential tremor as isolated bilateral upper-limb action tremor lasting at least 3 years, with or without tremor elsewhere.
- Hereditary risk is not a universal 50% prediction: that figure applies to transmission of a disease-associated variant in an established autosomal-dominant family.
- Essential tremor triggers include caffeine, stress, insufficient sleep, and some medicines; worsening after one exposure does not establish the diagnosis.
- Lágur glúkósi below 70 mg/dL, or 3.9 mmol/L, can cause shaking through an adrenaline response; levels below 54 mg/dL, or 3.0 mmol/L, require immediate attention.
- Blóðpróf can identify thyroid disease, metabolic problems, or medication-related contributors, but normal results neither confirm nor exclude essential tremor.
- Bráðaeinkenni include sudden shaking with weakness, speech difficulty, severe imbalance, or confusion; call emergency services rather than waiting for laboratory results.
What actually causes essential tremor?
Essential tremor causes are not fully established, but evidence points to inherited susceptibility and altered activity in networks connecting the cerebellum, thalamus, and motor cortex. The condition usually produces shaking during posture or movement, often at approximately 4–12 Hz, rather than being explained by one abnormal blood value.

The cerebellum helps coordinate the timing and accuracy of movement; disturbances across its connections can produce rhythmic oscillation rather than smooth control. The 2018 International Parkinson and Movement Disorder Society consensus separates the observable tremor syndrome from its underlying cause because the same movement pattern can arise through different mechanisms (Bhatia et al., 2018).
A 4–12 Hz rhythm means approximately 4–12 back-and-forth cycles each second, not 4–12 episodes a day. Frequency overlaps with other tremors, so a smartwatch reading or a visibly shaking cup cannot identify the cause without examining when the movement appears and which additional signs accompany it.
Kantesti er AI blóðprufugreiningartæki that can help explain laboratory findings relevant to tremor mimics, but no uploaded panel establishes essential tremor. Our stofnun og tilgangur center on interpreting laboratory information; a neurological examination answers a different question about movement.
At Kantesti, we separate 1 underlying syndrome from factors that make it more noticeable: caffeine may increase existing shaking without creating essential tremor itself. That distinction prevents a common mistake—assuming that improvement after removing a trigger proves the entire diagnosis was merely stress or diet.
Why do my hands shake when I use them?
Hands can shake during movement because essential tremor, enhanced physiological tremor, medication effects, and several neurological disorders all produce action tremor. The 2018 consensus describes essential tremor as isolated tremor affecting both upper limbs during action for at least 3 ára fresti, without other defining neurological signs.

Postural tremor appears when the arms are held against gravity; kinetic tremor appears during voluntary movement, such as pouring water or writing. A clinician may compare these 2 situations because shaking can be slight with outstretched arms yet much more disruptive when a hand approaches a cup.
Both hands are generally involved in essential tremor, but 2 affected hands do not have to shake equally. Hand dominance, task demands, and unequal severity can make one side more noticeable; persistent one-sided shaking nevertheless deserves assessment rather than an automatic essential-tremor label.
The 3-year criterion is a classification safeguard, not an instruction to postpone care for 3 years (Bhatia et al., 2018). A shorter-duration isolated action tremor may remain an indeterminate tremor syndrome while clinicians treat functional problems and watch for features that clarify its cause.
Numbness is not a defining feature of essential tremor, even when shaking and sensory symptoms affect the same hand. Record which of the 5 fingers becomes numb; the distribution described in our hand numbness guide can help distinguish a nerve-compression problem that needs separate assessment.
Is essential tremor hereditary in every family?
Essential tremor can run in families, but not every affected person has a recognizable family history, and routine genetic testing cannot confirm most cases. A 50% inheritance probability applies only to transmission of a relevant variant in a genuinely autosomal-dominant family—not to every child of every person with shaky hands.
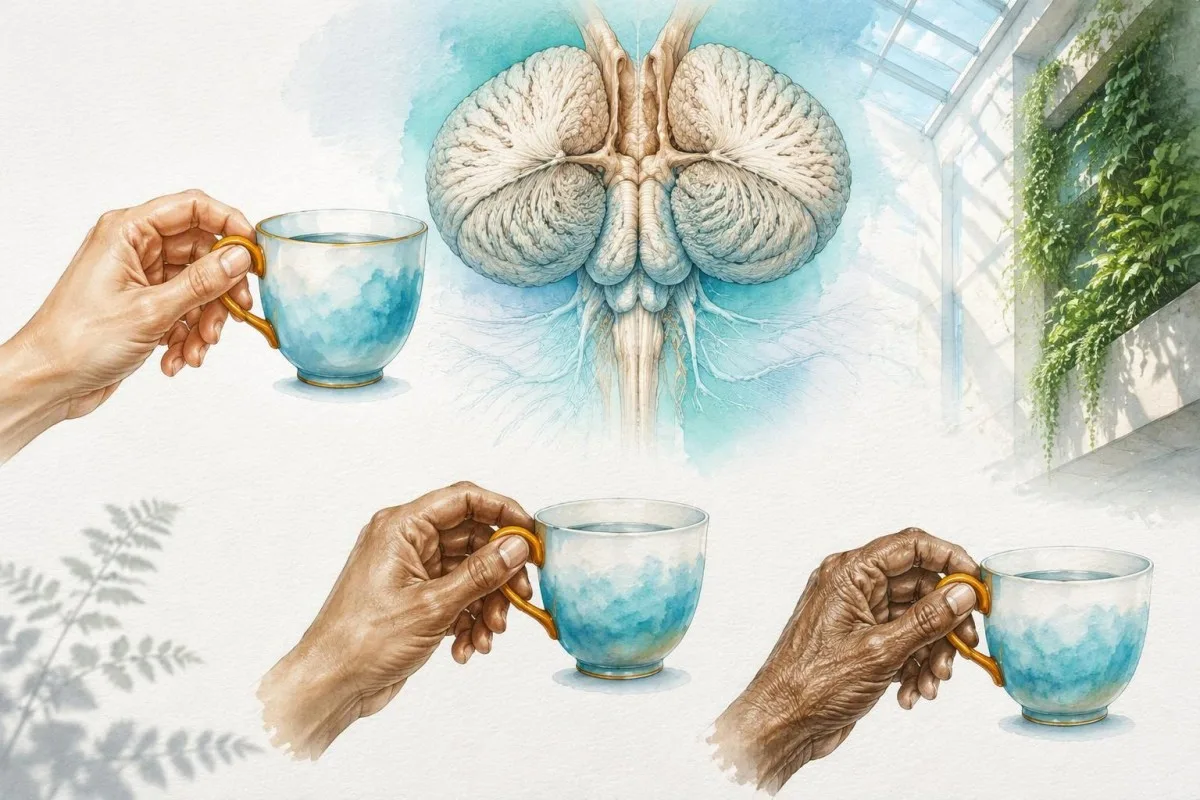
A family history should distinguish similar action tremor from Parkinsonian tremor, medication-related shaking, and an uncertain description of 'nervous hands.' A 3-generation history is often more informative than a yes-or-no question because age at onset, affected tasks, and accompanying neurological symptoms change how relatives' symptoms are interpreted.
An unaffected parent does not rule out inherited susceptibility: symptoms may be mild, begin later, or go unrecognized. Conversely, 2 relatives with tremor do not prove a single-gene disorder because relatives can share medications, exposures, and common age-related conditions as well as genetic variants.
Most essential tremor is not explained by a clinically validated 1-gene screening test, so a negative commercial genetic result cannot clear someone of the condition. The meaningful question is whether the overall pattern suggests ordinary familial essential tremor or a different disorder with an established genetic investigation.
Tremor accompanied by progressive balance problems, neuropathy, or cognitive change—especially after age 50—can justify consideration of fragile X-associated tremor/ataxia syndrome in the right family context. Our FMR1 testing explanation discusses a different genetic pathway; it is not a reason to screen every person with isolated action tremor.
Which essential tremor triggers make shaking worse?
Essential tremor triggers commonly include emotional stress, caffeine, nicotine, insufficient sleep, and physical fatigue, but individual sensitivity varies. A 7–14-day diary can reveal repeatable associations more reliably than judging the condition from one difficult morning or one stressful appointment.

Caffeine can amplify physiological tremor and make an established movement disorder more visible, but there is no universal tremor-producing dose. For a hypothetical person drinking 300 mg á dag, reducing intake gradually while keeping sleep and meals stable provides a cleaner observation than stopping caffeine and changing 4 other habits simultaneously.
Stress increases sympathetic activity, which can amplify shaking without making essential tremor a psychological disorder. Compare 2 similar tasks—such as writing at home and signing a form under observation—because performance pressure changes tremor amplitude even when the underlying neurological susceptibility remains the same.
Sleep loss may worsen motor steadiness, but fatigue after 1 poor night is not evidence of a newly developed neurological disease. Our poor-sleep laboratory guide explains why symptom changes and laboratory changes may coexist without one result accounting for the whole movement problem.
Some people notice brief improvement after alcohol, but that response is neither specific enough to diagnose essential tremor nor a safe treatment strategy. Tremor can worsen later, and shaking beginning 6–24 hours after reducing sustained heavy drinking raises concern for withdrawal rather than ordinary trigger sensitivity.
Can fasting or low glucose mimic essential tremor?
Low glucose can cause trembling, sweating, hunger, and palpitations through an adrenaline response; it usually produces episodes rather than a stable action-tremor syndrome. Glucose below 70 mg/dL (3.9 mmol/L) is a hypoglycemia alert threshold, while below 54 mg/dL (3,0 mmol/L) represents clinically significant hypoglycemia.

Skipping a meal does not automatically cause dangerous hypoglycemia in a person without diabetes, and shakiness alone cannot prove that glucose is low. A measurement taken during symptoms is more useful than a fasting result from 2 weeks earlier, particularly for someone using insulin or a sulfonylurea.
For an awake adult with diabetes who can swallow safely, a commonly used response is 15 g of rapid-acting carbohydrate, followed by a glucose recheck after 15 mínútur, according to their care plan. Confusion, inability to swallow, unconsciousness, or failure to recover requires emergency help; never give food or drink to an unconscious person.
Repeated suspected hypoglycemia in someone without diabetes is investigated using 3 linked findings: compatible symptoms, documented low plasma glucose, and improvement when glucose rises. Our leiðbeiningar um orsakir lágs glúkósa explains why medicines, illness, alcohol, and fasting history matter more than assuming a rare hormone disorder.
Dehydration, strenuous exercise, and insufficient food can also make a pre-existing tremor harder to control without being its original cause. In a hypothetical 45-year-old whose hands shake only after long workouts, the symptom timing points first toward exercise, intake, and medication review—not immediately toward familial essential tremor.
Which medicines can look like essential tremor?
Medication-induced tremor can resemble essential tremor, particularly after a medicine is started, increased, or accumulated because clearance changes. Common contributors include beta-2 agonist inhalers, lithium, valproate, some antidepressants, stimulants, theophylline, and tacrolimus; 1 recent prescription change can be more informative than a broad laboratory screen.

The review Insights into Pathophysiology from Medication-induced Tremor describes several mechanisms, including enhancement of physiological tremor and medication-associated neurological effects (Morgan et al., 2017). A dose-response relationship is useful evidence, but 2 causes can coexist: a medicine may amplify previously mild essential tremor rather than account for every symptom.
Lithium can produce a fine postural tremor at therapeutic concentrations, whereas a new coarse tremor with vomiting, confusion, or unsteadiness needs urgent toxicity assessment. Kantesti can help explain results from lithium safety monitoring, en 1 styrkur must be interpreted alongside sample timing, symptoms, kidney function, and interactions.
Valproate-associated tremor does not require a concentration above the laboratory's therapeutic interval, and changes in protein binding can complicate interpretation. Our valproate concentration guide explains why total and free measurements may answer 2 different questions; do not stop an antiseizure medicine abruptly to test a theory.
Theophylline-related shaking may accompany nausea or palpitations, making the theophylline timing guide relevant when that medicine is prescribed. Reduced kidney function can also alter exposure to some tremor-associated medicines; our leiðarvísir okkar um túlkun nýrnastarfsemi hvernig á að lesa blóðprufur hvers vegna 2 kidney markers require context rather than a single 'normal' flag.
How is essential tremor different from Parkinson’s tremor?
Essential tremor usually predominates during action, whereas Parkinsonian tremor often appears at rest and accompanies movement slowness or rigidity. Parkinsonian rest tremor commonly falls around 4–6 Hz, but frequency and movement timing overlap enough that neither feature alone provides a diagnosis.

Bradykinesia means more than feeling slow: examination looks for reduced speed together with decreasing amplitude or interruptions during repeated movements. A clinician may ask for about 10 finger taps, observing the sequence rather than interpreting one awkward movement as evidence of Parkinson's disease.
Parkinsonian tremor can reappear after the arms are held out, creating an action-like pattern that patients may mistake for essential tremor. Essential tremor can also acquire additional features over time, so 1 apparently clear distinction—'moving means essential, resting means Parkinson's'—is too simple for a reliable self-diagnosis.
A dopamine-transporter scan may help in selected cases when examination leaves uncertainty about a presynaptic dopaminergic deficit; it is not a routine essential-tremor confirmation test. The scan answers 1 narrower biological question and cannot replace assessment of medications, movement slowness, rigidity, and the overall neurological pattern.
Skin testing for abnormal phosphorylated alpha-synuclein is also an adjunct in selected diagnostic settings, not a screening requirement for shaky hands. Our Parkinson’s skin-test explanation describes why 1 positive or negative result must be interpreted within the suspected syndrome rather than used as an essential-tremor verdict.
What other conditions mimic movement-related hand tremor?
Dystonic, cerebellar, neuropathic, and functional tremors can all resemble essential tremor during movement, but their associated signs change the diagnosis. Enhanced physiological tremor, often around 8–12 Hz, is another common possibility when shaking is fine, trigger-sensitive, and not accompanied by a persistent neurological syndrome.
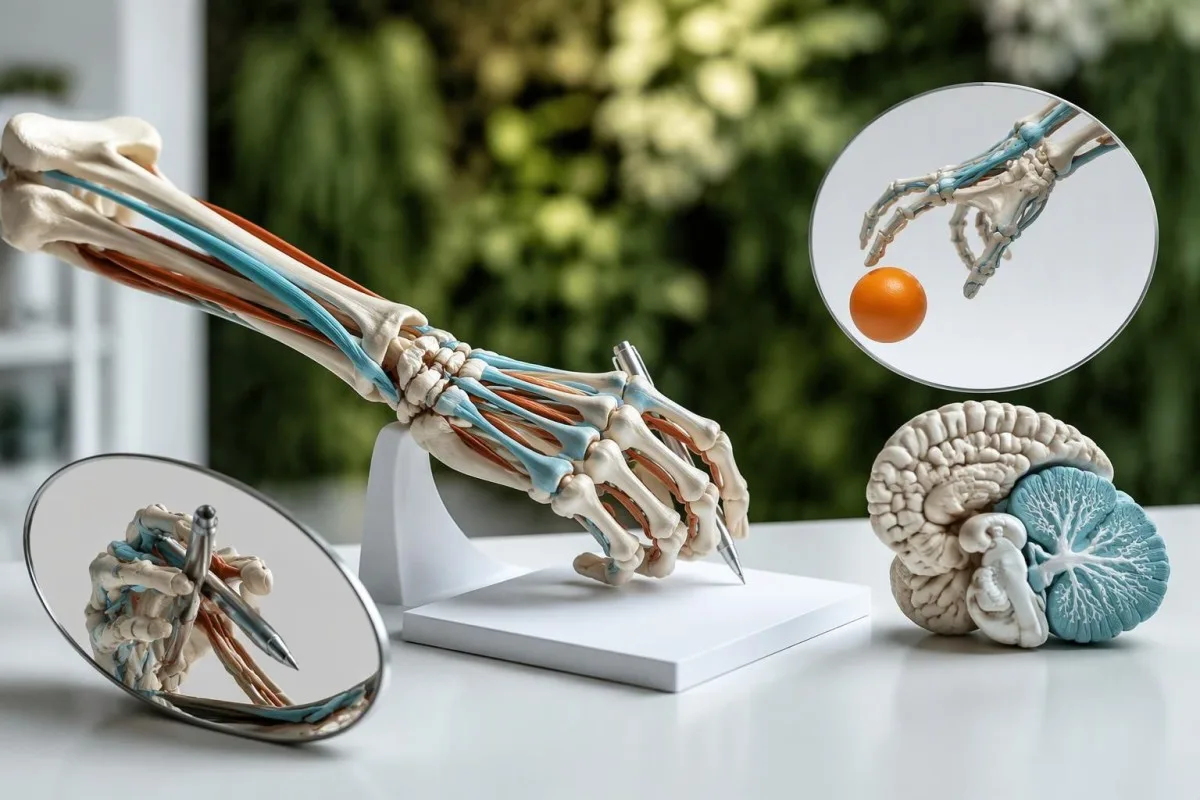
Dystonic tremor may be irregular, position-dependent, or accompanied by abnormal twisting or sustained posture. A hand that shakes during 1 writing position but steadies at a particular angle deserves examination for dystonia or task-specific tremor; the finding is not automatically proof of an unusual form of essential tremor.
Cerebellar tremor often becomes more prominent as the hand approaches a target and may accompany impaired coordination, abnormal eye movements, or gait imbalance. Clinicians compare 2 sides during finger-to-nose testing because marked asymmetry or additional cerebellar signs can justify imaging or a more targeted neurological investigation.
Neuropathic tremor is considered when shaking accompanies sensory loss, weakness, or reduced reflexes, particularly with certain peripheral nerve disorders. Our neuropathy antibody explanation illustrates why 1 antibody result cannot explain tremor without a compatible nerve examination and, when indicated, nerve-conduction testing.
Functional tremor is diagnosed through positive examination features, such as marked variability, distractibility, or entrainment to another movement—not simply normal blood tests. If tremor changes while the opposite hand taps at 2 different rhythms, that may contribute to specialist assessment; it does not mean symptoms are fabricated or that a home experiment establishes the diagnosis.
Which blood tests can find treatable causes of shaking?
Blood tests for shaking are selected to investigate alternatives, commonly thyroid dysfunction, low glucose, electrolyte disturbances, kidney or liver problems, and relevant medication exposure. Many adult laboratories use a TSH interval near 0.4–4.0 mIU/L, but the local interval and accompanying free T4 result determine interpretation.
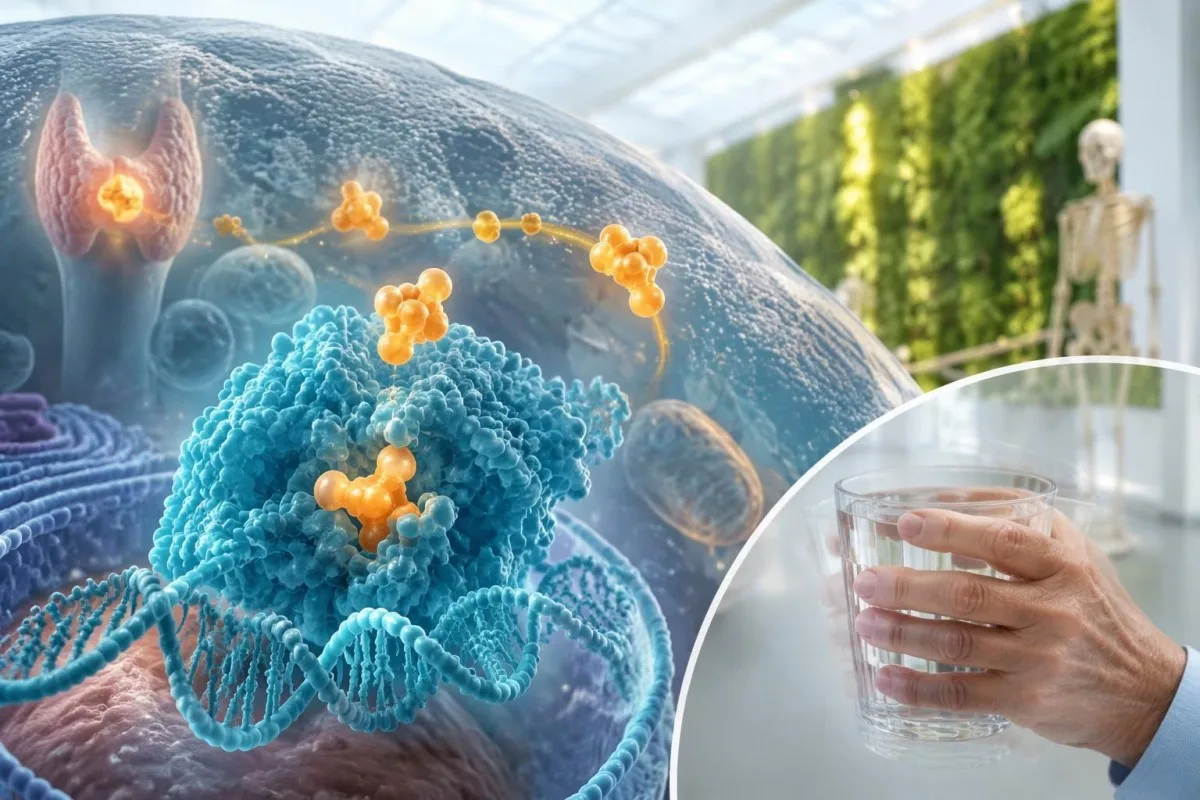
Overactive thyroid function can produce a fine action tremor with heat intolerance, weight loss, or a fast pulse. A hypothetical TSH of 0.02 mIU/L together with free T4 above that laboratory's interval supports thyrotoxicosis; our thyroid hormone explanation shows why TSH alone cannot establish its cause.
Electrolyte testing is more useful when shaking accompanies vomiting, diarrhea, diuretic use, cramps, or broader illness than when an isolated tremor has been stable for 10 ár. Magnesium intervals vary—many laboratories use approximately 1,7–2,2 mg/dL—and a low result may identify a treatable contributor without explaining the entire movement pattern.
Vitamin B12 assessment becomes more relevant when sensory changes, balance problems, anemia, restricted intake, or malabsorption accompany tremor. 1 borderline B12 result is not an essential-tremor biomarker; symptom pattern and sometimes additional testing determine whether a deficiency is clinically meaningful.
Kantesti er AI blóðrannsóknartúlkunarvettvangur that can help contextualize TSH, glucose, and other uploaded results against their reported units and intervals. Our laboratory biomarker guide supports that process, but even 20 normal measurements cannot replace examination of the shaking itself.
| Styrkur | Bil | Merking |
|---|---|---|
| Dæmigert viðmiðunarbil TSH hjá fullorðnum | Approximately 0.4–4.0 mIU/L | Use the laboratory's own interval; a result within it does not confirm or exclude essential tremor. |
| Markedly suppressed TSH | Undir 0,1 mIU/L | Assess free T4, sometimes T3, medicines, and assay interference; suppression alone does not prove overt hyperthyroidism. |
| Viðvörun um blóðsykursfall | Glúkósa undir 70 mg/dL (3.9 mmol/L) | May cause episodic shaking, especially with glucose-lowering medicines; follow the appropriate hypoglycemia plan. |
| Klínískt marktæk blóðsykurslækkun | Glucose below 54 mg/dL (3.0 mmol/L) | Requires immediate action; impaired consciousness or inability to swallow requires emergency assistance. |
Why can no single laboratory test confirm essential tremor?
No single laboratory test confirms essential tremor because it is a clinically defined movement syndrome without a validated diagnostic blood biomarker. The 3-year action-tremor criterion describes a pattern over time; it does not correspond to a measurable TSH, vitamin, inflammatory marker, or genetic cutoff.

Routine results can exclude or identify selected alternatives, but exclusion does not logically prove essential tremor. A person with 5 normal panels may still have dystonic tremor, a medication effect, functional tremor, or an early neurological syndrome that laboratory testing was never designed to distinguish.
Research into cerebellar cells, inhibitory signaling, imaging, and genetics has not produced a routine biomarker with established diagnostic performance across everyday tremor populations. 1 promising research association is different from a clinically validated test that reliably distinguishes essential tremor from the disorders patients actually present with.
Neurofilament light is a marker of neuroaxonal injury in several settings, not a specific essential-tremor assay. Our leiðarvísir um túlkun NfL hvernig á að lesa blóðprufur hvers vegna 1 elevated value needs age, clinical context, and other investigations; a normal value does not establish a benign tremor diagnosis.
Kantesti can explain what laboratory findings support and what they leave unanswered, but our AI cannot certify essential tremor from 1 PDF or photographOkkar meginreglur um ábyrga notkun gervigreindar are relevant here: stating the limits of an interpretation is part of making it medically useful.
What happens during an essential tremor assessment?
Essential tremor assessment combines history, examination, and observation of tasks, with testing added when particular findings suggest another cause. A 30–60-second video of a troublesome activity can be useful if symptoms fluctuate, provided it supplements rather than replaces an in-person or appropriately arranged clinical assessment.

The history should cover onset, progression, family patterns, medicines, stimulants, alcohol use, and functional difficulty. Bring 1 complete medication list that includes nonprescription decongestants, pre-workout products, inhalers, and supplements; names and timing often reveal more than a vague description of 'no regular medicines.'
Observation may include supported rest, outstretched arms, finger-to-nose testing, writing, spiral drawing, and pouring. Repeating 2 or 3 relevant tasks helps distinguish amplitude from disability: a visible tremor may barely affect eating, while a smaller tremor can seriously disrupt a musician's or technician's precision work.
Accelerometry and surface electromyography can quantify movement frequency and muscle activation when the pattern is uncertain, but 1 frequency measurement does not prove essential tremor. Brain MRI is generally reserved for atypical features such as abrupt onset, marked asymmetry, coordination abnormalities, or other neurological findings rather than routine uncomplicated cases.
Exposure testing should also be targeted, not an automatic 'toxin panel' for every shaky hand. Our leiðarvísir að prófi fyrir þungmálma explains why a credible occupational, environmental, or supplement exposure matters before ordering 1 specialized assay whose result might otherwise create confusion.
How do symptom patterns change the likely explanation?
The combination of timing, examination, and associated symptoms changes the likely cause of shaking, even when hand movements look similar. These 3 tilbúnu dæmi show why essential tremor, thyroid-related tremor, and medication amplification lead to different next steps rather than one universal laboratory package.
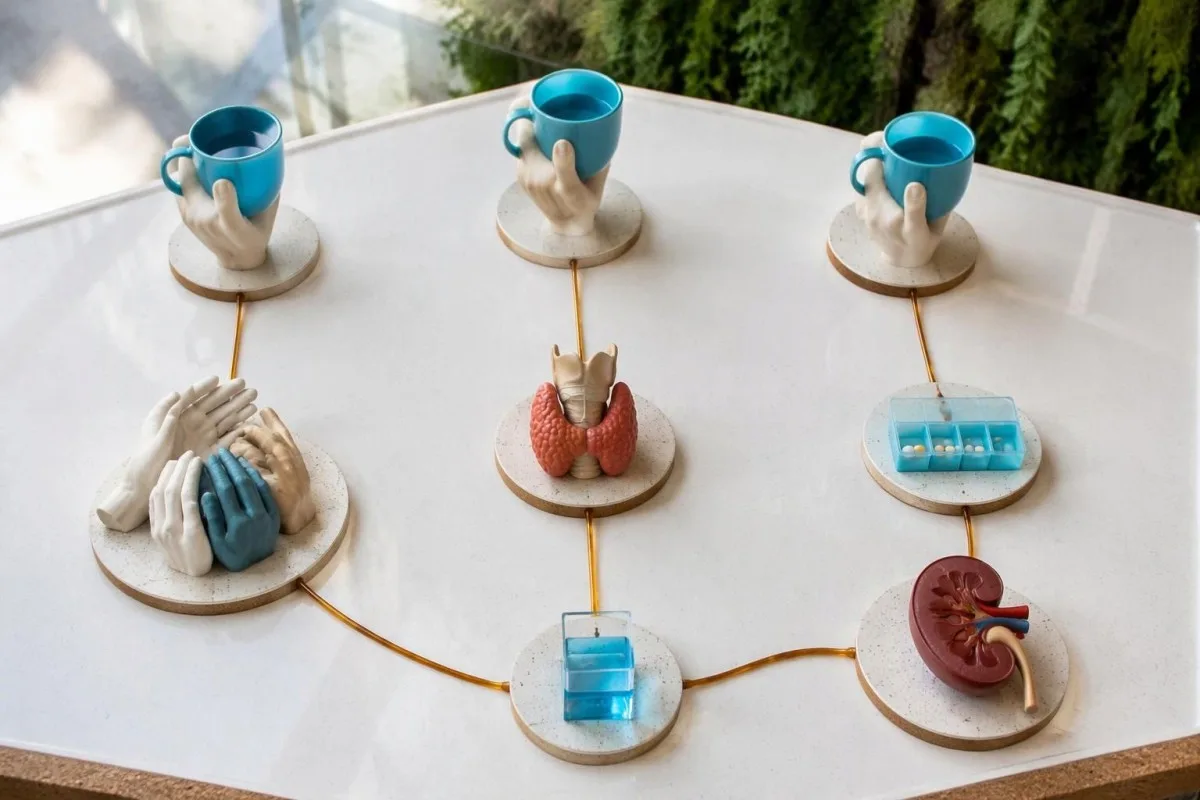
Imagine a 38 ára with bilateral cup-lifting tremor since their twenties, a similarly affected parent, and no rigidity, numbness, or gait change. Essential tremor becomes plausible after examination, but family resemblance remains supporting evidence rather than proof; normal thyroid results would remove one competing explanation, not establish the diagnosis.
Now consider a 52 ára with new fine shaking, weight loss, palpitations, TSH 0.02 mIU/L, and elevated free T4. Thyrotoxicosis needs assessment and treatment; persistence of tremor after thyroid function improves would prompt reassessment for an additional movement disorder rather than automatically declaring treatment failure.
A third hypothetical person, aged 67, notices worsening shaking after a medicine increase while kidney function has declined. Reviewing the medicine, interactions, concentration when appropriate, and clearance may identify a reversible amplifier; apparent improvement after adjustment still does not exclude a mild underlying essential tremor.
For established, functionally troublesome essential tremor, propranolol and primidone have Level A evidence in the 2011 American Academy of Neurology guideline; neither response confirms the diagnosis (Zesiewicz et al., 2011). Selection depends on asthma, pulse, blood pressure, falls, and interactions; our B-flókið öryggisleiðbeiningar explains why adding vitamins without a deficiency is not a substitute for tremor treatment.
When does new hand shaking need urgent care?
Sudden shaking with weakness, speech difficulty, new severe imbalance, confusion, or a severe headache requires urgent medical assessment, not an essential-tremor assumption. A movement change developing within minutes or hours is different from the gradual, longstanding pattern usually associated with essential tremor.

Call emergency services for possible stroke signs, even if shaking is the symptom that first attracted attention. Our leiðarvísi okkar um viðvörunarmerki heilablóðfalls explains balance, vision, face, arm, and speech changes; recording the exact time symptoms began helps emergency teams assess treatment options.
New coarse shaking with confusion, vomiting, or difficulty walking while taking lithium or another potentially neurotoxic medicine warrants urgent assessment. Do not wait for the next scheduled trough measurement: 1 apparently therapeutic previous result does not protect against a new interaction, dehydration, overdose, or change in clearance.
Shaking after reducing sustained heavy alcohol intake can be an early withdrawal symptom, and seizures, hallucinations, or escalating agitation are emergency signs. Withdrawal symptoms may begin around 6–24 hours after reduction, but timing varies; avoid managing significant withdrawal alone or using alcohol as a tremor remedy.
Book a nonemergency clinical review when shaking persists, spreads, changes character, or interferes with eating, drinking, work, or handwriting. A short diary covering 7 dagar can help, but do not delay assessment merely to complete it—especially when new sensory symptoms, balance trouble, or medication changes accompany the tremor.
Follow-up, AI limits, and research publication context
Useful follow-up tracks function, symptom pattern, and any identified reversible contributor, rather than repeatedly ordering normal laboratory panels. Choose 2 or 3 meaningful activities, such as carrying a cup, signing your name, and using a utensil, so progress reflects daily ability rather than the appearance of one isolated recording.

Keep recording conditions similar: compare the same task at a similar time, noting sleep, meals, caffeine, and medicine timing. 1 unusually steady or shaky day may reflect normal fluctuation; a sustained change across repeated observations is more helpful when discussing treatment benefit or a newly emerging neurological feature.
Kantesti er AI-knúið blóðprófunargreiningartól that can help organize laboratory explanations when a clinician investigates thyroid, metabolic, or medication-related contributors. Interpretation of 1 uploaded report cannot replace movement examination; our klínískt staðfestingarramma should be read alongside the specific limits of the task being assessed.
Repeat testing should answer a defined question, such as whether thyroid treatment has corrected an abnormality or a medication adjustment has changed exposure. Repeating the same broad panel every 4 vikur solely because essential tremor remains visible usually adds less information than reviewing function, side effects, and whether the clinical pattern has changed.
The 2 Figshare-útgáfur listed below are background reading on digestive and hormonal symptoms, not evidence establishing essential tremor causes or validating a tremor diagnosis. Our fasting and digestive-symptom guide provides adjacent context when reduced intake complicates symptoms; a DOI identifies a publication but does not itself establish peer review or clinical validity.
Algengar spurningar
Hver er helsta orsök nauðsynlegs skjálfta?
Nauðsynlegur skjálfti tengist arfgengri tilhneigingu og breyttri virkni í taugakerfum heilans sem samhæfa hreyfingar, en nákvæm orsök hans er enn ekki að fullu þekkt. Skjálftinn kemur oft fram við stöðuhald eða hreyfingu á um það bil 4–12 Hz. Hvorki þessi tíðni né fjölskyldusaga sannar greininguna. Læknar greina heilkennið út frá einkennamynstri þess, lengd, niðurstöðum skoðunar og mati á öðrum mögulegum skýringum.
Er nauðsynlegur skjálfti arfgengur og munu börnin mín fá hann?
Nauðsynlegur skjálfti getur verið ættgengur, en foreldri sem hefur hann leiðir ekki til þess að almennar 50%-líkur séu á að hvert barn fái hann. 50%-líkur á að erfðabreytileiki berist gilda um viðeigandi erfðabreytileika í fjölskyldu þar sem ríkjandi erfðir á sjálflitningi hafa verið staðfestar, en það á ekki við um allan nauðsynlegan skjálfta. Einkenni sem ráðast af aldri, ófullkomin sýnd og flóknar erfðir gera einstaklingsbundnar spár óvissar. Ættarsaga yfir 3 kynslóðir er gagnleg, en hefðbundnar erfðarannsóknir geta ekki staðfest flest tilvik nauðsynlegs skjálfta.
Af hverju skjálfa mér hendurnar þegar ég held á einhverju?
Hendur geta skolfið þegar haldið er á hlut vegna nauðsynlegs skjálfta, aukins lífeðlislegs skjálfta, áhrifa lyfja, ofvirks skjaldkirtils eða annarra hreyfitruflana. Nauðsynlegur skjálfti hefur yfirleitt áhrif á báðar hendur við hreyfingu, þó að alvarleikinn geti verið mismunandi milli hliða. Alþjóðleg samstaða miðar við að aðgerðatengdur skjálfti í báðum efri útlimum hafi verið til staðar í einangrun í að minnsta kosti 3 ár við flokkun, en ekki ætti að fresta mati þar til þeim tíma er náð. Nýtilkominn máttleysi, dofi, jafnvægisvandamál eða skyndileg breyting á einkennum breytir mati.
Getur blóðprufa greint nauðsynlegan skjálfta?
Engin blóðprufa getur staðfest nauðsynlegan skjálfta og eðlilegar niðurstöður rannsóknarstofuprófa útiloka hann ekki. Prófanir geta greint aðrar mögulegar orsakir, svo sem skjaldkirtilssjúkdóm, blóðsykur undir 70 mg/dL, truflanir á blóðsaltajafnvægi eða útsetningu fyrir viðeigandi lyfjum. Læknir velur rannsóknir út frá einkennum og skoðun í stað þess að panta eina allsherjar skjálftaprófun. Jafnvel nokkrar eðlilegar rannsóknarprófanir geta ekki greint á milli allra taugafræðilegra orsaka hreyfiskjálfta.
Veldur koffín nauðsynlegum skjálfta eða gerir það hann bara verri?
Koffín getur aukið lífeðlisfræðilegan skjálfta og magnað nauðsynlegan skjálfta, en það er ekki viðurkennd ein orsök nauðsynlegs skjálfta. Næmið er mismunandi, svo enginn algildur koffínskammtur veldur skjálfta hjá öllum. Dagbók í 7–14 daga þar sem koffínneysla er minnkuð smám saman og máltíðum og svefni haldið stöðugum getur hjálpað til við að greina tengsl. Bati sannar ekki að koffín hafi verið eina skýringin á skjálftanum.
Getur lyf valdið skjálfta jafnvel þótt lyfjagildið sé eðlilegt?
Medication-related tremor can occur even when a measured drug concentration falls within the laboratory's therapeutic interval. Lithium, valproate, beta-2 agonist inhalers, and some antidepressants are examples of medicines that can produce or amplify action tremor. One drug measurement must be interpreted with sample timing, dose changes, interactions, kidney function, and symptoms. Do not stop prescribed medicines abruptly; new coarse tremor with confusion or unsteadiness needs urgent assessment.
0 Hvenær ætti ég að hafa áhyggjur af handskjálfta?
0 Skyndilegur skjálfti í höndum ásamt máttleysi, talörðugleikum, rugli, miklum höfuðverk eða nýtilkomnu alvarlegu jafnvægisleysi krefst bráðamats. Ekki ætti að gera ráð fyrir að einkenni sem þróast á nokkrum mínútum eða klukkustundum séu nauðsynlegur skjálfti. Blóðsykursgildi undir 54 mg/dL krefst einnig tafarlausra viðbragða, og meðvitundarskerðing eða vangeta til að kyngja krefst bráðrar aðstoðar. Viðvarandi en hægfara skjálfti ætti að fá klínískt mat þegar hann hefur áhrif á daglegar athafnir eða breytir um eðli.
Fáðu útskýringar á niðurstöðum blóðrannsókna
Hladdu upp rannsóknarskýrslunni þinni og AI Kantesti útskýrir hvert lífmerki á mannamáli á nokkrum sekúndum. Yfir 2 milljónir manna um allan heim nota þjónustuna.
Heimildir
- Klein, T., Mitchell, S., & Weber, H. (2026). Niðurgangur eftir föstu, svört korn í hægðum og leiðarvísir um meltingarveginn 2026. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Leiðarvísir um heilsu kvenna: egglos, tíðahvörf og hormónaeinkenni. Kantesti AI Medical Research. DOI
- Bhatia KP et al. (2018). Consensus Statement on the classification of tremors. From the task force on tremor of the International Parkinson and Movement Disorder Society. Movement Disorders. DOI
- Morgan JC et al. (2017). Insights into Pathophysiology from Medication-induced Tremor. Tremor and Other Hyperkinetic Movements.
- Zesiewicz TA et al. (2011). Evidence-based guideline update: Treatment of essential tremor: Report of the Quality Standards Subcommittee of the American Academy of Neurology. Taugafræði. DOI PubMed
- 2M+Greindar rannsóknir
- 127+Lönd
- 100+Tungumál
Um læknateymið


E-E-A-T traustmerki
Reynsla
Læknastýrð klínísk yfirferð á vinnuferlum við túlkun rannsóknarniðurstaðna.
Sérþekking
Áhersla á rannsóknarstofulækningar: hvernig lífmarkarar hegða sér í klínísku samhengi.
Yfirvald
Dr. Thomas Klein fór yfir efnið læknisfræðilega, með framlagi frá Dr. Sarah Mitchell og Prof. Dr. Hans Weber.
Traustleiki
Rökstudd túlkun byggð á gögnum með skýrum eftirfylgnileiðum til að draga úr ávörun.





Fyrirvari um læknisfræðilegt efni
Þessi grein er eingöngu til fræðslu og felur ekki í sér læknisráðgjöf. Leitaðu alltaf til hæfs heilbrigðisstarfsmanns vegna ákvarðana um greiningu og meðferð.
Gefið út · Hafðu samband við ritstjórnarteymið
Gefið út af Kantesti Ltd, skráðu í Englandi og Wales, fyrirtækisnúmer. 17090423, London, Bretlandi.
