آزمایش ژنتیکی میتواند زیرگروههای EDS با تعریف مولکولی، از جمله EDS کلاسیک و عروقی را تأیید کند، اما معمولاً نمیتواند EDS هیپرموبایل را تأیید کند. نتیجه منفی پنل و یک واریانت با اهمیت نامشخص به پرسشهای متفاوتی پاسخ میدهند.

نکات کلیدی
- انواع قابلشناسایی: طبقهبندی EDS در سال ۲۰۱۷، ۱۳ زیرگروه را توصیف میکند؛ برای ۱۲ زیرگروه، علل مولکولی تثبیتشدهای وجود دارد که آزمایش ژنتیکی مناسب میتواند بررسیشان کند.
- EDS هیپرموبایل: هیچ آزمایش مولکولیِ پذیرفتهشده و معمولی نمیتواند hEDS را تأیید یا رد کند؛ تشخیص به ارزیابی بالینی نیاز دارد.
- EDS کلاسیک: COL5A1 و COL5A2 ژنهای اصلی هستند؛ برخی واریانتهای COL1A1 میتوانند فنوتیپی همپوشان با نوع کلاسیک ایجاد کنند.
- EDS عروقی: یک واریانت بیماریزا یا احتمالاً بیماریزای COL3A1، در صورت تفسیر همراه با یافتههای بالینی، میتواند vEDS را تأیید کند.
- طبقهبندی واریانت: آزمایشگاههای بالینی از ۵ دسته، از بیماریزا تا خوشخیم، استفاده میکنند؛ یک VUS تشخیص مثبت نیست.
- احتمالاً بیماریزا: چارچوب ACMG/AMP برای این طبقهبندی از قطعیت بیش از ۹۰٪ استفاده میکند، نه پیشبینی ۹۰درصدیِ شدت علائم.
- EDS مغلوب: تأیید معمولاً مستلزم وجود ۲ واریانت بیماریزا است که هر یک نسخهٔ متفاوتی از ژن مربوطه را تحت تأثیر قرار میدهد.
- خطر خانوادگی: در بسیاری از زیرگونههای غالب EDS، احتمال انتقال در هر بارداری ۵۰٪ است؛ خطرهای مغلوب به نتایج هر دو والد بستگی دارند.
آزمایش ژنتیکی کدام انواع EDS را میتواند تأیید کند؟
آزمایش ژنتیکی سندرم اهلرز-دانلوس میتواند زیرگونههایی را که از نظر مولکولی تعریف شدهاند تأیید کند، اما معمولاً EDS هایپرموبیل را تأیید نمیکند. طبقهبندی سال ۲۰۱۷، ۱۳ زیرگونهٔ EDS را مشخص میکند که برای ۱۲ مورد از آنها علل ژنتیکی تثبیتشدهاند؛ تأیید مستلزم واریانتی است که بهدرستی طبقهبندی شده باشد، الگوی وراثتی درست را داشته باشد و با یافتههای بالینی سازگار باشد.

آزمایش ژنتیکی سندرم اهلرز-دانلوس، DNA را بررسی میکند، نه مقدار کلاژنِ در گردش در خون شما را. انواع کلاسیک، عروقی، کیفواسکولیوتیک و چند شکل نادرتر EDS را میتوان به این روش بررسی کرد، اما پنلی شامل ۲۰ یا ۴۰ ژن بهطور خودکار همهٔ انواع واریانتهای مرتبط را پوشش نمیدهد؛ روشهای آزمایشگاه بهاندازهٔ فهرست ژنهای آن اهمیت دارند.
طبقهبندی بینالمللی، الگوهای بالینیِ قابلشناسایی را از علل مولکولی آنها جدا میکند (Malfait و همکاران، ۲۰۱۷). ۱۲ دستهٔ تعریفشده از نظر مولکولی به معنای نرخ تشخیص جهانیِ ۱۰۰٪ نیستند: ممکن است آزمایشگاهی ژنی را حذف کند، ناحیهای را که از نظر فنی بررسی آن دشوار است از دست بدهد، یا تغییری را شناسایی کند که هنوز نمیتوان آن را با اطمینان طبقهبندی کرد؛ توضیح ما دربارهٔ دستههای نتایج ژنتیکی همین تمایز را در یک بیماری ارثی دیگر بررسی میکند.
Kantesti یک تحلیلگر آزمایش خون مبتنی بر هوش مصنوعی است که به توضیح یافتههای معمول آزمایشگاهی کمک میکند، نه جایگزینی برای تشخیص مولکولی EDS. از نظر سازمانی، دامنهٔ بالینی Kantesti Ltd تفسیر آموزشی را از ارزیابی تخصصی متمایز میکند: نه ۱ پنل طبیعی آزمایش خون و نه توضیح تولیدشده با هوش مصنوعی نمیتواند مشخص کند که فردی به اختلال ارثی بافت همبند مبتلا است یا خیر.
کدام ژنها EDS کلاسیک و شبهکلاسیک را تأیید میکنند؟
EDS کلاسیک معمولاً شامل COL5A1 یا COL5A2 است، درحالیکه EDS شبهکلاسیک مرتبط با TNXB معمولاً مستلزم ۲ واریانت بیماریزاست. نامهای مشابه به معنای وراثت، روشهای آزمایشگاهی یا یافتههای بالینی یکسان نیستند؛ واریانتهای منتخب COL1A1 و بیماری مرتبط با AEBP1 نیز تمایزهای بیشتری ایجاد میکنند.
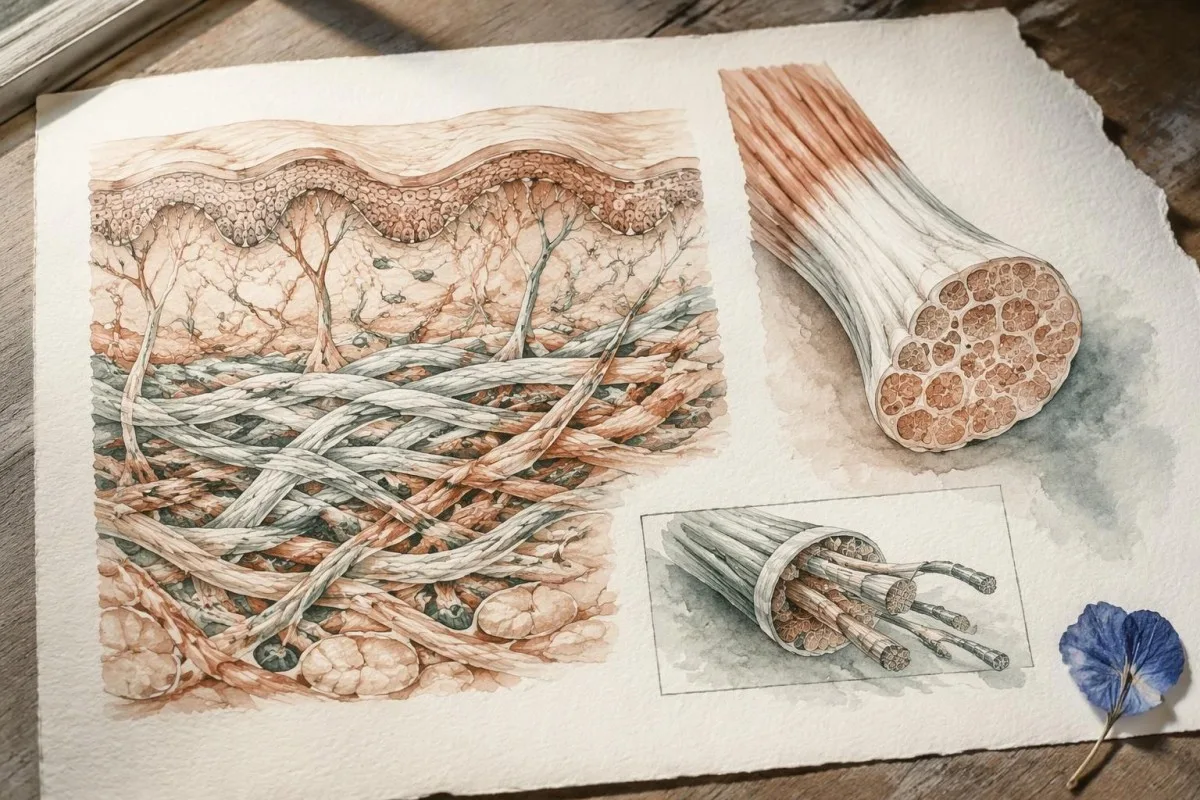
EDS کلاسیک، هایپرموبیلیتی مفاصل را با بیشکشسانی مشخص پوست و اسکارهای آتروفیک همراه میکند، هرچند تظاهر بیماری در میان اعضای خانواده متفاوت است. COL5A1 و COL5A2 اجزای کلاژن نوع V را کدگذاری میکنند و یک واریانت بیماریزا یا احتمالاً بیماریزا در حالت هتروزیگوت میتواند به تأیید کمک کند؛ اما یافتهای دلخواه در COL1A1 نمیتواند، زیرا واریانتهای متفاوت در آن ۱ ژن موجب فنوتیپهای بافت همبندِ اساساً متفاوتی میشوند.
EDS شبهکلاسیک مرتبط با TNXB اغلب موجب بیشکشسانی و کبودی آسان میشود، بیآنکه اسکارهای آتروفیک معمول EDS کلاسیک را ایجاد کند. TNXB در کنار شبهژن بسیار مشابهی به نام TNXA قرار دارد؛ بنابراین، گزارش باید توضیح دهد که آزمون چگونه آنها را از یکدیگر متمایز میکند و حذفها یا بازآراییها را شناسایی میکند؛ برخی تغییرات CYP21A2 مجاور را نیز درگیر میکنند و بهطور بالقوه یافتههای بافت همبند را به یک بیماری غدد درونریزِ جداگانه پیوند میدهند.
EDS شبهکلاسیک مرتبط با AEBP1 که گاهی EDS شبهکلاسیک نوع ۲ نامیده میشود، پس از طبقهبندی سال ۲۰۱۷ مشخص شد و عموماً مغلوب است. به همین دلیل است که باید فهرست واقعی ژنهای پنلی را که ادعا میکند همهٔ انواع EDS را پوشش میدهد بررسی کرد؛ راهنمای ما دربارهٔ خطر خانوادگی اختصاصی هر ژن explains why a condition name alone cannot determine inheritance or the meaning of a negative result.
آیا آزمایش ژنتیکی میتواند EDS عروقی را تأیید کند؟
Vascular EDS is usually confirmed by a pathogenic or likely pathogenic COL3A1 variant. COL3A1 encodes type III collagen, and the combination of molecular evidence with a personal or family history of arterial or organ complications carries more diagnostic weight than a high joint-flexibility score.

Generalized joint hypermobility is not required for vascular EDS, so a Beighton score of 2/9 does not rule it out. Features prompting specialist consideration include arterial dissection or rupture, unexplained bowel perforation, spontaneous pneumothorax, and a compatible family history; isolated bruising or flexibility is much less specific and should not be treated as equivalent evidence.
A confirmed COL3A1 result can change vascular surveillance, procedural planning, pregnancy counseling, and testing for relatives. Different variant mechanisms can influence average patterns of disease, but they do not provide a reliable countdown to an individual's first complication; for a heterozygous dominant variant, the usual transmission probability is 50% per pregnancy, even when an affected parent has relatively few symptoms.
Sudden severe chest, abdominal, back, or head pain, collapse, or new neurological symptoms require emergency assessment—not waiting several weeks for a panel result. Call the local emergency number, such as 999 or 112 where applicable, and report known or suspected vascular EDS; our اورژانسی سکته explain why new speech, vision, balance, or limb changes need immediate action.
کدام زیرگروههای نادرتر EDS علل ژنتیکی تثبیتشدهای دارند؟
The 9 other molecularly defined subtypes in the 2017 classification have distinct gene and inheritance requirements. A broad EDS panel can investigate them, but confirmation depends on variant mechanism—not simply finding any change in a gene associated with connective tissue.

Arthrochalasia EDS involves specific COL1A1 or COL1A2 changes affecting processing around exon 6, rather than every variant in either gene. Dermatosparaxis EDS involves biallelic ADAMTS2 variants, while cardiac-valvular EDS involves biallelic COL1A2 variants with an appropriate loss-of-function mechanism; these 3 diagnoses illustrate why gene name, variant location, and biological effect must be interpreted together.
Kyphoscoliotic EDS can involve 2 disease-causing variants in PLOD1 or FKBP14, with congenital hypotonia and early progressive spinal curvature providing useful clinical clues. Brittle cornea syndrome involves ZNF469 or PRDM5 and warrants careful ophthalmic assessment because corneal thinning changes management; a connective-tissue panel therefore needs to be matched to eye, skeletal, hearing, and muscle findings, not flexibility alone.
Spondylodysplastic EDS involves B4GALT7, B3GALT6, or SLC39A13, whereas musculocontractural EDS involves CHST14 or DSE; both groups usually follow recessive inheritance. Short stature, characteristic skeletal changes, or congenital contractures can direct testing more efficiently than adding dozens of unrelated genes, and 1 pathogenic variant in a recessive gene is ordinarily an incomplete explanation until the second allele is investigated.
Myopathic EDS involves COL12A1 and can follow dominant or recessive inheritance, while periodontal EDS involves heterozygous pathogenic variants in C1R or C1S. Severe early periodontal disease and lack of attached gingiva are particularly informative for the latter; unlike some metabolic conditions described in our enzyme and DNA results, most EDS diagnoses do not have a routine enzyme-screening shortcut.
چرا پنل منفی، EDS هیپرموبایل را رد نمیکند؟
A negative EDS panel does not exclude hypermobile EDS because hEDS lacks a routinely accepted diagnostic molecular test. The result means the laboratory did not identify reportable explanatory variants within its tested genes and methods—not that all inherited connective-tissue causes have been eliminated.

Most clinical EDS panels primarily investigate alternatives to hEDS, such as classical or vascular EDS and overlapping connective-tissue disorders. A hypothetical person with a Beighton score of 7/9, recurrent instability, and qualifying systemic findings could receive a negative 30-gene panel and still meet clinical hEDS criteria; the panel and the examination are answering different questions.
Research into hEDS genetics is active, but a candidate gene association is not the same as a validated test applicable to everyone with the condition. Before paying for a test described as hypermobile EDS genetic testing, ask for 3 things: the gene-disease evidence, the diagnostic validation, and the criteria used to decide whether a result confirms hEDS.
Neither orthostatic symptoms nor fatigue independently establishes hEDS, and neither symptom needs a positive genetic panel to deserve treatment. A person may need a separate standing or tilt-table assessment for suspected POTS; distinguishing 2 coexisting conditions avoids using one diagnosis as an explanation for every symptom or mistaking an association for proof of causation.
وقتی ژنتیک نمیتواند hEDS را تأیید کند، تشخیص آن چگونه انجام میشود؟
Hypermobile EDS is diagnosed through clinical criteria that assess generalized hypermobility, associated features, and exclusion of alternative explanations. Under the established 2017 adult criteria, the Beighton threshold is generally at least 5/9 through age 50 and at least 4/9 above age 50.
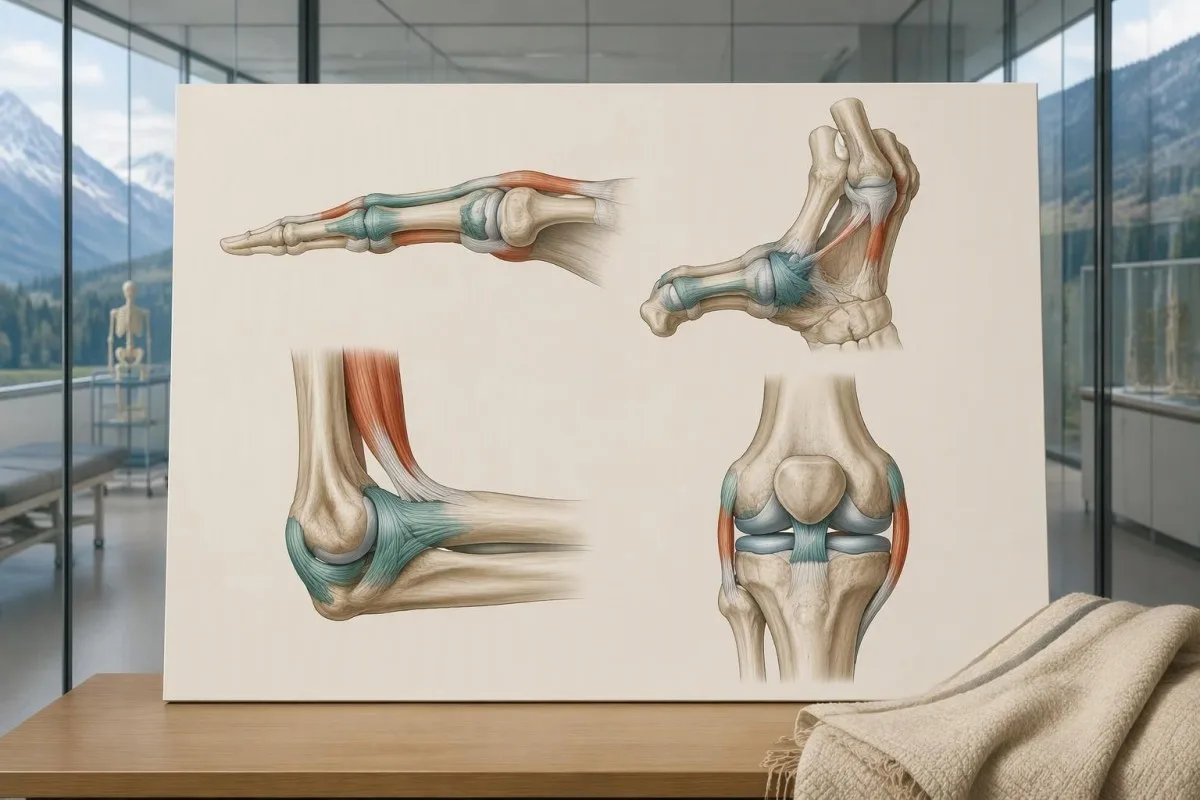
The 2017 criteria require all 3 major criteria, not just a high Beighton score. The second criterion requires at least 2 of 3 feature groups: systemic manifestations, a qualifying first-degree family history, or specified musculoskeletal complications; within the systemic group, at least 5 of 12 listed findings are required, so unrelated symptoms cannot simply be added together to reach a diagnosis.
Age and prior injury can alter measured flexibility, and historical hypermobility becomes relevant when someone is 1 point below the age-specific cutoff. The pediatric framework recommends a Beighton threshold of at least 6/9 for generalized joint hypermobility and reserves hEDS assessment for biological maturity (Tofts et al., 2023); childhood flexibility should not automatically become a lifelong adult diagnostic label.
Alternative explanations include other inherited connective-tissue disorders, neuromuscular conditions, and acquired rheumatologic disease; the exclusions depend on the person's findings rather than a mandatory universal blood-test package. An anti-RNP result, for example, belongs to an autoimmune connective-tissue assessment, not EDS DNA testing; clinicians may also diagnose a hypermobility spectrum disorder when symptoms are significant but all 3 hEDS criteria are not met.
چه کسانی به پنل EDS بهجای آزمایش هدفمند نیاز دارند؟
An EDS panel is most useful when clinical findings suggest a molecularly defined subtype or several overlapping inherited disorders. When a family already has 1 known pathogenic variant, targeted testing for that exact variant is usually more informative than starting with a new broad panel.

Marked skin fragility, characteristic scars, congenital hip dislocation, progressive early scoliosis, unusual corneal findings, or arterial complications can justify clinical genetics assessment. A genetics service may select a broader heritable connective-tissue or aortopathy panel rather than an EDS-only panel when 2 or more diagnostic possibilities overlap; the aim is to investigate the phenotype, not to maximize the number of genes purchased.
Testing the most clearly affected relative first often makes later family testing easier to interpret. A negative targeted result for a known familial variant is fundamentally different from an unexplained negative panel in the first person tested; this distinction also appears in our explanation of informative negative genetic results, although the condition-specific screening recommendations are different.
Routine panel testing is not always helpful for isolated hypermobility without features of a molecularly defined disorder, because additional genes can generate additional VUS findings without clarifying the diagnosis. Some laboratories need specialized methods for particular variant classes, as illustrated by repeat-expansion testing methods; before ordering 1 panel, ask which plausible diagnoses its technical design can actually address.
پنل EDS ممکن است از نظر فنی چه چیزی را از دست بدهد؟
An EDS panel can miss variants outside its coverage, certain deletions or rearrangements, and low-level mosaicism. Sequencing and deletion/duplication analysis are complementary methods, so a report stating that 99% of covered bases were read does not mean 99% of every possible EDS cause was excluded.

Small sequence changes are not the same as changes in gene copy number. Ask whether the assay includes deletion/duplication analysis, how poorly covered regions are completed, and whether complex loci such as TNXB receive validated additional testing; our copy-number interpretation guide shows why a reassuring number of copies can still leave unresolved questions in a different genetic setting.
Exome sequencing focuses mainly on protein-coding regions, while genome sequencing examines a broader DNA space; neither approach guarantees an explanation after 1 negative panel. Deep intronic variants, complex structural changes, mosaicism, and uncertain gene-disease relationships may require specialist analysis, and selected cases may benefit from RNA studies that investigate whether a suspected variant changes how a gene transcript is processed.
Kantesti is an AI blood test interpretation platform whose routine laboratory explanations do not validate an EDS panel's sequencing sensitivity. Our استانداردهای فنی و بالینی ما should not be interpreted as 100% accuracy for germline diagnosis; the molecular laboratory must provide its own assay validation, limitations, accredited reporting process, and variant-specific interpretation.
واریانتهای بیماریزا چه تفاوتی با VUS دارند؟
A pathogenic or likely pathogenic variant has enough evidence to support disease causation; a variant of uncertain significance does not. The ACMG/AMP framework uses 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign, and benign, with classification based on evidence rather than how unusual a DNA change looks.

Evidence can include population frequency, observations in affected families, segregation, well-validated functional studies, and the expected disease mechanism. A variant present in 1 person with hypermobility is not automatically causal, especially when that feature is common; Richards et al. (2015) specifically state that a VUS should not be used in clinical decision-making, preventing uncertain evidence from becoming a definitive diagnosis.
The ACMG/AMP definition of likely pathogenic corresponds to greater than 90% certainty that a variant is disease-causing. That percentage describes confidence in classification—not a 90% chance of arterial rupture, severe disability, or transmission—and even an established pathogenic variant must fit the gene, inheritance pattern, and clinical question before it can explain an individual's presentation.
A pathogenic classification also does not make every carrier's prognosis identical: penetrance and severity can vary with the gene, variant mechanism, and family context. Our explanation of variant effects and family risk illustrates this separation in another inherited disorder; for EDS, request the exact DNA and protein notation, laboratory classification, and report date rather than relying on a shortened portal label.
با یک واریانت EDS با اهمیت نامشخص چه باید کرد؟
An EDS VUS should trigger clarification, not an automatic EDS diagnosis or gene-specific treatment. The next steps are to review phenotype fit, check inheritance and assay limitations, and ask whether carefully selected family testing could provide evidence; testing 10 relatives without a clear question may add little.

Consider a clearly hypothetical adult whose panel finds 1 COL3A1 VUS and no pathogenic variants. The person does not have genetically confirmed vascular EDS on that basis, but a history of arterial dissection would still justify specialist evaluation; management follows the real clinical risk while the molecular uncertainty is investigated, rather than either ignoring the history or treating the VUS as proof.
For a recessive subtype, 2 variants must usually affect opposite gene copies, called being in trans, to explain the disorder. If both changes sit on the same copy, called being in cis, the other copy may remain functional; our discussion of recessive carrier result interpretation explains why parental testing can sometimes answer a specific phasing question rather than simply produce more results.
A VUS may later become benign, likely benign, likely pathogenic, or pathogenic as evidence changes, but there is no universal 6- or 12-month reclassification deadline. Ask who initiates reinterpretation, whether the laboratory contacts the ordering clinician, and how to update family findings; a new clinical event or informative relative's result can be more useful than repeatedly ordering the same unchanged panel.
نتایج مثبت و منفی پنل EDS چه معنایی دارند؟
A positive EDS panel result can confirm a subtype only when classification, inheritance, and phenotype align. A negative result can lower the likelihood of adequately tested molecular diagnoses, but it neither confirms hEDS nor excludes it; 1 result must be interpreted against the reason testing was ordered.
A hypothetical heterozygous pathogenic COL5A1 finding in someone with characteristic scars and hyperextensible skin can support classical EDS. By contrast, 1 pathogenic ADAMTS2 variant in a person without a second explanatory allele usually indicates carrier status rather than confirmed dermatosparaxis EDS; a report can therefore contain a genuine pathogenic finding without that finding explaining the person's symptoms.
The meaning of a negative result changes with pretest probability. When the examination strongly suggests a rare molecular subtype, the next question is whether the assay covered the relevant gene and variant mechanisms; when findings are nonspecific, expanding from 30 to 300 genes may increase uncertain or incidental findings without making the answer more useful or making hEDS genetically testable.
Clinical genetics may recommend a targeted technical follow-up, a different diagnostic hypothesis, or later reanalysis rather than immediately repeating the same panel. The relationship between phenotype and molecular findings also matters in gene and biochemical confirmation, though EDS does not share that condition's biochemical tests; ask for a written explanation of what remains plausible after 1 negative result.
نتایج EDS چه تأثیری بر کودکان و دیگر بستگان دارند؟
Family testing should follow the confirmed gene and inheritance pattern, not the broad EDS label. For many dominant subtypes, a heterozygous affected parent has a 50% transmission probability per pregnancy; when both parents carry a pathogenic variant for the same recessive subtype, the affected-child probability is usually 25%.

The standard recessive model gives a 25% chance of an affected child, a 50% chance of a carrier child, and a 25% chance of a child inheriting neither familial variant when both parents are carriers. Each pregnancy is a new event, not a running quota; partner testing must investigate the relevant gene sufficiently rather than checking only the variant carried by the first parent.
A negative family history does not exclude dominant EDS because a variant may arise de novo, relatives may have subtle findings, or family information may be incomplete. Testing children can be appropriate when a confirmed condition changes childhood care, particularly vascular EDS; this differs from some adult-onset predictive testing decisions, where timing and the child's future autonomy carry a different balance.
Hypermobile EDS can cluster in families, but no routine molecular result currently provides the same variant-specific cascade-testing pathway. Relatives should consent separately to testing and data sharing, and a family's 3 generations of history should distinguish documented diagnoses from suspected flexibility; our family consent and tracking guide explains why shared health information does not remove individual privacy or the need for personal assessment.
آیا آزمایشهای خون معمول یا تفسیر هوش مصنوعی میتوانند EDS را تشخیص دهند؟
Routine blood tests and AI blood-test interpretation cannot diagnose EDS or classify a germline variant independently. A CBC, ferritin, thyroid panel, or coagulation screen may investigate symptoms and alternative explanations, but there is no routine collagen blood concentration with a diagnostic cutoff for the 13 EDS subtypes.

Kantesti is an AI-powered blood test analysis tool that can explain routine biomarker results alongside reported symptoms. For example, a hypothetical adult with ferritin of 9 ng/mL and hemoglobin of 13.0 g/dL may have depleted iron stores despite hemoglobin within their laboratory's reference interval; our guide to کمبود آهن پیش از کمخونی explains why that finding deserves attention without becoming evidence for or against EDS.
Normal platelet counts, PT, and aPTT do not exclude connective-tissue fragility, and bruising can have more than 1 cause. Conversely, iron deficiency, thyroid dysfunction, or a bleeding disorder should not be dismissed simply because someone already has hEDS; our complete iron study interpretation addresses a treatable contributor to fatigue, not an inherited collagen diagnosis or a supplement-based cure.
An EDS genetic report contains sensitive information about both the individual and potentially their relatives, so it should not be treated as an ordinary screenshot for unrestricted sharing. Before sending even 1 report to an online service, check purpose, retention, deletion, and whether genetic-report analysis is supported; Kantesti AI's privacy information describes our data-handling approach, not authorization to replace a genetic counselor or molecular laboratory.
چه چیزهایی باید برای مشاوره ژنتیک همراه بیاورید و کدام منابع مفید هستند؟
Bring the complete genetic report, relevant medical records, and a structured family history to your genetics appointment. The 3 most useful questions are whether the result explains your phenotype, what the assay could have missed, and whether the finding changes your own or your relatives' care.
Record major complications with ages, documented diagnoses, and the exact relationship of affected relatives; a 3-generation pedigree can be more informative than an unverified statement that everyone is flexible. Include ophthalmology findings, relevant imaging, characteristic scarring, congenital orthopedic problems, and the full laboratory methods page, because a portal summary may omit gene coverage, deletion testing, or the distinction between a VUS and a pathogenic result.
Before leaving, ask who coordinates 1 next step and who will receive any amended report: the genetics service, the ordering clinician, or the molecular laboratory. Kantesti's استانداردهای محتوای پزشکی support clear separation of established evidence, hypothetical examples, and unresolved questions; this article's EDS recommendations draw on the international classification, ACMG/AMP interpretation guidance, and pediatric hypermobility framework cited below.
The 2 Zenodo publications listed in our research references cover urinalysis and iron studies, not EDS genetic-test validation. Our راهنمای تفسیر آزمایش ادرار may help explain a separate urine report, but neither urine urobilinogen nor iron-binding capacity confirms an EDS subtype; these publications should not be read as evidence that our platform performs molecular EDS diagnosis.
سوالات متداول
آیا آزمایش ژنتیک میتواند سندرم اهلرز-دانلوس را تشخیص دهد؟
A genetic test can confirm molecularly defined Ehlers-Danlos subtypes when it identifies an appropriately classified variant with the correct inheritance pattern and compatible clinical findings. The 2017 classification includes 13 subtypes, and 12 have established molecular causes that appropriate testing can investigate. Hypermobile EDS does not have a routinely accepted diagnostic molecular test. A panel's gene list, technical coverage, and variant interpretation determine what its result can establish.
آیا منفی بودن پنل EDS، سندرم اهلرز-دانلوس هایپرموبایل را رد میکند؟
A negative EDS panel does not rule out hypermobile EDS because hEDS is diagnosed clinically rather than by a validated routine molecular test. A hypothetical negative 30-gene panel means no explanatory reportable variant was found within that assay's scope. The result can help evaluate other inherited disorders, but it cannot prove or disprove hEDS. The next step is a clinical assessment that considers hypermobility, associated features, and alternative diagnoses.
آیا واریانت COL3A1 به این معنی است که من سندرم اهلرز-دانلوس عروقی دارم؟
واریانت COL3A1 تنها زمانی تأییدکنندهٔ EDS عروقی است که بیماریزا یا احتمالاً بیماریزا باشد و با یافتههای بالینی تفسیر شود. آزمایشگاههای بالینی از ۵ ردهٔ واریانت استفاده میکنند و واریانت با اهمیت نامشخص در COL3A1 به معنای تشخیص قطعی EDS عروقی نیست. عوارض شدید و بیتوضیح شریانی یا اندامی، حتی در صورت نامشخص بودن نتایج آزمایش، همچنان نیازمند ارزیابی متخصص هستند. درد شدید و ناگهانی، از حال رفتن یا علائم عصبی مستلزم دریافت مراقبت اورژانسی است و نباید تا زمان بازطبقهبندی واریانت منتظر ماند.
VUS در پنل ژنتیکی EDS به چه معناست؟
یک واریانت با اهمیت نامشخص یعنی شواهد موجود برای تعیین قطعی اینکه آیا آن تغییر DNA باعث بیماری میشود، کافی نیست. چارچوب ACMG/AMP، واریانتهای با اهمیت نامشخص را از واریانتهای احتمالاً بیماریزا متمایز میکند؛ این دسته نشاندهندهٔ اطمینان بیش از ۹۰٪ به نقش واریانت در ایجاد بیماری است. یک واریانت با اهمیت نامشخص نباید بهتنهایی مبنای تشخیص EDS، آزمایش پیشبینانه یا درمان اختصاصی ژن باشد. متخصص ژنتیک بالینی ممکن است بررسیهای هدفمند خانوادگی یا تفسیر مجدد در آینده را توصیه کند و در این فاصله، علائم و خطرها را بر اساس ملاحظات بالینی خودشان مدیریت کند.
چرا دو واریانت در یک ژن مرتبط با سندرم اهلرز-دانلوس یافت شدند؟
دو واریانت ممکن است اهمیت داشته باشند، زیرا چندین زیرگروه EDS از الگوی وراثت مغلوب پیروی میکنند و معمولاً وجود تغییرات بیماریزا در هر دو نسخهٔ ژن لازم است. آزمایشگاه باید مشخص کند که آیا هر دو تغییر بیماریزا یا احتمالاً بیماریزا هستند و آیا در ترانس قرار دارند، یعنی نسخههای مقابل را تحتتأثیر قرار میدهند. دو تغییر در سیس، یعنی تغییراتی که یک نسخهٔ واحد را تحتتأثیر قرار میدهند، ممکن است یک اختلال مغلوب را توضیح ندهند. یافتن یک واریانت بیماریزا و یک VUS نیز بهطور خودکار تأیید مولکولی را فراهم نمیکند.
اگر من به سندرم اهلرز-دانلوس مبتلا هستم، آیا باید فرزندانم آزمایش شوند؟
Children's testing depends on the confirmed subtype, whether a familial variant is known, and whether the result changes care during childhood. Many dominant EDS subtypes have a 50% transmission probability per pregnancy, making targeted testing useful when appropriate. When both parents carry variants for the same recessive subtype, the usual affected-child probability is 25% per pregnancy. Hypermobile EDS currently requires clinical evaluation rather than routine variant-specific family testing.
آیا آزمایشهای خون معمول میتوانند سندرم اهلرز-دانلوس را رد کنند؟
Normal routine blood tests cannot exclude Ehlers-Danlos syndrome because standard panels do not measure the inherited structural changes responsible for EDS. A normal CBC, PT, or aPTT does not rule out connective-tissue fragility, and no routine collagen blood cutoff diagnoses the 13 classified subtypes. Blood tests can identify separate contributors to symptoms, such as iron deficiency or thyroid dysfunction. Molecularly defined EDS requires appropriate genetic interpretation, while hypermobile EDS requires clinical assessment.
چگونه نتایج آزمایش خون را بخوانیم
گزارش آزمایشگاهی خود را بارگذاری کنید تا هوش مصنوعی Kantesti ظرف چند ثانیه هر زیستنشانگر را به زبان ساده توضیح دهد. بیش از 2 میلیون نفر در سراسر جهان از آن استفاده کردهاند.
منابع
- Klein, T., Mitchell, S., & Weber, H. (2026). اوروبیلینوژن در ادرار: راهنمای کامل تجزیه و تحلیل ادرار ۲۰۲۶. پژوهش پزشکی هوش مصنوعی Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). راهنمای بررسی آهن: TIBC، اشباع آهن و ظرفیت اتصال. پژوهش پزشکی هوش مصنوعی Kantesti. DOI
- Malfait F et al. (2017). The 2017 international classification of the Ehlers-Danlos syndromes. American Journal of Medical Genetics Part C: Seminars in Medical Genetics. DOI
- ریچاردز و همکاران (2015). استانداردها و دستورالعملهای تفسیر واریانتهای توالی: توصیه اجماعی مشترک کالج آمریکایی ژنتیک پزشکی و ژنومیک و انجمن آسیبشناسی مولکولی. ژنتیک در پزشکی. DOI پابمد
- Tofts LJ et al. (2023). Pediatric joint hypermobility: a diagnostic framework and narrative review. مجله بیماریهای نادر یتیم. DOI
- ۲ میلیون+آزمایشهای تجزیهوتحلیلشده
- 127+کشورها
- 100+زبانها
درباره تیم پزشکی


سیگنالهای اعتماد E-E-A-T
تجربه
بازبینی بالینی مبتنی بر نظر پزشک از فرایندهای تفسیر آزمایشگاه.
تخصص
تمرکز بر پزشکی آزمایشگاهی و اینکه نشانگرهای زیستی در زمینه بالینی چگونه رفتار میکنند.
اقتدارگرایی
با بازبینی پزشکی دکتر توماس کلاین، با مشارکت دکتر سارا میچل و پروفسور دکتر هانس وبر.
قابل اعتماد بودن
تفسیر مبتنی بر شواهد با مسیرهای پیگیری روشن برای کاهش هشدارها.






سلب مسئولیت پزشکی
این مقاله فقط برای اهداف آموزشی است و توصیه پزشکی محسوب نمیشود. برای تصمیمهای مربوط به تشخیص و درمان، همیشه با یک ارائهدهنده مراقبتهای بهداشتی واجد شرایط مشورت کنید.
منتشر شد · با تیم تحریریه تماس بگیرید
منتشرشده توسط Kantesti Ltd، ثبتشده در انگلستان و ولز، شماره شرکت. 17090423, ، لندن، بریتانیا.
