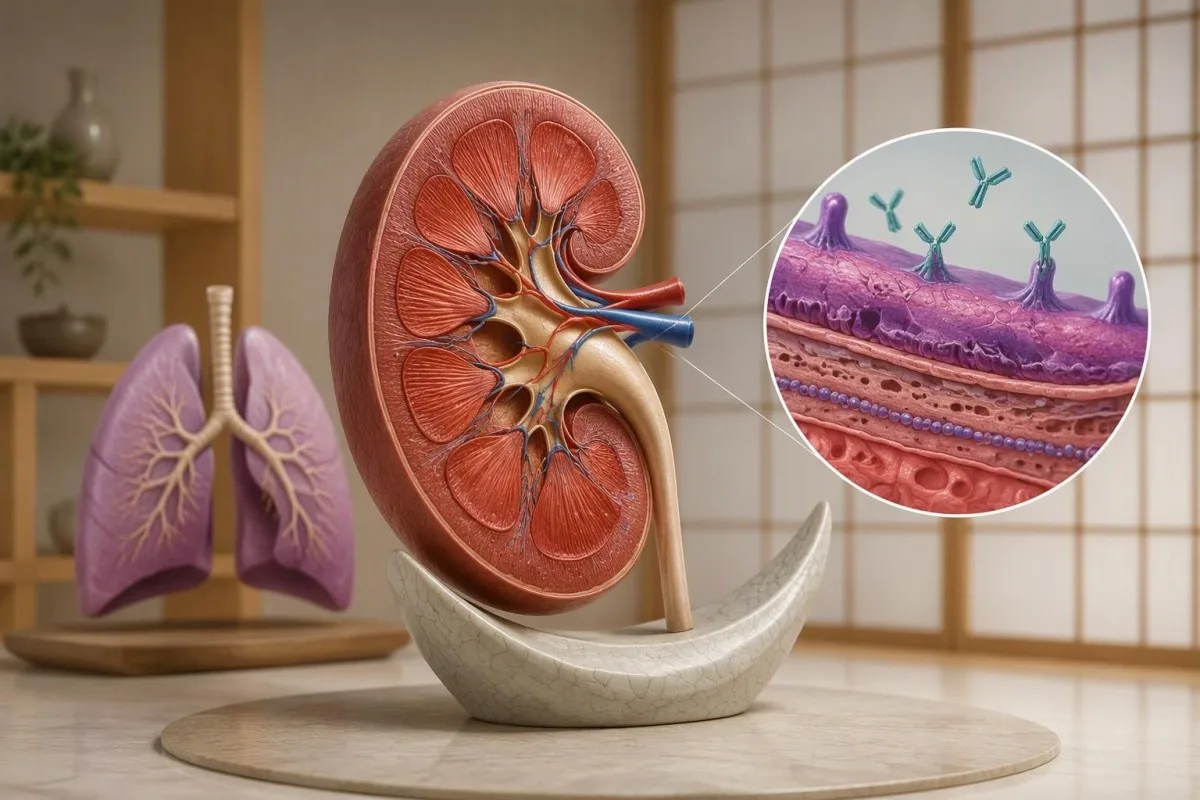
ይህ የፀረ-ሰው ውጤት ጊዜ-ነክ የኩላሊት መታወክን ሊያመለክት ይችላል—መተንፈስ የተለመደ በሚመስልበት ጊዜም ጭምር። ምርመራው በቤተ ሙከራ ዘዴ፣ በሽንት ምርመራ ውጤቶች፣ በኩላሊት ተግባር እና አንዳንዴም በቲሹ ምርመራ ላይ የተመሰረተ ነው።.


- አዎንታዊ የፀረ-GBM ፀረ-ሰው (antibodies) ሊከሰት የሚችለውን የፀረ-GBM በሽታን ይደግፋሉ ነገር ግን ምርመራውን ከአንድ የላቦራቶሪ ውጤት ብቻ ማረጋገጥ አይችሉም።.
- በኩላሊት ብቻ የሚከሰት በሽታ ይቻላል፦ የሳንባ ተሳትፎ በግምት 40–60% በተዘገቡ ክላሲክ ጉዳዮች ላይ ይከሰታል፣ ሁሉም ሰው አይደለም።.
- አጣዳፊ የኩላሊት ጉዳት ቢያንስ 0.3 mg/dL ወይም 26.5 µmol/L የ creatinine ጭማሪ በ48 ሰአት ውስጥ ያካትታል፤ ይህ ገደብ ለፀረ-GBM በሽታ የተለየ አይደለም።.
- የአስቸኳይ ምልክቶች ደም በማስነጠስ፣ አዲስ የትንፋሽ እጥረት፣ ወይም በከፍተኛ ሁኔታ የቀነሰ የሽንት ምርት ያካትታሉ፤ ለተደጋጋሚ የፀረ-ሰው (antibody) ምርመራ ከመጠበቅ ይልቅ የድንገተኛ እንክብካቤ ይጠይቁ።.
- የሽንት ማይክሮስኮፒ ከኩላሊት ማጣሪያዎች ደም መፍሰስን የሚደግፉ ቀይ የደም ሴል ካስት (red-cell casts) ሊለዩ ይችላሉ፣ ከወትሮው የፊኛ ኢንፌክሽን ይልቅ።.
- የአንቲቦዲ ገደቦች በመጠባበቂያ ክልል ውስጥ በዚያ ላቦራቶሪ ጎን ለጎን ትርጉም አለው 21 U/mL ውጤት:.
- ድርብ-አዎንታዊ በሽታ ፀረ-GBM ፀረዴዎች እና ANCA አንድ ላይ እንደሚከሰቱ ያመለክታል; የድጋሚ ክትትል እና የረጅም ጊዜ ህክምና ሊለውጥ ይችላል።.
- చికితል ጊዜ ጉዳዮች፡- ስፔሻሊስቶች ፈጣን እድገት ያለበትን በሽታ በጠንካራ ሁኔታ የሚጠቁም የክሊኒካዊ ሥዕል ከመረጋገጡ በፊት ሕክምና ሊጀምሩ ይችላሉ።.
- ንቅለ ተከላ ጊዜ በ KDIGO 2021 መሠረት ፀረ-GBM ፀረዴዎች ቢያንስ ለ 6 ወራት የማይታዩ መሆንን በአጠቃላይ ይፈልጋል።.
አዎንታዊ የፀረ-GBM ፀረ-ሰው (antibodies) ውጤቶች ምን ማለት ናቸው?
አዎንታዊ የፀረ-GBM ፀረ-ሰው (antibodies) ፀረ-ግሎሜሩላር ቤዝመንት ሽፋን በሽታን ሊያመለክት ይችላል, ይህም የኩላሊት ማጣሪያዎችን እና አንዳንድ ጊዜ ሳንባዎችን በፍጥነት ሊጎዳ የሚችል ራስን በራስ የመከላከል ሁኔታ ነው። እነሱ ራሳቸው የ Goodpasture syndrome ን አያረጋግጡም። ዛሬ ወደሚጠይቀው ሐኪም ያነጋግሩ; ደም ማሳል፣ አዲስ የትንፋሽ እጥረት፣ ወይም በከፍተኛ ሁኔታ የተቀነሰ ሽንት አስቸኳይ ግምገማ ይፈልጋል።.
Anti-GBM የፀረዴውን ኢላማ እንጂ ሙሉ ምርመራን አያመለክትም: የግሎሜሩላር ቤዝመንት ሽፋን የኩላሊት ማጣሪያ መሠረተ ልማት አካል ነው። አብዛኛው ክላሲክ በሽታ በካልሲየም IV ኮላጅን አልፋ-3 ሰንሰለት የነርቭ-ካልሲየም ክፍል ላይ ፀረዴዎችን ያጠቃልላል, ይህም በሳንባ አየር ከረጢቶች ውስጥም የሚገኝ መዋቅር ነው; ስለዚህ ተመሳሳይ የበሽታ መከላከያ ምላሽ 2 የተለያዩ ምልክቶችን ባላቸው 2 አካላት ላይ ተጽዕኖ ሊያሳድር ይችላል።.
እኔ Kantesti ዋና የሕክምና መኮንን የሆንኩት ቶማስ ክላይን ነኝ። የመጀመሪያ ጥያቄዬ የላቦራቶሪ ባንዲራ ምን ያህል አስደንጋጭ እንደሚመስል ሳይሆን ይህ ውጤት ከርቀት የአካል ጉዳት ማስረጃ ጋር አብሮ ይመጣል ወይ የሚል ነው። የ creatinine መረጋጋት ያለው አንድ ቀላል አዎንታዊ ውጤት, ከ creatinine ጭማሪ ጋር በ 48 ሰአታት ውስጥ ከማንኛውም ምቾት ማረጋገጫ ይልቅ በክሊኒሻኖች ክትትል የሚያስፈልገው ሁኔታ ነው.
ካንቴስቲ እ.ኤ.አ. AI የደም ምርመራ ተንታኝ creatinine, ኤሌክትሮላይቶች, እና የላቦራቶሪ ማጣቀሻ ክልሎችን በማንበብ ፀረ-GBM ውጤቶችን ለማብራራት ሊረዳ ይችላል, ነገር ግን ራስን የመከላከል የኩላሊት በሽታን ማረጋገጥ አይችልም. የእኛ ድርጅት እና ዓላማ የትምህርት ሚናውን ያብራራል; የእኛ መመሪያ አዎንታዊ ፀረ-ሰው አካል ውጤቶች 1 አዎንታዊ የበሽታ መከላከያ ጠቋሚ ለምን የምርመራ ውጤት አለመሆኑን ያብራራል.
የፀረ-GBM በሽታ ከ Goodpasture syndrome ጋር አንድ ነውን?
Anti-GBM በሽታ በኩላሊት-ብቻ በሽታ, በሳንባ-ብቻ በሽታ, እና ሁለቱንም አካላት የሚነካ በሽታን ያጠቃልላል. Goodpasture syndrome ብዙ ጊዜ ግሎሜሩሎኔፊራይተስ እና የሳንባ ደም መፍሰስ ጥምረት ተብሎ ይጠራል, ምንም እንኳን ዶክተሮች ስሙን በተቃርኖ ቢጠቀሙበትም. የ clasiic ፀረ-GBM ጉዳዮች ወደ 40-60% የሚሆኑት የሳንባ ተሳትፎ ስላላቸው, የቃላት አጠራር የኩላሊት ግምገማ አስቸኳይ እንደሆነ በጭራሽ መወሰን የለበትም.
ስሙ Goodpasture syndrome የ pulmonary-renal presentation ን ለማሳየት እንጂ መንስኤውን ለማረጋገጥ አይችልም። ANCA- ጋር ተያይዞ የሚመጣ ቫስኩላይተስ እና ሌሎች በሽታዎች እንዲሁ የኩላሊት እብጠት እና የአልቪዮላር ደም መፍሰስ ሊያስከትሉ ስለሚችሉ, የ Goodpasture syndrome ምርመራ etiological clarification ን ይፈልጋል; McAdoo እና Pusey's 2017 ግምገማ የ cliniical syndrome ን ከፀረዴ-የተመራ anti-GBM በሽታ ይለያል.
Anti-GBM በሽታ አልፎ አልፎ የሚከሰት ነው።, በcommonly cited ህዝቦች ውስጥ በየዓመቱ ወደ 1 ሚሊዮን ሰዎች አንድ ጉዳይ ገደማ ግምት ውስጥ ይገባል, ምንም እንኳን ግምቶች በቦታ እና በጉዳይ ፍለጋ ይለያያሉ. ያ አልፎ አልፎ መተርጎም አስፈላጊ ነው; እንዲያውም አንድ ጥሩ ምርመራ ከበሽታው ጋር ምንም ዓይነት ክሊኒካዊ ማስረጃ በሌላቸው ሰዎች ላይ ጥቅም ላይ ሲውል አሳሳች አወንታዊ ውጤቶችን ሊፈጥር ይችላል።.
በዚህ ሕመም ወቅት ዝቅተኛ eGFR ሊያንጸባርቅ ይችላል አጣዳፊ የኩላሊት ጉዳት, እንጂ የተመሠረተ የከባድ ደረጃ አይደለም. ሥር የሰደደ የኩላሊት በሽታ በአጠቃላይ ቢያንስ ለ 3 ወራት የሚቆዩ ያልተለመዱ ነገሮችን ይፈልጋል; የእኛ መመሪያ የኩላሊት ደረጃ ያንን ልዩነት ያብራራል ፣ ግን በፍጥነት እየተለወጠ ውጤት የረጅም ጊዜ የ CKD መለያ ስር ከመመዝገብ ይልቅ ፈጣን ግምገማ ይፈልጋል።.
የኩላሊት ጉዳት ያለ የሳንባ ምልክቶች ለምን ሊከሰት ይችላል?
የኩላሊት ብቻ ፀረ-ጂቢኤም በሽታ የሚከሰተው የፀረ-ሰው መዳረሻ እና የቲሹ ተጋላጭነት በኩላሊት ማጣሪያዎች እና በሳንባ የአየር ከረጢቶች መካከል ስለሚለያይ ነው። መደበኛ የመተንፈስ ስርዓት ኩላሊትን አይከላከልም ወይም ይህንን ምርመራ አያካትትም። ከሁሉም የጥንታዊ ጉዳዮች 40–60% ያህሉ ብቻ ሳንባዎችን ስለሚያካትቱ ፣ ሳል መጠበቅ ህክምናን ሊያዘገይ ይችላል።.
የግሎሜሩላር ማጣሪያ መሰናክል የማጣሪያ ግፊት በሚኖርበት ጊዜ ለደም ፕላዝማ በቋሚነት ይጋለጣል ፣ የሳንባ አልቪዮላር-ካፒላሪ መሰናክል የተለያዩ መዋቅራዊ ጥበቃዎችን ያደርጋል። የፀረ-ሰው መያያዝም ተዛማጅ የ collagen epitopes ተደራሽ ከሆኑ ይወሰናል ፤ ይህ በቀላሉ ፀረ-አካላት ወደ 1 አካል የሚዘዋወሩበት ሁኔታ አይደለም ነገር ግን ለሌላው መድረስ አይችሉም።.
ማጨስ እና የሃይድሮካርቦን ተጋላጭነት ከፀረ-ጂቢኤም በሽታ የሳንባ ተሳትፎ ጋር የተዛመዱ ናቸው ፣ እና የመተንፈሻ አካላት በሽታ የሳንባ መሰናክሉን ተጋላጭነት ሊጎዳ ይችላል። እነዚያ ማህበራት ትክክለኛውን የግል ስጋት ስሌት አይፈቅዱም ፦ አጫሽ ያልሆነ ሰው የሳንባ ተሳትፎ ሊያገኝ ይችላል ፣ አጫሽ ደግሞ የኩላሊት ብቻ በሽታ ሊኖረው ይችላል ፣ ስለዚህ 0 የመተንፈሻ አካላት ምልክቶች ደንብ-አልባ ምርመራ ሆነው መቅረብ የለባቸውም።.
የ creatinine ከ 0.9 ወደ 1.8 mg/dL በጥቂት ቀናት ውስጥ መጨመር ፣ ማይክሮስኮፕ ሽንት ደም ፣ እና ምንም ሳል የሌለበትን ታካሚ ያስቡ። ያ ጥምረት አስቸኳይ የኩላሊት ህክምና ግምገማ ይፈልጋል ምክንያቱም ማጣሪያ በእጅጉ ተቀይሯል ፤ የእኛ ዝቅተኛ eGFR ማስጠንቀቂያ ምልክቶች ደግሞ ጉልህ የሆነ የኩላሊት እክል መጀመሪያ ላይ የሚያስገርም ጸጥታ ሊሰማው የሚችለውን ያብራራሉ።.
የፀረ-GBM ፀረ-ሰው (antibody) የሙከራ ቁጥር እንዴት መነበብ አለበት?
የ የፀረ-ጂቢኤም ፀረ-ሰው ምርመራ ሪፖርት በሚያደርገው ላቦራቶሪ ዘዴ ፣ አሃዶች እና ገደብ በመጠቀም መተርጎም አለበት። ከእያንዳንዱ ምርመራ ሊተላለፍ የሚችል ሁለንተናዊ አዎንታዊ ትኩረት የለም። ለምሳሌ ፣ 21 U/mL ከ 20 U/mL የገደብ በላይ ትንሽ ነው - ግን ያ ምሳሌ የሚመከር የምርመራ ገደብ አይደለም።.
Immunoassays የተለያዩ የአንቲጂን ዝግጅቶች እና የመለኪያ ስርዓቶች ሊጠቀሙ ይችላሉ ፣ ውጤቶቹ እንደ U/mL ፣ IU/mL ፣ መረጃ ጠቋሚ ፣ ወይም ጥራት ያለው አዎንታዊ ሪፖርት ይደረጋሉ። ከሌላ ላቦራቶሪ 30 U/mL ጋር በነጻነት ሊነፃፀር የማይችል የመረጃ ጠቋሚ ምርመራ 30 ውጤት ፤ ልዩነቱ የጥራት እና የቁጥር ምርመራዎች እዚህ ጠቃሚ ነው።.
የሽንት ግኝቶች እና የኩላሊት ተግባር መደበኛ ሲሆኑ ዝቅተኛ ደረጃ አዎንታዊነት የበለጠ ምርመራ ይገባዋል ፣ ነገር ግን ከፍተኛ ትኩረት በራሱ የማይቀለበስ ጉዳትን ሊለካ አይችልም። አዝማሚያውን ከመተርጎምዎ በፊት 3 ዝርዝሮችን እመረምራለሁ ፦ ተመሳሳይ ምርመራ ጥቅም ላይ ውሏል እንደሆነ ፣ ህክምና መጀመሩ እንደሆነ ፣ እና ላቦራቶሪው ለውጡን ትንታኔያዊ ትርጉም ያለው እንደሆነ ይገልጸው እንደሆነ።.
Kantesti AI የላቦራቶሪ ውጤት የተሳሳተ ትርጉም ማስተካከል አይችልም ፣ ስለዚህ የመጀመሪያውን ሪፖርት በመቃኘት እሴቱን ፣ አሃዶችን ፣ የማጣቀሻውን ክፍተት እና የመሰብሰቢያውን ቀን ያረጋግጡ። የእኛ የፒዲኤፍ ቅጂ ቼክ ዝርዝር እነዚያን ምርመራዎች ይሸፍናል ፤ የጠፋው አስርዮሽ 2.1 ወደ 21 ሊለውጥ እና የፀረ-ሰው መለኪያ ጠቀሜታ ሊለውጥ ይችላል።.
የፀረ-GBM አዎንታዊ ውጤት ሐሰት ወይም አሳሳች ሊሆን ይችላል?
የውሸት አዎንታዊ ወይም ክሊኒካዊ በሆነ መንገድ አሳሳች የፀረ-GBM ውጤት ይቻላል, በተለይ አዎንታዊነት ደካማ በሆነበት እና የክሊኒካዊው ገጽታ የማይመጥንበት ጊዜ። ሐኪም በሌላ ዘዴ ማረጋገጫ እንዲሰጥ ሊጠይቅ ይችላል። ሆኖም ግን፣ ክሬቲኒን እየጨመረ ከሆነ፣ ሽንት ደም ካለው፣ ወይም የመተንፈሻ አካላት ምልክቶች የሳንባ ተሳትፎን የሚያመለክቱ ከሆነ ተደጋጋሚ የፀረ-ሰውነት ምርመራ ግምገማን ማዘግየት የለበትም።.
ቅድመ-ምርመራ ዕድል አዎንታዊ ውጤት ማለት ምን ማለት እንደሆነ ይለውጣል፡- በፍጥነት እየተራመደ ያለ የኩላሊት በሽታ ያለበት ሰው ለሰፊ የራስ-ሙቀት በሽታ ምርመራ ያለ ምንም ምልክት ከተሰጠው ሰው የተለየ የመነሻ ዕድል አለው። የትንታኔ ጣልቃገብነት፣ የእርግጠኛነት የሌለው ምላሽ እና የፀረ-ጂን እውቅና ልዩነት ትርጉምን ሊያደናግር ይችላል፤ በተመሳሳይ ምርመራ 2 ጊዜ መድገም ችግሩን ከመፍታት ይልቅ ሊደግመው ይችላል።.
ሪፖርት የተደረገው መደበኛ የሽንት ምርመራ በጥንቃቄ መመርመር አለበት፣ ምክንያቱም የሽንት ዱላ ማይክሮስኮፒ የተለየ ነው እና አሉታዊ ውጤት ጊዜን ወይም የናሙና ገደቦችን ሊያንፀባርቅ ይችላል። ሐኪሞች ብዙ ጊዜ ያጣምራሉ። የሽንት ዱላ ትርጓሜ ከሴዲመንት ምርመራ እና የፕሮቲን መለኪያ ጋር፤ ንጹህ የምትመስል የሽንት ናሙና በኩላሊት ውስጥ ምን እየተከናወነ እንዳለ መግለጽ አይችልም።.
የክሬቲኒን፣ የሽንት ማይክሮስኮፒ እና የሽንት አልቡሚን-ወደ-ክሬቲኒን ወይም የፕሮቲን-ወደ-ክሬቲኒን ጥምርታ ማረጋገጫ በሚሰጥበት ጊዜ ተጓዳኝ መረጃን ይሰጣሉ። የ3 mg/mmol ወይም ከዚያ በላይ የሆነ ACR፣ በግምት 30 mg/g፣ መደበኛ አይደለም ነገር ግን የፀረ-GBM በሽታን አያመለክትም፤ የእኛ የሽንት ክሬቲኒን ጥምርታ መመሪያ የ dilution-adjusted መለኪያዎች ከሽንት ክምችት ብቻ የበለጠ ጠቃሚ የሆኑበትን ምክንያት ያብራራል።.
የትኞቹ የሽንት ምርመራ ውጤቶች የኩላሊት ማጣሪያ ላይ ጉዳት ያመለክታሉ?
የደም ሽንት፣ የሽንት ፕሮቲን፣ የአልባሳት ቀይ የደም ሴሎች እና ቀይ የደም ሴል ካስት የፀረ-GBM ፀረ-አካላት አዎንታዊ ሲሆኑ የግሎሜሩላር ጉዳትን ሊደግፉ ይችላሉ። የቀይ የደም ሴል ካስት በተለይ የሚያሳስቡ ናቸው ምክንያቱም በኩላሊት ቱቦዎች ውስጥ ይመሰረታሉ። ከ3 ወይም ከዚያ በላይ ቀይ የደም ሴሎች በከፍተኛ የኃይል መስክ ላይ ብቻውን መገኘት የክሊኒካዊ ትርጓሜ ብቁ ነው, ነገር ግን መንስኤውን አያረጋግጥም.
ማይክሮስኮፒክ ሄማቱሪያ (Microscopic hematuria) ሽንት በግልጽ ከመቀየሩ በፊት ሊታዩ ይችላሉ, ስለዚህ ግልጽ የሆነ ሽንት የኩላሊት ማጣሪያዎች ያልተነካቁበት ማስረጃ አይደለም. በተቃራኒው, ለደም አዎንታዊ የሆነ የሽንት ዱላ ያለ ሙሉ ቀይ የደም ሴሎች የሂሞግሎቢን ወይም ማዮግሎቢን ሊያንጸባርቅ ይችላል; የሽንት ዱላውን ከማይክሮስኮፒ ውጤት ጋር ማወዳደር እነዚህን እድሎች ለመለየት ይረዳል, በተለይም ከከባድ የአካል ብቃት እንቅስቃሴ ወይም የጡንቻ ጉዳት በኋላ.
በፀረ-GBM በሽታ ውስጥ የፕሮቲን መጥፋት ወደ የኔፍሮቲክ ክልል, በአዋቂዎች ላይ በ conventionally 3.5 g በ24 ሰአት አካባቢ, ክሊኒካዊ በሆነ መንገድ ከባድ ለመሆን የለበትም። ታካሚው በጣም ትንሽ የፕሮቲን መለኪያ ያለው በፍጥነት እየራመደ ያለ የኩላሊት ጉዳት ሊኖረው ይችላል; የሽንት ፕሮቲን በጣም ከፍ ያለ መሆኑን ብቻ ማተኮር የበለጠ አስቸኳይ የክሬቲኒን ትራጀክተሪ ሊያመልጥ ይችላል።.
የናሙና ጥራት አስፈላጊ ነው ምክንያቱም የዘገየ ምርመራ የሴሉላር አካላት እና የካስት መለየት አስቸጋሪ ሊያደርግ ይችላል, እና የወር አበባ ብክለት የሄማቱሪያ ትርጓሜን ሊያወሳስበው ይችላል. የእኛ የሽንት ዝቃጭ መመሪያ ዋና ዋና ቅጦችን ያብራራል; የመጀመሪያው ናሙና ግልጽ ካልሆነ, ሐኪሞች 0 ሪፖርት የተደረጉ ካስት የግሎሜሩላር በሽታ የለም ብለው ከመገመት ይልቅ አዲስ ናሙና ሊጠይቁ ይችላሉ.
የትኞቹ የኩላሊት ተግባር ለውጦች ውጤቱን አስቸኳይ ያደርጉታል?
እየጨመረ ያለው የክሬቲኒን መጠን አዎንታዊ የፀረ-GBM ፀረ-አካላት ይበልጥ አስቸኳይ ያደርገዋል, በተለይም ከሽንት ደም ወይም ፕሮቲን ጋር. መደበኛ የአጣዳፊ የኩላሊት ጉዳት መስፈርቶች በ48 ሰአት ውስጥ ቢያንስ 0.3 mg/dL, ወይም 26.5 µmol/L, ወይም በ7 ቀናት ውስጥ ቢያንስ 1.5 እጥፍ መሰረታዊ ደረጃን ያካትታሉ; እነዚህ መስፈርቶች መንስኤውን አያመለክቱም.
An apparently normal creatinine can still represent acute kidney injury if it has risen substantially from a low baseline. An increase from 0.6 to 1.0 mg/dL over 48 hours meets the absolute rise criterion even if 1.0 is inside the laboratory's adult reference interval; the comparison with baseline is therefore more informative than the flag alone.
Estimated GFR equations are less reliable during rapidly changing kidney function because they assume a relatively steady creatinine concentration. Our BUN እና creatinine ንፅፅር explains additional influences such as dehydration and protein intake, but those alternatives do not safely explain away a 2-fold creatinine increase accompanied by positive anti-GBM antibodies and glomerular urine findings.
Kantesti፣ የ AI የደም ምርመራ ውጤት ትርጓሜ መድረክ, can organize dated laboratory results so a creatinine change over 48 hours is easier to recognize; treatment decisions still require a clinician. Urine output below 0.5 mL/kg/hour for 6 hours also meets a standard AKI criterion, although patients should seek help for markedly reduced urine without attempting a precise home calculation.
የትኞቹ ምልክቶች ከመደበኛ ሪፈራል ይልቅ የድንገተኛ እንክብካቤ ይፈልጋሉ?
Coughing up blood, new breathlessness, low oxygen, or markedly reduced urine output require emergency assessment when anti-GBM disease is possible. New oxygen saturation at or below 92% at sea level is concerning, but a normal home reading does not exclude lung bleeding. Do not wait for the antibody result to be repeated.
Alveolar hemorrhage can occur without obvious coughing up blood because blood remains within the air sacs rather than reaching the mouth. New breathlessness, an unexplained hemoglobin fall, and new lung imaging abnormalities can therefore be more informative than 0 visible blood; our shortness of breath testing guide explains why respiratory assessment requires more than a single laboratory marker.
Severe kidney injury can produce dangerous potassium accumulation, fluid overload, and acid–base disturbance before an antibody diagnosis is finalized. Potassium at or above 6.5 mmol/L generally requires emergency management; lower levels may also be urgent with AKI or ECG changes, as discussed in our potassium escalation guide.
Chest symptoms, confusion, fainting, or an abrupt fall in urine output should be described clearly to emergency services, including the known positive anti-GBM result. Bring the report and any creatinine measurements from the previous 7 days if readily available, but do not delay departure to gather paperwork; the clinical team can investigate and stabilize complications at the same time.
ባለሙያዎች የፀረ-GBM በሽታን እንዴት ያረጋግጣሉ?
Anti-GBM disease diagnosis combines serology with evidence of kidney or lung injury, and kidney biopsy often provides decisive information when safe and appropriate. Typical findings include crescentic glomerulonephritis and linear IgG staining along the glomerular basement membrane. These are 2 different observations: tissue injury and the pattern of antibody deposition.
Kidney biopsy can help establish the mechanism of injury and estimate how much potentially recoverable tissue remains, but no single microscopic feature should be read without context. Linear staining can occasionally occur in other settings, and atypical anti-GBM disease may differ from the classic pattern; specialists interpret light microscopy, immunofluorescence, and clinical findings together rather than treating 1 image as definitive.
የ KDIGO 2021 glomerular diseases guideline recommends starting treatment without delay when anti-GBM disease is strongly suspected, even before confirmation. That does not mean every isolated positive result needs immediate immunosuppression: a patient with rapidly worsening kidney function has a different risk balance from someone with stable creatinine and an equivocal antibody on 2 separate assays.
The broader assessment usually includes ANCA, a full blood count, electrolytes, urine studies, and investigations for alternative immune-mediated kidney disease. ANA, anti-dsDNA, and complement may be useful when lupus is a possibility; our መመሪያ ትርጉም anti-dsDNA explains why a second positive antibody can suggest an alternative or additional process rather than simply confirming the first.
ANCA አዎንታዊ በሆነበት ጊዜ ምን ይለወጣል?
ድርብ-አዎንታዊ በሽታ means a patient has both anti-GBM antibodies and ANCA, usually assessed through MPO-ANCA and PR3-ANCA testing. The acute presentation may resemble anti-GBM disease, while later relapse risk can resemble ANCA-associated vasculitis. Those 2 antibody systems therefore affect both immediate treatment and the longer-term follow-up plan.
McAdoo and colleagues' 2017 Kidney International cohort compared 37 double-positive patients with isolated anti-GBM disease and ANCA-associated vasculitis groups. The double-positive group showed features of both conditions, including clinically relevant later relapses; this is why disappearance of the anti-GBM antibody does not automatically justify stopping every form of immune monitoring or maintenance treatment.
An MPO test is not always an MPO-ANCA test: some laboratories offer myeloperoxidase concentration assays for other purposes, which do not answer the same autoimmune question. Confirm that the report identifies antibodies against MPO or PR3; there are 2 major antigen-specific ANCA targets, and a generic enzyme measurement should not be used to classify double-positive disease.
Complement levels can help explore competing diagnoses, but normal C3 and C4 do not exclude anti-GBM disease or ANCA-associated vasculitis. Our low complement interpretation guide explains how reduced complement may point toward another immune process; these 2 results refine the differential diagnosis rather than functioning as a safety check that rules out kidney injury.
የፀረ-GBM በሽታ እንዴት ይታከማል፣ ኩላሊቶችስ ሊያገግሙ ይችላሉ?
Classic anti-GBM disease is usually treated with plasma exchange, glucocorticoids, and cyclophosphamide, although specialists adapt treatment to presentation and recovery potential. KDIGO 2021 describes cyclophosphamide for approximately 2–3 months and glucocorticoids for about 6 months. Kidney recovery depends heavily on function and tissue damage when treatment begins.
Plasma exchange removes circulating antibodies, while immunosuppression reduces further antibody production and tissue-directed immune activity. Treatment often continues until anti-GBM antibodies are undetectable, commonly involving daily exchanges over approximately 2–3 weeks, though duration is individualized; antibody disappearance does not instantly repair scarred kidney tissue or guarantee that dialysis can be stopped.
KDIGO allows carefully selected exceptions to intensive treatment when a patient needs dialysis at presentation, has 100% crescents or more than 50% globally sclerotic glomeruli on an adequate biopsy, and has no pulmonary hemorrhage. These criteria require specialist judgment, not self-interpretation: lung involvement, sampling uncertainty, and the amount of viable tissue can change the treatment balance.
Treatment monitoring includes blood counts, kidney function, infection risk, and drug-specific precautions; changes across 2 visits may reflect medication effects rather than renewed autoimmune injury. Kantesti can help arrange those results chronologically, but our የመድኃኒት ደህንነት የዝንባሌ መመሪያ is educational support—not authorization to alter steroids, cyclophosphamide, or a specialist's plasma-exchange schedule.
ፀረ-ሰው (antibodies) አሉታዊ ከሆኑ በኋላ ምን ዓይነት ክትትል ያስፈልጋል?
A negative anti-GBM result after treatment does not mean follow-up can stop, because kidney recovery, medication toxicity, and possible ANCA overlap still need assessment. KDIGO 2021 recommends postponing kidney transplantation until anti-GBM antibodies have remained undetectable for at least 6 months. The monitoring schedule is individualized rather than a universal monthly timetable.
Relapse is uncommon in isolated classic anti-GBM disease, but double-positive disease needs a different long-term strategy because ANCA-associated vasculitis can recur. New urine blood, worsening creatinine, or recurrent breathlessness after 1 apparently successful treatment course deserves assessment; clinicians should not assume every new abnormality is relapse, but should not dismiss it merely because an earlier antibody test was negative.
የ 6-month antibody-negative interval before transplantation concerns recurrence risk, not simply recovery from the original hospitalization. Transplant teams also consider clinical stability, infection risk, cardiovascular health, and other eligibility factors; a person can be antibody-negative while still requiring dialysis, and that does not mean the original treatment failed to control the immune process.
Diet and supplements cannot remove anti-GBM antibodies or replace immune treatment, and impaired filtration changes the safety of many over-the-counter products. Our የኩላሊት ተጨማሪ ደህንነት መመሪያ explains common concerns; potassium-containing products, herbal mixtures, and high-dose nutrients deserve review when eGFR is reduced, even if only 1 ingredient is advertised as kidney-supporting.
የ CE ትርጓሜ ምን ሊረዳ ይችላል—እና ምን ክሊኒካል መሆን አለበት?
AI interpretation can help organize an anti-GBM report, but cannot diagnose Goodpasture syndrome or decide whether emergency treatment is needed. The most useful handoff includes the antibody method, creatinine trend, urine findings, and symptoms. A change over 48 hours can matter more than the report's color-coded positive flag.
ካንቴስቲ እ.ኤ.አ. የAI ላብ ሙከራ ትርጓሜ አገልግሎት that can explain the relationship between anti-GBM antibodies and accompanying laboratory findings when those results are supplied. Our የቴክኖሎጂ ማብራሪያ describes the interpretation workflow; the original report remains the source for 3 essentials—value, unit, and reference interval—and an AI summary is not independent confirmation.
A technical benchmark is not a clinical diagnosis study, and a tool that explains reports cannot assess lung sounds, examine urine itself, or interpret a kidney biopsy firsthand. Our የክሊኒካዊ ደረጃዎች እና ማረጋገጫ page provides methodological context; even excellent performance on 1 reporting task does not establish safety for every rare autoimmune presentation.
A note from Thomas Klein: the practical question to ask your clinician is, 'Do these antibodies come with evidence of kidney or lung injury, and how quickly should I be assessed?' As of ጥቅምት 6, 2026, this article cites KDIGO 2021 guidance and the named studies below; ask for an explicit plan today rather than leaving a positive result without a follow-up pathway.
ክሊኒካዊ ማጣቀሻዎች፣ ተዛማጅ ምርምሮች እና የጭንጭ ምንጮች ገደቦች
The anti-GBM recommendations in this article are supported by 3 directly relevant clinical references, listed separately from our 2 related Zenodo resources. The Zenodo materials concern coagulation and serum proteins; they are supporting laboratory education, not trials, clinical guidelines, or evidence that establishes a Goodpasture syndrome diagnosis.
KDIGO 2021 supplies the treatment and transplantation recommendations; McAdoo and Pusey 2017 explains classic disease mechanisms and presentations; McAdoo and colleagues 2017 addresses double-positive outcomes. These 3 sources answer different questions, and no general protein or coagulation guide can substitute for them; Kantesti's የህክምና አማካሪ መረጃ describes the clinical expertise relevant to interpreting medical content.
aPTT Normal Range: D-Dimer, Protein C Blood Clotting Guide. (n.d.). Zenodo. DOI: 10.5281/zenodo.18262555. This related coagulation interpretation resource explains laboratory concepts relevant to treatment safety, not anti-GBM confirmation; ResearchGate discovery search እና Academia.edu discovery search are search links, not verified publication profiles.
Serum Proteins Guide: Globulins, Albumin & A/G Ratio Blood Test. (n.d.). Zenodo. DOI: 10.5281/zenodo.18316300. This related serum protein resource explains why albumin and globulins add context without measuring anti-GBM activity; ResearchGate የህትመት ፍለጋ እና Academia.edu ማተሚያ ፍለጋ likewise do not establish independent peer review of either of these 2 resources.
በተደጋጋሚ የሚጠየቁ ጥያቄዎች
የ𝗚𝗕𝗠 ፀረ-ፀረ-ሰውነቶች አዎንታዊ መሆናቸው የగుድፓስቸር ሲንድሮም አለብኝ ማለት ነው?
አዎንታዊ የፀረ-GBM ፀረ-አካላት ለፀረ-GBM በሽታ ሊያመላክቱ ይችላሉ ነገር ግን ራስን የጉድፓስቸር ሲንድሮም በራሱ አያረጋግጡም። ምርመራው የኩላሊት ተግባር፣ የሽንት ግኝቶች እና የሳንባ ተሳትፎን ከግምት ውስጥ የሚያስገባ ክሊኒካዊ ግምገማን ይፈልጋል፣ የኩላሊት ባዮፕሲም ብዙውን ጊዜ ጠቃሚ ማስረጃዎችን ይሰጣል። የሳንባ ተሳትፎ በግምት 40–60% ከሚታወቁት የተለመዱ ጉዳዮች ውስጥ ስለሚከሰት የኩላሊት ብቻ በሽታ ይቻላል። ትዕዛዝ የሰጡትን ሐኪም በፍጥነት ያነጋግሩ እና ደም በማስነጠል፣ አዲስ የትንፋሽ እጥረት ወይም የሽንት መጠን መቀነስ ካለ አስቸኳይ የሕክምና እንክብካቤ ይጠይቁ።.
የፀረ-ጂቢኤም በሽታ ሳያስሉ ኩላሊትን ሊጎዳ ይችላል?
ፀረ-ጂቢኤም በሽታ ሳያስነጥስ ወይም ሌሎች ግልጽ የሳንባ ምልክቶችን ሳያስከትል ኩላሊትን ሊጎዳ ይችላል። የኩላሊት ማጣሪያዎች እና የሳንባ አየር ከረጢቶች በአንቲቦዲ ተደራሽነት እና ተጋላጭነት ይለያያሉ፣ ስለዚህ የአንድ አካል ተሳትፎ የሌላውን ተሳትፎ አይጠይቅም። ፀረ-ጂቢኤም ፀረዴዎች አዎንታዊ በሆኑበት ጊዜ ቢያንስ 0.3 mg/dL፣ ወይም 26.5 µmol/L የ creatinine ከፍታ በ48 ሰአት ውስጥ የኩላሊት ጉዳት ደረጃን ያሟላል እና አስቸኳይ ምርመራ ይፈልጋል። መደበኛ መተንፈስ የኩላሊት ምርመራን ማዘግየት የለበትም።.
አዎንታዊ ተደርጎ የሚወሰደው የፀረ-ጂቢኤም ፀረ-ሰው ደረጃ ምንድን ነው?
አወንታዊው የፀረ-ጂቢኤም ፀረ-አካል ገደብ በቤተ-ሙከራው ምርመራ እና በሚጠቀመው የመለኪያ አሃድ ላይ የተመሠረተ ነው። ለሁሉም ቤተ-ሙከራዎች ተፈጻሚ የሚሆን አንድም የዩኒቨርሳል U/mL ወይም IU/mL ገደብ የለም። እንደ ምሳሌ፣ 21 U/mL ከ20 U/mL የቤተ-ሙከራ ገደብ ትንሽ ከፍ ያለ ነው፣ ነገር ግን እነዚህ ቁጥሮች ለሌላ ምርመራ ተፈጻሚ መሆን የለባቸውም። አስቸኳይነቱ ከዚህ ጋር ተያይዞ ለሚከሰተው የኩላሊት ወይም የሳንባ ጉዳት እንጂ ለፀረ-አካል ክምችት ብቻ አይደለም።.
የፀረ-ጂቢኤም ፀረ-አካል ምርመራ አወንታዊ ሆኖ ቢገኝ ሊሳሳት ይችላል?
አዎንታዊ የፀረ-GBM ፀረ-ሰው ምርመራ የትንታኔ ጣልቃገብነት፣ አጠቃላይ ምላሽ ሰጪነት ወይም የበሽታው ዝቅተኛ የክሊኒካል ዕድል ስላለው ሊሳሳት ይችላል። የኩላሊት ተግባር መረጋጋት እና መደበኛ የሽንት ምርመራ ውጤቶች ጋር ደካማ አዎንታዊነት በሁለተኛ ዘዴ በማረጋገጥ ማረጋገጥ ሊያስፈልግ ይችላል። ተመሳሳይ ምርመራን 2 ጊዜ መድገም ተመሳሳይ የትንታኔ ችግር ሊፈጥር ይችላል, ስለዚህ ሐኪሞች ከቤተ-ሙከራው አማራጭ ምርመራን ሊወያዩ ይችላሉ። የኩላሊት ተግባር እየተባባሰ ወይም የሳንባ ምልክቶች በሚታዩበት ጊዜ ማረጋገጥ አስቸኳይ ግምገማን ማዘግየት የለበትም።.
የፀረ-ጂቢኤም ምልክቶች ወደ ድንገተኛ እንክብካቤ እንድሄድ የሚያደርጉኝ ምንድናቸው?
ደምን ማስነጠል፣ አዲስ ወይም እየባሰ የመተንፈስ ችግር፣ የሽንት ምርትን በከፍተኛ ሁኔታ መቀነስ፣ ግራ መጋባት ወይም ራስን መሳት የፀረ-ጂቢኤም በሽታ ከተጠረጠረ ድንገተኛ ግምገማ ያስፈልጋቸዋል። በባህር ጠለል ላይ አዲስ የኦክሲጅን ሙሌት 92% ወይም ከዚያ በታች መሆን የሚያሳስብ ነው፣ ምንም እንኳን መደበኛ የቤት ውስጥ ንባብ የሳንባ ተሳትፎን አያግድም። ከ 6.5 mmol/L በላይ ያለው ፖታስিয়াম በአጠቃላይ ድንገተኛ አያያዝን ይፈልጋል፣ እና ዝቅተኛ ደረጃዎች ከከባድ የኩላሊት ጉዳት ወይም የ ECG ለውጦች ጋር አደገኛ ሊሆኑ ይችላሉ። እርዳታ ከመጠየቅዎ በፊት የድጋሚ ፀረ-ሰው ምርመራን አይጠብቁ።.
የፀረ-ጂቢኤም በሽታ ሊታከም ይችላልን፣ የኩላሊት ንቅለ ተከላ ማድረግ እችላለሁን?
Anti-GBM በሽታ ሊታከም ይችላል፤ ይህም በተለምዶ የፕላዝማ ልውውጥ፣ ግሉኮርቲኮይድስ እና ሳይክሎፎስፋሚድ በመጠቀም ነው፤ ነገር ግን የኩላሊት ማገገም የሚወሰነው በሕክምናው ዋዜማ ላይ በደረሰው ጉዳት ክብደት እና ቆይታ ላይ ነው። KDIGO 2021 ሳይክሎፎስፋሚድ ለ2–3 ወራት እና ግሉኮርቲኮይድስ ለ6 ወራት ያህል እንዲሰጥ ይመክራል፤ ይህም በልዩ ባለሙያዎች ግለሰባዊ ማስተካከያዎች ይደረግበታል። በማይቀለበስ የኩላሊት ውድቀት ላይ ያሉ ሰዎች ንቅለ ተከላ እንዲያደርጉ ሊታሰብላቸው ይችላል። KDIGO ንቅለ ተከላ ከማድረግዎ በፊት ቢያንስ ለ6 ወራት anti-GBM ፀረ እንግዳ አካላት (antibodies) በማይታወቁበት ደረጃ ላይ እንዲቆዩ ይመክራል።.
ዛሬ የAI-የኃይል የደም ምርመራ ትንተና ያግኙ
በፍጥነት እና ትክክለኛ የላቦራቶሪ ምርመራ ትንተና ለማግኘት Kantestiን የሚያምኑ ከ2 ሚሊዮን በላይ ተጠቃሚዎችን ይቀላቀሉ። የደም ምርመራ ውጤትዎን ይስቀሉ እና በ15,000+ ባዮማርከሮች ላይ የተሟላ ትርጓሜን በሰከንዶች ውስጥ ይቀበሉ።.
📚 የተጠቀሱ የምርምር ህትመቶች
Klein, T., Mitchell, S., & Weber, H. (2026). aPTT መደበኛ ክልል፡ D-Dimer፣ ፕሮቲን ሲ የደም መርጋት መመሪያ. Kantesti AI የሕክምና ምርምር።.
Klein, T., Mitchell, S., & Weber, H. (2026). የሴረም ፕሮቲኖች መመሪያ፡ ግሎቡሊንስ፣ አልቡሚን እና የኤ/ጂ ጥምርታ የደም ምርመራ. Kantesti AI የሕክምና ምርምር።.
📖 ውጫዊ የሕክምና ማጣቀሻዎች
Kidney Disease: Improving Global Outcomes Glomerular Diseases Work Group (2021). KDIGO 2021 የክሊኒካዊ ልምድ መመሪያ ለግሎሜሩላር በሽታዎች አስተዳደር.። Kidney International።.
McAdoo SP and Pusey CD (2017). Anti-Glomerular Basement Membrane Disease.። የአሜሪካን ሶሳይቲ ኔፍሮሎጂ (American Society of Nephrology) ክሊኒካዊ ጆርናል።.
McAdoo SP et al. (2017). Patients double-seropositive for ANCA and anti-GBM antibodies have varied renal survival, frequency of relapse, and outcomes compared to single-seropositive patients.። Kidney International።.
⚕️ የሕክምና ማስተባበያ
ይህ ጽሑፍ ለትምህርታዊ ዓላማ ብቻ ነው እና የሕክምና ምክር አይደለም። ለምርመራ እና ለሕክምና ውሳኔዎች ሁልጊዜ ብቁ የጤና ባለሙያን ያማክሩ።.
የE-E-A-T እምነት ምልክቶች
ልምድ
በሐኪም መሪነት የላቦራቶሪ ትርጓሜ የስራ ፍሰቶች ክሊኒካዊ ግምገማ።.
ባለሙያነት
በክሊኒካዊ አውድ ውስጥ ባዮማርከሮች እንዴት እንደሚሰሩ ላይ የላቦራቶሪ ሕክምና ትኩረት።.
ስልጣን ያለው
በዶክተር ቶማስ ክላይን የተፃፈ ከዶክተር ሳራ ሚቸል እና ፕሮፌሰር ዶክተር ሃንስ ዌበር ግምገማ ጋር።.
አስተማማኝነት
ለማስጠንቀቂያ ምላሽ መቀነስ ግልጽ የቀጣይ መንገዶች ያለው በማስረጃ የተደገፈ ትርጓሜ።.