
Low antithrombin activity does not automatically mean inherited deficiency: an acute clot, heparin, severe illness or protein loss can temporarily lower it. Clinicians confirm persistent abnormalities with appropriately timed activity testing, sometimes antigen testing, and a medication-aware laboratory plan—often after the first 3 months of clot treatment.

要点
- 参考范围: Adult antithrombin activity commonly falls around 80–120%; use the interval printed on your own report.
- One low result: An activity of 65% during a new clot or heparin treatment cannot establish inherited antithrombin deficiency.
- 复查时间: The British Society for Haematology recommends testing natural anticoagulant deficiencies only after 3 months of anticoagulation for acute thrombosis.
- Activity versus antigen: Type I deficiency usually lowers both measurements; type II deficiency lowers function while antigen may remain normal.
- Medication interference: Apixaban, rivaroxaban and edoxaban can falsely increase activity in factor Xa-based assays; dabigatran can do so in thrombin-based assays.
- Protein loss: Adult nephrotic-range proteinuria is conventionally at least 3.5 g per 24 hours and can contribute to acquired antithrombin reduction.
- Family evaluation: A confirmed heterozygous inherited deficiency generally gives each child a 50% chance of inheriting the relevant variant—not a 50% certainty of developing a clot.
- 药物安全性: Never stop anticoagulation to obtain a cleaner laboratory result without an individualized plan from the prescribing clinician.
What does low antithrombin activity actually mean?
Low antithrombin activity means a laboratory assay detected less anticoagulant function than expected; it does not, by itself, identify the cause. A result below an adult laboratory’s lower limit—often around 80%—may reflect inherited deficiency, temporary consumption, reduced production, protein loss or a testing problem.

Antithrombin limits coagulation by inhibiting enzymes including thrombin, also called factor IIa, and factor Xa. An activity result of 60% describes performance relative to the assay’s calibration standard; it does not mean your circulation is 60% protected or that your chance of a clot is 40%.
A normal routine clotting panel does not exclude antithrombin deficiency, because PT and aPTT are not screening tests for every inherited tendency to clot. Our explanation of normal coagulation panel limitations helps separate these questions: whether coagulation times are prolonged and whether a particular natural anticoagulant functions normally are 2 different assessments.
Kantesti is an AI blood test analyzer that helps place an activity percentage alongside medication history and related laboratory results, rather than treating 1 abnormal flag as a diagnosis. Our company background and purpose explains that role; inherited deficiency still requires clinician-led confirmation, and urgent symptoms must be assessed independently of any AI interpretation.
What antithrombin activity range is considered low?
Adult antithrombin activity commonly has a reference interval of approximately 80–120%, although some laboratories use 80–130% or another validated interval. An activity of 75% is therefore often borderline low, but neither 75% nor any other single cutoff proves inherited deficiency or determines emergency treatment.

Many people with heterozygous inherited antithrombin deficiency have activity somewhere around 40–70%, but acquired conditions can produce the same values. Conversely, some inherited variants produce milder reductions or escape detection by particular assays; clinicians interpret the depth of the reduction together with repeat results, not as a stand-alone genetic fingerprint.
Age changes interpretation substantially: healthy term newborns can have antithrombin activity around 40–60% of adult values, with levels rising during infancy. Prematurity introduces additional variation, and late pregnancy or the early postpartum period can also affect results; applying an adult 80% lower limit indiscriminately can create a misleading label.
For a clearly hypothetical example, an otherwise well adult with activity of 78% and no previous clots needs a different evaluation from an adult with 42% during severe sepsis. Both reports may display the same low flag, but our guide to 范围之外的实验室结果 explains why reference limits are not interchangeable with diagnostic or treatment thresholds.
| 水平 | 范围 | 含义 |
|---|---|---|
| Common adult interval | Approximately 80–120% | Usually within range, but the laboratory’s own interval and assay sensitivity take precedence. |
| Borderline reduction | 70–79% | Often warrants context review and appropriately timed confirmation; not a diagnosis. |
| Clear reduction | 50–69% | Compatible with inherited or acquired deficiency; activity alone cannot distinguish them. |
| 明显降低 | Below 50% | Requires clinical review, especially during illness or thrombosis; the percentage alone does not establish an emergency. |
Antithrombin antigen vs activity: what is the difference?
一个 antithrombin activity test measures how effectively the protein inhibits a coagulation enzyme, while antithrombin antigen measures how much protein is present. Type I inherited deficiency generally lowers both; type II generally lowers activity despite a relatively normal antigen concentration, making these 2 tests complementary rather than interchangeable.

Most routine activity methods are chromogenic assays: the laboratory adds an enzyme and measures how much remains after antithrombin has inhibited it. The ISTH laboratory recommendations favor activity testing first, followed by antigen measurement when activity is low, with exclusion of acquired causes and assay interference before classification (Van Cott et al., 2020).
Consider 2 hypothetical repeat profiles obtained under suitable conditions: activity 52% with antigen 49% supports a quantitative pattern, whereas activity 52% with antigen 101% supports a qualitative pattern. These examples are not diagnostic formulas, because acquired illness can lower both measurements and antigen assays do not explain whether a functional result was distorted by medication.
Type II deficiency includes reactive-site, heparin-binding-site and other functional abnormalities; the choice of assay can change how readily a variant is detected. Kantesti’s explanations therefore distinguish quantity from performance, a distinction also illustrated by protein level versus function in C1 esterase inhibitor testing—but those are different proteins with different clinical consequences.
Can an acute clot temporarily lower antithrombin?
Acute thrombosis can temporarily reduce antithrombin activity through consumption, particularly when accompanied by illness, procedures or treatment effects. A value such as 58% during a newly diagnosed deep vein thrombosis therefore cannot reliably distinguish an inherited baseline deficiency from a reduction caused by the current event.
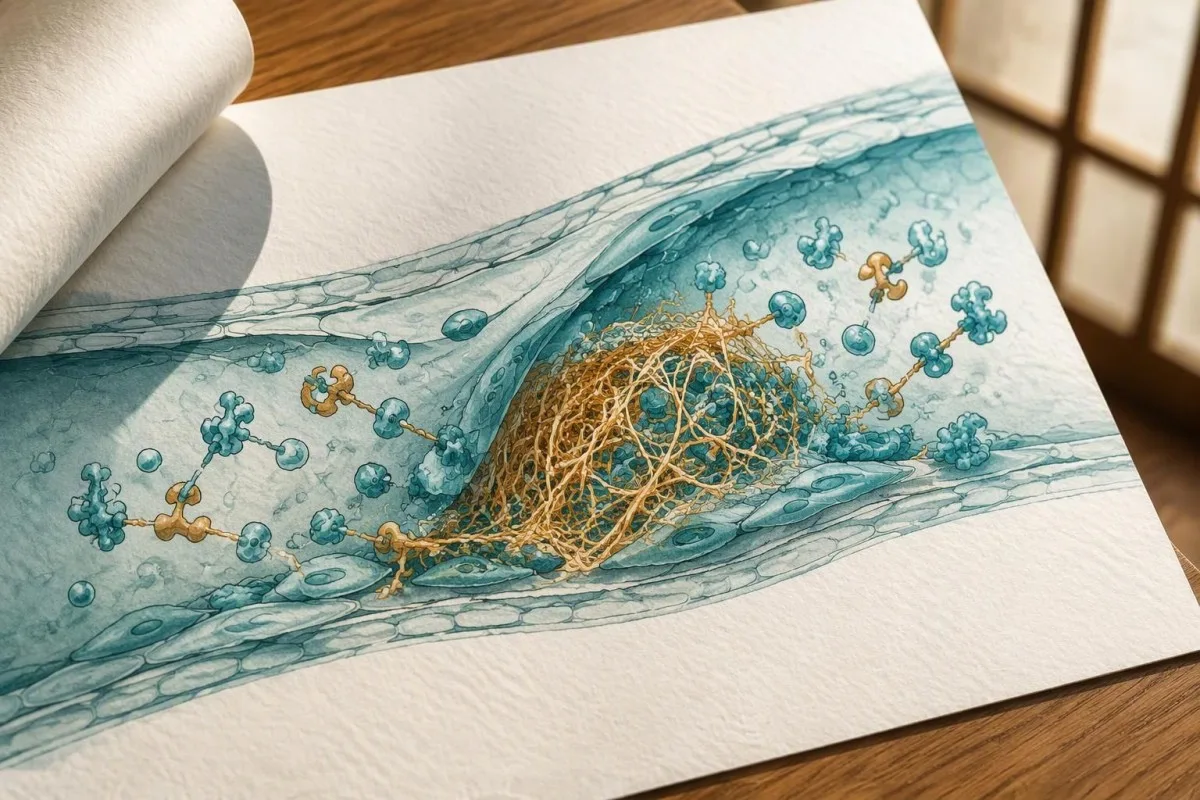
The British Society for Haematology recommends testing deficiencies of natural anticoagulants only after 3 months of anticoagulation for acute thrombosis, because early results are unreliable and rarely change immediate management (Arachchillage et al., 2022). This is a recommendation about diagnostic timing, not an instruction to delay treating a suspected clot or to stop anticoagulants at month 3.
A hypothetical patient has activity of 61% during a pulmonary embolism and 96% after recovery using an appropriate assay. That change supports a temporary reduction, but comparing 2 percentages remains incomplete unless the clinician knows whether heparin, a direct oral anticoagulant, replacement products or different laboratory methods affected either measurement.
D-dimer answers a different question: it reflects fibrin formation and breakdown, not antithrombin quantity or inherited status. Our clotting tests and D-dimer guide explains why an elevated D-dimer and low activity can occur together during 1 acute event without proving that the low antithrombin caused the clot.
Why can heparin treatment lower antithrombin activity?
Heparin can lower circulating antithrombin during treatment, so a low result obtained while receiving unfractionated or low-molecular-weight heparin may reflect an acquired reduction. Heparin also depends on antithrombin for much of its anticoagulant effect; activity of 50% during treatment can therefore raise both diagnostic and medication-monitoring questions.

Reduced antithrombin can contribute to apparent heparin resistance, but an unexpectedly high dose requirement does not prove inherited deficiency. During 1 episode of severe illness, increased factor VIII or fibrinogen may shorten aPTT-based impressions of anticoagulation even when heparin exposure is adequate, so clinicians may reassess the monitoring method rather than simply escalate treatment.
Some heparin anti-Xa assays add exogenous antithrombin and others do not; this difference can affect what the result says about heparin concentration versus its activity in the patient. Ask the laboratory about 2 separate methods—the antithrombin activity assay and the heparin monitoring assay—because their handling of antithrombin and heparin is not necessarily identical.
A platelet fall of more than 50% during heparin exposure raises a separate possibility, heparin-induced thrombocytopenia, which is not diagnosed by low antithrombin. Our explanation of PF4 testing and HIT assessment describes that distinction; decisions about changing heparin, using replacement antithrombin or scheduling a repeat require the treating team, not a self-directed medication pause.
How do severe illness and DIC reduce antithrombin?
Sepsis, disseminated intravascular coagulation and major physiological stress can reduce antithrombin through consumption, impaired production and altered distribution. A markedly low result—for example, 35%—during critical illness is often an acquired finding; it cannot be used alone to label someone with lifelong hereditary antithrombin deficiency.

DIC is assessed from a pattern, not 1 abnormal protein: falling platelets, prolonged PT, increased fibrin-related markers and sometimes reduced fibrinogen provide the relevant context. Fibrinogen may initially remain normal or elevated because it is an acute-phase protein, so a preserved fibrinogen concentration does not automatically rule out evolving consumption.
For a hypothetical example, activity of 38%, platelets of 72 × 10^9/L and worsening PT during a major systemic illness point toward an acquired coagulation disturbance rather than an isolated inherited finding. Our DIC laboratory pattern explanation shows why trends across several measurements are more informative than repeatedly checking antithrombin while the illness remains active.
Recent antithrombin concentrate or plasma treatment can raise measured activity and obscure the underlying baseline, adding a second source of uncertainty during the same hospital stay. A result of 105% after replacement does not exclude inherited deficiency, just as 35% before recovery does not prove it; document the product and timing before interpreting either percentage.
Can kidney protein loss cause low antithrombin activity?
Heavy urinary protein loss can contribute to acquired antithrombin reduction, particularly in nephrotic syndrome. Adult nephrotic-range proteinuria is conventionally at least 3.5 g per 24 hours; clinicians interpret antithrombin alongside urine protein, serum albumin and the underlying kidney disorder, rather than relying on creatinine or eGFR alone.
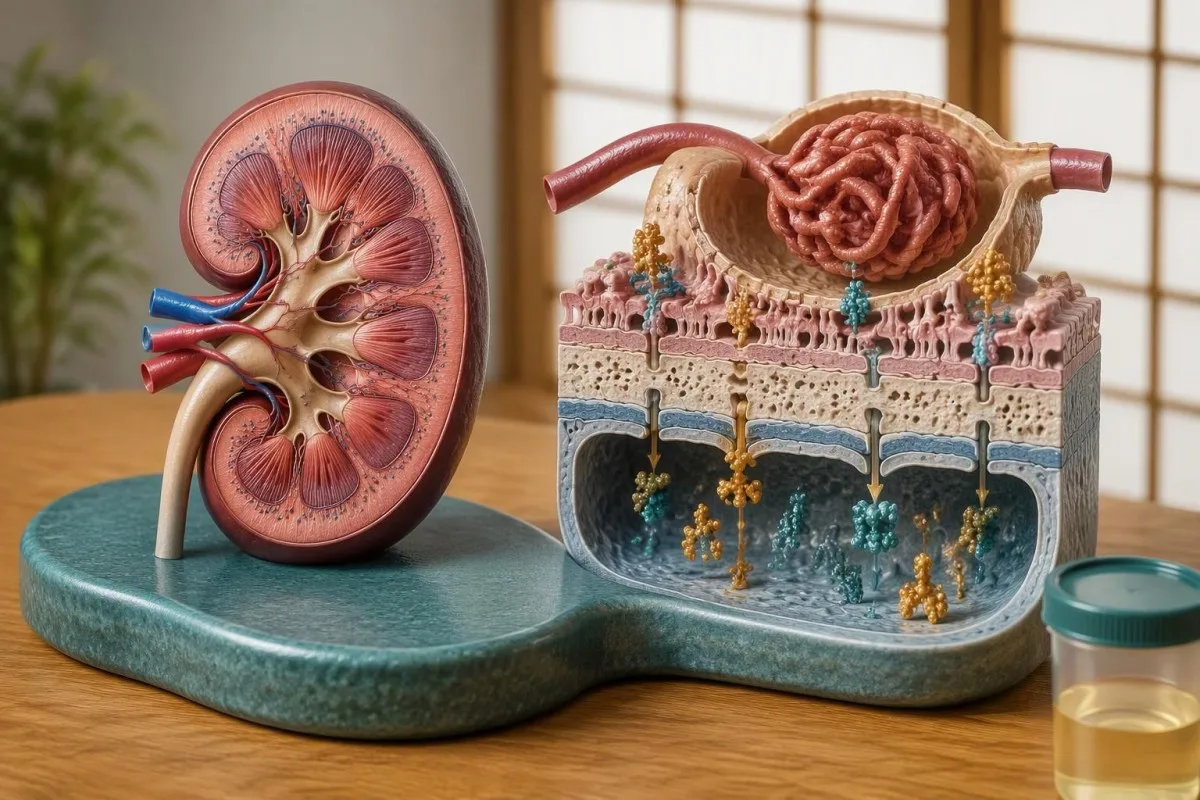
A normal eGFR does not exclude substantial protein leakage through the glomerular filtration barrier. For example, an adult with eGFR 95 mL/min/1.73 m², albumin 22 g/L and urine protein 6 g per day may have a strong acquired explanation for low activity despite apparently reassuring filtration results; persistent 泡沫尿液和蛋白质检测 deserve assessment in that context.
The relationship between nephrotic syndrome, antithrombin levels and clot risk is not uniform: not every person with nephrotic syndrome has low antithrombin, and the thrombotic tendency involves more than urinary loss of 1 protein. Underlying diagnosis matters, including membranous nephropathy, where PLA2R results and kidney monitoring help explain the kidney process rather than prove an inherited clotting disorder.
Kantesti is an AI blood test interpretation platform that can organize an antithrombin percentage alongside albumin and kidney markers, but it cannot infer the amount of urinary protein from eGFR alone. If activity remains 62% while heavy protein loss continues, repeat testing may still describe the acquired condition; the cleaner inherited assessment usually follows clinical stabilization and improvement of that competing explanation.
Can liver disease or other treatments lower antithrombin?
Reduced liver synthesis can lower antithrombin, especially in advanced liver disease, while certain treatments such as L-asparaginase can also cause acquired reductions. An activity of 55% alongside other abnormalities requires review of protein production, protein loss and treatment history before clinicians consider a genetic explanation.
ALT and AST reflect injury more than protein-making capacity, so normal or mildly elevated enzymes do not guarantee normal antithrombin production. If activity is 57%, albumin is 25 g/L and INR is 1.6, impaired synthesis becomes a possibility—but warfarin, nutrition and protein loss can confound that pattern, as our 肝功能检查解读指南 所解释的那样。.
Albumin cannot serve as a substitute antithrombin test because the 2 proteins have different turnover and can respond differently to illness or therapy. Our albumin and serum protein guide helps interpret the surrounding panel; a normal albumin does not exclude inherited antithrombin deficiency, and a low albumin does not prove that the liver caused it.
L-asparaginase can reduce anticoagulant proteins during cancer treatment, creating an acquired thrombosis risk that may need active management rather than merely a future repeat test. Major procedures, extracorporeal support and recent replacement products can also complicate 1 measurement; eating more protein or taking a vitamin supplement does not correct a SERPINC1-related defect or replace treatment of the underlying acquired cause.
Which anticoagulants interfere with antithrombin testing?
Direct oral anticoagulants can falsely increase antithrombin activity, potentially masking deficiency rather than causing a low flag. Apixaban, rivaroxaban and edoxaban interfere with factor Xa-based activity assays, while dabigatran can interfere with thrombin-based assays; the same patient’s 2 results may therefore differ because of assay design.

The mechanism is straightforward: the medication inhibits the assay’s added enzyme, and the instrument can misread that inhibition as stronger antithrombin function. The ISTH communication explicitly identifies these drug–assay combinations, including effects from direct thrombin inhibitors such as argatroban and bivalirudin (Van Cott et al., 2020); antigen testing usually avoids this particular functional interference, but does not replace an activity assessment.
A hypothetical activity of 108% on a factor Xa-based assay while taking rivaroxaban may conceal an underlying reduction; activity of 66% on that same drug still cannot be mathematically corrected into a true baseline. Anticoagulants also affect lupus anticoagulant test interpretation, but the direction and mechanism of interference are test-specific, not a universal rule for all thrombophilia assays.
Kantesti AI should support medication-aware interpretation rather than claim that 1 uploaded report identifies the laboratory’s reagent or removes a drug effect. Depending on the situation, the laboratory may use a less-affected assay, measure drug exposure or apply a validated removal procedure; our 技术验证与监督 describes the broader standards behind interpretation, not a guarantee that AI can resolve missing assay information.
Could sample handling explain an unexpected low result?
Sample quality and assay differences can make antithrombin results unreliable, especially when the laboratory flags collection or processing problems. Coagulation samples typically require a 9:1 ratio of sample to citrate anticoagulant; underfilling, inappropriate handling or an unsuitable specimen should be considered before interpreting an isolated abnormal percentage.
A hematocrit above approximately 55% may require citrate adjustment for coagulation testing because the amount of plasma relative to citrate is reduced. This is a laboratory preparation issue, not evidence of hereditary deficiency; if activity is 73% in a flagged specimen, ask whether the laboratory accepted the sample as valid and whether recollection is preferable to repeating the same material.
Hemolysis, lipemia and marked discoloration can interfere with optical methods, although the effect depends on the instrument and reagent rather than having 1 predictable direction. Our guides to hemolysis-related result distortion 和 lipemic specimens and redraws explain why a specimen-quality warning needs a method-specific answer instead of an automatic diagnosis.
Changing laboratories can create a second problem: an activity of 76% by one method and 84% by another may reflect analytical differences rather than biological recovery. Using the same laboratory helps trend comparison, but persistent clinical suspicion may justify a specialist laboratory using an alternative assay that is more sensitive to certain inherited variants; consistency and diagnostic sensitivity are 2 different goals.
When should low antithrombin activity be repeated?
Repeat antithrombin testing should occur after temporary causes have settled and medication effects have been addressed. Following an acute clot, the BSH recommendation is to wait until after 3 months of anticoagulation before testing natural anticoagulant deficiencies; the safest collection date then depends on the drug, assay and clinical situation.

An incidental borderline result in a well adult without a recent clot does not automatically require the same 3-month wait, because that interval addresses acute thrombosis. The clinician may instead arrange a separate repeat once collection issues and acquired causes are reviewed, adding antigen testing if activity remains low; there is no universally validated waiting interval that fits every outpatient finding.
Heparin-related reductions may recover after treatment ends, but laboratory policies and ongoing illness affect when a repeat becomes meaningful. For a DOAC, a fixed 48-hour pause is not universally adequate or safe: kidney function, dose timing, drug accumulation and assay sensitivity matter, and choosing a compatible method may avoid interrupting treatment entirely.
Kantesti’s trend tools can help organize 2 measurements with their dates, but a timeline should also record clot onset, heparin exposure, the last relevant medication dose and any replacement products. Our explanation of 出院后的结果 supports that workflow; warfarin does not usually lower antithrombin as it lowers vitamin K-dependent proteins, so protein C or S stopping rules should not be copied automatically.
What findings support inherited antithrombin deficiency?
Inherited antithrombin deficiency becomes more likely when activity remains low on separate, interpretable samples, acquired causes are excluded and the personal or family history fits. Two concordant results provide stronger evidence than 1 result during illness, but activity, antigen and sometimes SERPINC1 testing must still be considered together.

A clearly hypothetical profile of activity 54% and 56% on 2 suitable occasions, antigen 51%, no major protein loss and a first-degree relative with confirmed deficiency would support a quantitative inherited pattern. Early or recurrent venous thrombosis increases suspicion, but age alone is not diagnostic, and absence of a family history does not exclude a new variant or previously unrecognized disease.
SERPINC1 testing can help establish a molecular explanation when the laboratory phenotype is convincing and the result could affect management or family counseling. A variant of uncertain significance is not equivalent to a diagnosis, while a negative genetic test does not necessarily exclude every relevant change; the ISTH recommendations also note that molecular testing may identify defects missed by activity assays (Van Cott et al., 2020).
Antithrombin and protein S deficiency require different interpretive rules, even when they appear on the same thrombophilia panel. Our guide to low protein S activity explains several contrasting confounders; a type II antithrombin heparin-binding-site variant can also have a different risk profile from type I deficiency, so 1 generic risk estimate should not be applied to all confirmed variants.
When is family evaluation appropriate?
Family evaluation is usually considered after the original patient’s inherited deficiency is convincingly confirmed, especially when the result could change prevention, hormone choices or pregnancy planning. Most inherited antithrombin deficiency is autosomal dominant, giving each child of a heterozygous carrier a 50% chance of inheriting the relevant variant—not a certainty of thrombosis.

The BSH guideline discourages routine thrombophilia testing of all first-degree relatives but supports selective evaluation for relatives of people with antithrombin, protein C or protein S deficiency when results could influence management (Arachchillage et al., 2022). Our 基于风险的家族检测指南 explains why testing 1 relevant inherited condition can be more useful than ordering a broad panel without a clinical question.
ASH’s 2023 thrombophilia guideline similarly supports selective testing in certain families with known high-risk deficiencies, including decisions about estrogen exposure and prophylaxis during particular risk situations (Middeldorp et al., 2023). Many recommendations are conditional and based on very low-certainty evidence; antithrombin deficiency should not be treated as interchangeable with factor V Leiden results, which often carry a different risk profile.
Kantesti’s Family Health Risk feature can help organize information shared with consent, but it cannot determine whether a relative inherited a SERPINC1 variant from 1 family member’s activity percentage. Testing children requires age-aware laboratory interpretation and an assessment of whether the result would change care now; predictive testing also deserves counseling about privacy, uncertainty and the difference between inherited susceptibility and an actual clot.
随访计划和信息来源核查应包括什么?
Bring the original percentage, reference interval, medication list and sampling date to follow-up, along with details of the clot, illness or protein loss that could explain the result. Two decisions come first: whether the current finding needs clinical action and whether repeat testing would genuinely change treatment or family counseling.

A low activity percentage alone does not automatically require lifelong anticoagulation or antithrombin concentrate; treatment depends on previous thrombosis, the provoking circumstances, bleeding risk and the confirmed diagnosis. New one-sided leg swelling needs prompt assessment, while sudden shortness of breath, chest pain or fainting requires emergency care even if the last activity was 100%—do not wait for a repeat thrombophilia panel.
Kantesti is an AI lab test interpretation service that can help organize the 2-stage workflow of context review followed by clinician-directed confirmation, not replace hematology advice or authorize medication interruption. Our 负责任 AI 原则 describe that boundary; use AI explanations to prepare precise questions, including which enzyme the assay uses and whether activity and antigen should be collected together.
The clinical recommendations here draw on 3 directly relevant external sources: the ISTH laboratory communication, the BSH testing guideline and the ASH thrombophilia guideline. The 2 Zenodo publications below provide background on serum proteins and immune-related laboratory context—not clinical trials validating antithrombin diagnosis; our 医疗内容标准 和 补体和自身免疫检测指南 help readers distinguish supporting education from condition-specific evidence.
常见问题解答
抗凝血酶活性低就一定意味着遗传性缺乏吗?
0 低抗凝血酶活性并不总意味着遗传性缺乏。在急性血栓形成、肝素治疗、严重疾病、晚期肝病或大量尿蛋白丢失期间,活性可降至 60%。临床医生会先评估这些获得性原因,再通过在适当时间分别采集的样本确认是否持续降低。抗原检测,有时还有 SERPINC1 检测,有助于对已确认的异常进行分类。.
血栓形成后应在何时重复进行抗凝血酶活性检测?
急性血栓形成后,英国血液学会建议在接受抗凝治疗 3 个月后再检测天然抗凝物质缺乏。实际采样计划还必须考虑恢复情况、所使用的抗凝药物以及实验室检测方法。这项建议并不意味着每个人都应在 3 个月时停药。未经开具处方的临床医生指示,切勿为进行检测而中断抗凝治疗。.
抗凝血酶抗原与活性有什么区别?
抗凝血酶活性测量的是功能,而抗凝血酶抗原测量的是蛋白质含量。I 型缺乏通常会使两项结果均降低;II 型缺乏通常会使活性降低,而抗原相对正常。例如,复测活性为 52%、抗原为 101%,提示存在定性异常模式,但在排查获得性疾病和药物影响之前,尚不能确定其为遗传所致。抗原检测不能替代有效的功能评估。.
Can apixaban or rivaroxaban affect antithrombin results?
Apixaban and rivaroxaban can falsely increase antithrombin activity in factor Xa-based assays, potentially hiding deficiency. Dabigatran can similarly increase apparent activity in thrombin-based assays. A result of 100% while taking an interfering drug may therefore be less reassuring than it appears. The laboratory may choose a less-affected method or another validated strategy; stopping medication yourself is unsafe.
Is antithrombin activity of 70% dangerous?
Antithrombin activity of 70% is below many adult laboratory reference intervals, but the percentage alone does not establish an emergency or quantify personal clot risk. Its meaning depends on the assay, medications, previous clots, family history and current illness. An isolated result usually needs clinical review and a plan for appropriate confirmation. Sudden breathlessness, chest pain, fainting or new one-sided leg swelling requires assessment independently of that percentage.
Should my family be tested if I have antithrombin deficiency?
Selective family testing may be appropriate after inherited antithrombin deficiency has been convincingly confirmed, particularly when results would change prevention, hormone choices or pregnancy planning. A heterozygous carrier generally has a 50% chance of passing the relevant variant to each child, but this is not a 50% certainty that the child will develop thrombosis. BSH and ASH guidance support decision-focused evaluation rather than indiscriminate testing of every relative. Children need age-appropriate interpretation and discussion of whether testing changes care now.
获取血液检查结果解读
上传您的实验室报告,Kantesti 的 AI 会在几秒内用通俗语言解释每项生物标志物。全球已有超过 200 万人使用。.
参考
- Klein, T., Mitchell, S., & Weber, H. (2026). 血清蛋白指南:球蛋白、白蛋白与 A/G 比值血液检查。. Kantesti AI 医学研究。. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). C3 C4 补体血液检测与 ANA 滴度指南。. Kantesti AI 医学研究。. DOI
- Van Cott EM et al. (2020). Recommendations for clinical laboratory testing for antithrombin deficiency; Communication from the SSC of the ISTH. Journal of Thrombosis and Haemostasis. DOI
- Arachchillage DJ 等(2022)。. 血栓倾向检测:英国血液学会指南。. 《英国血液学杂志》。. DOI
- Middeldorp S 等(2023)。. 美国血液学会 2023 年静脉血栓栓塞症管理指南:血栓倾向检测。. 《Blood Advances》。. DOI
- 200万+分析的检测项目
- 127+国家
- 100+语言
关于医疗团队


E-E-A-T信任信号
经验
由医生主导的临床审阅:实验室解读工作流程。.
专业知识
实验室医学重点:生物标志物在临床情境中的表现。.
权威
经 Thomas Klein 医生医学审核,并由 Sarah Mitchell 医生和 Hans Weber 教授参与撰写。.
可信度
基于循证的解读,并提供清晰的后续路径以减少警报。.






医疗免责声明
本文仅用于教育目的,不构成医疗建议。诊断和治疗决策请始终咨询合格的医疗专业人员。.
发表 · 联系编辑团队
由 Kantesti Ltd 发布,在英格兰和威尔士注册,注册公司编号:. 17090423, ,英国伦敦。.
