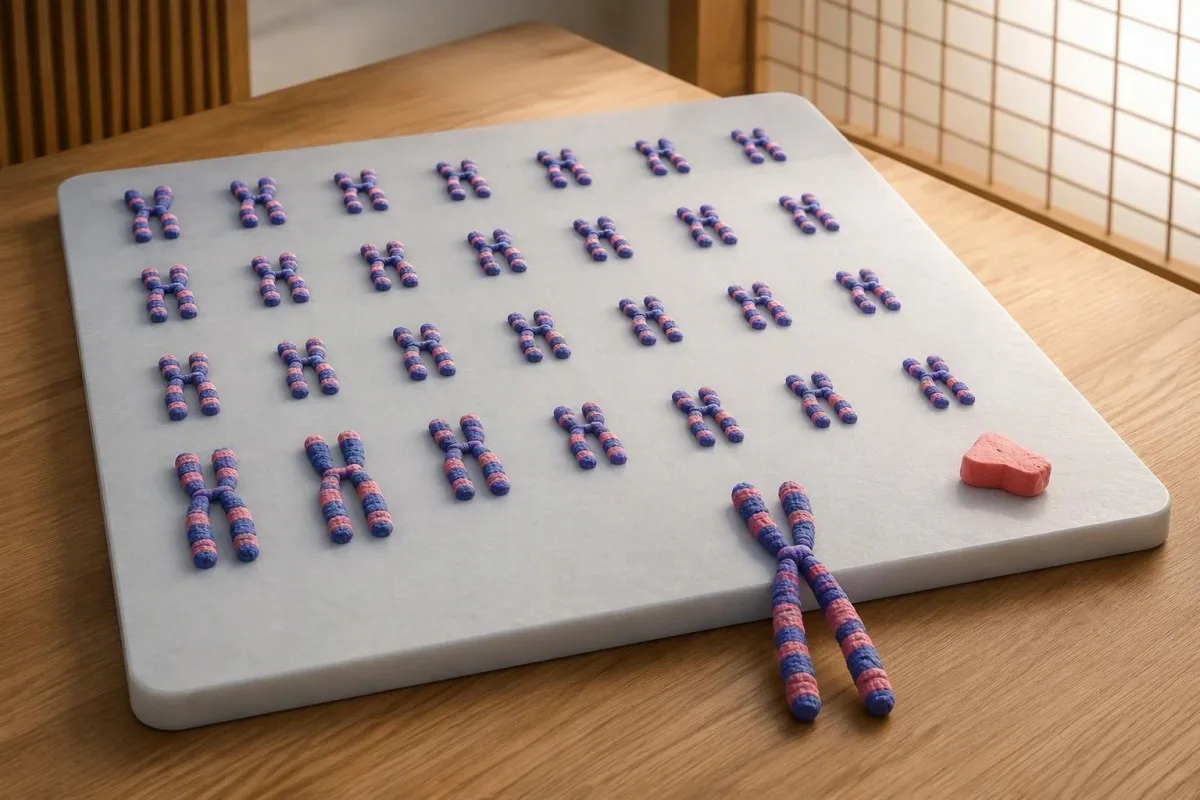
A chromosome result can confirm the diagnosis without predicting every health outcome. The specimen, cell count, and reason for testing all change how the report should be read.


- Turner syndrome test usually means a peripheral-blood karyotype examining at least 30 metaphase cells, interpreted alongside clinical findings.
- 45,X chromosome result means the examined cells contain 45 chromosomes, including one X chromosome; it does not describe intelligence or predict every complication.
- Mosaic Turner syndrome means at least two chromosome cell lines are present, such as 45,X and 46,XX; their proportions can differ between tissues.
- Normal blood karyotype reduces the likelihood of Turner syndrome but may miss low-level or tissue-limited mosaicism when clinical suspicion remains strong.
- Negative prenatal screening does not exclude Turner syndrome because cell-free DNA screening is not diagnostic and partly reflects placental chromosome patterns.
- Additional testing may include more cells, targeted FISH, or a second tissue specimen when a genetics specialist identifies a specific unresolved question.
- Cardiovascular assessment follows confirmation even in apparently mild mosaic cases; normal routine blood tests do not exclude aortic or valve abnormalities.
- Long-term surveillance includes kidney imaging, growth and pubertal assessment, hearing checks, and age-appropriate thyroid, glucose, liver, celiac, and bone monitoring.
Which Turner syndrome test confirms the diagnosis?
The usual confirmatory Turner syndrome test is a blood karyotype, interpreted with clinical findings. A 45,X result identifies cells with one X chromosome; mosaic Turner syndrome identifies different chromosome cell lines, such as 45,X/46,XX. A negative prenatal screen does not exclude either pattern, and confirmation should lead to cardiovascular, kidney, growth, hormonal, and hearing assessments.
The 2024 international guideline recommends examining at least 30 metaphase cells as the first-line chromosome analysis for suspected Turner syndrome (Gravholt et al., 2024). The laboratory counts chromosomes and examines their structure, so a normal complete blood count, thyroid result, or hormone panel cannot substitute for this investigation—even when all those results look reassuring.
Kantesti is an AI blood test analyzer that can help explain accompanying laboratory results, but it cannot confirm a chromosome diagnosis. ئۇچۇر our clinical focus explains our role; chromosome identification requires a cytogenetics laboratory, and reports describing 45,X, a structural X change, or mosaicism need interpretation by the treating clinician or genetics team.
My clinical emphasis, as Thomas Klein, MD, is to separate 2 questions: “What chromosome pattern was found?” and “What care does this person need?” A related sex-chromosome karyotype explanation illustrates the same distinction, although Turner syndrome involves different chromosome findings and a different surveillance pathway.
When should unexplained growth or puberty prompt testing?
Unexplained short stature, delayed puberty, primary amenorrhea, or certain congenital findings can justify a Turner syndrome karyotype. Testing should not depend on a webbed neck or other recognizable appearance; some people with mosaic Turner syndrome first come to attention during adolescent hormone assessment or an adult fertility investigation.
A girl whose height is below approximately −2 standard deviations, or whose growth trajectory is falling away from her family’s expected pattern, needs a clinical growth assessment rather than an automatic diagnosis. Turner testing may be appropriate even when growth hormone measurements are normal, because reduced growth can arise from chromosome-related mechanisms rather than classic growth hormone deficiency.
Absent breast development by around 13 years, or no first period by 15 يىل, warrants assessment for delayed puberty or primary amenorrhea; these are investigation triggers, not Turner-specific diagnostic cutoffs. Our guide to teenage hormone assessment explains why age, development, nutrition, and the laboratory’s pediatric reference intervals must be considered together.
مىسال سۈپىتىدە 14 ياشلىق with short stature and little pubertal development: a high FSH result may suggest reduced gonadal function, but it cannot establish the chromosome cause. I would also ask about congenital heart findings, repeated ear problems, neonatal hand or foot swelling, family heights, and previous genetic testing before deciding which investigations answer the actual clinical question.
What does a 45,X chromosome result actually mean?
A 45,X chromosome result means that the reported cell line contains 45 chromosomes, including one X chromosome rather than two sex chromosomes. In an appropriate clinical context, this supports Turner syndrome; the notation describes the examined cells, not a complete inventory of every cell in the person’s body.
Most human somatic cells contain 46 chromosomes: 22 pairs of autosomes and 2 sex chromosomes. Turner syndrome can result from complete or partial absence of a second sex chromosome, so a report need not say exactly 45,X to be clinically relevant; structural X findings require assessment of the missing or altered material.
SHOX gene dosage helps explain why short stature can occur: this gene lies in a region normally represented on both sex chromosomes, and losing one functional copy can affect growth. Chromosome count is therefore different from a hormone concentration; our explanation of result types and measurements helps readers distinguish descriptive findings from numerical laboratory ranges.
A report stating 45,X in 30 examined cells does not prove that no 46,XX cells exist elsewhere, and it does not mean that every Turner-associated complication will develop. Intelligence is usually within the normal range, although some people benefit from assessment of visuospatial skills, mathematics, attention, or social cognition—needs that cannot be read directly from the chromosome notation.
How is mosaic Turner syndrome different from 45,X?
Mosaic Turner syndrome means that at least 2 genetically different cell lines are present in the same person. A common example is 45,X/46,XX, but other combinations occur; a second cell line may contain a structural X change or Y chromosome material rather than an entirely typical 46,XX complement.
If a laboratory finds 8 cells with 45,X and 22 with 46,XX, the observed 45,X proportion is about 27% in that analyzed sample. That percentage is not the percentage of the whole body “affected,” and it is not a reliable numerical forecast of height, fertility, heart risk, or future hormone requirements.
Spontaneous puberty and menstruation are more likely in some 45,X/46,XX groups than in nonmosaic 45,X groups, but neither outcome is guaranteed for an individual. A person may have periods initially and later develop ovarian insufficiency; FSH elevation and its causes can help explain that hormonal change without pretending that one FSH measurement predicts its timing.
The distribution of 2 cell lines can differ between blood, skin, and other tissues, which is one reason outward appearance and blood percentages do not always match. I would not describe mosaic Turner syndrome as automatically “mild”: the practical question is which complications have been excluded through assessment, not whether the chromosome report contains a reassuring-looking second line.
Can a normal blood karyotype miss mosaicism?
A normal blood karyotype can miss low-level or tissue-limited mosaicism, particularly when the clinical picture remains strongly suggestive. Examining more cells improves the chance of detecting a minority cell line in the sampled tissue, but no finite blood-cell count proves that every other tissue has the same chromosome pattern.
Under a simplified independent-sampling model, finding no abnormal cells among 30 cells excludes a cell line occurring at roughly 10% or more with about 95% confidence. This is the statistical basis behind traditional mosaicism-exclusion tables, not a guarantee of diagnostic sensitivity in every patient (Hook, 1977); culture conditions and tissue differences can weaken the model’s assumptions.
At the same 95% confidence level, examining 60 negative cells corresponds to approximately a 5% upper bound, and 100 corresponds to approximately 3%, if sampling assumptions hold. The formula is 1 − 0.05^(1/n), where n is the number examined; it describes uncertainty within a specimen, not the chance that a person does or does not have Turner syndrome.
Kantesti is an AI lab test interpretation service that can help organize accompanying results, but a normal chemistry panel cannot resolve chromosome mosaicism. بىزنىڭ سۈنئىي ئىدراك تېخنىكىسى چۈشەندۈرۈشى describes a different task from cell counting; if a report says 46,XX in 30 cells, the next decision still depends on the referral indication and specialist assessment.
Why does a negative prenatal screen not exclude Turner syndrome?
A negative prenatal screen does not exclude Turner syndrome because screening estimates risk rather than establishing a fetal chromosome diagnosis. Cell-free DNA screening analyzes a mixture dominated by maternal DNA, with a pregnancy-associated component largely originating from the placenta; fetal mosaicism, placental differences, and assay limitations can produce discordant results.
Not every prenatal panel includes sex-chromosome aneuploidy, so “low risk” may refer only to trisomies 21, 18, and 13. The original report matters more than a remembered phone message: check which conditions were screened, whether monosomy X was included, and whether the laboratory reported a result or an uninterpretable sample.
Positive monosomy X screens also require caution: a clinical review described a pooled positive predictive value of about 26%, with substantial variation between studies and populations (Dowlut-McElroy et al., 2022). That number concerns positive screens, not sensitivity or the reassurance provided by a negative screen; it must not be used to calculate a particular pregnancy’s residual risk.
A later child with unexplained short stature or delayed puberty still deserves assessment despite an earlier “negative” prenatal result. An ordinary urine pregnancy result answers an even narrower question—it detects hCG, not chromosomes—and neither a normal ultrasound nor any single screening result can rule out all forms of 45,X mosaicism.
Which prenatal diagnostic tests clarify a suspected chromosome finding?
Chorionic villus sampling and amniocentesis can provide specimens for diagnostic chromosome testing, following counseling about their benefits, limitations, and procedure-related risks. Amniocentesis may be particularly useful when placental mosaicism is a concern because it samples a different source of pregnancy-associated cells from chorionic villus sampling.
CVS is usually performed in the first trimester, commonly around 11–14 weeks, whereas amniocentesis is generally performed from 15 weeks onward. A maternal-fetal medicine specialist should explain local timing and laboratory methods; the deciding issue is not simply which procedure is earlier, but which specimen can best resolve the suspected chromosome discrepancy.
A mosaic finding in chorionic villi may reflect confined placental mosaicism rather than the same pattern throughout the fetus. When 2 cell lines are reported, counseling may include whether cultured and uncultured preparations differ, whether amniocentesis is warranted, and what uncertainty remains even after additional testing—questions that are easily lost in a one-line summary.
Maternal chromosome testing can sometimes explain a positive cell-free DNA monosomy X result, but maternal findings do not automatically establish or exclude a fetal diagnosis. Keep the complete original report: our PDF تېكىستىنى تەكشۈرۈش تىزىملىكى is especially relevant when punctuation, brackets, or the distinction between 45,X and 46,XX could be altered during document extraction.
When do FISH, another tissue, or Y-material testing help?
Specialist-directed additional testing helps when the initial karyotype leaves a clinically meaningful question unanswered. Options can include counting more blood cells, targeted FISH, chromosome analysis of another tissue, or testing for Y chromosome material; these approaches are not interchangeable and should not be ordered as an indiscriminate “more is better” panel.
FISH uses fluorescent probes directed at selected chromosome regions, allowing laboratories to examine many nuclei for a defined target. A probe can help investigate a suspected minority cell line or unidentified marker chromosome, but a normal targeted result does not exclude every structural abnormality; even examining 100 nuclei only answers the question addressed by that particular assay.
If a 46,XX blood result conflicts with a strong Turner phenotype, a geneticist may consider buccal cells or skin-derived cells, depending on the suspected finding and validated laboratory methods. Chromosomal microarray can clarify some copy-number changes but may miss low-level mosaicism or balanced rearrangements; repeating blood testing alone cannot settle a chromosome pattern restricted to another tissue.
سىناق Y chromosome material is particularly relevant when a marker chromosome needs identification or a 45,X finding accompanies virilization; the 2024 guideline supports molecular investigation in that latter setting (Gravholt et al., 2024). Detection requires specialist discussion of gonadal growth risk and individualized management—not automatic surgery from an app; Kantesti AI’s كلىنىكىلىق ئۆلچەم ۋە چەكلىمىلەر should not be confused with cytogenetic validation.
Which heart and aortic checks follow confirmation?
Every confirmed Turner syndrome diagnosis warrants cardiovascular assessment, including people with mosaic findings and few outward features. Initial evaluation generally includes echocardiography and blood-pressure assessment; cardiovascular MRI is also recommended for newly diagnosed adolescents and adults, with timing and follow-up determined by age, findings, and clinical feasibility.
The 2024 guideline recommends cardiovascular MRI, in addition to or instead of initial echocardiography, for newly diagnosed adolescents and adults, ideally within 12 ئاي when appropriate (Gravholt et al., 2024). MRI can identify aortic and venous anatomy that echocardiography may not fully show; for children, MRI timing can depend on the ability to complete the study without general anesthesia.
Blood pressure should be assessed annually, preferably with ambulatory monitoring when available, because hypertension can amplify aortic risk and may be missed by a single office reading. Our discussion of hypertension assessment explains laboratory clues to other causes, but normal electrolytes or kidney markers do not eliminate Turner-associated cardiovascular surveillance.
Low-risk adults with an entirely reassuring initial evaluation may have imaging intervals of roughly 5–10 years, while abnormalities, pregnancy planning, or changing measurements require closer follow-up. Aortic size must be interpreted with body-size-aware methods; sudden severe chest, back, or neck pain, collapse, or new breathlessness needs emergency assessment rather than waiting for a chest-pain blood panel.
Why check kidney anatomy when creatinine is normal?
A renal ultrasound is recommended at Turner syndrome diagnosis because kidney anatomy and kidney function are different questions. A horseshoe kidney, unusual position, or collecting-system difference can exist despite a normal creatinine result; imaging establishes anatomy, while blood and urine tests assess function and selected complications.
بىر ئادەم 2 functioning kidney components joined in a horseshoe configuration without an abnormal estimated filtration rate. The reason to identify the anatomy is practical: it can change the assessment of urinary symptoms, drainage problems, stones, and blood pressure rather than merely adding another label to the medical record.
Creatinine-based eGFR does not show kidney shape, and its interpretation depends partly on muscle mass and the equation used. Our metabolic panel kidney guide explains that limitation; children require age-appropriate assessment, and an adult eGFR automatically printed beside a child’s result should not be accepted without checking the laboratory’s method.
If imaging identifies a significant renal anomaly, the clinician may add periodic urinalysis or protein assessment and tailor repeat imaging to symptoms; an annual proteinuria check is recommended for selected anomalies in the 2024 guidance. Repeated urinary symptoms, unexplained hypertension, or a change in renal markers should prompt review rather than assuming that a reassuring scan from childhood answers every later question.
Which thyroid, celiac, glucose, and liver tests come next?
Turner syndrome follow-up includes age-appropriate surveillance for thyroid disease, celiac disease, diabetes, and liver abnormalities. These tests monitor associated health risks rather than confirm the chromosome diagnosis; the 2024 international guideline provides starting ages and intervals, with earlier or more frequent investigation when symptoms or previous abnormalities justify it.
TSH screening is recommended every 1–2 years from age 2, with additional investigation for symptoms or abnormal results (Gravholt et al., 2024). Free T4 and, when appropriate, thyroid antibodies answer different follow-up questions; our thyroid test چۈشەندۈرۈشى helps distinguish hormone production from the pituitary signal that stimulates it.
Celiac screening generally uses tissue-transglutaminase IgA plus total IgA, beginning around age 2 and repeating every 2–5 years, or sooner for relevant symptoms. A low total IgA can make an IgA-based screen misleading, and avoiding gluten before testing can reduce sensitivity; the gluten-before-testing guide explains why dietary changes should be discussed before drawing conclusions.
HbA1c or fasting glucose and liver enzymes are generally checked every 1–2 years from age 10, with the exact panel and response tailored to the individual. Kantesti AI can help display these longitudinal results, but a reassuring HbA1c does not rule out every glucose abnormality, and a raised ALT should be investigated rather than automatically attributed to weight or to Turner syndrome itself.
How are growth, puberty, bones, and hearing assessed?
Growth, pubertal development, bone health, and hearing need planned assessment after Turner syndrome confirmation. Growth hormone treatment may help selected children even without classic growth hormone deficiency, while estrogen replacement may support puberty and skeletal health when endogenous hormone production is insufficient; neither treatment should be chosen from the chromosome percentage alone.
The 2024 guideline supports considering growth hormone from about age 2 when growth failure, short stature, or likely short adult height justifies treatment (Gravholt et al., 2024). A childhood growth hormone evaluation answers a related but different question; baseline growth, family height, treatment burden, and monitored response all matter more than a single IGF-1 value.
For girls with evidence of ovarian insufficiency, low-dose estrogen often begins around age 11–12, with gradual increases to imitate normal pubertal progression. Bone density assessment is generally obtained after growth completion and before age 21, then often every 5–10 years in adults; bone-loss investigations complement DXA, whose interpretation must account for short stature and smaller bone size.
Hearing assessment is generally recommended every 2–3 years in childhood and adolescence and every 5 years in adulthood, or sooner for symptoms (Gravholt et al., 2024). Hearing difficulties can be mistaken for poor concentration or school problems, so educational support should consider audiology alongside learning needs; vitamin D, dental care, and psychosocial support also belong in the follow-up plan.
What do mosaic results mean for fertility and pregnancy?
Mosaic chromosome findings may increase the possibility of spontaneous ovarian function, but they do not establish fertility or pregnancy safety. Menstrual history, hormone results, ovarian-reserve assessment, and specialist counseling address reproductive potential; cardiovascular evaluation answers the separate question of whether pregnancy would pose an unacceptable maternal risk.
AMH can help assess ovarian reserve, but there is no single Turner-specific AMH value that guarantees spontaneous conception or a successful preservation procedure. A mosaic proportion of 20% or 80% in blood cannot replace reproductive assessment; our explanation of low AMH interpretation describes why age, assay, treatment history, and the clinical purpose of testing affect interpretation.
A person who menstruates spontaneously may still face a shorter reproductive window, so fertility counseling should not be postponed until 12 months of unsuccessful trying if ovarian insufficiency is already suspected. Selected patients may consider fertility preservation, but suitability and expected benefit vary; an IVF laboratory assessment provides information without resolving the cardiovascular risks of carrying a pregnancy.
Donor eggs do not remove Turner-associated pregnancy risks, because those risks arise partly from the pregnant person’s cardiovascular anatomy and physiology. Preconception cardiac imaging is generally recommended within 2 years before a planned pregnancy or assisted reproduction, with additional assessment as indicated; some aortic findings make pregnancy inadvisable, and estrogen replacement itself should not be assumed to provide contraception.
Research publications and a practical follow-up checklist
After confirmation, the useful next step is a coordinated specialist plan—not repeated chromosome testing without a clinical question. As of October 12, 2026, the 2024 international Turner syndrome guideline is the principal contemporary guideline cited here; the accompanying general laboratory publications below are educational resources, not evidence that a blood-analysis tool can diagnose Turner syndrome.
Kantesti is an AI biomarker interpretation platform that can help organize the laboratory part of a Turner follow-up plan. Bring 3 practical records to the next visit: the complete cytogenetic report, previous heart and kidney imaging reports, and a dated list of medications and laboratory results; chromosome notation, specimen source, and cells counted should remain attached to the original report.
General laboratory publications should be read within their scope: the iron-panel interpretation guide concerns iron status, not chromosome confirmation. The قان ئۇيۇشنى تەكشۈرۈش يېتەكچىسى discusses clotting assays, which are not routine Turner diagnostic tests; their 2 supplied Zenodo DOIs are listed below with title-first APA citations and clearly identified repository-search links.
Editorial perspective from Thomas Klein, MD: ask who will coordinate genetics, endocrinology, cardiology, and primary care, and when the first follow-up review will occur. Kantesti’s داۋالاشقا ئائىت مەسلىھەت ئۇچۇرلىرى describes our clinical oversight context, but this draft does not assert an individual reviewer’s sign-off; before publication or clinical use, recommendations and any personal management plan require documented physician review.
دائىم سورايدىغان سوئاللار
تېرنېر ئۇنىۋېرسال كېسەللىكىنى قايسى قان تەكشۈرۈشى جەزملەشتۈرىدۇ؟
گۇمان قىلىنغان تۇرنېر ئۇنىۋېرسال كېسەللىكىنى دەسلەپكى قەدەمدە جەزملەشتۈرۈش ئۈچۈن ئادەتتە قوشۇمچە قان كايروتىپى تەكشۈرۈلىدۇ ۋە نەتىجىسى كلىنىكىلىق بايقاشلار بىلەن بىرلىكتە ئىزاھلىنىدۇ. 2024-يىللىق خەلقئارا كۆرسەتمە كەم دېگەندە 30 مېتافازا ھۈجەيرىسىنى تەكشۈرۈشنى تەۋسىيە قىلىدۇ. بۇ ئانالىز 45,X نى، موزايكىلىق ھۈجەيرە لىنىيەلىرىنى ۋە X خروموسومىنىڭ بەزى قۇرۇلمىلىق نورمالسىزلىقلىرىنى ئېنىقلىيالايدۇ. ئادەتتىكى ھورمون تەكشۈرۈشلىرى، تولۇق قان تەكشۈرۈش ۋە سۈنئىي ئەقىل تەجرىبىخانا ئىزاھاتى خروموسوما دىياگنوزىنى بېكىتەلمەيدۇ.
45,X نەتىجىسى ھەمىشە تۇرنېر ئۇنىۋېرسال كېسەللىكىنى بىلدۈرەمدۇ؟
مۇۋاپىق كلىنىكىلىق شارائىتتا تۇغما 45,X خىروموسوما نەتىجىسى تۇرنېر ئۇنىۋېرسال كېسەللىكىنى قوللايدۇ، ئەمما ئەۋرىشكە، ياش، ھۈجەيرە سانى ۋە تەكشۈرۈش سەۋەبى تەكشۈرۈپ چىقىلىشى كېرەك. بۇ ئىزاھاتتا دوكلات قىلىنغان ھۈجەيرە تۈرىدە بىر X خىروموسومىنى ئۆز ئىچىگە ئالغان 45 خىروموسوما بارلىقى كۆرسىتىلىدۇ. ياشانغان قۇرامىغا يەتكەنلەردە 45,X ھۈجەيرىلىرىنىڭ ئىنتايىن ئاز بولۇشى بەزىدە ئىلگىرى بايقالمىغان تۇغما تۇرنېر ئۇنىۋېرسال كېسەللىكىدىن كۆرە، ياشنىڭ چوڭىيىشىغا مۇناسىۋەتلىك X خىروموسومىنىڭ يوقىلىشىنى ئەكس ئەتتۈرۈشى مۇمكىن. كۈتۈلمىگەن دەرىجىسى تۆۋەن بايقاشلارغا دىئاگنوزنى پەقەت ئىزاھاتقا قاراپ قويماستىن، گېنتىكا مۇتەخەسسىسى باھا بېرىشى كېرەك.
نورمال كاريوتىپ موزايكى تۇرنېر ئۇنىۋېرسال كېسەللىكىنى يوققا چىقىرالامدۇ؟
نورمال قان كاريوتىپى Turner syndrome نىڭ ئېھتىماللىقىنى تۆۋەنلىتىدۇ، ئەمما تۆۋەن نىسبەتلىك ياكى پەقەت بەزى توقۇلمىلاردا كۆرۈلىدىغان موزايكىلىق ئەندىزىلەرنىڭ ھەممىسىنى يوققا چىقارمايدۇ. ئاددىيلاشتۇرۇلغان ئەۋرىشكە ئېلىش پەرەزلىرى ئاستىدا، 30 دانە مەنپىي ھۈجەيرە شۇ ئەۋرىشكىدىكى تەخمىنەن 10% لىك ئاز سانلىق ھۈجەيرە لىنىيەسىنى 95% ئىشەنچ دەرىجىسى بىلەن يوققا چىقىرىدۇ. بۇ ھېساب باشقا توقۇلمىلاردىكى خروموسوم ئەندىزىلىرىنى چۈشەندۈرمەيدۇ، شۇنداقلا تەجرىبىخانىدىكى ئەۋرىشكە ئېلىش ۋە ھۈجەيرە يېتىشتۈرۈشنىڭ تەسىرىگە ئۇچرايدۇ. كلىنىكىلىق گۇمان كۈچلۈك ۋە داۋاملىق بولسا، مۇتەخەسسىس يېتەكچىلىكىدە قوشۇمچە تەكشۈرۈش ئېلىپ بېرىشقا ئاساس بولالايدۇ.
NIPT تېرنېر ئۇنىۋېرسال كېسەللىكىنى بايقىماي قالامدۇ؟
0] ھەئە، NIPT دەپمۇ ئاتىلىدىغان ھۈجەيرەسىز DNA تەكشۈرۈشى تۇرنېر ئۇنىۋېرسال كېسەللىكىنى بايقىماي قېلىشى مۇمكىن، شۇنداقلا خەۋپى تۆۋەن نەتىجىدىن كېيىن ئۇنى يوققا چىقىرالمايدۇ. بەزى تەكشۈرۈش تاختىلىرى پەقەت 21، 18 ۋە 13-خروموسوم ترىسومىيەسىنى تەكشۈرىدۇ ۋە X مونوسومىيەسىنى ئۆز ئىچىگە ئالمايدۇ. X مونوسومىيەسى ئۆز ئىچىگە ئېلىنغان تەقدىردىمۇ، ھامىلىدىكى موزايكىلىق، بالا ھەمرىيىدىكى پەرقلەر ۋە تەكشۈرۈش ئۇسۇلىنىڭ چەكلىمىلىرى نەتىجىلەرنىڭ بىر-بىرىگە ماس كەلمەسلىكىنى كەلتۈرۈپ چىقىرىشى مۇمكىن. ھامىلىدارلىق مەزگىلىدىكى بايقاشلار ياكى كېيىنكى ئۆسۈپ يېتىلىش ۋە بالاغەتكە يېتىش مەسىلىلىرى سەۋەب بولغاندا، خروموسوما دىئاگنوزلۇق تەكشۈرۈشى يەنىلا كۆزدە تۇتۇلۇشى كېرەك.
موزائيكلىق نىسبىتى تۇرنېر ئۇنىۋېرسال كېسەللىكىنىڭ قانچىلىك ئېغىر بولىدىغانلىقىنى ئالدىن مۆلچەرلىيەلەمدۇ؟
0 قان ئەۋرىشكىسىدىكى موزائىكىلىقنىڭ نىسبىتى شەخستە تېرنېر ئۇنىۋېرسال كېسەللىكىنىڭ ئېغىرلىقىنى ئىشەنچلىك پەرەز قىلدۇرمايدۇ. تەھلىل قىلىنغان 30 ھۈجەيرىنىڭ ئىچىدىن 45,X بولغان 8 ھۈجەيرىنىڭ تېپىلىشى، شۇ ئەۋرىشكىدە كۆزىتىلگەن نىسبەتنىڭ تەخمىنەن 27% ئىكەنلىكىنى بىلدۈرىدۇ، پۈتۈن بەدەننىڭ 27% ئىكەنلىكىنى ئەمەس. ئوخشىمىغان توقۇلمىلاردا بۇ نىسبەت ئوخشىماسلىقى مۇمكىن، قان ئەۋرىشكىسى ئېلىش بولسا ئېنىقسىزلىق پەيدا قىلىدۇ. مەلۇم قىلىنغان 45,X نىسبىتى تۆۋەن بولغان تەقدىردىمۇ، يۈرەك، بۆرەك، ھورمون، ئاڭلاش ۋە ئۆسۈپ يېتىلىشنى باھالاش يەنىلا زۆرۈر.
موزايىك تېرنېر ئۇنىۋېرسال كېسەللىكى بار كىشىدە ھەيز كېلىشى ياكى ھامىلىدار بولۇشى مۇمكىنمۇ؟
موزايكا تۇرنېر ئۇنىۋېرسال كېسەللىكى بار بەزى كىشىلەردە، بولۇپمۇ 45,X/46,XX ھۈجەيرە ئەندىزىسى بولغاندا، ئۆزلۈكىدىن بالاغەتكە يېتىش، ھەيز كۆرۈش ياكى ھامىلىدار بولۇش ئەھۋاللىرى كۆرۈلىدۇ. بۇ ئېھتىماللىقلارنى قاندىكى موزايكىلىق نىسبىتى ياكى بىر قېتىملىق AMH نەتىجىسىگە قاراپ ئىشەنچلىك ئالدىن مۆلچەرلىگىلى بولمايدۇ. تۇغۇش ئىقتىدارى توغرىسىدىكى مەسلىھەت ۋە يۈرەك-قان تومۇرنى باھالاش ئايرىم-ئايرىم تەلەپتۇر؛ پىلانلانغان ھامىلىدارلىق ياكى ياردەمچى كۆپىيىشتىن ئىلگىرىكى 2 يىل ئىچىدە ھامىلىدارلىقتىن بۇرۇنقى يۈرەك تەسۋىرى ئادەتتە تەۋسىيە قىلىنىدۇ. تۇخۇم ھۈجەيرىسىنى ئىئانە قىلغۇچىدىن ئېلىش ھامىلىدارلىققا مۇناسىۋەتلىك يۈرەك-قان تومۇر خەۋپىنى يوقىتالمايدۇ، بەزى ئاورتا بايقاشلىرى ھامىلىدار بولۇشنى تەۋسىيە قىلمايدۇ.
What health checks are needed after Turner syndrome is confirmed?
Confirmed Turner syndrome should prompt cardiovascular evaluation, renal ultrasound, and assessment of growth, puberty, hearing, and other associated risks. Blood pressure should be assessed annually, and thyroid screening is generally recommended every 1–2 years from age 2. Glucose or HbA1c and liver enzyme surveillance generally begin around age 10 at 1–2-year intervals, while celiac screening follows a separate schedule. The treating team should tailor imaging, bone assessment, and repeat testing to age, symptoms, prior findings, and pregnancy plans.
بۈگۈنلا AI بىلەن قان تەكشۈرۈش تەھلىلى ئېلىڭ
دۇنيادىكى 2 مىليوندىن ئارتۇق ئىشلەتكۈچى Kantesti نى دەرھال، توغرا تەجرىبىخانا تەھلىلى ئۈچۈن ئىشەنچ قىلىدۇ. قان تەكشۈرۈش نەتىجىڭىزنى يوللاپ، 15,000+ بىئوماركىرلىرىنىڭ تولۇق چۈشەندۈرۈشىنى بىر نەچچە سېكۇنتتا ئېلىڭ.
📚 پايدىلىنىلغان تەتقىقات ئېلانلىرى
Klein, T., Mitchell, S., & Weber, H. (2026). تۆمۈر تەتقىقات قوللانمىسى: TIBC، تۆمۈرنىڭ تويۇنۇش دەرىجىسى ۋە باغلىنىش ئىقتىدارى. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). aPTT نورمال دائىرىسى: D-Dimer، C ئاقسىلى قان ئۇيۇش قوللانمىسى. Kantesti AI Medical Research.
📖 تاشقى داۋالاش پايدىلىنىش ماتېرىياللىرى
Gravholt CH et al. (2024). Clinical practice guidelines for the care of girls and women with Turner syndrome: proceedings from the 2023 Aarhus International Turner Syndrome Meeting. ياۋروپا ئىچكى كېسەللىكلەر ژۇرنىلى (European Journal of Endocrinology).
Dowlut-McElroy E et al. (2022). Cell-Free DNA Screening Positive for Monosomy X: Clinical Evaluation and Management of Suspected Maternal or Fetal Turner Syndrome. ئامېرىكا بېيىك-جىنىس ژورنىلى.
Hook EB (1977). Exclusion of chromosomal mosaicism: tables of 90%, 95% and 99% confidence limits and comments on use. American Journal of Human Genetics.
⚕️ تېببىي ئەسكەرتىش
بۇ ماقالە پەقەت تەربىيە-ئوقۇتۇش مەقسىتى ئۈچۈن بولۇپ، داۋالاش مەسلىھەتىنى تەشكىل قىلمايدۇ. دىئاگنوز قويۇش ۋە داۋالاش قارارلىرى ئۈچۈن ھەمىشە لاياقەتلىك ساغلاملىق مۇلازىمىتى تەمىنلىگۈچى بىلەن مەسلىھەتلىشىڭ.
E-E-A-T ئىشەنچ سىگناللىرى
تەجرىبە
دوختۇر رەھبەرلىكىدىكى لابوراتورىيە تەبىرىنى چۈشەندۈرۈش خىزمەت ئېقىملىرىنى بالىياتقۇچلۇق تەكشۈرۈش.
مۇتەخەسسىسلىك
بىئوماركىرلارنىڭ كىلىنىكىلىق مۇھىتتا قانداق ھەرىكەت قىلىدىغانلىقىغا مەركەزلەشكەن لابوراتورىيە تېبابىتى.
ھوقۇقدارلىق
دوكتور توماس كلېين تەرىپىدىن يېزىلغان، دوكتور سارا ميتچېل ۋە پروف. دوكتور ھانس ۋېبېر تەرىپىدىن تەكشۈرۈلگەن.
ئىشەنچلىكلىك
ئاگاھلاندۇرۇشنى ئازايتىش ئۈچۈن ئېنىق كېيىنكى قەدەملەر بىلەن ئىسپات-ئاساسلىق تەبىر.