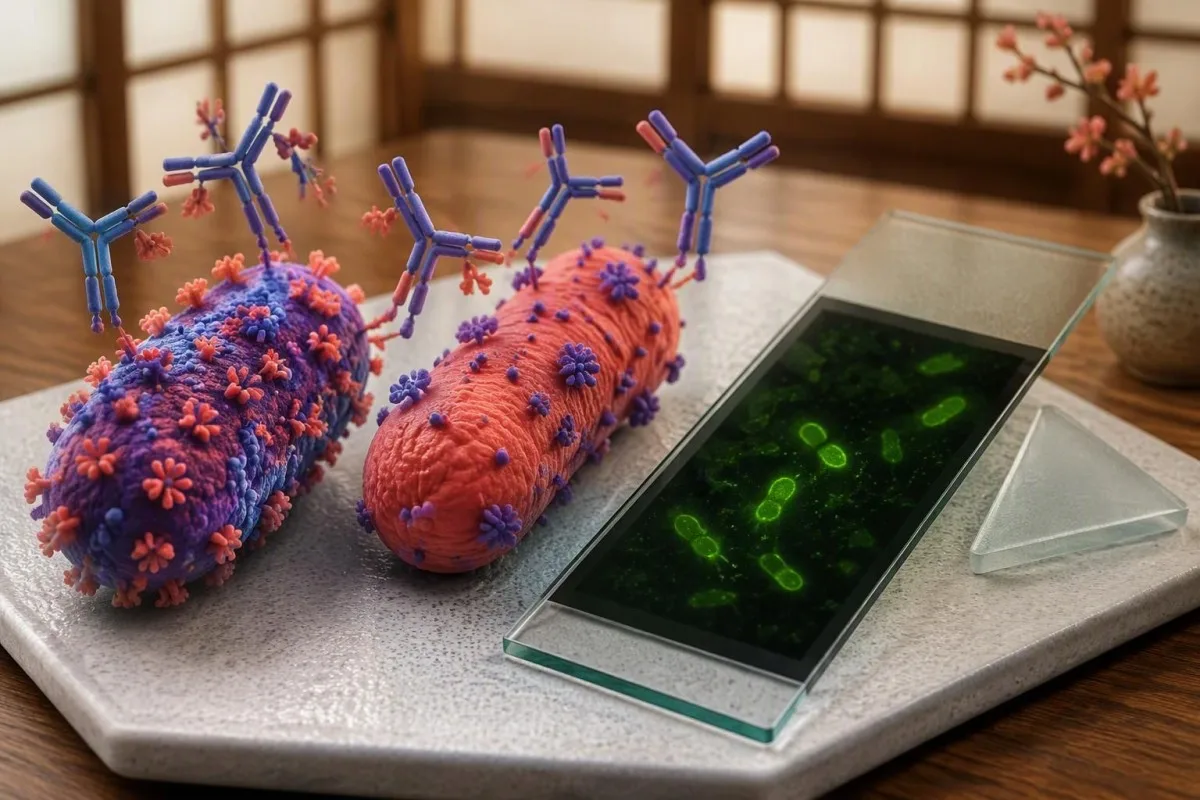
အဆင့် II IgG သည် မကြာသေးမီက ကူးစက်မှုကို မကြာခဏ ထောက်ကူပေးသည်၊ အဆင့် I IgG မြင့်တက်လာခြင်းသည် မေးခွန်းတစ်ခုကို မေးစေသည်။ နမူနာအချိန်၊ ဓာတ်ခွဲနည်းလမ်းနှင့် ခိုင်မာသော အာရုံစူးစိုက်မှု အထောက်အထားတို့က မည်သည့်ရလဒ်ကိုမဆို တကယ်အဓိပ္ပာယ်ဖွင့်ဆိုသည်။.


- Q ဖျားနာမှု ကိုယ်ခံအားများ Coxiella burnetii ကို ကိုယ်ခံအား တုံ့ပြန်မှုကို ဖော်ပြသည်၊ အပြုသဘောဆောင်သော ရလဒ်တစ်ခုသည် တက်ကြွသော ကူးစက်မှုကို တစ်ကိုယ်တည်း မတည်ထောင်နိုင်ပါ။.
- အဆင့် II IgG ပြင်းထန်သော Q ဖျားနာမှုတွင် အများဆုံးဖြစ်လေ့ရှိသည်၊ သို့သော် တစ်ခုတည်းသော အပြုသဘောဆောင်သော တိုင်းတာမှုသည် ယခင် ထိတွေ့မှုကိုလည်း ထင်ဟပ်စေနိုင်သည်။.
- ပူးတွဲနမူနာများ ခန့်မှန်းခြေအားဖြင့် 3–6 ပတ်ခန့်ခြား၍ စုဆောင်းထားသော အဆင့် II IgG တွင် လေးဆတိုးလာမှုကို ပြသပေးနိုင်ပြီး မကြာသေးမီက ကူးစက်မှုကို ထောက်ကူပေးသည်။.
- လေးဆတိုးလာခြင်း 1:64 မှ 1:256 ဟု အဓိပ္ပာယ်ရသည်၊ 1:64 မှ 1:128 မဟုတ်ပါ၊ ယုံကြည်စိတ်ချရသော နှိုင်းယှဉ်မှုအတွက် တူညီသောနည်းလမ်း၊ အကြိုက်ဆုံးမှာ တူညီသောဓာတ်ခွဲခန်း လိုအပ်သည်။.
- အဆင့် I IgG IFA ဖြင့် 1:1024 သို့မဟုတ် ထို့ထက်ပိုသော အဆင့်တွင် ခိုင်မာသော ကူးစက်မှု စုံစမ်းစစ်ဆေးမှုအတွက် CDC-associated အချက်ပြစွမ်းအားဖြစ်သည်၊ ၎င်းသည် မိမိကိုယ်တိုင် ရောဂါခွဲခြားခြင်းမဟုတ်ပါ။.
- ဓာတ်ခွဲခန်း ကန့်သတ်ချက်များ ကွာခြားသည်- ESC endocarditis စံနှုန်းသည် အဆင့် I IgG ကို 1:800 ထက်ပို၍ အသုံးပြုသည်၊ ၎င်းသည် ဓာတ်ခွဲခန်းတိုင်း၏ အစီရင်ခံစာ စကေးနှင့် မလဲလှယ်နိုင်ပါ။.
- စောစီးစွာ PCR ရောဂါဖြစ်ပွားပြီး ပထမ ၂ ပတ်ခန့်အတွင်း၊ အထူးသဖြင့် ပဋိဇီဝဆေးများ မစတင်မီ သို့မဟုတ် မကြာမီတွင် အလွန်အသုံးဝင်ပါသည်။.
- အန္တရာယ် ပိုများသော လူနာများ နှလုံး သွေးကြောရောဂါများ၊ သွေးကြောအစားထိုးခြင်း သို့မဟုတ် သွေးကြော ပွတ်ခြင်းများ၊ ကိုယ်ဝန်ဆောင်ခြင်းနှင့် ခုခံအား ကျဆင်းစေသော အခြေအနေများ ပါဝင်သည်။.
- အရေးပေါ် လက္ခဏာများ အသက်ရှူမဝခြင်း၊ စိတ်ရှုပ်ထွေးခြင်း၊ သတိလစ်ခြင်း သို့မဟုတ် အာရုံကြော ချို့ယွင်းမှု အသစ်များကဲ့သို့သော အရာများသည် ထပ်ခါတလဲလဲ ပဋိပစ္စည်းများ စောင့်ဆိုင်းမည့်အစား ချက်ချင်း အကဲဖြတ်ရန် လိုအပ်ပါသည်။.
Q ဖျားနာမှု ကိုယ်ခံအား အပြုသဘောဆောင်သော ရလဒ်သည် အဘယ်နည်း။
Q ဖျားနာမှု ကိုယ်ခံအားများ Coxiella burnetii ကို ခုခံအား တုံ့ပြန်မှုကို ပြသသည်။ အဆင့် II IgG သည် ပုံမှန်အားဖြင့် မကြာသေးမီ အပြင်းထန်ဆုံး ရောဂါပိုး ကူးစက်မှုတွင် အဓိကဖြစ်သည်၊ အဆင့် I IgG သိသိသာသာ မြင့်မားနေခြင်းသည် တည်တံ့သော အာရုံစူးစိုက်မှု ကူးစက်မှုအတွက် အကဲဖြတ်ရန် လိုအပ်ပါသည်။ မည်သည့် ပုံစံကမျှ ရောဂါ လတ်တလောဖြစ်နေသည်ကို တစ်ခုတည်းဖြင့် မဆုံးဖြတ်နိုင်ပါ- ရောဂါလက္ခဏာများ၊ ဓာတ်ခွဲခန်း-သတ်မှတ်ထားသော ကန့်သတ်ချက်များ၊ တွဲဖက်နမူနာများနှင့် တစ်ခါတစ်ရံ PCR သို့မဟုတ် ရုပ်ပုံရိုက်ခြင်း လိုအပ်ပါသည်။.
အစီရင်ခံစာ တစ်စောင်က Coxiella burnetii IgG အပေါင်းလက္ခဏာ လူနာများ မျှော်လင့်သည်ထက် ပိုမို ကျဉ်းမြောင်းသော မေးခွန်းကို ဖြေပေးသည်- ပဋိပစ္စည်းများကို ထိုစမ်းသပ်မှုဖြင့် ရှာဖွေတွေ့ရှိခဲ့သည်။ ၎င်းသည် မည်သည့်အချိန်တွင် ထိတွေ့မှု ဖြစ်ပွားခဲ့သည်၊ သို့မဟုတ် ပိုးများ တက်ကြွနေသေးသည်၊ သို့မဟုတ် ကုသမှု လိုအပ်သလား၊ ဤသုံးခုသည် သီးခြား ဆေးဘက်ဆိုင်ရာ မေးခွန်းများ ဖြစ်သည်၊ ၎င်းတို့ကို တစ်ခုထဲ ပေါင်းထည့်ခြင်းက မလိုအပ်သော စိုးရိမ်မှုကို ဖန်တီးသည်။.
Thomas Klein, Chief Medical Officer အဖြစ် ကျွန်ုပ် ရေးသားနေသည်၊ ကျွန်ုပ်၏ ပထမဆုံး အစီရင်ခံစာ ဖတ်ရှုသည့် မေးခွန်းမှာ ရလဒ်သည် အရည်အသွေး သို့မဟုတ် အမှန်တကယ် dilution titer ပါဝင်သလား ဖြစ်သည်။ ခြားနားချက်သည် ရလဒ်ဘေးရှိ အနီရောင် အလံထက် ပိုအရေးကြီးသည်- 1:64 နှင့် 1:1024 နှစ်ခုလုံးကို အပေါင်းလက္ခဏာဟု ခေါ်နိုင်သော်လည်း ၎င်းတို့သည် မတူညီသော စကားဝိုင်းများကို ဖြစ်ပေါ်စေသည်။ ကျွန်ုပ်တို့၏ ရှင်းလင်းချက် အပေါင်းလက္ခဏာ antibody ရလဒ်များ ထိုကျယ်ပြန့်သော ကွဲပြားမှုကို ဖြေရှင်းပေးပါသည်။.
Kantesti သည် AI သွေးစစ်ခွဲခြမ်းစိတ် ကိရိယာဖြစ်ပြီး အဆင့်-သတ်မှတ်ထားသော ရလဒ်များကို နမူနာရက်စွဲများနှင့် အခြားဓာတ်ခွဲခန်း တွေ့ရှိချက်များနှင့်အတူ ထားရှိရန် ကူညီပေးသည်၊ 1 ခု ညွှန်ပြထားသော ရလဒ်ကို ရောဂါအဖြစ် သဘောမထားပါ။ အကြောင်းအရာ ကျွန်တော်တို့ အဖွဲ့အစည်းမှာ သည် ဝန်ဆောင်မှု ပတ်ဝန်းကျင်ကို ရှင်းပြသည်၊ သံသယရှိ Q fever သည် ထိတွေ့မှု၊ စစ်ဆေးမှု တွေ့ရှိချက်များနှင့် အထူးပြု စမ်းသပ်မှုများ လိုအပ်မှုကို အကဲဖြတ်နိုင်သော ဆရာဝန်တစ်ဦး လိုအပ်ဆဲဖြစ်သည်။.
Q ဖျားနာမှု အဆင့် 1 နှင့် အဆင့် 2 တို့သည် တကယ်အဘယ်အရာကို ဖော်ပြသနည်း။
Q fever အဆင့် 1 နှင့် အဆင့် 2 Coxiella burnetii ၏ antigen ပုံစံများကို ဖော်ပြသည်၊ လူနာတိုင်း ဖြတ်သန်းရမည့် ၂ ခု ဆက်တိုက် ဖြစ်စဉ်များကို မဟုတ်ပါ။ အဆင့် I ပိုးများသည် ပြည့်စုံသော မျက်နှာပြင် lipopolysaccharide ကို ပိုင်ဆိုင်သည်၊ အဆင့် II antigen သည် ဓာတ်ခွဲခန်း နှင့် လိုက်လျောညီထွေဖြစ်အောင် ပြုလုပ်စဉ် ထုတ်လုပ်သော တိုတောင်းသော ပုံစံကို ထင်ဟပ်စေသည်။.
အဆင့် II IgG သည် အပြင်းထန်ဆုံး Q fever အတွင်း ပိုမို ထင်ရှားစွာ မြင့်တက်လေ့ရှိသည်။, အဆင့် I IgG မြင့်မားခြင်းသည် တည်တံ့သော အာရုံစူးစိုက်မှု ကူးစက်မှုကို အဖော်ပြုနိုင်ပါသည်။ ထိုဆက်နွယ်မှုများသည် အသုံးဝင်သော်လည်း မပြည့်စုံပါ- အပြင်းထန်ဆုံး ရောဂါပိုး ကူးစက်ပြီးနောက် ပဋိပစ္စည်း နှစ်အုပ်လုံးကို မြင့်မားနိုင်ပြီး တည်တံ့သော အာရုံစူးစိုက်မှု ရှိနေသည့်တိုင် အဆင့် II IgG သည် သိသိသာသာ ကျန်ရှိနိုင်သည် (Anderson et al., 2013)။.
ရောမဂဏန်း I နှင့် II တို့ကို အစီရင်ခံစာများတွင် နံပါတ် 1 နှင့် 2 ဖြင့် မကြာခဏ အစားထိုးလေ့ရှိသည်၊ ၎င်းတို့သည် တူညီသော antigen အမျိုးအစားများကို ရည်ညွှန်းသည်။ ၎င်းတို့ကို မရောထွေးသင့်ပါ။ IgG နှင့် IgM, ပဋိပစ္စည်း အတန်းအစားများကို ဖော်ပြသည်။ အထွေထွေ ကိုယ်ခံအားကို အဓိပ္ပာယ်ဖွင့်ဆိုရန် လမ်းညွှန် သည် စုစုပေါင်း IgG ပမာဏနှင့် ပိုး-သတ်မှတ်ထားသော IgG သည် မတူညီသော တိုင်းတာမှုများ ဖြစ်ရသည့် အကြောင်းရင်းကို ရှင်းပြသည်။.
A phase I-to-phase II comparison is a clue, not a standalone classification rule, and there is no universally diagnostic 1:1 ratio. Unlike the named antigen combinations used in EBV antibody patterns, Q fever interpretation depends heavily on endpoint titers, their change over time, and the presence or absence of a focal clinical problem.
Q ဖျားနာမှု ကိုယ်ခံအား တိုင်းတာမှုများနှင့် ဓာတ်ခွဲ ကန့်သတ်ချက်များကို မည်သို့ဖတ်သနည်း။
Q fever antibody titers usually report the highest serum dilution that remains reactive by indirect immunofluorescence, or IFA. A result of 1:256 is higher than 1:64; these are dilution endpoints, not antibody concentrations in mg/dL or IU/mL.
The denominator expresses how far the serum was diluted: 1:256 remains reactive at a greater dilution than 1:64. Laboratories may begin testing at different dilutions and use different antigen preparations or reading procedures, so a positive flag from one laboratory cannot automatically be assigned the clinical meaning used by another laboratory.
Screening positivity and a clinical decision threshold are not the same thing. A laboratory might classify a low endpoint as detectable, while a guideline uses a much higher phase I value to trigger investigation for persistent infection; an ELISA index of 2.4 cannot simply be converted into an IFA titer of 1:1024.
Ask for 3 details: the testing method, the phase-specific endpoints, and the laboratory's interpretive comment. Our discussion of qualitative နှင့် quantitative စမ်းသပ်ခြင်း explains why positive/negative reports cannot show a fourfold rise; if comparison is needed, the clinician may request quantitative IFA through a reference laboratory rather than repeating an unsuitable screening assay.
ပူးတွဲနမူနာများသည် မကြာသေးမီက Q ဖျားနာမှုကို မည်သို့ဖော်ထုတ်ရန် ကူညီသနည်း။
တွဲဆက်ထားသော သွေးရည်ကြည် နမူနာများ can identify recent Q fever by demonstrating a fourfold or greater increase in phase II IgG. The CDC's diagnostic approach compares an acute sample, ideally collected early in illness, with a convalescent sample collected approximately 3–6 weeks later (Anderson et al., 2013).
A rise from 1:64 to 1:256 is fourfold; 1:64 to 1:128 is only twofold. Many IFA methods use doubling dilutions, so a fourfold increase spans 2 dilution steps. That requirement helps distinguish a meaningful antibody rise from small differences in assay reading, although the complete clinical story remains necessary.
Both specimens should preferably go to the same laboratory, using the same method, and may be tested together to reduce run-to-run variation. A 1:128 result from one laboratory followed by 1:256 elsewhere is not reliable evidence of biological progression; our သွေးစစ်ဆေးမှု အချိန်ဇယား လမ်းညွှန် explains why measurement conditions belong on every comparison.
A first specimen collected 4 weeks into illness may already show a high phase II titer, leaving little room for a further fourfold rise. Failure to demonstrate a rise in that situation does not exclude recent infection; the initial sample was simply too late to capture the developing response, and PCR may also have become less sensitive.
At Kantesti, the useful comparison is not just earlier versus later: it is sample date versus symptom-onset date, with antibiotic timing added as a third reference point. Tell the clinician whether the first specimen was taken on day 3 or day 23, and ask whether a stored original specimen can be retested alongside the second sample.
အပြုသဘောဆောင်သော IgG ရလဒ်တစ်ခုသည် ရှေးဦး ကူးစက်မှုကို ကိုယ်စားပြုနိုင်သလား။
One positive Coxiella burnetii IgG result can reflect past exposure, because antibodies may persist for months or years. An isolated phase II IgG result cannot reliably distinguish a recent infection from a remote one, even when the numerical titer looks impressive.
The probability of active Q fever changes with the reason the test was ordered. A phase II titer of 1:256 in someone with recent fever after livestock exposure carries a different implication from the same result in a well person tested during a broad fatigue workup; the laboratory number has not changed, but the pretest probability has.
IgM does not settle the question on its own: it can persist and is generally less specific than IgG in Q fever testing. A positive IgM plus a single positive IgG still needs timing and clinical interpretation, rather than a simple new-infection label; the distinction resembles some issues discussed in CMV IgG interpretation, although the organisms require different diagnostic rules.
A single elevated phase II IgG titer may support a probable acute diagnosis in a clinically compatible case, but the laboratory's reporting framework must be checked. The CDC's 2013 guidance discusses a phase II IgG titer of at least 1:128 as supportive in that setting; it does not make 1:128 a universal diagnostic threshold for every assay or every asymptomatic patient.
အနုတ်လက္ခဏာ ရလဒ်တစ်ခုနောက်ပိုင်းတွင် PCR နှင့် ထပ်ခါတလဲလဲ စမ်းသပ်ခြင်းများသည် အဘယ်အချိန်တွင် အသုံးဝင်သနည်း။
Coxiella burnetii PCR is most useful early in acute illness, often during approximately the first 2 weeks and before or shortly after antibiotics begin. Antibodies are frequently negative during the first week, so an early negative serology result cannot exclude Q fever.
PCR detects bacterial genetic material, whereas IFA measures the host antibody response; those tests therefore have different windows of usefulness. A negative antibody result on day 5 and a positive PCR can be entirely consistent with acute Q fever, and a later positive IgG does not mean the earlier antibody assay malfunctioned.
Antibiotic exposure can reduce PCR sensitivity, and declining circulating bacterial material also limits detection later in illness. A negative PCR on day 18, especially after treatment, does not carry the same exclusionary weight as a well-timed early specimen; timing is similarly central to early dengue testing, although the actual tests and organisms differ.
Clinicians should not delay appropriate treatment for strongly suspected acute Q fever while waiting 3–6 weeks for convalescent antibodies. Record the exact antibiotic start date and ask which specimen type the reference laboratory accepts; serum, whole blood, and tissue testing have different uses, and a late negative blood PCR cannot by itself exclude a persistent focal infection.
မည်သည့် ထိတွေ့မှုများနှင့် လက္ခဏာများသည် Q ဖျားနာမှုကို ပို၍ ဖြစ်စေသနည်း။
Q fever becomes more plausible after exposure to aerosolized material from infected livestock, particularly sheep, goats, or cattle and their birth products. Acute illness commonly begins about 2–3 weeks after exposure and may cause fever, severe headache, pneumonia, or hepatitis without a distinctive rash.
Directly touching an animal is not required for Q fever exposure, because contaminated dust can be inhaled. A useful 3-week history includes farm visits, veterinary work, abattoir work, lambing or kidding environments, and nearby livestock activity; a patient who says they never handled animals may still have an exposure worth discussing.
Fever after animal contact has more than 1 possible explanation, and broadening the differential can prevent a positive Q fever antibody result from becoming an anchor. Unpasteurized dairy exposure or occupational animal contact may also prompt brucellosis testing interpretation. Freshwater or floodwater exposure may instead strengthen the case for leptospirosis test timing.
An ALT of 180 IU/L with fever may support a hepatitis presentation, but it does not identify Coxiella as the cause; acute Q fever can also occur with a normal white-cell count. Our အသည်းစစ်ဆေးမှု အတိုကောက်လမ်းညွှန် helps separate markers of liver injury from organism-specific testing, and normal routine results should not override a convincing exposure history.
အဆင့် I IgG မြင့်တက်လာသောအခါ အထူးကု ဆရာဝန်၏ အကဲဖြတ်မှုသည် အဘယ်အချိန်တွင် လိုအပ်သနည်း။
Elevated phase I IgG warrants evaluation when it reaches a method-specific concerning threshold, rises over time, or accompanies relevant symptoms or risk factors. CDC guidance uses phase I IgG at least 1:1024 by IFA together with an identifiable persistent focus to diagnose chronic Q fever (Anderson et al., 2013).
Phase I IgG at or above 1:1024 is not a treatment order. Some patients develop substantial phase I responses after acute infection without demonstrable persistent disease, so clinicians look for endocarditis, vascular infection, or another focal site rather than prescribing prolonged therapy based on the number alone; a stable patient usually needs coordinated assessment, not panic.
ဟိ 2023 ESC endocarditis guideline lists a phase I IgG titer greater than 1:800 as a major microbiological criterion for infective endocarditis (Delgado et al., 2023). That criterion belongs within a complete endocarditis evaluation; different dilution series and reference-laboratory methods help explain why 1:800 and 1:1024 appear in different documents without being universally interchangeable.
The Dutch consensus separates proven, probable, and possible chronic Q fever using combinations of serology, PCR, imaging, and clinical risk factors, rather than one antibody result alone (Wegdam-Blans et al., 2012). This is a useful corrective to the idea that antibodies directly measure disease severity, an issue also discussed in high ASO titer interpretation.
A Kantesti explanation should frame a phase I result of 1:2048 as a follow-up trigger, not a declaration of endocarditis. Fever, weight loss, night sweats, a known valve problem, an aortic aneurysm, or a vascular graft changes the urgency; conversely, a result below 1:1024 should not dismiss persistent focal infection when clinical suspicion is substantial.
ဆရာဝန်များသည် ခိုင်မာသော Q ဖျားနာမှုကို မည်သို့ စုံစမ်းစစ်ဆေးကြသနည်း။
Persistent focal Q fever requires a search for an anatomical site of ongoing infection, most often a heart valve or an abnormal vascular site. Evaluation may combine phase-specific IFA, PCR, echocardiography, vascular imaging, and specialist-directed FDG-PET/CT; no single test answers all of these questions.
A normal transthoracic echocardiogram does not exclude Q fever endocarditis, because vegetations may be small or absent and prosthetic material can complicate imaging. Transoesophageal echocardiography may be needed when suspicion remains; 1 reassuring scan should not automatically close the investigation in someone with compatible serology and a high-risk cardiac history.
Vascular grafts and aneurysms create a second major diagnostic pathway, sometimes without obvious cardiac findings. CT angiography or FDG-PET/CT may help identify the relevant focus, while tissue PCR can be informative if material becomes available for clinical reasons; clinicians should not obtain invasive tissue solely because an isolated phase I titer is 1:1024.
Routine blood cultures often remain negative in Q fever endocarditis, so culture-negative disease does not mean there is no infection. Bartonella is another organism considered in this setting, and our Bartonella titer explanation describes why targeted serology differs from ordinary culture; the selected tests depend on exposure history and the broader endocarditis differential.
Tell the laboratory when Q fever is suspected, because Coxiella culture requires specialized facilities and should not be requested casually. Our culture result interpretation guide explains what standard cultures can establish; a negative blood PCR, negative routine cultures, and 1 normal echocardiogram still need to be weighed against the patient's overall risk and imaging findings.
Q ဖျားနာမှု ထိတွေ့မှု သို့မဟုတ် ကူးစက်မှုနောက်ပိုင်းတွင် မည်သူသည် ပိုမိုနီးကပ်စွာ လိုက်နာရန် လိုအပ်သနည်း။
People with valve disease, prosthetic valves, vascular grafts, aneurysms, pregnancy, or certain forms of immunosuppression need closer clinical attention after Q fever. Persistent infection develops in a minority of patients—commonly described as fewer than 5% overall—but that average does not describe an individual high-risk patient.
A valve history can matter more than a twofold titer difference, so the clinician needs to know about prosthetic valves, congenital valve abnormalities, and previously documented valve disease. Not every incidental murmur carries the same risk; the practical question is whether a structural abnormality has been established and whether baseline cardiac assessment is appropriate.
Pregnancy changes both risk assessment and treatment choices, and compatible symptoms or newly concerning serology deserve prompt discussion with obstetric and infectious-disease teams. Q fever serology is not the same test as the routine pregnancy antibody screen, which assesses antibodies against red-cell antigens; 1 positive result on either report needs its own distinct clinical pathway.
Immunosuppression can alter symptoms and antibody responses, so a low titer should not be used as automatic reassurance in a symptomatic transplant recipient or someone receiving substantial immune-suppressing treatment. A person with no recalled acute illness can still have persistent focal Q fever; missing a memorable fever 6 months earlier does not exclude the diagnosis.
ပုံမှန် အဆင့် I နှင့် အဆင့် II IgG ပုံစံများသည် အဘယ်အရာကို အကြံပြုသနည်း။
Common Q fever antibody patterns suggest possibilities rather than establish diagnoses. Low phase I IgG with rising phase II IgG supports recent infection; stable phase II IgG may represent past exposure; high phase I IgG raises concern for a persistent focus when the clinical circumstances fit.
Consider an illustrative—not an actual patient—case: a 34-year-old veterinary worker has fever for 5 days, phase I IgG below detection, and phase II IgG of 1:64. If phase II IgG reaches 1:256 after 4 weeks using the same IFA method, that fourfold rise supports recent Q fever; the first low result did not mean the illness was mild.
Another hypothetical patient feels well and has phase II IgG of 1:256 with phase I IgG of 1:32, unchanged on a properly timed repeat. That pattern is compatible with prior exposure, but stability alone cannot establish the precise date of infection; 2 results obtained after antibodies have plateaued may miss the earlier rise entirely.
A third example is a 68-year-old with an aortic graft, weight loss, phase I IgG of 1:2048, and phase II IgG of 1:4096. Phase II remaining higher does not exclude persistent infection; the graft history and high phase I endpoint warrant specialist evaluation, and this is exactly where a simplistic phase-I-greater-than-phase-II rule can fail.
Kantesti is an AI blood test interpretation platform that can help organize these phase-specific values and their dates, but the report should never substitute a pattern label for a clinical diagnosis. Our ဆေးဘက်ဆိုင်ရာ စံချိန်စံညွှန်းများနှင့် အတည်ပြုချက် page describes the broader evaluation framework; an automated explanation cannot locate a vascular focus or independently exclude endocarditis.
Q ဖျားနာမှု ကိုယ်ခံအားများကို မည်သည့်အချိန်တွင် ထပ်မံစစ်ဆေးသင့်သနည်း။
Repeat testing depends on the question being asked: approximately 3–6 weeks helps confirm recent infection, while longer follow-up checks for persistent disease in selected patients. CDC guidance describes assessment around 6 months for lower-risk patients and closer monitoring at 3, 6, 12, 18, and 24 months for higher-risk groups.
Weekly antibody testing usually adds little, because IgG changes more slowly than symptoms and ordinary inflammatory markers. A repeat after 7 days may show a small fluctuation without settling whether infection is recent or persistent; worsening clinical symptoms require reassessment now, not a decision to wait until the next planned serology date.
Follow-up should preserve the original report, laboratory method, phase I and phase II values, symptom dates, and antibiotic history. Our အဓိပ္ပာယ်ရှိသော ဓာတ်ခွဲ comparative များ guide explains the value of consistent measurement conditions; a switch from a 1:800-based reference scale to a 1:1024-based scale should be identified before anyone labels the difference a true rise.
Kantesti can help organize a result timeline, but a 60-second explanation is not equivalent to 24 months of specialist surveillance. Our AI နည်းပညာ လမ်းညွှန် explains the report-processing context; the clinician should individualize follow-up for pregnancy, cardiac or vascular risk, persistent symptoms, and the exact national or reference-laboratory protocol being used.
အပြုသဘောဆောင်သော ကိုယ်ခံအားများသည် သင့်အား ပဋိဇီဝဆေးများ လိုအပ်ကြောင်း အဓိပ္ပာယ်ရသလား။
Positive Q fever antibodies do not automatically justify antibiotics. Symptomatic acute Q fever is commonly treated with doxycycline 100 mg twice daily for 14 days in appropriate adults, while confirmed persistent focal infection requires specialist-directed prolonged treatment; pregnancy and pediatric care require separate decisions.
Q fever endocarditis treatment is measured in months, not days, and commonly combines doxycycline with hydroxychloroquine under specialist supervision. CDC guidance describes at least 18 months for native-valve infection and 24 months for prosthetic-valve infection; drug interactions, retinal monitoring, clinical response, and serological trends matter, so these durations are not instructions for self-treatment.
Persistent fatigue after acute Q fever is not synonymous with persistent focal infection, and a positive IgG result does not prove that ongoing bacterial activity explains fatigue. A separate evaluation may uncover anemia or another contributor; our သံလေ့လာမှုများ အပြည့်အစုံ လမ်းညွှန် is relevant when hemoglobin or iron markers are abnormal, but iron results neither confirm nor exclude Coxiella infection.
There is no established supplement, dietary plan, or detox regimen that reliably clears Q fever IgG, and a titer of 1:256 does not create a nutrient prescription. New dark urine, jaundice, or renal abnormalities need their own assessment; our ဆီးစစ်ဆေးမှု (urinalysis) အဓိပ္ပာယ်ဖော် လမ်းညွှန် explains complementary findings without implying that urinary markers can diagnose Q fever.
သင့်ချိန်းဆိုမှုသို့ မည်သည့်အရာကို ယူဆောင်လာသင့်ပြီး မည်သည့်အရာကို ထပ်မံဖတ်သင့်သနည်း။
Bring the full laboratory report, not just the word positive, plus symptom-onset dates, exposure history, medication dates, and relevant cardiac or vascular records. As of October 11, 2026, the central distinction remains unchanged: antibodies support an assessment, but 1 result cannot independently establish recent or persistent focal Q fever.
Write down 4 questions: Which method was used? Are the phase I and phase II values actual endpoints? Is a paired sample needed? Does my history warrant a search for a persistent focus? Include the exact laboratory cutoff, because saying the result was high omits the detail that distinguishes a low screening positive from a phase I titer of 1:2048.
Kantesti is an AI-powered blood test analysis tool that can support preparation for that discussion, but urgent symptoms should bypass report upload and routine interpretation. Severe breathlessness, confusion, fainting, new neurological symptoms, or serious chest pain require immediate medical assessment; even 1 of these symptoms matters more than waiting for a second antibody sample.
My checklist as Thomas Klein, Chief Medical Officer at Kantesti LTD, separates report explanation from diagnosis and treatment. Information about our ဆေးဘက်ဆိုင်ရာ အကြံပေးဖွဲ့စည်းပုံ describes the organization of clinical input; this article does not represent a personal consultation, and any claim of independent review should be confirmed through the publication's actual editorial records.
The following 2 associated publications concern complementary laboratory interpretation, not the evidence for Q fever thresholds or treatment. Their DOI identifiers are supplied below for traceability; they should not be read as substitutes for the CDC, ESC, and Dutch consensus references cited in this article.
Kantesti. (n.d.). Urobilinogen in urine test: Complete urinalysis guide 2026. Zenodo. DOI: 10.5281/zenodo.18226379. A ResearchGate မှတ်တမ်းရှာဖွေမှု နှင့် Academia ထုတ်ဝေမှု ရှာဖွေမှု are discovery links, not verified hosted copies. Kantesti. (n.d.). Iron studies guide: TIBC, iron saturation & binding capacity. Zenodo. DOI: 10.5281/zenodo.18248745. The corresponding ResearchGate ထုတ်ဝေမှု ရှာဖွေမှု နှင့် Academia record search likewise do not establish independent peer review.
အမေးများသောမေးခွန်းများ
Coxiella burnetii IgG positive ဟု ဆိုသည်မှာ အဘယ်နည်း။
Coxiella burnetii IgG positive ဆိုသည်မှာ Q ကိုယ်ခံအားကို ဖြစ်စေသော သက်ရှိပိုးကို ဆန့်ကျင်သော ကိုယ်ခံအားကို စမ်းသပ်မှုက တွေ့ရှိကြောင်း ဆိုလိုပါသည်။ အပြုသဘောဆောင်သော ရလဒ်တစ်ခုသည် မကြာသေးမီက ကူးစက်မှု သို့မဟုတ် လပေါင်းများစွာမှ နှစ်ပေါင်းများစွာ ယခင်က ထိတွေ့မှုတို့ကို ထင်ဟပ်စေနိုင်ပြီး တက်ကြွသော ရောဂါကို အလိုအလျောက် မတည်ထောင်နိုင်ပါ။ အနက်အဓိပ္ပာယ်ဖွင့်ဆိုရန်အတွက် phase I နှင့် phase II ရလဒ်များ၊ ဓာတ်ခွဲခန်းနည်းလမ်း၊ လက္ခဏာများ၊ နှင့် နမူနာအချိန်တို့ လိုအပ်ပါသည်။ ခန့်မှန်းခြေအားဖြင့် 3-6 ပတ် ကွာခြားသော တွဲဖက်နမူနာများသည် မကြာသေးမီက ကူးစက်မှုကို ခွဲခြားသိမြင်ရန် ကူညီပေးနိုင်သည်။.
Q ဖျားနာ အဆင့် (I) နှင့် အဆင့် (II) IgG အကြား ကွာခြားချက်ကဘာလဲ။
Q fever phase I နှင့် phase II IgG တို့သည် လူနာ၏ရောဂါ၏ မတူညီသော အဆင့် ၂ ခုအစား Coxiella burnetii ၏ အချင်းချင်း ကွဲပြားသော ပုံစံ ၂ ခုကို အသိအမှတ်ပြုသည်။ Phase II IgG သည် ပြင်းထန်သော ကူးစက်မှုအတွင်း အများဆုံးဖြစ်လေ့ရှိပြီး၊ phase I IgG မြင့်မားနေခြင်းသည် နာတာရှည် ဒေသဆိုင်ရာ ကူးစက်မှုကို စိုးရိမ်စေသည်။ CDC ၏ လမ်းညွှန်ချက်များသည် IFA ဖြင့် phase I IgG ကို အနည်းဆုံး 1:1024 ဖြင့် အသုံးပြုပြီး နာတာရှည် ဖ关注 (focus) ၏ အထောက်အထားများနှင့် ပေါင်းစပ်ထားသည်။ အဆိုပါ 2 တိုင်းတာမှုများ၏ ဆွေမျိုးအချိုးသည် နာတာရှည် ကူးစက်မှုကို ကိုယ်တိုင်တရားစီရင်ရန် သို့မဟုတ် ဖယ်ထုတ်ရန် မဖြစ်နိုင်ပါ။.
Q ကိုရိုနာရောဂါပိုး တကိုယ်ရေ ခုခံအား တိုင်းတာမှု လေးဆတိုးလာသည်ဟု ဆိုနိုင်ပါသလား။
Q ဖျားနာ antibody တိုင်းတာမှု လေးဆ တိုးလာခြင်းသည် အဆုံးမှတ် 4 ဆ ၍ တိုးလာခြင်းဖြစ်သည်၊ ဥပမာ အဆင့် II IgG သည် 1:64 မှ 1:256 သို့ တိုးလာခြင်း။ 1:64 မှ 1:128 သို့ ပြောင်းလဲခြင်းသည် နှစ်ဆသာဖြစ်ပြီး ထိုစံနှုန်းနှင့် မကိုက်ညီပါ။ အတွဲလိုက် အစောပိုင်းနှင့် သက်သာလာသော နမူနာများကို ပုံမှန်အားဖြင့် 3–6 ပတ်ခန့် ကွာခြားမှုဖြင့် စုဆောင်းသည်။ တူညီသော IFA နည်းလမ်းနှင့် အထူးသဖြင့် တူညီသောဓာတ်ခွဲခန်းဖြင့် နှိုင်းယှဉ်ခြင်းသည် အလုံခြုံဆုံးဖြစ်သည်။.
အဆင့် I IgG တိုက်တာ 1:1024 က နာတာရှည် Q ကိုယ်ခံအားကို ဆိုလိုတာလား။
IFA ဖြင့် 1:1024 的 I 期 IgG 滴度是评估持续性局灶性 Q 热的原因,但本身并非诊断。CDC 指南结合了至少 1:1024 的 I 期 IgG 滴度与可识别的持续性病灶,例如心内膜炎或血管感染。2023 ESC 心内膜炎指南在完整的心内膜炎评估中将大于 1:800 的 I 期 IgG 滴度视为主要的微生物学标准。实验室各不相同,因此在应用任一阈值之前,必须检查报告的方法和解释。.
ကူးစက်မှုစောပိုင်းတွင် Q ဖျားနာရောဂါပိုးကို ခုခံနိုင်စွမ်းရှိသော ကိုယ်ခံအားပစ္စည်းများ (antibodies) သည် အနုတ်လက္ခဏာ ပြနိုင်ပါသလား။
Q ကူးစက်ရောဂါပိုးအတွက် ကိုယ်ခံအားပစ္စည်းများသည် ပြင်းထန်ရောဂါဖြစ်ပွားသည့် ပထမပတ်အတွင်းတွင် အနုတ်လက္ခဏာပြသနေနိုင်ပါသည်။ Coxiella burnetii PCR သည် အများအားဖြင့် ပထမ ၂ ပတ်ခန့်အတွင်း၊ အထူးသဖြင့် ပဋိဇီဝဆေးကုသမှု မစတင်မီ သို့မဟုတ် မကြာမီတွင် အလွန်အသုံးဝင်ပါသည်။ ရောဂါဖြစ်ပွားပြီးနောက် ၃-၆ ပတ်ခန့်အကြာတွင် စုဆောင်းထားသော နောက်ပိုင်း အနာကျက်ချိန်နမူနာသည် ရောဂါရှာဖွေရေး ကိုယ်ခံအားပစ္စည်း မြင့်တက်မှုကို ပြသပေးနိုင်သည်။ ဆရာဝန်တစ်ဦးသည် အနာကျက်ချိန် နမူနာ ဒုတိယတစ်ခုကို စောင့်ဆိုင်းနေစဉ် ပြင်းထန် Q ကူးစက်ရောဂါပိုးကို ပြင်းပြင်းထန်ထန် သံသယရှိနေသော်လည်း သင့်လျော်သောကုသမှုကို မနှောင့်နှေးသင့်ပါ။.
Q ကိုယ်ခံအားပိုး ဘယ်လောက်ကြာကြာ နေနိုင်သလဲ၊ ကုသမှုခံယူဖို့ လိုအပ်ပါသလား။
Q fever antibodies များသည် ထိတွေ့ပြီးနောက် လများ သို့မဟုတ် နှစ်များအထိ အပြုသဘောဆောင်နေနိုင်သောကြောင့်၊ ပုံမှန် IgG သည် ပဋိဇီဝဆေးများ မလိုအပ်ပါ။ သင့်လျော်သော အရွယ်ရောက်သူများတွင်၊ လက္ခဏာများပြသော ပြင်းထန်သော Q fever ကို ဒေါက်စီဆိုက်ကလင်း 100 mg တစ်နေ့နှစ်ကြိမ် ၁၄ ရက်ကြာ ကုသလေ့ရှိပြီး၊ အတည်ပြုပြီးသော ပုံမှန် focal infection သည် အထူးကုဆရာဝန်၏ ညွှန်ကြားချက်ဖြင့် ကြာရှည်ကုသရန် လိုအပ်ပါသည်။ Antibody ခေတ်ရေစီးကြောင်းများသည် စောင့်ကြည့်လေ့လာမှု၏ တစ်စိတ်တစ်ပိုင်းသာဖြစ်ပြီး ပျောက်ကင်းခြင်း သို့မဟုတ် ကုသမှုပျက်ကွက်ခြင်းကို သီးခြားစီ မတည်ထောင်နိုင်ပါ။ ကိုယ်ဝန်၊ ကလေးဘဝ၊ ဆေးဝါးများနှင့် ဓာတ်ပြုမှု၊ နှလုံး သို့မဟုတ် သွေးကြောဆိုင်ရာရောဂါများသည် သီးသန့်ပြုစုစောင့်ရှောက်မှု လိုအပ်ပါသည်။.
AI ပါဝါသုံး သွေးစစ်ဆေးမှု ရလဒ်ကို ယနေ့ စတင် ခွဲခြမ်းစိတ်ဖြာပါ
Kantesti ကို အချိန်မီ၊ တိကျသော ဓာတ်ခွဲခန်း စစ်ဆေးမှု ရလဒ်ခွဲခြမ်းစိတ်ဖြာမှုအတွက် ယုံကြည်သည့် ကမ္ဘာတစ်ဝန်း အသုံးပြုသူ 2 သန်းကျော်နှင့် ပူးပေါင်းပါ။ သင့် သွေးစစ်ဆေးမှု ရလဒ်များကို တင်ပြီး စက္ကန့်ပိုင်းအတွင်း 15,000+ biomarker များ၏ ပြည့်စုံသော အဓိပ္ပာယ်ဖတ်ချက်ကို ရယူပါ။.
📚 ကိုးကားထားသော သုတေသန ထုတ်ဝေမှုများ
Klein, T., Mitchell, S., & Weber, H. (2026). ဆီး Urobilinogen စစ်ဆေးမှု- ပြည့်စုံသော ဆီးစစ်ဆေးမှု လမ်းညွှန် 2026. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). သံဓာတ်လေ့လာမှုလမ်းညွှန်- TIBC၊ သံဓာတ်ပြည့်ဝမှုနှင့် ချည်နှောင်နိုင်စွမ်း. Kantesti AI Medical Research.
📖 ပြင်ပ ဆေးဘက်ဆိုင်ရာ ကိုးကားချက်များ
Anderson A et al. (2013). Diagnosis and Management of Q Fever—United States, 2013: Recommendations from CDC and the Q Fever Working Group. MMWR Recommendations and Reports.
Delgado V et al. (2023). 2023 ESC Guidelines for the management of endocarditis.။ European Heart Journal။.
Wegdam-Blans MCA et al. (2012). Chronic Q fever: review of the literature and a proposal of new diagnostic criteria.။ ကူးစက်ရောဂါ ဂျာနယ်။.
⚕️ ဆေးဘက်ဆိုင်ရာ ရှင်းလင်းချက်
ဤဆောင်းပါးသည် ပညာရေးဆိုင်ရာ ရည်ရွယ်ချက်အတွက်သာ ဖြစ်ပြီး ဆေးဘက်ဆိုင်ရာ အကြံဉာဏ် မဟုတ်ပါ။ ရောဂါရှာဖွေခြင်းနှင့် ကုသမှု ဆုံးဖြတ်ချက်များအတွက် အရည်အချင်းပြည့်မီသော ကျန်းမာရေးစောင့်ရှောက်မှုပေးသူနှင့် အမြဲတမ်း တိုင်ပင်ပါ။.
E-E-A-T ယုံကြည်မှု အချက်ပြများ
အတွေ့အကြုံ
ဆရာဝန်ဦးဆောင်သည့် ဓာတ်ခွဲခန်း အဓိပ္ပာယ်ဖတ်ခြင်း လုပ်ငန်းစဉ်များကို ပြန်လည်သုံးသပ်ခြင်း။.
ကျွမ်းကျင်မှု
biomarker များသည် ဆေးဘက်ဆိုင်ရာ အခြေအနေတွင် မည်သို့ ပြုမူနေသည်ကို အာရုံစိုက်သည့် ဓာတ်ခွဲခန်း ဆေးပညာ။.
အခွင့်အာဏာရှိခြင်း
ဒေါက်တာ Thomas Klein မှ ရေးသားပြီး ဒေါက်တာ Sarah Mitchell နှင့် ပါမောက္ခ ဒေါက်တာ Hans Weber တို့က ပြန်လည်သုံးသပ်ထားသည်။.
ယုံကြည်စိတ်ချရမှု
စိတ်ပူစရာများကို လျော့ချရန်အတွက် ရှင်းလင်းသော နောက်ဆက်တွဲ လမ်းကြောင်းများပါဝင်သည့် သက်သေအထောက်အထားအခြေပြု အဓိပ္ပာယ်ဖတ်ချက်။.