A positive galactomannan result supports possible invasive aspergillosis but does not confirm it. The specimen, immune status, scan findings and medications determine whether the next step is urgent assessment, additional testing or investigation of a misleading result.

Гол санаанууд
- Эерэг үр дүн means the assay detected a fungal cell-wall antigen; it does not, by itself, establish invasive aspergillosis.
- Galactomannan index is usually a unitless optical density ratio, not a fungal count, concentration in ng/mL or percentage probability.
- Laboratory cutoff is often an index of 0.5, but the laboratory's assay-specific interpretation takes priority.
- Research thresholds in the 2020 EORTC/MSGERC definitions include serum or plasma ≥1.0, BAL ≥1.0, or serum/plasma ≥0.7 together with BAL ≥0.8.
- Serum versus BAL matters: serum can miss lung-limited disease, while bronchoalveolar lavage can detect airway colonization without tissue invasion.
- Immune risk rises with prolonged severe neutropenia, transplantation and substantial immunosuppression; an ANC below 0.5 × 10^9/L for more than 10 days is a recognized research host factor.
- Antifungal treatment can reduce antigen detection; a negative result during mold-active treatment does not safely exclude infection.
- Яаралтай үнэлгээ is warranted when a positive result accompanies high-risk immunosuppression and fever or respiratory symptoms; severe breathing difficulty, confusion or significant coughing of blood requires emergency care.
What does a positive galactomannan test actually mean?
A galactomannan test positive result means a fungal cell-wall antigen was detected, but it does not confirm invasive Aspergillus infection. Interpretation depends on serum versus bronchoalveolar lavage, immune status, imaging, antifungal exposure and false-positive causes; high-risk patients with fever or respiratory symptoms need prompt specialist assessment rather than waiting for another number.

Galactomannan is an antigen, not an antibody, and the assay detects material released from fungal cell walls rather than a person's immune memory. A serum index of 0.8 therefore does not mean previous exposure, an 80% infection probability or eight organisms; those interpretations confuse the assay's signal with a clinical diagnosis.
Invasive aspergillosis means Aspergillus has entered and damaged tissue, whereas airway colonization means the organism is present without demonstrated invasion. A BAL index of 1.4 can occur in either setting, so clinicians connect the result to the reason for bronchoscopy, respiratory findings and imaging rather than using the positive flag as a treatment order.
Kantesti is an AI blood test analyzer that can help explain a reported galactomannan index alongside the specimen and supplied clinical context, without confirming infection. Манай компанийн суурь мэдээлэл explains our role; our guide to mold exposure test limits also distinguishes invasive fungal testing from environmental exposure claims.
Why serum and BAL galactomannan results can disagree
Serum galactomannan measures circulating antigen, while BAL galactomannan measures antigen in fluid collected from the lower airways during bronchoscopy. A negative serum result and positive BAL result can coexist in genuine lung-limited aspergillosis; the two specimens sample different compartments, not interchangeable versions of the same clinical signal.
Serum detection generally performs better in selected patients with hematological malignancy or stem-cell transplantation than in many non-neutropenic populations. Preserved neutrophil activity and disease concentrated in the airways can limit circulating antigen, so a serum index of 0.2 cannot overrule a suspicious chest CT and compatible BAL findings.
BAL testing brings the assay closer to the lung process, but it also brings colonization and collection-related contamination into the picture. For example, a BAL index of 1.1 with a serum index of 0.1 requires review of airway disease, lavage collection fluid and respiratory culture—not the conclusion that one laboratory result must be wrong.
Serum and BAL indices should not be averaged, because an average of 0.2 and 1.4 would discard the biological meaning of each compartment. Our explanation of чанарын болон тоон үр дүн helps distinguish a laboratory's positive flag from its numerical measurement; always retain the specimen name beside the index.
How to read the galactomannan index and cutoff
The galactomannan index is usually a unitless optical density ratio, and many laboratories flag results at 0.5 or above. That laboratory threshold is not identical to a research case-definition threshold: the 2020 EORTC/MSGERC definitions use higher or combined specimen thresholds to improve diagnostic specificity in defined populations.
The 2020 EORTC/MSGERC galactomannan thresholds include serum/plasma ≥1.0, BAL ≥1.0, or serum/plasma ≥0.7 together with BAL ≥0.8. These are mycological criteria within research definitions, not stand-alone diagnoses; probable disease also requires the relevant host and clinical criteria (Donnelly et al., 2020).
A serum index of 0.62 may therefore be laboratory-positive without meeting the single-specimen research threshold of 1.0. This is not a contradiction between laboratories and guidelines: lower cutoffs capture more possible cases, while higher cutoffs reduce some false positives; local protocols may also define an equivocal interval or require repeat testing.
There is no universal galactomannan index that automatically means critical illness, and an index of 2.0 does not indicate twice the tissue damage of 1.0. Kantesti keeps the reported cutoff separate from clinical urgency; our guide to хэвийн бус лабораторийн дохиоллын хэлэлцүүлэг нь дохиолол яагаад онош бус, харин тайлбарлан үнэлэх сануулга болохыг тайлбарлана.
| Түвшин | Хязгаар | Утга |
|---|---|---|
| Common laboratory-negative category | Index <0.5 | Below a frequently used assay cutoff; does not exclude invasive aspergillosis, especially during treatment or in non-neutropenic patients. |
| Positive by many laboratory protocols | Index 0.5–0.99 | Requires specimen-specific and clinical interpretation; may not meet the single-specimen EORTC/MSGERC research threshold. |
| Single-specimen research threshold | Serum/plasma ≥1.0 or BAL ≥1.0 | Meets a 2020 EORTC/MSGERC mycological criterion when the appropriate assay and specimen are used; not sufficient alone for probable disease. |
| Combined-specimen research threshold | Serum/plasma ≥0.7 and BAL ≥0.8 | Both thresholds together meet the combined galactomannan criterion; neither value independently confirms invasion. |
How immune status changes a positive result's significance
A positive galactomannan result is more concerning when the patient has a strong risk factor for invasive aspergillosis, such as prolonged severe neutropenia, stem-cell transplantation or substantial immunosuppression. The 2020 research definitions recognize an absolute neutrophil count below 0.5 × 10^9/L for more than 10 days as one host factor.
Duration and cause of neutropenia matter alongside the count. An ANC of 0.4 × 10^9/L during prolonged leukemia treatment has a different risk context from a stable, constitutionally lower count without recurrent infections; our нейтрофилийн тооллогын гарын авлага explains why the percentage alone is inadequate.
Corticosteroid exposure is another risk clue, but no single dose separates safe from unsafe for every patient. The EORTC/MSGERC research host criteria include at least 0.3 mg/kg/day for at least 3 weeks in the preceding 60 days—approximately 21 mg/day for a 70 kg adult—while bedside assessment also considers other immunosuppressants and underlying lung disease.
A normal neutrophil count does not guarantee normal fungal defense, because disorders such as chronic granulomatous disease affect cell function rather than simply cell number. Our guide to oxidative burst testing explains this distinction; a single reassuring CBC should not dismiss compatible fungal disease in someone with an established immune disorder.
Why the same positive index means different things in different patients
The probability that a positive galactomannan result represents invasive disease depends on the probability of disease before testing. In a 2019 Cochrane review of BAL testing in immunocompromised patients, an index cutoff of 1.0 had estimated sensitivity of 78% and specificity of 93%, but performance varied across studies.

A hypothetical low-risk calculation illustrates why screening can mislead. If 1,000 tested people had a 1% disease prevalence and the assay performed with 78% sensitivity and 93% specificity, approximately 8 would be true positives and 69 false positives—so only about 10% of positive results would represent disease.
With the same assumed test performance but a 20% disease prevalence, approximately 156 true positives and 56 false positives would occur among 1,000 people. About 74% of positive results would then represent disease; these are teaching calculations, not validated predictions for an individual or evidence that the Cochrane estimates apply to healthy population screening.
Lowering the BAL cutoff from 1.0 to 0.5 trades specificity for sensitivity: the review estimated 88% sensitivity and 81% specificity at 0.5 (de Heer et al., 2019). The broader lesson also appears in our discussion of tests that need confirmation, although the assays and diseases are different.
How antifungal treatment and prophylaxis affect interpretation
Mold-active antifungal treatment can reduce galactomannan detection, making a negative result less reassuring. The 2016 IDSA aspergillosis guideline advises against routine serum galactomannan screening during mold-active prophylaxis or treatment, while recognizing that BAL testing can still help investigate suspected disease (Patterson et al., 2016).
Medication identity and timing must accompany the result, because posaconazole, voriconazole and isavuconazole are mold-active agents, whereas fluconazole does not reliably cover Aspergillus. A serum index of 0.3 after several days of active treatment cannot be interpreted like a pretreatment index of 0.3; do not interrupt prescribed antifungals to obtain a more detectable result.
A positive result despite prophylaxis can suggest breakthrough disease, but it can also reflect inadequate exposure, a false-positive signal or another fungus. For example, a BAL index of 1.6 during posaconazole prophylaxis prompts review of adherence, absorption, drug levels where appropriate, culture and resistance testing—not an automatic conclusion that the fungus is resistant.
Azole antifungals can substantially increase tacrolimus exposure, so transplant teams may need dose adjustments and closer monitoring when treatment starts or stops. Our guide to такролимусын доод түвшин хэмжих хугацааны тухай гарын авлага explains the sampling issue; a correctly timed drug level answers a different question from a galactomannan index and cannot replace fungal assessment.
Which exposures can cause a false-positive galactomannan result?
False-positive galactomannan results can arise from cross-reacting fungi, some medication or infusion products, and certain collection-related exposures. An index of 0.9 is not automatically explained by antibiotic use: the exact product, formulation, batch, specimen and timing matter, and a plausible interference does not exclude simultaneous invasive infection.
Piperacillin–tazobactam was associated with false-positive galactomannan in older reports, but many contemporary formulations no longer show the same problem. Some amoxicillin–clavulanate formulations and intravenous immunoglobulin products have also been implicated; a single index of 1.2 after an infusion should prompt a product-specific discussion with microbiology rather than a blanket claim that all such medicines invalidate testing.
Other fungi can share antigens recognized by the assay, including Histoplasma and some Fusarium and Talaromyces species. A galactomannan index of 1.5 therefore does not identify an Aspergillus species; our guide to Histoplasma antigen interpretation explains why travel, residence and organism-specific tests can redirect the diagnosis.
Enteral-feed aspiration and antigen translocation through severely damaged intestinal mucosa have been reported as misleading sources, but the evidence is less predictable than for established assay thresholds. Two useful details are the timing of feeding or aspiration and the timing of sample collection; these possibilities are not a reason to restrict ordinary foods or label every positive result a dietary artifact.
Does a positive BAL result mean Aspergillus has invaded the lung?
A positive BAL galactomannan result does not prove lung tissue invasion, because antigen may come from Aspergillus colonizing the airways or from collection-related contamination. A BAL index above 1.0 strengthens a compatible investigation but still requires review of the bronchoscopy findings, host risk, imaging and other microbiological evidence.
Structural lung disease changes the interpretation of airway fungal findings. Bronchiectasis, previous cavities and lung transplantation can make airway colonization more plausible, while deterioration, compatible CT abnormalities or abnormal airway tissue increase concern; an index of 2.0 cannot determine which process is occurring without those accompanying findings.
Lavage collection deserves scrutiny when the BAL result seems out of proportion to the clinical picture. Some gluconate-containing balanced fluids have caused false-positive galactomannan in published reports, although products vary; if serum is 0.1 and BAL is 1.3, ask which fluid was used and whether the laboratory recognizes interference with that specific formulation.
Regional fungal diseases can resemble pulmonary aspergillosis without sharing an identical diagnostic pathway. For a patient with a BAL index of 0.8 and relevant travel or residence history, our guide to regional fungal antibody testing explains why separate investigations may be appropriate; do not assume every alternative lung fungus will cross-react with galactomannan.
Which scans and laboratory tests help establish the diagnosis?
Chest CT, respiratory fungal culture, microscopy and Aspergillus PCR can strengthen or challenge a positive galactomannan result. No single combination is appropriate for everyone: a serum index of 1.1 in a neutropenic patient with new pulmonary nodules is a different diagnostic problem from an isolated positive BAL result with stable chronic airway changes.
CT findings such as nodules with a surrounding ground-glass halo can support invasive aspergillosis, but they are not specific to Aspergillus. The classic halo is more useful in some neutropenic settings than in many non-neutropenic patients; a positive index of 1.4 and an atypical CT therefore still require a broader assessment rather than exclusion based on absent textbook imaging.
Culture can identify an organism and support susceptibility testing, while PCR detects fungal genetic material; neither a negative culture nor a positive airway PCR alone settles tissue invasion. Bacterial pneumonia can coexist or mimic the presentation, and our Legionella antigen guide explains another specimen-specific test that clinicians may select when the respiratory history fits.
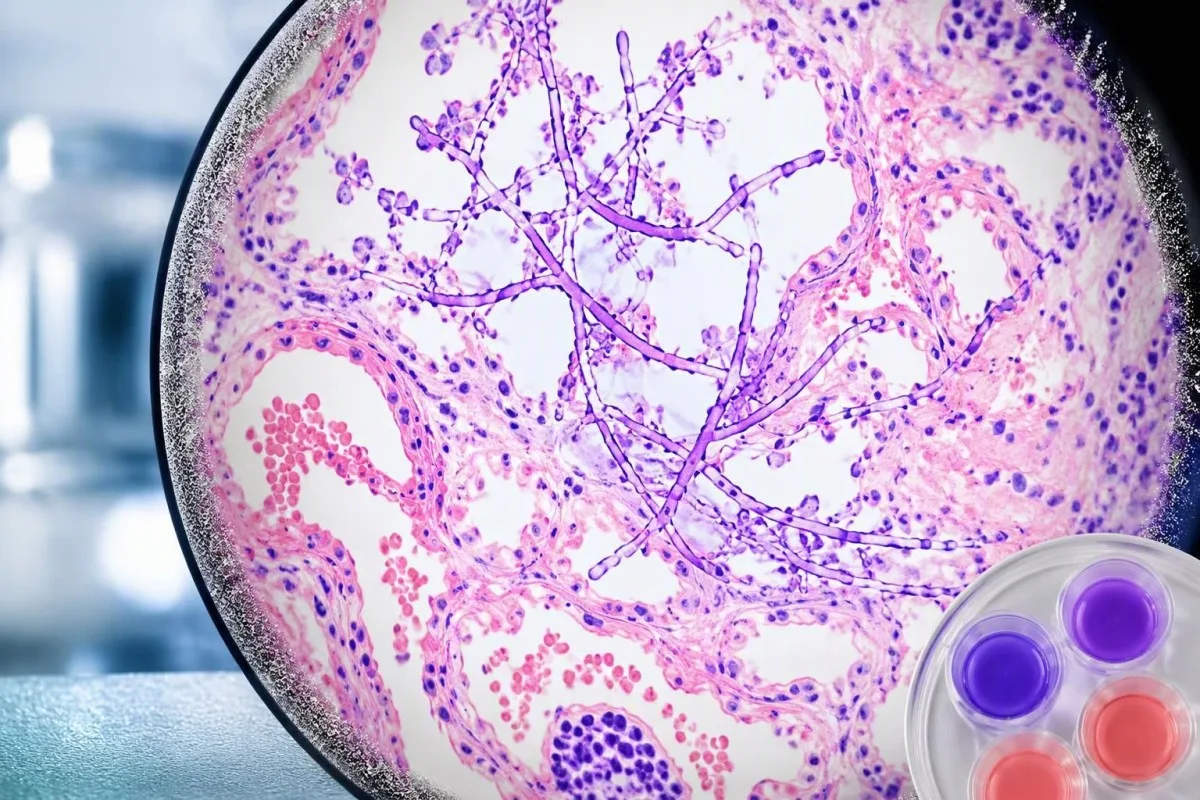
Tissue examination can demonstrate fungal invasion when sampling is feasible, and culture or molecular methods can help identify the fungus because hyphal appearance alone is not species-specific. A CRP of 80 mg/L may show a substantial inflammatory response but cannot identify Aspergillus; our нь эдгээр тэмдэгнүүд яагаад зөрж болохыг тайлбарладаг. explains why general inflammation markers remain supporting evidence.
When does a positive result require prompt specialist assessment?
Contact the treating hematology, transplant, respiratory or infectious-disease team promptly when a positive galactomannan result accompanies high-risk immunosuppression, fever or new respiratory symptoms. An index of 0.6 can warrant urgent action in that setting; the clinical risk matters more than waiting for the number to reach 1.0.

Fever during significant neutropenia requires urgent assessment regardless of the galactomannan result. Common febrile-neutropenia definitions include a single temperature of at least 38.3°C or at least 38.0°C sustained for 1 hour, but oncology services may use stricter instructions; follow the team's emergency plan rather than delaying to meet a published definition.
Severe breathing difficulty, confusion, fainting, significant coughing of blood or rapidly worsening chest symptoms requires emergency care. A room-air oxygen saturation of 92% or below is concerning for many adults without an individualized lower target, but a normal home reading does not rule out serious illness; our амьсгаадалт шалгах гарын авлага explains why symptoms and direct assessment take priority.
Strongly suspected invasive pulmonary aspergillosis may justify treatment while the diagnostic evaluation continues, as recommended by the 2016 IDSA guideline (Patterson et al., 2016). Conversely, an isolated index of 0.55 in a clinically stable, low-risk person may prompt verification and review first; neither scenario supports starting, stopping or selecting an antifungal without the treating clinician.
Should galactomannan be repeated, and do falling values mean recovery?
Repeat galactomannan can help clarify an unexpected result or monitor selected patients, but it must not delay urgent assessment. A change from serum 0.6 to 1.3 can strengthen concern when the clinical picture fits, while a fall from 2.0 to 0.7 may support improvement without proving that infection has cleared.
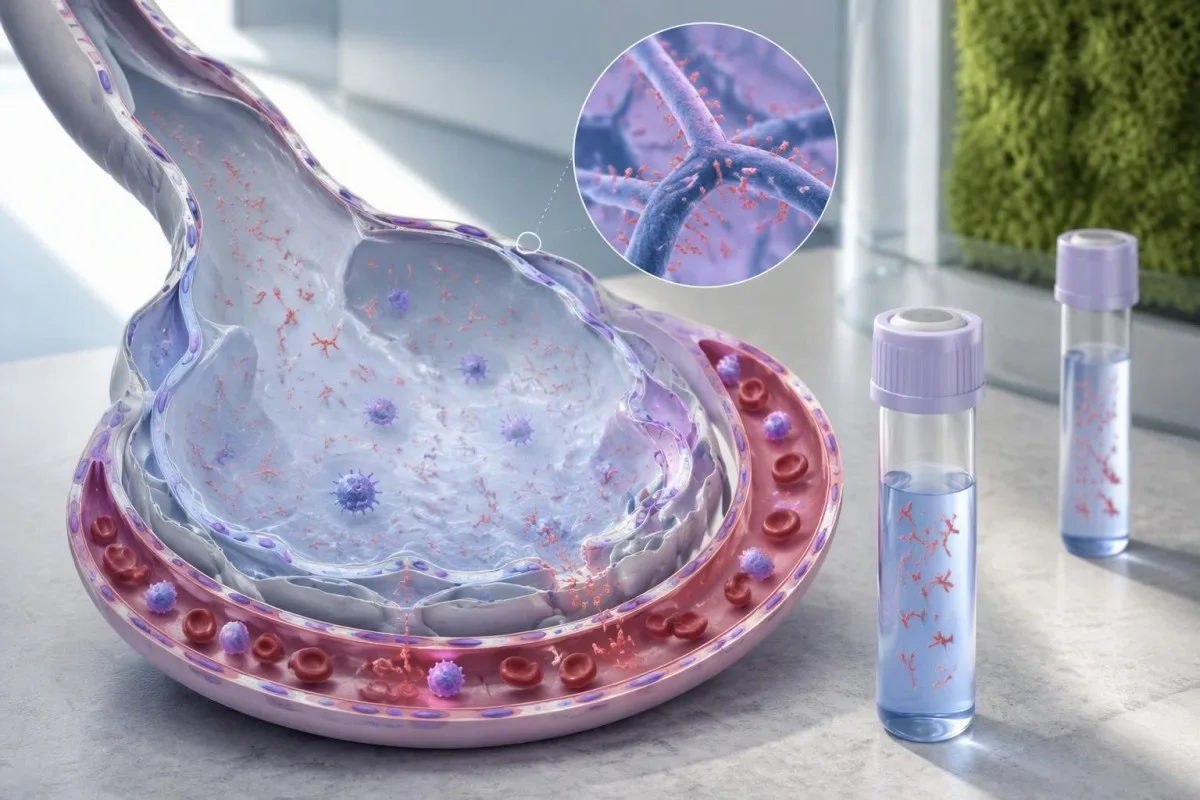
Repeat testing should use the same specimen type and preferably the same assay, because serum and BAL results cannot form a single interchangeable trend. The team may request a fresh sample or laboratory repeat after an unexpected index of 0.58; no universal 24-hour, 48-hour or weekly schedule applies to every patient and every reason for testing.
Serial serum galactomannan is most useful in selected hematological malignancy or stem-cell transplant patients whose antigen was elevated at baseline. A serum result that was always below 0.5 is a weak treatment-response marker, especially for lung-limited disease; our цусны шинжилгээний цагийн хуваарийн гарын авлага explains why treatment start dates must travel with laboratory trends.
Kantesti is an AI biomarker interpretation platform that can help organize serial laboratory values, such as an index changing from 1.8 to 0.9, for discussion with the treating team. Recovery still depends on symptoms, imaging, immune recovery and adequate treatment exposure; an antigen decline alone is not a safe rule for stopping antifungals.
Three hypothetical examples of galactomannan test interpretation
Galactomannan test interpretation changes when the same numerical result is placed in a different clinical setting. The following 3 examples are hypothetical teaching scenarios, not patient encounters; each shows why specimen type, host risk and supporting findings can matter more than whether the report displays a positive flag.
Example 1: a 56-year-old receiving leukemia treatment has an ANC of 0.2 × 10^9/L for 12 days, persistent fever, serum galactomannan 0.62 and new CT nodules. The index is below the single-specimen research threshold, but the overall pattern warrants urgent specialist investigation and possible treatment; our guide to marrow-related blood count changes explains why the underlying hematological condition matters.
Example 2: a 68-year-old with bronchiectasis has BAL galactomannan 1.35, serum 0.12, stable symptoms and no new CT abnormality. Colonization or a collection-related signal becomes more plausible, although neither is proven; the team would review lavage fluid, culture, previous scans and immune status before deciding that antifungal treatment offers more benefit than harm.
Example 3: a 43-year-old transplant recipient taking posaconazole has worsening cough, a new CT abnormality, BAL galactomannan 2.1 and serum 0.18. Treatment exposure may help explain the negative serum result, so breakthrough disease remains a concern; Kantesti can help explain the discordant report, but drug levels, organism identification and treatment decisions belong with the transplant and infection teams.
How Kantesti can support a galactomannan report review
Kantesti is an AI blood test interpretation platform that can help explain a reported galactomannan index, identify the stated specimen and organize accompanying laboratory results. An index of 0.8 needs different context in serum and BAL, and our explanation is educational support—not a diagnosis, validated fungal triage score or treatment recommendation.

Useful context includes the specimen, laboratory cutoff, collection date, symptoms and antifungal start date. An ANC of 0.3 × 10^9/L or a recent transplant also changes the questions worth asking, but those details must be supplied accurately; our клиник баталгаажуулалтын арга should not be read as evidence that this particular fungal assay has been independently validated for autonomous diagnosis.
Kantesti cannot inspect a bronchoscopy, verify tissue invasion or determine whether a specific infusion batch contains cross-reacting antigen. Even with a complete report showing an index of 1.7, the platform cannot replace chest imaging, microbiology consultation or drug-interaction management; bring the original laboratory report, not only an AI-generated explanation, to the appointment.
Share only the information needed for the question, and check consent before adding another person's results or immunosuppression history. Two practical privacy steps are removing unnecessary identifiers and checking how uploaded reports are handled; our нууцлал болон өгөгдлийн мэдээллийг describes the relevant controls, but urgent symptoms should be addressed before any digital review.
Research sources and a checklist for your specialist visit
The most useful follow-up connects 3 kinds of evidence: clinical risk, anatomical findings and microbiological results. The 2016 IDSA guideline, 2020 EORTC/MSGERC definitions and 2019 Cochrane BAL review support that combined approach; none turns a positive galactomannan index into a stand-alone diagnosis.

Prepare 5 questions for the treating team: Was the specimen serum or BAL, which cutoff was used, what makes invasive disease likely, could an exposure explain the signal, and what additional test would change management? For an index of 0.75, these answers are more useful than asking whether the result is simply high or low.
The 2 Zenodo publications listed below are supplementary educational resources about other laboratory panels, not studies validating galactomannan or Aspergillus diagnosis. Our цус бүлэгнэлтийн шинжилгээний гарын авлага болон ийлдэс уургийн гарын авлага may help explain accompanying results, but neither establishes fungal invasion or determines antifungal treatment.
Keep uncertainty explicit when evidence is incomplete, particularly with a borderline index, negative serum during treatment or a positive BAL in structural lung disease. At Kantesti, our эмнэлгийн агуулгын стандартууд separate educational interpretation from diagnosis; a single index of 1.0 should never outweigh serious symptoms or replace prompt specialist assessment.
Түгээмэл асуултууд
Галактоманнаны шинжилгээ эерэг гарах нь Аспергиллын халдварыг батлах уу?
Галактоманнан шинжилгээ эерэг гарсан нь Aspergillus-ийн инвазив халдварыг батлахгүй. Учир нь энэ шинжилгээ эдэд нэвчсэнийг бус, антигенийг илрүүлдэг. Олон лаборатори индексийн 0.5 гэсэн босго хэрэглэдэг ч амьсгалын замд мөөгөнцөр колони үүссэн байх, бусад мөөгөнцөртэй харилцан урвалд орох эсвэл бүтээгдэхүүнээс шалтгаалсан хөндлөн нөлөөнөөс эерэг дохио илэрч болно. Эмч нар сорьцын хариуг дархлааны эрсдэл, шинж тэмдэг, цээжний дүрс оношилгоо болон нэмэлт микробиологийн шинжилгээний хамт үнэлдэг. Индекс лабораторийн босгоос ялимгүй өндөр байсан ч халуурах эсвэл амьсгалын замын шинж тэмдэг илэрсэн өндөр эрсдэлтэй өвчтөнд яаралтай үнэлгээ хийх шаардлагатай.
Галактоманнаны хэвийн индекс хэд вэ?
Олон лаборатори галактоманнаны индексийг 0.5-аас бага бол сөрөг гэж тайлагнадаг боловч шинжилгээний тайланд заасан тухайн сорилын лавлах утгыг нэн түрүүнд баримтална. Индекс нь ихэвчлэн нэгжгүй оптик нягтын харьцаа байдаг болохоос ng/mL-ээр илэрхийлсэн концентраци эсвэл халдварын эрсдэлийн хувийн үзүүлэлт биш. EORTC/MSGERC-ийн 2020 оны судалгааны тодорхойлолтод галактоманнаны шалгуурыг ийлдэс/плазмд ≥1.0, BAL-д ≥1.0, эсвэл ийлдэс/плазмд ≥0.7 бөгөөд үүнтэй хамт BAL-д ≥0.8 гэж тодорхойлсон. Сөрөг хариу нь бүх хүн амын бүлэгт өвчнийг найдвартай үгүйсгэдэггүй, ялангуяа хөгц мөөгөнцрийн эсрэг идэвхтэй эмчилгээний үед.
Ийлдэсний шинжилгээ сөрөг байхад BAL галактоманнан эерэг байж болох уу?
0 BAL-ийн галактоманнан нь ийлдэс сөрөг байхад эерэг гарч болно. Учир нь угаадас уушгины хэсгээс дээж авдаг бол ийлдэс нь цусны эргэлт дэх антигенийг хэмждэг. Ийлдэсний үзүүлэлт 0.2 байх үед BAL-ийн индекс 1.4 гарах нь уушгиар хязгаарлагдсан өвчний үед тохиолдож болох ч амьсгалын замын колоничлол эсвэл дээж цуглуулахтай холбоотой хөндлөн нөлөөллийг мөн илтгэж болно. Энэ зөрүү нь нейтропенигүй өвчтөнүүд болон мөөгөнцрийн эсрэг эмчилгээ хийлгэж буй хүмүүст онцгой ач холбогдолтой. CT-ийн үр дүн болон эмнэлзүйн эрсдэлийг харгалзахгүйгээр эдгээр үр дүнг дундажлах эсвэл тайлбарлах ёсгүй.
Антибиотик эсвэл судсаар тарих иммуноглобулин хуурамч эерэг үр дүн үүсгэж болох уу?
Зарим эм болон дуслын бэлдмэл галактоманнаны шинжилгээний хуурамч эерэг хариу үүсгэж болох ч энэ нөлөө нь бүх бэлдмэлд нийтлэг бус, харин найрлагаас хамаардаг. Пиперациллин–тазобактамын хуучин бэлдмэлүүд үүнд нөлөөлдөг гэж үзэж байсан бол орчин үеийн олон бэлдмэлд ийм нөлөө ажиглагддаггүй; судсаар хийх зарим иммуноглобулин болон амоксициллин–клавуланатын бэлдмэлийн талаар ч мэдээлсэн. Дусал хийсний дараах 0.9 индекс гарсан бол яг ямар бэлдмэл хэрэглэсэн болон сорьцыг хэзээ авсныг лабораторитой нягтлах хэрэгтэй. Харилцан нөлөөлөл байж болзошгүй нь тухайн үед жинхэнэ халдвар хавсран явагдаж байгааг үгүйсгэхгүй.
Does a negative galactomannan result during antifungal treatment rule out infection?
A negative galactomannan result during mold-active antifungal treatment does not rule out invasive aspergillosis. Treatment can reduce antigen detection, so a serum index of 0.3 after therapy starts may be less reassuring than the same pretreatment result. Chest imaging, BAL testing and other microbiology may still be needed when suspicion remains high. Do not stop prescribed antifungals to make the test more likely to become positive.
When should I seek urgent care for a positive galactomannan test?
Seek prompt specialist assessment when a positive galactomannan result accompanies substantial immunosuppression, fever or new respiratory symptoms. An index of 0.6 can still be concerning in someone with prolonged severe neutropenia, and fever should trigger the oncology or transplant team's emergency instructions regardless of the antigen value. Severe breathing difficulty, confusion, fainting or significant coughing of blood requires emergency care. There is no universal galactomannan index that must be reached before urgent action is appropriate.
Does a falling galactomannan index mean antifungals can be stopped?
A falling galactomannan index does not by itself establish that antifungal treatment can be stopped. A serum decline from 2.0 to 0.7 may support improvement in selected patients whose antigen was initially elevated, but symptoms, imaging, immune recovery and treatment exposure still matter. Serum and BAL values should not be combined into one trend. The treating specialist determines treatment duration rather than using a single index or percentage decline.
Цусны шинжилгээний хариугаа тайлбарлуулаарай
Лабораторийн тайлангаа байршуулснаар Kantesti-ийн AI биомаркер бүрийг энгийн хэлээр хэдхэн секундэд тайлбарлана. Дэлхий даяар 2 сая гаруй хүн ашигладаг.
Лавлагаа
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT-ийн хэвийн хэмжээ: D-Dimer, Protein C болон цус бүлэгнэлтийн гарын авлага. Kantesti AI-ийн анагаахын судалгаа. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Ийлдсийн уургийн гарын авлага: Глобулин, альбумин ба A/G харьцааны цусны шинжилгээ. Kantesti AI-ийн анагаахын судалгаа. DOI
- Patterson TF et al. (2016). Practice Guidelines for the Diagnosis and Management of Aspergillosis: 2016 Update by the Infectious Diseases Society of America. Халдварт өвчний эмнэлзүйн сэтгүүл. DOI PubMed
- Donnelly JP et al. (2020). Revision and Update of the Consensus Definitions of Invasive Fungal Disease From the European Organization for Research and Treatment of Cancer and the Mycoses Study Group Education and Research Consortium. Халдварт өвчний эмнэлзүйн сэтгүүл. DOI PubMed
- de Heer K et al. (2019). Galactomannan detection in broncho-alveolar lavage fluid for invasive aspergillosis in immunocompromised patients. Cochrane Database of Systematic Reviews. DOI
- 2 сая+Шинжилсэн сорилууд
- 127+Улс орнууд
- 100+Хэлнүүд
Эмнэлгийн багийн тухай


E-E-A-T итгэлийн дохио
Туршлага
Эмчийн удирдлагатай лабораторийн тайлалын ажлын урсгалын клиник хяналт.
Мэргэшсэн байдал
Биомаркерууд клиникийн нөхцөлд хэрхэн ажиллаж/өөрчлөгдөж байгаад чиглэсэн лабораторийн анагаах ухаан.
Эрх мэдэл
Доктор Томас Кляйн эмнэлзүйн хувьд хянасан бөгөөд доктор Сара Митчелл, профессор доктор Ханс Вебер нар хувь нэмэр оруулсан.
Найдвартай байдал
Сэрэмжлүүлгийг бууруулахын тулд тодорхой дараагийн алхамтай, нотолгоонд суурилсан тайлал.





Эмнэлгийн хариуцлагаас татгалзах мэдэгдэл
Энэ нийтлэл зөвхөн боловсролын зорилготой бөгөөд эмнэлгийн зөвлөгөө биш болно. Оношилгоо, эмчилгээний шийдвэр гаргахдаа мэргэшсэн эрүүл мэндийн үйлчилгээ үзүүлэгчтэй заавал зөвлөлдөнө.
Хэвлэгдсэн · Редакцын багтай холбогдох
Kantesti Ltd компани Англи, Уэльст бүртгэлтэй, компанийн дугаар. 17090423, Лондон, Нэгдсэн Хаант Улс.
