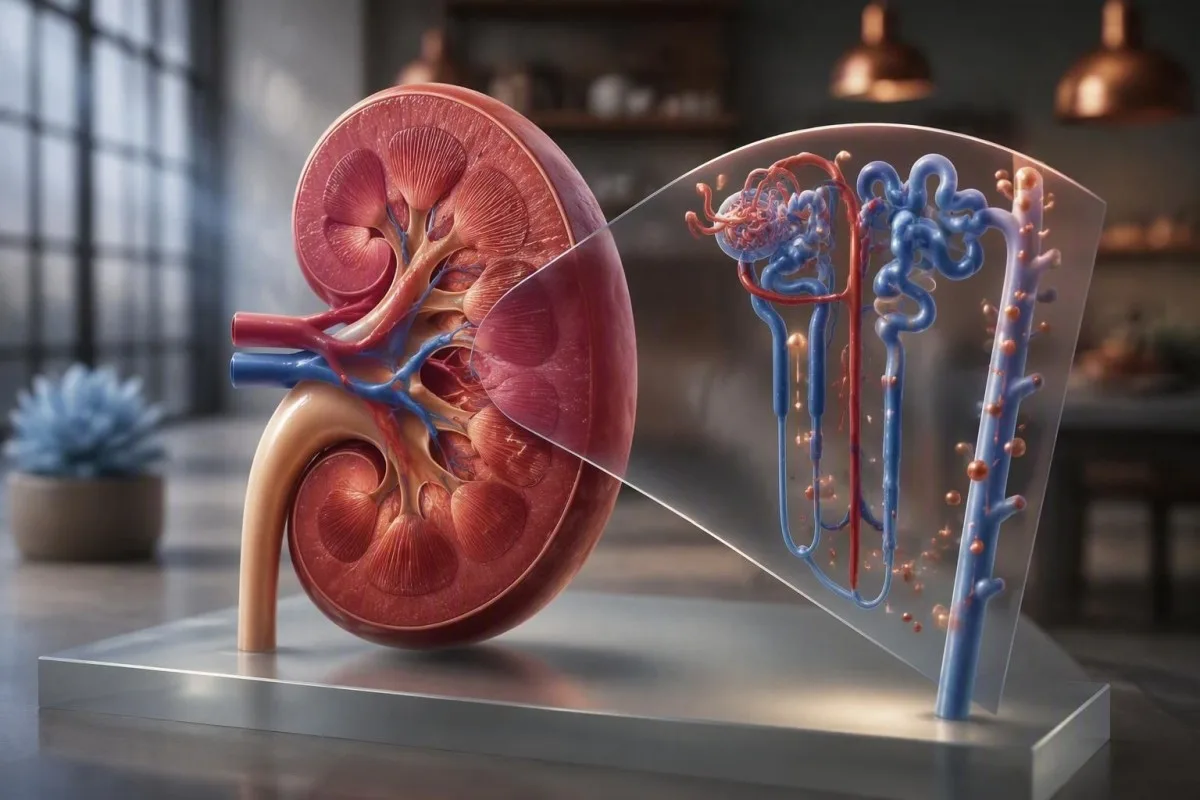
អាស៊ីតតម្រងនោមជាធម្មតាបណ្តាលឱ្យមានអាស៊ីតមេតាបូលីកដែលមានគម្លាតអ៊ីយ៉ុងធម្មតាខ្ពស់។ ការចង្អុលបង្ហាញយ៉ាងច្បាស់គឺ ប៉ូតាស្យូម, pH ទឹកនោម, សារធាតុជំនួសអាម៉ូញាក់ក្នុងទឹកនោម និងថាតើមុខងារតម្រងនោមនៅតែមានលក្ខណៈធម្មតាដែរឬទេ។.


- លំនាំស្នូល: RTA ជាធម្មតាផលិតប៊ីកាបូណាតទាបជាង 22 mmol/L, កើនឡើងក្លរួ, និងគម្លាតអ៊ីយ៉ុងក្នុងសេរ៉ូមធម្មតា។.
- pH ទឹកនោម: ក្នុងអាស៊ីតមេតាបូលីកដែលមិនបានព្យាបាល, pH ទឹកនោមខ្ពស់ជាងជាបន្តបន្ទាប់ 5.5 គាំទ្រ RTA ចុងឆ្ងាយ (ប្រភេទទី ១) ។.
- តម្រុយអំពីប៉ូតាស្យូម: RTA ប្រភេទទី ១ និងប្រភេទទី ២ ជាញឹកញាប់ធ្វើឱ្យប៉ូតាស្យូមថយចុះ; RTA ប្រភេទទី ៤ ជាធម្មតាធ្វើឱ្យវាកើនឡើងជាង 5.0 mmol/L.
- គម្លាតអ៊ីយ៉ុងក្នុងទឹកនោម: គម្លាតអ៊ីយ៉ុងក្នុងទឹកនោមវិជ្ជមានក្នុងអំឡុងពេលអាស៊ីតបង្ហាញពីការបញ្ចេញអាម៉ូញាក់មិនគ្រប់គ្រាន់; តម្លៃអវិជ្ជមានបង្ហាញពីជំងឺរាគ។.
- ការធ្វើតេស្តប្រភេទទី ២: ការបញ្ចេញប៊ីកាបូណាតតាមផ្នែកខ្ពស់ជាង 15% ការបញ្ចូលប៊ីคาร์បូណate ជួយគាំទ្ររោគវិទ្យា RTA ផ្នែក Proximal។.
- ប្រភេទ 4 អាទិភាព៖ Hyperkalemia ជាមួយប៊ីคาร์បូណate ទាបត្រូវការថ្នាំ, ជំងឺទឹកនោមផ្អែម, ក្រពេញ Adrenal និងការពិនិត្យមុខងារតម្រងនោមឱ្យបានឆាប់រហ័ស។.
- កុំធ្វើរោគវិនិច្ឆ័យដោយសារ CO2 តែមួយ៖ លទ្ធផល CO2 នៃបន្ទះគីមីគឺជាការប៉ាន់ប្រមាណប៊ីคาร์បូណate ហើយគួរតែត្រូវបានបញ្ជាក់ដោយការវិភាគឈាមនៅពេលដែលរូបភាពគ្លីនិកមិនច្បាស់លាស់។.
- កម្រិតបន្ទាន់៖ ប៊ីคาร์បូណate ក្រោម 15 mmol/L, ប៉ូតាស្យូមនៅឬលើសពី 6.0 mmol/L, ការភ័ន្តច្រឡំ, រោគសញ្ញាចង្វាក់បេះដូងមិនប្រក្រតីឬការដកដង្ហើមលឿនទាមទារការវាយតម្លៃបន្ទាន់។.
ចាប់ផ្តើមជាមួយនឹងលំនាំអាស៊ីត-មូលដ្ឋានស្នូល
ห้องปฏิบัติการអាស៊ីតតម្រងនោមជាទូទៅបង្ហាញពីប៊ីคาร์បូណate ទាប, ក្លរីនខ្ពស់និងចន្លោះអានសូរ៉ូមេត្រីធម្មតាទោះបីជាការច្រោះនៅតែរក្សាបានក៏ដោយ។. សំណួរជាក់ស្តែងដំបូងគឺថាតើCO2ទាបក្នុងបន្ទះគីមីតំណាងឱ្យអាស៊ីតមេតាប៉ូលីសពិតប្រាកដឬយ៉ាងណាជំនួសឱ្យការពន្យារគំរូ, អាស៊ីតផ្លូវដង្ហើម, ឬជំងឺចម្រុះ។.
នៅលើបន្ទះមេតាប៉ូលីសស្តង់ដារ, CO2 សរុបជាទូទៅជាអ្នកជំនួសជិតស្និទ្ធសម្រាប់ប៊ីคาร์បូណate; មន្ទីរពិសោធន៍មនុស្សពេញវ័យភាគច្រើនរាយការណ៍ប្រហែល 22-29 mmol/L ជាចន្លោះយោង។ តម្លៃ 18 mmol/L ជាមួយក្លរីន 112 មមូល/លីត្រ គឺជាលំនាំដែលមានអត្ថន័យច្រើនជាងតម្លៃតែមួយ។ ពិនិត្យ គន្លឹះតម្រងនោមមូលដ្ឋាននៃបន្ទះមេតាប៉ូលីស មុននឹងសន្មត់ថាជារោគវិនិច្ឆ័យបំពង់កម្រ។.
គណនាចន្លោះអានសូរ៉ូមេត្រីនៃសេរ៉ូមដោយយកសូឌ្យូមដកក្លរីនដកប៊ីคาร์បូណate៖ Na − (Cl + HCO3−). ជាមួយនឹងសូឌ្យូម 140, ក្លរីន 112 និងប៊ីคาร์បូណate 18 mmol/L, ចន្លោះគឺ 10 mmol/L, ដែលសមស្របនឹងអាស៊ីត hyperchloremic ឬអាស៊ីតមានចន្លោះធម្មតា។ ប្រសិនបើអាល់ប៊ុមីនទាប, បន្ថែមប្រហែល 2.5 mmol/L ទៅចន្លោះសម្រាប់រាល់ 1 g/dL នៃអាល់ប៊ុមីនក្រោម 4.0 g/dL។.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគឈាម AI ដែលអានប៊ីคาร์បូណate, ក្លរីន, ប៉ូតាស្យូម, ក្រេអាទីនីន និងអាល់ប៊ុមីនរួមគ្នាជំនួសឱ្យការសម្គាល់លទ្ធផលតែមួយ។ តាមបទពិសោធន៍របស់ខ្ញុំ, ការធ្លាក់ចុះ CO2 យ៉ាងឆាប់រហ័សពី 25 ទៅ 18 mmol/L គឺសមនឹងការធ្វើគំរូឡើងវិញនិងពិនិត្យថ្នាំទោះបីជា eGFR មើលទៅគួរឱ្យទុកចិត្តក៏ដោយ។ Thomas Klein, MD, នឹងមិនចាត់ថ្នាក់នេះថាជា RTA ដោយគ្មានការបញ្ជាក់នោះទេ។.
បញ្ជាក់អាស៊ីតមុននឹងចាត់ថ្នាក់វា
ការវិភាគឈាមវ៉ែនជាមួយនឹង pH ក្រោម 7.35 និងប៊ីคาร์បូណate គណនាទាបបញ្ជាក់ពីអាស៊ីតមេតាប៉ូលីស។ ប៊ីคาร์បូណate ទាបជាមួយនឹង PaCO2 ទាបក៏អាចឆ្លុះបញ្ចាំងពីអាស៊ីតផ្លូវដង្ហើមរ៉ាំរ៉ៃបានដែរ, ដូច្នេះបរិបទនៃការវិភាគឈាមនឹងជៀសវាងការធ្វើរោគវិនិច្ឆ័យខុសដែលអាចជៀសបាន។.
បំបែក RTA ចេញពីមូលហេតុផ្សេងទៀតដែលបណ្តាលឱ្យប៊ីកាបូណាតទាប
Diarrhea is the commonest mimic of RTA because both cause normal-gap metabolic acidosis. The kidney should increase ammonium excretion during gastrointestinal bicarbonate loss; it cannot do that adequately in most forms of RTA.
A negative urine anion gap, usually below −20 mmol/L, suggests high urinary ammonium and therefore an appropriate renal response to diarrhea. A positive result, often above 0 mmol/L, supports impaired ammonium excretion and raises RTA or advanced chronic kidney disease. Kraut and Madias describe this systematic distinction in CJASN (Kraut and Madias, 2012).
Do not overread the urine anion gap. It becomes unreliable with urine sodium below 25 mmol/L, unusual ammonium salts, ketoacid anions, toluene exposure, or recent diuretics. Urine osmolal gap can estimate ammonium more directly, although it is technically less tidy and varies by laboratory method.
Chronic kidney disease itself can lower bicarbonate once eGFR falls, particularly below 30 មីលីលីត្រ/នាទី/1.73 ម៉ែត្រការ៉េ, without being classic RTA. Compare creatinine, cystatin C when available, and albuminuria; our guide to ដំណាក់កាលនៃជំងឺតម្រងនោមរ៉ាំរ៉ៃ explains why one eGFR value needs context.
ប្រើប៉ូតាស្យូមដើម្បីបង្រួមប្រភេទ RTA
Low potassium points toward distal or proximal RTA, while high potassium strongly favors type 4 RTA. Potassium is not merely an accompanying abnormality: it reflects the transport defect and determines immediate safety.
Type 1 distal RTA often produces potassium below 3.5 mmol/L, nephrolithiasis, and urine that remains inappropriately alkaline. Type 2 proximal RTA can also cause hypokalemia, especially after alkali treatment increases distal sodium delivery. Severe potassium depletion may cause weakness, constipation or palpitations before acid-base symptoms are obvious.
Type 4 RTA usually presents with potassium above 5.0 mmol/L and bicarbonate commonly 17-22 mmol/L, rather than the very low bicarbonate sometimes seen in untreated distal disease. Diabetes, reduced renin production, adrenal insufficiency, trimethoprim, ACE inhibitors, ARBs, NSAIDs and potassium-sparing diuretics are frequent contributors. See slightly elevated potassium guidance for urgent thresholds.
Potassium at 6.0 mmol/L ឬខ្ពស់ជាងនេះ, new muscle weakness, fainting, chest discomfort, or an abnormal ECG needs urgent medical evaluation. A hemolyzed sample can falsely elevate potassium, but it should never be casually dismissed; repeat testing and ECG timing matter, as explained in potassium draw-error review.
ស្គាល់ប្រភេទ RTA ចុងឆ្ងាយប្រភេទទី ១ នៅលើលទ្ធផលមន្ទីរពិសោធន៍
Distal type 1 RTA causes normal-gap acidosis with urine pH persistently above 5.5, often low potassium, and a positive urine anion gap. The distal nephron cannot lower urine pH adequately despite systemic acidemia.
The useful bedside pattern is bicarbonate often below 20 mmol/L, ប៉ូតាស្យូមទាបជាង 3.5 mmol/L, and urine pH above 5.5 during confirmed acidosis. Urine pH alone is not diagnostic: a urinary tract infection with urease-producing organisms, recent vomiting, or an alkaline meal can also raise it. A fresh specimen and urine culture sometimes settle the ambiguity.
Calcium phosphate stones and nephrocalcinosis occur because alkaline urine reduces citrate availability and favors calcium phosphate precipitation. A 24-hour urine evaluation usually includes citrate, calcium, oxalate, sodium, volume and pH; calcium oxalate crystal results can add useful context, although crystal type does not establish RTA.
Acquired distal RTA should prompt a careful review for autoimmune disease, particularly Sjögren syndrome, lupus, chronic tubulointerstitial disease and medications such as amphotericin B. Dry eyes plus dry mouth plus this acid-base pattern is a worthwhile clinical lead; see our review of Sjögren testing clues.
ស្គាល់ប្រភេទ RTA ចុងជិតប្រភេទទី ២ នៅលើលទ្ធផលមន្ទីរពិសោធន៍
Proximal type 2 RTA begins with bicarbonate wasting, but urine pH can fall below 5.5 after serum bicarbonate reaches a new lower steady state. This changing urine pH is why one random specimen can mislead clinicians.
When plasma bicarbonate is above the reduced renal threshold, urine bicarbonate loss can drive urine pH above 5.5. Once serum bicarbonate falls to roughly 12-18 mmol/L, the distal nephron can still acidify urine and pH often drops below 5.5. That contrasts with distal RTA, where acidification remains defective.
A fractional excretion of bicarbonate greater than 15% during bicarbonate loading supports proximal RTA; values below 5% make it less likely. This specialist renal tubular acidosis test is not routinely needed in straightforward cases, but it is useful when urine pH and clinical history conflict.
Think beyond bicarbonate. Fanconi syndrome causes proximal wasting of phosphate, glucose despite normal serum glucose, urate, amino acids and low-molecular-weight proteins. New glycosuria with normal glucose should trigger review of glucose in urine causes and exposures such as tenofovir, ifosfamide, outdated tetracycline, or light-chain disease.
ស្គាល់ប្រភេទ RTA ប្រភេទទី ៤ និងលំនាំអ៊ីប៉ូអាល់ដូស្តេរ៉ូន
Type 4 RTA is the most common adult RTA pattern and combines mild normal-gap acidosis with hyperkalemia from low aldosterone activity or aldosterone resistance. Urine pH is often below 5.5 because the main defect is reduced ammonium generation, not complete failure of distal acidification.
Typical RTA blood test results show potassium 5.1-6.0 mmol/L, ប៊ីកាបូណាត 17-22 mmol/L, and chloride elevation with a normal anion gap. A positive urine anion gap can be present because ammonium excretion is low. In contrast, urine pH may be appropriately acidic, often below 5.5.
Diabetic kidney disease is a frequent setting because hyporeninemic hypoaldosteronism reduces distal sodium-driven potassium secretion. Renin and aldosterone testing can help, but posture, sodium intake, time of day and medicines alter both results substantially; renin result patterns are not interpretable in a vacuum.
កាន់តេស្ទី គឺជា ឧបករណ៍វិភាគតេស្តឈាមដោយ AI that can surface the combination of high potassium, low CO2, diabetes markers and kidney function for clinician follow-up. It cannot determine whether a prescribed RAAS blocker should be stopped; that decision depends on blood pressure, albuminuria, ECG findings and the reason the medicine was prescribed.
ធ្វើឱ្យ pH ទឹកនោម និងគម្លាតអ៊ីយ៉ុងក្នុងទឹកនោមត្រឹមត្រូវ
Fresh urine collected during untreated metabolic acidosis gives the most useful RTA evidence. Delayed analysis allows carbon dioxide loss and bacterial metabolism to alter urine pH, occasionally changing an apparent type 1 pattern.
Urine pH from a calibrated electrode is more accurate than a dipstick near the clinically important 5.3-5.5 range. Dipsticks are convenient but commonly read in increments of 0.5 to 1.0 pH unit. A clinician evaluating suspected distal RTA should request prompt analysis rather than relying on a specimen that sat at room temperature.
The urine anion gap is urine sodium plus urine potassium minus urine chloride. A value of +25 mmol/L during acidosis implies low ammonium excretion only if urine sodium is adequate and there are no unmeasured urinary anions. Our urine pH testing guide covers common non-RTA reasons for alkaline urine.
Urine osmolal gap may be preferable when the urine anion gap is distorted. A urine osmolal gap above roughly 200 mOsm/kg generally indicates substantial ammonium excretion, making diarrhea more likely than RTA, though the calculation is an estimate and assay availability varies.
កុំខកខានលំនាំអាស៊ីត-មូលដ្ឋានចម្រុះ
A normal anion gap does not exclude a concurrent high-gap acidosis. Mixed disorders are especially likely when bicarbonate is below 15 mmol/L, lactate is elevated, ketones are present, or kidney function has worsened abruptly.
Correct the anion gap for albumin before deciding it is normal. Albumin of 2.0 ក្រាម/dL lowers the expected gap by about 5 mmol/L, so an uncorrected gap of 12 mmol/L may actually be abnormal. This is a common miss in hospitalized patients with inflammation, malnutrition or liver disease.
A delta gap calculation is mainly helpful when the corrected anion gap is elevated: compare the gap rise above 12 with the bicarbonate fall below 24. It is less reliable in low-albumin states and after saline resuscitation. Lactate collection errors matter because a falsely high lactate can create a false mixed-disorder narrative.
I have seen patients with vomiting, saline infusion and early ketoacidosis show almost textbook hyperchloremia while still having a dangerous high-gap process. Check beta-hydroxybutyrate, lactate, glucose, renal function and medication exposure rather than treating the anion gap as a final verdict.
ពិនិត្យថ្នាំ និងការប៉ះពាល់ មុនពេលកំណត់ RTA
Medication review is part of the renal tubular acidosis test because several common drugs reproduce a tubular pattern. The timing of a bicarbonate or potassium change often offers more diagnostic value than a one-off specialist assay.
Topiramate and acetazolamide inhibit carbonic anhydrase and can cause a proximal or mixed RTA phenotype with low bicarbonate. Trimethoprim, heparin, calcineurin inhibitors, ACE inhibitors, ARBs and spironolactone can contribute to type 4 physiology. Bicarbonate often changes within days to weeks of starting or escalating the relevant drug.
Toluene exposure may produce hypokalemic acidosis with variable anion-gap behavior because hippurate is excreted in urine. If the history includes solvents, chronic inhalant exposure or unexplained severe hypokalemia, toxicology input is appropriate. A urine anion gap can be deceptively negative in this setting.
Kantesti AI flags medication-sensitive electrolyte combinations for review, but it does not replace a pharmacist or prescribing clinician. Keep an exact list of prescription medicines, over-the-counter NSAIDs, herbal preparations and salt substitutes; medication safety trend analysis is most useful when dates are attached to results.
រកមើលផលវិបាកនៃឆ្អឹង, ក្រួស និងជំងឺអូតូអ៊ុយមីន
Long-standing distal RTA can cause calcium phosphate stones, low urinary citrate and bone mineral loss. These complications may reveal the disorder before patients notice fatigue or muscle symptoms.
Chronic acidosis mobilizes bone buffer and increases renal calcium loss, while hypocitraturia removes a natural inhibitor of stone formation. Serum calcium can remain normal, so normal calcium does not rule out clinically meaningful skeletal effects. Check phosphate, alkaline phosphatase, 25-hydroxyvitamin D, PTH and a stone-focused urine profile when indicated.
A urine citrate below 320 មីលីក្រាម/ថ្ងៃ is commonly considered low in adult stone assessment, although laboratories use different cutoffs and collection quality matters. Potassium citrate is often preferred over sodium bicarbonate in distal RTA with calcium stones because it provides alkali and citrate while avoiding sodium-driven calciuria. Treatment dose must be individualized, especially if kidney function is reduced.
Autoimmune screening is guided by symptoms rather than ordered indiscriminately. Dryness, parotid enlargement, rash, neuropathy, arthralgia or proteinuria may justify ANA, SSA/SSB, complements and specialist review; ការបកស្រាយលទ្ធផល ANA explains why a positive ANA alone is not a diagnosis.
ជ្រើសរើសការធ្វើតេស្តបន្ទាប់តាមលំដាប់សមហេតុផល
The next tests after suspected RTA are repeat electrolytes, blood gas, urine pH, urine sodium-potassium-chloride, kidney assessment and a medication review. Specialists add targeted studies only after the basic pattern is verified.
Repeat a basic metabolic panel within days, or sooner if bicarbonate is below 18 mmol/L or potassium is abnormal. Pair it with venous blood gas, magnesium, phosphate, glucose, creatinine, albumin and urinalysis. Blood and urine ideally should be obtained before bicarbonate therapy, because alkali can temporarily change the diagnostic pattern.
For suspected distal RTA, ask about stones, obtain renal imaging when clinically appropriate, and consider urinary citrate. For proximal disease, measure urine glucose, phosphate, urate, protein type and fractional excretions. Proteinuria and casts may shift the concern from isolated tubular dysfunction to broader renal disease; granular cast findings មិនគួរត្រូវមើលរំលងឡើយ។.
As of September 16, 2026, Thomas Klein, MD, recommends using home-uploaded results as preparation for a clinical discussion, not as a diagnosis. Kantesti is an សេវាកម្មបកស្រាយការធ្វើតេស្តរបស់ AI lab that organizes trends and flags questions for the clinician, while our វិធីសាស្ត្រធ្វើឲ្យមានសុពលភាពផ្នែកវេជ្ជសាស្ត្ររបស់យើង explains its clinical oversight and limits.
យល់ពីគោលដៅការព្យាបាល និងការតាមដាន
RTA treatment corrects the cause when possible and replaces alkali while monitoring potassium, kidney function and stone risk. The target is generally a normal or near-normal serum bicarbonate, not simply relief of fatigue.
Adults with distal RTA often need alkali equivalent to roughly 1-2 mEq/kg/day, while proximal RTA may require 5-15 mEq/kg/day because filtered bicarbonate continues to be lost. Potassium citrate can be useful in hypokalemic distal RTA with stones, but it can be unsafe in type 4 RTA with hyperkalemia. Prescribers adjust to serial results rather than a fixed internet dose.
KDIGO's 2024 CKD guidance advises considering pharmacologic or dietary treatment to prevent clinically important acidosis, while avoiding overtreatment that pushes bicarbonate above the laboratory upper limit (KDIGO, 2024). In practice, many clinicians aim for bicarbonate at least 22 mmol/L, but the optimal target varies with CKD, blood pressure, edema risk and sodium sensitivity.
Recheck electrolytes about 1-2 សប្តាហ៍ after a meaningful alkali or medication change, sooner for high-risk potassium values. Patients with type 4 physiology need particular caution with potassium-containing citrate products; kidney supplement safety reviews why “natural” products can still alter electrolytes.
ដឹងនៅពេលដែលប៊ីកាបូណាតទាបត្រូវការការថែទាំបន្ទាន់
Low bicarbonate needs urgent assessment when it is severe, rapidly falling, or paired with dangerous potassium changes, altered breathing or neurological symptoms. RTA is usually treatable, but the lab pattern can also signal sepsis, ketoacidosis, toxin exposure or acute kidney injury.
Seek same-day urgent evaluation for bicarbonate below 15 mmol/L, ប៉ូតាស្យូមនៅឬលើសពី 6.0 mmol/L, ប៉ូតាស្យូមទាបជាង 2.5 mmol/L, new confusion, fainting, marked weakness, chest symptoms, or deep rapid breathing. These thresholds are not diagnoses, but they identify values that can affect cardiac and neuromuscular function quickly. Electrolyte-panel urgent signs provides a practical symptom checklist.
Children, pregnant people, older adults with frailty, and anyone with diabetes or advanced kidney disease may deteriorate with less laboratory reserve. Persistent vomiting, diarrhea, fever, poor intake or a new medication can convert compensated acidosis into a clinically significant problem over 24-48 hours.
Kantesti AI can help turn a multi-page report into questions for an appointment, but alarming symptoms should bypass digital interpretation and go directly to urgent clinical care. The ក្រុមប្រឹក្សាប្រឹក្សាវេជ្ជសាស្ត្រ supports our emphasis on escalation rather than false reassurance.
ការស្រាវជ្រាវគាំទ្រអ្វីខ្លះ — និងលទ្ធផលមន្ទីរពិសោធន៍អ្វីខ្លះដែលមិនអាចបញ្ជាក់បាន
No single renal tubular acidosis lab proves the diagnosis; clinicians diagnose RTA from a coherent blood, urine, medication and clinical pattern. The uncertainty is greatest when testing occurs after IV fluids, bicarbonate treatment, diuretics or an intercurrent illness.
Kraut and Madias' 2012 CJASN review remains useful because it emphasizes first separating high-gap from normal-gap acidosis, then assessing renal ammonium response. Karet's review of inherited distal RTA explains why early deafness, childhood stones or a family history can justify genetic evaluation rather than repeated nonspecific testing (Karet, 2002).
កាន់តេស្ទី គឺជា វេទិកាបកស្រាយសូចនាករជីវសាស្ត្រដោយ AI used across multilingual lab-report formats, but it cannot measure urine ammonium, inspect urine microscopy, or replace nephrology assessment. Our មគ្គុទេសក៍បច្ចេកវិទ្យា AI describes how contextual pattern recognition differs from clinical diagnosis.
Research publication: Kantesti LTD. (2026). កម្មវិធីវិភាគឈាមដោយ AI៖ ការវិភាគលើការធ្វើតេស្តចំនួន 2.5M | របាយការណ៍សុខភាពសកល 2026. Zenodo. https://doi.org/10.5281/zenodo.18175532. ResearchGate: https://www.researchgate.net/; Academia.edu: https://www.academia.edu/. Kantesti LTD. (2026). ការធ្វើតេស្តឈាម RDW៖ ការណែនាំពេញលេញសម្រាប់ RDW-CV, MCV និង MCHC. Zenodo. https://doi.org/10.5281/zenodo.18202598. ResearchGate: https://www.researchgate.net/; Academia.edu: https://www.academia.edu/.
សំណួរដែលសួរញឹកញាប់
តើលក្ខណៈមន្ទីរពិសោធន៍ណាដែលបង្ហាញពីជំងឺក្រពេញអាកាត?
Renal tubular acidosis usually causes a normal-anion-gap metabolic acidosis with bicarbonate below 22 mmol/L and chloride elevation. Potassium then helps classify the pattern: low potassium favors type 1 or type 2 RTA, while potassium above 5.0 mmol/L favors type 4 RTA. A blood gas confirms true metabolic acidosis, because low chemistry-panel CO2 alone can have other explanations.
តើកម្រិត pH នៃទឹកនោមអាចធ្វើរោគវិនិច្ឆ័យជំងឺអាស៊ីតតំរងនោមផ្នែកឆ្ងាយបានទេ?
Urine pH above 5.5 during confirmed systemic metabolic acidosis supports distal type 1 RTA, but it does not diagnose it by itself. A delayed specimen, alkaline diet, recent vomiting and urease-producing urinary infection can all raise urine pH. Clinicians interpret fresh urine pH alongside potassium, urine anion gap, blood bicarbonate and infection testing.
តើលទ្ធផលវិជ្ជមាននៃគម្លាតអានីនក្នុងទឹកនោមមានន័យដូចម្តេចចំពោះជំងឺអាស៊ីត?
A positive urine anion gap during normal-gap metabolic acidosis suggests low urinary ammonium excretion and therefore an inadequate renal acid response. The calculation is urine sodium plus urine potassium minus urine chloride, with values above 0 mmol/L often supporting RTA. It is less reliable when urine sodium is below 25 mmol/L, diuretics are active, or unusual unmeasured urinary anions are present.
តើអ្វីជាភាពខុសគ្នារវាង RTA labs ប្រភេទទី១ និងប្រភេទទី២?
Type 1 distal RTA usually shows urine pH persistently above 5.5 during acidosis, low potassium and a tendency to calcium phosphate stones. Type 2 proximal RTA wastes bicarbonate early, but urine pH often falls below 5.5 once serum bicarbonate reaches approximately 12-18 mmol/L. Fractional bicarbonate excretion above 15% during bicarbonate loading supports proximal RTA.
តើ RTA ប្រភេទ 4 មានន័យថាខ្សោយតម្រងនោមជានិច្ចទេ?
Type 4 RTA does not always mean kidney failure, although it commonly occurs with diabetic kidney disease or reduced kidney function. Its characteristic results are mild metabolic acidosis, often bicarbonate 17-22 mmol/L, plus hyperkalemia commonly above 5.0 mmol/L. Medicines that reduce aldosterone activity or potassium excretion can cause or worsen the pattern even with moderately preserved eGFR.
តើកម្រិតប៊ីកាបូណាតទាបគួរត្រូវព្យាបាលជាបន្ទាន់នៅពេលណា?
Bicarbonate below 15 mmol/L, a rapidly declining value, or acidosis with potassium at or above 6.0 mmol/L warrants urgent clinical assessment. Deep rapid breathing, confusion, fainting, chest symptoms and severe weakness are urgent symptoms regardless of the presumed cause. RTA is only one possible explanation; ketoacidosis, lactic acidosis, toxin exposure and acute kidney injury need prompt exclusion.
ទទួលការវិភាគឈាមដោយ AI ដែលមានថាមពលថ្ងៃនេះ
ចូលរួមជាមួយអ្នកប្រើប្រាស់ជាង 2 លាននាក់នៅទូទាំងពិភពលោក ដែលទុកចិត្ត Kantesti សម្រាប់ការវិភាគលទ្ធផលតេស្តមន្ទីរពិសោធន៍ភ្លាមៗ និងត្រឹមត្រូវ។ ផ្ទុកឡើងលទ្ធផលពិនិត្យឈាមរបស់អ្នក ហើយទទួលការបកស្រាយយ៉ាងទូលំទូលាយនៃសញ្ញាសម្គាល់ (biomarkers) 15,000+ ក្នុងរយៈពេលប៉ុន្មានវិនាទី។.
📚 ឯកសារស្រាវជ្រាវដែលបានយោង
Klein, T., Mitchell, S., & Weber, H. (2026). កម្មវិធីវិភាគឈាមដោយ AI៖ ការវិភាគលើការធ្វើតេស្តចំនួន 2.5M | របាយការណ៍សុខភាពសកល 2026.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
Klein, T., Mitchell, S., & Weber, H. (2026). ការពិនិត្យឈាម RDW៖ មគ្គុទេសក៍ពេញលេញសម្រាប់ RDW-CV, MCV និង MCHC.។ ការស្រាវជ្រាវវេជ្ជសាស្ត្រដោយ AI របស់ Kantesti។.
📖 ឯកសារយោងវេជ្ជសាស្ត្រខាងក្រៅ
Kraut JA et al. (2012). Differential diagnosis of nongap metabolic acidosis: value of a systematic approach.ទស្សនាវដ្តីព្យាបាលគ្លីនិកនៃ American Society of Nephrology។.
Karet FE (2002). Inherited distal renal tubular acidosis. Journal of the American Society of Nephrology។.
KDIGO CKD Work Group (2024). ប្រការណែនាំអនុវត្តគ្លីនិក KDIGO ឆ្នាំ 2024 ស្ដីពីការវាយតម្លៃ និងការគ្រប់គ្រងជំងឺតម្រងនោមរ៉ាំរ៉ៃ.។ Kidney International.
⚕️ ការបដិសេធផ្នែកវេជ្ជសាស្ត្រ
អត្ថបទនេះមានគោលបំណងសម្រាប់ការអប់រំប៉ុណ្ណោះ ហើយមិនមែនជាការផ្តល់ដំបូន្មានផ្នែកវេជ្ជសាស្ត្រទេ។ សូមពិគ្រោះជាមួយអ្នកផ្តល់សេវាសុខភាពដែលមានសមត្ថភាពជានិច្ច សម្រាប់ការសម្រេចចិត្តអំពីការធ្វើរោគវិនិច្ឆ័យ និងការព្យាបាល។.
សញ្ញាទុកចិត្ត E-E-A-T
បទពិសោធន៍
ការពិនិត្យព្យាបាលដោយវេជ្ជបណ្ឌិតលើដំណើរការការបកស្រាយលទ្ធផលមន្ទីរពិសោធន៍។.
ជំនាញ
ផ្តោតលើវិទ្យាសាស្ត្រមន្ទីរពិសោធន៍ថា សញ្ញាសម្គាល់ (biomarkers) មានឥរិយាបថយ៉ាងដូចម្តេចក្នុងបរិបទព្យាបាល។.
ភាពមានសិទ្ធិអំណាច
សរសេរដោយវេជ្ជបណ្ឌិត Thomas Klein ជាមួយការពិនិត្យឡើងវិញដោយវេជ្ជបណ្ឌិត Sarah Mitchell និងសាស្ត្រាចារ្យវេជ្ជបណ្ឌិត Hans Weber។.
ភាពគួរឱ្យទុកចិត្ត
ការបកស្រាយដោយផ្អែកលើភស្តុតាង ជាមួយផ្លូវបន្តតាមដានច្បាស់លាស់ ដើម្បីកាត់បន្ថយការភ័យខ្លាច។.