This antibody result can point to a time-sensitive kidney disorder—even when breathing feels normal. Diagnosis depends on the laboratory method, urine findings, kidney function, and sometimes tissue examination.


- Positive anti-GBM antibodies support possible anti-GBM disease but cannot establish a diagnosis from 1 laboratory result alone.
- Kidney-only disease is possible: lung involvement occurs in approximately 40–60% of classic reported cases, not everyone.
- 急性腎障害 includes a creatinine rise of at least 0.3 mg/dL, or 26.5 µmol/L, within 48 hours; this threshold is not specific to anti-GBM disease.
- 緊急症状 include coughing up blood, new breathlessness, or sharply reduced urine output; seek emergency care rather than waiting for a repeat antibody test.
- 尿顕微鏡検査 can identify red-cell casts, which support bleeding from the kidney filters rather than an ordinary bladder infection.
- Antibody cutoffs differ between assays: a result of 21 U/mL has meaning only alongside that laboratory's reference interval.
- Double-positive disease means anti-GBM antibodies and ANCA occur together; it can change relapse surveillance and long-term treatment.
- 治療のタイミング matters: specialists may start treatment before confirmation when the clinical picture strongly suggests rapidly progressive disease.
- Transplant timing generally requires anti-GBM antibodies to remain undetectable for at least 6 months, according to KDIGO 2021.
What do positive anti-GBM antibodies actually mean?
Positive anti-GBM antibodies may indicate anti-glomerular basement membrane disease, an autoimmune condition that can rapidly damage kidney filters and sometimes the lungs. They do not, by themselves, confirm Goodpasture syndrome. Contact the ordering clinician today; coughing up blood, new breathlessness, or markedly reduced urine requires emergency assessment.
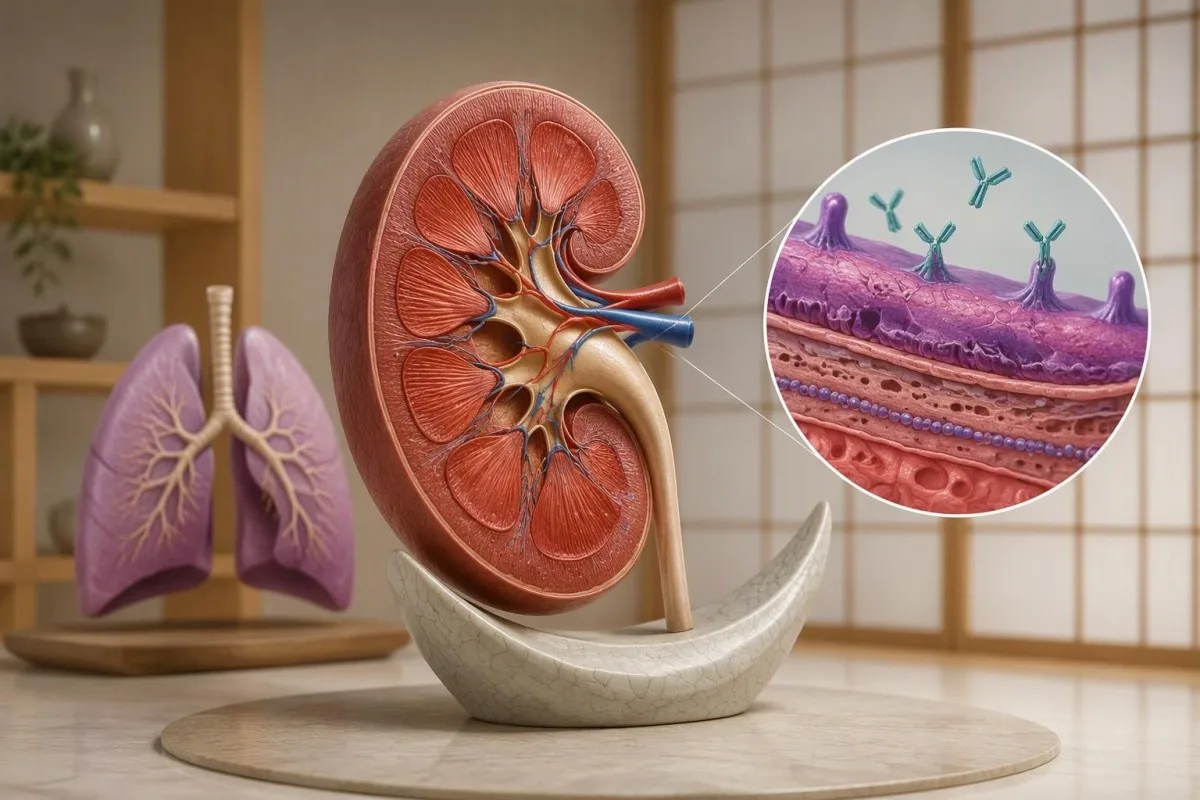
Anti-GBM describes the antibody's target, not a complete diagnosis: the glomerular basement membrane is part of the kidney's filtration barrier. Most classic disease involves antibodies against the noncollagenous domain of the alpha-3 chain of type IV collagen, a structure also found in lung air sacs; the same immune response can therefore affect 2 organs with very different symptoms.
I'm Thomas Klein, Chief Medical Officer at Kantesti; my first question is whether this result accompanies evidence of organ injury, rather than how alarming the laboratory flag looks. A single mildly positive result with stable creatinine is a different situation from positivity plus a creatinine rise over 48 hours, although both need clinician-led follow-up rather than casual reassurance.
カンテスティは AI血液検査分析装置 that can help explain anti-GBM results alongside creatinine, electrolytes, and laboratory reference intervals, but cannot confirm autoimmune kidney disease. Our organization and purpose explain that educational role; our guide to 陽性抗体結果 explains why 1 positive immune marker is not the same as a diagnosis.
Is anti-GBM disease the same as Goodpasture syndrome?
Anti-GBM disease includes kidney-only disease, lung-only disease, and disease affecting both organs. Goodpasture syndrome often refers to the combination of glomerulonephritis and lung bleeding, although clinicians use the name inconsistently. Approximately 40–60% of classic anti-GBM cases have lung involvement, so the terminology should never determine whether kidney assessment is urgent.
The name Goodpasture syndrome can describe a pulmonary–renal presentation rather than prove its cause. ANCA-associated vasculitis and other disorders can also produce kidney inflammation with alveolar bleeding, so a Goodpasture syndrome diagnosis needs etiological clarification; McAdoo and Pusey's 2017 review distinguishes the clinical syndrome from antibody-mediated anti-GBM disease.
Anti-GBM disease is rare, with an estimated incidence around 1 case per million people annually in commonly cited populations, although estimates differ by location and case detection. That rarity matters when interpreting an unexpected screening result: even a good test can generate misleading positives when used in people with little clinical evidence of the disorder.
A low eGFR during this illness may reflect 急性腎障害, not an established chronic stage. Chronic kidney disease generally requires abnormalities lasting at least 3 months; our kidney staging guide explains that distinction, but a rapidly changing result needs an acute assessment rather than being filed under a long-term CKD label.
Why can kidney injury occur without lung symptoms?
Kidney-only anti-GBM disease occurs because antibody access and tissue vulnerability differ between kidney filters and lung air sacs. A normal breathing pattern does not protect the kidneys or exclude this diagnosis. Since only approximately 40–60% of classic cases involve the lungs, waiting for a cough can delay treatment.
The glomerular filtration barrier is continuously exposed to circulating plasma under filtration pressure, whereas the lung's alveolar–capillary barrier has different structural protections. Antibody binding also depends on whether relevant collagen epitopes are accessible; this is not simply a situation where antibodies circulate to 1 organ but somehow fail to reach the other.
Smoking and hydrocarbon exposure are associated with pulmonary involvement in anti-GBM disease, and respiratory illness may influence the lung barrier's susceptibility. Those associations do not allow a precise personal risk calculation: a nonsmoker can develop lung involvement, while a smoker may have kidney-only disease, so 0 respiratory symptoms should never be used as a rule-out test.
Consider an illustrative patient with creatinine increasing from 0.9 to 1.8 mg/dL over several days, microscopic urine blood, and no cough at all. That combination needs urgent nephrology assessment because filtration has changed substantially; our 低eGFRの警告サイン also explain why significant kidney impairment can initially feel surprisingly quiet.
How should the anti-GBM antibody test number be read?
の anti-GBM antibody test must be interpreted using the reporting laboratory's method, units, and cutoff. There is no universal positive concentration that can be transferred between every assay. For example, 21 U/mL is only slightly above a cutoff of 20 U/mL—but that example is not a recommended diagnostic threshold.
Immunoassays may use different antigen preparations and measurement systems, with results reported as U/mL, IU/mL, an index, or a qualitative positive. A result of 30 on an index assay cannot be meaningfully compared with 30 U/mL from another laboratory; the distinction between 定性および定量的検査 is particularly useful here.
Low-level positivity deserves more scrutiny when urine findings and kidney function are normal, but a high concentration still cannot measure irreversible damage by itself. I would examine 3 details before interpreting a trend: whether the same assay was used, whether treatment had begun, and whether the laboratory describes the change as analytically meaningful.
Kantesti AI cannot repair an incorrect transcription of a laboratory result, so verify the value, units, reference interval, and collection date against the original report. Our PDF文字起こしチェックリスト covers those checks; a missing decimal can turn 2.1 into 21 and change the apparent significance of an antibody measurement.
Can a positive anti-GBM result be false or misleading?
A false-positive or clinically misleading anti-GBM result is possible, particularly when positivity is weak and the clinical picture does not fit. A clinician may request confirmation using another method. However, 1 repeat antibody test must not delay assessment when creatinine is rising, urine contains blood, or respiratory symptoms suggest lung involvement.
Pretest probability changes what a positive result means: a person tested for rapidly progressive kidney disease has a different starting likelihood from someone given a broad autoimmune screen without symptoms. Analytical interference, nonspecific reactivity, and differences in antigen recognition can complicate interpretation; repeating the same assay 2 times may reproduce the same problem rather than resolve it.
A reportedly normal urine test should be examined carefully, because a dipstick is not the same as microscopy and a negative result may reflect timing or specimen limitations. Clinicians often pair urine dipstick interpretation with sediment examination and protein measurement; 1 clean-looking urine sample cannot describe everything happening inside the kidney.
Creatinine, urine microscopy, and a urine albumin-to-creatinine or protein-to-creatinine ratio provide complementary information during confirmation. An ACR of at least 3 mg/mmol, approximately 30 mg/g, is abnormal but does not identify anti-GBM disease; our urine creatinine ratio guide explains why dilution-adjusted measurements are more useful than urine concentration alone.
Which urine findings suggest injury to the kidney filters?
Hematuria, proteinuria, dysmorphic red cells, and red-cell casts can support glomerular injury when anti-GBM antibodies are positive. Red-cell casts are especially concerning because they form within kidney tubules. An isolated finding of 3 or more red cells per high-power field warrants clinical interpretation, but does not establish the cause.
顕微鏡的血尿 may appear before urine visibly changes color, so clear urine is not evidence that the kidney filters are unaffected. Conversely, a dipstick positive for blood can reflect hemoglobin or myoglobin without intact red cells; comparing the dipstick with 1 microscopy result helps distinguish these possibilities, particularly after intense exercise or muscle injury.
Protein loss in anti-GBM disease does not have to reach the nephrotic range, conventionally around 3.5 g per 24 hours in adults, to be clinically serious. A patient can have rapidly progressive kidney injury with a much smaller protein measurement; focusing only on whether urine protein is dramatically elevated can miss the more urgent creatinine trajectory.
Sample quality matters because delayed examination can make cellular elements and casts harder to identify, and menstrual contamination can complicate hematuria interpretation. Our 尿沈渣ガイド explains the principal patterns; if the first specimen is inconclusive, clinicians may request a fresh sample rather than assume 0 reported casts means no glomerular disease.
Which kidney function changes make the result urgent?
A rising creatinine level makes positive anti-GBM antibodies more urgent, especially alongside urine blood or protein. Standard acute kidney injury criteria include a rise of at least 0.3 mg/dL, or 26.5 µmol/L, within 48 hours, or at least 1.5 times baseline within 7 days; these criteria do not identify the underlying cause.
An apparently normal creatinine can still represent acute kidney injury if it has risen substantially from a low baseline. An increase from 0.6 to 1.0 mg/dL over 48 hours meets the absolute rise criterion even if 1.0 is inside the laboratory's adult reference interval; the comparison with baseline is therefore more informative than the flag alone.
Estimated GFR equations are less reliable during rapidly changing kidney function because they assume a relatively steady creatinine concentration. Our BUNとクレアチニンの比較 explains additional influences such as dehydration and protein intake, but those alternatives do not safely explain away a 2-fold creatinine increase accompanied by positive anti-GBM antibodies and glomerular urine findings.
Kantestiは、医師の監督のもとで開発されており、当社の医師とアドバイザーが、リスクに関する表現が患者に対してどのように組み立てられるかをレビューします。この取り組みの背後にいる臨床医については、当社の AI血液検査の読み方プラットフォーム, can organize dated laboratory results so a creatinine change over 48 hours is easier to recognize; treatment decisions still require a clinician. Urine output below 0.5 mL/kg/hour for 6 hours also meets a standard AKI criterion, although patients should seek help for markedly reduced urine without attempting a precise home calculation.
Which symptoms require emergency care rather than a routine referral?
Coughing up blood, new breathlessness, low oxygen, or markedly reduced urine output require emergency assessment when anti-GBM disease is possible. New oxygen saturation at or below 92% at sea level is concerning, but a normal home reading does not exclude lung bleeding. Do not wait for the antibody result to be repeated.
Alveolar hemorrhage can occur without obvious coughing up blood because blood remains within the air sacs rather than reaching the mouth. New breathlessness, an unexplained hemoglobin fall, and new lung imaging abnormalities can therefore be more informative than 0 visible blood; our shortness of breath testing guide explains why respiratory assessment requires more than a single laboratory marker.
Severe kidney injury can produce dangerous potassium accumulation, fluid overload, and acid–base disturbance before an antibody diagnosis is finalized. Potassium at or above 6.5 mmol/L generally requires emergency management; lower levels may also be urgent with AKI or ECG changes, as discussed in our potassium escalation guide.
Chest symptoms, confusion, fainting, or an abrupt fall in urine output should be described clearly to emergency services, including the known positive anti-GBM result. Bring the report and any creatinine measurements from the previous 7 days if readily available, but do not delay departure to gather paperwork; the clinical team can investigate and stabilize complications at the same time.
How do specialists confirm an anti-GBM disease diagnosis?
Anti-GBM disease diagnosis combines serology with evidence of kidney or lung injury, and kidney biopsy often provides decisive information when safe and appropriate. Typical findings include crescentic glomerulonephritis and linear IgG staining along the glomerular basement membrane. These are 2 different observations: tissue injury and the pattern of antibody deposition.
Kidney biopsy can help establish the mechanism of injury and estimate how much potentially recoverable tissue remains, but no single microscopic feature should be read without context. Linear staining can occasionally occur in other settings, and atypical anti-GBM disease may differ from the classic pattern; specialists interpret light microscopy, immunofluorescence, and clinical findings together rather than treating 1 image as definitive.
の KDIGO 2021 glomerular diseases guideline recommends starting treatment without delay when anti-GBM disease is strongly suspected, even before confirmation. That does not mean every isolated positive result needs immediate immunosuppression: a patient with rapidly worsening kidney function has a different risk balance from someone with stable creatinine and an equivocal antibody on 2 separate assays.
The broader assessment usually includes ANCA, a full blood count, electrolytes, urine studies, and investigations for alternative immune-mediated kidney disease. ANA, anti-dsDNA, and complement may be useful when lupus is a possibility; our 抗dsDNA解釈ガイド explains why a second positive antibody can suggest an alternative or additional process rather than simply confirming the first.
What changes if ANCA is also positive?
Double-positive disease means a patient has both anti-GBM antibodies and ANCA, usually assessed through MPO-ANCA and PR3-ANCA testing. The acute presentation may resemble anti-GBM disease, while later relapse risk can resemble ANCA-associated vasculitis. Those 2 antibody systems therefore affect both immediate treatment and the longer-term follow-up plan.
McAdoo and colleagues' 2017 Kidney International cohort compared 37 double-positive patients with isolated anti-GBM disease and ANCA-associated vasculitis groups. The double-positive group showed features of both conditions, including clinically relevant later relapses; this is why disappearance of the anti-GBM antibody does not automatically justify stopping every form of immune monitoring or maintenance treatment.
An MPO test is not always an MPO-ANCA test: some laboratories offer myeloperoxidase concentration assays for other purposes, which do not answer the same autoimmune question. Confirm that the report identifies antibodies against MPO or PR3; there are 2 major antigen-specific ANCA targets, and a generic enzyme measurement should not be used to classify double-positive disease.
Complement levels can help explore competing diagnoses, but normal C3 and C4 do not exclude anti-GBM disease or ANCA-associated vasculitis. Our low complement interpretation guide explains how reduced complement may point toward another immune process; these 2 results refine the differential diagnosis rather than functioning as a safety check that rules out kidney injury.
How is anti-GBM disease treated, and can kidneys recover?
Classic anti-GBM disease is usually treated with plasma exchange, glucocorticoids, and cyclophosphamide, although specialists adapt treatment to presentation and recovery potential. KDIGO 2021 describes cyclophosphamide for approximately 2–3 months and glucocorticoids for about 6 months. Kidney recovery depends heavily on function and tissue damage when treatment begins.
Plasma exchange removes circulating antibodies, while immunosuppression reduces further antibody production and tissue-directed immune activity. Treatment often continues until anti-GBM antibodies are undetectable, commonly involving daily exchanges over approximately 2–3 weeks, though duration is individualized; antibody disappearance does not instantly repair scarred kidney tissue or guarantee that dialysis can be stopped.
KDIGO allows carefully selected exceptions to intensive treatment when a patient needs dialysis at presentation, has 100% crescents or more than 50% globally sclerotic glomeruli on an adequate biopsy, and has no pulmonary hemorrhage. These criteria require specialist judgment, not self-interpretation: lung involvement, sampling uncertainty, and the amount of viable tissue can change the treatment balance.
Treatment monitoring includes blood counts, kidney function, infection risk, and drug-specific precautions; changes across 2 visits may reflect medication effects rather than renewed autoimmune injury. Kantesti can help arrange those results chronologically, but our 薬剤安全性トレンドガイド is educational support—not authorization to alter steroids, cyclophosphamide, or a specialist's plasma-exchange schedule.
What follow-up is needed after antibodies become negative?
A negative anti-GBM result after treatment does not mean follow-up can stop, because kidney recovery, medication toxicity, and possible ANCA overlap still need assessment. KDIGO 2021 recommends postponing kidney transplantation until anti-GBM antibodies have remained undetectable for at least 6 months. The monitoring schedule is individualized rather than a universal monthly timetable.
Relapse is uncommon in isolated classic anti-GBM disease, but double-positive disease needs a different long-term strategy because ANCA-associated vasculitis can recur. New urine blood, worsening creatinine, or recurrent breathlessness after 1 apparently successful treatment course deserves assessment; clinicians should not assume every new abnormality is relapse, but should not dismiss it merely because an earlier antibody test was negative.
の 6-month antibody-negative interval before transplantation concerns recurrence risk, not simply recovery from the original hospitalization. Transplant teams also consider clinical stability, infection risk, cardiovascular health, and other eligibility factors; a person can be antibody-negative while still requiring dialysis, and that does not mean the original treatment failed to control the immune process.
Diet and supplements cannot remove anti-GBM antibodies or replace immune treatment, and impaired filtration changes the safety of many over-the-counter products. Our 腎臓サプリメントの安全性ガイド explains common concerns; potassium-containing products, herbal mixtures, and high-dose nutrients deserve review when eGFR is reduced, even if only 1 ingredient is advertised as kidney-supporting.
What can AI interpretation help with—and what must stay clinical?
AI interpretation can help organize an anti-GBM report, but cannot diagnose Goodpasture syndrome or decide whether emergency treatment is needed. The most useful handoff includes the antibody method, creatinine trend, urine findings, and symptoms. A change over 48 hours can matter more than the report's color-coded positive flag.
カンテスティは AIラボ検査解釈サービス that can explain the relationship between anti-GBM antibodies and accompanying laboratory findings when those results are supplied. Our 技術説明 describes the interpretation workflow; the original report remains the source for 3 essentials—value, unit, and reference interval—and an AI summary is not independent confirmation.
A technical benchmark is not a clinical diagnosis study, and a tool that explains reports cannot assess lung sounds, examine urine itself, or interpret a kidney biopsy firsthand. Our 臨床基準と検証 page provides methodological context; even excellent performance on 1 reporting task does not establish safety for every rare autoimmune presentation.
A note from Thomas Klein: the practical question to ask your clinician is, 'Do these antibodies come with evidence of kidney or lung injury, and how quickly should I be assessed?' As of 2026年10月6日, this article cites KDIGO 2021 guidance and the named studies below; ask for an explicit plan today rather than leaving a positive result without a follow-up pathway.
Clinical references, related research, and source limitations
The anti-GBM recommendations in this article are supported by 3 directly relevant clinical references, listed separately from our 2 related Zenodo resources. The Zenodo materials concern coagulation and serum proteins; they are supporting laboratory education, not trials, clinical guidelines, or evidence that establishes a Goodpasture syndrome diagnosis.
KDIGO 2021 supplies the treatment and transplantation recommendations; McAdoo and Pusey 2017 explains classic disease mechanisms and presentations; McAdoo and colleagues 2017 addresses double-positive outcomes. These 3 sources answer different questions, and no general protein or coagulation guide can substitute for them; Kantesti's 医学顧問情報 describes the clinical expertise relevant to interpreting medical content.
aPTT Normal Range: D-Dimer, Protein C Blood Clotting Guide. (n.d.). Zenodo. DOI: 10.5281/zenodo.18262555. This related coagulation interpretation resource explains laboratory concepts relevant to treatment safety, not anti-GBM confirmation; ResearchGate discovery search そして Academia.edu discovery search are search links, not verified publication profiles.
Serum Proteins Guide: Globulins, Albumin & A/G Ratio Blood Test. (n.d.). Zenodo. DOI: 10.5281/zenodo.18316300. This related serum protein resource explains why albumin and globulins add context without measuring anti-GBM activity; ResearchGateの出版物検索 そして Academia.edu 論文検索 likewise do not establish independent peer review of either of these 2 resources.
よくある質問
抗GBM抗体が陽性であることは、グッドパスチャー症候群であることを意味しますか?
抗GBM抗体の陽性反応は、抗GBM病の可能性を支持しますが、それ自体でグッドパスチャー症候群を確定するものではありません。診断には、腎機能、尿所見、および肺の関与の可能性についての臨床評価が必要であり、しばしば腎生検が重要な証拠となります。報告された古典的な症例の約40〜60%で肺の関与が見られるため、腎臓のみの病気も考えられます。オーダーした臨床医に速やかに連絡し、血痰、新たな息切れ、または著しく尿量が減少した場合は、救急外来を受診してください。.
抗GBM病は咳を伴わずに腎臓に影響を与えることはありますか?
抗GBM病は、咳やその他の明らかな肺症状を引き起こすことなく腎臓を損傷する可能性があります。抗体のアクセスしやすさと感受性が異なるため、片方の臓器の関与はもう片方の臓器の関与を必要としません。クレアチニンの上昇が少なくとも0.3 mg/dL、または26.5 µmol/L、48時間以内は、急性腎障害の標準基準を満たし、抗GBM抗体が陽性である場合は緊急の解釈が必要です。正常な呼吸は腎臓の評価を遅らせるべきではありません。.
陽性とみなされる抗GBM抗体価はどれくらいですか?
陽性抗GBM抗体のカットオフ値は、検査室の検査方法および報告単位によって異なります。すべての検査室に適用される単一の普遍的なU/mLまたはIU/mLの閾値はありません。例として、21 U/mLは、検査室のカットオフ値20 U/mLをわずかに上回っていますが、これらの数値は他の検査方法に適用されるべきではありません。緊急度は、抗体濃度だけでなく、付随する腎臓または肺の損傷によって異なります。.
抗GBM抗体検査は間違っていますか?
偽陽性となる場合があるため、抗GBM抗体検査は信頼性に欠けることがあります。これは、分析的干渉、非特異的反応性、または疾患の臨床的確率が低いことに起因します。腎機能が安定しており、尿所見が正常な場合の弱い陽性所見は、2番目の方法を用いた確認を促す可能性があります。同じアッセイを2回繰り返しても同じ分析的問題が再現されることがあるため、臨床医は検査室と代替検査について相談することができます。腎機能が悪化している場合や肺症状がある場合は、緊急評価を遅らせてはなりません。.
どの抗GBM症状で救急受診すべきですか?
血を吐く、息切れの新規または悪化、尿量の著しい減少、錯乱、または失神は、抗GBM病が疑われる場合に緊急評価を要します。平地での新しい酸素飽和度が92%以下であることは懸念されますが、自宅での通常の測定値が肺の関与を除外するものではありません。カリウム値が6.5 mmol/L以上である場合は、一般的に緊急管理が必要であり、より低い値でも急性腎障害またはECG変化を伴う場合は危険となる可能性があります。支援を求める前に、抗体検査の再検査を待たないでください。.
Can anti-GBM disease be treated, and can I have a kidney transplant?
Anti-GBM disease can be treated, usually with plasma exchange, glucocorticoids, and cyclophosphamide, but kidney recovery depends on the severity and duration of injury before treatment. KDIGO 2021 describes cyclophosphamide treatment for approximately 2–3 months and glucocorticoids for about 6 months, with individual adjustments by specialists. People with irreversible kidney failure may be considered for transplantation. KDIGO recommends waiting until anti-GBM antibodies have remained undetectable for at least 6 months before transplantation.
今日、AIによる血液検査分析を
いますぐ利用しませんか。即時で正確な検査分析を提供するKantestiを信頼する、世界中の200万人以上のユーザーに参加してください。血液検査結果をアップロードすると、15,000+のバイオマーカーについて数秒で包括的な解釈が得られます。.
📚 参考文献
Klein, T., Mitchell, S., & Weber, H. (2026). aPTT正常範囲:Dダイマー、プロテインC血液凝固ガイド.。 Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). 血清タンパク質ガイド:グロブリン、アルブミン、A/G比の血液検査.。 Kantesti AI Medical Research.
📖 外部の医学的参考文献
Kidney Disease: Improving Global Outcomes Glomerular Diseases Work Group (2021). 糸球体疾患の管理に関するKDIGO 2021臨床診療ガイドライン.。 Kidney International.
McAdoo SP and Pusey CD (2017). Anti-Glomerular Basement Membrane Disease.。 アメリカ腎臓学会誌(Clinical Journal of the American Society of Nephrology)。.
McAdoo SP et al. (2017). Patients double-seropositive for ANCA and anti-GBM antibodies have varied renal survival, frequency of relapse, and outcomes compared to single-seropositive patients.。 Kidney International.
⚕️ 医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
トーマス・クライン博士が執筆し、サラ・ミッチェル博士およびハンス・ヴェーバー教授によるレビュー。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.