
CTX can show how actively bone is being broken down, but the result is highly sensitive to sampling conditions, treatment and kidney function.

要点
- CTX meaning: CTX-I is a blood marker of collagen breakdown and reflects bone resorption, not bone mineral density or fracture risk by itself.
- 空腹時: Food can suppress CTX, so many laboratories request an overnight fast of 8-12 hours before a morning sample.
- 1日の時間帯: CTX commonly peaks overnight and falls during the day; a morning result is not directly comparable with an afternoon result.
- 単位: CTX may appear as pg/mL or ng/L; these two units are numerically equivalent, while 1 ng/mL equals 1,000 pg/mL.
- 薬の効果: Bisphosphonates and denosumab usually lower CTX, whereas teriparatide and abaloparatide can raise it during bone-building treatment.
- Diagnosis limit: A single CTX value cannot diagnose osteoporosis; diagnosis relies mainly on DXA bone mineral density, fracture history and clinical risk.
- 腎機能: Reduced kidney clearance can raise CTX independently of increased bone resorption, making renal results part of interpretation.
- 再検査: Repeat CTX under the same fasting, morning and laboratory conditions when monitoring a treatment response.
What does the CTX blood test measure?
The CTX bone turnover marker measures bone resorption, the process in which osteoclasts break down old bone and release fragments of type I collagen into the circulation. CTX does not measure bone density directly, and a result outside a laboratory interval does not prove osteoporosis or bone loss.

Serum CTX-I, also called the C-terminal telopeptide test, detects a fragment released when type I collagen is degraded. About 90% of the organic matrix of bone is type I collagen, so CTX acts as a short-term biochemical signal of osteoclast activity rather than a direct scan of skeletal strength.
A CTX result can change within hours, while a DXA scan reflects accumulated mineral density over months or years. For example, a hypothetical 62-year-old with CTX of 720 pg/mL may have active resorption, but that number alone cannot tell us whether the person has osteoporosis, a recent fracture, menopause-related turnover or a medication effect.
Kantesti is an AI blood test analyzer that places CTX beside related results such as calcium, phosphate, alkaline phosphatase, creatinine and vitamin D rather than treating the marker as a diagnosis. Our About Usページ explains how we distinguish an interpretation aid from clinical diagnosis.
Why one CTX result cannot diagnose osteoporosis
One CTX value cannot diagnose osteoporosis because CTX reflects current resorption, whereas osteoporosis is diagnosed from bone mineral density, fragility fractures and overall fracture risk. A high result may indicate increased turnover, but it does not quantify how much bone has been lost.

The diagnostic threshold for osteoporosis is a DXA T-score of −2.5 or lower at the femoral neck, total hip or lumbar spine in appropriate postmenopausal women and men aged 50 years or older. CTX has no equivalent universal diagnostic cutoff, because assay calibration, age, sex, menopause and kidney function alter the result.
A low CTX can also be misleading. A person taking alendronate may have CTX below 100 pg/mL with stable treatment, while another person with the same value may have naturally low turnover; the number does not distinguish those situations without medication history and prior results.
CTX can complement fracture-risk assessment but should not replace it. The 血液検査のバイオマーカーガイド provides broader context for reading a biomarker pattern, including why a result that is statistically unusual is not automatically clinically dangerous.
Does fasting change CTX test results?
Fasting usually makes CTX easier to compare because food suppresses circulating CTX, particularly after carbohydrate-containing meals. Many laboratories therefore request an overnight fast of 8-12 hours and a morning collection, although the exact instruction belongs to the ordering laboratory.
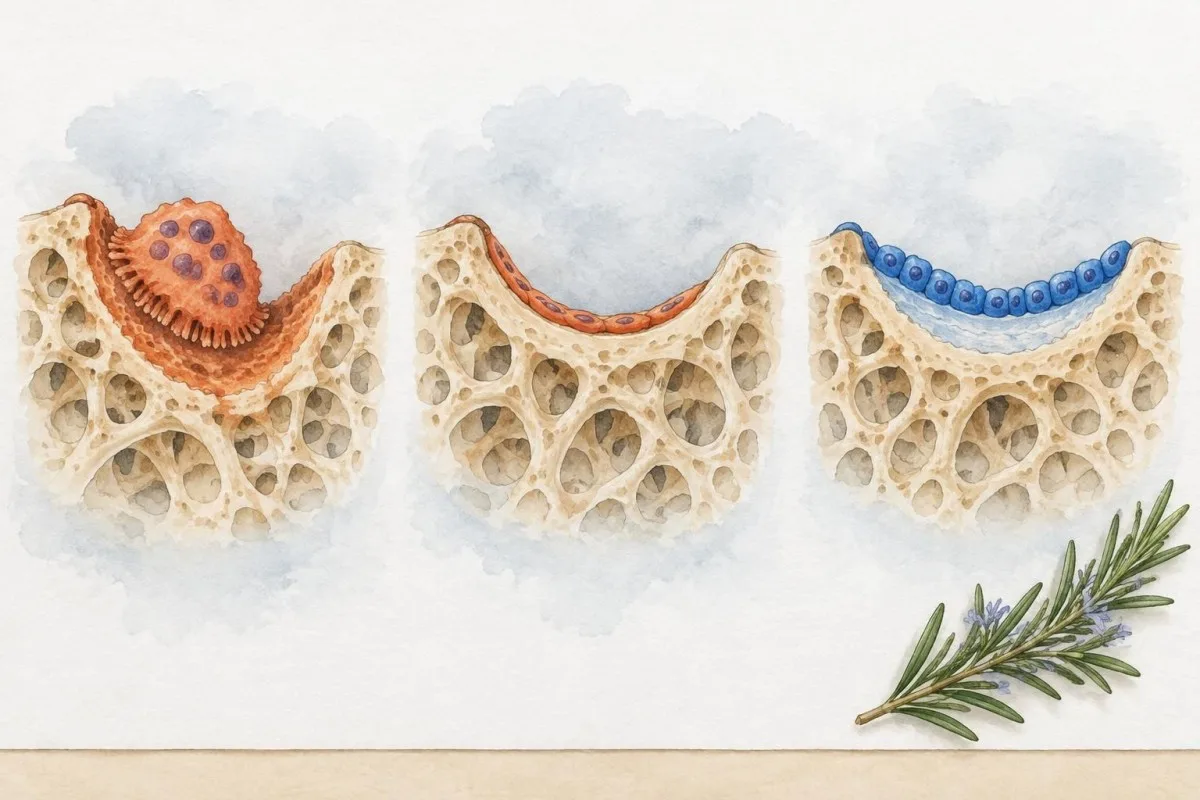
A meal can lower CTX through insulin and nutrient-related changes in bone metabolism, with suppression lasting several hours. The size of the effect varies; a practical interpretation is that a non-fasting CTX of 180 pg/mL may not be comparable with a fasting result of 420 pg/mL drawn from the same person on another day.
Water is generally permitted during a fasting blood test, while calories, milk, sweetened drinks and many nutritional supplements may break the fast. Do not stop prescribed medicines unless the clinician or laboratory specifically instructs you; the purpose is to standardise the sample, not to create medication risk.
「 CTX fasting test is not a separate assay. It means the same serum CTX measurement collected under fasting conditions; preparation details can be checked in our guide to what fasting required means.
Why does the time of day matter for CTX?
CTX follows a circadian rhythm: concentrations are generally higher overnight and in the early morning, then decline during the day. A 7:30 a.m. fasting sample and a 3:00 p.m. non-fasting sample should not be used as if they were interchangeable.

In many adults, CTX is lowest in the afternoon and rises during sleep, with peak-to-trough differences often around 20-50%. The precise pattern varies by age, menopause, sleep schedule and metabolic health, so the range is a useful warning rather than a fixed conversion factor.
For treatment monitoring, aim for the same collection window each time, such as 7:00-9:00 a.m., after the same fasting period. A hypothetical change from 560 pg/mL at 8:00 a.m. to 300 pg/mL at 2:00 p.m. might reflect timing and food rather than a true 46% biological improvement.
Shift work and jet lag deserve special attention because sleep timing can alter the biological rhythm behind the clock time. Our 血液検査のタイミングガイド explains why a clock-based comparison can fail when the body schedule changes.
What is a normal CTX range?
There is no single normal CTX range that applies to every laboratory, assay, age group or sex. The most reliable reference interval is the one printed beside your result, interpreted with the assay name, fasting status, collection time and treatment history.

The table shows illustrative interpretation bands, not diagnostic ranges. CTX may be reported in pg/mL or ng/L, and those units are numerically equivalent; 500 pg/mL equals 500 ng/L, whereas 0.5 ng/mL equals 500 pg/mL.
Some European laboratories report manufacturer-specific premenopausal, postmenopausal and male intervals, while other laboratories use locally validated populations. Kantesti is an AI blood test interpretation platform that reads the laboratory's own reference interval before comparing a CTX result with general published patterns.
Age-related turnover is not a minor detail: growing adolescents can have much higher bone turnover than adults, and postmenopausal women often have higher CTX than premenopausal women. The 医学的検証に関する情報 describes why laboratory context and clinical review remain necessary for AI-assisted interpretation.
| レベル | 範囲 | 意味 |
|---|---|---|
| Illustrative untreated adult zone | 300-600 pg/mL | A possible mid-range result in some morning assays; not a universal normal interval. |
| Higher turnover signal | 600-900 pg/mL | May reflect increased resorption, but requires age, menopause, fasting and renal context. |
| Markedly high signal | 900-1,200 pg/mL | Consider untreated high turnover, recent fracture, endocrine disease or a sampling issue. |
| 非常に高い結果 | >1,200 pg/mL | Prompt clinical review is sensible; this is not an emergency threshold by itself. |
How do osteoporosis medicines lower CTX?
Antiresorptive medicines usually lower CTX because they reduce osteoclast activity. Oral or intravenous bisphosphonates, denosumab, hormone therapy and some selective estrogen receptor modulators can all produce lower CTX, but the speed and size of change differ substantially.

Bisphosphonates may reduce CTX over weeks to months, often by roughly 30-60% depending on the drug, adherence, baseline turnover and collection conditions. A low result during treatment generally indicates pharmacological suppression, not proof that bone has become structurally stronger at every skeletal site.
Denosumab acts more rapidly; clinical studies commonly observe CTX reductions of approximately 70-90% within days to weeks after injection, followed by recovery as the six-month dosing interval ends. A result taken near the end of an interval may therefore differ from one taken one month after treatment.
Medication lists should include dose, route, last administration date and missed doses. The osteoporosis blood test guide explains why calcium, phosphate, parathyroid hormone and kidney tests may clarify a CTX result better than CTX alone.
Which medicines can raise or complicate CTX?
Bone-building medicines can raise CTX temporarily, while some hormonal and endocrine medicines alter bone turnover indirectly. Teriparatide and abaloparatide commonly increase formation markers first and may also increase resorption; romosozumab often lowers CTX while increasing formation markers early in treatment.
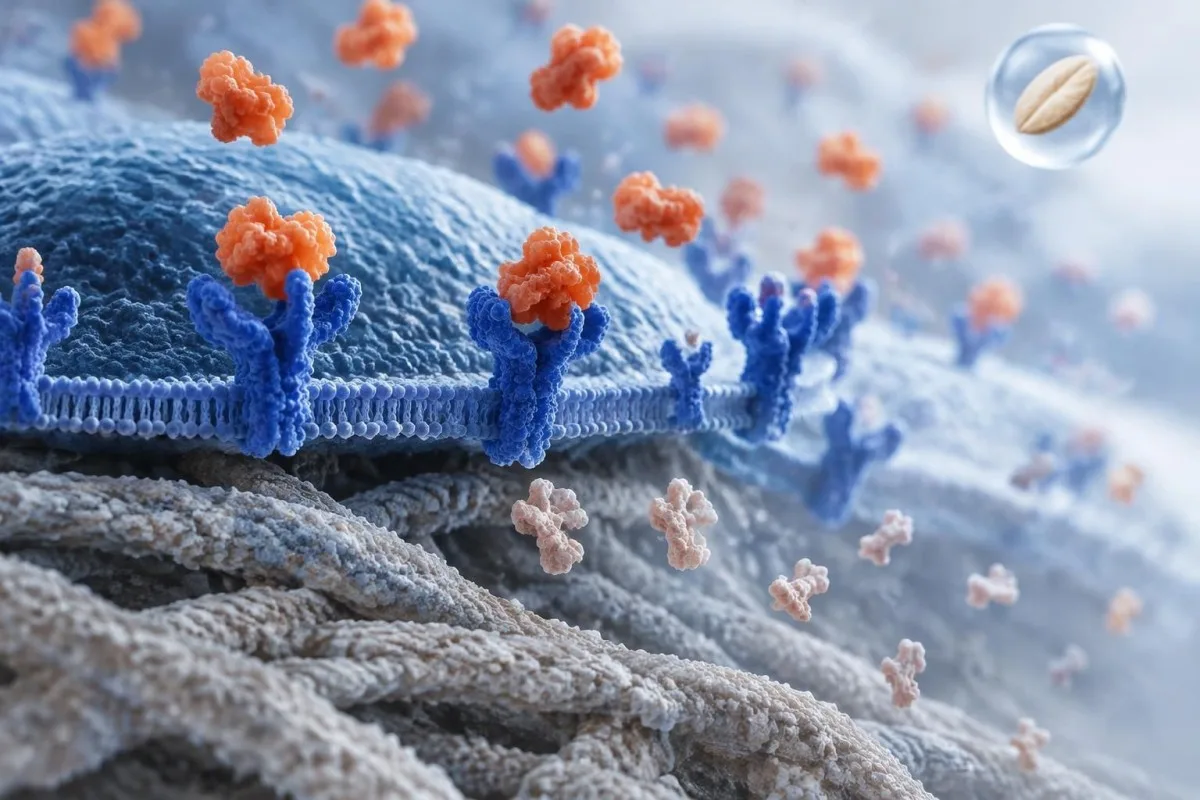
A temporary CTX rise during teriparatide or abaloparatide does not automatically mean treatment is damaging bone. These medicines stimulate remodelling, so clinicians often interpret CTX with a formation marker such as P1NP and with the treatment's intended sequence.
Excess thyroid hormone, primary hyperparathyroidism and prolonged glucocorticoid exposure can disturb bone turnover, but their CTX patterns are not identical. Menopause can raise CTX as estrogen protection falls, while pregnancy and breastfeeding require separate physiological interpretation rather than adult treatment cutoffs.
Hormone status matters when reading results from women around menopause. Our women's health testing guide discusses why a CTX value should be linked to reproductive stage, symptoms and other laboratory findings.
Can kidney function make CTX look high?
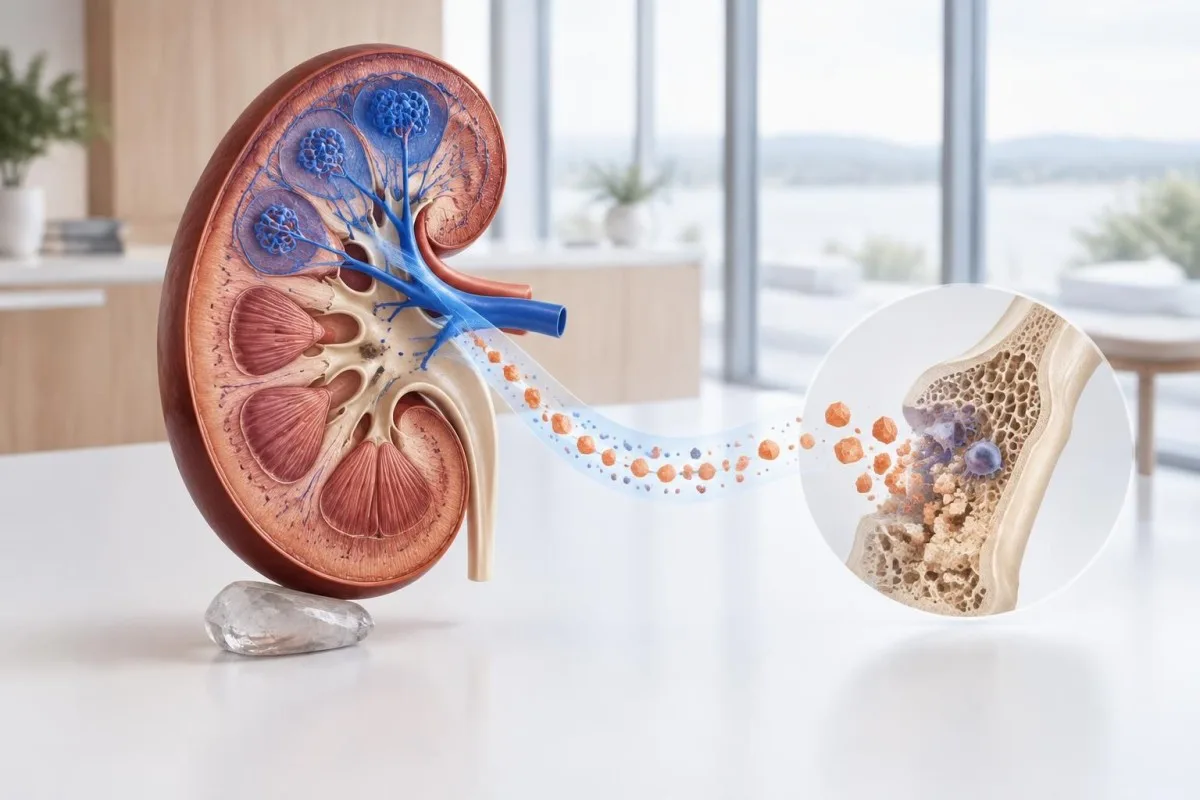
Reduced kidney function can raise CTX because the kidneys help clear CTX fragments from the circulation. An elevated CTX in chronic kidney disease may therefore reflect both altered bone turnover and slower clearance, so it should not be interpreted with a healthy-kidney reference interval.

Creatinine and estimated glomerular filtration rate should be reviewed alongside CTX, especially when eGFR is below 未満であればCKDを示唆し、さらに. In advanced kidney disease, mineral and bone disorder can produce complex turnover states, and a serum CTX value may not reliably separate high turnover from impaired clearance.
A hypothetical patient with CTX of 840 pg/mL and eGFR of 38 mL/min/1.73 m² needs a different discussion from a patient with the same CTX and eGFR of 95. The first result may require kidney-mineral assessment, calcium, phosphate, parathyroid hormone and alkaline phosphatase before any osteoporosis conclusion.
Kidney-related interpretation also affects medication safety, particularly for some bisphosphonates. The high urine calcium guide shows how calcium handling tests can add context, although urine calcium does not replace CTX or DXA.
What else can cause a high CTX result?
High CTX can result from menopause, recent fracture healing, immobilisation, hyperparathyroidism, untreated hyperthyroidism, low calcium or vitamin D status, and some cancers affecting bone. The result becomes more informative when it matches the history and a related biochemical pattern.

Bone turnover often rises during fracture repair, so CTX drawn within weeks to months after a fracture may reflect healing biology. Immobilisation can also increase resorption; a person confined to bed for 4〜8週間ごとに may not have a result comparable with their usual active baseline.
Vitamin D deficiency does not always produce a high CTX by itself, but low 25-hydroxyvitamin D combined with high parathyroid hormone and low-normal calcium can indicate secondary hyperparathyroidism. A 25-hydroxyvitamin D result below 20 ng/mL is commonly classified as deficient, although treatment thresholds vary by guideline and clinical setting.
Paget disease, hyperparathyroidism and other high-turnover disorders need targeted evaluation rather than a CTX-based label. Our Paget disease blood test explanation describes why alkaline phosphatase may be more useful for some focal bone processes.
When is CTX useful before osteoporosis treatment?
Before treatment, CTX can provide a baseline estimate of bone resorption and help identify a result that needs explanation before medication starts. It is most useful when collected fasting in the morning and interpreted with DXA, fracture history, kidney function and secondary-cause tests.

A baseline CTX above the laboratory's upper interval may support active turnover, but it does not decide treatment alone. A baseline below 100 pg/mL can occur in untreated people and does not guarantee low fracture risk because bone density, architecture and falls still matter.
The most useful baseline includes the date and time, hours fasting, exercise in the previous 24 hours, recent fracture, menstrual or menopause status, kidney function and medicines. Recording these variables can prevent a false impression that a later 25% change represents a treatment effect.
Kantesti can organise CTX with other uploaded laboratory values and trend dates, but treatment choice belongs to a qualified clinician. Our AI trend analyzer for medication safety is designed to help users see patterns that still need human medical review.
How should CTX be monitored during bisphosphonate treatment?
During bisphosphonate treatment, a falling CTX can support biological response, but the change must exceed expected analytical and biological variation. Monitoring is usually more meaningful after several months and when the same assay, fasting state and collection time are used.

A practical monitoring interval is often 3〜6か月 after starting or changing an oral bisphosphonate, although guidance and clinical circumstances differ. For example, a fall from 680 to 420 pg/mL may suggest response, but the clinician should verify adherence, timing, fasting status and laboratory method before calling it treatment failure.
The International Osteoporosis Foundation and International Federation of Clinical Chemistry position paper by Vasikaran et al. describes bone turnover markers as useful for monitoring treatment when standardisation and least-significant-change principles are respected. A result that changes by only 10% may be noise in a test with substantial within-person variation.
A persistently high CTX despite prescribed oral therapy may indicate missed doses, incorrect administration, malabsorption, very high baseline turnover or an assay problem. Review the osteoporosis treatment laboratory guide before assuming the medicine has failed.
What does CTX mean after denosumab?
After denosumab, CTX is expected to fall sharply and may rise again when the next dose is delayed or treatment stops. A rising result near the end of the six-month interval is not interpreted like a rising result several weeks after an injection.
Denosumab is commonly administered every 6ヶ月, and delayed treatment can allow bone resorption to rebound. A CTX result cannot determine independently whether an injection is safe to delay; clinicians use the dosing date, fracture history and an agreed transition plan.
After denosumab cessation, rebound bone turnover can be substantial and vertebral fracture risk may increase, especially when follow-on antiresorptive treatment is not provided. CTX may help monitor suppression during a transition, but no single universal post-denosumab target applies to every assay or patient.
Record the injection date to the nearest day, because a result at month 1 and a result at month 7 answer different clinical questions. A senior medication-effects review can also be useful; see medicine-related blood test patterns for broader interpretation principles.
Can CTX guide a bisphosphonate holiday?
CTX may contribute to decisions about a bisphosphonate treatment holiday, but it cannot by itself decide when treatment should stop or restart. Fracture risk, treatment duration, DXA trend, age, vertebral imaging and the specific bisphosphonate remain central.
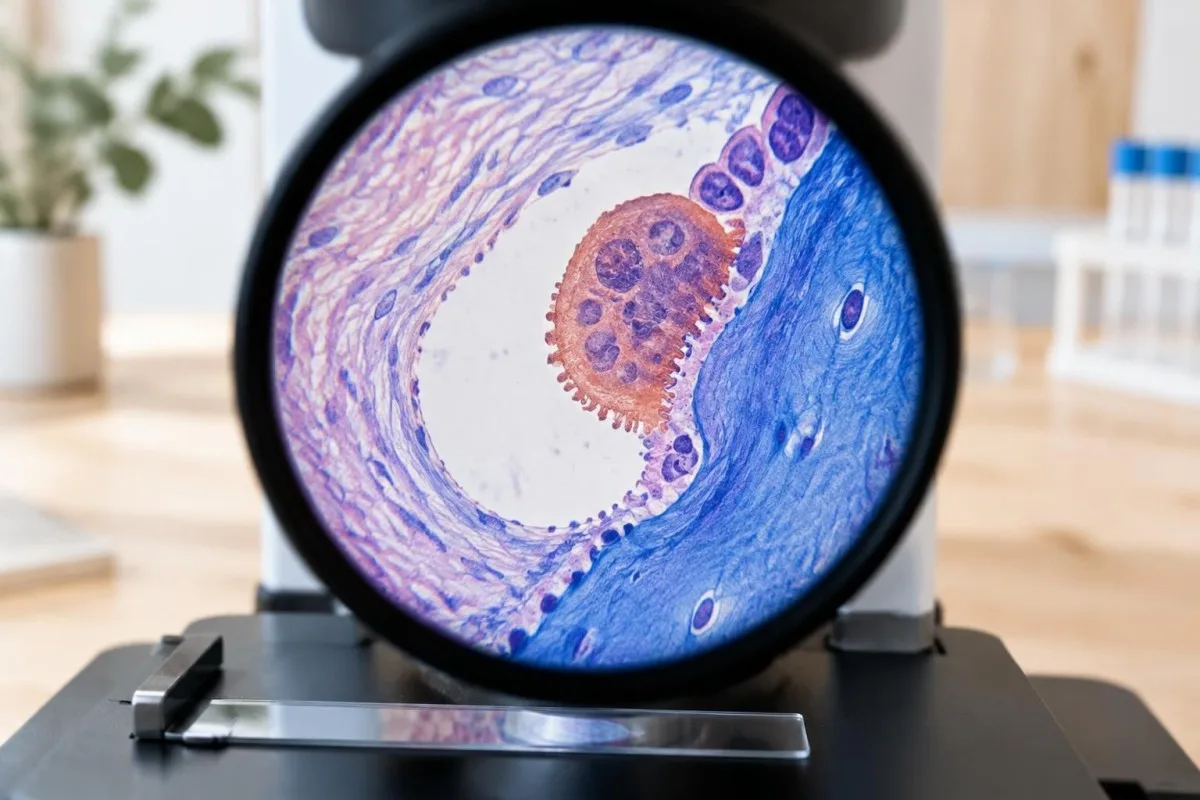
Bisphosphonates remain in bone for years, so CTX may stay suppressed after treatment stops, particularly after intravenous zoledronic acid. A CTX of 150 pg/mL one year after stopping does not prove continued fracture protection, just as a CTX of 500 pg/mL does not automatically require immediate retreatment.
The evidence for using CTX thresholds to time a holiday is honestly mixed because studies use different assays, schedules and clinical outcomes. Eastell et al. describe this limitation in their review of bone turnover markers: biological plausibility is stronger than evidence for one universal decision cutoff.
の 基本的な血液検査ガイド offers a useful preparation framework for repeat testing, including why a baseline should be comparable with follow-up rather than simply convenient.
How does CTX compare with DXA and fracture risk?
DXA measures areal bone mineral density, while CTX measures a changing biochemical signal of resorption; neither test fully captures bone strength alone. A person can have low CTX and low bone density, or high CTX with a DXA result that is not yet osteoporotic.

DXA results are expressed as T-scores or Z-scores, whereas CTX is usually reported in pg/mL, ng/L or ng/mL. A T-score of −2.5 is a diagnostic criterion in relevant adults; no CTX value has the same diagnostic status.
Fracture risk also depends on previous hip or vertebral fracture, glucocorticoid exposure, age, falls, family history, smoking, alcohol and secondary disease. The reason CTX combined with DXA is more useful than CTX alone is that turnover and accumulated density describe different parts of the risk pathway.
A fracture-risk calculator may incorporate clinical variables that CTX does not capture. Kantesti's AI biomarker interpretation can help place a CTX result beside the rest of a laboratory report, but it cannot see vertebral imaging or independently confirm a fracture history.
How should you prepare for a repeat CTX test?
For a useful repeat CTX test, reproduce the same fasting period, morning collection time, laboratory method and medication timing whenever possible. Consistency often improves interpretation more than chasing a particular number.
Ask whether the laboratory requests 8〜12時間 without calories and whether water is allowed. Avoid unusually strenuous exercise for the preceding day if your clinician advises it, and document illness, fracture, immobilisation, supplements and any missed osteoporosis dose.
Do not independently stop denosumab, bisphosphonates, thyroid replacement or glucocorticoids to alter CTX. Bring the exact drug name, dose, route and last dose date; a medication taken 2 days ago and an injection given 2 months ago have very different implications.
If the first sample was afternoon, non-fasting or processed by another assay, the clinician may prefer a new standardised baseline rather than a direct percentage comparison. Our blood test result timeline explains how timing, illness and medicines can create apparent changes.
How should you discuss CTX test results?
Discuss CTX with the clinician who knows your DXA, fracture history, kidney function and osteoporosis treatment plan. The most useful question is usually not “Is my CTX normal?” but “What does this result mean for my current clinical context and treatment timing?”
Bring the report's reference interval, units, collection time, fasting duration, recent meals, recent exercise and the date of your last osteoporosis medicine. A CTX of 400 pg/mL has a different meaning in an untreated 35-year-old, a postmenopausal person on alendronate and a patient with eGFR of 25.
Seek prompt medical advice for a new low-trauma hip or vertebral fracture, severe new back pain, marked height loss or symptoms suggesting calcium disturbance; CTX is not an emergency triage test. A very high value should usually lead to review, not panic, because sampling conditions and secondary causes can produce large differences.
Our AI blood test analysis tool can summarise CTX alongside related laboratory values and flag questions for follow-up, while its interpretation remains informational rather than a diagnosis or medication instruction. For technical details about how our AI works, see the Kantesti テクノロジーガイド.
よくある質問
骨粗鬆症における適切なCTX値とは?
骨粗鬆症を診断または除外する単一のCTX値はありません。成人の朝の測定では、未治療の場合に約300~600 pg/mLを示すことがありますが、年齢、閉経、腎機能、絶食、採取時間、測定法によって解釈は大きく変わり得ます。関連する骨格部位でのDXA Tスコアが−2.5以下であること、または基準を満たす脆弱性骨折があることは、CTXにはない診断上の重要性を持ちます。CTXは、臨床評価と併せて、治療モニタリングまたは骨代謝回転マーカーとして使用するのが最適です。
CTX血液検査は空腹時に受けるべきですか?
多くの検査室では、食事によってCTXが数時間抑制される可能性があるため、午前中のCTX血液検査の前に8~12時間の一晩の絶食を求めています。通常、水は飲んでも構いませんが、カロリー、牛乳、加糖飲料は標準化に影響することがあります。検査を指示した臨床医から指示がない限り、処方された骨粗鬆症治療薬や甲状腺薬の服用を中止しないでください。午前8時に採取した絶食時の結果は、午後に採取した非絶食時のサンプルよりも、同様の時間帯に採取した別の絶食時の結果とのほうが比較しやすくなります。
What does a high CTX result mean?
A high CTX result suggests increased bone resorption or reduced clearance, but it does not prove osteoporosis. Menopause, recent fracture healing, immobilisation, hyperparathyroidism, untreated hyperthyroidism, low vitamin D with secondary parathyroid activity and kidney disease can all affect CTX. A result above 600 pg/mL may be high in some adult morning assays, while other laboratories use different intervals. The report should be reviewed with medication history, eGFR, calcium, phosphate, alkaline phosphatase, parathyroid hormone and DXA.
What does a low CTX result mean?
A low CTX result commonly indicates suppressed bone resorption, especially after bisphosphonate or denosumab treatment. Values below 100 pg/mL can occur during effective antiresorptive therapy, but they can also occur naturally or after a fasting morning collection. Low CTX does not prove that bone density is normal or that fracture risk is absent. Medication timing, treatment adherence, DXA findings and fracture history determine whether the result is reassuring or expected.
How quickly does denosumab lower CTX?
Denosumab can lower CTX rapidly, with reductions of approximately 70-90% reported within days to weeks in many treatment studies. CTX may rise again as the six-month dosing interval ends or when an injection is delayed. The result must therefore be interpreted against the exact injection date rather than a generic “on treatment” label. Denosumab should not be stopped or delayed without a clinician-directed plan because rebound bone turnover and vertebral fracture risk can occur after cessation.
Can kidney disease make CTX high?
Yes, reduced kidney function can raise CTX because the kidneys help clear CTX fragments and chronic kidney disease can alter mineral and bone metabolism. An eGFR below 60 mL/min/1.73 m² deserves particular caution, while advanced kidney disease can make standard osteoporosis reference intervals unsuitable. A CTX of 840 pg/mL with eGFR 38 is not interpreted like the same CTX with eGFR 95. Creatinine, eGFR, calcium, phosphate, parathyroid hormone and alkaline phosphatase should be reviewed together.
血液検査結果の見方を確認しましょう
検査報告書をアップロードすると、KantestiのAIが数秒で各バイオマーカーを平易な言葉で説明します。世界中で200万人以上が利用しています。.
参考文献
- Klein, T., Mitchell, S., & Weber, H. (2026). ニパウイルス血液検査:早期検出・診断ガイド2026。. Kantesti AI医学研究。. 掲載日
- Klein, T., Mitchell, S., & Weber, H. (2026). B型陰性血液型、LDH血液検査、網赤血球数ガイド。. Kantesti AI医学研究。. 掲載日
- Vasikaran S et al. (2011). Markers of bone turnover for the prediction of fracture risk and monitoring of treatment: a need for international reference standards. Osteoporosis International. 掲載日
- Eastell R et al. (2018). Bone turnover markers: are they clinically useful? European Journal of Endocrinology. 掲載日
- 200万以上分析対象の検査
- 127+国
- 100+言語
医療チームについて


E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
Thomas Klein医師による医学的レビュー。Sarah Mitchell医師およびHans Weber教授の協力。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.



医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
公開 · 編集チームにお問い合わせください
Kantesti Ltdが発行。イングランドおよびウェールズで登録、会社番号. 17090423, 、英国ロンドン。.
