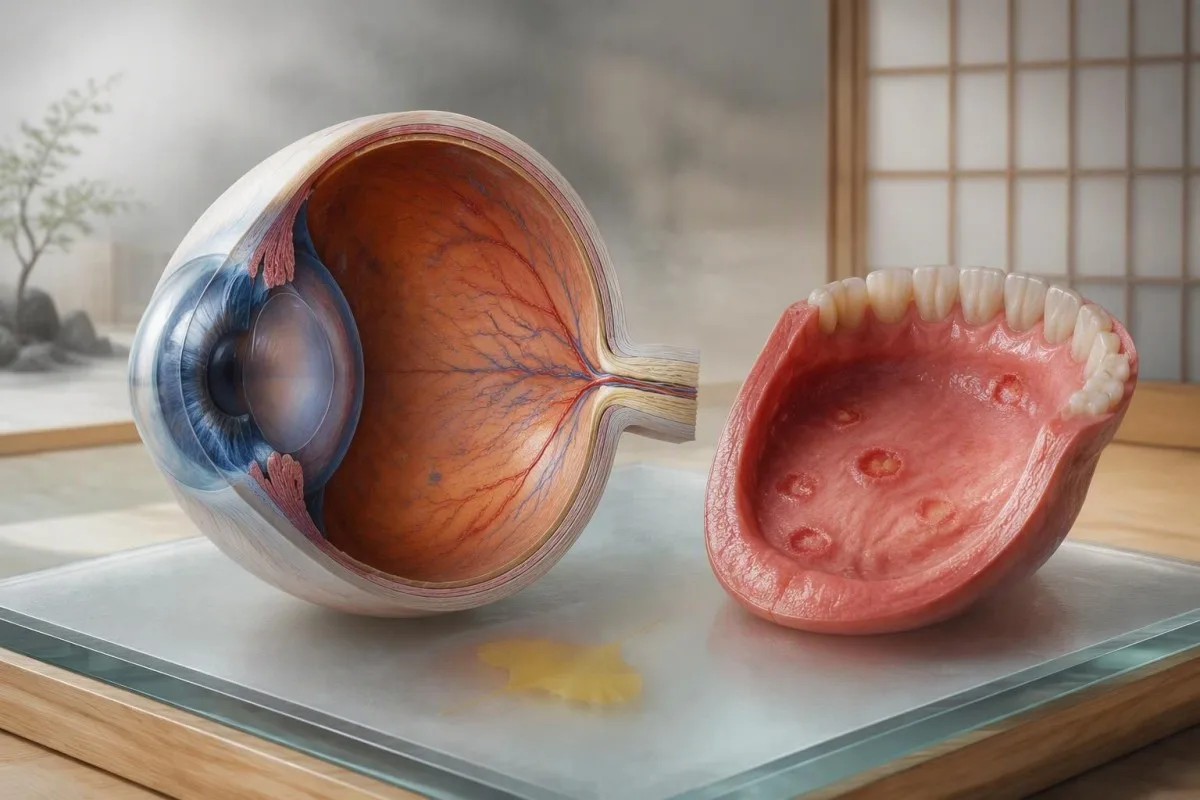
Recurring mouth sores alone are common; mouth sores plus eye pain, genital ulcers, unusual skin lesions, or clot-like symptoms need a different level of attention. As of September 23, 2026, this guide uses a symptom-first approach to help you act without trying to diagnose yourself.


- Eye pain with light sensitivity needs same-day ophthalmology or emergency assessment, especially if vision is blurred or reduced.
- Recurrent mouth ulcers occurring at least 3 times in 12 months are part of older Behçet classification criteria, but do not diagnose Behçet by themselves.
- ICBD scoring assigns 2 points each to oral ulcers, genital ulcers, and eye disease; a total of 4 or more supports classification after clinical assessment.
- Genital ulcers from Behçet often heal with a scar, whereas many common infectious causes need swab testing and different treatment.
- CRPとESR can be normal during a Behçet flare and cannot exclude eye, vessel, neurological, or bowel involvement.
- Sudden visual change is an emergency because untreated posterior uveitis can threaten sight over days rather than months.
- No blood test confirms Behçet disease; diagnosis depends on the recurring pattern, examination findings, and careful exclusion of mimics.
- Medication timing matters: starting steroid tablets before an eye examination can partially mask visible inflammation but should never delay urgent care.
Which Behçet symptoms need action today?
Eye pain, new light sensitivity, floating spots, a red eye with blurred vision, or any drop in vision need same-day assessment because Behçet-related uveitis can affect the retina as well as the front of the eye. A painful mouth ulcer alone rarely needs emergency care, but the combination of recurrent ulcers and eye symptoms changes the calculation quickly.
Call emergency services or attend an emergency eye service now for sudden loss of vision, a curtain or shadow, severe headache with a painful red eye, weakness, confusion, coughing blood, or one-sided leg swelling. These symptoms are not specific to Behçet disease, but they can signal eye, neurological, arterial, or venous complications where hours matter.
For a painful red eye without visual change, I still advise assessment within 24 hours rather than waiting for a routine appointment. In my clinical experience, patients often call it “conjunctivitis” because the eye looks red; uveitis symptoms more often include deep ache, photophobia, and a sense that indoor light is oddly harsh.
カンテスティは AI血液検査分析装置 that can organize inflammatory markers, full blood count results, liver and kidney values for a clinician conversation, but it cannot assess vision or rule out uveitis. If you have laboratory reports alongside symptoms, our 血液検査のバイオマーカーガイド can help you identify what was measured.
When recurrent mouth ulcers point beyond canker sores
Recurrent mouth ulcers are common and usually are not Behçet disease, particularly when they are small, heal within 7 to 14 days, and occur without genital, eye, skin, joint, vascular, or neurological symptoms. Behçet becomes more plausible when painful oral ulcers recur in clusters and are accompanied by disease in another body system.
The 1990 International Study Group criteria used recurrent oral ulceration at least 3 times in 12 months as an entry feature, plus two of genital ulcers, eye lesions, skin lesions, or a positive pathergy test. Those criteria were designed for classification in research, not for telling a person at home that they do or do not have the condition (International Study Group for Behçet’s Disease, 1990).
Aphthae from stress, a cheek bite, orthodontic friction, sodium-lauryl-sulfate toothpaste, iron deficiency, vitamin B12 deficiency, folate deficiency, celiac disease, or inflammatory bowel disease can look remarkably similar. Ulcers on the soft palate or attached gum, grouped tiny blisters, or a first episode with fever lean more toward herpes-family infections than typical aphthae.
Take dated phone photographs with a coin-sized scale object beside the area, then record how many days each episode lasts. That simple diary is often more diagnostically useful than a single normal CRP; our guide to B12 と葉酸の症状 explains two correctable contributors to recurrent ulcers.
How genital ulcers change the differential diagnosis
Genital ulcers that recur with mouth ulcers deserve prompt sexual-health or specialist assessment, but Behçet is only one possible cause. Behçet ulcers are often deep, painful, and may leave a scar; swab-confirmed infections, inflammatory skin conditions, and medication reactions require different care.
A new genital ulcer should usually be examined while active, ideally within 48 to 72 hours, because herpes PCR swabs are most informative before the affected surface begins to heal. Syphilis testing is also appropriate when exposure history or examination suggests it, even though a classic syphilis ulcer is often painless.
In Behçet disease, genital ulcers commonly involve the scrotum in men and the vulvar area in women, and scar formation after healing is a useful historical clue. Do not assume that a negative STI screen proves Behçet: fixed drug eruption, Crohn disease, lichen planus, and complex aphthosis remain possibilities.
Clinicians ask about medicines taken in the prior 1 to 3 weeks, including non-steroidal anti-inflammatory drugs and antibiotics, because drug reactions can mimic inflammatory ulcers. If urinary discomfort is part of the story, this overview of urine testing and culture explains why a dipstick alone cannot identify an ulcer cause.
What uveitis symptoms feel like and why they are urgent
Behçet-related uveitis can cause eye pain, light sensitivity, redness, floaters, haze, or reduced vision, and it requires urgent slit-lamp and retinal examination. A normal-looking eye does not safely exclude posterior uveitis, which may be relatively painless yet threaten central vision.
Anterior uveitis tends to cause ache, photophobia, and a red ring around the iris; posterior inflammation more often produces floaters, distortion, blind patches, or declining sharpness. Behçet can produce occlusive retinal vasculitis, which is why an ophthalmologist may use dilated examination, optical coherence tomography, and fluorescein angiography rather than relying on visual acuity alone.
The EULAR 2018 recommendations advise close collaboration between rheumatology and ophthalmology for eye involvement and favor immunosuppressive treatment for posterior-segment disease rather than steroid-only management (Hatemi et al., 2018). The immediate point is practical: do not drive yourself if your vision is changing.
I have seen patients postpone review because their redness faded overnight while the floaters remained. Persistent floaters after a painful red eye are not a “watch it for a week” symptom; compare this with other causes of eye pressure and field loss in our glaucoma testing guide.
Skin, joint, bowel and neurological clues worth reporting
Behçet disease can affect skin, joints, the gut, brain, and blood vessels in addition to the mouth and eyes. A tender red lump on the shin, acne-like pustules after adolescence, swollen knees or ankles, recurrent abdominal pain with diarrhea, or severe new headaches each adds useful pattern information.
Joint symptoms usually involve a few large joints and can be intermittent, with knees, ankles, and wrists appearing often in clinic histories. A visibly swollen joint with fever needs same-day assessment because septic arthritis is a separate emergency and cannot be distinguished from an inflammatory flare by symptoms alone.
Bowel involvement may cause cramping, diarrhea, weight loss, or blood in stool, but these symptoms overlap substantially with Crohn disease and ulcerative colitis. Fecal calprotectin above a laboratory’s reference interval supports intestinal inflammation, yet it does not name the cause; our explanation of カルプロテクチン対ラクトフェリン covers that limitation.
New severe headache, double vision, balance trouble, weakness, altered behavior, or fever with neck stiffness needs emergency assessment. Neuro-Behçet is uncommon, but delaying evaluation because a person assumes every symptom is “just a flare” is a mistake I want readers to avoid.
When blood vessel symptoms are an emergency
One-sided leg swelling, chest pain, sudden breathlessness, coughing blood, or a cold painful limb need emergency evaluation in anyone with suspected or confirmed Behçet disease. Behçet can inflame veins and arteries, and a clotting event must be assessed with imaging and specialist judgment rather than a home symptom checklist.
A swollen painful calf can be deep-vein thrombosis, cellulitis, muscle injury, or a ruptured cyst; ultrasound is commonly needed to separate them. A D-dimer result is not definitive in active inflammatory disease because inflammation itself can increase the value, as discussed in our D-ダイマー精度ガイド.
Behçet-related thrombosis is unusual in that vein-wall inflammation may contribute directly, so treatment plans can differ from an ordinary provoked clot. This is exactly why anticoagulant decisions should involve clinicians familiar with the person’s vascular imaging and aneurysm risk rather than internet dosing advice.
体温が 38.0°C with a hot, swollen limb or chest symptoms is an emergency threshold in practical terms, not a diagnostic threshold for Behçet. Get urgent care first; sorting out whether Behçet was involved comes later.
Why there is no single blood test for Behçet disease
No blood test confirms or excludes Behçet disease. Diagnosis is clinical: clinicians combine recurring features over time, examine active findings, consider geography and family history, and exclude infections, inflammatory bowel disease, lupus-spectrum conditions, and other mimics.
The International Criteria for Behçet’s Disease assigns 2 points each for oral aphthosis, genital aphthosis, and ocular lesions; skin, neurological, and vascular manifestations score 1 point each, and a pathergy test can add 1 point. A score of 4点以上 classifies patients for research purposes, but it is not a substitute for clinical judgment (Davatchi et al., 2014).
CRP may be raised during active systemic inflammation, while ESR can remain elevated longer after symptoms settle; both can be normal in isolated eye or neurological disease. A full blood count may show anemia, high platelets, or neutrophilia, but none is specific enough to use as a Behçet test.
カンテスティは AI血液検査の読み方プラットフォーム that reads CBC, CRP, ESR, ferritin, kidney and liver results together with their laboratory ranges, not as diagnostic proof of an inflammatory disease. For context on autoimmune screening limits, see our ANA test explanation.
What tests a specialist may use after the symptom history
Specialists choose tests to document organ involvement and rule out alternatives, not to find a single Behçet marker. The useful test depends on your symptoms: urgent ophthalmic imaging for visual complaints, swabs for active genital ulcers, stool testing for bowel symptoms, and ultrasound or CT imaging for suspected vascular disease.
An eye team may measure visual acuity, intraocular pressure, and retinal thickness, then photograph retinal vessels during an active episode. For a person with mouth ulcers plus chronic diarrhea, coeliac serology, stool calprotectin, colonoscopy, and biopsies may be more informative than repeating broad autoimmune antibody panels.
Pathergy testing involves a standardized small skin prick and is interpreted 24 to 48 hours later; positivity varies substantially by population and technique. HLA-B51 is associated with Behçet risk in some populations, but a positive result is neither diagnostic nor a reason to treat an asymptomatic person.
Bring previous eye letters, ulcer photographs, medication dates, and every laboratory report to the consultation. Kantesti AI can help create a chronological laboratory summary; our AI trend analysis guide explains why the date of a CRP is as relevant as the number.
How to document symptoms before a rheumatology visit
A dated symptom record can shorten the route to an accurate diagnosis because Behçet features come and go. Record the first day, last day, location, severity from 0 to 10, photographs of visible findings, and whether eye or neurological symptoms occurred in the same 30-day period.
Use four columns: mouth or genital ulcers; eye symptoms; skin or joint symptoms; and systemic symptoms such as fever, bowel change, headache, or leg swelling. Write down treatments and response, including topical steroid use, colchicine, antibiotics, and the exact day treatment began; medication can alter what the clinician sees.
A lesion that lasts more than 21 days, is unusually large, or repeatedly occurs in exactly the same location merits direct examination even without other Behçet features. Weight loss of 5% or more over 6 to 12 months, persistent fever, and waking night sweats are broader red flags that should not be attributed to aphthae automatically.
Dr. Thomas Klein’s practical rule is simple: bring evidence of the episode, not only a memory of it. If your results span several years, this 長期的な検査ガイド shows which context details make changes interpretable.
What can ease symptoms while you wait for medical review
Topical treatments can reduce the pain of mouth ulcers, but they do not protect vision or treat vascular, neurological, or bowel Behçet disease. For uncomplicated oral aphthae, clinicians may use topical corticosteroids early in an episode, anesthetic rinses, or protective pastes after checking for infection and medication contraindications.
Avoid acidic, sharp, or very hot foods during active ulcers, and use a soft toothbrush; these measures reduce mechanical irritation but do not alter disease activity. Alcohol-containing mouthwash can sting and worsen dryness, so a bland saline rinse is often better tolerated.
Colchicine is commonly considered for recurrent mucocutaneous and joint manifestations, while eye, vessel, nervous-system, and severe gastrointestinal disease usually require specialist-directed immunosuppression. The exact drug choice depends on the organ involved, pregnancy plans, infection risk, previous treatment, and local prescribing practice; it should never be copied from a social-media post.
Do not start leftover oral steroids to manage an eye flare without speaking to an eye clinician. If ulcers make eating difficult, our article on 鉄分を多く含む食品 may help with gentle nutrition planning when iron intake has fallen, but supplements need laboratory context.
Common misconceptions about Behçet symptoms
A normal CRP, a negative ANA, or a lack of family history does not rule out Behçet disease; equally, recurring ulcers do not prove it. The diagnosis sits in the pattern over time, which is why certainty sometimes takes months and occasionally longer.
Misconception one: Behçet only occurs in people from one region. Prevalence is higher along the historical Silk Road, but the disease occurs worldwide and clinicians should assess the phenotype, not use ancestry as an exclusion rule. Age of onset is often in early adulthood, yet new symptoms at other ages still deserve a proper differential.
Misconception two: every flare must raise laboratory inflammation markers. Behçet activity can be localized, and a CRP below a laboratory’s upper limit does not overrule a new visual complaint or documented retinal inflammation. Our article on ESR and CRP patterns explains why inflammatory tests can disagree.
Misconception three: all genital ulcers are sexually transmitted. Testing is sensible and stigma-free, but a clinician should consider the full list of genital ulcers causes rather than stopping after one negative result.
How to read blood results without missing the clinical picture
Blood results can identify anemia, nutritional deficiencies, medication effects, and systemic inflammation, but they cannot measure Behçet activity in the eye or prove the diagnosis. A result should be interpreted against your own baseline, current symptoms, medication list, and the laboratory’s reference interval.
A CBC can show microcytic anemia from iron deficiency, macrocytosis from B12 or folate deficiency, or raised platelets during inflammation; these patterns often explain fatigue or recurrent ulcers better than an autoimmune label. Ferritin may rise during inflammation, so a “normal” ferritin does not always exclude depleted iron stores when CRP is high.
Kidney and liver panels matter before and during some immunomodulatory treatments, but a single mild ALT rise has many alternative explanations. Read serial results rather than assuming a medication caused every out-of-range value; our liver test guide は、一般的な交絡因子を概説しています。.
カンテスティは AI搭載の血液検査解析ツール that can flag a trend for discussion while preserving the original laboratory units and reference intervals. Dr. Thomas Klein recommends taking the original PDF to your clinician, because an AI interpretation is context support, not an examination or prescription.
Who should request rheumatology and ophthalmology review
People with recurring oral ulcers plus genital ulcers, uveitis symptoms, characteristic skin findings, unexplained clots, or recurrent inflammatory joint symptoms should request specialist review. A person with eye symptoms should see ophthalmology urgently; rheumatology evaluation should not delay that eye assessment.
Primary care can begin the workup by examining active lesions, arranging ulcer swabs where appropriate, checking CBC, ferritin, B12, folate, CRP, ESR, and targeted infection testing, then referring based on the pattern. A suspected clot, focal neurological deficit, or visual change bypasses the ordinary outpatient pathway.
Ask the specialist three specific questions: which findings support Behçet versus a mimic; which organ complications should trigger urgent contact; and which monitoring tests are required if treatment starts. That conversation is more useful than asking whether one antibody was “positive enough.”
Kantesti’s medical content is reviewed against clinical safety standards, and readers can see our approach in 医学的検証. For questions about clinician oversight and our team, visit the 医療諮問委員会.
A practical next-step plan for recurring ulcers and eye pain
Act today for any vision change, severe red painful eye, sudden breathlessness, one-sided limb swelling, new weakness, or confusion; otherwise, book prompt review when ulcers recur across more than one body site. Do not wait for a blood test result to decide whether a visual symptom needs urgent assessment.
For isolated mouth ulcers, photograph the episode, count recurrences over 12 months, check for triggers, and arrange routine care if episodes are frequent, severe, or prolonged. For mouth plus genital ulcers, ask for examination during an active episode and appropriate infection testing before assuming an inflammatory cause.
For eye pain, light sensitivity, floaters, or blur, contact an emergency eye service or emergency department the same day. Bring your symptom diary and medication list, but do not delay leaving home to collect every report; vision assessment comes first.
Kantesti helps people organize laboratory information across visits, while diagnosis and treatment remain with the treating clinician. Read more about the people behind the organization on our About Usページ, and use this article as a discussion tool rather than a self-diagnosis checklist.
よくある質問
再発性の口内炎は、ベーチェット病の唯一の症状になり得ますか?
再発性の口内炎はベーチェット病で起こり得ますが、再発性アフタ性口内炎やその他の一般的な原因によることがはるかに多いです。以前の国際ベーチェット病調査グループ(ISG)の診断基準では、分類のために12ヶ月以内に少なくとも3回の口腔潰瘍エピソードと、さらに2つの追加の特徴カテゴリーが必要でした。したがって、再発性の口腔潰瘍のみではベーチェット病とは診断されません。21日以上続く再発性の潰瘍、性器潰瘍や眼症状を伴う潰瘍、または食事摂取を制限する潰瘍は、医学的な診察を受ける価値があります。.
ベーチェット病のどのような眼症状が緊急のケアを必要としますか?
新しいかすみ目、視力低下、飛蚊症、著しい光過敏、痛みを伴う赤い目、または視野の影は、ぶどう膜炎や網膜の関与を反映する可能性があるため、同日中の眼科検査が必要です。後部ぶどう膜炎は、ほとんど赤みや痛みがなく、飛蚊症や視覚の歪みを引き起こすことがあります。視力が変化した場合は、CRPの結果や通常の膠原病科の診察のために24〜48時間待たないでください。突然の視力喪失、激しい頭痛、または神経症状は、救急サービスを必要とします。.
ベーチェット病の口内炎は、普通のカンカーソル(アフタ性口内炎)と見た目が違いますか?
ベーチェット病の口腔潰瘍は、通常のアフタ性潰瘍と似ていることが多く、見た目だけでは信頼性がありません。通常は痛みを伴い、円形または楕円形をしており、群発して再発することもあります。より情報価値のある手がかりは、性器、眼、皮膚、関節、腸、血管などの他の部位での病気の繰り返しです。ベーチェット病の潰瘍は7日から21日で治癒することがありますが、21日を超える持続的な罹患部位は、他の原因について直接評価する必要があります。日付入りの写真と12ヶ月間の再発回数は臨床的に有用です。.
血液検査でベーチェット病を診断できますか?
血液検査でベーチェット病を正確に診断し、確定または除外することはできません。 CBC、CRP、ESR、フェリチン、B12、葉酸、腎機能検査、肝機能検査、感染症検査、および標的型画像検査は、結果または競合する診断を特定できます。 ICBD分類システムは臨床所見を使用しており、口腔、性器、眼の所見で2点、4点以上で分類を支持します。 CRPが正常であっても、眼または神経系の関与を除外するものではありません。.
ベーチェット病以外で最も一般的な性器潰瘍の原因は何ですか?
一般的な性器潰瘍の原因には、単純ヘルペス感染症、梅毒、固定薬疹、炎症性腸疾患、扁平苔癬、外傷性刺激、非特異的アフタなどが含まれます。ヘルペスPCR検査が最も有効な活動期に新鮮な潰瘍を検査することは、理想的には48~72時間以内に行うべきです。ベーチェット病の潰瘍は再発したり瘢痕を残したりする可能性がありますが、瘢痕形成だけでは診断できません。性感染症検査は定期的な医療行為であり、原因についての判断を示すものではありません。.
Should I ask for HLA-B51 testing if I suspect Behçet disease?
HLA-B51 testing can show a genetic association with Behçet disease, but it cannot diagnose the condition or determine whether treatment is needed. Many people with HLA-B51 never develop Behçet disease, and many confirmed patients do not carry it. Specialists may use it as minor contextual information in a difficult case, particularly when the clinical pattern is incomplete. Active eye findings, genital ulcers, vascular symptoms, and a documented recurrence pattern carry much more practical weight.
今日、AIによる血液検査分析を
いますぐ利用しませんか。即時で正確な検査分析を提供するKantestiを信頼する、世界中の200万人以上のユーザーに参加してください。血液検査結果をアップロードすると、15,000+のバイオマーカーについて数秒で包括的な解釈が得られます。.
📚 参考文献
Klein, T., Mitchell, S., & Weber, H. (2026). 多言語AI支援臨床意思決定サポートによるハンタウイルス早期トリアージ:設計、工学的検証、および50,000件の解釈済み血液検査レポートにわたる実世界展開。(2026)。Figshare。https://doi.org/10.6084/m9.figshare.32230290。ResearchGate: https://www.researchgate.net。Academia.edu: https://www.academia.edu。..。 Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). A Pre-Registered, Rubric-Based Automated Technical Benchmark of the Kantesti Blood-Test Interpretation Engine on 100,000 Synthetic Test Cases. (2026). Figshare. https://doi.org/10.6084/m9.figshare.32095435. ResearchGate: https://www.researchgate.net. Academia.edu: https://www.academia.edu..。 Kantesti AI Medical Research.
📖 外部の医学的参考文献
⚕️ 医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
トーマス・クライン博士が執筆し、サラ・ミッチェル博士およびハンス・ヴェーバー教授によるレビュー。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.