
A positive flu A test usually means influenza virus was detected in your respiratory sample. Most uncomplicated symptoms improve within 3–7 days; antiviral decisions depend on symptom timing, risk factors, and illness severity.

Wichtichste punten
- Positive útkomst means influenza A antigen or genetic material was detected; the test does not measure how severe your illness will become.
- Expected recovery is usually 3–7 days for the acute illness, although cough and fatigue can continue for 2 weeks or longer.
- Antiviral timing matters most within 48 hours of symptom onset, but severe illness and high-risk patients may benefit from treatment started later.
- Standard adult oseltamivir treatment is 75 mg twice daily for 5 days when kidney function permits; a clinician must select the appropriate prescription.
- Groepen mei heger risiko include adults aged 65 or older, children younger than 5, pregnant people, and people with certain chronic conditions or weakened immunity.
- Besmetlikens commonly begins about 1 day before symptoms and continues for 5–7 days afterward; children and immunocompromised people may shed virus longer.
- Return to activities generally requires improving symptoms and at least 24 hours without fever or fever-reducing medication under CDC community guidance, followed by 5 days of added precautions.
- Driuwende warskôgingssymptomen include breathing difficulty, persistent chest pressure, confusion, severe dehydration, or deterioration after initial improvement; do not wait for another test.
What should you do after an influenza A positive result?
In influenza A positive result usually means flu virus was detected: stay home, rest, drink fluids, and contact a clinician promptly if you are high-risk or symptoms started within 48 oeren. Most uncomplicated illness improves within 3–7 dagen, but breathing difficulty, chest pain, confusion, or severe dehydration needs urgent assessment.

Count the 48-hour treatment window from your first symptoms, not from when the laboratory released the result. A hypothetical person who developed chills on Monday evening and received a positive result on Wednesday morning may still be within that window; someone tested on day 5 is not.
Record 3 useful details before calling: when symptoms began, your highest measured temperature, and whether you can drink and urinate normally. Add pregnancy, immune-suppressing medicines, chronic heart or lung disease, and kidney problems, because those details can change the decision even when the positive test looks identical.
A positive result is not a severity score. Two people with the same report can need different care: a healthy 25-year-old improving on day 4 may need supportive treatment, while a 70-year-old with worsening breathlessness needs prompt examination regardless of how faint the test line appears.
Kantesti is in AI bloedtestanalysator that helps explain accompanying laboratory findings, not a substitute for respiratory examination or antiviral prescribing. Our organisaasje en doel explain that distinction; a flu swab and a CBC answer 2 different clinical questions.
What does a positive influenza A test actually detect?
A positive influenza A test detects either viral proteins on a rapid antigen assay or viral genetic material on a molecular assay such as PCR. Neither result alone establishes how infectious you are, how severe your illness is, or which influenza A subtype you have; many routine reports simply distinguish A from B.

Rapid antigen tests usually produce a result in about 10–15 minutes, but a faint detection line must still be interpreted using that kit's instructions. A line appearing after the permitted reading window, or a missing control line, cannot be treated as a valid positive result.
PCR amplifies selected RNA sequences and is generally more sensitive than traditional rapid antigen testing. Some rapid molecular systems return results within 15–30 minuten, so speed alone does not identify the technology; the IDSA influenza guideline recommends molecular testing over traditional antigen assays when available in relevant clinical settings (Uyeki et al., 2019).
Routine seasonal tests often do not distinguish A(H1N1)pdm09 from A(H3N2), and they do not automatically identify an unusual animal-associated influenza strain. Tell your clinician about recent poultry, livestock, or relevant occupational exposure rather than assuming that an ordinary A-positive report has answered the subtype question.
Flu antigen and PCR results are usually kwalitatyf, not measurements comparable with a glucose concentration in mg/dL. Our explanation of kwalitative versus kwantitative resultaten clarifies why a detected/not-detected report cannot be converted into a percentage of illness severity.
Could an influenza A positive result be wrong?
An influenza A positive result can occasionally be false, especially with an antigen test when little flu is circulating. Traditional rapid antigen assays have often shown approximately 50–70% sensitivity and 95–99% specificity, although performance varies substantially by product, specimen quality, age, and testing conditions.

Consider a clearly hypothetical test with 60% sensitivity and 98% specificity used in 1,000 people when 5% truly have influenza. It would identify about 30 true positives and 19 false positives, so approximately 61% of positive results would represent true influenza—not 98%, because specificity and positive predictive value are different measures.
By 30% prevalence, that same hypothetical test would produce about 180 true positives and 14 false positives among 1,000 people. Its positive predictive value would rise to roughly 93%; this is why clinicians weigh local circulation and symptoms rather than treating every positive rapid result as equally certain.
A positive antigen result followed by a negative PCR deserves context, not an automatic verdict that 1 test must be defective. Different collection times, swab sites, sampling quality, and assay targets can contribute to disagreement; repeat molecular testing may be appropriate when the result changes treatment or institutional precautions.
Another respiratory virus can produce similar symptoms, and 2 viruses can coexist. Us gids foar RSV-symptomen by folwoeksenen explains overlapping presentations; separately, recent live nasal influenza vaccination can occasionally affect molecular detection, whereas an injected inactivated flu vaccine cannot create influenza RNA in a nasal swab.
How long does influenza A last?
Uncomplicated influenza A usually causes 3–7 dagen of acute illness, with fever often lasting around 3–4 days. Cough, reduced stamina, and fatigue can continue for 2 weeks or longer, particularly in older adults or people with chronic lung disease; gradual improvement matters more than a fixed recovery deadline.
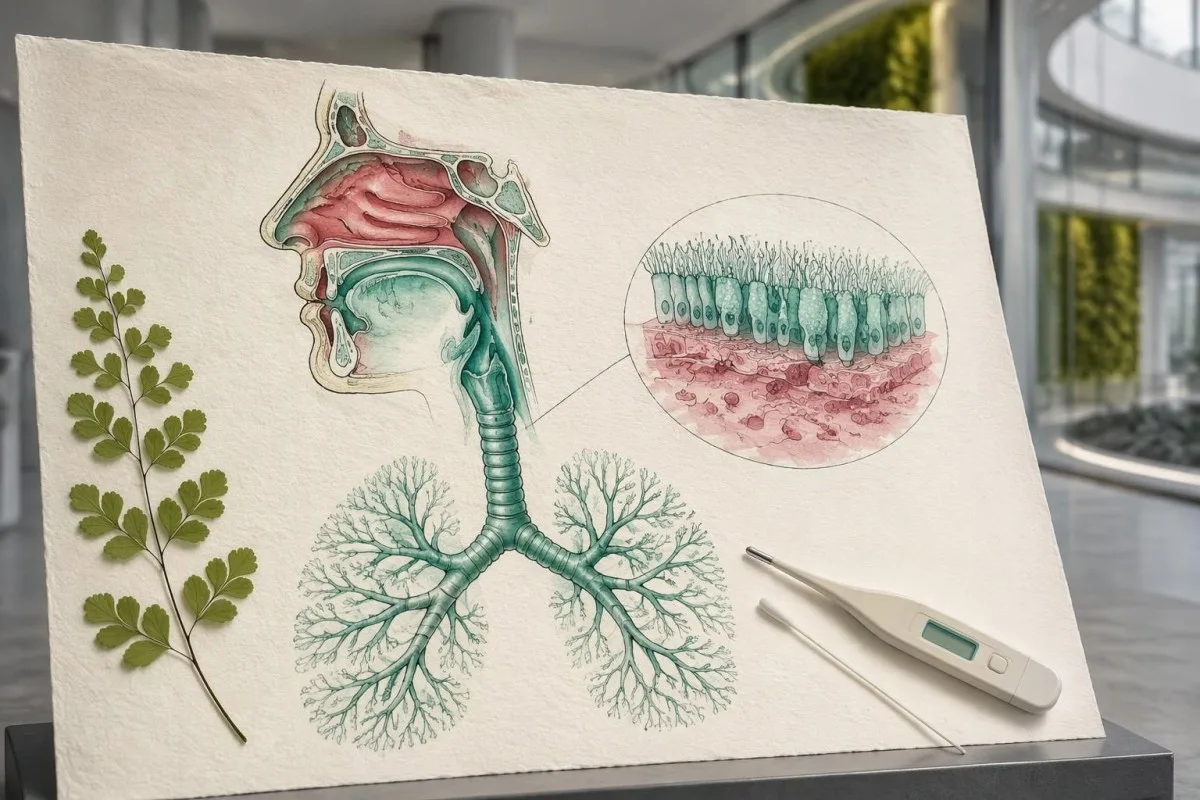
Influenza symptoms commonly begin 1–4 days after exposure, with an average incubation around 2 days. Day 1 of illness means the first symptoms, not the exposure day; mixing those starting points makes recovery and antiviral timelines appear contradictory when they are not.
A hypothetical adult whose fever ends on day 4 may still cough on day 10 because airway irritation and clearance mechanisms recover more slowly. A dry cough that is steadily easing is different from new breathlessness, recurrent fever, or chest pain after apparent recovery.
Persistent fever beyond approximately 4 dagen, or fever that returns after disappearing, warrants clinical advice—sooner for high-risk people or anyone worsening. This is a practical reassessment point rather than a diagnostic cutoff: some uncomplicated cases run longer, while a complication can appear before day 4.
Fatigue lasting 2-3 wiken does not by itself diagnose a chronic fatigue disorder, and supplements should not replace assessment when symptoms are substantial. Our persistent fatigue assessment guide distinguishes short post-viral recovery from a much longer syndrome; prolonged or worsening symptoms deserve a broader review.
Why does PCR positivity not precisely measure contagiousness?
PCR positivity does not precisely determine contagiousness because PCR detects influenza RNA, not whether enough viable virus is present to transmit to another person. Many adults can spread flu from about 1 day before symptoms until 5–7 days afterward, but RNA detection and infectious-virus shedding do not end on identical schedules.
Transmission risk is usually greatest during the first 3 days of illness, when respiratory viral burden is often high. Children and immunocompromised people may shed infectious virus for longer than typical adults, so their isolation decisions sometimes need individualized advice rather than a calendar copied from another household member.
A PCR result that remains positive after day 7 may reflect ongoing replication, residual RNA, or a mixture of both. Routine PCR cannot separate those possibilities reliably; viral culture can assess viable virus in specialized settings, but it is not a practical everyday clearance test.
A cycle threshold of 30, for example, is not a universal safe-to-return number. Ct values depend on the assay, specimen type, collection quality, and processing, and many reports omit them; using a cutoff from another laboratory can create false reassurance or unnecessarily prolonged isolation.
Persistent molecular detection is also discussed in our adenovirus PCR interpretation guide, but the timelines for 2 different viruses should not be equated. For influenza, assess symptom progression, time since onset, immune status, and the vulnerability of people you may expose.
When can you return to work, school, or normal activities?
Neffens CDC community respiratory-virus guidance, return to usual activities generally requires symptoms improving overall and at least 24 hours without fever, without fever-reducing medicine. After returning, use added precautions for 5 dagen; healthcare settings, vulnerable patients, local public-health rules, and school policies may require different arrangements.

Fever-free means fever-free without paracetamol, acetaminophen, or ibuprofen masking the temperature for those 24 oeren. If you never had fever, you still need overall symptom improvement; the absence of fever does not prove that you cannot transmit influenza.
During the next 5 dagen, improve ventilation, wear a well-fitting mask when appropriate, keep distance from vulnerable people, and use careful hand and cough hygiene. A hypothetical person returning on day 6 should not interpret permission to work as permission to share a poorly ventilated room with an immunocompromised relative.
UK public-facing advice commonly emphasizes staying home when you have a high temperature or feel too unwell for normal activities rather than using an identical numbered return rule. The 24-hour plus 5-day framework is a named CDC approach, not a universal legal requirement across every country or workplace.
Repeat PCR is not usually needed to return after uncomplicated flu, and a negative antigen test is not a complete transmission guarantee. Our gids oer herstel fan norovirus en oerdracht illustrates why rules differ between pathogens; do not borrow its commonly used 48-hour gastrointestinal exclusion interval for influenza.
Who should contact a clinician about antivirals today?
Prompt antiviral assessment is especially appropriate for hospitalized patients, severe or worsening illness, and people at increased complication risk—even when symptoms began more than 48 oeren ago. Higher-risk groups include adults 65 jier of âlder, children younger than 5, pregnant people, and people with important chronic conditions or weakened immunity.

Bern younger than 2 years have particularly high complication risk, while pregnancy-related risk continues through the first 2 weeks after delivery. Asthma, chronic lung or heart disease, diabetes, kidney disease, and immune suppression also influence treatment; US risk lists additionally include severe obesity, commonly defined as BMI 40 kg/m² or higher.
The IDSA guideline recommends starting treatment promptly for hospitalized or high-risk patients and those with severe or progressive illness, without delaying for test confirmation when influenza is suspected (Uyeki et al., 2019). Its 48-hour threshold mainly helps guide treatment of otherwise healthy outpatients; it is not a rule that forbids later treatment.
Imagine 2 hypothetical adults testing positive on day 4: a healthy 32-year-old whose symptoms are improving and a 68-year-old with diabetes and increasing breathlessness. Their prescriptions may differ because preventing complications in the second person matters more than achieving a small reduction in symptom duration in the first.
For children, dosing depends on age and weight, not simply dividing a 75 mg adult capsule without guidance. Our explanation of pediatric interpretation safety limits supports clinician-led decisions; vulnerable household contacts should also ask promptly whether exposure management is appropriate, especially within 48 hours of exposure.
What influenza A treatment can a clinician prescribe?
Influenza A treatment may include oseltamivir, baloxavir, inhaled zanamivir, or intravenous peramivir, depending on age, severity, pregnancy, kidney function, and local availability. A common adult oseltamivir regimen is 75 mg twice daily for 5 days, but that dose is not appropriate for everyone.
Oseltamivir is often preferred for hospitalized patients and during pregnancy because it has the most established clinical experience in those settings. Its usual adult dose assumes suitable renal clearance; dose adjustment is generally needed when creatinine clearance is 60 mL/min or lower, and children require age- or weight-specific prescriptions.
Baloxavir is a single-dose oral option for eligible uncomplicated influenza patients in some countries. For eligible patients weighing 20 to less than 80 kg, the usual dose is 40 mg; at 80 kg or more, it is 80 mg, and it should not be taken together with calcium-, iron-, magnesium-, or zinc-containing products because absorption can fall.
Inhaled zanamivir is commonly prescribed as 10 mg twice daily for 5 days, but clinicians generally avoid it in asthma or COPD because of bronchospasm risk. Peramivir can be given intravenously as a 600 mg single adult dose for appropriate uncomplicated cases with normal renal function; these alternatives are not interchangeable choices for every severely ill patient.
Kantesti is in AI-oandreaune ark foar analyse fan bloedtests that can help explain why kidney measurements affect medication discussions, without selecting or changing a prescription. Our klinysk validaasjeramtwurk describes interpretation safeguards, while niersresultaten nei útdroeging explains why a single illness-time eGFR may not represent your baseline.
How much do antivirals help, and what are the trade-offs?
For otherwise healthy adults treated early, oseltamivir generally shortens influenza symptoms by approximately 17–25 hours, not several guaranteed days. The size of benefit varies across analyses; evidence about preventing serious complications in uncomplicated outpatients is less consistent than evidence for modest symptom relief.

An individual-patient meta-analysis in The Lancet reported median symptom alleviation at 97.5 hours with oseltamivir versus 122.7 hours with placebo among adults with confirmed influenza (Dobson et al., 2015). Those trial averages do not predict exactly when an individual patient will recover, and treatment was studied mainly when started early.
A clinical-study-report review in BMJ estimated a smaller adult benefit of about 16.8 hours and questioned some complication outcomes because definitions and verification were inconsistent (Jefferson et al., 2014). The evidence here is genuinely mixed: different analysis populations and outcome definitions partly explain why the conclusions do not line up perfectly.
In the Dobson analysis, nausea occurred in approximately 9.9% versus 6.2%, and vomiting in 8.0% versus 3.3%, with oseltamivir versus placebo. Taking oseltamivir with food may improve tolerance; persistent vomiting matters because it can prevent hydration and reliable medication absorption, not merely cause inconvenience.
Kantesti does not translate a 1-day average benefit into a promise of preventing hospitalization or becoming noncontagious sooner. Medication review is particularly useful in older adults; our guide to medication effects in seniors explains why renal function and concurrent medicines deserve attention even when the antiviral course is short.
Which home treatments are useful and safe?
Useful home care includes regular fluids, rest, and fever or pain relief when appropriate; these measures improve comfort but do not directly eliminate influenza. For many adults, paracetamol or acetaminophen is taken as 500–1,000 mg per dose, with intervals and daily limits determined by the local product label and personal risk factors.

Do not exceed the package's daily acetaminophen limit, often 3,000–4,000 mg in adults, and obtain advice about lower limits with liver disease, low body weight, or regular heavy alcohol use. Combination cold remedies may contain the same ingredient; our acetaminophen overdose timing guide explains why accidental duplication needs prompt advice even before symptoms appear.
Ibuprofen may help suitable adults, commonly at 200–400 mg per over-the-counter dose, but dehydration, kidney disease, stomach ulcer history, anticoagulants, and pregnancy can make it unsuitable. Avoid using a fixed number of litres as a universal hydration target when heart or kidney disease requires fluid restriction; take small, frequent sips if nausea limits intake.
Do not give aspirin or salicylate-containing products to children or adolescents with suspected influenza unless a clinician specifically directs otherwise, because of Reye syndrome risk. Our salicylate safety explanation addresses a different concern—overdose—and reinforces why an adult 325 mg tablet is not a routine pediatric fever treatment.
Honey may soothe cough for children older than 1 year and adults, but it should never be given to infants younger than 12 months. Broth and ordinary food can help maintain intake; high-dose vitamin or zinc products are not proven influenza cures, and mineral supplements can interfere with single-dose baloxavir.
Which influenza symptoms require urgent medical care?
Seek emergency help for breathing difficulty, persistent chest pressure, new confusion, blue or grey lips, collapse, or inability to stay awake. Influenza can cause respiratory or other complications before a planned follow-up visit; a reassuring test result or fewer than 48 hours of symptoms does not make those warning signs safe to watch at home.
If you use a pulse oximeter, a repeated oxygen saturation of 92% or lower at sea level usually warrants emergency assessment unless a clinician has given a different individualized plan. Readings of 93–94%, a significant fall from your baseline, or worsening breathlessness need prompt advice; altitude, circulation, device quality, and skin pigmentation can affect accuracy.
In children, fast or laboured breathing, ribs pulling inward, unusual unresponsiveness, or dehydration with no urine for about 8 hours are urgent warning signs. A temperature of 38°C or higher in an infant younger than 3 months needs immediate medical assessment, even if a flu test offers an apparent explanation.
Chest pain, new palpitations, fainting, or disproportionate breathlessness can signal problems beyond ordinary airway irritation. Our hantlieding foar myokarditistesten explains why troponin sometimes matters; however, neither a single normal value nor a positive influenza result can independently rule out every cause of chest pain.
Severe muscle pain or weakness with cola-coloured urine deserves urgent evaluation because influenza can occasionally affect muscle and kidney function. Our warskôgingsbuorden foar donkere urine distinguishes concentrated urine from other causes; do not assume that 1 unusually dark sample is harmless when substantial weakness accompanies it.
Does positive influenza A rule out pneumonia or bacterial infection?
A positive influenza A test does not rule out pneumonia, bacterial coinfection, or another respiratory virus. New fever after improvement, increasing breathlessness, low oxygen, or focal chest findings may require examination and imaging; WBC, CRP, and procalcitonin can support reasoning but cannot independently settle whether antibiotics are needed.

A hypothetical person who improves on days 3–4 and develops fever and breathlessness on day 6 needs reassessment for complications, rather than simply restarting the original recovery countdown. Bacterial pneumonia can occur during influenza or after initial improvement; some patients also develop primary viral pneumonia without bacterial coinfection.
A WBC of 12 × 10⁹/L of CRP of 80 mg/L, for example, does not prove bacterial infection because influenza and physiological stress can elevate both. Our guide to WBC en CRP ferskil explains why direction of change, examination findings, steroid use, and sampling time matter more than isolated labels.
A procalcitonin below 0.25 ng/mL may lower suspicion of bacterial infection in some respiratory-care algorithms, but it must not override clinical evidence of pneumonia or sepsis. Our gids foar de ynterpretaasje fan procalcitonine explains timing limitations; early infection and localized disease can produce lower values than expected.
Kantesti explains accompanying inflammatory markers as contextual evidence, not an antibiotic prescription or a way to clear someone for home care. Antibiotics do not treat influenza itself; 2 simultaneous processes, such as viral influenza plus bacterial pneumonia, require a different plan from uncomplicated flu and may justify treatment before all results are available.
Do you need another flu test or follow-up blood work?
Most people recovering normally from uncomplicated influenza do not need repeat PCR, routine blood tests, or a test of cure. Follow-up is more useful when symptoms worsen, remain substantial after 2-3 wiken, or create a specific concern such as dehydration, pneumonia, anemia, or a medication-related kidney problem.

Repeating PCR on day 10 simply to obtain a negative result can prolong worry without changing care. Exceptions include selected immunocompromised patients, severe hospitalized illness, unusual exposures, and institutional outbreak decisions; clinicians may use additional testing for those specific purposes rather than treating negativity as a universal recovery endpoint.
Influenza can temporarily alter inflammatory markers, white-cell counts, and sometimes liver enzymes, while dehydration can affect kidney measurements. Our illness-related laboratory timeline explains why comparing an acute-illness result with a well-state sample 2–4 weeks later, when clinically appropriate, is often more informative than testing every day.
Return to exercise gradually after fever has resolved and ordinary daily activity is comfortable; begin with perhaps 10–15 minutes of easy activity rather than your usual training session. Stop and obtain medical advice for chest pain, palpitations, fainting, or disproportionate breathlessness, because those symptoms should not be dismissed as deconditioning.
Kantesti can help organize existing laboratory results and trends, but our gids foar ynterpretaasjetechnology explains why the original report, units, and clinical context remain necessary. A creatinine measured during day 2 dehydration should not automatically be interpreted as a new permanent baseline or used to change medicines without professional review.
What can our interpretation and research sources tell you?
Laboratory interpretation can explain associated findings, but it cannot establish influenza contagiousness or replace a clinical assessment. Kantesti is an AI bloedtest-útslachplatfoarm that places supplied values and trends in context; a flu PCR result and a creatinine result describe 2 different biological processes, not interchangeable measures of infection severity.
Protect identifying information when sharing results, especially if a report contains names, dates of birth, or family details alongside multiple laboratory valuesUs begelieding oer privacy en gegevens explains the relevant controls; a family member's report should be shared only with appropriate permission, not because flu affected the same household.
Creatinine and urea can help clinicians investigate dehydration, but no single ratio proves its cause or determines an antiviral dose by itself. Our urea and creatinine guide explains the distinction; for example, BUN 30 mg/dL and creatinine 1.0 mg/dL can reflect several clinical contexts rather than a definitive influenza complication.
De 3 external clinical references below support the influenza discussion: the IDSA guideline addresses testing and treatment decisions, while the Lancet and BMJ analyses explain oseltamivir benefits and uncertainty. Our medyske ynhâldsnoarmen distinguish guideline evidence, trial evidence, hypothetical examples, and product information rather than presenting them as equally authoritative.
De 2 Figshare-publikaasjes listed separately below are broader educational resources on gastrointestinal and women's health topics; they are not influenza treatment trials or evidence that our software determines infectiousness. A DOI makes a resource identifiable and retrievable—it does not, by itself, establish peer review, clinical validation, or relevance to a flu treatment decision.
Faak stelde fragen
Wat moat ik dwaan as myn test op influenza A posityf is?
As jo gryp A-test posityf is, bliuw dan thús, rêst, drink genôch en beoardielje oft jo daliks medysk advys nedich hawwe. Nim betiid kontakt op mei in medysk behanneler as de symptomen binnen 48 oeren begûnen, of op elk momint as jo swier binne, 65 jier of âlder binne, in ferswakke ymmúnsysteem hawwe of wichtige groanyske oandwaningen hawwe. De measte ûnkomplisearre symptomen wurde binnen 3–7 dagen better, hoewol't hoastjen en wurgens langer oanhâlde kinne. Swierrichheden mei sykheljen, oanhâldende druk op 'e boarst, betizing of slimme útdroeging fereaskje driuwende medyske soarch ynstee fan noch in thústest.
Hoe lang duorret influenza A by folwoeksenen?
Unkomplisearre influenza A feroarsaket by folwoeksenen oer it generaal 3–7 dagen akute sykte, wêrby't de koarts faak 3–4 dagen oanhâldt. Hoastjen en wurgens kinne ek nei't de koarts ferdwûn is noch 2 wiken of langer trochgean. In stadige ferbettering is mear gerêststellend as it berikken fan in bepaalde kalinderdei. Weromkommende koarts, nije sykhelnood of efterútgong nei ferbettering freget om in nije beoardieling op komplikaasjes.
Can I still take oseltamivir after 48 hours?
Oseltamivir may still be appropriate after 48 hours for hospitalized patients, people with severe or progressive influenza, and those at increased complication risk. The 48-hour window marks the period with the clearest symptom-reduction benefit in uncomplicated outpatients; it is not an absolute treatment deadline for everyone. A common adult regimen is 75 mg twice daily for 5 days, but kidney impairment and pediatric age or weight change dosing. A clinician should make the treatment decision without delaying urgent care for repeat testing.
Does a positive influenza A PCR mean I am still contagious?
A positive influenza A PCR means viral RNA was detected, not that contagiousness has been precisely measured. Many adults can transmit influenza from about 1 day before symptoms until 5–7 days afterward, while children and immunocompromised people may shed infectious virus longer. PCR can remain positive when transmission risk has fallen because detectable RNA and viable virus do not disappear simultaneously. Symptoms, time since onset, immune status, and exposure to vulnerable people are more useful than PCR alone for practical decisions.
When can I go back to work after testing positive for influenza A?
CDC community guidance generally allows return when symptoms are improving overall and you have been fever-free for at least 24 hours without fever-reducing medicine. Use additional precautions for the next 5 days, including ventilation and a well-fitting mask where appropriate. If you never developed fever, overall symptom improvement still matters. Local workplace, school, healthcare, and public-health rules can differ, and a repeat negative PCR is not usually required for uncomplicated recovery.
Do I need antibiotics for a positive influenza A test?
Antibiotics do not treat influenza A itself, so a positive flu test alone is not a reason to take them. Antibiotics may be needed if a clinician identifies or strongly suspects bacterial coinfection, such as pneumonia. New fever and breathlessness after improvement around days 3–7 should prompt reassessment rather than automatic self-treatment. Neither a WBC of 12 × 10⁹/L nor a CRP of 80 mg/L can independently distinguish bacterial infection from influenza-related inflammation.
Lit jo bloedtest resultaten útlizze
Laad jo laboratoariumrapport op en de AI fan Kantesti leit elke biomarker binnen sekonden út yn gewoane taal. Brûkt troch mear as 2 miljoen minsken wrâldwiid.
Referinsjes
- Klein, T., Mitchell, S., & Weber, H. (2026). Diarree nei fêstjen, swarte spikkels yn de stoelgong en GI-hantlieding 2026. Kantesti AI Medysk Undersyk. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Gids foar de sûnens fan froulju: ovulaasje, menopoaze en hormonale symptomen. Kantesti AI Medysk Undersyk. DOI
- Uyeki TM et al. (2019). Clinical Practice Guidelines by the Infectious Diseases Society of America: 2018 Update on Diagnosis, Treatment, Chemoprophylaxis, and Institutional Outbreak Management of Seasonal Influenza. Clinical Infectious Diseases. DOI
- Dobson J et al. (2015). Oseltamivir treatment for influenza in adults: a meta-analysis of randomised controlled trials. The Lancet. DOI
- Jefferson T et al. (2014). Oseltamivir for influenza in adults and children: systematic review of clinical study reports and summary of regulatory comments. BMJ. DOI
- 2M+Analysearre tests
- 127+Lannen
- 100+Talen
Oer it medyske team


E-E-A-T fertrouwensignalen
Ûnderfining
Dokter-oandreaune klinyske resinsje fan lab-ynterpretaasje-wurkprosessen.
Ekspertize
Fokus fan laboratoariummedisyne op hoe’t biomarkers har gedrage yn in klinyske kontekst.
Autoriteit
Medysk beoardiele troch Dr. Thomas Klein, mei bydragen fan Dr. Sarah Mitchell en prof. dr. Hans Weber.
Betrouberens
Bewiis-basearre ynterpretaasje mei dúdlike ferfolchpaadkes om alarm te ferminderjen.






Medyske disclaimer
Dit artikel is allinnich foar ûnderwiisdoelen en foarmet gjin medysk advys. Rieplachtsje altyd in kwalifisearre soarchferliener foar besluten oer diagnoaze en behanneling.
Publisearre · Nim kontakt op mei it redaksjeteam
Publisearre troch Kantesti Ltd, registrearre yn Ingelân en Wales, bedriuwsnûmer. 17090423, Londen, Feriene Keninkryk.
