Wilson disease rarely announces itself through one abnormal number. The diagnosis comes from matching copper transport results with liver, neurological and genetic evidence.

Points clés à retenir
- No single result confirms Wilson disease: clinicians combine copper studies, examination findings, liver assessment and sometimes ATP7B testing.
- Ceruloplasmin below 10 mg/dL is strongly suggestive, but low values also occur with malnutrition, protein loss and other liver disorders.
- Total serum copper is often low in Wilson disease because less copper is attached to ceruloplasmin; it may become high during acute liver injury.
- 24-hour urine copper above 100 micrograms per day supports Wilson disease in untreated symptomatic adults, but the threshold is not diagnostic alone.
- Leipzig scores of 4 or more make Wilson disease highly likely when the component findings have been assessed correctly.
- ATP7B testing supports the diagnosis when two disease-causing variants are found, but a negative panel does not exclude every pathogenic variant.
- Urgent symptoms matter: jaundice, confusion, severe vomiting, unusual sleepiness or rapidly worsening liver tests need same-day medical assessment.
Which Wilson disease blood test results are convincing?
No single Wilson disease blood test confirms the diagnosis. Clinicians usually combine ceruloplasmin, total and non-ceruloplasmin copper, 24-hour urine copper, liver findings, examination signs and ATP7B genetics; a Leipzig score of 4 or more supports an established diagnosis.

A ceruloplasmin below 10 mg/dL, urine copper above 100 micrograms per 24 hours, a Kayser–Fleischer ring, or biallelic pathogenic ATP7B variants can each raise suspicion, but each has exceptions. A normal ceruloplasmin does not exclude Wilson disease, and a high urine result can follow severe liver inflammation or poor collection.
For example, a hypothetical 22-year-old with ceruloplasmin of 8 mg/dL, urine copper of 180 micrograms per day, mild ALT elevation and neurological symptoms has a much stronger pattern than someone with ceruloplasmin of 9 mg/dL alone. The reason is that separate tests are measuring different parts of copper handling.
Kantesti is an AI blood test analyzer that organizes copper, liver and blood-count results into a pattern rather than treating one flagged value as proof. Our interpretation is educational; a hepatologist, gastroenterologist or metabolic specialist must make the diagnosis and decide whether treatment is needed. Methodology and clinical oversight are described in our normes de validation médicale.
How does the ceruloplasmin test work?
Le ceruloplasmin test measures the main copper-carrying protein in blood; adult laboratory ranges are commonly about 20–40 mg/dL, although methods and populations differ. Values below 10 mg/dL are strongly suggestive of Wilson disease, while 10–20 mg/dL is an indeterminate zone that needs other evidence.
Ceruloplasmin is made in the liver and normally carries roughly 95% of circulating serum copper in its active form. A low result can reflect impaired ATP7B-dependent loading of copper, but it can also occur with severe liver failure, nephrotic protein loss, malnutrition, malabsorption or rare inherited disorders of protein production.
A ceruloplasmin result above 40 mg/dL does not rule out Wilson disease because inflammation, pregnancy, estrogen-containing contraception and infection can increase the protein. Some European laboratories report a lower adult reference limit near 18 or 20 mg/dL, so the report's own interval matters more than copying a threshold from another website.
A hypothetical patient taking estrogen-containing contraception might have ceruloplasmin of 32 mg/dL despite Wilson disease, whereas a person with advanced non-Wilson cirrhosis might have 12 mg/dL. Readers comparing results can use this copper-to-zinc interpretation guide to understand why protein-bound trace metals require context.
| Niveau | Intervalle | Signification |
|---|---|---|
| Fourchette typique chez l’adulte | 20–40 mg/dL | Does not exclude Wilson disease, especially with neurological disease or liver failure. |
| Limite basse | 10–20 mg/dL | Indeterminate; repeat or confirm with copper studies and clinical evidence. |
| Très bas | 5–10 mg/dL | Strongly suspicious, but protein loss and severe liver disease remain alternatives. |
| Très bas | <5 mg/dL | Highly abnormal and potentially supportive, but never diagnostic by itself. |
What does serum copper show in Wilson disease?
Total serum copper is often low in untreated Wilson disease, commonly below a laboratory lower limit near 70 micrograms/dL, because ceruloplasmin-bound copper is reduced. High serum copper can occur in acute liver failure, active hepatitis or after copper is released from damaged liver cells, so the direction of the result is not enough.
Total serum copper includes copper attached to ceruloplasmin plus non-ceruloplasmin copper, sometimes called free or exchangeable copper. A typical adult total-copper interval is approximately 70–140 micrograms/dL, but laboratories use different assays; a low total value can coexist with biologically harmful unbound copper.
The practical calculation is often expressed as non-ceruloplasmin copper equals total copper minus ceruloplasmin-bound copper, with the latter estimated from ceruloplasmin concentration. The estimate becomes unreliable when ceruloplasmin is measured by an immunological method, when units are mixed, or when total copper and ceruloplasmin are not collected on the same date.
A hypothetical result of total copper 45 micrograms/dL and ceruloplasmin 6 mg/dL is more concerning than either result alone, while total copper 210 micrograms/dL during acute hepatitis may represent released hepatic copper rather than a stable baseline. Low copper has many causes, so readers can compare patterns in our guide to low copper causes and follow-up.
How is the 24-hour urine copper test interpreted?
Le 24-hour urine copper test measures copper excreted over a complete day; untreated symptomatic adults with Wilson disease often exceed 100 micrograms per 24 hours. Results above 40 micrograms per day may be abnormal in children, but collection quality, age and liver inflammation change the interpretation.

A complete collection starts after the bladder is emptied, then includes every subsequent specimen until the same time the next day. A result of 100 micrograms per 24 hours or more is supportive in many untreated adults, while values below 40 micrograms per day make Wilson disease less likely but do not exclude it in early or asymptomatic disease.
The test can be falsely low when one void is missed, the container is not stored as instructed or urine volume is unusually small. It can be falsely high with cholestasis, acute liver injury, copper-containing contamination or recent chelation; treatment with penicillamine or trientine also changes urinary copper and must be documented.
A hypothetical patient produces 1,800 mL of urine and excretes 135 micrograms of copper in 24 hours, but forgot the first morning specimen; the number cannot be interpreted confidently without discussing a repeat collection. Urine creatinine can help assess completeness, as explained in this urine creatinine interpretation guide.
Which liver blood tests support the diagnosis?
Liver tests show the organ injury and synthetic function associated with Wilson disease, but they do not identify copper accumulation by themselves. ALT and AST may be mildly or markedly elevated, bilirubin can rise, and low albumin or prolonged prothrombin time can indicate impaired function rather than simply liver-cell irritation.

ALT and AST indicate cellular injury, whereas alkaline phosphatase and bilirubin provide clues about bile flow and excretory function. In acute Wilson-related liver failure, an unusually low alkaline-phosphatase-to-bilirubin relationship and Coombs-negative hemolysis can be important, but no universal ratio should replace specialist assessment.
A typical adult ALT reference limit may be around 7–56 IU/L and AST around 10–40 IU/L, yet laboratory upper limits differ by sex, method and population. A result such as AST 180 IU/L with bilirubin 8 mg/dL is clinically more urgent than ALT 65 IU/L alone, especially if INR is rising or symptoms are developing.
Kantesti AI interprets liver panels by separating injury markers depuis liver function markers, then relating them to copper results and trends. This does not diagnose Wilson disease; it helps prevent a common error in which a normal albumin or mildly raised ALT is treated as proof that copper-related liver disease is absent. See our plain-language bilan hépatique for the roles of each marker.
Why are imaging and fibrosis tests included?
Liver assessment estimates the damage caused by copper accumulation and helps determine urgency; it does not independently confirm Wilson disease. Ultrasound, elastography, FibroScan, platelet count, INR, albumin and sometimes liver tissue copper measurement answer different clinical questions.

Elastography reports liver stiffness in kilopascals, but inflammation, cholestasis and congestion can temporarily raise the value without equivalent fibrosis. For example, stiffness of 14 kPa may suggest advanced fibrosis in one setting, yet acute hepatitis can produce a similar reading; the result must be paired with platelets, bilirubin, INR and clinical history.
Liver tissue copper above approximately 250 micrograms per gram of dry weight supports Wilson disease, but sampling error is substantial because copper may be unevenly distributed. A tissue result below that threshold does not reliably exclude disease if the specimen is small, poorly handled or taken after treatment.
The pattern of liver damage can be followed with repeated tests rather than one isolated scan. Readers can see why stiffness values require calibration in this guide des résultats du FibroScan, but a specialist should interpret any result suggesting cirrhosis, portal hypertension or rapidly worsening function.
How does the Leipzig score combine the evidence?
Le Leipzig score combines clinical, biochemical, genetic and tissue findings; a score of 4 or more establishes Wilson disease in the appropriate clinical context, 2–3 is probable, and 0–1 is unlikely. The score is a reasoning framework, not a substitute for reviewing the original assays and examination.
The score can assign points for Kayser–Fleischer rings, neurological symptoms, ceruloplasmin concentration, Coombs-negative hemolysis, liver copper, ATP7B variants and urine copper. A ceruloplasmin below 10 mg/dL contributes more evidence than a borderline result, while a single ATP7B variant does not carry the same weight as two disease-causing variants.
For a hypothetical example, ceruloplasmin 8 mg/dL may contribute 2 points, a confirmed Kayser–Fleischer ring 2 points, and two pathogenic ATP7B variants 4 points; the total would strongly support diagnosis, but the specialist still checks whether the genetic findings are truly pathogenic and whether another disorder explains the presentation.
Kantesti is an AI blood test interpretation platform that can arrange these inputs into a readable timeline, including dates, units and treatment status. It cannot inspect corneas, validate a genetic variant or replace a formal Leipzig assessment; our guide des biomarqueurs explains why reference intervals and diagnostic thresholds are not interchangeable.
What does ATP7B genetic testing prove?
Finding two pathogenic ATP7B variants on opposite chromosome copies strongly supports Wilson disease and can establish the diagnosis when interpreted by genetics experts. Finding one variant may indicate carrier status, while a negative panel does not exclude disease because some variants are difficult to detect or remain clinically uncertain.

ATP7B encodes a copper-transporting ATPase that helps load ceruloplasmin and excrete excess copper into bile. Sequencing may detect small sequence changes, while deletion or duplication analysis may be needed for larger changes; a test report should state which methods were used rather than simply saying genetic test performed.
A variant of uncertain significance is not a confirmed diagnosis and should not guide treatment by itself. Family testing can clarify whether two variants are on opposite chromosome copies, but relatives need genetic counselling because a carrier may have no disease while still having reproductive implications.
Kantesti can help place ATP7B findings beside ceruloplasmin and urine copper, but our AI cannot reclassify a variant or provide inherited-disease counselling. The Guide de technologie IA explains why automated interpretation should surface uncertainty instead of turning a laboratory phrase into a diagnosis.
What if the Wilson disease tests disagree?
Conflicting Wilson disease results are common enough that clinicians repeat or extend testing rather than choosing the most alarming number. Low ceruloplasmin with normal urine copper, or high urine copper with normal ceruloplasmin, is an unresolved pattern—not a negative or positive diagnosis.
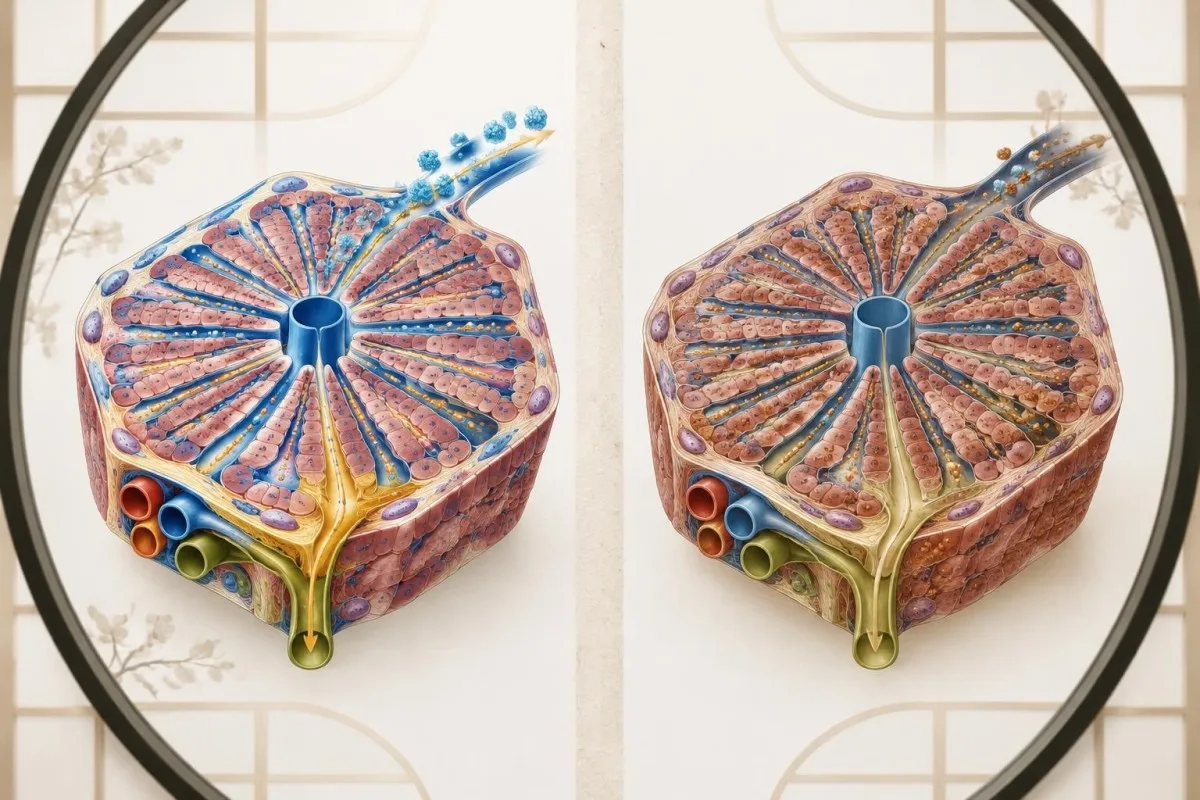
A low ceruloplasmin may reflect protein loss, malnutrition or another liver disorder, while a high urine copper may reflect cholestasis or recent chelation. Conversely, early disease, a missed urine sample or prior treatment can produce a deceptively modest urine result even when Wilson disease remains plausible.
For example, a hypothetical adult with ceruloplasmin 14 mg/dL, serum copper 58 micrograms/dL and urine copper 32 micrograms per day needs review of symptoms, liver tests, medications, urine completeness and family history. Repeating a properly collected test may be more useful than calculating a complex ratio from mismatched specimens.
High zinc exposure can interfere with copper balance and produce low copper findings, while copper supplements can raise serum copper without correcting the underlying transport problem. Our related explanation of high zinc and copper loss covers a frequent confounder, but suspected Wilson disease still warrants specialist review.
How do age and pregnancy change interpretation?
Age, pregnancy and hormonal treatment alter copper results, so adult cutoffs cannot be copied automatically into children or pregnancy. Wilson disease can present in childhood or later adulthood, and pregnancy or estrogen exposure may raise ceruloplasmin and total serum copper without proving that copper handling is normal.

In children, urine copper above roughly 40 micrograms per 24 hours may be concerning, but age-specific reference intervals and collection reliability matter. A child with unexplained liver disease, movement changes, tremor or a family history may need testing even when a single ceruloplasmin result is within the adult range.
During pregnancy, increased estrogen stimulates ceruloplasmin production and can raise total serum copper, while non-ceruloplasmin copper may require more careful interpretation. A result of 180 micrograms/dL total copper during pregnancy cannot be labelled Wilson disease from that number alone; clinicians consider trimester, ceruloplasmin and urine copper.
For families reviewing several reports, our guidance on interpreting blood tests in children explains why age, consent and clinical supervision matter. Do not stop prescribed treatment or begin zinc, copper or chelation without the treating team, particularly during pregnancy.
Which other conditions mimic Wilson disease?
Other liver, nutritional, kidney and copper-exposure disorders can imitate part of the Wilson disease pattern. Autoimmune hepatitis, viral hepatitis, cholestasis, severe malnutrition, nephrotic protein loss, copper deficiency and acute liver failure can all distort ceruloplasmin, serum copper or urine copper.

Low ceruloplasmin is not specific: it can accompany significant protein loss, inadequate nutrition or advanced liver disease. High bilirubin also has many causes, including hemolysis and bile-flow disorders; a high bilirubin result should be separated into direct and indirect fractions before it is attributed to Wilson disease.
A hypothetical patient with bilirubin 6 mg/dL, ALT 420 IU/L, alkaline phosphatase 90 IU/L and Coombs-negative hemolysis may need urgent evaluation for acute Wilson-related liver failure, but viral, autoimmune and drug-related causes must still be tested. The combination is more informative than any isolated enzyme value.
Readers can review the causes of les schémas de bilirubine élevée alongside the copper workup, but online interpretation cannot distinguish every mimic. A specialist may add viral serology, autoimmune markers, blood-count review, nutritional assessment and medication or supplement history.
How should samples be prepared and collected?
Preparation for a Wilson disease blood test mainly means documenting treatment, supplements, hormones and collection timing; fasting is not universally required. The 24-hour urine collection needs special care because a missed void can make the copper total falsely reassuring.
Before collection, tell the laboratory about zinc, copper, multivitamins, chelating medicines, liver medicines and hormonal contraception. Do not stop a prescribed medicine without medical advice; the purpose is to help clinicians interpret whether a copper result reflects untreated disease, treatment response or an external exposure.
For a 24-hour urine test, record the start and finish times, collect every void, keep the container as instructed and report spills or missed samples. A normal urine copper value after an incomplete collection is not equivalent to a valid negative test, especially when symptoms or liver tests remain concerning.
Fasting requirements differ by laboratory and by the other tests ordered at the same time; this fasting instruction guide explains why a request marked fasting required should be followed. Uploading a report to Kantesti can help organize units and dates, but the original laboratory comments and specimen notes should remain available to the clinician.
When do Wilson disease results need urgent care?
Jaundice with confusion, severe sleepiness, repeated vomiting, easy bruising, dark urine, rapidly rising bilirubin or a prolonged INR needs urgent medical assessment. Wilson-related acute liver failure can worsen quickly, and waiting for every outpatient copper result may be unsafe.
INR measures clotting performance, while bilirubin reflects pigment processing and excretion; together with mental-status change they can indicate deteriorating liver function. An INR above 1.5 in a person with acute liver injury is clinically significant, although the complete picture determines whether acute liver failure is present.
A hypothetical person with bilirubin 12 mg/dL, INR 2.1, AST 900 IU/L and new confusion should seek emergency care rather than wait for a 24-hour urine result. Acute Wilson disease can also involve Coombs-negative hemolysis, so falling haemoglobin, rising LDH and low haptoglobin may add urgency.
Dark urine has many causes, including bilirubin, dehydration and muscle injury, but jaundice or confusion changes the risk. Our explanation of schémas d'alerte d'urine foncée may help with general context; it is not a substitute for emergency assessment when severe symptoms are present.
How should you read a Wilson disease report?
Read a Wilson disease report as a dated pattern, not as a list of isolated red flags: record the method, units, reference interval, treatment status, liver findings and whether urine collection was complete. The same numerical result can mean different things before and after zinc or chelation therapy.

Start with ceruloplasmin and total copper, then check whether non-ceruloplasmin copper was calculated using compatible units. Next review 24-hour urine copper, bilirubin, ALT, AST, alkaline phosphatase, albumin, INR, platelet count and creatinine; a trend over weeks may reveal deterioration or treatment response that one draw cannot show.
Kantesti is an AI-powered blood test analysis tool that can compare uploaded reports, normalize common units and highlight changes across dates. It cannot confirm Wilson disease, assess Kayser–Fleischer rings, determine whether an ATP7B variant is pathogenic or replace a clinician's physical examination.
Use the report to prepare questions: Was the urine collection complete? Was treatment already started? Are the genetic variants classified as pathogenic? Does the clinical picture produce a Leipzig score of 4 or more? For information about specialist review and governance, see the Conseil consultatif médical.
Foire aux questions
Une seule analyse de sang peut-elle confirmer la maladie de Wilson ?
Aucun test sanguin isolé ne confirme la maladie de Wilson. Une céruloplasmine inférieure à 10 mg/dL est fortement évocatrice, mais des valeurs basses s’observent également en cas de pertes protéiques, de malnutrition et de maladie hépatique avancée. Le diagnostic repose généralement sur l’association de la céruloplasmine, du cuivre sérique, du cuivre urinaire des 24 heures, de l’évaluation hépatique, des résultats de l’examen clinique et du dépistage d’ATP7B, souvent à l’aide d’un score de Leipzig de 4 ou plus.
Quel taux de céruloplasmine évoque la maladie de Wilson ?
A ceruloplasmin result below 10 mg/dL strongly suggests Wilson disease, while 10–20 mg/dL is generally indeterminate and needs supporting evidence. Typical adult reference intervals are approximately 20–40 mg/dL, but laboratories differ. Normal ceruloplasmin does not exclude Wilson disease, particularly in neurological disease, pregnancy or estrogen exposure.
Is serum copper high or low in Wilson disease?
Total serum copper is often low in untreated Wilson disease, commonly below about 70 micrograms/dL, because less copper is attached to ceruloplasmin. Serum copper can become high during acute liver failure or active hepatitis when stored copper is released from damaged liver cells. The result must therefore be interpreted with ceruloplasmin and urine copper rather than alone.
What 24-hour urine copper level is diagnostic?
Untreated symptomatic adults with Wilson disease often have 24-hour urine copper above 100 micrograms per day, while values above about 40 micrograms per day may be concerning in children. These thresholds are supportive, not independently diagnostic. Missed urine, acute liver injury, cholestasis and copper-lowering treatment can substantially change the result.
Does a positive ATP7B test prove Wilson disease?
Two clearly pathogenic ATP7B variants strongly support Wilson disease and may establish the diagnosis in the correct clinical setting. One variant may indicate carrier status, and a variant of uncertain significance is not diagnostic. A negative genetic panel does not exclude Wilson disease because some variants or structural changes may not be detected by every test.
When is Wilson disease an emergency?
Wilson disease becomes an emergency when liver injury is accompanied by confusion, severe sleepiness, repeated vomiting, jaundice, rapidly rising bilirubin or a prolonged INR. An INR above 1.5 during acute liver injury is clinically concerning, although the full assessment determines acute liver failure. Do not wait for a 24-hour urine result before seeking urgent care if these warning signs are present.
Faites-vous expliquer vos résultats prise de sang
Téléversez votre compte rendu d’analyses et l’IA de Kantesti explique chaque biomarqueur en langage clair en quelques secondes. Déjà utilisé par plus de 2 millions de personnes dans le monde.
Références
- Klein, T., Mitchell, S., & Weber, H. (2026). Guide sur le test sanguin C3 C4 du complément et le titre ANA. Recherche médicale par IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Test sanguin pour le virus Nipah : guide de détection précoce et de diagnostic 2026. Recherche médicale par IA de Kantesti. DOI
- Roberts EA, Schilsky ML (2008). Diagnosis and treatment of Wilson disease: an update. Hépatologie. DOI PubMed
- European Association for Study of the Liver (2012). EASL clinical practice guidelines: Wilson's disease. Journal of Hepatology. DOI PubMed
- Ferenci P et al. (2003). Diagnosis and phenotypic classification of Wilson disease. Journal of Hepatology. DOI PubMed
- 2 millions et plusTests analysés
- 127+Des pays
- 100+Langues
À propos de l’équipe médicale


Signaux de confiance E-E-A-T
Expérience
Revue clinique guidée par un médecin des flux d’interprétation des analyses.
Compétence
Orientation en médecine de laboratoire sur la façon dont les biomarqueurs se comportent dans un contexte clinique.
autorité
Révisé médicalement par le Dr Thomas Klein, avec la contribution de la Dre Sarah Mitchell et du Pr Dr Hans Weber.
Fiabilité
Interprétation fondée sur des preuves, avec des parcours de suivi clairs pour réduire l’alarme.




Avertissement médical
Cet article est fourni à des fins éducatives uniquement et ne constitue pas un avis médical. Consultez toujours un professionnel de santé qualifié pour les décisions de diagnostic et de traitement.
Publié · Contacter l’équipe éditoriale
Publié par Kantesti Ltd, immatriculée en Angleterre et au pays de Galles, sous le numéro d’entreprise. 17090423, Londres, Royaume-Uni.
