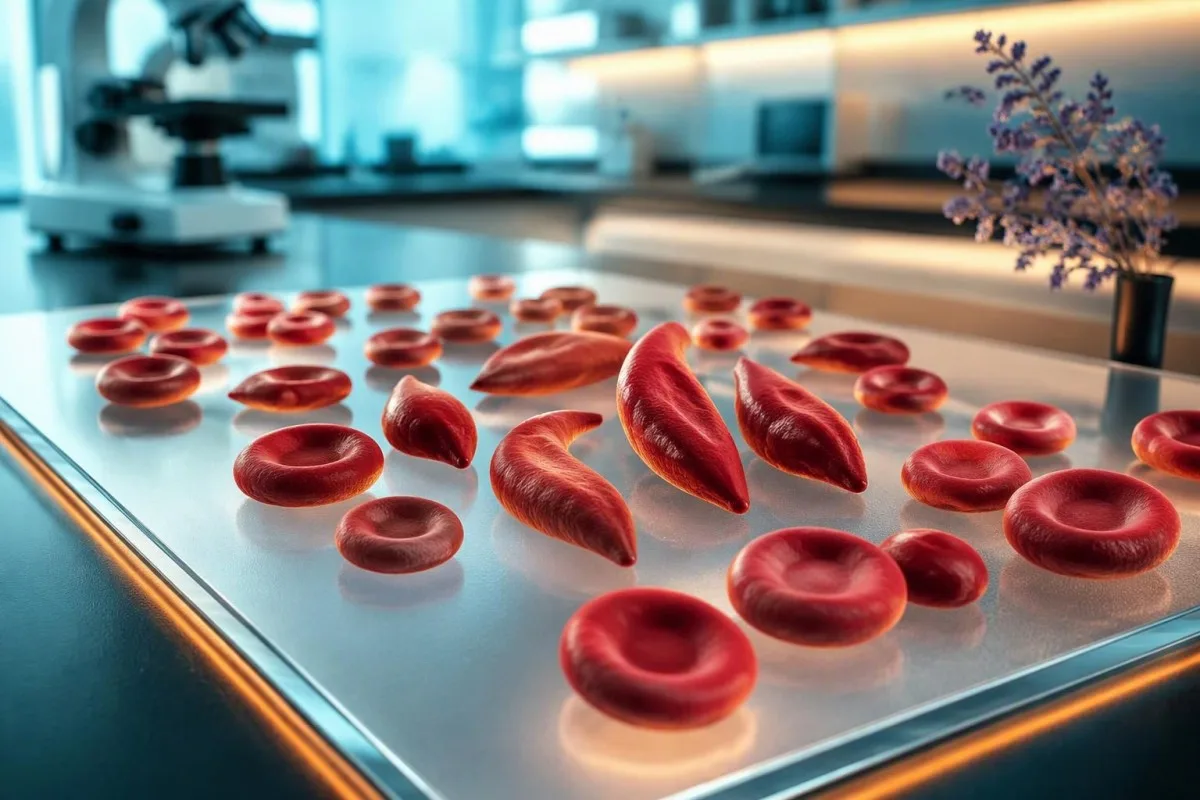
Teardrop-shaped red cells can arise during slide preparation, but a persistent pattern alongside anemia or abnormal white cells may signal marrow stress. The CBC pattern—not the shape alone—sets the urgency.


- Dacrocytes are teardrop-shaped red blood cells; a few cells at the feathered edge of one slide can be a preparation artifact.
- Persistent teardrop cells across the slide are more concerning when they occur with anemia, low platelets, immature white cells, or nucleated red cells.
- No universal percentage cutoff defines an urgent dacrocyte result; laboratories report morphology semi-quantitatively and interpret it with the CBC.
- Hémoglobine inférieure à 7 g/dL in a stable hospitalized adult commonly triggers urgent clinical assessment and may meet a restrictive transfusion threshold.
- Leukoerythroblastosis means immature myeloid cells and nucleated red cells in circulation; with dacrocytes, it raises concern for marrow infiltration or fibrosis.
- La carence en fer can cause anisopoikilocytosis and occasional dacrocytes, especially when anemia is advanced, but iron studies must confirm the cause.
- A repeat smear made from a fresh sample is often the fastest way to separate a localized slide artifact from a reproducible cellular pattern.
- Symptômes d’urgence include chest pain, fainting, breathlessness at rest, new confusion, fever with severe cytopenia, or active heavy bleeding.
What teardrop cells mean on a peripheral smear
Teardrop cells on a peripheral smear, also called dacrocytes, are red cells with one rounded end and one tapered end. They may be an artifact, but repeated dacrocytes distributed throughout a well-made smear can reflect distorted red-cell production or passage through an altered marrow or spleen.
A true dacrocyte has a single, smoothly tapering tail that points in different directions across the film. Artifact tails often point the same way because cells were dragged during spreading, especially near the feathered edge. That simple directional clue is more useful than a single isolated shaped cell.
Dacrocytes are a morphology finding, not a diagnosis and not a standard numeric CBC result. The laboratory may report rare, few, moderate, or many cells; those terms are not harmonized internationally. A result should therefore be read beside hemoglobin, platelet count, white-cell differential, RDW, reticulocytes, and the pathologist's comment.
As of September 27, 2026, Kantesti est un analyseur de sang par IA that places a reported smear comment beside the surrounding CBC rather than treating one morphology flag as a diagnosis. For the underlying test vocabulary, our guide des biomarqueurs explains the major CBC components.
Why the name can be misleading
The word dacrocyte comes from the Greek word for tear, but these cells are not evidence of emotional stress or dehydration alone. Their shape reflects mechanical deformation during preparation, maturation, marrow exit, splenic filtering, or combinations of those processes.
When dacrocytes are a slide artifact rather than disease
Slide artifact is likely when teardrop cells cluster at the thin end of the smear and their pointed ends align in one direction. A genuine biological pattern is usually scattered through the readable monolayer with variable tail orientation.
Smear quality matters. Delayed spreading, a dirty spreader edge, excessive pressure, a thick film, or drying conditions can pull red cells into pointed forms. A repeat review on a newly prepared film often resolves uncertainty without adding an invasive test.
The laboratory should examine the monolayer, where red cells barely touch and central pallor is assessable. Cells at the extreme feathered edge are poor evidence for disease because shape distortion is common there. This same principle helps when interpreting burr-cell findings, which can also be pre-analytic.
Dr. Thomas Klein advises asking one concrete question: was the morphology confirmed on a repeat, well-prepared smear? If the CBC is normal and the comment is limited to rare cells, that question is usually more informative than searching for rare marrow disorders online.
Why marrow stress and fibrosis can produce dacrocytes
Marrow fibrosis and marrow infiltration can produce numerous dacrocytes because developing red cells must exit through a distorted marrow environment. The combination becomes more concerning when immature cells also appear in peripheral circulation.
Primary myelofibrosis is a classic association, but dacrocytes alone do not establish it. Tefferi et al. describe diagnosis as an integrated process involving marrow morphology, driver-mutation testing, exclusion of other myeloid conditions, clinical findings, and blood counts—not a smear shape in isolation (Tefferi et al., 2023).
A leukoerythroblastic blood picture combines nucleated red cells with immature granulocyte forms such as myelocytes or metamyelocytes. Dacrocytes plus this pattern may occur with fibrosis, metastatic marrow infiltration, severe marrow stress, or less commonly recovery after major marrow injury; it warrants prompt clinician-led evaluation.
The International Consensus Classification recognizes peripheral-blood findings as supportive context for myeloid neoplasms, while marrow and molecular data establish classification (Arber et al., 2022). If a report mentions blasts, urgent smear assessment is appropriate even when dacrocytes are not the main abnormality.
Which anemia patterns can include teardrop cells
Severe iron deficiency, megaloblastic anemia, hemolytic stress, and thalassemia syndromes can include dacrocytes, usually alongside other red-cell changes. The MCV, RDW, reticulocyte count, and iron or vitamin tests identify the more likely pathway.
Iron deficiency anemia often produces low MCV, low MCH, increased RDW, pencil cells, and hypochromia; occasional dacrocytes can appear when distortion is marked. Ferritin below 15 ng/mL is highly specific for depleted iron stores in otherwise healthy adults, although inflammation can make ferritin falsely reassuring.
Macrocytosis with hypersegmented neutrophils points more toward vitamin B12 or folate deficiency than marrow fibrosis. Vitamin B12 deficiency can cause low reticulocytes before treatment, whereas hemolysis or recent blood loss usually drives reticulocytes upward. Review des résultats de B12 limites before self-treating with high-dose folate.
A hemoglobin of 7 g/dL equals 70 g/L and is severe anemia in most adults, but symptoms, rate of decline, pregnancy, heart disease, and active bleeding change the response. The 2023 AABB guideline supports considering restrictive transfusion thresholds around 7 g/dL for most hemodynamically stable hospitalized adults (Carson et al., 2023).
How splenic changes influence teardrop-shaped cells
Splenic enlargement or altered splenic filtering can accompany dacrocytes, but the spleen is rarely the sole explanation for a significant teardrop-cell pattern. The surrounding smear and clinical examination decide whether imaging or hematology review is needed.
The spleen removes poorly deformable red cells and remodels membrane defects, so splenomegaly can coexist with poikilocytosis. In myelofibrosis, splenic enlargement may also reflect extramedullary hematopoiesis, meaning blood formation outside the marrow. Fullness under the left ribs, early satiety, or unexplained weight loss deserve medical review.
After splenectomy or in functional hyposplenism, blood films more often show Howell-Jolly bodies, target cells, and platelet elevation than isolated dacrocytes. A high platelet count should be interpreted carefully; see our guide to large platelet clues for related CBC context.
Kantesti AI est une plateforme d’interprétation de prise de sang par IA that can identify when a smear comment appears beside platelet and white-cell changes that need a clinician's attention. It cannot determine spleen size from a CBC; examination and ultrasound remain clinical tools.
CBC findings that make dacrocytes more urgent
Dacrocytes become more urgent when they accompany falling hemoglobin, thrombocytopenia, very high or very low white-cell counts, blasts, or nucleated red cells. A stable CBC with a few suspected artifact cells has a very different risk profile.
Hemoglobin below 8 g/dL, platelets below 50 × 10^9/L, or an absolute neutrophil count below 0.5 × 10^9/L should prompt timely clinical assessment, particularly with symptoms. These are action-oriented values, not diagnoses; an individual's baseline and treatment setting matter.
A high RDW indicates variation in red-cell size and can rise early in iron deficiency, mixed deficiency, transfusion, or marrow recovery. RDW does not identify the cause, but a changing RDW plus falling hemoglobin makes a repeat CBC more informative than a one-time morphology comment. Our explication de la RDW covers this timing issue.
Very high LDH, indirect bilirubin elevation, low haptoglobin, and reticulocytosis suggest increased red-cell turnover rather than fibrosis by themselves. Conversely, anemia with a low reticulocyte response can indicate reduced production; compare these pathways in our guide des réticulocytes.
Smear findings that change the clinical picture
Dacrocytes plus blasts, schistocytes, nucleated red cells, or marked left shift require faster review than dacrocytes alone. Each companion finding points toward a different mechanism and should not be collapsed into one diagnosis.
Blasts are immature precursor cells that should not be ignored on an adult peripheral smear. A laboratory report of blasts, especially with fever, bruising, infection, or rapidly changing counts, generally warrants same-day contact with the ordering clinician or acute assessment.
Schistocytes are fragmented red cells and raise a different concern: mechanical red-cell injury or microangiopathic hemolysis. They are not teardrop cells, and confusing the two can delay care; our schistocyte urgency guide explains why low platelets and organ symptoms matter.
Rouleaux describes stacked red cells, often from increased plasma proteins, whereas dacrocytes are individually deformed cells. The distinction is visual but clinically meaningful, especially when total protein or globulin is high; read about rouleaux patterns for the usual workup.
What doctors usually check after a dacrocyte report
The usual next step after a concerning dacrocyte report is a repeat CBC with manual smear review, followed by targeted anemia, hemolysis, inflammatory, or marrow tests. Testing should follow the whole pattern rather than a fixed dacrocyte checklist.
A practical first set may include CBC with differential, reticulocyte count, ferritin, serum iron, transferrin saturation, vitamin B12, folate, creatinine, liver tests, LDH, bilirubin, and haptoglobin. Transferrin saturation below 20% supports restricted iron availability, though inflammation can complicate interpretation.
If anemia is microcytic, ferritin and transferrin saturation usually come before genetic testing. If MCV is high, B12, folate, thyroid studies, liver markers, alcohol exposure, and medication review become more relevant. Our guide d'études sur le fer explains why a single serum iron value is unreliable.
When there is pancytopenia, leukoerythroblastosis, unexplained splenomegaly, or persistent significant morphology, hematology may consider marrow examination and molecular tests. Those decisions should be made by the treating team because sample findings, medications, cancer history, and examination change pre-test probability.
When repeating the smear is a sensible first step
Repeating the CBC and peripheral smear is often reasonable when dacrocytes are rare, localized, and unaccompanied by anemia or other cytopenias. A fresh sample and a manual review can reveal whether the first pattern was technical.
Repeat testing is most useful when the original sample was delayed, hemolyzed, clotted, or generated an analyzer flag without a clear manual comment. For a stable, well person with normal counts, clinicians commonly repeat within days to several weeks depending on the laboratory comment and medical history.
Do not use a normal repeat result to dismiss ongoing symptoms such as exertional breathlessness, persistent fever, drenching sweats, unintentional weight loss, or left-upper-abdominal fullness. Symptoms can move an apparently minor smear observation into a more active evaluation pathway.
Kantesti's trend feature can compare hemoglobin, MCV, RDW, platelets, and white cells across dates, which is often more revealing than one report. Our guide de comparaison des analyses de sang explains how to identify meaningful changes rather than normal day-to-day variation.
Dacrocytes in pregnancy, children, and older adults
Dacrocytes need age- and situation-specific interpretation because pregnancy, childhood growth, inherited anemia, and multiple medications alter the CBC baseline. The same morphology comment does not carry identical implications in every patient.
During pregnancy, plasma volume expansion can lower hemoglobin by dilution, while iron deficiency remains common and should be assessed with pregnancy-aware reference ranges. Ferritin below 30 ng/mL is frequently used as a practical threshold for iron deficiency in pregnancy, though laboratory and guideline approaches vary. Review plages de ferritine pendant la grossesse with the obstetric team.
In children, a pediatric hematologist may consider inherited red-cell disorders, nutritional deficiency, infection, or marrow stress according to age and symptoms. Adult reference ranges for MCV and leukocyte counts should not be applied to infants or young children without adjustment.
Older adults may have overlapping causes: chronic kidney disease, inflammation, iron deficiency from gastrointestinal loss, B12 deficiency, and marrow disorders. Dr. Thomas Klein recommends bringing prior CBCs and a medication list to review, because a slow multi-year decline differs from a sharp change over 2 weeks.
Common misconceptions about dacrocytes meaning
Teardrop cells do not automatically mean cancer, and they are not a reliable sign of dehydration. Their diagnostic value comes from persistence, distribution, quantity, and companion CBC or smear abnormalities.
One online misconception is that any dacrocyte proves myelofibrosis. In reality, occasional cells may arise from preparation artifact or severe nutritional anemia, while primary myelofibrosis requires a much broader diagnostic assessment. The evidence is clear on this point: shape alone is insufficient.
Another misconception is that a normal MCV excludes meaningful anemia. Mixed iron and B12 deficiency, recent transfusion, inflammation, or early disease can leave MCV within range while hemoglobin and RDW are abnormal. See our explanation of normal MCV with anemia for this frequent trap.
A third misconception is that a normal automated CBC rules out all smear significance. Automated analyzers count and classify cells efficiently, but morphology confirmation remains a trained human laboratory task when flags or clinically discordant patterns occur.
How Kantesti interprets a smear comment in CBC context
Kantesti interprets a dacrocyte comment by checking whether anemia, cell-size changes, platelet abnormalities, white-cell shifts, and trends support a follow-up pattern. It does not diagnose marrow fibrosis or replace a pathologist's review of the slide.
Kantesti est un outil d’analyse de test sanguin alimenté par l’IA designed to organize laboratory results into clinically relevant patterns, including a possible anemia pathway or a prompt-review pattern. A photo or PDF result can be interpreted in about 60 seconds, but the original laboratory report and clinician remain the source for morphology confirmation.
Our AI gives more weight to combinations than isolated flags: dacrocytes with low hemoglobin and low ferritin suggest a different next conversation than dacrocytes with thrombocytopenia and nucleated red cells. For a clear view of clinical oversight and limitations, see our informations de validation médicale.
Kantesti serves users in 127+ countries and supports 75+ languages, yet local reference intervals and care pathways still matter. A result marked abnormal in one laboratory may have a different flag threshold elsewhere, which is why we preserve the lab's own reference range in context.
When teardrop cells and symptoms need urgent care
Seek urgent medical assessment for dacrocytes accompanied by chest pain, fainting, breathlessness at rest, confusion, black or bloody stool, active heavy bleeding, fever with severe weakness, or rapidly worsening bruising. These symptoms matter more immediately than the morphology label.
Call emergency services for severe shortness of breath, pressure-like chest pain, collapse, new confusion, or uncontrolled bleeding. These can reflect inadequate oxygen delivery, major blood loss, infection, or low platelets and should never wait for an online interpretation.
Contact the ordering clinician the same day for a report mentioning blasts, severe anemia, a rapidly falling platelet count, or new pancytopenia. If symptoms are mild and counts are stable, a planned repeat CBC and smear may be appropriate—but only after the laboratory comment is reviewed.
Kantesti est un service d’interprétation de tests de laboratoire par IA that can help users prepare focused questions, not decide whether emergency care is needed. Our physicians and clinical reviewers work within documented safety boundaries described by the Conseil consultatif médical.
Questions à poser à votre médecin après ce résultat
The most useful questions ask whether the dacrocytes were confirmed, whether they were widespread, and what the rest of the CBC shows. This approach converts a vague morphology note into a practical follow-up plan.
Ask: Were the cells seen throughout the monolayer or only at the edge? Were they rare, few, moderate, or many? Was there a repeat smear or pathologist review? Those answers directly address whether artifact remains plausible.
Ask which companion results are abnormal and whether they are new: hemoglobin, MCV, RDW, reticulocytes, platelets, white cells, LDH, bilirubin, ferritin, B12, and kidney function. Bring prior reports, particularly if you have had règles menstruelles abondantes or a history of gastrointestinal symptoms.
Finally, ask what would change the plan: repeat testing, iron replacement, imaging for splenic enlargement, hematology referral, or urgent review. Kantesti's clinical logic is described in our Guide de technologie IA, but personal treatment decisions belong with the clinician who knows your history.
Questions fréquemment posées
Les cellules en larme sur un frottis périphérique sont-elles toujours graves ?
Les cellules en larme ne sont pas toujours graves car un petit nombre peut résulter d'un artéfact de préparation de frottis, surtout lorsque les extrémités effilées s'alignent et se regroupent près du bord plumeux. Les dacrocytes persistants répartis sur tout le frottis méritent plus d'attention lorsque l'hémoglobine est basse, les plaquettes sont réduites ou que des cellules immatures apparaissent. Il n'y a pas de seuil de pourcentage universel d'inquiétude ; les laboratoires utilisent des rapports morphologiques semi-quantitatifs. Une répétition de la CBC et un frottis frais examiné manuellement peuvent clarifier une constatation isolée.
Que signifient les dacrocytes dans une analyse de sang ?
Les dacrocytes signifient que certains globules rouges ont un corps arrondi avec une extrémité effilée, créant une apparence en goutte d'eau. Ils peuvent survenir en cas de fibrose ou d'infiltration médullaire, de carence martiale sévère, d'anémie mégaloblastique, de changements spléniques ou d'artefact technique sur frottis. Les dacrocytes seuls ne diagnostiquent pas la myélofibrose, la leucémie ou le cancer. Leur signification dépend des résultats de la CBC tels que l'hémoglobine, l'MCV, les plaquettes, la formule leucocytaire et le taux de réticulocytes.
Une carence en fer peut-elle causer des dacryocytes ?
La carence en fer peut contribuer à la formation de cellules en forme de larme lorsque l'anémie et la variation de la forme des globules rouges sont importantes, mais elle produit généralement aussi un faible MCV, un faible MCH, une augmentation du RDW et une hypochromie. Une ferritinémie inférieure à 15 ng/mL suggère fortement une déplétion des réserves de fer chez des adultes par ailleurs en bonne santé, tandis que l'inflammation peut élever la ferritinémie malgré une carence. Une saturation de la transferrine inférieure à 20% peut apporter des preuves supplémentaires de la disponibilité limitée du fer. Les cliniciens doivent identifier la source de la perte de fer plutôt que de supposer que l'alimentation est la seule cause.
Quand les dacrocytes doivent-ils suggérer une référence en hématologie ?
Les dacryocytes doivent inciter à envisager une référence en hématologie lorsqu'ils persistent sur frottis répété et surviennent avec une anémie inexpliquée, une thrombocytopénie, des anomalies des globules blancs, des globules rouges nucléés, des granulocytes immatures, des blastes ou une splénomégalie. Une hémoglobine proche ou inférieure à 7 g/dL, des plaquettes inférieures à 50 × 10^9/L, ou une anémie symptomatique peuvent nécessiter une évaluation plus urgente. Les décisions de référence dépendent également de la vitesse de changement de la CBC et des antécédents de cancer ou de traitement. Un hématologue ne peut ordonner des tests de moelle, moléculaires ou d'imagerie que lorsque le tableau complet les justifie.
La déshydratation peut-elle causer des cellules en forme de larme?
La déshydratation peut concentrer l'hémoglobine et l'hématocrite, mais ce n'est pas une cause directe typique de véritables cellules en larme. Une lame de frottis sanguin mal préparée ou épaisse peut créer des artefacts de globules rouges pointus qui peuvent être confondus avec des dacrocytes. Si une déshydratation est suspectée, un clinicien peut répéter la CBC après une hydratation normale et vérifier si l'hémoglobine, le sodium, l'urée et la créatinine se normalisent. Des dacrocytes persistants après une répétition de frottis de qualité nécessitent une interprétation au-delà de l'état d'hydratation.
Quels symptômes avec des cellules en forme de larme nécessitent des soins d'urgence ?
Les soins d'urgence sont appropriés lorsqu'un rapport de cellules en larme survient avec des douleurs thoraciques, une syncope, un essoufflement au repos, une nouvelle confusion, des saignements incontrôlés, des selles noires ou sanglantes, ou une fièvre avec une faiblesse profonde. Ces symptômes peuvent indiquer une anémie sévère, une perte de sang active, une infection ou un taux dangereusement bas de plaquettes plutôt qu'une conséquence des dacrocytes eux-mêmes. Une hémoglobine proche ou inférieure à 7 g/dL est un seuil transfusionnel restrictif couramment utilisé chez les adultes hospitalisés stables, mais les symptômes et les conditions médicales peuvent nécessiter une intervention plus tôt. N'attendez pas un frottis répété si des symptômes graves sont présents.
Obtenez dès aujourd’hui une analyse de sang par IA
Rejoignez plus de 2 millions d’utilisateurs dans le monde qui font confiance à Kantesti pour une analyse instantanée et précise des analyses de laboratoire. Téléversez vos résultats prise de sang et recevez une interprétation complète des biomarqueurs de 15,000+ en quelques secondes.
📚 Publications de recherche citées
Équipe de recherche Kantesti (2026). Guide du bilan sanguin du complément C3 C4 et du titre ANA. Recherche médicale par IA Kantesti.
Équipe de recherche Kantesti (2026). Test sanguin de dépistage du virus Nipah : Guide de détection précoce et de diagnostic 2026. Recherche médicale par IA Kantesti.
📖 Références médicales externes
⚕️ Avertissement médical
Cet article est fourni à des fins éducatives uniquement et ne constitue pas un avis médical. Consultez toujours un professionnel de santé qualifié pour les décisions de diagnostic et de traitement.
Signaux de confiance E-E-A-T
Expérience
Revue clinique guidée par un médecin des flux d’interprétation des analyses.
Compétence
Orientation en médecine de laboratoire sur la façon dont les biomarqueurs se comportent dans un contexte clinique.
autorité
Rédigé par le Dr Thomas Klein, avec relecture par le Dr Sarah Mitchell et le Prof. Dr Hans Weber.
Fiabilité
Interprétation fondée sur des preuves, avec des parcours de suivi clairs pour réduire l’alarme.