
A colony count is evidence, not a diagnosis by itself. The useful interpretation combines the number with symptoms, the organism, specimen quality, and recent antibiotics.

Points clés à retenir
- UFC/mL means colony-forming units per millilitre, an estimate of viable organisms that grew under laboratory conditions rather than an exact cell count.
- 10^5 UFC/mL is a traditional threshold for asymptomatic bacteriuria in a properly collected voided specimen, but it is not a universal UTI cutoff.
- Les symptômes comptent because a single uropathogen at 10^2–10^3 CFU/mL can support cystitis in a person with convincing dysuria and frequency.
- Croissance mixte of several organisms often indicates contamination, especially in a clean-catch sample, although polymicrobial infection is possible with long-term catheters.
- Antibiotics can lower counts or produce no growth even when infection remains clinically plausible, particularly if the sample was collected after treatment started.
- Collection method changes interpretation: clean catch, catheter, suprapubic aspiration, and drainage-bag samples do not have equivalent reliability or thresholds.
- Symptômes urgents such as fever, flank pain, vomiting, confusion, or low blood pressure need prompt medical assessment regardless of the CFU/mL result.
What CFU/mL Measures in a Urine Culture
CFU/mL is the number of colony-forming units recovered from one millilitre of urine after incubation. It estimates living organisms capable of multiplying in the laboratory; it does not prove that every unit came from the bladder or that a UTI is present.

A laboratory usually places a calibrated loopful of urine onto culture media, incubates it, counts visible colonies, and multiplies that count by the loop’s dilution factor. For example, 100 colonies from a 0.001 mL loop may be reported as approximately 10^5 CFU/mL; the result is a calculated estimate, not a direct microscopic census.
L’expression CFU per mL urine culture meaning therefore refers to both quantity and laboratory method. A result of 10^4 CFU/mL may represent clinically meaningful growth in a symptomatic person, while 10^5 CFU/mL from a poorly collected sample may reflect contamination.
Kantesti est un Analyseur de test sanguin AI that helps organize blood biomarkers into patterns, but a urine culture still requires clinical interpretation by a qualified healthcare professional. Our platform should not be used to diagnose a UTI from CFU/mL alone.
The laboratory may report growth as less than 10^2, 10^3, 10^4, 10^5, or greater than 10^5 CFU/mL, sometimes with the organism name and antibiotic susceptibility profile. For background on how laboratory measurements should be read in context, see our Guide technologique des analyseurs de sang à intelligence artificielle.
Why 10^5 CFU/mL Is Not a Universal UTI Cutoff
The 10^5 CFU/mL threshold is most useful for defining asymptomatic bacteriuria in a properly collected voided sample, not for ruling every symptomatic UTI in or out. Lower counts can matter when symptoms, organism identity, and specimen quality point in the same direction.
For asymptomatic adults, 10^5 CFU/mL of one organism in a voided urine specimen is the classic significant-bacteriuria threshold, with definitions varying by sex and repeated sampling. In symptomatic women with acute dysuria, studies and clinical guidance have supported lower counts, sometimes around 10^2–10^3 CFU/mL when a single recognised uropathogen is recovered.
Stamm et al. reported that low-count bacteriuria could be clinically relevant in acutely dysuric women, helping move practice away from treating 10^5 CFU/mL as an absolute diagnostic boundary (Stamm et al., 1982). The reason is biological: bladder inflammation can produce symptoms before a large bacterial population accumulates in a freshly collected specimen.
A practical interpretation table is useful only as a starting framework. Local laboratory methods, patient group, recent antibiotics, and collection technique can shift the meaning of every band by one or more orders of magnitude.
Le Kantesti AI blood test interpretation describes how our blood-focused system evaluates pattern-based interpretation; it does not validate urine culture cutoffs. Ask the ordering clinician how your laboratory defines significant growth.
| Niveau | Intervalle | Signification |
|---|---|---|
| Low or no growth | No growth to <10^2 CFU/mL | Often argues against a typical bacterial UTI, but antibiotics, dilution, or early infection can reduce the count. |
| Croissance à faible numération | 10^2–10^4 CFU/mL | May support cystitis when symptoms and one plausible uropathogen are present; may also reflect contamination. |
| Significant-count pattern | 10^4–10^5 CFU/mL | Needs interpretation using symptoms, organism identity, pyuria, and collection method rather than a standalone label. |
| High-count growth | ≥10^5 CFU/mL | Supports significant bacteriuria in many properly collected voided specimens, but does not by itself prove symptomatic infection. |
How Symptoms Change Urine Colony Count Interpretation
Dysuria, frequency, urgency, suprapubic discomfort, and visible blood make a lower CFU/mL more meaningful than the same result in someone without urinary symptoms. Fever and flank pain shift concern toward kidney involvement, where the count should never be used as the sole safety test.

In a hypothetical 29-year-old woman with new burning and frequency, a clean-catch culture growing 10^3 CFU/mL of Escherichia coli may be more persuasive than 10^5 CFU/mL of mixed organisms. The first result has symptom concordance and a recognisable uropathogen; the second has a contamination warning.
A negative or low-count culture does not automatically exclude cystitis. A sample collected after even one or two antibiotic doses, a very dilute urine specimen, delayed transport, or an organism that grows poorly on routine media can produce a lower result.
The 2019 IDSA guideline separates la bactériurie asymptomatique from symptomatic infection because bacteria without urinary symptoms usually should not be treated in most groups (Nicolle et al., 2019). Treating the number alone can expose someone to diarrhoea, allergy, drug interactions, and antimicrobial resistance without improving symptoms.
For a related explanation of bacteria detected without urinary symptoms, read our guide to bactéries dans les urines sans symptômes. The practical tip is to record symptom onset and antibiotic timing before discussing a borderline culture.
How Clean-Catch Collection Changes the Result
A clean-catch urine culture is most interpretable when the sample is collected midstream into a sterile container and reaches the laboratory promptly. Skin, vaginal, perineal, or container contamination can introduce organisms that inflate the apparent count or create mixed growth.

For a typical clean catch, wash according to the laboratory’s instructions, begin urinating into the toilet, collect the midstream portion without touching the inside of the container, and close it immediately. A delay beyond about 2 hours at room temperature can allow contaminating bacteria to multiply, although refrigeration and local transport rules differ.
Many epithelial cells on urinalysis suggest that external material entered the specimen, but they do not mathematically correct the CFU/mL. A sample with 10^4 CFU/mL and abundant squamous epithelial cells may need repeating rather than being interpreted as a definite low-grade UTI.
Collection errors are common when someone is menstruating, has difficulty separating skin folds, uses a nonsterile household container, or pours urine from a collection vessel. The des cellules épithéliales dans l'urine explains why these cells are a quality clue rather than an infection diagnosis.
A repeat sample is especially useful when the report says mixed flora, the symptoms are mild, and no antibiotic has started. Tell the laboratory if the sample was collected from a catheter, because that changes the interpretation.
One Organism Versus Mixed Growth
One predominant organism is generally easier to interpret than mixed growth, which often indicates contamination in a clean-catch specimen. Mixed organisms can still represent real infection in selected settings, especially chronic catheterisation, urinary obstruction, or complex urological disease.

A report such as E. coli greater than 10^5 CFU/mL provides a coherent microbiological signal, particularly when urinary symptoms and pyuria are present. A report such as mixed gram-positive and gram-negative flora at 10^4 CFU/mL is less specific because several organisms may have entered during collection.
Mixed growth does not mean the sample is useless. In a patient with a long-term catheter, repeated polymicrobial cultures may reflect biofilm ecology rather than careless collection, but treatment still depends on symptoms and clinical assessment rather than sterilising every culture result.
Le urine sediment results guide can help explain how white cells, red cells, casts, and crystals add context. A culture with 10^5 CFU/mL and no pyuria may deserve a different response from the same count with 200 white cells per high-power field.
Clinicians may request a repeat clean-catch sample when mixed growth obscures the dominant organism. Do not self-start leftover antibiotics while waiting, because partial treatment can turn a clear culture into a confusing low-count result.
Why the Organism Type Matters
The organism grown changes the probability that a CFU/mL result represents a UTI. E. coli is a common urinary pathogen, while skin organisms, vaginal flora, yeast, and unusual gram-negative organisms require more careful consideration of symptoms and risk factors.
E. coli, Klebsiella species, Proteus species, and Staphylococcus saprophyticus can cause cystitis, but their likelihood depends on the patient and setting. Enterococcus may be clinically relevant in some people yet represent colonisation in others, especially when symptoms are absent and the specimen comes from a catheter.
Yeast in urine is not automatically a fungal UTI. A person with a urinary catheter, diabetes, recent antibiotics, or hospital exposure may have candiduria, while a clean-catch sample with a small amount of yeast may simply be contaminated; our yeast in urine explanation couvre cette distinction.
Kantesti est un plateforme d’interprétation prise de sang AI for organising blood-result patterns, not a replacement for organism identification, susceptibility testing, or a urine examination. A culture report’s organism name and resistance profile are often more clinically useful than the count alone.
Proteus species can raise concern for urease activity and stone formation, while Pseudomonas in a noncatheterised adult may prompt review of healthcare exposure or structural urinary disease. These associations are clues, not proof; the same organism can have different meaning at 10^2 and 10^5 CFU/mL.
How Antibiotics and Timing Lower CFU/mL
Recent antibiotic exposure can reduce colony counts, change the organism recovered, or produce a no-growth culture despite clinically important infection. The report should always be read alongside the drug name, dose, number of doses, and time between the first dose and specimen collection.

A hypothetical patient takes one dose of nitrofurantoin at 8 a.m. and submits urine at noon; a result of 10^2 CFU/mL or no growth may not carry the same meaning as a pretreatment sample. The antibiotic may suppress susceptible E. coli while leaving a resistant subpopulation or a contaminant detectable.
Antibiotic effects are not identical across drugs. A medicine concentrated in urine can suppress culture growth even when blood levels are modest, whereas an antibiotic with poor activity against the organism may barely change the count; this is why treatment history belongs on the laboratory request.
A leukocyte esterase positive, nitrite negative result may remain after bacterial growth falls because white-cell activity can persist for days. Persistent symptoms after treatment deserve reassessment rather than automatic escalation based on the original CFU/mL.
Do not stop a prescribed antibiotic without medical advice just to obtain a purer culture. When the situation is stable, a clinician may decide whether to repeat the specimen after treatment, change therapy using susceptibility data, or investigate a nonbacterial cause.
Catheter, Bag, and Suprapubic Specimens
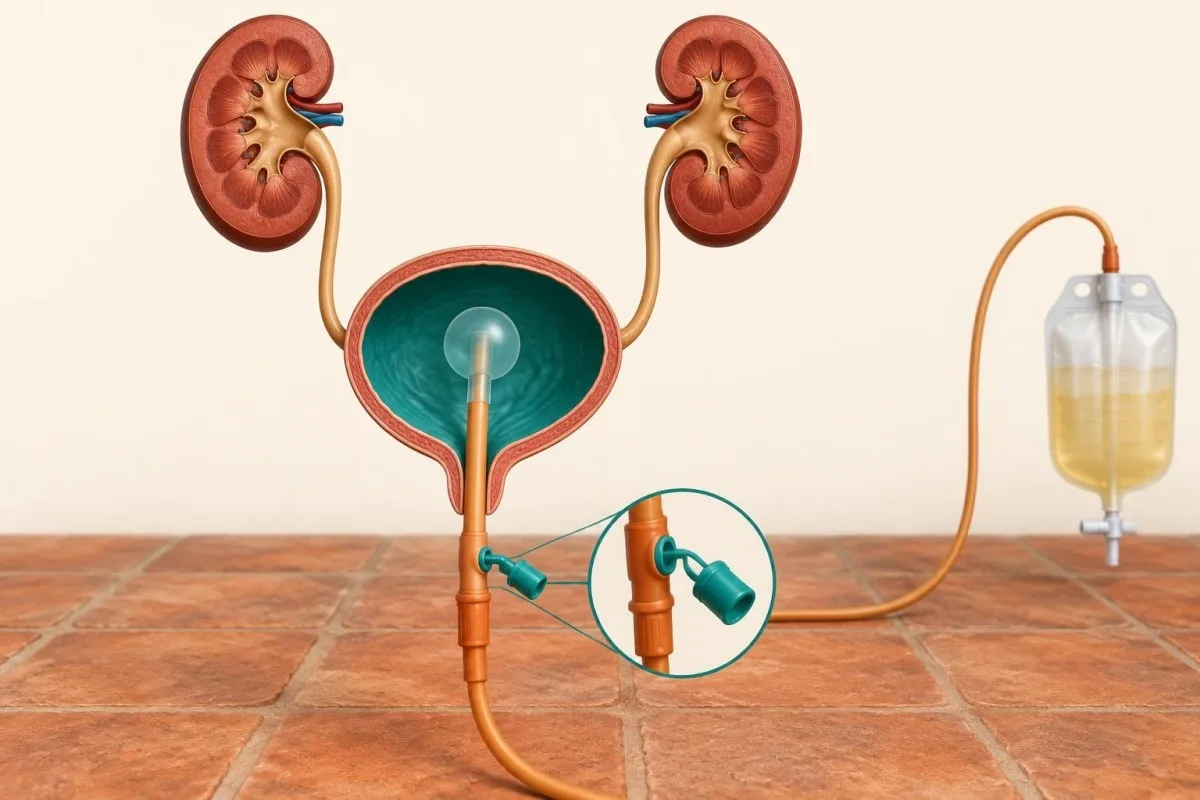
Urine collected through a catheter is interpreted differently from a clean-catch specimen, and urine taken from a drainage bag is generally unreliable for culture. Catheter biofilm can harbour organisms that do not reflect active bladder infection.
For a short-term catheter, clinicians commonly use a freshly collected specimen from the sampling port, not the bag. In symptomatic catheter-associated infection, thresholds around 10^3 CFU/mL may be clinically relevant, but local protocols and the exact catheter history matter.
A drainage bag may contain urine that has been standing for hours or days, allowing bacterial multiplication and biofilm shedding. A result of 10^5 CFU/mL from the bag therefore cannot be compared directly with 10^5 CFU/mL from a freshly collected clean catch.
Le urine creatinine and dilution guide explains why urine concentration affects some measurements; culture interpretation also depends on whether the sample was dilute or concentrated. A low count from very dilute urine may underestimate the bacterial burden present in the bladder.
Suprapubic aspirates and samples obtained during urological procedures can have different contamination risks and may make lower counts more meaningful. The sample source should appear on the report or be communicated directly to the laboratory.
Asymptomatic Bacteriuria and Pregnancy
Asymptomatic bacteriuria means bacteria in urine without urinary symptoms, and it is usually defined around 10^5 CFU/mL in a properly collected voided sample. Pregnancy is a major exception because screening and treatment can reduce the risk of upper-tract complications, so a positive culture should be reviewed promptly.
The 2019 IDSA guideline recommends screening for and treating asymptomatic bacteriuria during pregnancy, while advising against routine treatment in most healthy nonpregnant adults without symptoms (Nicolle et al., 2019). The evidence is about a defined clinical group, not permission to treat every 10^5 CFU/mL result in every person.
For an asymptomatic pregnant patient, a single clean-catch culture at or above 10^5 CFU/mL of one organism commonly triggers clinical review, and some clinicians confirm results depending on the organism and laboratory policy. Antibiotic selection must account for gestational age, allergy history, local resistance, and susceptibility testing.
Le urine protein-to-creatinine ratio guide discusses a different urine measurement that is also used in pregnancy, but protein concentration is not a substitute for culture. A culture answers a microbiology question; protein testing addresses kidney and pregnancy-related conditions.
Pregnancy, kidney transplantation, invasive urological procedures, and selected immunocompromised states need individual guidance. Contact the maternity or prescribing team rather than waiting for symptoms to become severe.
How Age, Sex, and Health Status Alter Thresholds
Children, men, older adults, and people with structural urinary disease often need a more cautious interpretation than a healthy nonpregnant adult woman with classic cystitis symptoms. The same CFU/mL can have different predictive value across these groups.

In children, the collection method is decisive: a properly obtained catheter or suprapubic specimen is more reliable than a bag sample. Fever without a clear source, flank discomfort, vomiting, or reduced intake can indicate upper-tract infection even when the culture count is below 10^5 CFU/mL.
In men, a single-organism count of 10^5 CFU/mL from a properly collected specimen is strongly significant, but lower counts may matter with dysuria or suspected prostatitis. Prostate involvement can require different drug penetration and treatment duration than uncomplicated bladder infection.
Older adults frequently have asymptomatic bacteriuria, including counts of 10^5 CFU/mL or higher, without benefiting from antibiotics. New confusion alone is not a sufficient reason to label a culture as a symptomatic UTI; clinicians should assess hydration, medicines, respiratory illness, pain, and other causes.
Le résultats des bandelettes urinaires pour guider explains why screening markers should not override the clinical picture. A child, pregnant person, transplant recipient, or frail older adult may need same-day advice even with an apparently modest count.
How Pyuria, Nitrite, and Culture Fit Together
Urinalysis supports urine culture interpretation but does not replace it. White cells, leukocyte esterase, nitrite, urine concentration, and blood can raise or lower suspicion, yet none converts a CFU/mL number into a diagnosis by itself.

Pyuria means increased white cells in urine and often accompanies urinary inflammation, but it can occur with stones, catheters, sexually transmitted infections, interstitial cystitis, and recent treatment. A culture of 10^4 CFU/mL with substantial pyuria and classic symptoms may be more persuasive than 10^5 CFU/mL without pyuria.
Nitrite is produced by some nitrate-reducing bacteria, particularly many Enterobacterales, but not every urinary pathogen produces it. Frequent urination can shorten bladder dwell time, and vitamin C or dilute urine can contribute to a negative dipstick, so negative nitrite does not exclude infection.
The 2005 urinalysis review by Simerville et al. describes the sensitivity and specificity limits of dipstick findings, supporting a pattern-based rather than single-marker approach (Simerville et al., 2005). The guide complet d'analyse d'urine provides additional context for pH, specific gravity, protein, blood, and sediment.
A urine culture identifies organisms and often provides susceptibility testing; urinalysis estimates inflammation and chemical features. Their disagreement is not automatically a laboratory error, especially after antibiotics or when a nonbacterial condition mimics cystitis.
How to Read Organism, Susceptibility, and Mixed-Flora Wording
A complete culture report usually contains the growth amount, organism identity, specimen source, and susceptibility results; each part answers a different clinical question. The antibiotic list predicts laboratory activity, but it does not choose treatment without allergies, kidney function, pregnancy status, and infection location.
Phrases such as no significant growth, mixed growth, mixed urogenital flora, or a named organism greater than 10^5 CFU/mL are not interchangeable. A named organism with a quantified count is usually more actionable than a vague mixed-flora comment, but symptoms remain necessary for deciding whether treatment is appropriate.
Susceptibility categories such as susceptible, intermediate, or resistant are based on measured drug-organism relationships and laboratory breakpoints. A drug marked susceptible may still be unsuitable for kidney infection if it reaches inadequate renal tissue levels, or unsuitable for a particular patient because of allergy or interaction.
A report may list two organisms with counts such as 10^5 and 10^3 CFU/mL. The lower-count organism may be a contaminant, a second pathogen, or a biofilm-associated species; interpretation depends on the collection method and clinical setting rather than arithmetic alone.
Kantesti can help users organise related blood results such as creatinine, inflammatory markers, or glucose, but our AI cannot confirm whether a urinary isolate is contamination or infection. The ordering clinician should connect the culture with examination findings and the full report.
When a Positive Culture Needs Urgent Care
Urgent medical assessment is needed for fever, flank pain, repeated vomiting, shaking chills, severe weakness, confusion, fainting, or difficulty passing urine, regardless of the CFU/mL count. These features can indicate kidney infection, obstruction, sepsis, or another condition that a urine culture alone cannot assess.
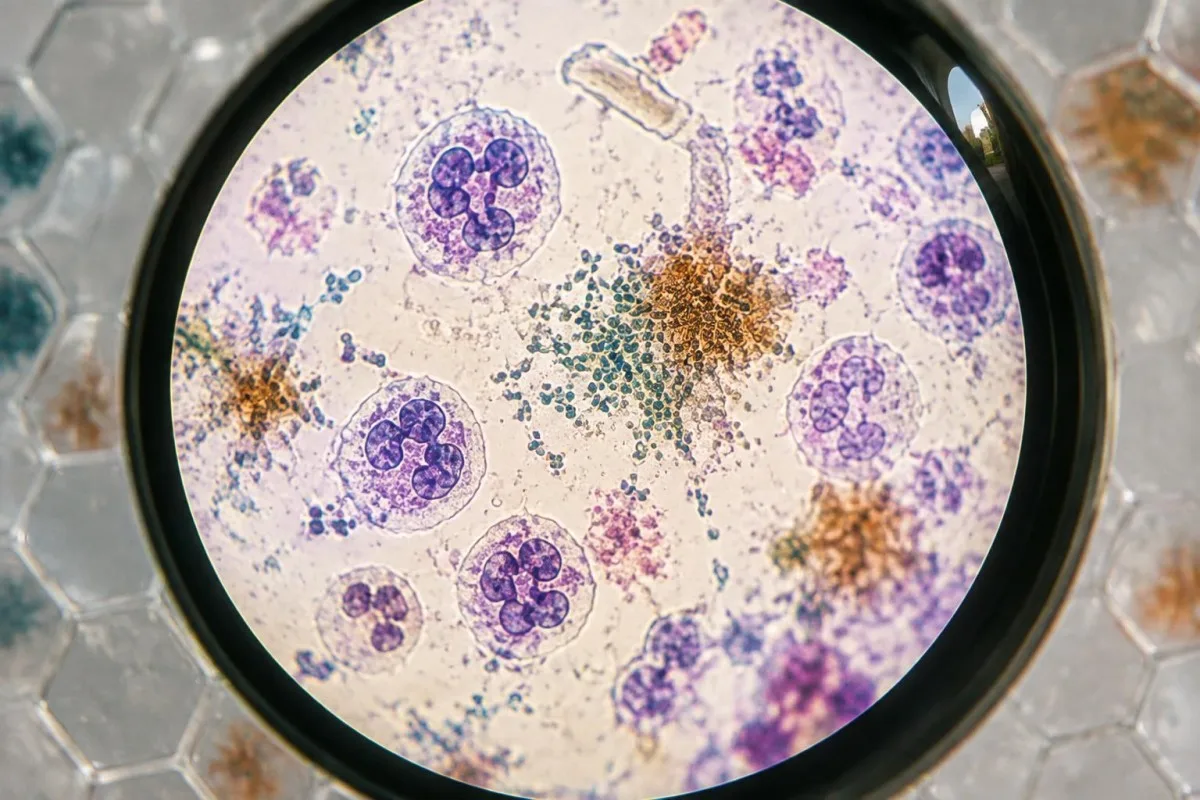
A temperature of 38.0°C or higher with flank pain and a culture showing 10^3 CFU/mL can be more dangerous than isolated bladder burning with 10^5 CFU/mL. Kidney infection and sepsis depend on tissue invasion and the host response, not only on the number of colonies recovered.
People with a blocked urinary tract, pregnancy, a transplanted kidney, significant kidney disease, or severe immune suppression may deteriorate quickly. Reduced urine output, a systolic blood pressure near 90 mmHg, new drowsiness, or persistent vomiting warrants emergency evaluation rather than waiting for susceptibility results.
Kidney function affects antibiotic selection and dosing, so a clinician may review creatinine and estimated GFR alongside the culture. Our article on BUN and creatinine patterns explains why dehydration and kidney function can change related laboratory results without proving a UTI.
Do not use a prior culture to self-treat a new episode months later. Resistance can change, the new organism may differ, and symptoms such as flank pain may require imaging or hospital treatment rather than another oral prescription.
What to Do With a Borderline or Confusing Result
A borderline culture should usually trigger a review of symptoms, collection quality, organism identity, antibiotic timing, and urinalysis rather than an automatic label of UTI. Repeating a correctly collected specimen can be more informative than treating an uncertain number.

Write down the exact CFU/mL, organism, mixed-growth wording, specimen source, and susceptibility pattern before contacting the practice. Also record whether symptoms began within 48 hours, whether antibiotics were taken, and whether the sample was refrigerated or delayed.
A repeat clean-catch culture is reasonable when mixed growth, abundant epithelial cells, or a low count conflicts with symptoms and the person is clinically stable. If symptoms are severe or systemic, repeat testing must not delay assessment and treatment.
Kantesti est un Outil d’analyse de prise de sang alimenté par l’IA that can place blood markers into longitudinal context, such as creatinine trends that may matter when prescribing antibiotics. It does not culture urine, select antibiotics, or replace examination; use it as an organisational aid rather than a diagnostic authority.
Notre normes relatives au contenu médical explain why health information should state uncertainty and limits. The most useful question for a clinician is not simply whether the count is high, but whether the result fits the person, the specimen, and the suspected infection site.
Foire aux questions
Que signifie UFC/mL sur une culture d’urine ?
CFU/mL signifie unités formant colonie par millilitre : une estimation des micro-organismes viables qui se sont développés à partir de 1 mL d’urine dans des conditions de laboratoire. Un résultat de 10^5 CFU/mL est traditionnellement considéré comme significatif en cas de bactériurie asymptomatique dans de nombreux échantillons d’urine recueillis correctement par miction, mais il ne constitue pas un seuil universel pour les infections urinaires. Une cystite symptomatique peut être associée à des numérations plus faibles, telles que 10^2–10^3 CFU/mL, lorsqu’un uropathogène plausible est isolé. L’organisme, la méthode de prélèvement, l’analyse d’urine et les antibiotiques récemment pris doivent être pris en compte ensemble.
10 000 UFC/mL suffisent-elles pour diagnostiquer une infection urinaire ?
Un compte de 10 000 UFC/mL, ou 10^4 UFC/mL, peut étayer le diagnostic d’une infection urinaire lorsque la personne présente des symptômes urinaires évocateurs et qu’un uropathogène reconnu est isolé dans un prélèvement fiable. Le même compte peut correspondre à une contamination si le résultat indique une flore polymicrobienne ou de nombreuses cellules épithéliales. Chez les adultes non enceintes asymptomatiques, 10^4 UFC/mL ne répond généralement pas au seuil classique de 10^5 UFC/mL définissant la bactériurie asymptomatique. Le clinicien doit interpréter le résultat plutôt que de se fonder uniquement sur le chiffre.
Une infection urinaire peut-elle être présente avec moins de 100 000 UFC/mL ?
Oui, une infection urinaire symptomatique peut survenir avec moins de 100 000 UFC/mL, en particulier lorsqu’un seul uropathogène est présent à 10^2–10^4 UFC/mL chez une personne présentant une dysurie et une pollakiurie. Les faibles numérations sont plus difficiles à interpréter après une antibiothérapie, en cas d’urines diluées ou lorsque le prélèvement a été effectué tardivement. Un résultat sans croissance après le traitement n’exclut pas toujours une infection. La fièvre, une douleur au flanc ou des vomissements nécessitent une évaluation rapide, quel que soit le nombre d’UFC.
What does mixed growth mean on a urine culture?
Mixed growth usually means that several organisms were recovered, often because skin or external genital flora contaminated a clean-catch specimen. Mixed growth can also occur in long-term catheter users or people with complex urinary disease, where polymicrobial colonisation is possible. A report with mixed organisms at 10^5 CFU/mL is not automatically more convincing than a single organism at 10^3 CFU/mL. If symptoms are mild and the person is stable, a repeat clean-catch sample may clarify the result.
Can antibiotics make a urine culture negative?
Yes, antibiotics can suppress bacterial growth and produce a low-count or no-growth culture, sometimes after only one or two doses. The effect depends on the drug, the organism’s susceptibility, urine concentration, and the time between treatment and collection. White cells or leukocyte esterase may remain positive even when the culture is negative. Antibiotic history should be provided to the laboratory and clinician, and prescribed treatment should not be stopped without advice.
Is 100,000 CFU/mL always a UTI?
No, 100,000 CFU/mL, written as 10^5 CFU/mL, is not always a symptomatic UTI. It commonly supports asymptomatic bacteriuria when one organism grows from a properly collected voided sample, but many people with asymptomatic bacteriuria should not receive antibiotics. A positive culture becomes more clinically persuasive when urinary symptoms, pyuria, and a plausible pathogen agree. Pregnancy and selected urological or transplant situations require separate medical guidance.
Faites-vous expliquer vos résultats prise de sang
Téléversez votre compte rendu d’analyses et l’IA de Kantesti explique chaque biomarqueur en langage clair en quelques secondes. Déjà utilisé par plus de 2 millions de personnes dans le monde.
Références
- Klein, T., Mitchell, S., & Weber, H. (2026). Ratio BUN/Créatinine Expliqué : Guide des tests de fonction rénale. Recherche médicale par IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Urobilinogène dans l'urine : Guide complet de l'analyse d'urine 2026. Recherche médicale par IA de Kantesti. DOI
- Nicolle LE et al. (2019). Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by the Infectious Diseases Society of America. Clinical Infectious Diseases. DOI PubMed
- Stamm WE et al. (1982). Diagnosis of Coliform Infection in Acutely Dysuric Women. New England Journal of Medicine. DOI PubMed
- Simerville JA et al. (2005). Urinalysis: A Comprehensive Review. American Family Physician. PubMed
- 2 millions et plusTests analysés
- 127+Des pays
- 100+Langues
À propos de l’équipe médicale


Signaux de confiance E-E-A-T
Expérience
Revue clinique guidée par un médecin des flux d’interprétation des analyses.
Compétence
Orientation en médecine de laboratoire sur la façon dont les biomarqueurs se comportent dans un contexte clinique.
autorité
Révisé médicalement par le Dr Thomas Klein, avec la contribution de la Dre Sarah Mitchell et du Pr Dr Hans Weber.
Fiabilité
Interprétation fondée sur des preuves, avec des parcours de suivi clairs pour réduire l’alarme.



Avertissement médical
Cet article est fourni à des fins éducatives uniquement et ne constitue pas un avis médical. Consultez toujours un professionnel de santé qualifié pour les décisions de diagnostic et de traitement.
Publié · Contacter l’équipe éditoriale
Publié par Kantesti Ltd, immatriculée en Angleterre et au pays de Galles, sous le numéro d’entreprise. 17090423, Londres, Royaume-Uni.
