
A high serum amyloid A result usually reflects inflammation—not proof of amyloidosis. The more useful questions are whether it stays elevated between illnesses and whether urine or kidney tests show organ involvement.

要点
- Serum amyloid A is an inflammation-responsive protein; a single elevated result cannot diagnose amyloidosis.
- 参考限值 vary by assay; many laboratories use an upper limit around 10 mg/L, but your report's own interval takes priority.
- Temporary elevation can accompany an infection or inflammatory flare; a hypothetical fall from 120 to 8 mg/L after recovery suggests resolution of that inflammatory response.
- 持续升高 matters more than one peak, especially when results remain above the laboratory limit between symptoms.
- AA amyloidosis develops from tissue deposits derived from serum amyloid A; blood testing measures the precursor, not the deposits.
- 复查 after an uncomplicated illness may be planned approximately 2–4 weeks after recovery, but this is a practical option rather than a universal guideline.
- 肾脏评估 often includes urine albumin-to-creatinine ratio, creatinine, and eGFR; an ACR of at least 3 mg/mmol warrants contextual assessment.
- Confirmed AA amyloidosis may be monitored using a specialist-directed SAA target below 10 mg/L; this treatment target is not a diagnostic cutoff.
Does a high serum amyloid A test mean amyloidosis?
不是。A high serum amyloid A result usually indicates an inflammatory response, not confirmed amyloidosis. Even a result of 100 mg/L can occur during an acute illness without tissue deposits; amyloidosis requires evidence of deposited amyloid and identification of its type, not simply an elevated precursor protein.
Serum amyloid A, usually abbreviated SAA, and AA amyloid are related but different materials. The first circulates during inflammation; the second consists of insoluble fibrils deposited in tissues. A hypothetical laboratory flag above 10 mg/L tells you that the circulating concentration exceeds that assay's reference limit, not that fibrils have formed.
Amyloidosis has several protein-specific forms, including AA, AL, 和 ATTR amyloidosis. These 3 names describe different precursor proteins and different diagnostic pathways; a high SAA result does not identify AL or ATTR disease. That distinction prevents a common reasoning error: treating every test containing the word amyloid as if it measured the same condition.
Kantesti 是一个 人工智能血液检测分析仪 that helps explain why an SAA result of 25 mg/L needs its laboratory range, illness timing, and associated kidney findings before interpretation. Our 生物标志物参考指南 provides broader laboratory context; an AI explanation cannot establish whether amyloid is present in tissue or replace clinical assessment.
How should you read serum amyloid A test results?
Serum amyloid A test results should be read against the reporting laboratory's reference interval, usually in mg/L. Many assays use an upper limit around 10 mg/L, but there is no universally accepted set of mild, moderate, or emergency SAA bands that diagnoses amyloidosis or determines urgency.

Units can change the apparent size of a result. One mg/L equals 1 µg/mL, whereas 10 mg/L equals 1 mg/dL. A report showing 2 mg/dL therefore represents 20 mg/L—not 2 mg/L—and confusing these units can create false reassurance or unnecessary alarm before any medical interpretation begins.
Different reference limits can produce different flags for the same concentration. For example, a hypothetical SAA of 8 mg/L is above a laboratory limit of 6 mg/L but below a limit of 10 mg/L. Our explanation of 定量实验室结果 clarifies why a numerical concentration and a positive-or-negative result carry different information.
Comparisons are strongest when serial samples use the same laboratory and assay. A change from 12 to 15 mg/L across 2 different methods may not have the same meaning as a large rise measured consistently during worsening symptoms. Our guide to 在实验室访问之间变化 explains biological and analytical variation without assuming every difference represents disease progression.
| 水平 | 范围 | 含义 |
|---|---|---|
| Within the example laboratory range | <10 mg/L | Compatible with low current inflammatory activity; does not exclude existing amyloid deposits or other amyloidosis types. |
| Above the example laboratory limit | ≥10 mg/L | Suggests an inflammatory response; the cause and clinical significance depend on symptoms, timing, and other tests. |
| Repeated elevation between illnesses | Serial results ≥10 mg/L | Using this example limit, persistent elevation warrants assessment of ongoing inflammation; it still does not establish AA amyloidosis. |
| Emergency SAA threshold | 不存在统一的截断值 | Urgency is determined by clinical deterioration and organ findings, not by an SAA number alone. |
How are serum amyloid A and amyloidosis connected?
The connection between serum amyloid A and amyloidosis concerns AA amyloidosis: sustained production of SAA supplies the precursor from which AA fibrils can develop. Acute-phase SAA includes 2 major inducible forms, SAA1 and SAA2; routine testing does not show whether circulating protein has become deposited amyloid.
Duration of exposure matters alongside concentration. Long-standing inflammatory disease can maintain SAA production for years, but not everyone with chronic inflammation develops AA amyloidosis. Protein processing, genetic susceptibility, and the underlying disease modify risk; a single concentration cannot provide an individual's probability or a reliable countdown to tissue deposition over the next 5 years.
A prospective study in The Lancet linked circulating SAA control with changes in amyloid load and clinical outcome in people already diagnosed with AA amyloidosis (Gillmore et al., 2001). Concentrations below 10 mg/L were associated with more favorable outcomes, but this was a monitoring study—not evidence that crossing 10 mg/L diagnoses amyloidosis in someone having their first test.
0 家族性地中海热, or FMF, illustrates why recurrent inflammation deserves a different assessment from an isolated respiratory illness. A hypothetical person with repeated fever episodes and SAA of 35 mg/L between attacks needs evaluation of the inflammatory syndrome and kidney screening. Our MEFV testing explanation describes why genetics supports a clinical diagnosis rather than replacing it.
What causes high serum amyloid A besides amyloidosis?
High serum amyloid A can result from infections, inflammatory arthritis, inflammatory bowel disease, autoinflammatory disorders, and tissue injury or recent procedures. Concentrations can rise into the hundreds of mg/L during acute inflammation, so magnitude alone cannot distinguish a temporary illness from the chronic exposure associated with AA amyloidosis.
SAA cannot reliably identify the organism or justify antibiotics by itself. Viral and bacterial illnesses can both raise SAA; a hypothetical result of 180 mg/L with fever does not determine which treatment is appropriate. Symptoms, examination, and targeted microbiology matter more than treating the inflammation marker as an organism-specific test or assuming a larger rise necessarily means bacterial disease.
Inflammatory markers can disagree because they respond differently to timing, disease, and treatment. At Kantesti, we treat a hypothetical SAA of 22 mg/L with CRP of 3 mg/L as a pattern to investigate—not proof that 1 result is wrong. Our WBC 和 CRP 对比 explains similar disagreements and why they cannot replace examination when someone is becoming unwell.
Organ-specific testing may be more informative than repeating broad markers indefinitely. Persistent diarrhea with SAA of 28 mg/L, for example, may prompt stool testing and gastrointestinal assessment rather than an immediate amyloidosis investigation. Our discussion of intestinal inflammation stool tests explains how calprotectin or lactoferrin can help localize a problem that a circulating inflammatory protein cannot locate.
Why do temporary and persistent SAA elevations differ?
A temporary SAA elevation rises with an inflammatory event and falls as that event resolves; persistent elevation continues between episodes or after recovery. A hypothetical change from 120 to 8 mg/L is reassuring about current inflammation, whereas repeated values of 18, 22, and 19 mg/L raise a different question.

Repeated exposure is more relevant to AA risk than one isolated peak. There is no universal rule that 2 abnormal samples or 6 weeks of elevation equals amyloidosis. Samples obtained during separate infections may not represent a genuinely elevated baseline; clinicians therefore ask whether the person was well, whether treatment changed, and whether the same inflammatory condition remained active between measurements.
In a cohort of 374 people with established systemic AA amyloidosis, amyloid deposits regressed in 60% of those whose median SAA was below 10 mg/L (Lachmann et al., 2007). Those figures describe an already diagnosed population; they cannot be used to calculate the risk of amyloidosis for an otherwise well person with a single high screening result.
A falling trend is not a measurement of disappearing deposits. In a hypothetical example, SAA falling from 120 to 8 mg/L represents an approximately 93% reduction in circulating concentration, not a 93% reduction in amyloid burden or future risk. Our 血液检测时间指南 explains why recording illness dates alongside results makes trends clinically interpretable.
Which findings make persistent SAA more concerning?
Persistent SAA elevation plus protein in the urine deserves more attention than SAA elevation alone because AA amyloidosis commonly affects the kidneys. A urine albumin-to-creatinine ratio, or ACR, of at least 3 mg/mmol is abnormal in standard adult categories, although many conditions other than amyloidosis cause albuminuria.

A normal eGFR does not exclude early kidney involvement. A hypothetical person with eGFR of 90 mL/min/1.73 m² and persistent ACR of 45 mg/mmol may still have substantial kidney disease because filtration and protein leakage measure different processes. The combination warrants assessment, but diabetes, other glomerular diseases, and several systemic conditions remain possible explanations—not just amyloid deposition.
Reduced filtration needs its own evaluation rather than being attributed automatically to a high SAA result. An eGFR below 60 mL/min/1.73 m² persisting for at least 3 months meets a standard chronic kidney disease criterion; an abrupt decline may instead indicate an acute problem. Our kidney warning signs guide explains symptoms that should accelerate assessment.
Foamy urine is a reason to consider testing, not a diagnosis. A hypothetical person with persistent bubbles, ankle swelling, and SAA of 30 mg/L should discuss urine protein measurement, serum albumin, and kidney function rather than relying on urine appearance. Our explanation of 持续的泡沫尿 separates potentially meaningful protein leakage from turbulence, concentrated urine, and cleaning products.
When should an elevated serum amyloid A test be repeated?
Repeat SAA testing is most useful when it answers whether inflammation has resolved or whether a known inflammatory disease is controlled. After an uncomplicated illness, a clinician may choose approximately 2–4 weeks after recovery; that interval is a practical option, not a validated universal SAA retesting schedule.

Do not postpone assessment just to obtain a cleaner baseline. A hypothetical SAA of 150 mg/L during persistent fever, worsening breathlessness, or reduced urine output should prompt evaluation of the illness now, not a routine repeat in 4 weeks. Retesting can accompany care, but it must not become a substitute for identifying infection, an inflammatory flare, or acute organ dysfunction.
A useful repeat request usually records 3 things: the date symptoms resolved, any medication changes, and whether the same assay will be used. Recovery after a procedure or hospital admission may take longer than the disappearance of fever; our guide to 住院后实验室变化 explains why discharge does not necessarily mean inflammatory markers have reached their baseline.
Kantesti 是一个 AI 生物标志物解读平台 that can place serial SAA results, such as 80, 24, and 9 mg/L, beside the dates supplied in a report or history. That sequence suggests falling inflammatory activity only if the measurements are comparable; our interpretation should not imply that 3 falling values exclude tissue amyloid or determine a medication dose.
Which blood and urine tests help interpret high SAA?
Useful companion tests often include CRP, a full blood count, creatinine with eGFR, serum albumin, and urine ACR or protein-to-creatinine ratio. These answer different questions; an SAA of 40 mg/L cannot tell whether kidney filtration is impaired, protein is leaking, or a separate blood-cell abnormality needs investigation.
Urine sampling conditions influence albumin measurements. Exercise, fever, urinary infection, and contamination can cause temporary abnormalities, so a modestly increased ACR may need confirmation under suitable conditions. A hypothetical ACR of 5 mg/mmol during fever is interpreted differently from the same result on repeated well-day samples; our 尿液 ACR 检测准备指南 explains practical collection choices.
Low serum albumin can reflect urinary loss, inflammation, impaired synthesis, or other causes. Many adult laboratories use approximately 35–50 g/L as their albumin interval, but albumin of 29 g/L does not identify which mechanism applies. Our 血清蛋白解释指南 explains why albumin and globulins should be interpreted with urine findings and the wider clinical picture.
Total urine protein and urine albumin are not identical measurements. In adults, protein excretion of at least 3.5 g per 24 hours is commonly described as nephrotic-range proteinuria, but nephrotic syndrome also requires clinical and laboratory context. Substantial protein loss with persistently elevated SAA warrants kidney assessment regardless of whether the eventual diagnosis is AA amyloidosis, another glomerular condition, or a mixed problem.
How do specialists confirm or exclude AA amyloidosis?
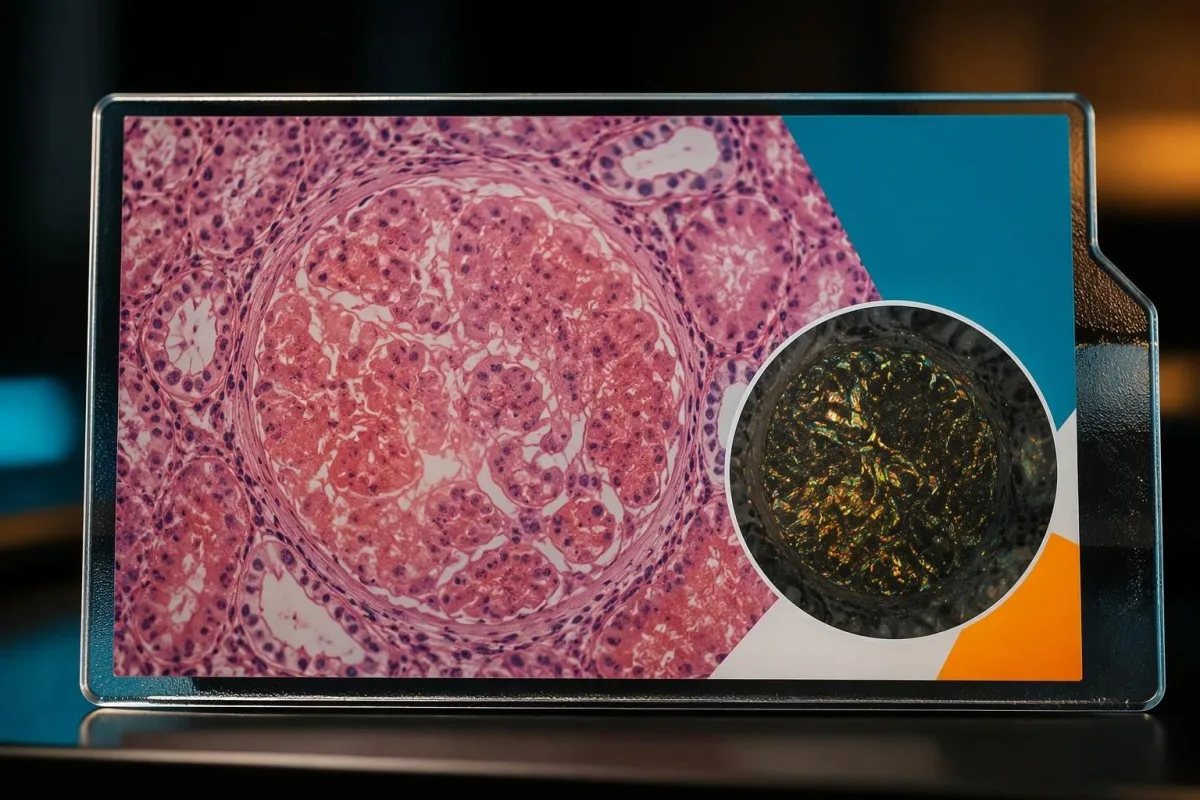
AA amyloidosis is generally confirmed by demonstrating amyloid in tissue and identifying the deposited protein as AA. Congo red staining supports detection, while validated protein typing establishes the subtype. An SAA concentration of 60 mg/L cannot replace either step, and the appropriate tissue examination depends on the clinical presentation.

Finding amyloid and naming its type are separate diagnostic tasks. Under polarized light, Congo-red-positive deposits characteristically show apple-green birefringence; immunohistochemistry or specialized mass spectrometry can then help identify the precursor. There are more than 3 systemic amyloidosis types, so an inflammatory history alone is not enough to label a deposit AA when another protein could require different treatment.
一个 AL amyloidosis workup commonly includes serum free light chains plus serum and urine immunofixation because a small abnormal clone may not produce an obvious routine electrophoresis spike. Kidney impairment also affects free light chain concentrations and ratios; our free light chain guide explains why 1 abnormal ratio does not independently establish AL amyloidosis.
A monoclonal protein does not automatically identify the deposited amyloid. A hypothetical older adult with SAA of 20 mg/L and a small monoclonal band could have inflammation and an unrelated gammopathy, making tissue typing especially valuable when amyloidosis is suspected. Our discussion of immunofixation result patterns explains why a band is evidence of a protein pattern—not proof of its clinical consequences.
When does high SAA need specialist or urgent assessment?
Specialist assessment may help when SAA remains elevated without a clear explanation, a chronic inflammatory disorder is poorly controlled, or urine and kidney findings suggest organ involvement. There is no SAA emergency cutoff: a result of 200 mg/L in a recovering person may be less urgent than new severe symptoms with 20 mg/L.
Referral should follow the suspected problem, not merely the test name. Rheumatology or an autoinflammatory service may assess unexplained recurrent inflammation; nephrology may assess proteinuria or falling filtration; a specialist amyloidosis center may help with confirmed or strongly suspected deposits. A hypothetical 3-month pattern of raised SAA plus abnormal urine testing can justify coordinated assessment without assuming that amyloidosis is already established.
Urgent medical care is appropriate for severe breathlessness, confusion, fainting, very low urine output, or rapidly worsening swelling, irrespective of SAA. These findings may reflect infection, fluid imbalance, or acute organ dysfunction rather than amyloid itself. A hypothetical person producing markedly less urine over 24 hours should not wait for another inflammation-marker result before seeking assessment of the underlying cause.
Urine abnormalities can suggest a different urgent diagnosis. Protein together with substantial blood, cellular casts, or a rapid creatinine rise may point toward an active glomerular process rather than uncomplicated chronic AA deposition. Our 全面尿液分析解释 describes how 2 urine reports with similar protein flags can carry different implications once sediment findings and symptoms are included.
How is persistent SAA treated or monitored?
Persistent SAA is managed by treating its underlying inflammatory cause, not by treating the number in isolation. In confirmed AA amyloidosis, specialists often aim to maintain SAA below 10 mg/L, informed by longitudinal outcome studies; the preferred target and monitoring interval still depend on the assay, disease, and treatment.
Disease-specific treatment matters more than generic anti-inflammatory advice. Colchicine is an established treatment for FMF and helps prevent its inflammatory complications; EULAR's 2016 recommendations address control of attacks and subclinical inflammation, including SAA monitoring where available (Özen et al., 2016). This does not make colchicine an appropriate self-treatment for an unexplained SAA of 25 mg/L in someone without an established indication.
Treatment can change symptoms and biomarkers at different rates. A hypothetical inflammatory arthritis patient whose SAA falls from 70 to 11 mg/L after prescribed therapy still needs assessment of symptoms, function, safety tests, and kidney findings. Our rheumatoid factor interpretation guide explains a related principle: no single laboratory marker provides a complete measure of inflammatory disease severity or treatment response.
Normalizing SAA does not mean organ follow-up can stop. Proteinuria and filtration may improve slowly, remain abnormal, or reflect irreversible damage despite good inflammatory control. A specialist might choose monitoring every 1–3 months during an active treatment adjustment, but that is an individualized example rather than a universal schedule; infection risk, medication toxicity, and the underlying disease determine what else needs checking.
What can a normal serum amyloid A result still miss?
A normal SAA result does not exclude existing AA amyloid deposits, AL amyloidosis, or ATTR amyloidosis. It mainly describes inflammatory precursor production around the time of sampling. A value of 6 mg/L after effective treatment can coexist with previously deposited AA amyloid and continuing proteinuria or reduced kidney function.
Serum amyloid A and serum amyloid P are different proteins. Serum amyloid P has been used in specialized imaging of amyloid deposits, whereas an SAA blood assay measures an inflammation-responsive precursor; neither name should be shortened to an interchangeable amyloid test. These 2 proteins also differ from amyloid-beta, which belongs to a separate neurological biomarker context rather than routine AA monitoring.
An unexpected result should first be checked against the report and sampling circumstances. Kantesti AI should not assume that SAA of 4 mg/L cancels out worsening kidney findings or that every flagged sample is analytically reliable. Our sample quality flag guide explains why interference comments require assay-specific review instead of assuming that a general sample flag affects every measurement equally.
Serial SAA is a proxy for inflammatory exposure, not a direct measure of fibril mass. A hypothetical patient with values below 10 mg/L for 3 months and continuing albuminuria may need continued organ monitoring rather than a new conclusion that amyloidosis was never present. Conversely, persistently raised SAA without organ findings is a reason to investigate inflammation—not to label a person with unconfirmed deposits.
How can you prepare SAA results for a useful clinical review?
准备 the original SAA report, its units and range, previous measurements, illness dates, medication changes, and available urine or kidney results. 。Kantesti 是一种 AI 血液检查解读平台 that can help organize this context; 1 isolated number is less useful than a documented sequence showing when each measurement occurred.
Useful questions focus on decisions rather than labels. Ask whether an SAA of 35 mg/L fits the recent illness, when a well-day repeat would change management, and whether urine ACR is appropriate given your history. Also ask what finding would trigger referral; agreeing on that threshold for action is more useful than repeatedly requesting tests without a clinical question or follow-up plan.
AI-assisted interpretation should preserve laboratory units and avoid converting uncertainty into a diagnosis. For example, 2 reports using different reference intervals should not be presented as definite deterioration without noting the methods and dates. Our AI解读技术指南 provides background on our approach; laboratory trends still require clinical verification before medication changes, reassurance about organ disease, or specialist referral decisions.
Kantesti LTD is a UK company, Company No. 17090423; our role is to explain laboratory information, not perform tissue diagnosis. Readers can review our company background when deciding how to use that support. A practical appointment note has 3 columns—result and units, symptoms at sampling, and treatment at sampling—so uncertainty remains visible rather than disappearing inside a summary.
Research publications: clinical evidence and interpretation limits
Clinical AA studies support longitudinal SAA monitoring, not diagnosis from a single elevated result. The Lancet study from 2001 and the NEJM cohort from 2007 examined people with established AA amyloidosis; their outcome associations cannot directly estimate risk for someone whose first SAA test is above the laboratory range.

Observational associations do not establish a universal screening threshold. The below-10 mg/L target in AA monitoring reflects favorable outcomes in diagnosed cohorts, not a sharp biological boundary between safety and deposition. Differences in inflammatory disease, treatment, exposure duration, and laboratory methods limit transfer to a healthy screening population; a value of 11 mg/L is not automatically a fundamentally different risk state from 9 mg/L.
The 2 Kantesti publications listed below address a synthetic technical benchmark and a clinical validation framework, not an SAA-specific prospective diagnostic study. A benchmark involving 100,000 synthetic cases does not by itself demonstrate sensitivity for AA amyloidosis in real patients. Our 技术和临床标准 should be read separately from the peer-reviewed medical references that support the clinical statements in this article.
The clinically useful distinction remains inflammation versus organ deposition. One high SAA result usually asks why inflammation is present; repeated elevation asks whether that exposure is continuing; abnormal kidney findings ask whether an organ disorder needs assessment. Those are 3 different questions, and keeping them separate allows repeat testing, disease-specific treatment, and specialist investigation to be used for the right reason.
常见问题解答
血清淀粉样蛋白A水平高是否意味着我患有淀粉样变性?
血清淀粉样蛋白 A 升高并不能诊断淀粉样变性;它通常提示存在炎症反应。许多实验室采用约 10 mg/L 的参考上限,但超过该限值并不能证明组织中存在沉积。慢性炎症患者若持续升高且伴有蛋白尿,可能需要进一步评估。AA 型淀粉样变性通常需要组织学证据和蛋白分型,而 AL 型和 ATTR 型淀粉样变性涉及不同的前体蛋白。.
血清淀粉样蛋白A检测的正常范围是多少?
The normal range for a serum amyloid A test depends on the laboratory and assay, with many laboratories using an upper limit around 10 mg/L. Your report's stated interval should take priority over a generic online range. One mg/L equals 1 µg/mL, and 10 mg/L equals 1 mg/dL. A result within range does not exclude previously established amyloid deposits or other amyloidosis types.
感染会导致血清淀粉样蛋白A水平非常高吗?
感染可使血清淀粉样蛋白A升至数百 mg/L,但这并不能证明患有淀粉样变性。病毒性和细菌性疾病均可使 SAA 升高,因此,像 150 mg/L 这样的数值本身无法确定病原体,也无法判断是否需要使用抗生素。治疗应根据症状、检查结果和有针对性的检测来指导。康复后复查有助于判断此次升高是否为暂时性的。.
什么时候应该重复进行血清淀粉样蛋白A高值检测?
A high serum amyloid A test should be repeated when the result will help assess recovery or control of an inflammatory condition. After an uncomplicated illness, a clinician may choose approximately 2–4 weeks after recovery, but there is no universal SAA retesting interval. Use the same laboratory when possible and record symptoms and medication changes at both sampling dates. Persistent fever, reduced urine output, or worsening breathlessness requires assessment rather than waiting for a routine repeat.
What SAA level causes AA amyloidosis?
No single serum amyloid A concentration reliably predicts when AA amyloidosis will develop. Sustained inflammatory exposure, the underlying condition, and individual susceptibility matter more than crossing 1 numerical boundary. In established AA amyloidosis, serial SAA below 10 mg/L has been associated with more favorable outcomes in longitudinal studies. That monitoring target is not a diagnostic threshold for a person with an isolated high result.
Can I have amyloidosis with normal serum amyloid A?
Amyloidosis can be present with normal serum amyloid A because the test does not measure tissue deposits and does not assess every amyloidosis type. A hypothetical SAA of 6 mg/L after successful inflammatory treatment can coexist with established AA deposits and continuing kidney abnormalities. AL and ATTR amyloidosis are not excluded by normal SAA. Evaluation depends on the suspected subtype, organ findings, and appropriate specialist tests.
Which tests should be checked with high serum amyloid A?
Companion tests for high serum amyloid A often include CRP, a full blood count, creatinine with eGFR, serum albumin, and urine albumin-to-creatinine ratio. Urine ACR of at least 3 mg/mmol is abnormal in standard adult categories, although the cause is not necessarily amyloidosis. Persistent proteinuria can be clinically significant even when eGFR is above 60 mL/min/1.73 m². The most useful combination depends on symptoms, previous results, and the suspected source of inflammation.
获取血液检查结果解读
上传您的实验室报告,Kantesti 的 AI 会在几秒内用通俗语言解释每项生物标志物。全球已有超过 200 万人使用。.
参考
- Klein, T., Mitchell, S., & Weber, H. (2026). 基于Kantesti血液检测解释引擎的预注册、基于评分量表的自动化技术基准,使用100,000个合成测试用例。. Kantesti AI 医学研究。. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). 临床验证框架 v2.0(医学验证页面)。. Kantesti AI 医学研究。. DOI
- Gillmore JD et al. (2001). Amyloid load and clinical outcome in AA amyloidosis in relation to circulating concentration of serum amyloid A protein. The Lancet. DOI
- Lachmann HJ et al. (2007). Natural History and Outcome in Systemic AA Amyloidosis. The New England Journal of Medicine. DOI
- Özen S et al. (2016). EULAR recommendations for the management of familial Mediterranean fever. Annals of the Rheumatic Diseases. DOI
- 200万+分析的检测项目
- 127+国家
- 100+语言
关于医疗团队


E-E-A-T信任信号
经验
由医生主导的临床审阅:实验室解读工作流程。.
专业知识
实验室医学重点:生物标志物在临床情境中的表现。.
权威
经 Thomas Klein 医生医学审核,并由 Sarah Mitchell 医生和 Hans Weber 教授参与撰写。.
可信度
基于循证的解读,并提供清晰的后续路径以减少警报。.




医疗免责声明
本文仅用于教育目的,不构成医疗建议。诊断和治疗决策请始终咨询合格的医疗专业人员。.
发表 · 联系编辑团队
由 Kantesti Ltd 发布,在英格兰和威尔士注册,注册公司编号:. 17090423, ,英国伦敦。.
