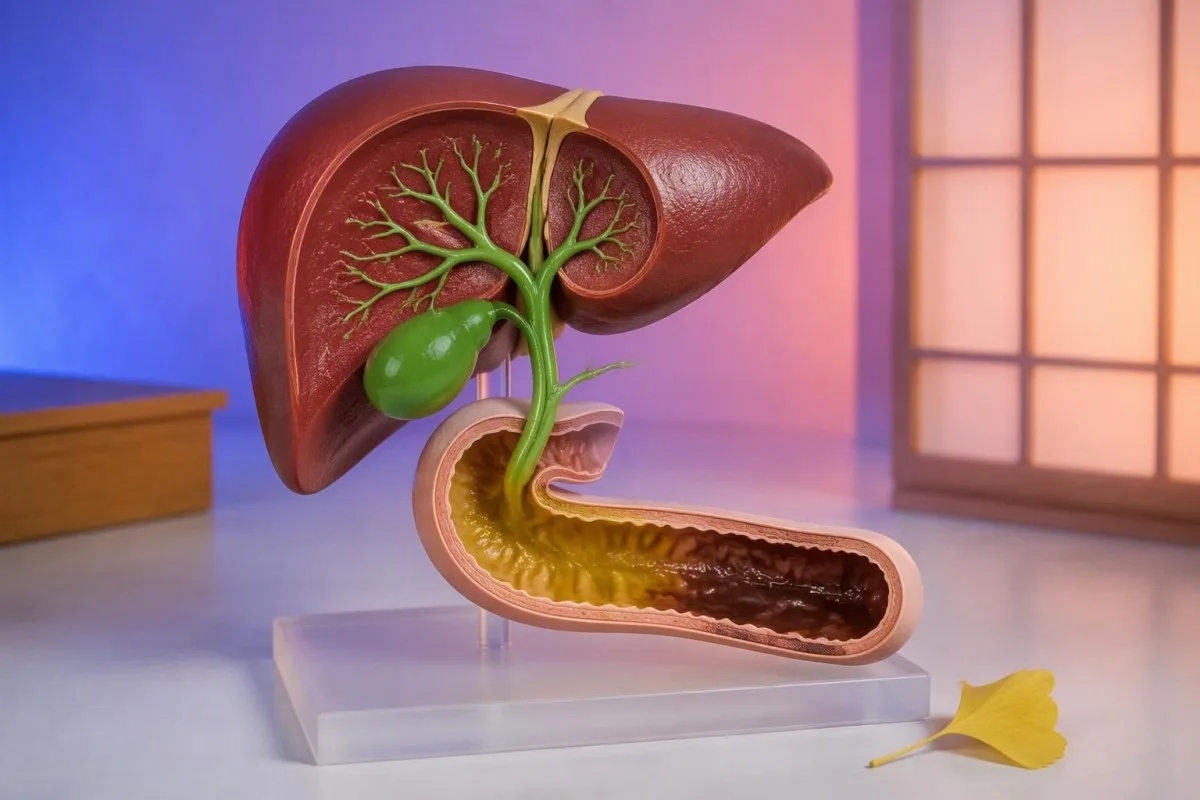
කහ පැහැති මළපහ බොහෝ විට කෙටි කාලීන ආහාර හෝ වේගවත් සංක්රමණ වෙනසක් වේ, නමුත් මේද සහිත නොකඩවා පැවතීම, තද මුත්රා, වේදනාව, උණ හෝ බර අඩු වීම ගණනය කිරීම වෙනස් කරයි. වැසිකිළියේ එක් බැල්මකට වඩා රටාව වැදගත් වේ.


- සංක්ෂිප්ත කහ මළපහ මේද අධික ආහාර, කහ, කැරට් හෝ පාචන රෝගයකින් පසු, පැය 48-72 තුළ විසඳෙන්නේ නම් එය සාමාන්යයෙන් හානිකර නොවේ.
- පිත්තාශ වර්ණකය සාමාන්යයෙන් මළපහ දුඹුරු පැහැයට හැරේ; වේගවත් සංක්රමණය බඩවැල් බැක්ටීරියා එය සම්පූර්ණයෙන් වෙනස් කිරීමට පෙර කහ-කොළ පැහැයෙන් ඉතිරි විය හැකිය.
- මේද සහිත, පාවෙන මළපහ ෆ්ලෂ් කිරීමට අපහසු වන අතර එය අතිරික්ත මේදය පෙන්නුම් කරන අතර අග්න්යාශය, පිත්තාශය හෝ කුඩා බඩවැල් මැලබ්සෝර්ප්ෂන් සඳහා සමාලෝචනයක් ඉල්ලා සිටිය යුතුය.
- සුදුමැලි මැටි මළපහ සමඟ තද මුත්රා බඩවැලට පිත්තාශය අඩු වීමක් පෙන්නුම් කළ හැකි අතර එකම දින වෛද්ය ඇගයීමක් අවශ්ය වේ.
- කහ පාචනය උණ, විජලනය, සංචාරක නිරාවරණය, හෝ දින 7කට වඩා පවතින රෝග ලක්ෂණ ඇති අයට මල පරීක්ෂා කිරීම අවශ්ය විය හැකිය.
- අක්මා පරීක්ෂණ ALP, GGT, බිලිරුබින්, ALT, සහ AST වැනි දේ බොහෝ බඩවැල් හේතු වලින් පිත්තාශයේ ගලා යන රටා වෙන්කර හඳුනා ගැනීමට උපකාරී වේ.
- අහිතකර ලෙස බර අඩුවීම මාස 6-12 තුළ 5% හෝ ඊට වැඩි ප්රමාණයක් සහ පවතින මල වෙනස්වීමක් වෛද්ය සමාලෝචනයක් අවශ්ය වේ.
- ළමයින් සහ වැඩිහිටියන් ඉක්මනින් විජලනය විය හැක; මුත්රා කිරීම අඩුවීම, කම්මැලි බව, හෝ දියර තබා ගැනීමට නොහැකි වීම හදිසි ප්රතිකාර අවශ්ය වේ.
වැඩිහිටියන් තුළ කහ මළපහ යනු කුමක්ද?
කහ මළපහ බොහෝ විට අදහස් කරන්නේ ආහාර පිත්තාශයේ වර්ණක සම්පූර්ණයෙන්ම දුඹුරු වීමට තරම් ඉක්මනින් බඩවැල් හරහා ගමන් කළ බවයි, නැතහොත් මෑතකදී ආහාර, අතිරේකයක්, හෝ පාචනය රෝගයක් එහි පෙනුම වෙනස් කර ඇති බවයි. වේදනාව, උණ, සෙංගමාලය, හෝ බර අඩු වීමකින් තොරව හුදකලා කහ මළපහක් කලාතුරකින් හදිසි තත්ත්වයකි.
පිත්තාශය කහ-කොළ තරලයක් ලෙස ආරම්භ වන අතර, බඩවැල් බැක්ටීරියා බිලිරුබින්-නිපදවන වර්ණක ස්ටර්කොබිලින් බවට පරිවර්තනය කරයි, එය ප්රධාන දුඹුරු මල වර්ණකයයි. සංක්රමණය වේගවත් වන විට, විශේෂයෙන් බ්රಿಸ್ಟල් වර්ගයේ 6 හෝ 7 මළපහ සමඟ, එම පරිවර්තනය අසම්පූර්ණ වන අතර එහි ප්රතිඵලය අබ කහ, කහ-කොළ, හෝ දුඹුරු පැහැයට පෙනෙන්නට පුළුවන. Bristol මළපහ වගුව (Bristol stool chart) වර්ණයට වඩා එය වඩාත් ප්රයෝජනවත් වන්නේ අනුකූලතාවය වේගය වෙනසට හේතු වනවාද යන්න අපට කියන බැවිනි.
මගේ සායනික අත්දැකීම් වලදී, ආලෝකය පුදුම සහගත ලෙස බොහෝ විට අනවශ්ය බියක් ඇති කරයි: සිසිල් LED නානකාමර ආලෝකය සාමාන්ය තද දුඹුරු මළපහ කහ පැහැයෙන් පෙනේ. ආචාර්ය තෝමස් ක්ලයින්, අනතුරු ඇඟවීමේ රෝග ලක්ෂණ නොමැති නම්, ආහාර වේලක් වෙනස් කිරීමට හෝ පරීක්ෂණ ඇණවුම් කිරීමට පෙර දිවා එළියෙන් ඊළඟ එක හෝ දෙකේ මළපහ පරීක්ෂා කරන ලෙස නිර්දේශ කරයි. 72 පැය වඩා අඩු කාලයක් පවතින සහ පැහැදිලි ආහාරමය ප්රේරකයෙකු අනුගමනය කරන වර්ණ වෙනසක් සාමාන්යයෙන් නිරීක්ෂණය කරනු ලැබේ, ප්රතිකාර නොකෙරේ.
කන්ටෙස්ටි යනු AI රුධිර පරීක්ෂණ විශ්ලේෂකය එය බිලිරුබින්, ක්ෂාරීය පොස්පේටේස්, GGT, ALT, AST, ඇල්බුමින්, සහ දැවිල්ල සලකුණු එකම අනුගාමික සන්දර්භයකට ගෙන එයි. එම පරීක්ෂණ මගින් මළපහ වල වර්ණය තනිවම හඳුනා නොගන්නා නමුත්, සායනික වශයෙන් වැදගත් අවහිර වීමක් කහ මළපහ සහ සෙංගමාලය සමඟ ඇති වනවාට වඩා අඩු සම්භාවිතාවක් ඇති කරයි.
වර්ණය යනු ඉඟියක්, රෝග විනිශ්චයක් නොවේ
වැසිකිළි බඳුනකට වර්ණය තනුක කර පරාවර්තනය කළ හැකිය, එබැවින් වෛද්යවරුන් අනුකූලතාවය, සංඛ්යාතය, තෙල් ගතිය, දුර්ගන්ධය, වේදනාව, medicine ෂධ ලබා ගැනීමේ කාලය, මෑතකදී ප්රතිජීවක ඖෂධ, සහ සංචාරය ගැන විමසනු ඇත. ඡායාරූපයක් වෛද්යවරයෙකුට පුනරාවර්තන රටාවක් සංසන්දනය කිරීමට උපකාරී වන නමුත්, එය තද මුත්රා හෝ දරුණු උදර වේදනාව සහිත සුදුමැලි මළපහ සඳහා වන හදිසි තක්සේරුවක් කිසි විටෙකත් ප්රමාද නොකළ යුතුය.
කහ මළපහ ඇති කළ හැකි ආහාර, අතිරේක සහ ඖෂධ
කහ, අධික කැරොටිනොයිඩ් සහිත ආහාර, ආහාර වර්ණ, සහ මේද සහිත ආහාරවල හදිසි වැඩිවීමක් රෝගයකින් තොරව කහ හෝ තැඹලි-කහ මළපහ නිපදවිය හැකිය. ප්රායෝගික පරීක්ෂණය නම් නිරාවරණය නැවැත්වූ පසු සහ මළපහ වල අනුකූලතාවය යථා තත්ත්වයට පත්වන විට වර්ණය ස්ථාවර වනවාද යන්නයි.
කහ හෝ කර්කුමින් අතිරේක 500-2,000 mg දිනපතා මාත්රාවලින් මළපහට දීප්තිමත් කහ පැහැයක් ලබා දිය හැකි අතර, කැරට්, ස්කොෂ්, පැණි අල, සහ කහ ආහාර වර්ණක තැඹිලි-කහ පැහැයට මාරු කළ හැකිය. මෙම වර්ණක සෙංගමාලයට සමාන නොවේ; ඒවා සාමාන්යයෙන් සුදුමැලි මළපහ, කැසීම, තද මුත්රා, හෝ සෘජු බිලිරුබින් වැඩි වීමක් ඇති නොකරයි. අතිරේක ලේබල්, විශේෂයෙන්ම කුඩු සහ ගම්මි, විවිධ වර්ණ ආකලන සමඟ සමාලෝචනය කරන්න.
මේදය සහිත අවන්හල් ආහාර නිසා ඊළඟ උදෑසන වඩාත් ලිහිල්, සැහැල්ලු මළපහක් ඇතිවිය හැකිය, එය වඩාත් ශක්තිමත් ගැස්ට්රොකොලික් චලනය උත්තේජනය කරයි. එය පුනරාවර්තන ස්ටෙටෝරියා වලින් වෙනස් වේ, එය මහා, ග්රීස්, සුදුමැලි-කහ, නිතර පාවෙන, සහ තෙල් සහිත පටලයක් ඉතිරි වන අතර. අපගේ මාර්ගෝපදේශය මළපහ වල නොදිරන ලද ආහාර දෘශ්ය ශාක කොටස් පමණක් malabsorption වල සාක්ෂි නොවන බව පැහැදිලි කරයි.
සමහර medicines ෂධ ද වැදගත් වේ: orlistat මේදය අවශෝෂණය අවහිර කරන බැවින් තෙල් සහිත කහ-තැඹිලි කාන්දු වීම බහුලව සිදු වන අතර, මැග්නීසියම් සහිත ප්රති-ඇසිඩ් සහ මෙට්ෆෝමින් සංක්රමණය වේගවත් කළ හැකිය. බිස්මුත් බොහෝ විට මළපහ අඳුරු කරයි, කහ පැහැයට හරවන්නේ නැත. නියමිත medicine ෂධයක් හදිසියේම නතර නොකරන්න; pharmacist ෂධවේදීවරයෙකු හෝ prescriber ෂධ නියම කරන්නෙකුගෙන් විමසන්න, කාලය සහ මාත්රාව වෙනසට ගැලපේද කියා.
වේගවත් සංක්රමණය කහ පාචනයට හේතු වන්නේ කෙසේද?
කහ පාචනය ඇතිවන්නේ මළපහ බඩවැල් හරහා වේගයෙන් ගමන් කරන විට, ජලය නැවත අවශෝෂණය කිරීමට සහ පිත්තාශයේ වර්ණක පරිවෘත්තීය කිරීමට ප්රමාණවත් කාලයක් ඉතිරි නොවන විටයි. වෛරස් ගැස්ට්රොඑන්ටරයිටිස්, කනස්සල්ලට සම්බන්ධ බඩවැල් වේගවත් කිරීම, ආහාර නොඉවසීම, සහ සමහර medicines ෂධ පොදු ප්රේරකයෝ වේ.
A person with abrupt watery diarrhea who is otherwise well often has a self-limited viral illness; yellow colour in that setting is usually a transit marker rather than excess bile production. Adults should aim for frequent oral rehydration, roughly 200-250 mL after each loose stool, adjusted for heart or kidney restrictions. Reduced urination for 8 hours, dizziness on standing, or confusion signals clinically meaningful dehydration.
Bile acids reaching the colon can stimulate water secretion and urgency, creating yellow-green loose stools. Bile acid diarrhea is especially worth considering after gallbladder removal, ileal disease, or ileal surgery, although symptoms overlap heavily with irritable bowel syndrome. The AGA guideline advises targeted testing for bile acid diarrhea in chronic watery diarrhea rather than assuming it is functional bowel disease (Smalley et al., 2019).
If loose yellow stool follows fasting, a large coffee, or a high-fructose drink, tracking the trigger for 2 weeks can be more revealing than a random single stool test. For a more detailed distinction between short-term and persistent symptoms, read our ආහාර ජීර්ණ රෝග ලක්ෂණ මාර්ගෝපදේශය. Blood in stool, nocturnal diarrhea, or symptoms persisting beyond 4 weeks move this out of the self-care category.
මළපහ තුළ පිත කහ සිට දුඹුරු පැහැයට වෙනස් කරන්නේ කෙසේද?
Bile in stool is normal; reduced delivery of bile or unusually rapid movement through the bowel changes its expected brown colour. Yellow-green stool usually reflects pigment that has not been fully processed, whereas putty-coloured or grey-white stool raises concern for too little bile entering the gut.
The liver makes about 500-1,000 mL of bile daily, and the gallbladder concentrates and releases it after meals. Bilirubin enters bile after red-cell pigment is processed by the liver, then intestinal microbes convert it through urobilinogen-related compounds into brown stercobilin. This is why a true blockage often produces both pale stool and dark tea-coloured urine: conjugated bilirubin is redirected into urine.
A yellow stool is not automatically “too much bile.” That phrase gets repeated online, but clinicians usually mean rapid transit, bile acid-related diarrhea, or impaired fat digestion when they investigate. The combination of a pale stool, generalized itching, yellow eyes, and dark urine is more informative than stool colour by itself; see our overview of ඉහළ සෘජු බිලිරුබින්.
Kantesti AI interprets liver-panel results as a pattern, not as isolated red flags. A raised ALP and GGT with direct bilirubin elevation is more compatible with cholestasis than an isolated mild ALT rise, while completely normal bilirubin and ALP make a major bile-duct blockage less likely. Reference intervals still vary by laboratory, so the report’s own range remains the starting point.
කහ මළපහ කවදාද පිත්තාශය, අක්මාව හෝ පිත්තාශ මාර්ග ගැටලුවක් පෙන්නුම් කරන්නේ?
Yellow stool becomes more concerning when it is pale or clay-like and occurs with dark urine, jaundice, fever, itch, or right-upper abdominal pain. These features can indicate cholestasis, hepatitis, gallstone-related obstruction, or less commonly pancreatic obstruction.
Obstructive patterns are most urgent when pain is severe or fever develops. A stone obstructing the common bile duct may cause episodic upper abdominal pain, nausea, jaundice, and rising bilirubin; fever with jaundice and abdominal pain can indicate ascending cholangitis and needs emergency assessment. The cholecystitis blood test guide explains why normal early blood work cannot safely exclude a biliary problem when symptoms fit.
For adults, ALP above the laboratory upper limit plus elevated GGT supports a hepatobiliary source of ALP, although neither test locates a blockage. Total bilirubin above approximately 34 µmol/L (2 mg/dL) can make yellowing of the eye whites visible, but visible jaundice may appear earlier or later depending on skin tone and lighting. Ultrasound is often the first imaging test when obstruction is suspected.
කන්ටෙස්ටි යනු AI රුධිර පරීක්ෂණ ප්රතිඵල වේදිකාව used to identify liver-test combinations that merit clinical follow-up rather than to replace an examination or scan. As of September 30, 2026, our clinical rule remains straightforward: pale stool with dark urine should be assessed the same day, even if pain has eased. Early obstruction can fluctuate, which is the annoying part.
මේද සහිත කහ මළපහ සහ මැලබ්සෝර්ප්ෂන් රටා
Repeated greasy, floating, foul-smelling yellow stool can indicate fat malabsorption, also called steatorrhoea. Pancreatic enzyme deficiency, coeliac disease, bile-flow disorders, and small-bowel disease are leading explanations when this pattern persists.
Steatorrhoea is not just a stool that floats once; it is usually recurrent, bulky, difficult to flush, and may leave an oily ring. People can lose weight despite eating normally because unabsorbed fat carries calories away, and long-standing malabsorption may lower fat-soluble vitamins A, D, E, and K. A qualitative stool-fat screen can help, but a timed 72-hour fecal-fat collection remains a reference method in selected cases.
Pancreatic exocrine insufficiency becomes more plausible with upper abdominal symptoms, diabetes, chronic pancreatitis risk factors, or low fecal elastase. A fecal elastase value below 200 µg/g supports pancreatic insufficiency, while values below 100 µg/g are more strongly suggestive; watery samples can falsely lower the measurement by dilution. Our stool elastase explanation covers this often-missed pre-analytic trap.
Coeliac disease may cause loose pale-yellow stools, iron deficiency, folate deficiency, abdominal bloating, fatigue, or no obvious gastrointestinal symptoms at all. The 2023 ACG guideline recommends tissue transglutaminase IgA testing with total IgA while the person is eating gluten, because starting a gluten-free diet before testing can produce a falsely reassuring result (Rubio-Tapia et al., 2023).
ආසාදනය, පරපෝෂිතයන් සහ ගමන්-සබැඳි කහ මළපහ
Acute yellow diarrhea with cramps is often infectious, while persistent greasy diarrhea after untreated water exposure raises suspicion for Giardia and other parasites. Most short illnesses resolve, but duration, fever, travel history, and immune status determine whether testing is sensible.
Giardia often produces bloating, sulfurous belching, fatigue, and pale or greasy loose stools 1-2 weeks after exposure, though timing varies. Risk rises after drinking untreated surface water, daycare exposure, or close household contact; a multiplex stool PCR or antigen test can detect infection without relying on a single microscopy sample. Persistent symptoms deserve a test rather than repeated empiric antibiotics.
Invasive bacterial illness is more likely when diarrhea contains blood, fever exceeds 38.5°C, or there is significant abdominal tenderness. The ACG guideline on acute diarrheal infections recommends stool testing when symptoms are severe, prolonged, dysenteric, or linked to outbreak and travel circumstances (Riddle et al., 2016). Antibiotics can occasionally worsen particular infections, so the diagnosis matters.
Children with yellow watery stools need a lower threshold for assessment because dehydration can develop over hours rather than days. Track wet nappies or urine output, tears, alertness, and drinking—not merely bowel-movement count. Our මළ සංස්කෘති මාර්ගෝපදේශය explains why a positive organism is interpreted alongside symptoms, not treated automatically.
නොකඩවා පවතින කහ මළපහ සඳහා වෛද්යවරුන් භාවිතා කරන පරීක්ෂණ
Persistent yellow stool is assessed with history first, then targeted liver tests, coeliac blood tests, stool studies, and imaging when the pattern points toward bile, infection, or malabsorption. There is no single “yellow stool blood test.”
A useful first blood panel often includes full blood count, electrolytes, CRP, ALT, AST, ALP, GGT, bilirubin, albumin, and coeliac serology. Low albumin below 35 g/L can occur with significant intestinal protein loss, liver synthetic dysfunction, or inflammation, but it is not specific to malabsorption. If diarrhea is prolonged, potassium and bicarbonate are clinically relevant because bowel losses can disturb both.
Stool testing should answer a question: PCR or culture for an infectious syndrome, fecal calprotectin or lactoferrin for suspected intestinal inflammation, fecal elastase for possible pancreatic insufficiency, and fecal fat when steatorrhoea is convincing. Calprotectin is best viewed as an inflammation signal rather than a diagnosis; our comparison of calprotectin and lactoferrin explains the trade-offs.
කන්ටෙස්ටි යනු AI මගින් බලගැන්වූ රුධිර පරීක්ෂණ විශ්ලේෂණ මෙවලම that can organize relevant blood-test trends, including bilirubin and ALP changes over time, in about 60 seconds after a report upload. A normal blood panel cannot rule out Giardia, bile acid diarrhea, or mild coeliac disease, so our output should support a clinician-led next step rather than falsely close the investigation.
මළපහ වල වර්ණය සමඟ අක්මා පරීක්ෂණ කියවීම
A cholestatic liver-test pattern usually means ALP and GGT rise more prominently than ALT and AST, often with direct bilirubin elevation. Stool colour adds useful context, but blood results and symptoms determine urgency.
ALT and AST reflect hepatocyte injury more than bile flow, while ALP can arise from liver or bone. GGT helps clinicians decide whether a raised ALP is likely hepatobiliary, though alcohol, metabolic liver disease, and certain medicines can raise GGT without obstruction. A GGT of 90 IU/L with normal bilirubin means something very different from GGT 90 IU/L plus jaundice and pale stool.
The R-ratio can assist specialists: divide ALT as a multiple of its upper limit by ALP as a multiple of its upper limit. A ratio above 5 suggests a hepatocellular pattern, below 2 suggests cholestatic injury, and 2-5 is mixed; it is a triage tool, not a diagnosis. Patients can explore the component tests in our කොලෙස්ටැසිස් රුධිර-පරීක්ෂණ මාර්ගෝපදේශය.
Dr. Thomas Klein has seen people worry about a marginally high ALP that later proves to be bone-related, particularly during fracture healing or vitamin D deficiency. That is why clinicians may add ALP isoenzymes, vitamin D, calcium, phosphate, or imaging rather than assuming a liver diagnosis. The stool story can make that distinction more or less urgent.
පිත්තාශය ඉවත් කිරීමෙන් පසු කහ පාචනය
Diarrhea after gallbladder removal can occur because bile flows continuously into the intestine rather than being released in concentrated pulses with meals. It often begins soon after surgery, is worse after fatty meals, and can be yellow-green because transit is accelerated.
Not everyone develops post-cholecystectomy diarrhea, and it is not automatically lifelong. Smaller lower-fat meals for 2-4 weeks can reduce urgency while the bowel adapts, but severe restriction is rarely necessary long term. Persistent watery stools more than 4 weeks after surgery should prompt discussion of bile acid diarrhea and other causes, especially if symptoms wake a person at night.
Where available, SeHCAT retention testing can support bile acid malabsorption; alternatives include serum 7α-hydroxy-4-cholesten-3-one or carefully monitored treatment trials. Bile-acid sequestrants may help but can interfere with absorption of thyroid medication, warfarin, and fat-soluble vitamins, so dose spacing is not a minor detail. A pharmacist can provide the exact schedule.
This pattern differs from a new episode of severe pain, fever, jaundice, or pale stool after surgery, which needs urgent assessment for a retained stone or another complication. Our overview of the පිත්තාශ අම්ල රුධිර පරීක්ෂාව also explains why generalized itching shifts attention back toward cholestasis rather than simple rapid transit.
ළමුන්, ගර්භනී කාන්තාවන් සහ වැඩිහිටියන් තුළ කහ මළපහ
Yellow stools are common in breastfed infants and are usually normal, while persistent pale stools in any child require prompt paediatric evaluation. Pregnancy and older age also change the threshold for acting because dehydration and bile disorders carry different risks.
Breastfed infant stool is frequently mustard-yellow, loose, and seedy; that is expected when an infant is feeding and growing normally. Acholic stool, meaning distinctly white, grey, or putty coloured, is different and should be assessed urgently because biliary atresia and other neonatal cholestatic conditions are time-sensitive. Parents are right to trust a repeated colour pattern rather than one diaper under odd lighting.
During pregnancy, new pale stool, dark urine, itching of the palms or soles, or jaundice should lead to same-day maternity assessment. Serum bile acids can rise in intrahepatic cholestasis of pregnancy, but the test should be interpreted with liver results, gestational age, symptoms, and local obstetric guidance. The itching blood-test guide gives a practical testing framework.
In older adults, a new persistent stool change deserves attention sooner because medication effects, pancreatic disease, malignancy, and infection are more common, while thirst may be blunted. A loss of 5% body weight in 6-12 months is clinically significant at any age. Frailty, kidney disease, or diuretic use lowers the margin for dehydration.
පළමු පැය 72 තුළ කළ යුතු දේ
For a single yellow stool or mild yellow diarrhea without red flags, hydration, a brief food-and-symptom record, and observation for 48-72 hours are reasonable. Avoid aggressive “cleanses,” fasting, or self-started antibiotics, which often muddy the clinical picture.
Write down the timing, Bristol stool type, meals, supplements, medicine changes, travel, fever, pain, urine colour, and number of bowel movements. This is more clinically useful than describing stool as “weird.” If you had a high-dose turmeric product, a fatty meal, or a stomach bug and symptoms settle within 3 days, no testing may be required.
Use oral rehydration solution rather than only plain water if diarrhea is frequent; standard solutions contain glucose and sodium in proportions that improve intestinal water absorption. Adults without fluid restrictions can use small repeated sips, especially after each loose stool. Avoid sports drinks as the sole replacement when diarrhea is substantial because their sodium content is often lower and sugar content higher.
If symptoms persist, our blood test for diarrhea guide can help you prepare questions for a clinician. Kantesti AI can also place liver and electrolyte results in chronological context, but an app cannot assess abdominal tenderness, hydration status, or jaundice through a screen. Those limitations matter.
කහ මළපහ කවදාද වෛද්ය සමාලෝචනයක් හෝ හදිසි ප්රතිකාරයක් අවශ්ය වන්නේ?
Seek urgent care for pale stool with dark urine or jaundice, severe or worsening abdominal pain, fever with jaundice, fainting, confusion, or signs of major dehydration. Arrange routine medical review for yellow stool lasting more than 1-2 weeks, recurring greasy stool, weight loss, or persistent diarrhea.
Emergency assessment is appropriate for inability to keep fluids down, black tarry stool, visible blood, severe weakness, a rigid abdomen, or jaundice with fever. These combinations carry more diagnostic weight than yellow colour alone because they may indicate bleeding, significant infection, obstruction, or systemic illness. If in doubt, err on the side of being seen—particularly for children, pregnancy, and immunosuppression.
A non-urgent appointment is still warranted if stool changes persist beyond 7 days with diarrhea or beyond 2 weeks without diarrhea, even when pain is absent. Bring medication and supplement containers, a 7-day symptom log, and prior laboratory reports. The article on blood in stool urgency helps distinguish red and black warning colours from benign food effects.
Kantesti's medical review standards are described by our වෛද්ය උපදේශක මණ්ඩලය, සහ අපේ අපගේ සායනික වලංගුකරණ ප්රවේශය explains where automated interpretation stops. Kantesti is an AI රසායනාගාර පරීක්ෂණ අර්ථකථන සේවාව designed to surface follow-up patterns; it does not provide emergency triage or replace a clinician examining you.
කහ මළපහ හමුවීම වඩාත් ප්රයෝජනවත් කරන ප්රශ්න
The most useful appointment questions ask whether the stool pattern fits rapid transit, malabsorption, infection, or impaired bile flow and which test would change management. A focused history can prevent both under-testing and broad low-yield testing.
Ask: “Does my symptom pattern justify liver tests, coeliac testing, stool PCR, fecal calprotectin, fecal elastase, or ultrasound?” The answer should be tied to your duration, weight change, pain location, travel, surgery, and stool texture. A blanket panel is not always better; for example, stool PCR does not diagnose pancreatic enzyme deficiency, and liver tests do not rule out Giardia.
Ask for the actual results and the laboratory reference ranges, not simply “normal” or “abnormal.” A bilirubin trend from 9 to 28 µmol/L may be meaningful if it is paired with new dark urine, while an isolated stable bilirubin of 24 µmol/L can have a different explanation. Our අක්මා පැනල් සාරාංශය outlines what each component can and cannot tell you.
Kantesti AI was built by Kantesti Ltd to help people organize laboratory reports across visits, with privacy-focused handling and multilingual interpretation in 75+ languages. For the method behind that work, see our AI තාක්ෂණික මාර්ගෝපදේශය. A good next step is specific: test, monitor, image, treat, or safely observe—not merely “repeat everything.”
පතුළේ රේඛාව: සමස්ත රටාවට වර්ණය ගලපන්න
Most yellow stool causes are temporary dietary or fast-transit effects, but pale stool, greasy recurrence, dark urine, jaundice, fever, pain, or weight loss need medical evaluation. The combination of colour, texture, duration, and associated symptoms is far more reliable than colour alone.
A brief yellow stool after turmeric, a rich meal, or a 24-hour diarrheal illness can usually be watched for 48-72 hours. Repeated oily floating stool points toward fat malabsorption, while clay-coloured stool with dark urine points toward reduced bile flow. That distinction is clinically useful because the investigations—and the urgency—are different.
Keep the evidence in proportion. Most patients I see with a short-lived colour change do not have serious liver or pancreatic disease, yet a small number have warning combinations that should not be dismissed as “just diet.” The fecal fat test guide is a sensible next read when oiliness and floating are the recurring features.
කන්ටෙස්ටි යනු AI biomarker interpretation platform that helps connect laboratory patterns to informed questions for your clinician. It is not a substitute for care when red flags are present; severe pain, jaundice, fever, dehydration, or pale stool with dark urine should always be assessed in person.
නිතර අසන ප්රශ්න
වැඩිහිටියන්ගේ කහ මළපහ යනු කුමක්ද?
වැඩිහිටියන්ගේ කහ මළපහ සාමාන්යයෙන් සිදුවන්නේ බඩවැල් වේගයෙන් ගමන් කිරීම, මෑතකදී ආහාරයට ගත් වර්ණකයක්, අධික මේද සහිත ආහාරයක් හෝ කෙටි කලක් පවතින පාචනීය රෝගයක් නිසාය. එය මෘදු හෝ ජලය සහිත වන අතර, වේදනාව, උණ, තද මුත්රා, සෙංගමාලය හෝ බර අඩු වීමකින් තොරව පැය 48-72 තුළ පහව ගියහොත්, එය සාමාන්යයෙන් හදිසි තත්ත්වයක් නොවේ. නැවත නැවත සිදුවන මේද සහිත, පාවෙන, සේදීමෙන් ඉවත් කිරීමට අපහසු කහ මළපහ මේද අවශෝෂණය අඩුවීමක් පෙන්නුම් කරන අතර එය පරීක්ෂා කළ යුතුය. තද මුත්රා සහිත තද අළු හෝ මැටි පාට මළපහට දිනෙන් දින සායනික ඇගයීමක් අවශ්ය වේ, මන්ද පිත ගලා යාම අඩු විය හැකිය.
පිත්ත නිසා කහ පැහැති මළපහ ඇතිවිය හැකිද?
Bile can contribute to yellow-green stool when intestinal transit is fast because its pigments have not been fully transformed into brown stercobilin. Normal bile production is about 500-1,000 mL daily, and bile itself is not a sign of disease when it reaches the bowel normally. The concern is not simply “too much bile”; it is persistent watery diarrhea from bile acids or too little bile reaching the intestine, which can produce pale stool. Dark urine, itch, jaundice, or a raised direct bilirubin level make a bile-flow problem more likely.
කහ පාචන ගැන කවදාටද මට කරදර වෙන්න ඕනෙ?
දින 7කට වඩා පවතී නම්, විජලනයට හේතු වේ නම්, අධි-අවදානම් සංචාරයකින් පසුව හෝ ප්රතිකාර නොකළ ජලය නිරාවරණය වීමෙන් පසුව, නැතහොත් 38.5°C ට වැඩි උණ, රුධිරය, දැඩි වේදනාව හෝ බර අඩු වීමක් සමඟ සිදුවන්නේ නම්, කහ පාචනය සඳහා කඩිනම් වෛද්ය උපදෙස් අවශ්ය වේ. පැය 8ක් පුරා මුත්රාශය අඩුවීම, කැපී පෙනෙන කරකැවිල්ල, පටලැවිල්ල, හෝ දියර රඳවා තබා ගැනීමේ නොහැකියාව ඇති වැඩිහිටියන් වහාම තක්සේරු කළ යුතුය. ළමුන් තුළ, උදාසීනතාවය, දුර්වල ලෙස පානය කිරීම, කඳුළු නොමැතිකම, හෝ අඩු තෙත් ඩයපර් මාරු කිරීම් කඩිනම් අනතුරු ඇඟවීමේ සලකුණු වේ. නිරාවරණය සහ රෝග ලක්ෂණ රටාව අනුව මළපහ PCR, සංස්කෘතිය, හෝ පරපෝෂිත පරීක්ෂණයක් සුදුසු විය හැකිය.
කහ පැහැති අසූචි වලින් අග්න්යාශයේ පිළිකාවක් අදහස් කරනවාද?
කහ පැහැති මළපහ පමණක් වීමෙන් අග්න්යාශ පිළිකාවක් අදහස් නොවන අතර ආහාර, වේගවත් ගමන් මාර්ගය, හෝ කෙටි ආන්ත්රික රෝගයකින් බොහෝ විට සිදුවිය හැක. අග්න්යාශ රෝග පිළිබඳව වෛද්යවරු පරික්ෂා කරන්නේ, පැහැදිලි හෝ මේද සහිත මළපහ නැවත ඇතිවන විට, එයට හේතුව නොදන්නා බර අඩු වීම, නිරන්තර ඉහළ උදරයේ හෝ පිටුපස වේදනාව, අලුත් දියවැඩියාව, සෙංගමාලය, හෝ 200 µg/g ට වඩා අඩු මළ එලෙස්ටේස් සමඟිනි. මෙම රෝග ලක්ෂණ සඳහා අග්න්යාශ එන්සයිම ඌණතාවය සහ පිත්තාශ අවහිර වීම ඇතුළු පිළිකා නොවන බොහෝ පැහැදිලි කිරීම් තිබේ. මළපහ වල වර්ණයෙන් ස්වයං-රෝග විනිශ්චය කිරීමට වඩා නිරන්තර අනතුරු ඇඟවීමේ රටාවන් තක්සේරු කළ යුතුය.
කාංසාව නිසා කහ පැහැති මළපහ ඇති විය හැකිද?
කාංසාව, විශේෂයෙන් කෝපාවිෂ්ට බඩවැල් සින්ඩ්රෝමය ඇති පුද්ගලයින් තුළ, ගට්-බ්රේන් සංඥා හරහා මලපහ පිටවීම වේගවත් කිරීමෙන් වක්රව කහ පැහැති මළපහ වලට දායක විය හැකිය. වේගවත් සංක්රමණය, පිත්තාශයේ වර්ණකයට දුඹුරු පැහැ ගැන්වීමට අඩු කාලයක් ඉතිරි වන බැවින්, මළපහ ලිහිල්, කහ-කොළ සහ හදිසි බවට පත් කළ හැකිය. 50 ට පසු රෝග ලක්ෂණ අලුත් වුවහොත්, නින්දෙන් අවදි වුවහොත්, රුධිරය, උණ, බර අඩු වීම, සුදුමැලි මළපහ, හෝ අසාමාන්ය අක්මා පරීක්ෂණ ඇතුළත් වුවහොත් කාංසාව හේතුවක් ලෙස උපකල්පනය නොකළ යුතුය. සති 2 ක කාලයක් පුරා රෝග ලක්ෂණ දිනපොතක්, ආතති කාලය ඇත්තෙන්ම බඩවැල් වෙනස්කම් සමඟ සම්බන්ධ දැයි බොහෝ විට පැහැදිලි කරයි.
පරස්පර කහ පාට අසූචි සඳහා ප්රයෝජනවත් වන පරීක්ෂණ මොනවාද?
කහ පැහැති අසූචි දිගටම පැවතීම සාමාන්යයෙන් bilirubin, ALP, GGT, ALT, AST, සහ albumin ඇතුළු අක්මා පරීක්ෂණ මගින්, රෝග ලක්ෂණ රටාව අනුව මුහුණත හෝ coeliac පරීක්ෂණ මගින් තක්සේරු කෙරේ. 200 µg/g ට අඩු Fecal elastase, අග්න්යාශයික එන්සයිම හිඟකමකට සහාය දක්වන අතර, මළපහ calprotectin, බඩවැල්වල දැවිල්ල හඳුනා ගැනීමට උපකාරී වේ. මළපහ PCR හෝ ප්රතිදේහජනක පරීක්ෂණ, සංචාරයෙන් පසු, ජලයට නිරාවරණය වීමෙන් පසු, හෝ දිගු කාලීන රෝග ලක්ෂණ ඇති වූ විට පාචනය සඳහා ප්රයෝජනවත් වේ. පිත්තාශයේ ගල් හෝ පිත්තාශයේ අවහිරතා පිළිබඳ කනස්සල්ලක් ඇති කරන සුදුමැලි මළපහ, තද මුත්රා, සෙංගමාලය, හෝ උදරයේ ඉහළ වේදනාවක් ඇති විට සාමාන්යයෙන් අල්ට්රා සවුන්ඩ් භාවිතා කරයි.
අදම AI බලයෙන් රුධිර පරීක්ෂණ විශ්ලේෂණය ලබාගන්න
තත්පර කිහිපයකින් ක්ෂණික හා නිවැරදි රසායනාගාර පරීක්ෂණ විශ්ලේෂණය සඳහා Kantesti විශ්වාස කරන ලොව පුරා මිලියන 2කට වැඩි පරිශීලකයන්ට එක්වන්න. ඔබගේ රුධිර පරීක්ෂණ ප්රතිඵල උඩුගත කර, තත්පර කිහිපයකින් 15,000+ ජෛව සලකුණු පිළිබඳ සවිස්තර අර්ථකථනය ලබාගන්න.
📚 යොමු කර ඇති පර්යේෂණ ප්රකාශන
ක්ලයින්, ටී., මිචෙල්, එස්., සහ වෙබර්, එච්. (2026). Kantesti LTD. (2026). Women's Health Guide: Ovulation, Menopause & Hormonal Symptoms. Figshare. DOI: 10.6084/m9.figshare.31830721. Kantesti AI වෛද්ය පර්යේෂණ.
ක්ලයින්, ටී., මිචෙල්, එස්., සහ වෙබර්, එච්. (2026). Kantesti LTD. (2026). Multilingual AI Assisted Clinical Decision Support for Early Hantavirus Triage: Design, Engineering Validation, and Real-World Deployment Across 50,000 Interpreted Blood Test Reports. Figshare. DOI: 10.6084/m9.figshare.32230290. Kantesti AI වෛද්ය පර්යේෂණ.
📖 බාහිර වෛද්ය යොමු
⚕️ වෛද්ය වියාචනය
මෙම ලිපිය අධ්යාපනික අරමුණු සඳහා පමණක් වන අතර වෛද්ය උපදෙස් ලෙස නොසැලකේ. රෝග නිદાન සහ ප්රතිකාර තීරණ සඳහා සෑම විටම සුදුසුකම් ලත් සෞඛ්ය සේවා සපයන්නෙකුගෙන් උපදෙස් ලබාගන්න.
E-E-A-T විශ්වාස සංඥා
අත්දැකීම්
වෛද්යවරයා විසින් මෙහෙයවන ලද රසායනාගාර අර්ථකථන ක්රියාවලි පිළිබඳ සමාලෝචනය.
ප්රවීණතාව
සායනික සන්දර්භය තුළ ජෛව සලකුණු (biomarkers) හැසිරෙන ආකාරය පිළිබඳ රසායනාගාර වෛද්ය විද්යා අවධානය.
අධිකාරීත්වය
ආචාර්ය තෝමස් ක්ලයින් විසින් ලියන ලද අතර ආචාර්ය සාරා මිචෙල් සහ මහාචාර්ය ආචාර්ය හෑන්ස් වෙබර් විසින් සමාලෝචනය කරන ලදී.
විශ්වසනීයත්වය
අනතුරු ඇඟවීම් අඩු කිරීමට පැහැදිලි පසුකැඳවීම් මාර්ග සහිත සාක්ෂි-පාදක අර්ථකථනය.