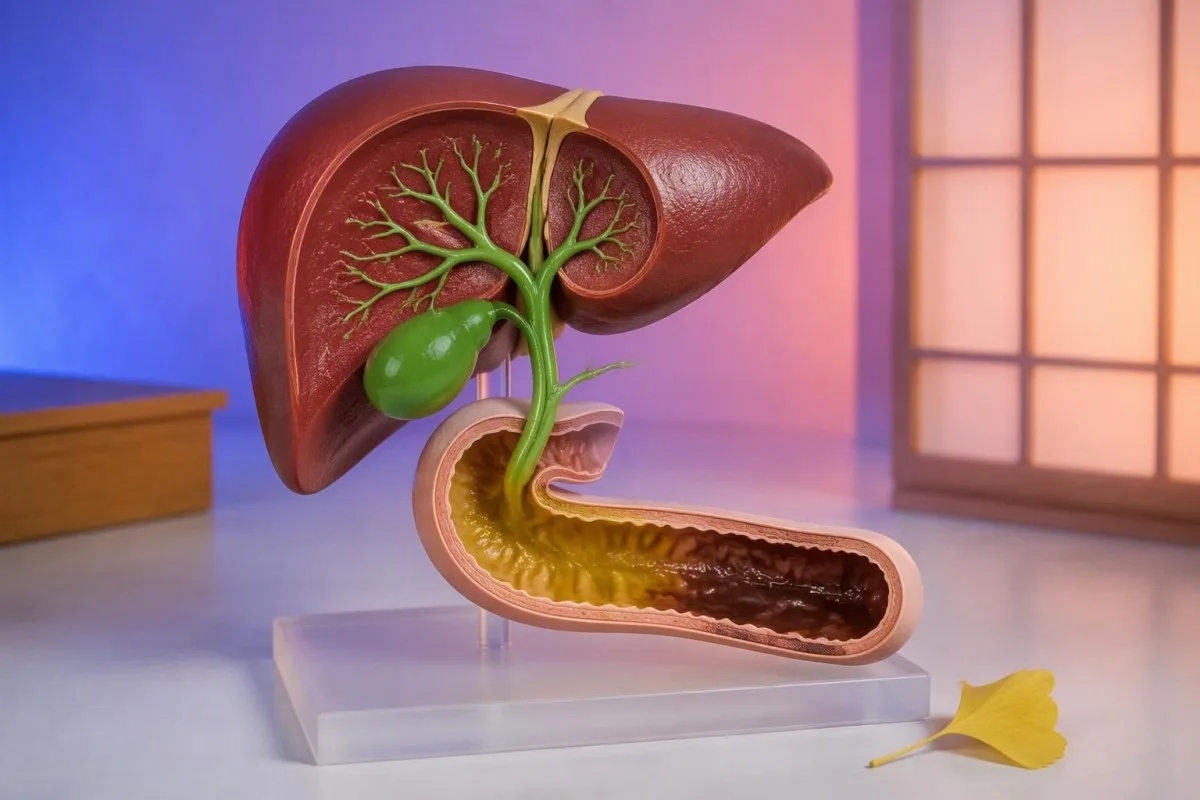
Ang dilaw nga pagdumi kasagaran usa ka hamubo nga kausaban sa pagkaon o dali nga pagbiyahe, apan ang pagpadayon nga tambok, itom nga ihi, kasakit, hilanat, o pagkawala sa timbang nagbag-o sa kalkulasyon. Ang sumbanan mas hinungdanon kaysa usa ka pagtan-aw sa kasilyas.


- Hamubo nga dilaw nga hugaw human sa pagkaon nga daghang tambok, turmeric, carrots, o sakit nga kalibanga kasagaran dili makadaot kung mawala sulod sa 48-72 ka oras.
- Bilious pigment normal nga naghimo sa hugaw nga brown; ang dali nga pagbiyahe mahimong magbilin niini nga dilaw-berde sa dili pa kini hingpit nga mabag-o sa mga bakterya sa tinai.
- Tambok, naglutaw nga hugaw nga lisud i-flush nagpaila sa sobrang tambok ug kinahanglan magpukaw sa pagrepaso alang sa pancreatic, apdo, o malabsorption sa gamay nga tinai.
- Maputla nga hugaw nga sama sa clay kauban ang itom nga ihi mahimong magpakita og pagkunhod sa apdo nga moabot sa tinai ug nagkinahanglan og pagtimbang-timbang sa klinika sa samang adlaw.
- Dilaw nga kalibang nga adunay hilanat, dehydration, pagkaladlad sa pagbiyahe, o mga simtomas nga molungtad og sobra sa 7 ka adlaw mahimong magkinahanglan og pagsulay sa hugaw.
- Mga pagsulay sa atay sama sa ALP, GGT, bilirubin, ALT, ug AST makatabang sa pag-ila sa mga pattern sa pagdagayday sa apdo gikan sa daghang hinungdan sa tinai.
- Dili tuyo nga pagkunhod sa timbang nga 5% o labaw pa sulod sa 6-12 ka bulan uban sa padayon nga pagbag-o sa hugaw nagkinahanglan og medikal nga pagrepaso.
- Mga bata ug mga tigulang dali nga ma-dehydrate; ang pagkunhod sa pag-ihi, katapulan, o ang kawalcoholic sa paghawid sa mga pluwido nagkinahanglan og dinalian nga pag-atiman.
Unsay kasagarang ipasabot sa dilaw nga hugaw sa mga hamtong
Ang dilaw nga hugaw kasagaran nagpasabot nga ang pagkaon mibalhin sa tinai nga mas paspas aron ang mga pigmento sa apdo dili hingpit nga mahimong brown, o nga ang bag-o nga pagkaon, suplemento, o sakit nga kalibang nagbag-o sa hitsura niini. Usa ka talagsaon nga dilaw nga pagbag-o sa tinai nga walay kasakit, hilanat, jaundice, o pagkawala sa timbang talagsa ra nga usa ka emerhensya.
Ang apdo magsugod isip usa ka dilaw-green nga pluwido, ug ang mga bakterya sa tinai nag-convert sa mga pigmento nga nakuha gikan sa bilirubin ngadto sa stercobilin, ang nag-unang brown nga pigmento sa hugaw. Sa diha nga ang pagbiyahe paspas, ilabi na sa Bristol type 6 o 7 nga hugaw, ang pag-convert dili kompleto ug ang resulta mahimong tan-awon nga mustard yellow, yellow-green, o tan. Ang Bristol stool chart mas mapuslanon kaysa kolor lamang tungod kay ang pagkamakanunayon nagsulti kanato kung ang katulin ba ang hinungdan sa pagbag-o.
Sa akong klinikal nga kasinatian, ang suga makahatag og dili kinahanglan nga kabalaka nga makapakurat sa kasubsob: ang bugnaw nga suga sa banyo nga LED naghimo sa normal nga light-brown nga hugaw nga daw dilaw. Si Dr. Thomas Klein nagrekomendar sa pagsusi sa sunod nga usa o duha ka pagbag-o sa tinai sa kahayag sa adlaw sa dili pa usbon ang pagkaon o mag-order og mga pagsulay, basta walay mga simtoma sa pasidaan. Ang pagbag-o sa kolor nga molungtad og ubos sa 72 ka oras ug nagsunod sa usa ka tin-aw nga hinungdan sa pagkaon kasagaran gi-obserbar, dili gitambalan.
Si Kantesti usa ka AI blood test analyzer nga nagbutang sa bilirubin, alkaline phosphatase, GGT, ALT, AST, albumin, ug mga marka sa panghubag sa usa ka follow-up nga konteksto. Kadtong mga pagsulay dili makadugmok sa kolor sa hugaw sa ilang kaugalingon, apan ang normal nga pattern sa atay naghimo sa klinikal nga makahuluganon nga pagbabag nga dili kaayo posible kaysa kini mahimong dilaw nga hugaw dugang jaundice.
Ang kolor usa ka timailhan, dili usa ka pagdayagnos
Ang usa ka kasilyas mahimong makatunaw ug makapabanaag sa kolor, mao nga ang mga kliniko mangutana bahin sa texture, kasubsob, pagka-lana, baho, kasakit, oras sa tambal, bag-o nga antibiotics, ug pagbiyahe. Ang usa ka litrato makatabang sa usa ka kliniko sa pagtandi sa usa ka balik-balik nga pattern, apan kini kinahanglan nga dili gayud maglangan sa dinalian nga pagtimbang-timbang alang sa luspad nga hugaw nga adunay ngitngit nga ihi o grabe nga kasakit sa tiyan.
Mga pagkaon, suplemento ug tambal nga makahatag og dilaw nga hugaw
Ang turmeric, mga pagkaon nga taas og carotenoid, mga tina sa pagkaon, ug ang kalit nga pagtaas sa tambok sa pagkaon mahimong makagama og dilaw o orange-yellow nga hugaw nga walay sakit. Ang praktikal nga pagsulay mao kung ang kolor molig-on human mohunong ang pagkaladlad ug ang pagkamakanunayon sa hugaw mobalik sa baseline.
Ang turmeric o curcumin supplements mahimong magkolor sa hugaw nga hayag nga dilaw sa dosis nga 500-2,000 mg kada adlaw, samtang ang mga carrot, kalabasa, kamote, ug mga dilaw nga tina sa pagkaon mahimong magbag-o sa kolor ngadto sa orange-yellow. Kining mga pigmento dili parehas sa jaundice; dili sila kasagarang hinungdan sa luspad nga hugaw, pangangati, ngitngit nga ihi, o pagtaas sa direktang bilirubin. Susiha ang mga label sa suplemento, labi na ang mga powder ug gummies nga adunay daghang mga additive sa kolor.
Ang usa ka tambok nga pagkaon sa restawran mahimong makagama og luag, mas gaan nga hugaw sa sunod nga buntag pinaagi lamang sa pag-aghat sa mas kusog nga gastrocolic motility. Kana lahi sa balik-balik nga steatorrhoea, nga lagmit tan-awon nga bulky, greasy, pale-yellow, molutaw balik-balik, ug magbilin ug oily film. Ang among giya sa wala matunaw nga pagkaon sa hugaw nagpatin-aw nganong ang makita nga mga piraso sa utanon lamang dili kasagaran ebidensya sa malabsorption.
Ang ubang mga tambal usab importante: ang orlistat kasagarang hinungdan sa oily yellow-orange leakage tungod kay kini nagbabag sa pagsuyop sa tambok, samtang ang mga antacid nga adunay magnesium ug metformin mahimong makapadali sa pagbiyahe. Ang bismuth mas sagad makapagngitngit sa hugaw, dili makapabindag niini. Ayaw ibagsak ang usa ka gireseta nga tambal sa kalit; pangutana sa usa ka pharmacist o preskriber kung ang oras ug dosis mohaum sa kausaban.
Ngano nga ang dali nga pagbiyahe moresulta sa dilaw nga kalibanga
Ang dilaw nga kalibang mahitabo kung ang hugaw moagi sa tinai nga paspas, nga magbilin og gamay ra nga oras sa pagsuyop pag-usab sa tubig ug pag-metabolize sa mga pigmento sa apdo. Ang viral gastroenteritis, ang pagpadali sa tinai nga may kalabotan sa kabalaka, ang dili pagtugot sa pagkaon, ug ang ubang mga tambal mao ang kasagarang mga hinungdan.
A person with abrupt watery diarrhea who is otherwise well often has a self-limited viral illness; yellow colour in that setting is usually a transit marker rather than excess bile production. Adults should aim for frequent oral rehydration, roughly 200-250 mL after each loose stool, adjusted for heart or kidney restrictions. Reduced urination for 8 hours, dizziness on standing, or confusion signals clinically meaningful dehydration.
Bile acids reaching the colon can stimulate water secretion and urgency, creating yellow-green loose stools. Bile acid diarrhea is especially worth considering after gallbladder removal, ileal disease, or ileal surgery, although symptoms overlap heavily with irritable bowel syndrome. The AGA guideline advises targeted testing for bile acid diarrhea in chronic watery diarrhea rather than assuming it is functional bowel disease (Smalley et al., 2019).
If loose yellow stool follows fasting, a large coffee, or a high-fructose drink, tracking the trigger for 2 weeks can be more revealing than a random single stool test. For a more detailed distinction between short-term and persistent symptoms, read our giya sa mga simtomas sa paghilis. Blood in stool, nocturnal diarrhea, or symptoms persisting beyond 4 weeks move this out of the self-care category.
Unsaon pag-usab sa apdo sa hugaw ang kolor gikan sa dilaw ngadto sa brown
Bile in stool is normal; reduced delivery of bile or unusually rapid movement through the bowel changes its expected brown colour. Yellow-green stool usually reflects pigment that has not been fully processed, whereas putty-coloured or grey-white stool raises concern for too little bile entering the gut.
The liver makes about 500-1,000 mL of bile daily, and the gallbladder concentrates and releases it after meals. Bilirubin enters bile after red-cell pigment is processed by the liver, then intestinal microbes convert it through urobilinogen-related compounds into brown stercobilin. This is why a true blockage often produces both pale stool and dark tea-coloured urine: conjugated bilirubin is redirected into urine.
A yellow stool is not automatically “too much bile.” That phrase gets repeated online, but clinicians usually mean rapid transit, bile acid-related diarrhea, or impaired fat digestion when they investigate. The combination of a pale stool, generalized itching, yellow eyes, and dark urine is more informative than stool colour by itself; see our overview of taas nga direct bilirubin.
Kantesti AI interprets liver-panel results as a pattern, not as isolated red flags. A raised ALP and GGT with direct bilirubin elevation is more compatible with cholestasis than an isolated mild ALT rise, while completely normal bilirubin and ALP make a major bile-duct blockage less likely. Reference intervals still vary by laboratory, so the report’s own range remains the starting point.
Kanus-a ang dilaw nga hugaw nagpaila sa problema sa gallbladder, atay o bile-duct
Yellow stool becomes more concerning when it is pale or clay-like and occurs with dark urine, jaundice, fever, itch, or right-upper abdominal pain. These features can indicate cholestasis, hepatitis, gallstone-related obstruction, or less commonly pancreatic obstruction.
Obstructive patterns are most urgent when pain is severe or fever develops. A stone obstructing the common bile duct may cause episodic upper abdominal pain, nausea, jaundice, and rising bilirubin; fever with jaundice and abdominal pain can indicate ascending cholangitis and needs emergency assessment. The cholecystitis blood test guide explains why normal early blood work cannot safely exclude a biliary problem when symptoms fit.
For adults, ALP above the laboratory upper limit plus elevated GGT supports a hepatobiliary source of ALP, although neither test locates a blockage. Total bilirubin above approximately 34 µmol/L (2 mg/dL) can make yellowing of the eye whites visible, but visible jaundice may appear earlier or later depending on skin tone and lighting. Ultrasound is often the first imaging test when obstruction is suspected.
Si Kantesti usa ka AI pagsabot sa resulta sa blood test platform used to identify liver-test combinations that merit clinical follow-up rather than to replace an examination or scan. As of September 30, 2026, our clinical rule remains straightforward: pale stool with dark urine should be assessed the same day, even if pain has eased. Early obstruction can fluctuate, which is the annoying part.
Tambok nga dilaw nga hugaw ug mga sumbanan sa malabsorption
Repeated greasy, floating, foul-smelling yellow stool can indicate fat malabsorption, also called steatorrhoea. Pancreatic enzyme deficiency, coeliac disease, bile-flow disorders, and small-bowel disease are leading explanations when this pattern persists.
Steatorrhoea is not just a stool that floats once; it is usually recurrent, bulky, difficult to flush, and may leave an oily ring. People can lose weight despite eating normally because unabsorbed fat carries calories away, and long-standing malabsorption may lower fat-soluble vitamins A, D, E, and K. A qualitative stool-fat screen can help, but a timed 72-hour fecal-fat collection remains a reference method in selected cases.
Pancreatic exocrine insufficiency becomes more plausible with upper abdominal symptoms, diabetes, chronic pancreatitis risk factors, or low fecal elastase. A fecal elastase value below 200 µg/g supports pancreatic insufficiency, while values below 100 µg/g are more strongly suggestive; watery samples can falsely lower the measurement by dilution. Our stool elastase explanation covers this often-missed pre-analytic trap.
Coeliac disease may cause loose pale-yellow stools, iron deficiency, folate deficiency, abdominal bloating, fatigue, or no obvious gastrointestinal symptoms at all. The 2023 ACG guideline recommends tissue transglutaminase IgA testing with total IgA while the person is eating gluten, because starting a gluten-free diet before testing can produce a falsely reassuring result (Rubio-Tapia et al., 2023).
Impeksyon, parasito ug dilaw nga hugaw nga may kalabotan sa pagbiyahe
Acute yellow diarrhea with cramps is often infectious, while persistent greasy diarrhea after untreated water exposure raises suspicion for Giardia and other parasites. Most short illnesses resolve, but duration, fever, travel history, and immune status determine whether testing is sensible.
Giardia often produces bloating, sulfurous belching, fatigue, and pale or greasy loose stools 1-2 weeks after exposure, though timing varies. Risk rises after drinking untreated surface water, daycare exposure, or close household contact; a multiplex stool PCR or antigen test can detect infection without relying on a single microscopy sample. Persistent symptoms deserve a test rather than repeated empiric antibiotics.
Invasive bacterial illness is more likely when diarrhea contains blood, fever exceeds 38.5°C, or there is significant abdominal tenderness. The ACG guideline on acute diarrheal infections recommends stool testing when symptoms are severe, prolonged, dysenteric, or linked to outbreak and travel circumstances (Riddle et al., 2016). Antibiotics can occasionally worsen particular infections, so the diagnosis matters.
Children with yellow watery stools need a lower threshold for assessment because dehydration can develop over hours rather than days. Track wet nappies or urine output, tears, alertness, and drinking—not merely bowel-movement count. Our stool culture guide explains why a positive organism is interpreted alongside symptoms, not treated automatically.
Mga pagsulay nga gigamit sa mga clinician alang sa makanunayon nga dilaw nga hugaw
Persistent yellow stool is assessed with history first, then targeted liver tests, coeliac blood tests, stool studies, and imaging when the pattern points toward bile, infection, or malabsorption. There is no single “yellow stool blood test.”
A useful first blood panel often includes full blood count, electrolytes, CRP, ALT, AST, ALP, GGT, bilirubin, albumin, and coeliac serology. Low albumin below 35 g/L can occur with significant intestinal protein loss, liver synthetic dysfunction, or inflammation, but it is not specific to malabsorption. If diarrhea is prolonged, potassium and bicarbonate are clinically relevant because bowel losses can disturb both.
Stool testing should answer a question: PCR or culture for an infectious syndrome, fecal calprotectin or lactoferrin for suspected intestinal inflammation, fecal elastase for possible pancreatic insufficiency, and fecal fat when steatorrhoea is convincing. Calprotectin is best viewed as an inflammation signal rather than a diagnosis; our comparison of calprotectin and lactoferrin explains the trade-offs.
Si Kantesti usa ka AI-powered blood test analysis tool that can organize relevant blood-test trends, including bilirubin and ALP changes over time, in about 60 seconds after a report upload. A normal blood panel cannot rule out Giardia, bile acid diarrhea, or mild coeliac disease, so our output should support a clinician-led next step rather than falsely close the investigation.
Pagbasa sa mga pagsulay sa atay kauban ang kolor sa hugaw
A cholestatic liver-test pattern usually means ALP and GGT rise more prominently than ALT and AST, often with direct bilirubin elevation. Stool colour adds useful context, but blood results and symptoms determine urgency.
ALT and AST reflect hepatocyte injury more than bile flow, while ALP can arise from liver or bone. GGT helps clinicians decide whether a raised ALP is likely hepatobiliary, though alcohol, metabolic liver disease, and certain medicines can raise GGT without obstruction. A GGT of 90 IU/L with normal bilirubin means something very different from GGT 90 IU/L plus jaundice and pale stool.
The R-ratio can assist specialists: divide ALT as a multiple of its upper limit by ALP as a multiple of its upper limit. A ratio above 5 suggests a hepatocellular pattern, below 2 suggests cholestatic injury, and 2-5 is mixed; it is a triage tool, not a diagnosis. Patients can explore the component tests in our giya sa pagsulay sa dugo sa cholestasis.
Dr. Thomas Klein has seen people worry about a marginally high ALP that later proves to be bone-related, particularly during fracture healing or vitamin D deficiency. That is why clinicians may add ALP isoenzymes, vitamin D, calcium, phosphate, or imaging rather than assuming a liver diagnosis. The stool story can make that distinction more or less urgent.
Dilaw nga kalibanga human sa pagtangtang sa gallbladder
Diarrhea after gallbladder removal can occur because bile flows continuously into the intestine rather than being released in concentrated pulses with meals. It often begins soon after surgery, is worse after fatty meals, and can be yellow-green because transit is accelerated.
Not everyone develops post-cholecystectomy diarrhea, and it is not automatically lifelong. Smaller lower-fat meals for 2-4 weeks can reduce urgency while the bowel adapts, but severe restriction is rarely necessary long term. Persistent watery stools more than 4 weeks after surgery should prompt discussion of bile acid diarrhea and other causes, especially if symptoms wake a person at night.
Where available, SeHCAT retention testing can support bile acid malabsorption; alternatives include serum 7α-hydroxy-4-cholesten-3-one or carefully monitored treatment trials. Bile-acid sequestrants may help but can interfere with absorption of thyroid medication, warfarin, and fat-soluble vitamins, so dose spacing is not a minor detail. A pharmacist can provide the exact schedule.
This pattern differs from a new episode of severe pain, fever, jaundice, or pale stool after surgery, which needs urgent assessment for a retained stone or another complication. Our overview of the pagsulay sa dugo sa bile acids also explains why generalized itching shifts attention back toward cholestasis rather than simple rapid transit.
Dilaw nga hugaw sa mga bata, pagmabdos ug mga tigulang nga hamtong
Yellow stools are common in breastfed infants and are usually normal, while persistent pale stools in any child require prompt paediatric evaluation. Pregnancy and older age also change the threshold for acting because dehydration and bile disorders carry different risks.
Breastfed infant stool is frequently mustard-yellow, loose, and seedy; that is expected when an infant is feeding and growing normally. Acholic stool, meaning distinctly white, grey, or putty coloured, is different and should be assessed urgently because biliary atresia and other neonatal cholestatic conditions are time-sensitive. Parents are right to trust a repeated colour pattern rather than one diaper under odd lighting.
During pregnancy, new pale stool, dark urine, itching of the palms or soles, or jaundice should lead to same-day maternity assessment. Serum bile acids can rise in intrahepatic cholestasis of pregnancy, but the test should be interpreted with liver results, gestational age, symptoms, and local obstetric guidance. The itching blood-test guide gives a practical testing framework.
In older adults, a new persistent stool change deserves attention sooner because medication effects, pancreatic disease, malignancy, and infection are more common, while thirst may be blunted. A loss of 5% body weight in 6-12 months is clinically significant at any age. Frailty, kidney disease, or diuretic use lowers the margin for dehydration.
Unsay buhaton sa unang 72 ka oras
For a single yellow stool or mild yellow diarrhea without red flags, hydration, a brief food-and-symptom record, and observation for 48-72 hours are reasonable. Avoid aggressive “cleanses,” fasting, or self-started antibiotics, which often muddy the clinical picture.
Write down the timing, Bristol stool type, meals, supplements, medicine changes, travel, fever, pain, urine colour, and number of bowel movements. This is more clinically useful than describing stool as “weird.” If you had a high-dose turmeric product, a fatty meal, or a stomach bug and symptoms settle within 3 days, no testing may be required.
Use oral rehydration solution rather than only plain water if diarrhea is frequent; standard solutions contain glucose and sodium in proportions that improve intestinal water absorption. Adults without fluid restrictions can use small repeated sips, especially after each loose stool. Avoid sports drinks as the sole replacement when diarrhea is substantial because their sodium content is often lower and sugar content higher.
If symptoms persist, our blood test for diarrhea guide can help you prepare questions for a clinician. Kantesti AI can also place liver and electrolyte results in chronological context, but an app cannot assess abdominal tenderness, hydration status, or jaundice through a screen. Those limitations matter.
Kanus-a ang dilaw nga hugaw nagkinahanglan og medikal nga pagrepaso o dinalian nga pag-atiman
Seek urgent care for pale stool with dark urine or jaundice, severe or worsening abdominal pain, fever with jaundice, fainting, confusion, or signs of major dehydration. Arrange routine medical review for yellow stool lasting more than 1-2 weeks, recurring greasy stool, weight loss, or persistent diarrhea.
Emergency assessment is appropriate for inability to keep fluids down, black tarry stool, visible blood, severe weakness, a rigid abdomen, or jaundice with fever. These combinations carry more diagnostic weight than yellow colour alone because they may indicate bleeding, significant infection, obstruction, or systemic illness. If in doubt, err on the side of being seen—particularly for children, pregnancy, and immunosuppression.
A non-urgent appointment is still warranted if stool changes persist beyond 7 days with diarrhea or beyond 2 weeks without diarrhea, even when pain is absent. Bring medication and supplement containers, a 7-day symptom log, and prior laboratory reports. The article on blood in stool urgency helps distinguish red and black warning colours from benign food effects.
Kantesti's medical review standards are described by our Lupon sa Medikal nga Magtatambag, ug ang among pamaagi sa pagpamatuod sa klinikal explains where automated interpretation stops. Kantesti is an AI lab test interpretation service designed to surface follow-up patterns; it does not provide emergency triage or replace a clinician examining you.
Mga pangutana nga makapahimo sa usa ka dilaw nga appointment sa hugaw nga mas mapuslanon
The most useful appointment questions ask whether the stool pattern fits rapid transit, malabsorption, infection, or impaired bile flow and which test would change management. A focused history can prevent both under-testing and broad low-yield testing.
Ask: “Does my symptom pattern justify liver tests, coeliac testing, stool PCR, fecal calprotectin, fecal elastase, or ultrasound?” The answer should be tied to your duration, weight change, pain location, travel, surgery, and stool texture. A blanket panel is not always better; for example, stool PCR does not diagnose pancreatic enzyme deficiency, and liver tests do not rule out Giardia.
Ask for the actual results and the laboratory reference ranges, not simply “normal” or “abnormal.” A bilirubin trend from 9 to 28 µmol/L may be meaningful if it is paired with new dark urine, while an isolated stable bilirubin of 24 µmol/L can have a different explanation. Our overview sa liver panel outlines what each component can and cannot tell you.
Kantesti AI was built by Kantesti Ltd to help people organize laboratory reports across visits, with privacy-focused handling and multilingual interpretation in 75+ languages. For the method behind that work, see our giya sa teknolohiya sa AI. A good next step is specific: test, monitor, image, treat, or safely observe—not merely “repeat everything.”
Konklusyon: itugma ang kolor sa tibuok nga sumbanan
Most yellow stool causes are temporary dietary or fast-transit effects, but pale stool, greasy recurrence, dark urine, jaundice, fever, pain, or weight loss need medical evaluation. The combination of colour, texture, duration, and associated symptoms is far more reliable than colour alone.
A brief yellow stool after turmeric, a rich meal, or a 24-hour diarrheal illness can usually be watched for 48-72 hours. Repeated oily floating stool points toward fat malabsorption, while clay-coloured stool with dark urine points toward reduced bile flow. That distinction is clinically useful because the investigations—and the urgency—are different.
Keep the evidence in proportion. Most patients I see with a short-lived colour change do not have serious liver or pancreatic disease, yet a small number have warning combinations that should not be dismissed as “just diet.” The fecal fat test guide is a sensible next read when oiliness and floating are the recurring features.
Si Kantesti usa ka plataporma sa paghubad sa AI biomarker that helps connect laboratory patterns to informed questions for your clinician. It is not a substitute for care when red flags are present; severe pain, jaundice, fever, dehydration, or pale stool with dark urine should always be assessed in person.
Kanunay nga Gipangutana nga mga Pangutana
Unsay gipasabut sa dalag nga tai sa mga hamtong?
Ang dilaw nga tae sa mga hamtong kasagaran nagpakita sa paspas nga paglihok sa tinai, usa ka bag-o nga pigment sa pagkaon, usa ka pagkaon nga taas og tambok, o usa ka hamubo nga sakit nga kalibanga. Kung kini humok o matubigon ug mohusay sulod sa 48-72 ka oras nga walay kasakit, hilanat, itom nga ihi, jaundice, o pagkawala sa timbang, kini kasagaran dili emerhensya. Ang balik-balik nga tambok, naglutaw, lisud-banlawan nga dilaw nga tae nagsugyot sa fat malabsorption ug kinahanglan nga susihon. Ang luspad nga abo o clay nga tae nga adunay itom nga ihi nagkinahanglan ug same-day clinical assessment tungod kay ang agos sa apdo mahimong mamenosan.
Makapahinabo ba ang apdo ug dalag nga tai?
Bile can contribute to yellow-green stool when intestinal transit is fast because its pigments have not been fully transformed into brown stercobilin. Normal bile production is about 500-1,000 mL daily, and bile itself is not a sign of disease when it reaches the bowel normally. The concern is not simply “too much bile”; it is persistent watery diarrhea from bile acids or too little bile reaching the intestine, which can produce pale stool. Dark urine, itch, jaundice, or a raised direct bilirubin level make a bile-flow problem more likely.
Kanus-a ko angay mabalaka bahin sa dalag nga kalibanga?
Ang dalag nga pagtatae nagkinahanglan og dinalian nga tambag medikal kon molungtad kini og kapin sa 7 ka adlaw, hinungdan sa dehydration, mosunod sa taas og risgo nga pagbiyahe o pagkaladlad sa dili matambalan nga tubig, o mahitabo uban ang hilanat nga labaw sa 38.5°C, dugo, grabeng kasakit, o pagkunhod sa timbang. Ang mga hamtong nga adunay pagkunhod sa pag-ihi sulod sa 8 ka oras, grabeng pagkalipong, kalibog, o kawalay katakus sa pagpugong sa mga pluwido kinahanglan mangayo og dinalian nga pagsusi. Sa mga bata, ang pagkataspilok, dili maayong pag-inom, walay luha, o diyutay nga basa nga lampin mga dinalian nga mga timailhan sa pasidaan. Ang stool PCR, culture, o parasite test mahimong angay depende sa pagkaladlad ug sumbanan sa sintomas.
Ang dilaw nga bangkito nagpasabot ba sa kanser sa pancreas?
Ang dalag nga tai sa iyang kaugalingon dili nagpasabot ug kanser sa pancreas ug mas kanunay nga gipahinabo sa pagkaon, paspas nga paghilis, o usa ka mubo nga sakit sa gastrointestinal. Ang mga clinician nagsusi sa sakit sa pancreas kung ang maputla o mantikaon nga mga tai magbalik-balik uban ang dili maipatin-aw nga pagkawala sa timbang, makanunayon nga sakit sa ibabaw nga tiyan o likod, bag-ong diabetes, jaundice, o ubos nga fecal elastase nga ubos sa 200 µg/g. Kini nga mga sintomas adunay daghang mga pagpatin-aw nga dili kanser, lakip ang pancreatic enzyme insufficiency ug bile obstruction. Ang makanunayon nga mga sumbanan sa pasidaan kinahanglan nga susihon kaysa sa pag-ila sa kaugalingon gikan sa kolor sa tai.
Makapahinabog ba ang kabalaka ug dalag nga tae?
Ang kabalaka mahimong makatampo sa dalag nga bangkito sa dili direkta pinaagi sa pagpadali sa pagbiyahe sa tinai pinaagi sa gut-brain signaling, ilabi na sa mga tawo nga adunay irritable bowel syndrome. Ang mas paspas nga pagbiyahe mahimong magbilin sa bangkito nga luag, dalag-berde, ug dinalian tungod kay ang bile pigment adunay gamay nga panahon aron mahimong brown. Ang kabalaka kinahanglan dili isipon nga hinungdan kung ang mga sintomas bag-o pagkahuman sa edad nga 50, makapukaw sa usa gikan sa pagkatulog, adunay dugo, hilanat, pagkawala sa timbang, maputla nga bangkito, o abnormal nga mga pagsulay sa atay. Ang diary sa sintomas sulod sa 2 ka semana kasagaran maklaro kung ang oras sa stress tinuod nga nagkonektar sa mga pagbag-o sa tinai.
Unsa nga mga pagsulay ang mapuslanon alang sa padayon nga dalag nga lingkuranan?
Ang padayon nga dalag nga tai kasagaran gisusi gamit ang mga pagsulay sa atay lakip ang bilirubin, ALP, GGT, ALT, AST, ug albumin, dugangan pa ang gipunting nga pagsulay sa tai o coeliac base sa sumbanan sa sintomas. Ang fecal elastase ubos sa 200 µg/g nagpalig-on sa posibleng kakulangan sa pancreatic enzyme, samtang ang fecal calprotectin makatabang sa pag-ila sa intestinal inflammation. Ang stool PCR o antigen testing mapuslanon alang sa kalibanga human sa pagbiyahe, pagkaladlad sa tubig, o dugay nga mga sintomas. Ang ultrasound kasagarang gigamit kung ang luspad nga tai, ngitngit nga ihi, jaundice, o sakit sa taas nga tiyan nagpatunghag kabalaka bahin sa gallstones o pagbabag sa apdo.
Karon na ang AI-Powered Blood Test Analysis
Apil sa kapin sa 2 milyon nga mga user sa tibuok kalibutan nga nagsalig sa Kantesti para sa dayon ug tukma nga pag-analisa sa lab test. I-upload ang imong resulta sa blood test ug makadawat og komprehensibong pagsabot sa 15,000+ nga mga biomarker sulod sa mga segundo.
📚 Mga Napangalan nga Research Publications
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). Women's Health Guide: Ovulation, Menopause & Hormonal Symptoms. Figshare. DOI: 10.6084/m9.figshare.31830721. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). Multilingual AI Assisted Clinical Decision Support for Early Hantavirus Triage: Design, Engineering Validation, and Real-World Deployment Across 50,000 Interpreted Blood Test Reports. Figshare. DOI: 10.6084/m9.figshare.32230290. Kantesti AI Medical Research.
📖 Mga Panlabas nga Sanggunian sa Medisina
⚕️ Pagpasabot sa Medikal
Kini nga artikulo para sa katuyoan sa edukasyon ra ug dili kini mosangpot sa medikal nga tambag. Kanunay mokonsulta sa usa ka kwalipikado nga healthcare provider alang sa mga desisyon sa diagnosis ug pagtambal.
Mga E-E-A-T Trust Signals
Kasinatian
Pagsusi sa klinika nga gipangulohan sa doktor sa mga workflow sa interpretasyon sa lab.
Kahanas
Pokus sa medisina sa laboratoryo kung giunsa paglihok ang mga biomarker sa konteksto sa klinika.
Pagka-awtorisado
Gisulat ni Dr. Thomas Klein ug gisusi ni Dr. Sarah Mitchell ug Prof. Dr. Hans Weber.
Kasaligan
Interpretasyon nga base sa ebidensya, nga adunay klaro nga mga agianan sa sunod nga buhat aron makunhuran ang kabalaka.