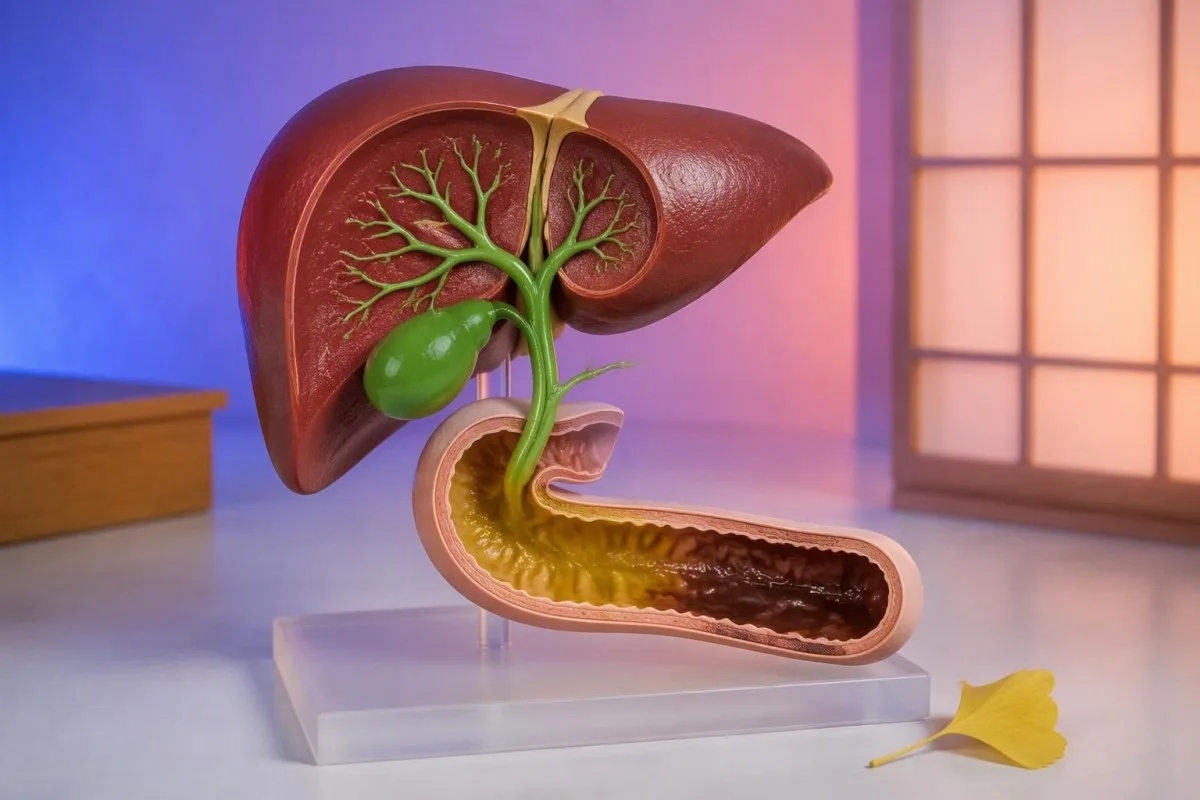
Դեղին կղանքը հաճախ ժամանակավոր է, կապված սննդի կամ արագ անցման հետ, սակայն յուղոտ հետքերը, մուգ մեզը, ցավը, տենդը կամ քաշի կորուստը փոխում են իրավիճակը։ Ավելի կարևոր է զուգարանակոնքի մեջ դիտարկված պատկերը, քան մեկ հայացքը։.


- Կարճատև դեղին կղանք բարձր ճարպային սնունդից, քրքումից, գազարից կամ լուծային հիվանդությունից հետո սովորաբար անվնաս է, երբ այն անցնում է 48-72 ժամվա ընթացքում։.
- Լեղային պիգմենտ սովորաբար կղանքը դարձնում է շագանակագույն; արագ անցումը կարող է թողնել այն դեղնականաչ մինչև աղիքային բակտերիաները լիովին փոխեն այն։.
- Յուղոտ, լողացող կղանք որը դժվար է լվացվում, ցույց է տալիս ավելորդ ճարպ և պետք է հանգեցնի ենթաստամոքսային, լեղային կամ բարակ աղիքային մալաբսորբցիայի վերանայման։.
- Բաց, կավագույն կղանք՝ մուգ մեզի հետ կարող է ցույց տալ, որ աղիք է հասնում քիչ լեղու քանակ և պահանջում է նույն օրվա կլինիկական գնահատում։.
- Դեղին փորլուծություն տենդով, ջրազրկումով, ճանապարհորդության հետ կապված ազդեցությամբ կամ 7 օրից ավելի տևող ախտանիշներով կարիք կարող է լինել աղիքային հետազոտություն։.
- Լյարդի թեստեր ինչպես ALP, GGT, բիլիռուբին, ALT և AST, օգնում են տարբերակել լեղու հոսքի ձևերը աղիքային պատճառների մեծ մասից։.
- Անկանխամտածված քաշի կորուստ 5%-ի 6-12 ամսվա ընթացքում 51%-ով կամ ավելի շատ, persistent stool change-ի հետ միասին, բժշկական վերանայում է պահանջում։.
- Երեխաները և տարեցները կարող են արագորեն ջրազրկվել; միզարձակության նվազում, լethargy կամ հեղուկ չպահպանելը շտապ օգնության կարիք ունի։.
Ինչ է սովորաբար նշանակում դեղին կղանք մեծահասակների մոտ
Դեղին կղանքը հաճախ նշանակում է, որ սնունդը չափից շատ արագ է անցել աղիքներով, որպեսզի լեղու պիգմենտները լիովին գունափոխվեն, կամ որ վերջին սնունդը, հավելումը կամ փորլուծության հիվանդությունը փոխել է դրա տեսքը։. Միայնակ դեղին աղիքի շարժումը առանց ցավի, տենդի, դեղնախտի կամ քաշի կորստի հազվադեպ է արտակարգ իրավիճակ։.
Լեղու սկիզբը դեղնականաչ հեղուկ է, իսկ աղիքային բակտերիաները բիլիռուբինից ստացված պիգմենտները փոխակերպում են ստերկոբիլինի, որը կղանքի հիմնական դարչնագույն պիգմենտն է։ Երբ անցումը արագ է, հատկապես Բրիստոլի 6-րդ կամ 7-րդ տիպի կղանքի դեպքում, այդ փոխակերպումն անավարտ է, և արդյունքը կարող է լինել մանուշակագույն դեղին, դեղնականաչ կամ բաց շագանակագույն։ Bristol-ի կղանքի աղյուսակ ավելի օգտակար է, քան միայն գույնը, քանի որ կոնսիստենցիան մեզ ասում է, արդյոք արագությունն է փոփոխության պատճառը։.
Իմ կլինիկական փորձում լուսավորությունը զարմանալիորեն հաճախ է անհիմն ահ բերում. սառը LED լոգարանի լուսավորությունը նորմալ բաց շագանակագույն կղանքը դեղին է դարձնում։ Դոկտոր Թոմաս Քլայնը խորհուրդ է տալիս ստուգել հաջորդ մեկ-երկու աղիքի շարժումները ցերեկային լույսի ներքո՝ նախքան դիետան փոխելը կամ թեստեր պատվիրելը, եթե չկան նախազգուշացնող ախտանիշներ։ Գույնի փոփոխությունը, որը տևում է 72 ժամից պակաս և հստակ դիետիկ պատճառ ունի, սովորաբար դիտարկվում է, ոչ թե բուժվում։.
Կանտեստին մի է AI արյան անալիզատոր որը բիլիռուբինը, ալկալային ֆոսֆատազան, GGT-ն, ALT-ն, AST-ն, ալբումինը և բորբոքման մարկերները մեկ հետագա հսկողության կոնտեքստում է դնում։ Այս թեստերը ինքնին կղանքի գույնը չեն ախտորոշում, սակայն լյարդի նորմալ պատկերը կլինիկապես նշանակալի խցանումը շատ ավելի քիչ հավանական է դարձնում, քան դեղին կղանքի և դեղնախտի դեպքում կլիներ։.
Գույնը հուշում է, ոչ թե ախտորոշում
Թութակային ամանը կարող է նոսրացնել և արտացոլել գույնը, ուստի կլինիցիստները հարցնում են հյուսվածքի, հաճախականության, յուղայնության, հոտի, ցավի, դեղորայքի ժամանակացույցի, վերջին հակաբիոտիկների և ճանապարհորդության մասին։ Լուսանկարը կարող է օգնել կլինիցիստին համեմատել կրկնվող ձևը, բարձորեն այն չպետք է ուշացնի շտապ գնահատումը բաց կղանքի համար մուգ մեզի կամ ուժեղ որովայնի ցավի դեպքում։.
Սնունդ, հավելումներ և դեղամիջոցներ, որոնք կարող են դեղին կղանք առաջացնել
Բողկ, բարձր կարոտինոիդներով սնունդ, սննդային ներկանյութեր և դիետիկ ճարպի հանկարծակի աճը կարող են առաջացնել դեղին կամ նարնջադեղին կղանք առանց հիվանդության։. Պրակտիկ թեստը այն է, թե արդյոք գույնը հանգստանում է ազդեցության դադարեցումից հետո, և կղանքի կոնսիստենցիան վերադառնում է իր սկզբնական վիճակին։.
Բողկ կամ քրքումի հավելումները կարող են դեղին ներկել կղանքը 500-2000 մգ օրական չափաբաժիններով, մինչդեռ գազարը, դդմի, քաղցր կարտոֆիլը և դեղին սննդային ներկերը կարող են գույնը տեղափոխել նարնջադեղինի։ Այս պիգմենտները չեն նույնանում դեղնախտի հետ. նրանք սովորաբար չեն առաջացնում բաց կղանք, քոր, մուգ մեզ կամ ուղղակի բիլիռուբինի բարձրացում։ Վերանայեք հավելումների պիտակները, հատկապես փոշիները և գումիները՝ տարբեր գունային հավելումներով։.
Ճաշարանում ճարպային ուտեստը կարող է հաջորդ առավոտյան լուծ, ավելի բաց կղանք առաջացնել՝ պարզապես ուժեղ գաստրոկոլիկ շարժունակություն խթանելով։ Սա տարբերվում է կրկնվող ստեատորեայից, որը հակված է լինել ծավալուն, յուղոտ, բաց դեղին, անընդհատ լողալ և յուղոտ հետք թողնել։ Մեր ուղեցույցը չմարսված սնունդը կղանքում բացատրում է, թե ինչու կղանքում տեսանելի բուսական բեկորները միայնակ սովորաբար չեն մալաբսորբցիայի ապացույց։.
Որոշ դեղորայք նույնպես կարևոր են. օրլիստատը սովորաբար առաջացնում է յուղոտ դեղնանարնջագույն արտահոսք, քանի որ այն արգելափակում է ճարպի ներծծումը, մինչդեռ մագնեզիում պարունակող անտացիդները և մետֆորմինը կարող են արագացնել անցումը։ Բիսմուտը ավելի հաճախ է մուգացնում կղանքը, ոչ թե դեղնացնում։ Մի դադարեցրեք դեղատոմսով նշված դեղը հանկարծակի. դիմեք դեղագետին կամ նշանակողին, արդյոք ժամանակացույցը և չափաբաժինը համապատասխանում են փոփոխությանը։.
Ինչու արագ անցումը առաջացնում է դեղին լուծ
Դեղին փորլուծությունն առաջանում է, երբ կղանքը արագորեն անցնում է աղիքով, թողնելով շատ քիչ ժամանակ ջուրը նորից ներծծելու և լեղու պիգմենտները մարսելու համար։. Վիրուսային գաստրոէնտերիտը, անհանգստությամբ պայմանավորված աղիքների արագացումը, սննդի անհանդուրժողականությունը և որոշ դեղորայքներ սովորական պատճառներ են։.
A person with abrupt watery diarrhea who is otherwise well often has a self-limited viral illness; yellow colour in that setting is usually a transit marker rather than excess bile production. Adults should aim for frequent oral rehydration, roughly 200-250 mL after each loose stool, adjusted for heart or kidney restrictions. Reduced urination for 8 hours, dizziness on standing, or confusion signals clinically meaningful dehydration.
Bile acids reaching the colon can stimulate water secretion and urgency, creating yellow-green loose stools. Bile acid diarrhea is especially worth considering after gallbladder removal, ileal disease, or ileal surgery, although symptoms overlap heavily with irritable bowel syndrome. The AGA guideline advises targeted testing for bile acid diarrhea in chronic watery diarrhea rather than assuming it is functional bowel disease (Smalley et al., 2019).
If loose yellow stool follows fasting, a large coffee, or a high-fructose drink, tracking the trigger for 2 weeks can be more revealing than a random single stool test. For a more detailed distinction between short-term and persistent symptoms, read our մարսողական ախտանշանների ուղեցույց. Blood in stool, nocturnal diarrhea, or symptoms persisting beyond 4 weeks move this out of the self-care category.
Ինչպես լեղու ազդեցությունը փոխում է կղանքի գույնը դեղինից դեպի շագանակագույն
Bile in stool is normal; reduced delivery of bile or unusually rapid movement through the bowel changes its expected brown colour. Yellow-green stool usually reflects pigment that has not been fully processed, whereas putty-coloured or grey-white stool raises concern for too little bile entering the gut.
The liver makes about 500-1,000 mL of bile daily, and the gallbladder concentrates and releases it after meals. Bilirubin enters bile after red-cell pigment is processed by the liver, then intestinal microbes convert it through urobilinogen-related compounds into brown stercobilin. This is why a true blockage often produces both pale stool and dark tea-coloured urine: conjugated bilirubin is redirected into urine.
A yellow stool is not automatically “too much bile.” That phrase gets repeated online, but clinicians usually mean rapid transit, bile acid-related diarrhea, or impaired fat digestion when they investigate. The combination of a pale stool, generalized itching, yellow eyes, and dark urine is more informative than stool colour by itself; see our overview of )): )).
Kantesti AI interprets liver-panel results as a pattern, not as isolated red flags. A raised ALP and GGT with direct bilirubin elevation is more compatible with cholestasis than an isolated mild ALT rise, while completely normal bilirubin and ALP make a major bile-duct blockage less likely. Reference intervals still vary by laboratory, so the report’s own range remains the starting point.
Երբ դեղին կղանքը մատնանշում է լեղապարկի, լյարդի կամ լեղուղիների խնդիր
Yellow stool becomes more concerning when it is pale or clay-like and occurs with dark urine, jaundice, fever, itch, or right-upper abdominal pain. These features can indicate cholestasis, hepatitis, gallstone-related obstruction, or less commonly pancreatic obstruction.
Obstructive patterns are most urgent when pain is severe or fever develops. A stone obstructing the common bile duct may cause episodic upper abdominal pain, nausea, jaundice, and rising bilirubin; fever with jaundice and abdominal pain can indicate ascending cholangitis and needs emergency assessment. The cholecystitis blood test guide explains why normal early blood work cannot safely exclude a biliary problem when symptoms fit.
For adults, ALP above the laboratory upper limit plus elevated GGT supports a hepatobiliary source of ALP, although neither test locates a blockage. Total bilirubin above approximately 34 µmol/L (2 mg/dL) can make yellowing of the eye whites visible, but visible jaundice may appear earlier or later depending on skin tone and lighting. Ultrasound is often the first imaging test when obstruction is suspected.
Կանտեստին մի է AI արյան անալիզի մեկնաբանություն հարթակ used to identify liver-test combinations that merit clinical follow-up rather than to replace an examination or scan. As of September 30, 2026, our clinical rule remains straightforward: pale stool with dark urine should be assessed the same day, even if pain has eased. Early obstruction can fluctuate, which is the annoying part.
Յուղոտ դեղին կղանք և մալաբսորբցիայի պատկերներ
Repeated greasy, floating, foul-smelling yellow stool can indicate fat malabsorption, also called steatorrhoea. Pancreatic enzyme deficiency, coeliac disease, bile-flow disorders, and small-bowel disease are leading explanations when this pattern persists.
Steatorrhoea is not just a stool that floats once; it is usually recurrent, bulky, difficult to flush, and may leave an oily ring. People can lose weight despite eating normally because unabsorbed fat carries calories away, and long-standing malabsorption may lower fat-soluble vitamins A, D, E, and K. A qualitative stool-fat screen can help, but a timed 72-hour fecal-fat collection remains a reference method in selected cases.
Pancreatic exocrine insufficiency becomes more plausible with upper abdominal symptoms, diabetes, chronic pancreatitis risk factors, or low fecal elastase. A fecal elastase value below 200 µg/g supports pancreatic insufficiency, while values below 100 µg/g are more strongly suggestive; watery samples can falsely lower the measurement by dilution. Our stool elastase explanation covers this often-missed pre-analytic trap.
Coeliac disease may cause loose pale-yellow stools, iron deficiency, folate deficiency, abdominal bloating, fatigue, or no obvious gastrointestinal symptoms at all. The 2023 ACG guideline recommends tissue transglutaminase IgA testing with total IgA while the person is eating gluten, because starting a gluten-free diet before testing can produce a falsely reassuring result (Rubio-Tapia et al., 2023).
Վարակիչ, մակաբուծական և ճանապարհորդության հետ կապված դեղին կղանք
Acute yellow diarrhea with cramps is often infectious, while persistent greasy diarrhea after untreated water exposure raises suspicion for Giardia and other parasites. Most short illnesses resolve, but duration, fever, travel history, and immune status determine whether testing is sensible.
Giardia often produces bloating, sulfurous belching, fatigue, and pale or greasy loose stools 1-2 weeks after exposure, though timing varies. Risk rises after drinking untreated surface water, daycare exposure, or close household contact; a multiplex stool PCR or antigen test can detect infection without relying on a single microscopy sample. Persistent symptoms deserve a test rather than repeated empiric antibiotics.
Invasive bacterial illness is more likely when diarrhea contains blood, fever exceeds 38.5°C, or there is significant abdominal tenderness. The ACG guideline on acute diarrheal infections recommends stool testing when symptoms are severe, prolonged, dysenteric, or linked to outbreak and travel circumstances (Riddle et al., 2016). Antibiotics can occasionally worsen particular infections, so the diagnosis matters.
Children with yellow watery stools need a lower threshold for assessment because dehydration can develop over hours rather than days. Track wet nappies or urine output, tears, alertness, and drinking—not merely bowel-movement count. Our կղանքի կուլտուրայի ուղեցույցը explains why a positive organism is interpreted alongside symptoms, not treated automatically.
Թեստեր, որոնք կլինիցիստները օգտագործում են մշտական դեղին կղանքի համար
Persistent yellow stool is assessed with history first, then targeted liver tests, coeliac blood tests, stool studies, and imaging when the pattern points toward bile, infection, or malabsorption. There is no single “yellow stool blood test.”
A useful first blood panel often includes full blood count, electrolytes, CRP, ALT, AST, ALP, GGT, bilirubin, albumin, and coeliac serology. Low albumin below 35 g/L can occur with significant intestinal protein loss, liver synthetic dysfunction, or inflammation, but it is not specific to malabsorption. If diarrhea is prolonged, potassium and bicarbonate are clinically relevant because bowel losses can disturb both.
Stool testing should answer a question: PCR or culture for an infectious syndrome, fecal calprotectin or lactoferrin for suspected intestinal inflammation, fecal elastase for possible pancreatic insufficiency, and fecal fat when steatorrhoea is convincing. Calprotectin is best viewed as an inflammation signal rather than a diagnosis; our comparison of calprotectin and lactoferrin explains the trade-offs.
Կանտեստին մի է AI-ով աշխատող արյան թեստի վերլուծության գործիք that can organize relevant blood-test trends, including bilirubin and ALP changes over time, in about 60 seconds after a report upload. A normal blood panel cannot rule out Giardia, bile acid diarrhea, or mild coeliac disease, so our output should support a clinician-led next step rather than falsely close the investigation.
Լյարդի թեստերի ընթերցումը՝ կղանքի գույնի հետ մեկտեղ
A cholestatic liver-test pattern usually means ALP and GGT rise more prominently than ALT and AST, often with direct bilirubin elevation. Stool colour adds useful context, but blood results and symptoms determine urgency.
ALT and AST reflect hepatocyte injury more than bile flow, while ALP can arise from liver or bone. GGT helps clinicians decide whether a raised ALP is likely hepatobiliary, though alcohol, metabolic liver disease, and certain medicines can raise GGT without obstruction. A GGT of 90 IU/L with normal bilirubin means something very different from GGT 90 IU/L plus jaundice and pale stool.
The R-ratio can assist specialists: divide ALT as a multiple of its upper limit by ALP as a multiple of its upper limit. A ratio above 5 suggests a hepatocellular pattern, below 2 suggests cholestatic injury, and 2-5 is mixed; it is a triage tool, not a diagnosis. Patients can explore the component tests in our Խոլեստազի արյան թեստի ուղեցույց.
Dr. Thomas Klein has seen people worry about a marginally high ALP that later proves to be bone-related, particularly during fracture healing or vitamin D deficiency. That is why clinicians may add ALP isoenzymes, vitamin D, calcium, phosphate, or imaging rather than assuming a liver diagnosis. The stool story can make that distinction more or less urgent.
Դեղին լուծ լեղապարկի հեռացումից հետո
Diarrhea after gallbladder removal can occur because bile flows continuously into the intestine rather than being released in concentrated pulses with meals. It often begins soon after surgery, is worse after fatty meals, and can be yellow-green because transit is accelerated.
Not everyone develops post-cholecystectomy diarrhea, and it is not automatically lifelong. Smaller lower-fat meals for 2-4 weeks can reduce urgency while the bowel adapts, but severe restriction is rarely necessary long term. Persistent watery stools more than 4 weeks after surgery should prompt discussion of bile acid diarrhea and other causes, especially if symptoms wake a person at night.
Where available, SeHCAT retention testing can support bile acid malabsorption; alternatives include serum 7α-hydroxy-4-cholesten-3-one or carefully monitored treatment trials. Bile-acid sequestrants may help but can interfere with absorption of thyroid medication, warfarin, and fat-soluble vitamins, so dose spacing is not a minor detail. A pharmacist can provide the exact schedule.
This pattern differs from a new episode of severe pain, fever, jaundice, or pale stool after surgery, which needs urgent assessment for a retained stone or another complication. Our overview of the արյան թեստ՝ լեղաթթուների համար also explains why generalized itching shifts attention back toward cholestasis rather than simple rapid transit.
Դեղին կղանքը երեխաների, հղի կանանց և տարեցների մոտ
Yellow stools are common in breastfed infants and are usually normal, while persistent pale stools in any child require prompt paediatric evaluation. Pregnancy and older age also change the threshold for acting because dehydration and bile disorders carry different risks.
Breastfed infant stool is frequently mustard-yellow, loose, and seedy; that is expected when an infant is feeding and growing normally. Acholic stool, meaning distinctly white, grey, or putty coloured, is different and should be assessed urgently because biliary atresia and other neonatal cholestatic conditions are time-sensitive. Parents are right to trust a repeated colour pattern rather than one diaper under odd lighting.
During pregnancy, new pale stool, dark urine, itching of the palms or soles, or jaundice should lead to same-day maternity assessment. Serum bile acids can rise in intrahepatic cholestasis of pregnancy, but the test should be interpreted with liver results, gestational age, symptoms, and local obstetric guidance. The itching blood-test guide gives a practical testing framework.
In older adults, a new persistent stool change deserves attention sooner because medication effects, pancreatic disease, malignancy, and infection are more common, while thirst may be blunted. A loss of 5% body weight in 6-12 months is clinically significant at any age. Frailty, kidney disease, or diuretic use lowers the margin for dehydration.
Ինչ անել առաջին 72 ժամվա ընթացքում
For a single yellow stool or mild yellow diarrhea without red flags, hydration, a brief food-and-symptom record, and observation for 48-72 hours are reasonable. Avoid aggressive “cleanses,” fasting, or self-started antibiotics, which often muddy the clinical picture.
Write down the timing, Bristol stool type, meals, supplements, medicine changes, travel, fever, pain, urine colour, and number of bowel movements. This is more clinically useful than describing stool as “weird.” If you had a high-dose turmeric product, a fatty meal, or a stomach bug and symptoms settle within 3 days, no testing may be required.
Use oral rehydration solution rather than only plain water if diarrhea is frequent; standard solutions contain glucose and sodium in proportions that improve intestinal water absorption. Adults without fluid restrictions can use small repeated sips, especially after each loose stool. Avoid sports drinks as the sole replacement when diarrhea is substantial because their sodium content is often lower and sugar content higher.
If symptoms persist, our blood test for diarrhea guide can help you prepare questions for a clinician. Kantesti AI can also place liver and electrolyte results in chronological context, but an app cannot assess abdominal tenderness, hydration status, or jaundice through a screen. Those limitations matter.
Երբ դեղին կղանքը պահանջում է բժշկական վերանայում կամ շտապ օգնություն
Seek urgent care for pale stool with dark urine or jaundice, severe or worsening abdominal pain, fever with jaundice, fainting, confusion, or signs of major dehydration. Arrange routine medical review for yellow stool lasting more than 1-2 weeks, recurring greasy stool, weight loss, or persistent diarrhea.
Emergency assessment is appropriate for inability to keep fluids down, black tarry stool, visible blood, severe weakness, a rigid abdomen, or jaundice with fever. These combinations carry more diagnostic weight than yellow colour alone because they may indicate bleeding, significant infection, obstruction, or systemic illness. If in doubt, err on the side of being seen—particularly for children, pregnancy, and immunosuppression.
A non-urgent appointment is still warranted if stool changes persist beyond 7 days with diarrhea or beyond 2 weeks without diarrhea, even when pain is absent. Bring medication and supplement containers, a 7-day symptom log, and prior laboratory reports. The article on blood in stool urgency helps distinguish red and black warning colours from benign food effects.
Kantesti's medical review standards are described by our Բժշկական խորհրդատվական խորհուրդ, և մեր կլինիկական վավերացման մոտեցումը explains where automated interpretation stops. Kantesti is an ԱԻ լաբորատոր թեստի մեկնաբանման ծառայությունում designed to surface follow-up patterns; it does not provide emergency triage or replace a clinician examining you.
Հարցեր, որոնք դեղին կղանքի հետ կապված հանդիպումը դարձնում են ավելի օգտակար
The most useful appointment questions ask whether the stool pattern fits rapid transit, malabsorption, infection, or impaired bile flow and which test would change management. A focused history can prevent both under-testing and broad low-yield testing.
Ask: “Does my symptom pattern justify liver tests, coeliac testing, stool PCR, fecal calprotectin, fecal elastase, or ultrasound?” The answer should be tied to your duration, weight change, pain location, travel, surgery, and stool texture. A blanket panel is not always better; for example, stool PCR does not diagnose pancreatic enzyme deficiency, and liver tests do not rule out Giardia.
Ask for the actual results and the laboratory reference ranges, not simply “normal” or “abnormal.” A bilirubin trend from 9 to 28 µmol/L may be meaningful if it is paired with new dark urine, while an isolated stable bilirubin of 24 µmol/L can have a different explanation. Our լյարդային պանել՝ ակնարկ outlines what each component can and cannot tell you.
Kantesti AI was built by Kantesti Ltd to help people organize laboratory reports across visits, with privacy-focused handling and multilingual interpretation in 75+ languages. For the method behind that work, see our AI տեխնոլոգիայի ուղեցույց. A good next step is specific: test, monitor, image, treat, or safely observe—not merely “repeat everything.”
Եզրակացություն՝ համադրեք գույնը ամբողջ պատկերին
Most yellow stool causes are temporary dietary or fast-transit effects, but pale stool, greasy recurrence, dark urine, jaundice, fever, pain, or weight loss need medical evaluation. The combination of colour, texture, duration, and associated symptoms is far more reliable than colour alone.
A brief yellow stool after turmeric, a rich meal, or a 24-hour diarrheal illness can usually be watched for 48-72 hours. Repeated oily floating stool points toward fat malabsorption, while clay-coloured stool with dark urine points toward reduced bile flow. That distinction is clinically useful because the investigations—and the urgency—are different.
Keep the evidence in proportion. Most patients I see with a short-lived colour change do not have serious liver or pancreatic disease, yet a small number have warning combinations that should not be dismissed as “just diet.” The fecal fat test guide is a sensible next read when oiliness and floating are the recurring features.
Կանտեստին մի է AI բիոմարկերների մեկնաբանման հարթակ that helps connect laboratory patterns to informed questions for your clinician. It is not a substitute for care when red flags are present; severe pain, jaundice, fever, dehydration, or pale stool with dark urine should always be assessed in person.
Հաճախակի տրվող հարցեր
Ինչ է նշանակում դեղին մեզ մեծահասակների մոտ։
възрастните най-често отразява бърз чревен транзит, скорошен хранителен пигмент, високомаслено хранене или краткотрайно диарично заболяване. Ако е мек или воднист и се успокои в рамките на 48-72 часа без болка, треска, тъмна урина, жълтеница или загуба на тегло, обикновено не е спешен случай. Рецидивиращи мазни, плаващи, трудни за изхвърляне с вода жълти изпражнения предполагат малабсорбция на мазнини и трябва да бъдат прегледани. Светло сиви или глинести изпражнения с тъмна урина изискват клинична оценка в същия ден, тъй като притокът на жлъчка може да бъде намален.
Կարո՞ղ է լեղին դեղին աթոռ առաջացնել։
Bile can contribute to yellow-green stool when intestinal transit is fast because its pigments have not been fully transformed into brown stercobilin. Normal bile production is about 500-1,000 mL daily, and bile itself is not a sign of disease when it reaches the bowel normally. The concern is not simply “too much bile”; it is persistent watery diarrhea from bile acids or too little bile reaching the intestine, which can produce pale stool. Dark urine, itch, jaundice, or a raised direct bilirubin level make a bile-flow problem more likely.
Ե՞րբ պետք է անհանգստանամ դեղին լուծի առնչությամբ։
Դեղին լուծը շտապ բժշկական խորհրդատվության կարիք ունի, երբ այն տևում է ավելի քան 7 օր, առաջացնում է ջրազրկում, հաջորդում է բարձր ռիսկային ճանապարհորդությանը կամ չմշակված ջրի հետ շփմանը, կամ ուղեկցվում է 38.5°C-ից բարձր ջերմությամբ, արյամբ, ուժեղ ցավով կամ քաշի կորստով։ Մեծահասակները, որոնց մոտ 8 ժամ դադարում է մեզարտադրությունը, նշված գլխապտույտ, շփոթվածություն կամ հեղուկ չպահելու անկարողություն կա, պետք է շտապ գնահատվեն։ Երեխաների մոտ՝ փորկապություն, վատ խմելը, արցունքների բացակայությունը կամ քիչ թաց մանկական տակդիրները շտապ նախազգուշացնող նշաններ են։ Փորի ՊՇՌ, կուլտուրա կամ պարազիտների թեստը կարող է պատշաճ լինել՝ կախված շփման և ախտանիշների դրսևորումից։.
Դեղին կղանքը ենթաստամոքսային քաղցկեղի՞ նշան է:
Դեղին կղանքը ինքնին ենթաստամոքսային գեղձի քաղցկեղ չի նշանակում, և շատ ավելի հաճախ այն պայմանավորված է դիետայով, արագ անցմամբ կամ ստամոքս-աղեստանային համակարգի կարճատև հիվանդությամբ։ Կլինիցիստները ուսումնասիրում են ենթաստամոքսային գեղձի հիվանդությունը, երբ բաց կամ յուղոտ կղանքը կրկնվում է անբացատրելի քաշի կորստի, ստամոքսի վերին մասում կամ մեջքի ցավի, նոր դիաբետի, դեղնախտի կամ ցածր ֆեկալ էլաստազայի՝ 200 µg/g-ից ցածր մակարդակի հետ միասին։ Այս ախտանիշներն ունեն բազմաթիվ ոչ քաղցկեղային բացատրություններ, ներառյալ ենթաստամոքսային ֆերմենտային անբավարարությունը և լեղու խցանումը։ Կղանքի գույնից ինքնահաշվարկի փոխարեն պետք է գնահատել մշտական նախազգուշացնող նախանշանները։.
Անհանգստությունը կարո՞ղ է դեղին աղիքային շարժումներ առաջացնել։
Անհանգստությունը կարող է անուղղակիորեն նպաստել դեղնավուն կղանքին՝ արագացնելով աղիքային անցումը աղիք-ուղեղային ազդանշանների միջոցով, հատկապես աղիքային գրգռական համախտանիշ ունեցող մարդկանց մոտ։ Արագ անցումը կարող է հանգեցնել փուխր, դեղնականաչ և շտապ կղանքի, քանի որ լեղու պիգմենտին ավելի քիչ ժամանակ է մնում դառնալու շագանակագույն։ Անհանգստությունը չպետք է համարել պատճառ, եթե 50 տարեկանից հետո ախտանիշները նոր են, արթնացնում են քնից, ուղեկցվում են արյամբ, տենդով, քաշի կորստով, բաց դեղնավուն կղանքով կամ լյարդի փորձաքննության աննորմալ արդյունքներով։ Ախտանիշների օրագիրը 2 շաբաթվա ընթացքում հաճախ պարզում է, արդյոք սթրեսի ժամկետը իսկապես համապատասխանում է աղիքային փոփոխությունների հետ։.
Որո՞նք են օգտակար հետազոտությունները դեղին կղանքի դեպքում։
Դեղնավուն կղանքի դժվարությունը սովորաբար գնահատվում է լյարդի թեստերով, ներառյալ բիլիռուբին, ALP, GGT, ALT, AST և ալբումին, գումարած նպատակային կղանքի կամ ցելիակիա թեստավորում՝ ախտանիշների համաձայն։ 200 µg/g-ից ցածր կղանքի էլաստազը աջակցում է ենթաստամոքսային գեղձի ֆերմենտային անբավարարության հնարավորությանը, մինչդեռ կղանքի կալպրոտեկտինը կարող է օգնել բորբոքային աղիքային հիվանդությունների հայտնաբերմանը։ Ճամփորդությունից, ջրի հետ շփումից կամ երկարատև ախտանիշներից հետո փորլուծության դեպքում օգտակար է կղանքի PCR կամ հակածնային թեստավորումը։ Ուլտրաձայնային հետազոտությունը հաճախ օգտագործվում է, երբ բաց գույնի կղանքը, մուգ մեզը, դեղնախտը կամ որովայնի վերին մասում ցավը մտահոգություն է առաջացնում լեղաքարերի կամ լեղու արգելափակման վերաբերյալ։.
Ստացեք AI-ով աշխատող արյան անալիզի վերլուծություն այսօր
Միացեք ավելի քան 2 միլիոն օգտատերերի ամբողջ աշխարհում, ովքեր վստահում են Kantesti-ին՝ լաբորատոր թեստերի ակնթարթային, ճշգրիտ վերլուծության համար։ Վերբեռնեք ձեր արյան անալիզի արդյունքները և ստացեք 15,000+ բիոմարկերների համապարփակ մեկնաբանություն վայրկյանների ընթացքում։.
📚 Հղված հետազոտական հրապարակումներ
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). Women's Health Guide: Ovulation, Menopause & Hormonal Symptoms. Figshare. DOI: 10.6084/m9.figshare.31830721.։ Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). Multilingual AI Assisted Clinical Decision Support for Early Hantavirus Triage: Design, Engineering Validation, and Real-World Deployment Across 50,000 Interpreted Blood Test Reports. Figshare. DOI: 10.6084/m9.figshare.32230290.։ Kantesti AI Medical Research.
📖 Արտաքին բժշկական հղումներ
⚕️ Բժշկական հրաժարում
Այս հոդվածը միայն կրթական նպատակների համար է և չի հանդիսանում բժշկական խորհրդատվություն։ Ախտորոշման և բուժման որոշումների համար միշտ խորհրդակցեք որակավորված բուժաշխատողի հետ։.
E-E-A-T վստահության ազդանշաններ
Փորձառություն
Բժշկի կողմից ղեկավարվող կլինիկական վերանայում՝ լաբորատոր մեկնաբանության աշխատանքային հոսքերի համար։.
Մասնագիտություն
Լաբորատոր բժշկության կենտրոնացում՝ այն բանի վրա, թե ինչպես են բիոմարկերները դրսևորվում կլինիկական համատեքստում։.
Հեղինակություն
Գրված է դոկտոր Թոմաս Քլայնի կողմից՝ դոկտոր Սառա Միթչելի և պրոֆեսոր դոկտոր Հանս Վեբերի կողմից վերանայմամբ։.
Հուսալիություն
Ապացույցների վրա հիմնված մեկնաբանություն՝ հստակ հետագա քայլերի ուղիներով՝ ահազանգերը նվազեցնելու համար։.