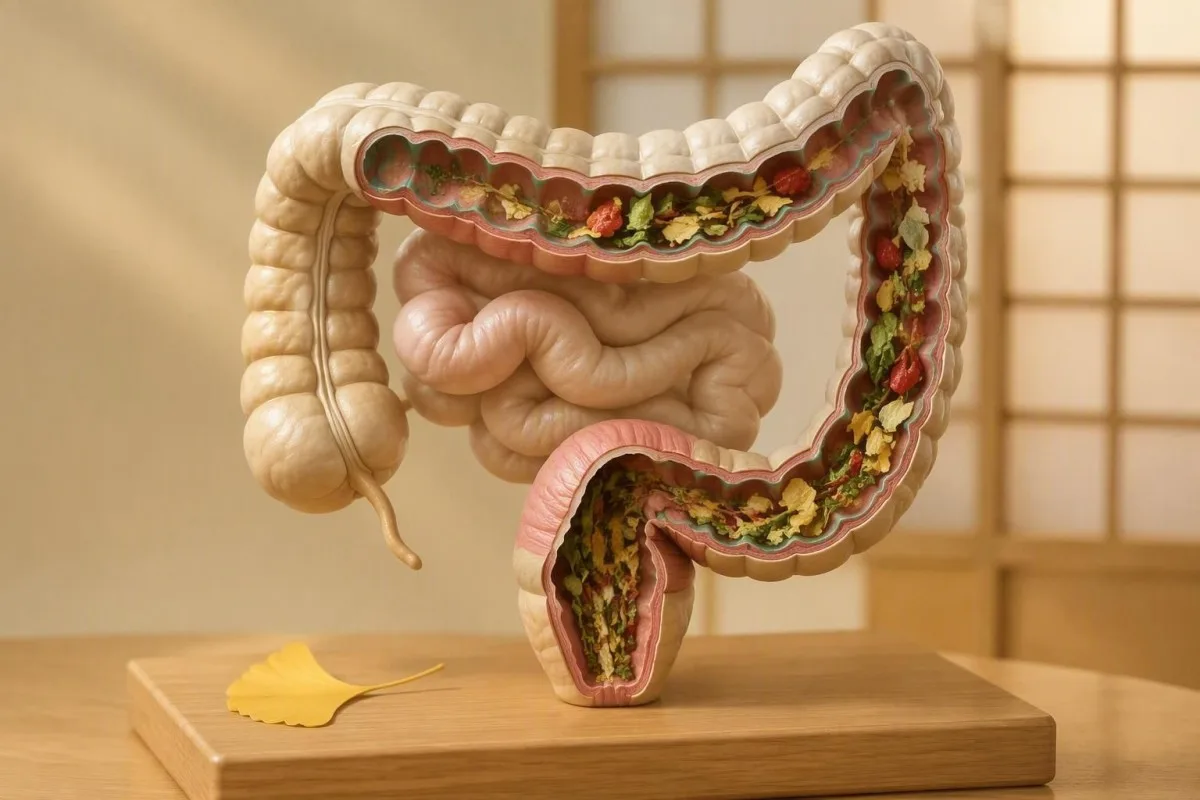
පෙනෙන ආහාර අංශු සාමාන්යයෙන් ජීර්ණය වීමේ වේගය හෝ ආහාරයේ ව්යුහය සම්බන්ධ ගැටලුවක් මිස ඔබේ ශරීරය පෝෂ්ය පදාර්ථ අවශෝෂණය කර ගැනීමට අසමත් වන බවට සාක්ෂියක් නොවේ. මළපහ වල රටාව, ඔබේ බර, රෝග ලක්ෂණ සහ රුධිර පරීක්ෂණ ප්රතිඵල එය පරීක්ෂා කිරීම වටීද යන්න තීරණය කරයි.


- මළපහ වල ජීර්ණය නොවූ ආහාර තන්තු බහුල ආහාර ගැනීමෙන් පසු සාමාන්යයෙන් හානිකර නොවන අතර, බර අඩු වීම, නිදන්ගත පාචනය, හෝ තෙල් සහිත මළපහ නොමැතිව සිදු වේ.
- එළවළු හම් ඉරිඟු, ගම්මිරිස්, තක්කාලි, කොළ එළවළු සහනිෂ්පාදන වලින් දෘශ්යමාන වේ, මන්ද මිනිසුන් සෙලියුලෝස් ජීර්ණය නොකරයි.
- වේගවත් ගමනාගමනය ගැස්ට්රයිටිස්, ආතති-ආශ්රිත පාචනය, උත්තේජක විරේචක, මැග්නීසියම් නිෂ්පාදන, හෝ අධික කැෆේන් භාවිතයෙන් පසු මළපහ වල ආහාර අංශු ඉතිරි කළ හැකිය.
- ස්ටෙටෝරියා යනු මහත, සුදුමැලි, තෙල් සහිත, සේදීමට අපහසු මළපහ වන අතර එය විටින් විට පෙනෙන ආහාර කැබලි වලට වඩා කනස්සල්ලට කරුණකි.
- අහිතකර ලෙස බර අඩුවීම 5% හෝ ඊට වැඩි ප්රමාණයක් මාස 6 ත් 12 ත් අතර කාලයකදී වෛද්ය සමාලෝචනයක්, විශේෂයෙන්ම අඛණ්ඩ ලිහිල් මළපහ සමඟ සුදුසුකම් ලබයි.
- මලෙහි කැල්ප්රෙක්ටීන් බඩවැල්වල දැවිල්ල තක්සේරු කිරීමට උපකාරී වේ; වැඩිහිටියන්ගේ ක්රියාකාරී ගිනි අවුලුවන බඩවැල් රෝගයක් අඩු කිරීමට සාමාන්යයෙන් 50 micrograms/g ට වඩා අඩු අගයන් උපකාරී වේ.
- මලෙහි ඉලාස්ටේස්-1 200 micrograms/g ට වඩා අඩු අගයක් අග්න්යාශයික එන්සයිම අසමර්ථතාවයක් පෙන්නුම් කරයි, නමුත් ජලය සහිත සාම්පල ව්යාජ ලෙස අඩු ප්රතිඵල ලබා දිය හැකිය.
- Coeliac පරීක්ෂණය පුද්ගලයෙකු තවමත් ග්ලූටන් අනුභව කරන විට වඩාත් විශ්වාසදායක වේ; වෛද්යවරයෙකු සමඟ පරීක්ෂා කිරීම ගැන සාකච්ඡා කිරීමට පෙර ග්ලූටන් රහිත ආහාර වේලක් ආරම්භ නොකරන්න.
මළපහ වල පෙනෙන ආහාර සාමාන්යයෙන් ඇති විට
මලෙහි ජීර්ණය නොවූ ආහාර සාමාන්යයෙන් දක්නට ලැබෙන්නේ කෙඳි බහුල ආහාර ගැනීමෙන් පසු විටින් විට දිස්වන විට සහ අනෙක් අතට ඔබ හොඳින් සිටින විට, බර පවත්වා ගන්නා විට සහ මළපහ සාමාන්ය වන විටය. වඩාත් පොදු පැහැදිලි කිරීම නම් දෘශ්යමාන ශාක සෛල බිත්ති ද්රව්ය මිස පෝෂණීය අවශෝෂණය අසමත් වීම නොවේ.
මගේ සායනික අත්දැකීම් වලදී, සතියකට වරක් හෝ දෙවරක් ඉරිඟු ඇට, තක්කාලි හම්, නිවිති තන්තු, හෝ ගම්මිරිස් පීල් දකින කෙනෙකුට අවශෝෂණ ගැටලුවක් ඇත්තේ කලාතුරකිනි. ශාක සෛල බිත්ති අඩංගු වේ සෙලියුලෝස්, සහ මානව ආහාර ජීර්ණ එන්සයිම සෙලියුලෝස් අවශෝෂණය කළ හැකි සීනි බවට බිඳ දමන්නේ නැත. ආහාර ඇතුළත ඇති මෘදු පිෂ්ඨය, ප්රෝටීන්, මේදය සහ බොහෝ විටමින් සාමාන්යයෙන් අවශෝෂණය වී තිබිය හැක.
සන්සුන් රටාව කැපී පෙනෙන ලෙස අනුකූල වේ: හඳුනාගත හැකි ආහාරයක් හඳුනාගත හැකි ආහාර වේලක් අනුගමනය කරයි, මළපහ සංඛ්යාතය ඔබගේ සාමාන්ය මූලික මට්ටමට ආසන්න වේ, සහ ප්රගතිශීලී තෙහෙට්ටුවක් හෝ බර අඩු වීමක් නොමැත. ආචාර්ය තෝමස් ක්ලයින්ගේ ප්රායෝගික රීතිය නම්, තනි භයානක වැසිකිළි-බඳුනක් නිරීක්ෂණය කිරීමක් ලෙස නොව, මළපහ දෙස 2 සිට 4 සති දක්වා රටාවක් ලෙස විනිශ්චය කළ යුතු බවයි. Bristol මළපහ වගුව (Bristol stool chart) එම රටාව වඩාත් නිවැරදිව විස්තර කිරීම පහසු කරයි.
කන්ටෙස්ටි යනු AI රුධිර පරීක්ෂණ විශ්ලේෂකය යකඩ සංචිත, විටමින් B12, ඇල්බුමින්, අක්මා සලකුණු සහ දැවිල්ල සලකුණු වැනි වෛෂයික ඉඟි සමඟ හැකි ආහාර ජීර්ණ රෝග ලක්ෂණ තැබීමට උපකාරී වේ. සාමාන්ය පෝෂණ පැනලයක් සෑම බඩවැල් තත්වයක්ම බැහැර නොකරයි, නමුත් එය දරුණු දිගුකාලීන මැලෝබ්සෝර්ප්ෂන් එකක් අඩු කිරීමට බොහෝ සෙයින් ඉඩ සලසයි.
ආහාර අංශු සහ එළවළු කැබලි ඇත්තෙන්ම අදහස් කරන්නේ කුමක්ද?
මලෙහි ආහාර අංශු බොහෝ විට දෘඩ ශාක ද්රව්යවල කොටස් වන අතර, ඒවායේ හැඩය රෝගයකට වඩා ආහාර වේලක් වෙත යොමු කළ හැකිය. පැතලි විනිවිද පෙනෙන හම් සහ තන්තුමය නූල් මේද බිංදු, ශ්ලේෂ්මල හෝ රුධිරයෙන් වෙනස් වේ.
ඉරිඟු පщиковර්, ක්විනෝවා හිස්, තක්කාලි හම්, බෙල් පෙපර් කчикуල්, හතු සෛල බිත්ති, සහ කොළ පැහැති කොළ තන්තු බොහෝ විට දක්නට ලැබේ. ඒවායේ දීප්තිමත් වර්ණය පුදුමයට පත් කළ හැකිය, මන්ද වර්ණක ද්රව්ය සංක්රමණයෙන් දිවි ගලවා ගත හැකි බැවිනි; බීට්රූට් මල රතු පැහැයට හැරිය හැකි අතර, නිවිති තද කොළ පැහැති කැබලි ඉතිරි කළ හැකිය. මෙය බොහෝ වැඩිහිටි ආහාර ඉලක්ක වලට ආසන්න, 25 සිට 35 g දක්වා තන්තු අඩංගු ආහාර ගැනීමෙන් පසු විශේෂයෙන්ම පොදු වේ.
ප්රයෝජනවත් වෙනසක් නම් ද්රව්යයද යන්නයි හඳුනාගත හැකි. සාමාන්ය මල අතර හඳුනාගත හැකි කැබලි කිහිපයක් සාමාන්යයෙන් ආහාර ව්යුහය හෝ වේගවත් සංක්රමණයට යොමු කරයි; විසරණය වන තෙල් සහිත දිලිසීමක්, සුදු මැටි වැනි මලක්, හෝ මේදය සිරවීම නිසා නැවත නැවත පාවෙන මලක් වෙනස් විමර්ශන රේඛාවක් අවශ්ය වේ. තිරසාර සුදු මල අවධානයට ලක්විය යුතුය, මන්ද එය බඩවැල් වෙත ළඟා වන පිත්තාශයේ අඩුවීමක් පිළිබිඹු කළ හැකි බැවිනි; අපගේ මාර්ගෝපදේශය බලන්න සුදු මල රටා.
සෑම මළපහ චලනයක්ම ඡායාරූප ගැනීමෙන් ස්වයං-රෝග විනිශ්චය කිරීමට උත්සාහ නොකරන්න. ඒ වෙනුවට, පසුගිය පැය 24 තුළ ආහාර, අතිරේක, මත්පැන්, අසනීප සහ මළපහ සංඛ්යාතය දින 7ක් සඳහා ලියන්න. එම කුඩා දිනපොත බොහෝ විට ඉතා සාමාන්ය පැහැදිලි කිරීමක් හෙළි කරයි—විශේෂයෙන් නව ඉහළ-තන්තු උදෑසන ආහාරය, මැග්නීසියම් අතිරේකය, හෝ පාචන රෝගය.
තන්තු බහුල ආහාර ජීර්ණයෙන් දිවි ගලවා ගන්නේ ඇයි?
ඉහළ-තන්තු සහිත ආහාර දෘශ්යමාන එළවළු කැබලි නිපදවිය හැකිය, මන්ද මානව එන්සයිමවලට සෙලියුලෝස්, ලig්නින් සහ සමහර ප්රතිරෝධී පිෂ්ඨ ව්යුහයන් ජීර්ණය කළ නොහැකි බැවිනි. Seeing the outer layer of a food does not mean the calorie or micronutrient content passed through untouched.
Chewing and cooking change how much plant matter remains visible. A raw salad with kale, carrots, pepper skins, seeds, and legumes creates more recognisable residue than the same ingredients cooked into a soup. Even so, colonic bacteria ferment part of the fibre into short-chain fatty acids, which support the colonic lining and are absorbed as energy.
Rapidly raising fibre from 10 g to 30 g daily can also cause gas, urgency, and looser stools for 1 to 2 weeks. Most patients find a slower increase—about 5 g every 3 to 4 days—with adequate fluids is more comfortable. A sudden fibre increase may make food particles more obvious without causing any nutritional deficit.
If a high-fibre diet causes daily pain, nocturnal diarrhoea, or worsening bloating, do not simply force more fibre. Fermentable carbohydrates can aggravate symptoms in some people with irritable bowel syndrome, while coeliac disease and inflammatory conditions need different management. Our article on foods that shift stool tests explains why diet changes should precede stool testing by a sensible interval.
බඩවැල් ගමන් කිරීමේ වේගය ආහාර දෘශ්යමාන කරන්නේ කෙසේද?
Fast intestinal transit can leave vegetable pieces in stool because food spends less time being mechanically broken down and exposed to digestive enzymes. Acute diarrhoea is the classic setting, but medication, stress, and diet can do the same thing.
Stool normally takes roughly 24 to 72 hours to travel through the colon, although healthy variation is broad. When transit speeds up, more water remains in stool and food is less fragmented. Viral gastroenteritis, food poisoning, a large coffee intake, endurance running, anxiety, and menstruation-related bowel changes can all temporarily shorten transit.
Magnesium citrate and magnesium oxide commonly loosen stool because poorly absorbed magnesium draws water into the bowel; doses above 350 mg daily from supplements are more likely to cause gastrointestinal effects. Metformin, antibiotics, GLP-1 medicines, laxatives, and some sugar alcohols can also change stool form. Do not stop a prescribed medicine without discussing it with the prescriber.
Chronic diarrhoea means loose or watery stool for 4 weeks or longer, not merely three bowel movements after a spicy meal. The British Society of Gastroenterology guideline recommends a structured history, medication review, coeliac serology, and targeted stool testing when diarrhoea persists (Arasaradnam et al., 2018). For related warning patterns, read our පාචනය රුධිර පරීක්ෂණ මාර්ගෝපදේශය (diarrhoea blood test guide).
හපන, ආහාර වේගය සහ නොසලකා හරින ලද යාන්ත්රික හේතුව
Poor chewing can make food look less digested even when pancreatic enzymes and intestinal absorption are normal. The mouth is the first grinding stage of digestion, and rushed eating changes what reaches the colon.
I see this most often in people who eat lunch at a desk, have dental discomfort, wear poorly fitting dental appliances, or swallow quickly after a long fast. Large pieces of mushroom, carrot, nuts, leafy greens, and legumes are mechanically harder for the stomach and bowel to reduce. The practical experiment is simple: chew deliberately for 7 days before changing supplements or buying tests.
A 52-year-old runner I reviewed had visible kale and lentil fragments after race weekends, but no weight loss and a stable ferritin of 64 ng/mL. His pattern improved when he ate a smaller pre-run fibre load, drank less coffee immediately before exercise, and slowed his evening meal. That is not a universal prescription, but it shows why context beats panic.
Difficulty swallowing, choking, pain with chewing, or an unexpected change in dentition deserves dental or medical assessment rather than a digestive cleanse. If you have coexisting tiredness, paleness, or poor appetite, the අඩු ෆෙරිටින් රෝග ලක්ෂණ මාර්ගෝපදේශය may help you recognise when a blood count and iron studies are reasonable.
මැලබ්සෝර්ප්ෂන් හානිකර නොවන දෘශ්ය තන්තු වලින් වෙනස් වන්නේ කෙසේද?
Malabsorption usually causes a repeated cluster of symptoms—weight loss, chronic loose stool, excess gas, nutrient deficiency, or greasy bulky stool—not isolated vegetable pieces. The combination matters far more than the visual appearance of one bowel movement.
ස්ටෙටෝරියා describes excess fat in stool and often looks pale, bulky, oily, foul-smelling, or difficult to flush. It may float, although floating alone is not diagnostic because gas can do that too. A repeated greasy film plus weight loss is a much stronger warning sign than seeing corn or seeds.
Malabsorption symptoms can include iron-deficiency anaemia, recurrent mouth ulcers, low folate, vitamin B12 deficiency, low albumin, bruising from vitamin K deficiency, or bone pain from low vitamin D. No single blood test proves malabsorption, and normal results do not exclude early coeliac disease. Kantesti's AI biomarker interpretation platform reviews iron indices, full blood count, albumin, calcium, liver tests, and nutrient markers as a pattern rather than treating one low value as a diagnosis.
The reason clinicians worry about loose oily stool combined with a falling weight is that together they suggest lost calories and fat-soluble nutrients, whereas food particles alone usually do not. If stool appears greasy or unusually light for more than 2 weeks, our faecal fat test overview explains what collection-based testing can and cannot establish.
කඩිනම් වෛද්ය සමාලෝචනයක් අවශ්ය වන අනතුරු ඇඟවීමේ සංඥා
Visible food needs medical review when it occurs with blood in stool, black tarry stool, fever, persistent pain, dehydration, or unintentional weight loss. These features raise concern for inflammation, infection, bleeding, obstruction, or clinically meaningful malabsorption.
Seek urgent care today for black tar-like stool, maroon or large-volume red stool, severe constant abdominal pain, a rigid abdomen, fainting, confusion, or inability to keep fluids down. Black stool can be caused by iron or bismuth, but true melena is sticky, offensive, and may signal upper gastrointestinal bleeding. A positive stool blood test needs clinician-directed follow-up rather than repeated home tests.
Arrange a routine appointment within days to weeks if diarrhoea lasts beyond 4 weeks, stools wake you at night, weight drops by 5% or more in 6 to 12 months, or you develop persistent fatigue. Fever above 38.0°C with diarrhoea, recent international travel, recent antibiotics, or immune suppression lowers the threshold for stool infection testing.
Age changes the threshold too. New bowel habit change after age 50, or at any age with a first-degree relative with colorectal cancer or inflammatory bowel disease, deserves a proper review. Clinicians may use a faecal immunochemical test for occult bleeding, but it does not diagnose coeliac disease, pancreatic insufficiency, or all bowel conditions.
CEeliac රෝගයේ හෝඩුවාවන්, නිරන්තර ආහාර අංශු පිටුපස
Coeliac disease should be considered when persistent loose stools or food particles accompany iron deficiency, weight loss, recurrent mouth ulcers, low bone density, or a family history of coeliac disease. Many adults have non-classic symptoms and do not look underweight.
The first-line blood test is usually tissue transglutaminase IgA together with total IgA. A negative tissue transglutaminase IgA result is less reliable in IgA deficiency, which is why total IgA matters; IgG-based tests may then be used. The American College of Gastroenterology advises testing while the patient is consuming gluten, not after a self-started gluten-free diet (Rubio-Tapia et al., 2023).
Low ferritin can precede anaemia in coeliac disease. Ferritin below 15 ng/mL strongly supports iron deficiency in many laboratories, although inflammation can make ferritin appear falsely reassuring; transferrin saturation below 20% adds useful context. Our සුදුලූනු රහිත ආහාර අභියෝග මාර්ගෝපදේශය discusses why stopping gluten before testing can create a false-negative result.
Dr. Thomas Klein has seen patients delay diagnosis because they assumed bloating and vegetable pieces meant they simply needed probiotics. Probiotics may change symptoms in selected cases, but they do not diagnose or treat immune-mediated gluten injury. Kantesti is an AI මගින් බලගැන්වූ රුධිර පරීක්ෂණ විශ්ලේෂණ මෙවලම that can identify a blood-test pattern worth discussing with a clinician, not replace confirmatory coeliac assessment.
අග්න්යාශයේ හෝ පිත්තාශයේ ගැටළු ඇතිවිය හැකි විට
Pancreatic enzyme deficiency and reduced bile delivery are more likely when stool is repeatedly greasy, pale, bulky, and associated with weight loss than when it simply contains vegetable skins. Both conditions affect fat digestion, so the stool changes are usually conspicuous.
The pancreas supplies lipase, proteases, and amylase to the small intestine. Faecal elastase-1 below 200 micrograms/g may suggest pancreatic exocrine insufficiency, while values below 100 micrograms/g are more strongly suggestive; a watery stool sample can dilute elastase and give a falsely low result. This test should be interpreted alongside symptoms, nutrition, imaging, and history of pancreatitis, pancreatic surgery, cystic fibrosis, or heavy alcohol exposure.
Bile obstruction can make stool pale or putty-coloured and may occur with dark urine, yellowing of the eyes, itching, or right-upper abdominal pain. Blood tests may show raised alkaline phosphatase, gamma-glutamyl transferase, and direct bilirubin, but normal liver tests do not explain every pale stool episode. Review our කොලෙස්ටැසිස් රුධිර-පරීක්ෂණ රටා for the combinations clinicians use.
Do not take over-the-counter digestive enzymes indefinitely to mask these symptoms. Enzymes can be appropriate after a diagnosis, but they may delay recognition of a bile duct or pancreatic condition. A stool elastase result is most helpful when the sample is formed or semi-formed and the symptom history is clear.
කුමන මළපහ පරීක්ෂණ සුදුසුද සහ ඇයි?
Stool testing is appropriate for persistent diarrhoea, greasy stools, blood, fever, travel-related symptoms, or suspected bowel inflammation—not for one isolated piece of corn. The best test depends on the clinical question.
මලෙහි කැල්ප්රෙක්ටීන් measures neutrophil-related intestinal inflammation. In many adult laboratories, a result below 50 micrograms/g makes active inflammatory bowel disease less likely, while 50 to 150 micrograms/g often leads to repeat testing after infection, NSAID use, or a flare settles. Values above 250 micrograms/g more strongly support prompt clinical investigation, although cut-offs vary by assay and age.
Stool culture or molecular pathogen testing is most useful with acute diarrhoea plus fever, blood, severe illness, recent travel, outbreaks, or immune compromise. Ova-and-parasite testing should be targeted to travel, exposure, prolonged diarrhoea, or specific risks rather than ordered automatically. Our stool culture results guide explains why a report can show normal flora without answering every symptom.
For pancreatic questions, request faecal elastase; for fat loss, clinicians may use a qualitative stain or quantitative faecal fat collection; for inflammatory questions, calprotectin or lactoferrin is usually more useful. The calprotectin versus lactoferrin comparison helps patients understand why these tests are not interchangeable.
දිගුකාලීන අවශෝෂණ ගැටළු හෙළි කළ හැකි රුධිර පරීක්ෂණ
Blood tests can reveal the consequences of chronic malabsorption, especially iron deficiency, anaemia, low albumin, vitamin deficiencies, and electrolyte disturbance. They do not identify food particles directly, but they can show whether digestion problems are affecting the rest of the body.
A sensible initial panel often includes full blood count, ferritin with transferrin saturation, folate, vitamin B12, albumin, liver tests, renal function, calcium, and coeliac serology when symptoms fit. Albumin below 35 g/L may reflect poor intake, inflammation, liver disease, kidney loss, or intestinal protein loss; it is not a stand-alone malabsorption diagnosis. Persistent low magnesium or potassium in someone with diarrhoea can signal clinically significant fluid losses.
කන්ටෙස්ටිගේ AI රසායනාගාර පරීක්ෂණ අර්ථකථන සේවාව can organise these results against the laboratory's own ranges and show trends across dates. In our analysis of more than 2 million interpreted tests, the most useful signal is often a direction of travel—ferritin falling from 42 to 18 ng/mL, for example—rather than one borderline result.
Vitamin B12 below 200 pg/mL, or approximately 148 pmol/L, is commonly considered low, though laboratory thresholds differ and methylmalonic acid can clarify equivocal cases. Folate deficiency, iron deficiency, and low vitamin D together raise the index of suspicion for small-bowel disease, but diet restriction alone can produce the same combination. See our Primerjava B12 in folata before treating a low value in isolation.
ළමුන් සහ වැඩිහිටියන් සඳහා විශේෂ සැලකිල්ල
Children with visible food in stool are often experiencing normal dietary fibre passage or a short-lived viral illness, but poor growth and persistent diarrhoea need paediatric assessment. In older adults, a new bowel change deserves a lower threshold for review.
For children, contact a clinician promptly if there are fewer wet nappies or urinations, dry mouth, unusual sleepiness, fever, blood in stool, repeated vomiting, or slowed growth. Babies and toddlers can pass partially digested peas, carrots, and corn after diet changes because their chewing and digestive capacity are still developing. Never use adult anti-diarrhoeal medicines in a child without professional guidance.
In older adults, poor dentition, reduced appetite, polypharmacy, diabetes medicines, antibiotics, and reduced mobility can all alter stool appearance. New constipation alternating with diarrhoea, iron-deficiency anaemia, or a positive stool blood test should not be blamed on vegetables. Our article about senior medication effects may help prepare a medication list for the appointment.
Weight should be measured rather than guessed. A 3 kg loss matters differently in a 45 kg person than in a 100 kg person, which is why clinicians use percentage loss; 5% over 6 to 12 months is a common trigger for assessment. For paediatric laboratory questions, ළමුන් සඳහා ආරක්ෂිත AI අර්ථ නිරූපණය explains the limits of automated result support.
ඔබේ හමුවීමට පෙර දින 7 ක ප්රායෝගික සැලැස්මක්
A 7-day food, stool, and symptom record often separates harmless food residue from a persistent clinical pattern before any test is ordered. Record details that change medical decisions, not every minor variation.
Record meal timing, high-fibre foods, alcohol, caffeine, supplements, medicines, stool frequency, Bristol type, pain, urgency, and whether stool was oily or difficult to flush. Weigh yourself once at the start and once at day 7 under similar conditions. Avoid abruptly eliminating gluten if coeliac testing may be needed, and avoid starting enzyme products just before a clinical review.
Hydration is particularly important during diarrhoea. Adults with uncomplicated fluid loss can usually use oral rehydration solution or frequent small drinks; dizziness on standing, minimal urination for 8 to 12 hours, or inability to retain fluids needs same-day advice. If fasting has coincided with symptoms, our fasting and stool-change guide covers common non-dangerous mechanisms.
Bring a photograph only if it genuinely shows blood, black stool, pale stool, or repeated oily residue; most clinicians do not need routine images of vegetable pieces. Bring the diary and a medication list instead. Those two items often shorten the path to the right test more than an unstructured description of “undigested food.”
ආහාර අංශු, ඩෙටොක්ස් සහ එන්සයිම පිළිබඳ මිථ්යා විශ්වාස
Visible food particles do not prove a “leaky gut,” toxin buildup, parasite infection, or lack of stomach acid. These claims sound plausible because the symptom is visual, but they are not reliable diagnostic shortcuts.
Commercial detoxes and colon cleanses can actually create the diarrhoea that makes food more visible. Stimulant laxatives may cause urgency, cramping, electrolyte shifts, and dependence when used regularly. Magnesium-containing products can be useful for constipation under guidance, but a new loose-stool pattern after starting them is often pharmacological rather than mysterious.
Parasites are possible after relevant travel, contaminated water exposure, certain occupational exposures, or prolonged diarrhoea, but food pieces are not a parasite test. Testing is more accurate than empiric anti-parasitic treatment because different organisms need different medicines. Our ova and parasite testing guide explains when sample collection is actually worthwhile.
Digestive enzymes can be medically appropriate for confirmed pancreatic exocrine insufficiency, but dosing depends on fat intake and diagnosis. “Low stomach acid” supplements may be unsafe for people with ulcers, gastritis, reflux, or certain medicines. Evidence-based review means identifying the mechanism first, then choosing treatment—not trying every bottle on the shelf.
වෛද්යවරයෙකු හමුවීමක් වෙන්කරවා ගත යුත්තේ කවදාද සහ කුමක් ඇසිය යුතුද?
Book a clinician review if food particles persist for more than 2 to 4 weeks with diarrhoea, pain, weight loss, greasy stools, or abnormal blood results. A focused history and a few targeted tests are usually more useful than broad commercial panels.
Ask: “Does my stool pattern suggest inflammation, infection, fat malabsorption, coeliac disease, or rapid transit?” Then ask which one or two tests would change management. This phrasing helps avoid scattershot testing. If you have existing results, include the laboratory name, collection date, reference ranges, and whether you were ill or taking supplements at the time.
Kantesti can help you organise a blood-test PDF or photo for discussion, flagging linked abnormalities and longitudinal changes in about 60 seconds; it cannot examine you, inspect a stool sample, or replace a clinician's diagnosis. Our approach is reviewed against clinical standards described in our වෛද්ය සනාථ කිරීමේ දළ විශ්ලේෂණය සඳහා මූලික වේ, with physician input from the වෛද්ය උපදේශක මණ්ඩලය.
As of September 20, 2026, the sensible bottom line remains reassuring but specific: occasional vegetable pieces in otherwise normal stool are common; persistent greasy diarrhoea, blood, weight loss, fever, or nutrient-deficiency clues are not. The Kantesti ජෛව සලකුණු මාර්ගෝපදේශය තුළය. can help you prepare informed questions from laboratory results, while your own clinician determines the diagnosis and next step.
නිතර අසන ප්රශ්න
මළපහ තුළ ජීර්ණය නොවූ ආහාර සාමාන්යද?
ආහාර ජීර්ණය නොවූ ආහාර මළපහ තුළ තිබීම සාමාන්ය දෙයක් වන විට, ද්රව්යය recognisable ශාක තන්තු, such as corn, tomato skin, spinach, peppers, or legumes, වන අතර බර අඩුවීමක් හෝ දියරමය මළපහක් නොමැති විට. මිනිසුන්ට සෙලියුලෝස් ජීර්ණය කළ නොහැකි බැවින්, ආහාරවල ඇති පෝෂ්ය පදාර්ථ අවශෝෂණය කර ගත්තද, පිටත ශාක ව්යුහයන් දෘශ්යමාන විය හැකිය. මේ රටාව 2 සිට 4 සතිවලට වඩා වැඩි කාලයක් පවතී නම්, මේද සහිත මළපහ, වේදනාව, උණ, රුධිරය හෝ 6 සිට 12 මාසවලදී 5% ට වඩා වැඩි බරක් අඩුවුවහොත් වෛද්ය පරීක්ෂාවක් සුදුසු වේ.
මගේ මළපහ තුළ එළවළු කැබලි දකින්නේ ඇයි?
මලෙහි එළවළු කැබලි සාමාන්යයෙන් පෝෂ්ය පදාර්ථ අවශෝෂණය නොවීම් වලට වඩා සෙලියුලෝස් බහුල පොතු, ප්රමාණවත් පරිදි හපන නොහැකීම, හෝ මහා බඩවැලේ වේගවත් ගමනාගමනය පිළිබිඹු කරයි. අමු කේල්, ඉරිඟු, හතු, ගම්මිරිස් පොතු, තක්කාලි පොතු සහ ක්විනෝවා ලෙලි යනු පොදු උදාහරණ වන අතර ඒවායේ ව්යුහාත්මක ද්රව්ය මානව ජීර්ණයට ප්රතිරෝධී වන බැවිනි. දිනකට තන්තු ග්රෑම් 10 සිට 30 දක්වා හදිසි වැඩිවීමක්, මහා බඩවැලේ සකස් වන අතර සති 1 සිට 2 දක්වා මෙම කැබලි වඩාත් කැපී පෙනෙන ලෙස කිරීමට හේතු විය හැක.
මළපහේ ආහාර තිබීමෙන් මට මැලැක්සෝර්ප්ෂන් (malabsorption) ඇති බවක්ද?
මළපහ තුළ ආහාර පමණක් තිබීම malabsorption (ශෝෂණ ඌනතාවය) අදහස් නොකරයි. Malabsorption (ශෝෂණ ඌනතාවය) බොහෝ විට සිදුවන්නේ ලිහිල් හෝ තෙල් සහිත, විශාල මළපහ, අහම්බෙන් බර අඩුවීම, තෙහෙට්ටුව, යකඩ ඌනතාවය, විටමින් මට්ටම අඩුවීම හෝ ඇල්බියුමින් මට්ටම අඩුවීම යන රෝග ලක්ෂණ නැවත නැවත ඇතිවීමයි. මයික්රො ග්රෑම් 200 ට අඩු faecal elastase-1 මට්ටමක් pancreatic enzyme insufficiency (අග්න්යාශයික එන්සයිම ඌනතාවය) පෙන්නුම් කළ හැකි අතර, gluten-ralated small-bowel disease (ග්ලූටන් ආශ්රිත කුඩා අන්ත්ර රෝග) සැක කරන විට coeliac blood tests (සීලියැක් රුධිර පරීක්ෂණ) භාවිතා කරයි.
මේද මලක් පෙනෙන්නේ කෙසේද?
මේද මළ, ස්ටisTrackorea ලෙසද හැඳින්වේ, සාමාන්යයෙන් සුදුමැලි, විශාල, තෙල් සහිත, අසාමාන්ය ලෙස දුර්ගන්ධයක් ඇති, සහ එළවළු අඩංගු වීම පමණක් නොව, සේදීමෙන් ඉවත් කිරීමට අපහසු වේ. මළ මුසු විය හැක, නමුත් මුසු වීම පමණක් රෝග විනිශ්චයක් නොවේ, මන්ද බඩවැල් වායූන්ටද මළ මුස් කිරීමට හැකිය. බර අඩු වීමත් සමඟ නැවත නැවත තෙල් සහිත මළ පහවීම, සායනික ඇගයීමක්, නිතර faecal elastase, අක්මා පරීක්ෂණ, පෝෂණ සලකුණු, සහ සමහර විට quantitative faecal fat testing ඇතුළත් විය යුතුය.
කාංසාව මළපහ තුළ නොපිසූ ආහාර ඇති කළ හැකිද?
ආතතිය මගින් බඩවැල් වේගයෙන් චලනය වීමට සලස්වන අතර, විශේෂයෙන්ම එය පාචනය, නිතර බඩ යන ස්වභාවය, කැෆේන් භාවිතය හෝ කඩිමුඩියේ ආහාර ගැනීම ඇති කරන විට, මළපහ තුළ ජීර්ණ නොවූ ආහාරවලට දායක විය හැක. වේගවත් චලනය නිසා ආහාර කුඩා කැබලිවලට බිඳීමට අඩු කාලයක් ඉතිරි වේ, එබැවින් එළවළු ප Україні and fibres හඳුනාගත හැකි ලෙස පැවතිය හැකිය. රුධිරය රතු වීම, කළු තාර වැනි මළපහ, 38.0°C ට වඩා උණ, රාත්රී පාචනය නැවැත්වීමට අපහසු වීම, හෝ අහම්බෙන් බර අඩු වීම ආතතිය මගින් පැහැදිලි කළ නොහැක.
මැලැක්සෝප්ෂන් පරීක්ෂා කරන්නේ කුමක්ද?
මැලabsorption සඳහා වන පරීක්ෂණ, සැක කෙරෙන හේතුව අනුව තෝරා ගනු ලැබේ, අතර සම්පූර්ණ රුධිර ගණනය, ට්රාන්ස්ෆෙරින් සංතෘප්තතාවය සහිත ෆෙරටින්, විටමින් B12, ෆෝලේට්, ඇල්බුමින්, කැල්සියම්, celiac serology, මළ මූත්රා එලාස්සේස්, සහ මළ මූත්රා කැල්ප්රොටෙක්ටින් ඇතුළත් විය හැකිය. මයික්රොග්රෑම්/ග්රෑම් 50 ට අඩු මළ මූත්රා කැල්ප්රොටෙක්ටින් බොහෝ විට වැඩිහිටියන් තුළ ක්රියාකාරී ගිනි අවුලුවන බඩවැල් රෝගය අඩු කරයි, අතර මයික්රොග්රෑම් 200 ට අඩු මළ මූත්රා එලාස්සේස්, අග්න්යාශයික බාහිර ස්රාවී ඌනතාවය අඟවනු ඇත. වෛද්යවරයෙකු විසින් මළ මූත්රා පෙනුම, ඖෂධ, ආහාර, බර ප්රවණතාවය, සහ වෛද්ය ඉතිහාසය සමඟ ප්රතිඵල අර්ථකථනය කළ යුතුය.
අදම AI බලයෙන් රුධිර පරීක්ෂණ විශ්ලේෂණය ලබාගන්න
තත්පර කිහිපයකින් ක්ෂණික හා නිවැරදි රසායනාගාර පරීක්ෂණ විශ්ලේෂණය සඳහා Kantesti විශ්වාස කරන ලොව පුරා මිලියන 2කට වැඩි පරිශීලකයන්ට එක්වන්න. ඔබගේ රුධිර පරීක්ෂණ ප්රතිඵල උඩුගත කර, තත්පර කිහිපයකින් 15,000+ ජෛව සලකුණු පිළිබඳ සවිස්තර අර්ථකථනය ලබාගන්න.
📚 යොමු කර ඇති පර්යේෂණ ප්රකාශන
ක්ලයින්, ටී., මිචෙල්, එස්., සහ වෙබර්, එච්. (2026). නිරාහාරව සිටීමෙන් පසු පාචනය, මළපහ වල කළු ලප සහ ආමාශ ආන්ත්රික රෝග මාර්ගෝපදේශය 2026. Kantesti AI වෛද්ය පර්යේෂණ.
ක්ලයින්, ටී., මිචෙල්, එස්., සහ වෙබර්, එච්. (2026). කාන්තා සෞඛ්ය මාර්ගෝපදේශය: ඩිම්බ මෝචනය, ආර්තවහරණය සහ හෝමෝන රෝග ලක්ෂණ. Kantesti AI වෛද්ය පර්යේෂණ.
📖 බාහිර වෛද්ය යොමු
⚕️ වෛද්ය වියාචනය
මෙම ලිපිය අධ්යාපනික අරමුණු සඳහා පමණක් වන අතර වෛද්ය උපදෙස් ලෙස නොසැලකේ. රෝග නිદાન සහ ප්රතිකාර තීරණ සඳහා සෑම විටම සුදුසුකම් ලත් සෞඛ්ය සේවා සපයන්නෙකුගෙන් උපදෙස් ලබාගන්න.
E-E-A-T විශ්වාස සංඥා
අත්දැකීම්
වෛද්යවරයා විසින් මෙහෙයවන ලද රසායනාගාර අර්ථකථන ක්රියාවලි පිළිබඳ සමාලෝචනය.
ප්රවීණතාව
සායනික සන්දර්භය තුළ ජෛව සලකුණු (biomarkers) හැසිරෙන ආකාරය පිළිබඳ රසායනාගාර වෛද්ය විද්යා අවධානය.
අධිකාරීත්වය
ආචාර්ය තෝමස් ක්ලයින් විසින් ලියන ලද අතර ආචාර්ය සාරා මිචෙල් සහ මහාචාර්ය ආචාර්ය හෑන්ස් වෙබර් විසින් සමාලෝචනය කරන ලදී.
විශ්වසනීයත්වය
අනතුරු ඇඟවීම් අඩු කිරීමට පැහැදිලි පසුකැඳවීම් මාර්ග සහිත සාක්ෂි-පාදක අර්ථකථනය.