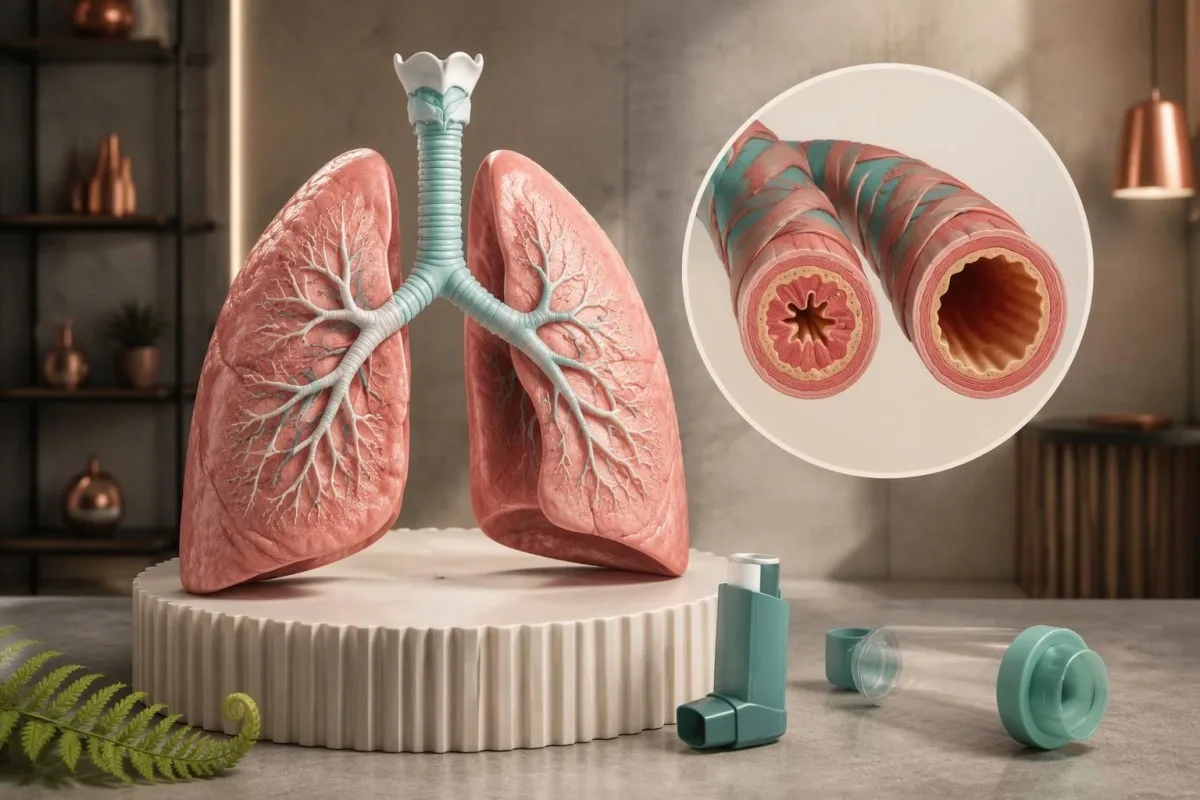
Asthma can cause changing breathlessness, nighttime cough or exercise symptoms—even when nobody hears a wheeze. Breathing tests matter more than an isolated laboratory result.

Punts essencials
- Asthma symptoms include variable wheezing, breathlessness, chest tightness and cough; having 1 symptom does not establish the diagnosis.
- Nighttime waking from asthma symptoms even once in the previous 4 weeks is a reason to review symptom control under the GINA assessment framework.
- Cough without wheezing can occur in cough-variant asthma, but cough lasting more than 8 weeks in adults has several other possible causes.
- Spirometry response of at least 12% and 200 mL in adult FEV1 after a bronchodilator supports variable airflow limitation under commonly used asthma criteria.
- Peak-flow variability averaging more than 10% over 2 weeks supports asthma in adults under GINA criteria; NICE uses a different diagnostic threshold.
- FeNO of at least 50 ppb in adults supports type 2 airway inflammation in the appropriate clinical context, but low FeNO does not exclude asthma.
- Eosinofils sanguins above 0.5 × 10^9/L can reflect allergy, asthma or other conditions; a blood result alone cannot confirm asthma.
- Signes respiratòris d’urgéncia include inability to speak normally, exhaustion, confusion, blue or grey lips, or poor response to the prescribed reliever; do not wait for a test result.
What are the early signs of asthma?
Asthma symptoms are changing episodes of wheezing, breathlessness, chest tightness or cough, often worse at night or after exercise; asthma can occur without obvious wheezing. Spirometry and peak-flow monitoring help demonstrate variable airflow limitation, whereas blood tests alone cannot confirm asthma. Severe breathing difficulty, confusion or a reliever that is not helping requires emergency care.
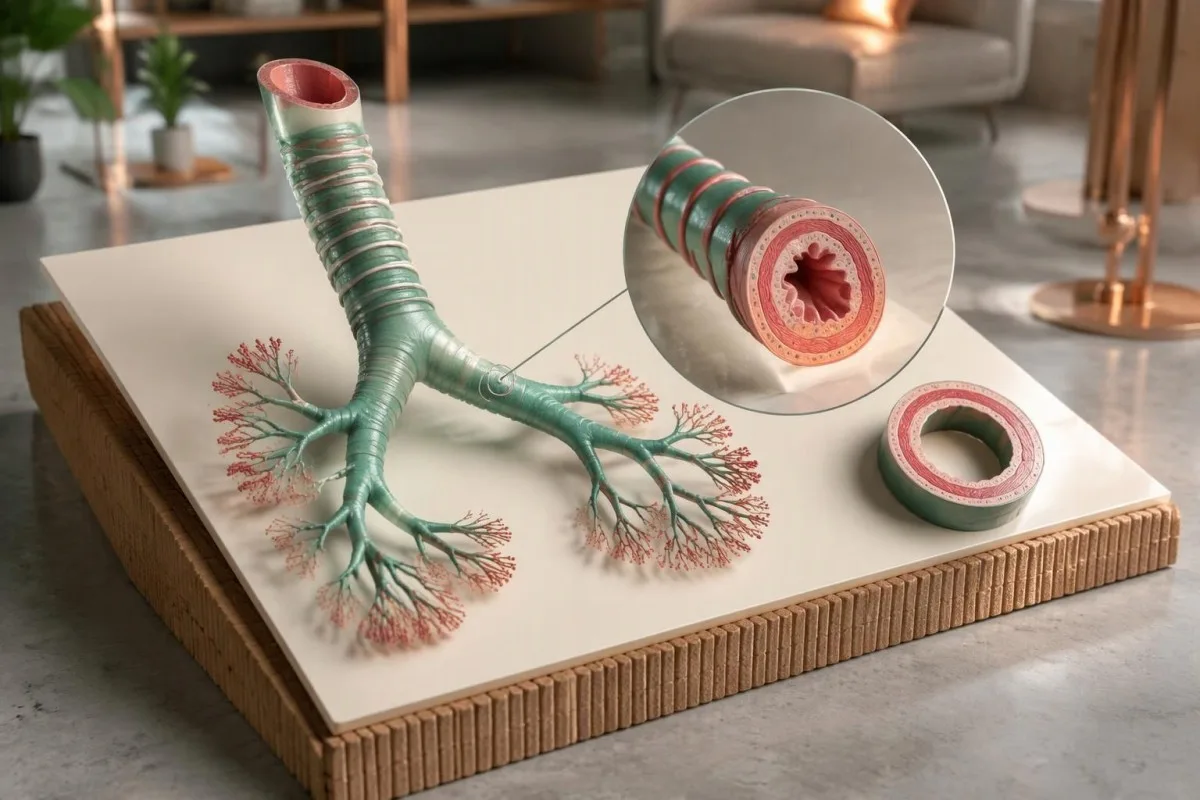
The early signs of asthma often involve a change from your usual breathing rather than a constant symptom: a familiar walk becomes harder, laughter starts a cough, or a cold leaves unusually prolonged chest symptoms. Record the pattern for 2 weeks if symptoms are mild and stable, but seek assessment sooner if breathing is worsening.
Symptom-free intervals do not rule out asthma. A person can have 3 comfortable days followed by tightness after cold-air exercise because airway sensitivity and exposure vary; similarly, a normal chest examination between episodes cannot establish that the airways always function normally.
A hypothetical 34-year-old might report coughing after running, waking twice in a week and feeling entirely well at work. That combination raises suspicion more than one isolated cough, but the next step is a clinical history and objective testing—not assuming that improvement after a borrowed inhaler proves asthma.
Kantesti es un Analizador de tèst de sang d'IA that helps explain supportive laboratory findings, not a substitute for measuring airflow. Our organizacion e ambit clinic distinguish laboratory interpretation from respiratory diagnosis: even 2 normal laboratory panels cannot exclude an intermittent breathing disorder.
Why are asthma symptoms at night more noticeable?
Asthma symptoms at night can become more noticeable because airway calibre and inflammatory activity follow daily rhythms, while bedroom allergens or reflux may add triggers. Under the GINA 2025 symptom-control assessment, any asthma-related nighttime waking during the previous 4 weeks warrants attention.

Nighttime cough is not automatically asthma. Cough after lying down with sour taste or regurgitation suggests another possible contributor, and our reflux symptom patterns explain why timing helps; 2 conditions can coexist, so identifying reflux does not necessarily explain every episode of breathlessness.
Repeated waking carries more information than the clock time alone. Write down the number of awakenings over 7 nights, whether you felt tightness or breathlessness, and whether your prescribed reliever helped; a cough at midnight after a meal differs from waking near dawn with difficulty exhaling.
GINA's 2025 strategy assesses daytime symptoms, nighttime waking, activity limitation and, where applicable, short-acting reliever use over 4 weeks. A person who sleeps poorly because of asthma should not interpret a normal daytime oxygen reading as evidence of good control, because oxygen saturation does not measure airway variability.
A bedroom diary can separate exposure from coincidence: note whether symptoms occur at home, away from home or after changing bedding during a 2-week period. Avoid deliberately re-exposing yourself to a suspected trigger; persistent waking deserves a treatment and inhaler-technique review rather than simply adding extra pillows.
Can asthma cause a cough without wheezing?
Asthma cough without wheezing is possible, particularly in cough-variant asthma, where cough may be the main symptom and routine spirometry can be normal. In adults, cough lasting more than 8 weeks requires evaluation for other causes as well as asthma.

Cough-variant asthma and non-asthmatic eosinophilic bronchitis can both cause chronic cough associated with eosinophilic airway inflammation. The distinction matters because the second condition typically lacks the variable airflow limitation or airway hyperresponsiveness characteristic of asthma; an elevated eosinophil count cannot distinguish these 2 diagnoses by itself.
A normal initial breathing test does not close the investigation when the symptom pattern remains convincing. Clinicians may repeat spirometry during symptoms or consider a supervised bronchial challenge, whereas coughing spells with vomiting or a relevant contact history may need whooping cough testing with attention to how many weeks have elapsed.
Medication review can identify an overlooked explanation for cough. An ACE inhibitor used for blood pressure can cause a dry cough even after months of treatment, so bring a complete medication list rather than focusing only on drugs started within the previous 2 weeks; do not stop prescribed treatment without advice.
The absence of wheezing has 2 very different meanings: mild asthma may produce no audible wheeze, while a severe attack may become quiet because too little air is moving. Quiet breathing combined with exhaustion, difficulty speaking or worsening breathlessness is an emergency—not evidence that the attack has ended.
How do exercise-triggered asthma symptoms behave?
Exercise-induced bronchoconstriction causes temporary airway narrowing during or after exercise, often becoming most noticeable within about 5–10 minutes after stopping. Exercise symptoms alone do not prove asthma, because laryngeal obstruction, anaemia and other conditions can also limit breathing.

Exercise-related laryngeal obstruction often causes throat tightness or noisy breathing during inhalation at peak effort, then settles relatively quickly after stopping. Bronchoconstriction more often affects expiration and recovery; these are clues rather than absolute rules, and the 2 conditions can occur in the same person.
A supervised exercise challenge measures airflow rather than relying on whether exercise feels difficult. A fall in FEV1 of more than 10% and more than 200 mL after exercise supports asthma in adults under GINA's diagnostic framework; local protocols and criteria for exercise-induced bronchoconstriction may differ.
Reduced exercise tolerance without cough, tightness or variable wheeze deserves a broader assessment. Our iron stores in athletes guide explains why a hypothetical runner with ferritin of 12 ng/mL may need an iron assessment, but that result would not explain away independently documented airway narrowing.
An exercise diary should include intensity, weather and whether symptoms peak during activity or 10 minutes afterward. Once assessed, many people can remain active using a clinician-agreed plan; avoid testing your limits during an unstable period or repeatedly using a reliever without reviewing the underlying treatment.
Which triggers commonly bring on asthma symptoms?
Asthma triggers include respiratory viruses, pollen, dust mites, animal allergens, smoke, air pollution, cold air and exercise. A 2-week exposure diary can suggest patterns, but a suspected trigger is not the same thing as a confirmed allergy or a diagnosis of asthma.

Allergy testing identifies sensitisation, not necessarily the cause of every breathing episode. A positive specific IgE result to 1 allergen becomes clinically useful when exposure reliably matches symptoms; our los tests d'alergia per component guide explains why more detailed panels still require a relevant history.
Damp buildings can worsen respiratory symptoms through several mechanisms, including allergen exposure and irritation. There is no single laboratory panel that establishes 'mould-related asthma'; our mould testing limitations distinguish targeted allergy assessment from unsupported broad testing, and symptoms should be evaluated even when 1 panel is normal.
Work-related asthma can appear after months or years of exposure and may improve on weekends or holidays. Record work tasks and breathing measurements across both work and non-work days for an occupational assessment; a specialist may need more than the standard 2-week diagnostic diary, and intentional exposure challenges are unsafe.
Some beta-blockers, including certain eye drops, can worsen bronchoconstriction, while aspirin or other NSAIDs trigger symptoms in a susceptible subgroup rather than everyone with asthma. Review all medications, including over-the-counter products, during 1 appointment; do not stop cardiovascular drugs or attempt a home aspirin challenge.
What else can look like asthma?
Asthma-like symptoms can result from reflux, upper-airway disorders, COPD, anaemia, cardiac disease or respiratory infection. At least 2 separate conditions may contribute, so persistent symptoms despite appropriate asthma treatment should prompt reassessment rather than automatic dose escalation.

Wheeze limited to one area or symptoms beginning suddenly after choking suggest focal airway obstruction rather than typical diffuse asthma. The finding deserves clinical assessment, particularly in a child; a single persistent wheeze has a different diagnostic meaning from episodes that change with several unrelated triggers.
Fixed obstruction on repeated spirometry does not automatically mean COPD, because longstanding asthma can also leave persistent airflow limitation. Smoking history, age and previous lung disease help distinguish causes, while early emphysema or a strong family history may justify alpha-1 antitrypsin assessment rather than assuming 1 diagnostic label explains everything.
Recurrent chest infections, poor growth or a chronic productive cough in a young person should widen the investigation. A sweat chloride result of at least 60 mmol/L supports cystic fibrosis in the appropriate diagnostic setting; values of 30–59 mmol/L require further evaluation rather than being treated as an asthma result.
New breathlessness with chest pressure, fainting or inability to lie comfortably needs timely assessment for non-asthma causes. Even 1 abrupt episode of unexplained breathlessness can be urgent, and attributing symptoms to anxiety before checking relevant respiratory and cardiac possibilities risks missing a treatable condition.
How does spirometry support an asthma diagnosis?
Spirometry measures airflow, including FEV1 and FVC, and can show obstruction that improves after a bronchodilator. An adult FEV1 increase of at least 12% and 200 mL supports variable airflow limitation under commonly used asthma criteria, but a negative test does not exclude intermittent asthma.

The FEV1/FVC ratio helps identify obstruction, but interpretation should use an age-appropriate lower limit of normal rather than applying 0.70 to every patient. The European Respiratory Society adult diagnostic guideline recommends spirometry and bronchodilator testing within a structured assessment, followed by additional tests when necessary (Louis et al., 2022).
Consider a hypothetical result: FEV1 rises from 1.90 L to 2.18 L after the test medication. The increase is 280 mL and 14.7% of the starting value, meeting the commonly used adult reversibility criterion; the finding supports asthma when the history fits, but it is not a diagnosis detached from clinical context.
Guidelines and laboratory reporting standards do not always express reversibility in the same way. NICE NG245 also accepts an adult FEV1 increase of at least 10% of predicted normal; if predicted FEV1 is 3.40 L, that same 280 mL improvement is only 8.2% of predicted, explaining why 2 reporting conventions can produce different flags.
Testing quality matters: spirometry usually seeks at least 3 acceptable manoeuvres, and adult repeatability commonly requires the best FEV1 values to be within 150 mL. Our breathlessness laboratory guide explains complementary investigations, but no laboratory interpretation can compensate for an unreliable breathing manoeuvre.
How can a peak-flow diary help diagnose asthma?
Peak-flow monitoring can document variable breathing when spirometry is unavailable or initially inconclusive. GINA uses average daily variability above 10% in adults and above 13% in children over 2 weeks as supportive evidence; NICE NG245 uses a 20% diagnostic threshold in its pathway.

Use the same meter and technique each time, usually measuring morning and evening as instructed. Perform 3 blows per session and record the highest acceptable reading in L/min; note symptoms and medication timing, because taking a bronchodilator before one session but not the other can distort the comparison.
Daily variability can be calculated as the highest minus the lowest reading divided by their mean, multiplied by 100. If a hypothetical day's readings are 380 and 460 L/min, variability is 80/420 × 100, or 19.0%; the diagnostic assessment uses the average across the monitoring period, not that single day's percentage.
Peak-flow action zones and diagnostic variability answer different questions. A personalised plan may use at least 80% of personal best, 50–79%, and below 50% to guide action, whereas diagnosis examines fluctuations over time; a low personal best should not be accepted as normal without checking technique and clinical status.
Kantesti es un plataforma d’interpretacion d’analisi de sang d’AI, not a service for confirming asthma from a 2-week breathing diary. Our AI report safety checks explain why readers should distinguish a recorded value, an automated explanation and a clinician's diagnosis—particularly when different guidelines use different thresholds.
What do FeNO and eosinophils tell you about asthma?
FeNO measures nitric oxide in exhaled breath, while blood eosinophils measure an inflammatory cell population; both can support assessment of type 2 asthma. NICE NG245 uses FeNO of at least 50 ppb in adults and at least 35 ppb in children aged 5–16 within its diagnostic pathways.
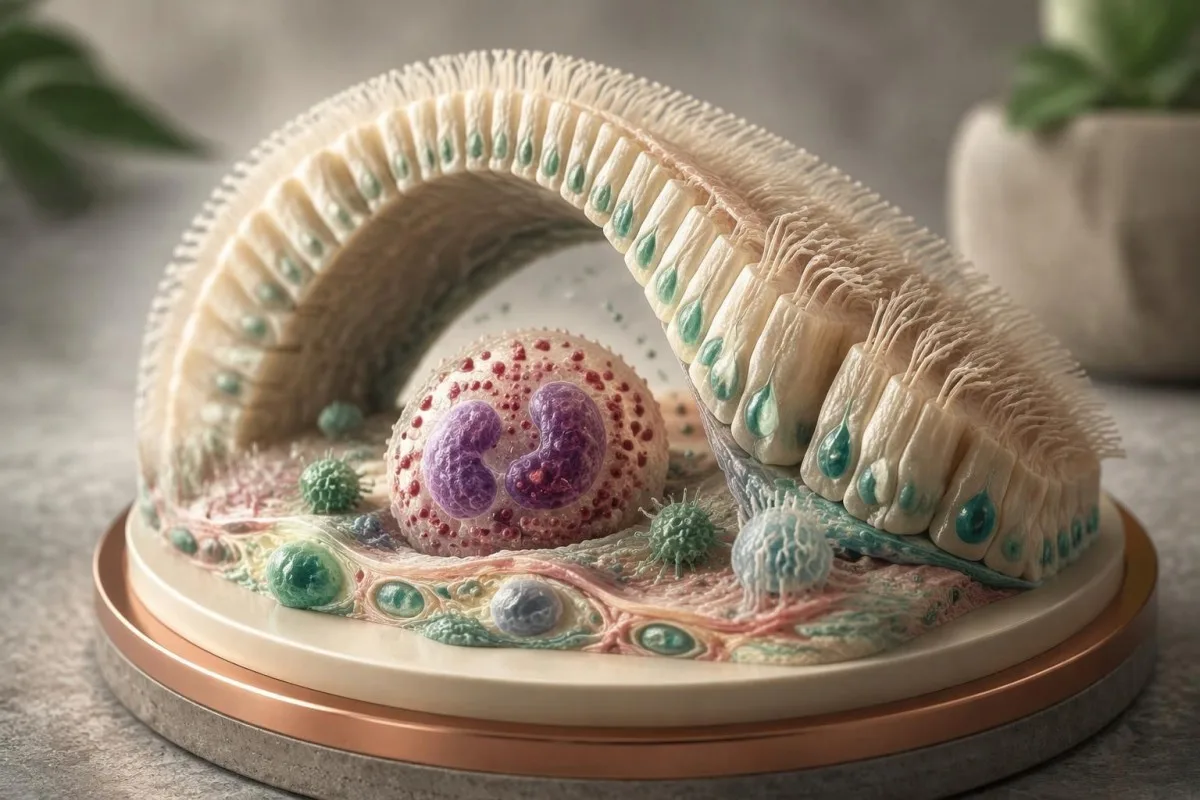
The NICE/BTS/SIGN 2024 guideline allows an elevated blood eosinophil count above the laboratory reference range or FeNO of at least 50 ppb to establish an adult diagnosis within its suggestive-history pathway. This does not mean a blood test alone confirms asthma: the recommendation depends on clinical assessment, and GINA places greater emphasis on documenting variable airflow limitation.
A low FeNO reading does not rule out asthma, particularly after inhaled corticosteroid treatment or in non-type-2 disease. Allergic rhinitis can raise FeNO without proving lower-airway asthma, so a hypothetical reading of 60 ppb with nasal symptoms but no compatible breathing history needs a different interpretation from 60 ppb with recurrent nocturnal tightness.
Eosinophil counts above 0.5 × 10^9/L, equivalent to 500 cells/µL, commonly attract attention, although laboratories use different upper limits. Our high eosinophil interpretation explains why persistent counts of at least 1.5 × 10^9/L require broader evaluation for medications, parasites and other disorders—not simply a stronger asthma label.
Steroid timing can change both FeNO and eosinophil results, sometimes making 2 tests taken weeks apart look inconsistent. Our estandards d'interpretacion clinica support reporting such limitations; tell the clinician when you last used inhaled or oral steroids, but never stop treatment just to make a test more likely to turn positive.
Why can't blood tests alone confirm asthma?
Blood tests alone cannot confirm asthma because they do not demonstrate variable airflow limitation or reliably distinguish asthma from every alternative cause of cough. Even 1 markedly abnormal eosinophil or IgE result needs a compatible history and an appropriate diagnostic pathway.
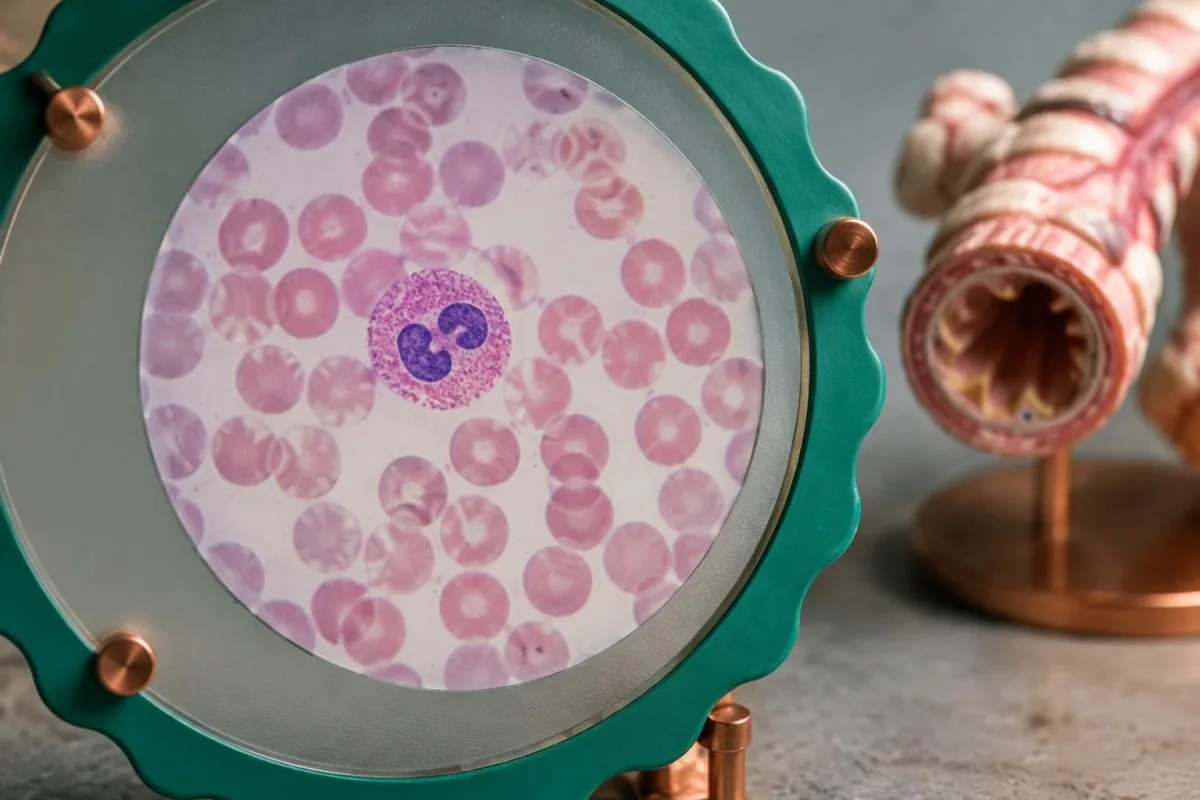
Total IgE and allergen-specific IgE are different measurements: one reflects an overall antibody concentration, while the other tests sensitisation to selected allergens. There is no universal total-IgE cutoff that diagnoses asthma across adults and children; a positive result to 1 allergen may explain sensitisation without proving that exposure causes wheeze.
A CBC may identify anaemia that contributes to breathlessness, and selected inflammatory tests may help assess a suspected infection. Our comparason globuls blancs e CRP explains why these markers can disagree; an elevated CRP of 25 mg/L is not an asthma threshold and cannot independently determine whether antibiotics are needed.
Kantesti AI can help readers compare eosinophil counts, haemoglobin and other reported markers, but it cannot establish variable airflow limitation from a laboratory PDF. A hypothetical eosinophil change from 0.62 to 0.18 × 10^9/L after steroid treatment may reflect treatment exposure rather than the disappearance of asthma.
Routine asthma diagnosis does not require ordering every available inflammatory marker. Bring existing results and a medication timeline covering at least the previous 2 weeks; clinicians can then select tests for a specific question, such as anaemia, allergy or treatment planning, instead of treating a large panel as a substitute for breathing assessment.
Which breathing warning signs require emergency care?
Apelatz immediatament los servicis d'escasença for severe breathlessness, inability to speak normally, blue or grey lips, confusion, drowsiness, exhaustion or a prescribed reliever that is not helping. If available, peak flow below 50% of personal best or oxygen saturation of 92% or less with acute symptoms adds urgency; do not wait for either measurement.

A quiet or 'silent' chest during worsening breathing can indicate critically reduced air movement, not recovery. Peak flow below 33% of personal best is a life-threatening feature in UK acute-asthma frameworks, but inability to obtain a reading because of severe breathlessness is itself concerning; call the local emergency number, such as 999 or 112 where applicable.
While help is coming, sit upright and use your prescribed reliever according to your written action plan or emergency-dispatch instructions. Do not drive yourself, and do not delay the call to perform repeated peak-flow tests; even 1 episode of confusion or marked exhaustion can signal that self-management is no longer safe.
An oxygen reading does not measure carbon dioxide, and home devices can be inaccurate because of movement, cold fingers or other factors. Our arterial gas interpretation explains why a normal or rising PaCO2 near or above 45 mmHg during severe acute asthma can concern clinicians when vigorous breathing would usually lower it.
Sudden breathlessness with chest pain, coughing up blood or unilateral leg swelling may indicate another emergency; our urgent leg clot signs explain that connection. Breathing difficulty with tongue or throat swelling after an exposure can be anaphylaxis: use a prescribed adrenaline auto-injector immediately and call emergency services, because 1 asthma inhaler does not replace anaphylaxis treatment.
How are asthma symptoms assessed in children?
Children's asthma symptoms may include nighttime cough, wheeze, reduced play or breathlessness rather than a clear description of chest tightness. Objective testing is often possible from about age 5, while younger children usually need a pattern-based assessment and monitored treatment response.
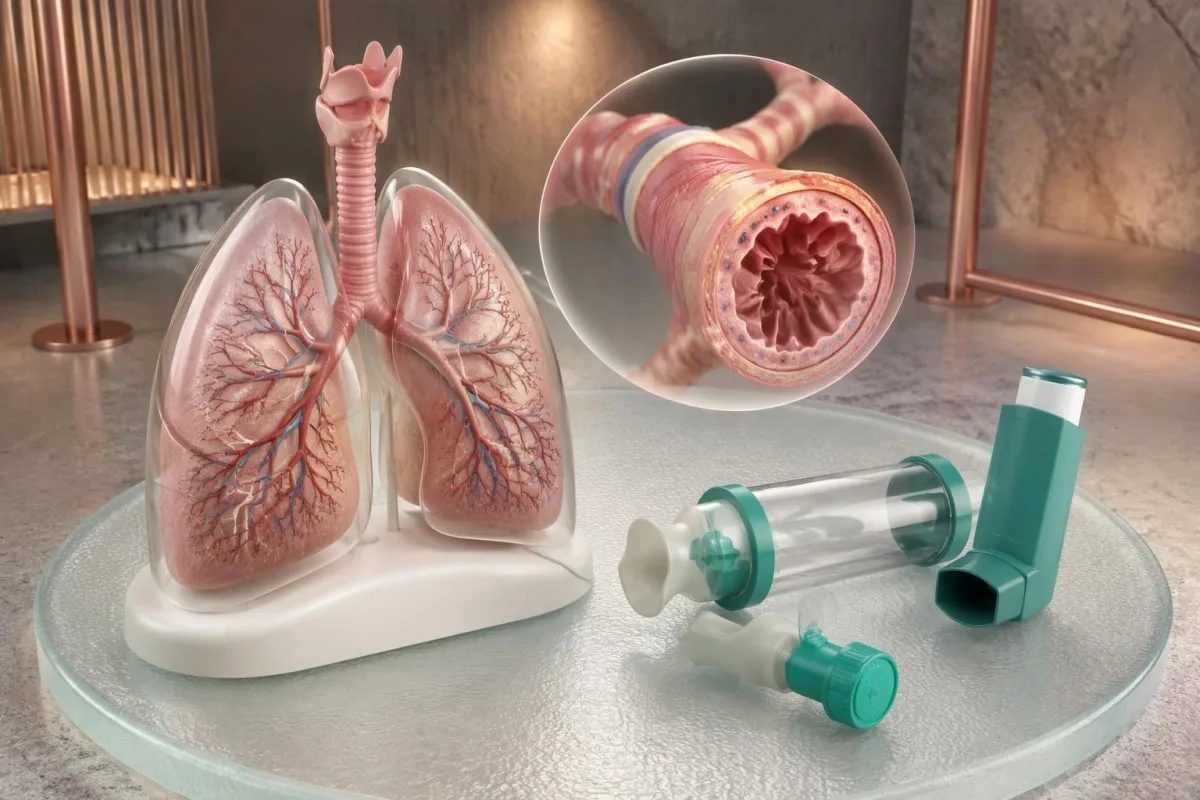
Preschool viral wheeze is not identical to established persistent asthma. Clinicians consider whether symptoms occur only during colds or also between illnesses, along with allergy history and family risk; 2 children who wheeze with the same virus can have different longer-term patterns, so a permanent label should not rest on one episode.
A treatment trial in a child younger than 5 may be assessed over approximately 8–12 weeks under NICE guidance, depending on the presentation. Improvement needs to be interpreted alongside adherence, device technique and natural recovery from a virus; a treatment response is useful evidence, but it is not an isolated laboratory-style confirmation.
Children's spirometry requires age-appropriate interpretation and coaching, not adult thresholds pasted onto smaller lungs. GINA uses an FEV1 increase of at least 12% of predicted in children as a supportive bronchodilator criterion, and a technically poor test may need repetition even if the report prints a reassuring percentage.
Nòstre children's laboratory safety guide explains why age-specific ranges matter without replacing respiratory assessment. In a child, marked chest recession, inability to drink or speak normally, unusual sleepiness or worsening breathing warrants urgent help; even 1 such sign outweighs a normal previous test.
What should you bring to an asthma assessment?
Prepare for an asthma assessment by bringing your symptom pattern, medication list, inhaler devices and any previous breathing or laboratory results. A 2-week diary of symptoms, exposures and clinician-requested peak-flow readings is often more useful than a long list of unrelated tests.

Ask the testing service which inhalers, if any, should be withheld and for how long before spirometry. Instructions vary by medication and test purpose, so do not assume a universal 12-hour rule; if symptoms worsen while following preparation instructions, use needed treatment and contact the service rather than prioritising an ideal test.
Bring the actual inhaler and spacer so a clinician can observe technique rather than relying on a description. Different devices require different inhalation patterns, and 1 correct demonstration can reveal why a prescribed treatment seemed ineffective; poor technique can look like resistant disease even when the medication choice is appropriate.
Kantesti es un Outil d’analisi de sang amb IA that can help explain accompanying laboratory reports while the clinician evaluates breathing symptoms. Our guia de tecnologia amb IA describes the interpretation workflow, but an estimated processing time of about 60 seconds should never be confused with the time needed to establish a respiratory diagnosis.
Share only the information needed for the assessment, particularly when organising results for another family member. Our informacions sus la confidencialitat e las donadas explains handling considerations; keep symptom diaries and original reports available for clinical review, and do not let uploading 1 document delay urgent care or a necessary breathing appointment.
Research publications and evidence behind asthma testing
Asthma diagnostic evidence comes primarily from respiratory guidelines and studies of airflow, airway responsiveness and inflammatory markers. The 3 external references below directly support this article; the 2 Zenodo laboratory guides are separate educational resources and are not studies validating asthma diagnosis.

GINA's 2025 strategy links a characteristic symptom history with evidence of variable expiratory airflow limitation, while the 2024 NICE/BTS/SIGN guideline specifies a different sequence of objective tests. The European Respiratory Society adult guideline supplies a third structured approach (Louis et al., 2022); comparing all 3 helps explain why clinicians may reasonably order tests in different sequences.
Los documents de Kantesti guia RDW e globuls roges provides background when a CBC raises a separate question about anaemia and breathlessness. Its Zenodo DOI identifies that publication, not proof that RDW diagnoses asthma; even 2 abnormal red-cell indices must be interpreted as haematology findings rather than measurements of airway narrowing.
Lo guida d'interpretacion del rapòrt renal addresses BUN, creatinine and clinical context rather than asthma symptoms. Its separate Zenodo DOI is included for publication transparency, and neither of these 2 laboratory guides establishes the sensitivity, specificity or effectiveness of an asthma diagnostic pathway.
Nòstre nòrmas de contengut medical distinguish guideline-supported facts from educational examples and product descriptions. Kantesti does not claim that these 2 DOI resources validate asthma detection; uncertain symptoms need clinical assessment, and emergency breathing warning signs require immediate action regardless of how recently a report was interpreted.
Preguntes més freqüents
Quins son los primièrs signes de l’asma chez los adultes ?
Los primièrs signes de l’asma en los adultes comprenon sovent una alteracion de l’alenada, una sensacion d’opression toracica, de siblaments o una tos que s’agreuja la nuèch o aprèp l’exercici. Una periòda sens simptòmas exclutz pas l’asma, perque la limitacion del flus d’aire pòt variar d’un jorn a l’autre. Un diari dels simptòmas sus 2 setmanas pòt ajudar un professional de santat a identificar de tendéncias quand los simptòmas son leugièrs e estables. Una espirometria o un autre examen objectiu adaptat es necessari per confirmar lo diagnostic, e una agravacion de la respiracion deu èsser avalorada mai lèu.
Can you have asthma without wheezing?
Asthma can occur without audible wheezing, particularly when cough is the main symptom or when symptoms are absent during an examination. Adult cough lasting more than 8 weeks needs assessment for asthma and other causes, including reflux, medication effects and non-asthmatic eosinophilic bronchitis. Normal initial spirometry may lead to repeat testing or a supervised bronchial challenge if suspicion remains. A quiet chest during severe breathlessness is different: it can indicate dangerously low airflow and requires emergency help.
Why does asthma get worse at night?
Asthma can worsen at night because airway function follows daily rhythms and bedroom allergens or reflux may add triggers. GINA's symptom-control assessment treats any asthma-related nighttime waking in the previous 4 weeks as a reason to review control. Record awakenings, breathing symptoms and prescribed reliever use rather than assuming every nighttime cough is asthma. Repeated waking should prompt a clinical review, while severe breathing difficulty requires emergency care.
Can a blood test tell if you have asthma?
A blood test alone cannot confirm asthma because it does not demonstrate variable airflow limitation or exclude all other causes of breathing symptoms. Eosinophils above 0.5 × 10^9/L can occur with asthma, allergies, medications or other disorders. NICE NG245 allows elevated eosinophils to establish an adult diagnosis within a suggestive-history pathway, but that is a clinical algorithm—not interpretation of an isolated blood result. Clinicians may also use spirometry, FeNO, peak-flow monitoring or bronchial challenge according to the presentation and local guidance.
Can you have asthma with normal spirometry?
Normal spirometry does not exclude asthma because airway narrowing can be intermittent or suppressed by treatment. Clinicians may repeat spirometry during symptoms, arrange twice-daily peak-flow measurements for 2 weeks or request a supervised bronchial challenge. An adult FEV1 improvement of at least 12% and 200 mL after a bronchodilator supports variability under commonly used criteria. Preparation instructions depend on the medication and test, so never stop an inhaler without specific clinical advice.
When should asthma symptoms be treated as an emergency?
Asthma symptoms require emergency help when breathing is severe, normal speech is difficult, the person becomes exhausted or confused, lips appear blue or grey, or the prescribed reliever is not helping. Peak flow below 50% of personal best or oxygen saturation of 92% or less with acute symptoms adds concern, but emergency action should not wait for measurements. Sit upright, call the local emergency number and use the prescribed reliever according to the written plan or dispatcher instructions. Do not drive yourself, and treat a quiet chest with worsening breathlessness as a warning rather than reassurance.
Fasètz-vos explicar los resultats analisi de sang
Telecargatz vòstre compte rendut de laboratòri e l’IA de Kantesti explica cada biomarcador en lenga simpla en qualques segondas. Utilizat per mai de 2 milions de personas dins lo mond.
Referéncias
- Klein, T., Mitchell, S., & Weber, H. (2026). Analisi de sang RDW: guida completa de RDW-CV, MCV e MCHC. Recèrca medicala per IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Explicacion del rapport BUN/Creatinina : Guia de test de foncion renal. Recèrca medicala per IA de Kantesti. DOI
- Global Initiative for Asthma (2025). Global Strategy for Asthma Management and Prevention. GINA Strategy Report.
- National Institute for Health and Care Excellence, British Thoracic Society, and Scottish Intercollegiate Guidelines Network (2024). Asthma: diagnosis, monitoring and chronic asthma management (BTS, NICE, SIGN). NICE Guideline NG245.
- Louis R et al. (2022). European Respiratory Society guidelines for the diagnosis of asthma in adults. European Respiratory Journal. DOI
- 2M+Tèsts analisats
- 127+Païses
- 100+Lengas
A prepaus de l’equipa medicala


Senhals de confiança E-E-A-T
Experiéncia
Revisión clinica menada pel metge de las practicas d’interpretacion de las analisis.
Expertisa
Fòcus sus la medicina de laboratòri sus cossí los biomarcadors se comportan dins un contèxte clinic.
Autoritat
Revisat medicalament pel Dr Thomas Klein, amb de contribucions de la Dr Sarah Mitchell e del Prof. Dr Hans Weber.
Fisança
Interpretacion basada sus d’evidéncias amb de camins de seguiment clars per reduzir l’alarmisme.




Avís medical
Aqueste article es solament per tòcas educatius e constituís pas de conselh medical. Consultatz totjorn un professional de la sant qualificat per las decisions de diagnostica e de tractament.
Publicat · Contactar l’equipa editoriala
Publicat per Kantesti Ltd, enregistrada en Anglatèrra e País de Galas, n° d’entrepresa. 17090423, Londres, Reialme Unit.
