A negative neurocysticercosis test does not rule out a single brain cyst or calcified disease. CT, MRI, and urgent assessment of new seizures matter more than reassurance from antibody testing alone.

핵심 요점
- 음성 항체 do not exclude neurocysticercosis, especially when imaging shows only 1 affected area or calcifications.
- Reference-laboratory EITB can approach 98% sensitivity with more than 1 viable cyst, but performance is substantially lower with a single cyst.
- Single-cyst sensitivity is often approximately 50–60% in published EITB estimates; these figures do not apply to every commercial antibody assay.
- Noncontrast CT is particularly useful for small calcifications, which are often approximately 1–4 mm across.
- MRI evaluates viable cysts, surrounding edema, and ventricular or subarachnoid disease; specialized 3-dimensional sequences may improve detection.
- First seizures require urgent medical assessment regardless of the antibody result. Call emergency services for a first known seizure or other emergency features.
- Five minutes is an emergency threshold for an ongoing convulsive seizure, not a reason to wait before seeking help.
- Calcified-only disease generally does not need antiparasitic medication, but seizure treatment and further imaging may still be necessary.
Can a negative neurocysticercosis test rule it out?
A negative neurocysticercosis test cannot reliably exclude the disease, particularly with 1 brain cyst or calcified remnants. Antibody testing measures the immune response rather than directly inspecting the brain; CT and MRI establish the location and stage of suspicious findings, while a first seizure requires urgent assessment.

The result is conditional, not absolute. A cysticercosis antibody test that performs well in people with several viable cysts may perform poorly in someone with just 1 small affected area, so the word 음성 means no detectable response on that assay—not no cysts anywhere in the nervous system.
For a hypothetical example, consider a 34-year-old with a first seizure, a negative antibody report, and a solitary ring-enhancing finding on MRI. The report cannot settle whether that finding represents cysticercosis, another infection, or a noninfectious process; its meaning depends on the scan, exposure history, and neurological assessment together.
칸테스티는 AI 혈액검사 분석기 that can help explain reported laboratory findings, but it cannot exclude brain disease from 1 negative antibody result. Our organization and mission explain our laboratory-information focus; readers should not treat an automated report explanation as clearance to delay seizure care.
Why can antibody testing miss a single brain cyst?
A single cyst can produce an antibody response below the assay's detection threshold. Published reference-laboratory EITB estimates often place sensitivity near 50–60% for a single cyst, compared with approximately 98% when more than 1 viable cyst is present; the difference reflects disease burden and assay performance.
The IDSA/ASTMH guideline recommends enzyme-linked immunoelectrotransfer blot, or EITB, as confirmatory serology and explicitly warns that sensitivity is poor with a single parenchymal finding or calcifications alone (White et al., 2018). High sensitivity reported for patients with multiple cysts, ventricular disease, or subarachnoid disease should not be transferred to someone with 1 small cerebral abnormality.
Imagine, purely for illustration, that an assay has 55% sensitivity in 100 people whose single-cyst disease has already been established independently. Approximately 45 would test negative despite having the condition; this worked example explains missed detection, not the probability that any particular negative result represents disease.
Repeating the same assay after 2 weeks may not correct a weak response caused by low disease burden. That differs from infections in which early sampling is the main problem, as explained in our timing-related false-negative guide; ask whether imaging or a better-characterized assay would change the next decision.
Why can calcified neurocysticercosis remain symptomatic?
Calcified neurocysticercosis can cause seizures despite negative antibodies, because the remaining mineralized focus can still be associated with local irritation and episodic surrounding edema. Typical calcifications may measure approximately 1–4 mm, but their small size does not establish whether they are clinically harmless.
A calcification is generally a remnant rather than a living cyst that antiparasitic medication can eliminate. In the IDSA/ASTMH guideline, calcified-only parenchymal disease is managed symptomatically rather than with antiparasitic drugs; a person with 1 calcified focus and seizures may therefore need antiseizure treatment without needing cyst-killing medication (White et al., 2018).
Surrounding edema can appear intermittently, sometimes long after the original cyst has degenerated. MRI may show this tissue response even when the calcification is more obvious on CT, which is why the 2 scans can tell different but compatible stories rather than one proving that the other is wrong.
Neither a negative antibody result nor a persistent positive result measures seizure risk by itself. The broader lesson resembles other seronegative neurological conditions, discussed in our negative neurological antibody results guide: absence of detectable antibodies is not equivalent to absence of a clinically relevant neurological process.
Which cysticercosis antibody test was actually performed?
The useful first question is whether the report describes EITB, ELISA, or another antibody method, because these are not interchangeable tests. A negative index below 1 laboratory's cutoff cannot inherit the performance figures of a different reference-laboratory assay, even when both reports use the name cysticercosis IgG.

EITB using purified parasite glycoproteins is the preferred serological method in the IDSA/ASTMH guideline, while crude-antigen ELISA methods have recognized sensitivity and specificity limitations (White et al., 2018). Before comparing 2 results, check the method, specimen type, reference interval, and whether the laboratory used a validated confirmatory procedure.
Some laboratories report a qualitative result; others provide an optical-density ratio or numerical index. A value such as 0.8 in a hypothetical assay does not represent 0.8 cysts, an 80% disease probability, or a universal severity score—our 정성 및 정량 결과 guide explains that distinction.
Kantesti AI's role is to help readers preserve the laboratory's original wording rather than reinterpret 1 method through another method's thresholds. Our 실험실 마커 가이드 provides broader report-reading context; for this result, keep the actual assay name available when discussing referral or repeat testing.
How does exposure history change diagnostic suspicion?
Neurocysticercosis follows ingestion of Taenia solium eggs, usually through fecal contamination from a person carrying the intestinal tapeworm. Eating undercooked pork can cause intestinal taeniasis, but brain cysts arise through a different transmission step; symptoms may emerge years after exposure rather than within 1 recent trip.

A vegetarian can develop cysticercosis because eggs can contaminate food or hands independently of meat consumption. Useful history includes past residence, household contacts, sanitation conditions, and possible exposure to a tapeworm carrier; asking only about meals eaten during the last 2 weeks can miss the relevant background.
A negative stool examination does not exclude cysts in the brain. Stool testing addresses intestinal tapeworm carriage, whereas CT and MRI assess nervous-system findings; these are 2 different sites and clinical questions, although public-health teams may recommend evaluating contacts when a carrier could be involved.
Normal eosinophils also cannot exclude neurocysticercosis, and raised eosinophils do not identify the brain as the affected site. Our parasite antibody interpretation guide discusses a separate parasite with similar localization limits; the practical point is to avoid using 1 routine cell count as a substitute for targeted neurological evaluation.
When do new seizures need emergency assessment?
A first known seizure needs urgent medical assessment regardless of antibody results, and emergency services should be contacted for a first seizure or an ongoing seizure with concerning features. A convulsive seizure lasting 5 minutes, repeated seizures without recovery, breathing difficulty, pregnancy, or significant injury requires emergency care.

Do not wait for the 5-minute mark to seek help after a first known seizure. Keep the person away from hazards, cushion the head if safely possible, do not restrain them or put anything in their mouth, and place them on their side once convulsions stop if they are breathing normally.
Persistent confusion, a severe new headache, fever with neck stiffness, or new weakness increases concern for causes beyond cysticercosis. Sudden one-sided weakness or speech difficulty also demands emergency assessment, as our 뇌졸중 경고 징후 안내 explains; 1 negative infection test cannot rule out stroke, meningitis, or a structural brain problem.
After a suspected seizure, stop driving and avoid swimming alone, heights, or operating machinery until a clinician provides advice consistent with local rules. If a witness can safely record the duration and describe movements or recovery, those observations may be more useful than ordering a second antibody test before the first neurological assessment.
What does CT add to neurocysticercosis diagnosis?
Noncontrast CT is particularly useful for detecting calcified cyst remnants, including small approximately 1–4 mm foci that MRI may show less clearly. CT also helps assess urgent structural problems such as hydrocephalus, but 1 isolated calcification is not automatically proof of neurocysticercosis or the cause of a seizure.
Calcium appears dense on CT, allowing radiologists to identify mineralized remnants and describe their distribution. The IDSA/ASTMH guideline recommends both MRI and noncontrast CT when classifying newly diagnosed neurocysticercosis, because the 2 modalities have complementary strengths rather than being interchangeable alternatives (White et al., 2018).
An incidental calcification needs context: previous granulomatous disease, other causes of mineralization, and scan appearance can influence interpretation. If 1 calcification sits near a suspected seizure focus, concordance with symptoms and EEG may strengthen the explanation, but anatomical proximity alone cannot establish causation.
A laboratory marker used in selected head-injury pathways does not test for brain cysts or replace imaging after an unexplained seizure. Our head-injury CT decisions guide illustrates that narrower setting; ask the clinician whether the present question requires noncontrast CT, contrast imaging, MRI, or a combination of 2 modalities.
What does MRI reveal that CT may miss?
MRI is better suited to evaluating viable cysts, surrounding edema, and many ventricular or subarachnoid findings. Specialized 3-dimensional sequences such as CISS or FIESTA can improve visualization of cyst membranes within cerebrospinal fluid spaces, where a cyst may otherwise resemble the surrounding fluid.
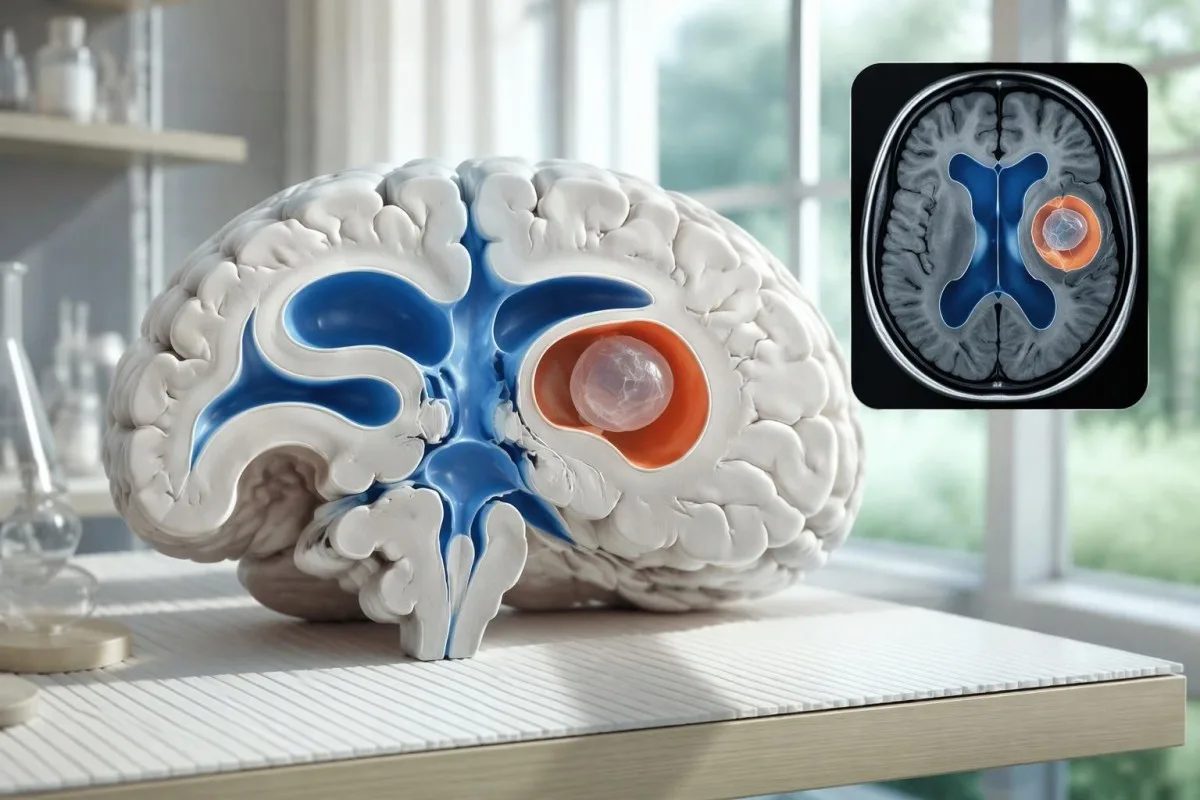
A cyst inside the ventricles can obstruct cerebrospinal fluid flow and cause hydrocephalus even without numerous parenchymal cysts. Headache with vomiting, declining alertness, or new visual symptoms therefore changes urgency; 1 reassuring antibody result should not override symptoms that suggest raised pressure or impaired fluid circulation.
MRI may show a scolex, the small internal structure of the parasite, inside a compatible cyst. This finding can be highly specific when confidently identified, whereas ring enhancement alone has a broader differential; our brain imaging warning signs guide explains why structural abnormalities require interpretation rather than diagnosis from 1 visual feature.
A routine MRI protocol may not answer every cysticercosis question. If ventricular or subarachnoid disease is suspected, discuss whether thin-section 3-dimensional imaging is needed; radiologists choose sequences and contrast according to the clinical question, and a normal scan using 1 protocol does not prove every possible disease compartment has been adequately assessed.
How is neurocysticercosis diagnosed when tests disagree?
Neurocysticercosis diagnosis combines imaging, clinical findings, exposure information, and supporting tests, rather than requiring a positive antibody result in every case. The revised diagnostic criteria published in 2017 give characteristic neuroimaging findings a central role and distinguish strong evidence from less-specific supportive features (Del Brutto et al., 2017).
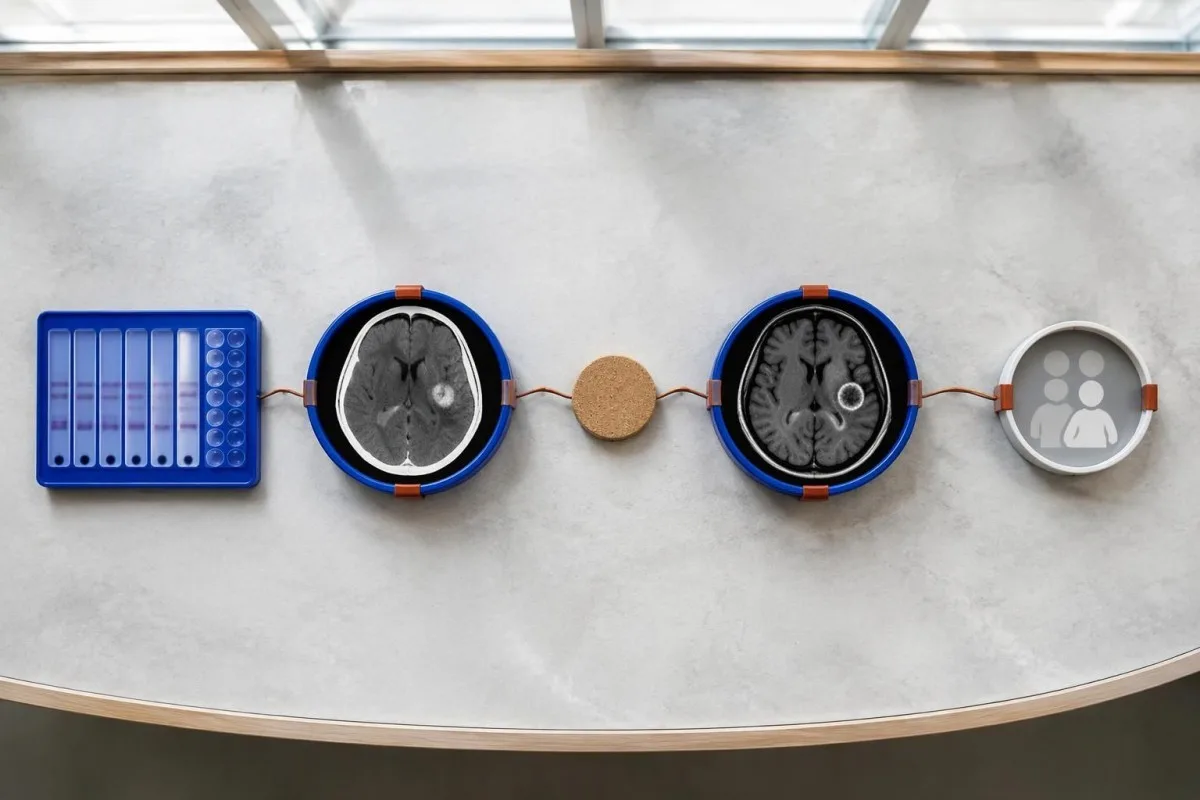
Evidence should be weighted, not tallied. A confidently visualized scolex inside a compatible cyst is different from 1 nonspecific ring-enhancing area, while a positive antibody result is different from direct evidence that a finding is in the brain; our 양성 항체 결과 가이드 explains why detection alone cannot establish location.
For a clearly hypothetical probability example, start with a 30% pretest probability and assume a single-cyst assay has 55% sensitivity and 99% specificity. In 1,000 comparable people, about 135 affected and 693 unaffected people would test negative, leaving approximately a 16% probability of disease among negative results—still substantial, although these assumed figures are not a personal risk calculator.
The most useful disagreement to investigate is whether each test is answering the same question. A negative antibody test, a CT calcification, and MRI edema can all be compatible with 1 calcified disease process; unexplained discrepancies should prompt review of the assay and images rather than automatic dismissal of either result.
What else can resemble a single cyst on brain imaging?
A single ring-enhancing brain finding is not specific to neurocysticercosis. Other possibilities include tuberculoma, an abscess, a neoplasm, or an inflammatory process; clinicians use appearance, location, immune status, symptoms, and sometimes follow-up imaging or tissue examination to distinguish these possibilities rather than relying on 1 antibody panel.
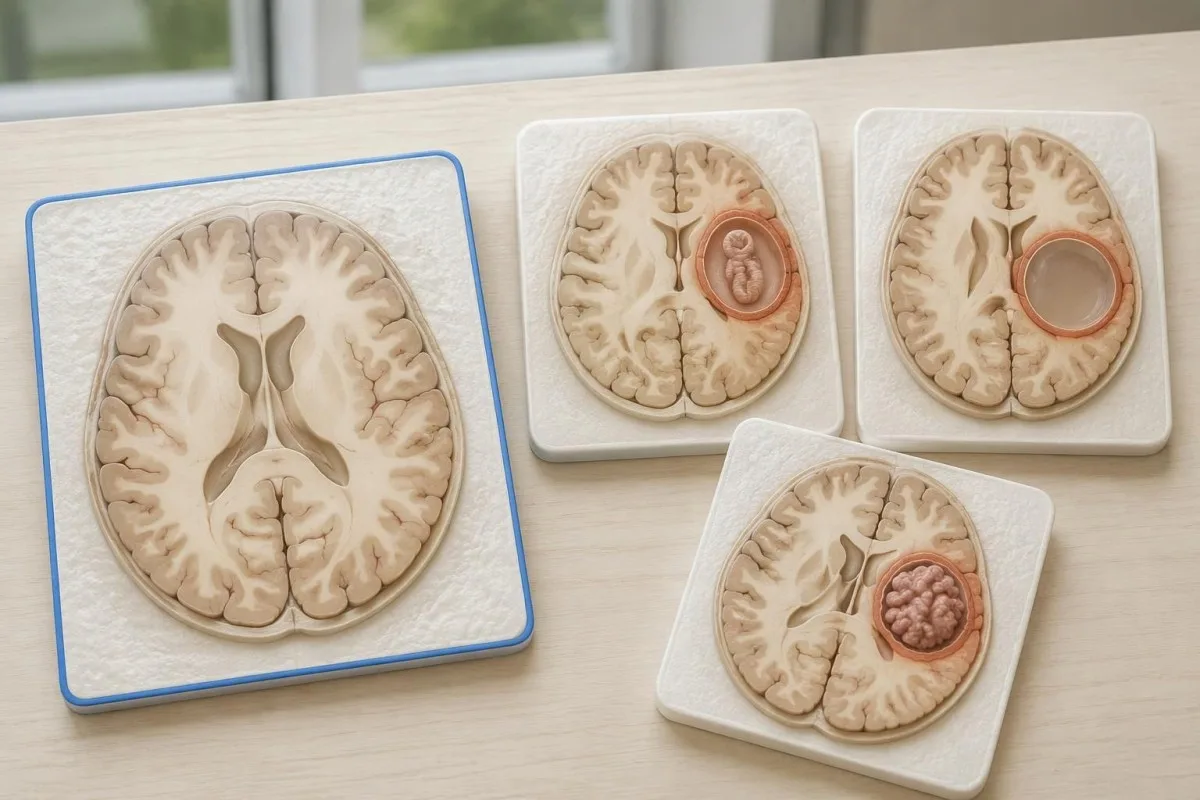
Edema, restricted diffusion, internal structures, and the number of findings all contribute to the differential, but no single nonspecific feature settles every case. Fever and immune suppression may change the suspected cause; a 2 cm ring-enhancing area in a hypothetical immunocompromised person warrants a different investigation from a tiny calcification in an otherwise well person.
Toxoplasmosis is one consideration in selected immunocompromised patients, and a positive IgG result can indicate past exposure rather than prove an active brain process. Our Toxoplasma IgG interpretation guide explains that laboratory distinction; imaging and the patient's immune status determine whether the result is clinically relevant to 1 or more cerebral findings.
New seizures accompanied by rapidly evolving memory problems, psychiatric changes, or abnormal movements can also suggest encephalitis rather than a solitary parasite cyst. Our encephalitis diagnostic pathway describes how MRI, EEG, and cerebrospinal fluid testing answer different questions; a second negative cysticercosis antibody result does not investigate those alternatives.
Can antigen testing, PCR, or CSF resolve uncertainty?
Antigen tests, PCR, and cerebrospinal fluid analysis can add information in selected cases, particularly when extraparenchymal disease is suspected. None is a universal rescue test after 1 negative antibody result: availability, assay validation, disease compartment, and safety of lumbar puncture determine whether additional testing is appropriate.
Antibody testing detects the host response, while antigen testing aims to detect parasite-derived material and may better reflect viable disease burden. Antigen detection is often less useful when only 1 small parenchymal cyst or calcifications are present; molecular testing is used in some specialist settings, but performance cannot be generalized across every laboratory or specimen.
Lumbar puncture is not routinely required for an uncomplicated solitary parenchymal finding and can be unsafe when obstructive hydrocephalus or significant mass effect is present. Cerebrospinal fluid tests for other disorders also require disease-specific interpretation, as our CSF band interpretation guide explains; 1 abnormal CSF marker does not identify every possible cause.
칸테스티는 AI 혈액검사 결과 해석 플랫폼, not a service that orders lumbar punctures, identifies cysts on scans, or confirms neurological infections. Our AI 해석 기술이 explains the laboratory-report workflow; when 2 tests disagree, our role is to clarify their stated meanings and limitations, not select an invasive diagnostic procedure.
Why does treatment depend on cyst stage and location?
Treatment depends on whether cysts are viable, degenerating, calcified, or located outside the brain tissue, not simply on antibody positivity. Selected viable parenchymal cases receive antiparasitic treatment, whereas calcified-only disease generally receives symptom-directed care; ventricular obstruction may require a procedural approach rather than 1 standard medication regimen.

For selected patients with 1–2 viable parenchymal cysts, the IDSA/ASTMH guideline describes albendazole treatment for 10–14 days with appropriate accompanying care. This is a specialist-directed recommendation, not a home-treatment instruction: antiparasitic drugs can provoke an inflammatory response, and untreated hydrocephalus or diffuse cerebral edema changes the order of management (White et al., 2018).
WHO's 2021 guidance focuses on defined presentations of parenchymal neurocysticercosis, while the IDSA/ASTMH guideline also addresses ventricular, subarachnoid, and other forms in detail. Differences in imaging access and disease compartment explain why 1 treatment recommendation cannot be transferred to every patient with an antibody result; the guidelines do not turn negative serology into a rule-out test.
Corticosteroids may accompany antiparasitic therapy, but prolonged use requires additional safety planning, including assessment for relevant latent infections. Our Strongyloides and steroid safety guide explains a separate risk that matters before immune-suppressing treatment; an eye examination is also recommended before antiparasitic therapy to evaluate possible intraocular cysts.
What should follow-up monitor beyond antibody results?
Follow-up should track seizures, neurological symptoms, imaging changes, and medication safety, rather than use antibody disappearance as proof of recovery. For viable parenchymal cysts, the IDSA/ASTMH guideline suggests repeat MRI at least every 6 months until the cystic component resolves, with earlier reassessment when symptoms change.

Antibodies may remain detectable after the original disease process has changed, and low-burden disease may never produce a positive result. If 1 new seizure occurs during follow-up, clinicians consider adherence, medication interactions, recurrent edema, and other causes; a rising or falling antibody index alone cannot distinguish among those explanations.
Kantesti AI can help explain reported laboratory results during medication follow-up, but a drug concentration is not a stand-alone measure of seizure control. Our 레베티라세탐 혈중 농도 해석 guide explains why sample timing and kidney function matter; 2 measurements collected at different times after dosing may not be directly comparable.
Monitoring depends on the chosen drug and treatment duration: prolonged albendazole therapy can require liver-test and blood-count surveillance, while some antiseizure medicines can affect sodium. Our 전해질 안전 가이드 discusses those separate laboratory concerns; do not stop an antiseizure medicine or change its dose because 1 cysticercosis antibody result is negative.
What can Kantesti explain, and what research cannot prove?
AI report interpretation cannot confirm or exclude neurocysticercosis from laboratory results alone. Kantesti는 AI 기반 혈액검사 분석 도구 whose role here is to organize reported laboratory findings; a negative result still needs clinical context, and 1 new seizure takes priority over reviewing an automated explanation.

Prepare a focused review packet with the original antibody report, assay method, CT or MRI report, symptom timeline, and medication list. These 5 information categories reduce the risk of discussing a result without its context; ask specifically whether the imaging suggests viable, degenerating, calcified, ventricular, or subarachnoid disease and which unanswered question the next test would address.
The 2 Kantesti publications listed below are a repository-deposited global analysis report and an educational RDW guide, not clinical evidence validating neurocysticercosis diagnosis. Our RDW 및 CBC 가이드 can support interpretation of a separately ordered blood count, but RDW, MCV, and MCHC do not establish whether a brain cyst is present.
Evidence for the neurological recommendations in this article comes from the cited diagnostic criteria and clinical guidelines, not from general AI benchmarking or laboratory-report volume. Our technical validation scope should be read within its stated boundaries; neither 1 successful report explanation nor a large aggregate dataset substitutes for condition-specific diagnostic validation.
자주 묻는 질문
혈액 검사 결과가 음성이어도 신경낭미충증에 걸릴 수 있나요?
네, 혈액 항체 검사 결과가 음성이더라도 신경낭미충증이 있을 수 있으며, 특히 뇌 낭종이 1개이거나 석회화 병변만 있는 경우 그렇습니다. 발표된 참고검사실 EITB 민감도 추정치는 단일 낭종의 경우 약 50–60%로, 생존 낭종이 여러 개일 때보다 상당히 낮은 것으로 나타나는 경우가 많습니다. 따라서 CT, MRI, 증상 및 노출 이력은 여전히 진단의 핵심입니다. 새로 발생한 발작은 음성 검사 결과에 안심하기보다 긴급히 평가받아야 합니다.
신경낭미충증을 진단하는 가장 신뢰할 수 있는 검사는 무엇인가요?
신경낭미충증 검사 하나만으로 모든 진단적 의문에 답할 수는 없습니다. 뇌 영상 검사와 적절히 선택한 혈청학적 검사는 상호 보완적입니다. IDSA/ASTMH 가이드라인에서 EITB는 선호되는 확진용 항체 검사법이지만, 낭종이 1개뿐인 질환은 놓칠 수 있습니다. 비조영 CT는 석회화 확인에 특히 유용하고, MRI는 다수의 생존 낭종, 부종 및 뇌척수액 공간의 이상을 더 잘 평가합니다. 임상의는 단일 음성 결과를 확정적인 것으로 간주하지 않고 이러한 소견을 종합합니다.
Is CT or MRI better for neurocysticercosis?
CT and MRI have different strengths in neurocysticercosis diagnosis. Noncontrast CT often detects small calcifications approximately 1–4 mm across more clearly, while MRI evaluates viable cysts, surrounding edema, and ventricular or subarachnoid disease. Specialized 3-dimensional MRI sequences may help identify cyst membranes in cerebrospinal fluid spaces. The IDSA/ASTMH guideline recommends both modalities when classifying newly diagnosed disease.
Can a calcified cyst still cause seizures?
A calcified cysticercosis remnant can remain associated with seizures even though it is no longer a viable cyst. Some calcified foci, often only 1–4 mm across, develop intermittent surrounding edema that may be visible on MRI. Negative antibodies do not exclude this mechanism, and persistent positive antibodies do not measure seizure risk. Calcified-only disease generally receives symptom-directed treatment rather than antiparasitic medication.
Should I repeat a negative cysticercosis antibody test?
Repeating a negative cysticercosis antibody test is not automatically the best next step. With 1 small cyst or calcified disease, a weak antibody response may remain negative even if the same assay is repeated after 2 weeks. A clinician may instead review the original method, request a better-characterized confirmatory assay, or prioritize CT and MRI. New seizures or worsening neurological symptoms should not wait for repeat testing.
When should I seek emergency help for a first seizure?
A first known seizure warrants urgent medical assessment and contacting local emergency services, regardless of a negative neurocysticercosis antibody test. A convulsive seizure lasting 5 minutes, repeated seizures without recovery, breathing difficulty, pregnancy, or significant injury is an emergency. Do not restrain the person or put anything in their mouth, and place them on their side once convulsions stop if they are breathing normally. Do not drive until a clinician has assessed the event and explained the applicable restrictions.
혈액검사 결과 보는법
검사실 보고서를 업로드하면 Kantesti의 AI가 몇 초 안에 각 바이오마커를 쉬운 말로 설명합니다. 전 세계 200만 명 이상이 사용하고 있습니다.
참고 자료
- Klein, T., Mitchell, S., & Weber, H. (2026). AI 혈액검사 분석기: 2.5M건 분석 | 글로벌 헬스 리포트 2026. Kantesti AI 의학 연구. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW 혈액검사: RDW-CV, MCV 및 MCHC 완전 가이드. Kantesti AI 의학 연구. DOI
- White AC Jr et al. (2018). Diagnosis and Treatment of Neurocysticercosis: 2017 Clinical Practice Guidelines by the Infectious Diseases Society of America (IDSA) and the American Society of Tropical Medicine and Hygiene (ASTMH). 임상감염병학. DOI
- Del Brutto OH et al. (2017). Revised diagnostic criteria for neurocysticercosis. Journal of the Neurological Sciences. DOI
- World Health Organization (2021). WHO guidelines on management of Taenia solium neurocysticercosis. 세계보건기구.
- 200만+분석한 검사
- 127+국가
- 100+언어
의료진 소개


E-E-A-T 신뢰 신호
경험
의사가 주도하는 검사 해석 워크플로 임상 검토.
전문적 지식
임상 맥락에서 바이오마커가 어떻게 거동하는지에 대한 검사실 의학 중심.
권위
Thomas Klein 박사의 의학적 검토를 거쳤으며, Sarah Mitchell 박사와 Hans Weber 교수의 기여가 있었습니다.
신뢰성
경고를 줄이기 위한 명확한 후속 경로가 포함된 근거 기반 해석.






의학적 면책 조항
이 글은 교육 목적만을 위한 것이며 의학적 조언을 구성하지 않습니다. 진단 및 치료 결정에는 항상 자격을 갖춘 의료 전문가와 상담하세요.
게시됨 · 편집팀에 문의
Kantesti Ltd 발행, 잉글랜드 및 웨일스에 등록된 회사, 회사 번호. 17090423, 런던, 영국.
