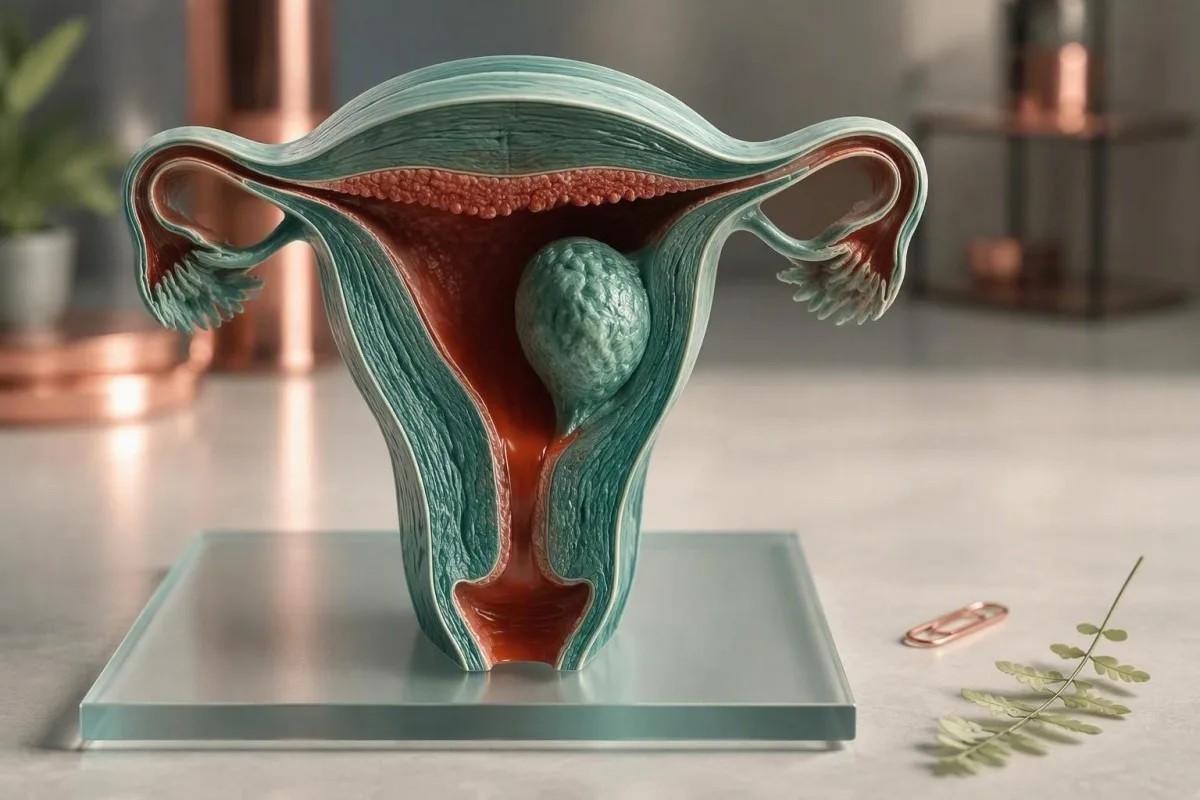
ಪ್ರತಿ ಗಂಟೆಗೆ 2 ಗಂಟೆಗಳ ಕಾಲ ಪ್ಯಾಡ್ ಅಥವಾ ಟ್ಯಾಂಪೂನ್ ಅನ್ನು ನೆನೆಸುವುದು, ಗಾಲ್ಫ್ ಚೆಂಡಿಗಿಂತ ದೊಡ್ಡ ಗಡ್ಡೆಗಳನ್ನು ಹಾದುಹೋಗುವುದು, ಮೂರ್ಛೆ ಹೋಗುವುದು ಅಥವಾ ಗರ್ಭಾವಸ್ಥೆಯಲ್ಲಿ ರಕ್ತಸ್ರಾವವಾಗುವುದು ತುರ್ತು ಮೌಲ್ಯಮಾಪನವನ್ನು ಬಯಸುತ್ತದೆ. ಹೆಚ್ಚಿನ ಭಾರವಾದ ಋತುಗಳು ಚಿಕಿತ್ಸೆ ನೀಡಬಹುದಾದವು, ಆದರೆ ಮಾದರಿಯು - ಸರಳವಾಗಿ ಮೊತ್ತವಲ್ಲ - ನೀವು ಎಷ್ಟು ಬೇಗನೆ ಆರೈಕೆಯನ್ನು ಪಡೆಯಬೇಕು ಎಂಬುದನ್ನು ನಿರ್ಧರಿಸುತ್ತದೆ.


- ತುರ್ತು ಮಿತಿ: ಕನಿಷ್ಠ 1 ಪ್ಯಾಡ್ ಅಥವಾ ಟ್ಯಾಂಪೂನ್ ಪ್ರತಿ ಗಂಟೆಗೆ 2 ಸತತ ಗಂಟೆಗಳ ಕಾಲ ನೆನೆಸುವುದು, ವಿಶೇಷವಾಗಿ ತಲೆತಿರುಗುವಿಕೆ ಅಥವಾ ಉಸಿರಾಟದ ತೊಂದರೆ ಇದ್ದರೆ, ತುರ್ತು ವೈದ್ಯಕೀಯ ಮೌಲ್ಯಮಾಪನವನ್ನು ನೀಡುತ್ತದೆ.
- ಗರ್ಭಧಾರಣೆಯ ಪರೀಕ್ಷೆ: ಗರ್ಭಧಾರಣೆಯ ಧನಾತ್ಮಕ ಅಥವಾ ಸಂಭವನೀಯತೆಯೊಂದಿಗೆ ಯಾವುದೇ ಅನಿರೀಕ್ಷಿತ ಭಾರವಾದ ಯೋನಿ ರಕ್ತಸ್ರಾವವು ಅದೇ ದಿನದ ಮೌಲ್ಯಮಾಪನವನ್ನು ಬಯಸುತ್ತದೆ ಏಕೆಂದರೆ ಗರ್ಭಕೋಶದ ಹೊರಗಿನ ಗರ್ಭಧಾರಣೆ ಮತ್ತು ಗರ್ಭಪಾತವು ಆರಂಭದಲ್ಲಿ ಒಂದೇ ರೀತಿ ಕಾಣಿಸಬಹುದು.
- ಕಬ್ಬಿಣದ ನಷ್ಟ: 15 µg/L ಗಿಂತ ಕೆಳಗಿನ ಫೆರಿಟಿನ್, ಹಿಮೋಗ್ಲೋಬಿನ್ ಇನ್ನೂ ರಕ್ತಹೀನತೆಯ ವ್ಯಾಪ್ತಿಗೆ ಬೀಳದಿದ್ದರೂ, ಖಾಲಿಯಾದ ಕಬ್ಬಿಣದ ಸಂಗ್ರಹವನ್ನು ಬಲವಾಗಿ ಬೆಂಬಲಿಸುತ್ತದೆ.
- ಸಾಮಾನ್ಯ ಕಾರಣಗಳು: ಅಂಡೋತ್ಪತ್ತಿ ಹಾರ್ಮೋನ್ ವ್ಯತ್ಯಾಸ, ಫೈಬ್ರಾಯ್ಡ್ಗಳು, ಅಡೆನೊಮಿಯೋಸಿಸ್, ಪಾಲಿಪ್ಸ್, ತಾಮ್ರದ IUD ಗಳು, ಥೈராய್ ಕಾಯಿಲೆ ಮತ್ತು ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ವಿರುದ್ಧದ ಔಷಧಿಗಳು ಆಗಾಗ್ಗೆ ಭಾರವಾದ ಋತುಸ್ರಾವದ ಕಾರಣಗಳಾಗಿವೆ.
- ತುರ್ತು ಲಕ್ಷಣಗಳು: ಮೂರ್ಛೆ ಹೋಗುವುದು, ಎದೆ ನೋವು, ವಿಶ್ರಾಂತಿಯಲ್ಲಿ ಉಸಿರಾಟದ ತೊಂದರೆ, ಒಂದು ಬದಿಯ ಸೊಂಟದ ನೋವು, ಜ್ವರ, ಅಥವಾ ವೇಗದ ನಾಡಿಮಿಡಿತವು ಭಾರವಾದ ಋತುಸ್ರಾವದ ಎಚ್ಚರಿಕೆ ಚಿಹ್ನೆಗಳಾಗಿವೆ, ಅದು ಸಾಮಾನ್ಯ ನೇಮಕಾತಿಗಾಗಿ ಕಾಯಬಾರದು.
- ವಯಸ್ಸು ಮುಖ್ಯ: 12 ತಿಂಗಳ ಋತುಸ್ರಾವವಿಲ್ಲದ ನಂತರದ ರಕ್ತಸ್ರಾವವು ಋತುಬಂಧದ ನಂತರದ ರಕ್ತಸ್ರಾವವಾಗಿದೆ ಮತ್ತು ಒಮ್ಮೆ ಮಾತ್ರ ಸಂಭವಿಸಿದರೂ ಕೂಡಲೇ ತನಿಖೆ ಮಾಡಬೇಕಾಗುತ್ತದೆ.
- ಉಪಯುಕ್ತ ಮೊದಲ ಪರೀಕ್ಷೆಗಳು: ಗರ್ಭಧಾರಣೆಯ ಪರೀಕ್ಷೆ, ಸಂಪೂರ್ಣ ರಕ್ತದ ಎಣಿಕೆ, ಫೆರಿಟಿನ್, ಮತ್ತು ಉದ್ದೇಶಿತ ಥೈರಾಯ್ಡ್ ಅಥವಾ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ಪರೀಕ್ಷೆಗಳು ಅಪಾಯವನ್ನು ಸ್ಪಷ್ಟಪಡಿಸುತ್ತವೆ; ಅಲ್ಟ್ರಾಸೌಂಡ್ ಅನೇಕ ರಚನಾತ್ಮಕ ಕಾರಣಗಳನ್ನು ಗುರುತಿಸುತ್ತದೆ ಆದರೆ ಎಲ್ಲವನ್ನೂ ಅಲ್ಲ.
- ಔಷಧಿ ಎಚ್ಚರಿಕೆ: ಸೂಚಿಸಲಾದ ಹೆಪ್ಪುರೋಧಕಗಳನ್ನು ನಿಮ್ಮದೇ ಆದ ಮೇಲೆ ನಿಲ್ಲಿಸಬೇಡಿ; ತುರ್ತು ವೈದ್ಯರು ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ಅಪಾಯವನ್ನು ಸಮತೋಲನಗೊಳಿಸುವಾಗ ರಕ್ತಸ್ರಾವವನ್ನು ಸುರಕ್ಷಿತವಾಗಿ ಕಡಿಮೆ ಮಾಡಬಹುದು.
ಎಷ್ಟು ಭಾರವಾದರೆ, ಮತ್ತು ಯಾವಾಗ ಅದು ತುರ್ತು?
ತೀವ್ರವಾದ ಋತುಸ್ರಾವದ ರಕ್ತಸ್ರಾವವು ರಕ್ಷಣೆಯನ್ನು ತ್ವರಿತವಾಗಿ ಅತಿಯಾಗಿ ಮೀರಿದರೆ ಅಥವಾ ಕಡಿಮೆ ರಕ್ತ ಪರಿಚಲನೆಯ ಲಕ್ಷಣಗಳನ್ನು ಉಂಟುಮಾಡಿದರೆ ತುರ್ತು ಆಗುತ್ತದೆ. ನೀವು 2 ಗಂಟೆಗಳ ಕಾಲ ಪ್ರತಿ ಗಂಟೆಗೆ ಒಂದು ಪ್ಯಾಡ್ ಅಥವಾ ಟ್ಯಾಂಪೂನ್ ಅನ್ನು ನೆನೆಸಿದರೆ, ಮೂರ್ಛೆ ಹೋದರೆ, ಗೊಂದಲಕ್ಕೊಳಗಾದರೆ, ಎದೆ ನೋವು ಇದ್ದರೆ, ಉಸಿರಾಡಲು ತೊಂದರೆ ಇದ್ದರೆ, ಅಥವಾ ಗರ್ಭಿಣಿಯಾಗಿರಬಹುದು ಎಂದು ನೀವು ಭಾವಿಸಿದರೆ ಈಗಲೇ ತುರ್ತು ಆರೈಕೆಗೆ ಹೋಗಿ.
ಪ್ರತಿ ಚಕ್ರಕ್ಕೆ 80 mL ಗಿಂತ ಹೆಚ್ಚಿನ ಋತುಸ್ರಾವದ ರಕ್ತಸ್ರಾವವು ಋತುಬಂಧದ ವ್ಯಾಖ್ಯಾನವಾಗಿತ್ತು, ಆದರೆ ಯಾರೂ ಅದನ್ನು ಮನೆಯಲ್ಲಿ ವಿಶ್ವಾಸಾರ್ಹವಾಗಿ ಅಳೆಯಲು ಸಾಧ್ಯವಿಲ್ಲ. ಆಚರಣೆಯಲ್ಲಿ, ಬಟ್ಟೆ ಅಥವಾ ಹಾಸಿಗೆಯ ಮೂಲಕ ಹರಿಯುವುದು, ರಾತ್ರಿಯಿಡೀ ಹೆಚ್ಚಿನ ಹೀರಿಕೊಳ್ಳುವ ಉತ್ಪನ್ನವನ್ನು ಬದಲಾಯಿಸುವುದು, ಅಥವಾ ಎರಡು ಉತ್ಪನ್ನಗಳನ್ನು ಒಟ್ಟಿಗೆ ಬಳಸುವುದು ಹೆಚ್ಚು ಉಪಯುಕ್ತವಾಗಿದೆ. NICE ಮಾರ್ಗದರ್ಶಿ NG88 ರೋಗಿಗಳನ್ನು ಪರಿಮಾಣವನ್ನು ಅಂದಾಜಿಸಲು ಕೇಳುವುದಕ್ಕಿಂತ ದೈನಂದಿನ ಜೀವನದ ಮೇಲೆ ಪರಿಣಾಮವನ್ನು ನಿರ್ಣಯಿಸಲು ಸಲಹೆ ನೀಡುತ್ತದೆ (NICE, 2018).
ಸಂಯೋಜನೆಯು ಯಾವುದೇ ಒಂದು ಸುಳಿವಿಗಿಂತ ಹೆಚ್ಚು ಮುಖ್ಯವಾಗಿದೆ. ನಿರಂತರವಾಗಿ 100 ಬೀಟ್ಸ್ ಪ್ರತಿ ನಿಮಿಷಕ್ಕಿಂತ ಹೆಚ್ಚಿನ ನಾಡಿ ಮಿಡಿತ ಮತ್ತು ನಿಂತ ನಂತರ ತಲೆತಿರುಗುವಿಕೆಯು ಗಮನಾರ್ಹ ಪ್ರಮಾಣದ ನಷ್ಟ ಅಥವಾ ರಕ್ತಹೀನತೆಯನ್ನು ಸೂಚಿಸುತ್ತದೆ, ಆದರೆ ದಿನ 2 ರಂದು ವ್ಯವಸ್ಥಿತ ಲಕ್ಷಣಗಳಿಲ್ಲದೆ ಕೇವಲ ದೊಡ್ಡ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯು ಸಾಮಾನ್ಯವಾಗಿ ಹಾಗಲ್ಲ. ಸೆಪ್ಟೆಂಬರ್ 16, 2026 ರಂತೆ, ನಾನು ಇನ್ನೂ ರೋಗಿಗಳಿಗೆ ತಮ್ಮ ವೈಯಕ್ತಿಕ ಮೂಲ ರೇಖೆಯಿಂದ ಆಕಸ್ಮಿಕ ಬದಲಾವಣೆಯನ್ನು ವೈದ್ಯಕೀಯವಾಗಿ ಅರ್ಥಪೂರ್ಣವೆಂದು ಪರಿಗಣಿಸಲು ಸಲಹೆ ನೀಡುತ್ತೇನೆ.
ಡಾ. ಥಾಮಸ್ ಕ್ಲೈನ್ ಅವರು ತಮ್ಮ ಋತುಗಳು ಯಾವಾಗಲೂ ಕಷ್ಟಕರವಾಗಿದ್ದರಿಂದ ತೀವ್ರವಾದ ಆಯಾಸವನ್ನು ಸಾಮಾನ್ಯವೆಂದು ಪರಿಗಣಿಸಿದ ರೋಗಿಗಳನ್ನು ನೋಡಿದ್ದಾರೆ. ನೀವು ಸುರಕ್ಷಿತವಾಗಿ ಕೋಣೆಯನ್ನು ದಾಟಲು, ಚಾಲನೆ ಮಾಡಲು, ಅಥವಾ ಸಾಮಾನ್ಯ ಸ್ಥಿತಿಯಲ್ಲಿ ಎಚ್ಚರವಾಗಿರಲು ಸಾಧ್ಯವಾಗದಿದ್ದರೆ, ಮುಂದಿನ ಪ್ಯಾಡ್ ಕಡಿಮೆ ತುಂಬಿದೆಯೇ ಎಂದು ಕಾಯುವ ಬದಲು ತುರ್ತು ಸಹಾಯವನ್ನು ಪಡೆಯಿರಿ; ನಮ್ಮ ಮಾರ್ಗದರ್ಶಿಯು ತಲೆತಿರುಗುವಿಕೆ ರಕ್ತ ಪರೀಕ್ಷೆಗಳು ಲಕ್ಷಣಗಳು ನಾಟಕೀಯ ಪ್ರಯೋಗಾಲಯ ಫಲಿತಾಂಶಕ್ಕಿಂತ ಮುಂಚಿತವಾಗಿ ಏಕೆ ಬರಬಹುದು ಎಂಬುದನ್ನು ವಿವರಿಸುತ್ತದೆ.
ಕಾಳಜಿಯ ಮಟ್ಟವನ್ನು ಬದಲಾಯಿಸುವ ರಕ್ತಸ್ರಾವದ ಮಾದರಿಗಳು
Sudden bleeding between periods, after sex, after menopause, or in a possible pregnancy deserves faster assessment than a familiar heavy day-2 period. The timing can point toward pregnancy-related causes, cervical or uterine pathology, infection, or medication effects.
Bleeding with one-sided lower abdominal pain, shoulder-tip pain, collapse, or a positive pregnancy test is an emergency until ectopic pregnancy is excluded. A urine pregnancy test can be falsely negative very early, so clinicians may repeat serum beta-hCG after 48 hours and use ultrasound based on symptoms rather than a single result; see our early pregnancy test guide.
Postcoital bleeding is often benign—cervical ectropion, a polyp, or dryness can explain it—but recurrent episodes warrant a speculum examination and up-to-date cervical screening. Bleeding after menopause is never considered a normal hormone fluctuation: even a small episode after 12 months without periods needs prompt review.
Very heavy bleeding beginning at menarche, after dental work, or alongside frequent nosebleeds and easy bruising raises the possibility of a bleeding disorder. About 5% to 24% of women with heavy menstrual bleeding may have von Willebrand disease depending on the population studied, which is why a normal platelet count alone is not enough to rule it out (ACOG Committee Opinion No. 785, 2019).
Clots: useful clue, poor measuring tool
Clots larger than about 2.5 cm, roughly a golf ball, suggest that flow is outpacing the body’s ability to keep menstrual fluid liquid. Their presence does not diagnose fibroids or a clotting disorder, but repeated large clots plus flooding should move an appointment forward.
ಭಾರವಾದ ಋತುಗಳ ಹಾರ್ಮೋನು ಮತ್ತು ಅಂಡೋತ್ಪತ್ತಿ ಕಾರಣಗಳು
Irregular ovulation is one of the most common heavy menstrual bleeding causes, especially in the first years after periods begin and during perimenopause. Without regular progesterone exposure, the endometrium can build up for weeks and then shed heavily and unpredictably.
Anovulatory cycles often produce intervals longer than 35 days followed by 7 to 14 days of variable bleeding. Polycystic ovary syndrome, marked weight change, under-fueling, severe illness, and the menopause transition can all disrupt ovulation, but no hormone panel can diagnose the cause from one random cycle-day sample; LH and FSH patterns need timing and symptoms.
Thyroid disease can change cycle regularity and flow, although mild TSH variation is rarely the sole explanation for dramatic flooding. Overt hypothyroidism commonly presents with elevated TSH and low free T4; hyperprolactinemia can also suppress ovulation, particularly when irregular periods accompany milky discharge, headaches, or visual change.
ಕಾಂತೆಸ್ಟಿ ಒಬ್ಬ AI ರಕ್ತ ಪರೀಕ್ಷಾ ವಿಶ್ಲೇಷಕ that places full blood count, ferritin, thyroid markers, and cycle context side by side rather than treating a borderline TSH as an automatic explanation. In my experience, the useful question is often whether an endocrine finding explains the whole pattern—or merely coexists with fibroids, iron loss, or a medicine effect.
Perimenopause is not a diagnosis of exclusion
Ages 45 to 55 are common years for erratic ovulation, but new flooding still requires assessment for structural causes. “It is probably menopause” should never be the final answer when bleeding becomes heavier, longer, or more frequent than your usual cycle.
ರಚನಾತ್ಮಕ ಕಾರಣಗಳು: ಗರ್ಭಕೋಶದ ಫೈಬ್ರಾಯ್ಡ್ಗಳು, ಅಡೆನೊಮಿಯೋಸಿಸ್ ಮತ್ತು ಪಾಲಿಪ್ಸ್
Uterine fibroid bleeding commonly causes prolonged flow, clots, pelvic pressure, and anemia, particularly when a fibroid distorts the uterine cavity. Adenomyosis more often combines heavy bleeding with deep, progressively painful periods, while polyps often cause spotting between periods.
Fibroids are benign smooth-muscle growths, and many never cause symptoms. The location matters: submucosal fibroids near the cavity tend to cause more bleeding than similarly sized fibroids on the outer uterine surface, so a 2-cm submucosal fibroid may matter more than a 6-cm subserosal one.
A transvaginal ultrasound is usually the first imaging test, but it can miss small polyps and some cavity lesions. Hysteroscopy allows direct inspection of the uterine cavity and is especially useful when bleeding persists despite normal ultrasound findings or when ultrasound suggests a submucosal fibroid.
Treatment is individualized: tranexamic acid, anti-inflammatory medication, hormonal therapy, a levonorgestrel intrauterine system, hysteroscopic removal, embolization, or surgery may be considered. A scan finding is not an emergency by itself; urgent care is driven by active blood loss, severe pain, pregnancy risk, or circulatory symptoms, not by fibroid diameter alone. Read more about பெண்களின் ஹார்மோன் அறிகுறிகள்.
ಭಾರವಾದ ಋತುಚಕ್ರ ಎಂದು ಊಹಿಸುವ ಮೊದಲು ಗರ್ಭಧಾರಣೆಯ ಪರೀಕ್ಷೆಯು ಏಕೆ ಬರುತ್ತದೆ
Any person who could be pregnant and has unusual heavy bleeding needs pregnancy testing the same day. Ectopic pregnancy, miscarriage, and bleeding from an early intrauterine pregnancy can overlap in appearance, but their urgency differs sharply.
A positive test plus severe one-sided pain, shoulder-tip pain, fainting, or pain on opening the bowels needs emergency assessment immediately. These features raise concern for ectopic pregnancy, which can become life-threatening before visible bleeding becomes heavy; beta-hCG values and ultrasound findings must be interpreted together, not separately.
After a confirmed early pregnancy loss, bleeding can range from period-like to heavier than a period. Passing tissue, fever of 38.0°C or higher, foul discharge, escalating pain, or soaking more than 2 pads per hour for 2 consecutive hours requires urgent reassessment because retained tissue or infection may need treatment.
Do not use a falling home-test line as proof that everything is resolving safely. Clinicians may follow quantitative beta-hCG until it falls appropriately, and our explanation of beta-hCG after miscarriage describes why a single value is less informative than the trend.
Pregnancy bleeding is not a “wait and see” category
Heavy bleeding in pregnancy should be assessed on the day it occurs, even if cramps are mild. RhD-negative patients may also need anti-D prophylaxis depending on gestation and local protocol, so contact an early-pregnancy unit or emergency service promptly.
ಔಷಧಿಗಳು, ಸಾಧನಗಳು ಮತ್ತು ದೇಹದಾದ್ಯಂತದ ಕಾರಣಗಳು
Copper IUDs, anticoagulants, antiplatelet medicines, and some hormonal regimens can increase menstrual flow, but they should not be blamed without checking for anemia and other causes. Liver disease, kidney disease, platelet disorders, and severe thyroid dysfunction can also alter bleeding risk.
Copper IUD-related heaviness is usually greatest in the first 3 to 6 months after insertion, then often settles. New flooding years later is less likely to be simply “the coil” and deserves the same assessment as any new heavy period, including pregnancy testing if expulsion or malposition is possible.
Warfarin, direct oral anticoagulants, aspirin, and some antidepressants can worsen menstrual loss. Never stop an anticoagulant without the prescriber’s advice: the risk of stroke or thrombosis may outweigh the bleeding risk, and clinicians can consider dose timing, gynecologic treatment, or a different agent.
A normal PT/INR and aPTT do not exclude von Willebrand disease or platelet function problems. For a practical explanation of what standard tests miss, see coagulation panel limits; recurrent mucosal bleeding, family history, and bleeding after procedures justify hematology input.
The medication list should include supplements
High-dose fish oil, ginkgo, garlic extracts, and non-prescribed anti-inflammatory products can alter bleeding or interact with prescribed treatment. Bring photographs of bottles and the exact dose; “a natural supplement” is not a clinically useful medication history.
ಕಬ್ಬಿಣದ ಕೊರತೆ ಮತ್ತು ರಕ್ತಹೀನತೆ: ನಷ್ಟವು ಹಿಡಿತಕ್ಕೆ ಬರುತ್ತಿದೆ ಎಂದು ಅರ್ಥೈಸುವ ಲಕ್ಷಣಗಳು
A heavy period can cause iron deficiency before it causes anemia, and a normal hemoglobin does not rule out depleted iron stores. Fatigue, reduced exercise tolerance, palpitations, restless legs, headaches, and hair shedding can appear when ferritin is low.
A ferritin below 15 µg/L is highly specific for absent iron stores in most otherwise well adults; many clinicians investigate symptoms and ongoing loss when ferritin is below 30 µg/L. Ferritin rises during inflammation, so a value of 45 µg/L can still mask deficiency when C-reactive protein is elevated; ಫೆರಿಟಿನ್ ಮತ್ತು CRP must be read together.
Hemoglobin below 120 g/L is anemia in non-pregnant adult women under World Health Organization criteria. The body adapts gradually, which is why someone may be functioning at 90 g/L yet feel breathless on stairs; a rapid fall, syncope, chest discomfort, or hemoglobin near 70 g/L generally requires urgent hospital-based assessment.
ಕಾಂತೆಸ್ಟಿ ಒಬ್ಬ AI ರಕ್ತ ಪರೀಕ್ಷೆ ವರದಿ ಅರ್ಥ ಪ್ಲಾಟ್ಫಾರ್ಮ್ that compares ferritin, hemoglobin, MCV, RDW, transferrin saturation, and prior results to identify a developing iron-loss pattern. A falling MCV may lag behind ferritin depletion by months, and our ಕಡಿಮೆ MCV ಟ್ರಿಯೇಜ್ ಮಾರ್ಗದರ್ಶಿ explains why thalassemia trait remains an alternative in some populations.
Oral iron is not an instant rescue treatment
Oral elemental iron commonly provides 40 to 65 mg per dose, but it cannot stabilize an actively bleeding person. Absorption and tolerance vary, and intravenous iron or transfusion decisions depend on symptoms, hemoglobin trajectory, ongoing loss, and comorbidity—not a ferritin number alone.
ಅತಿಯಾಗಿ ಪರೀಕ್ಷಿಸದೆ ಕಾರಣವನ್ನು ಸ್ಪಷ್ಟಪಡಿಸುವ ಯಾವ ಪರೀಕ್ಷೆಗಳು?
The most useful initial work-up is usually a pregnancy test, full blood count, ferritin, and a focused history, with ultrasound or additional tests chosen from the pattern. Broad hormone panels and tumor markers rarely answer the first urgent question.
A full blood count assesses hemoglobin, hematocrit, red-cell indices, and platelets. Hemoglobin tells us the current oxygen-carrying impact; ferritin estimates stored iron, while an elevated platelet count can be a reactive clue to iron deficiency rather than a primary blood disorder—our hemoglobin and hematocrit guide ವ್ಯತ್ಯಾಸವನ್ನು ವಿವರಿಸುತ್ತದೆ.
Testing for TSH is reasonable when periods are irregular or symptoms suggest thyroid disease. Tests for prolactin, androgen excess, clotting disorders, or STI infection should be guided by history: indiscriminate screening creates confusing false positives and can delay imaging or gynecologic examination.
ಕಾಂತೆಸ್ಟಿ ಒಬ್ಬ AI-ಚಾಲಿತ ರಕ್ತ ಪರೀಕ್ಷೆ ವಿಶ್ಲೇಷಣೆ ಸಾಧನ that organizes these results into a physician-ready timeline, while diagnosis still requires clinical examination and, when indicated, ultrasound or hysteroscopy. Our ಜೈವಿಕ ಗುರುತುಗಳ ಮಾರ್ಗದರ್ಶಿ details which measurements are included in common laboratory panels.
Why CA-125 is usually the wrong first test
CA-125 is not a screening test for a typical heavy period and rises in many benign settings, including menstruation, endometriosis, and fibroids. It is considered only when a clinician finds a relevant mass or symptom pattern, because an isolated result can create more alarm than clarity.
ಗರ್ಭಕೋಶದ ಫೈಬ್ರಾಯ್ಡ್ ರಕ್ತಸ್ರಾವವನ್ನು ಸಾಮಾನ್ಯವಾಗಿ ಹೇಗೆ ಚಿಕಿತ್ಸೆ ನೀಡಲಾಗುತ್ತದೆ
Uterine fibroid bleeding can often be reduced without removing the uterus, but the best option depends on cavity distortion, anemia, fertility plans, pain, and fibroid location. Treatment should address both the bleeding today and the iron loss that may follow it.
Tranexamic acid is a non-hormonal medicine taken only during heavy days; common regimens use 1 g orally three times daily for up to 5 days, though local prescribing differs. It reduces menstrual loss for many patients but is not appropriate for everyone with a history of thrombosis, so individualized prescribing matters.
A levonorgestrel-releasing intrauterine system is highly effective for many people with heavy bleeding when the cavity is not significantly distorted. It may cause irregular spotting for the first 3 to 6 months, a trade-off that is easier to tolerate when patients know it is expected rather than treatment failure.
Hysteroscopic removal is often suitable for cavity-based fibroids or polyps; myomectomy, uterine artery embolization, and hysterectomy have different effects on future pregnancy and recovery. Dr. Thomas Klein’s practical advice is to ask the surgeon to describe the fibroid’s FIGO location, not merely its size, before committing to a procedure.
Pain can point toward adenomyosis
Heavy flow plus worsening cramping, pelvic fullness, and pain during sex is more suggestive of adenomyosis or endometriosis than a painless small fibroid. Ultrasound can identify some adenomyosis features, while MRI is reserved for selected uncertain or complex cases.
ಆರೈಕೆಯನ್ನು ಏರ್ಪಡಿಸುವಾಗ ಮನೆಯಲ್ಲಿ ಏನು ಮಾಡಬೇಕು
If you are stable, tracking flow, protecting hydration, and arranging timely review are sensible first steps; home care is not a substitute for urgent evaluation when red flags appear. Record product changes, clot size, pain location, temperature, medications, and pregnancy-test results.
Use the same product type when possible and count fully soaked items rather than guessing volume. Photographing a calendar or noting “changed at 09:00, 10:15, and 11:00” gives a clinician much better information than “very heavy,” especially if you later feel too unwell to recall details.
Drink normally to thirst and eat regular meals, but do not try to compensate for active loss with excessive water alone. Avoid aspirin for period pain unless it has been specifically prescribed, because it can impair platelet function; ibuprofen may reduce menstrual loss for some people but is unsuitable with ulcers, kidney disease, allergy, certain anticoagulants, or pregnancy.
If iron deficiency has already been confirmed, food can support but not rapidly restore stores. Pairing lentils, beans, seafood, eggs, or fortified grains with vitamin-C-containing foods may improve non-heme iron absorption; our iron-rich food guide gives practical examples without overselling diet as treatment.
What not to do
Do not double hormonal doses, combine several anti-inflammatory medicines, or borrow tranexamic acid from another person. These choices can obscure symptoms, worsen gastrointestinal or clotting risk, and make safe prescribing harder.
ಹದಿಹರೆಯದವರು ಮತ್ತು ಜೀವನಪರ್ಯಂತ ಲಕ್ಷಣಗಳನ್ನು ಹೊಂದಿರುವವರಲ್ಲಿ ಭಾರವಾದ ರಕ್ತಸ್ರಾವ
Heavy bleeding from the first few periods is more likely to reflect an ovulatory transition or an inherited bleeding disorder than fibroids. Adolescents who soak products hourly, become pale, miss school, or have easy bruising deserve prompt assessment rather than reassurance alone.
Cycles are often irregular for the first 2 to 3 years after menarche because the ovulatory system is still maturing. That does not make severe loss normal: ACOG recommends assessment for anemia, endocrine causes of anovulation, and bleeding disorders when adolescent bleeding is heavy (ACOG Committee Opinion No. 785, 2019).
Ask specifically about bleeding after tooth extraction, frequent nosebleeds lasting more than 10 minutes, easy bruising larger than 5 cm, or relatives with diagnosed bleeding disorders. Testing for von Willebrand factor is affected by stress, acute bleeding, pregnancy, estrogen, and illness, so hematology may repeat tests when the person is stable.
A parent or caregiver can help by tracking products and symptoms without minimizing embarrassment. Our review of von Willebrand bleeding patterns explains why a normal routine clotting screen does not close the investigation.
Iron treatment is often needed before the final diagnosis
Teenagers with hemoglobin below 100 g/L and ongoing heavy loss often need a structured iron and bleeding-control plan in parallel. Waiting for every specialist test before treating symptomatic anemia is rarely good care.
ಹೆರಿಗೆಯ ನಂತರ, ಋತುಬಂಧದ ಮೊದಲು, ಮತ್ತು ಋತುಬಂಧದ ನಂತರದ ರಕ್ತಸ್ರಾವ
Bleeding after childbirth, after age 45 with a new pattern, or after menopause follows different safety rules from an ordinary heavy period. Postpartum bleeding can worsen rapidly, while postmenopausal bleeding requires prompt exclusion of endometrial disease.
After delivery, heavy flow that suddenly increases, produces large clots, causes dizziness, or occurs with fever and uterine tenderness needs immediate obstetric assessment. Postpartum hemorrhage is usually defined clinically as cumulative loss of at least 1,000 mL or bleeding accompanied by signs of hypovolemia, but waiting to estimate volume at home is unsafe.
During perimenopause, skipped cycles followed by heavy bleeding are common, yet age does not rule out polyps, fibroids, hyperplasia, or malignancy. Endometrial sampling is commonly considered for abnormal uterine bleeding at age 45 or older, and earlier when there is persistent bleeding or risk factors such as obesity or chronic anovulation.
Bleeding after 12 consecutive months without a period is postmenopausal bleeding, even if it is only pink spotting. It should be assessed promptly with examination and often transvaginal ultrasound or endometrial sampling; if pregnancy is relevant after a recent loss, our pregnancy hormone ranges can help explain the testing sequence.
Hormone therapy can confuse the picture
Unscheduled bleeding can occur in the first 3 to 6 months of menopausal hormone therapy, but heavy or persistent bleeding still needs review. Never alter prescribed hormone doses without speaking to the clinician who manages them.
ತುರ್ತು ಆರೈಕೆ ಮತ್ತು ತುರ್ತು ವೈದ್ಯಕೀಯ ಪರಿಣತರು ಏನು ಪರಿಶೀಲಿಸುತ್ತಾರೆ
Urgent clinicians first assess circulation, pregnancy status, and the rate of ongoing loss before pursuing every possible cause. Expect pulse, blood pressure, temperature, abdominal examination, pregnancy testing, and targeted laboratory studies when bleeding is significant.
A person can have a “normal” blood pressure while compensating for acute loss, so clinicians look at pulse, standing symptoms, skin temperature, mental clarity, urine output, and repeated observations. Hemoglobin may initially underestimate abrupt loss because plasma volume shifts take time; this is one reason symptoms and trend matter so much.
Emergency treatment may include intravenous fluid, antiemetic medication, pain relief, hormonal therapy, tranexamic acid, iron, or blood products depending on severity and cause. Pelvic examination and ultrasound are used selectively; they should be explained and performed with consent, with a chaperone available according to local practice.
Bring a medication list, your last period date, product-change timeline, known fibroid or bleeding-disorder history, and any recent blood results. Kantesti can help organize laboratory trends, but emergency decisions must be made by the clinician examining you; our ವೈದ್ಯಕೀಯ ಮಾನ್ಯತಾ ವಿಧಾನ explains the limits of automated interpretation.
When a normal ultrasound does not end the work-up
Persistent heavy bleeding with a normal ultrasound may still require hysteroscopy, endometrial sampling, or bleeding-disorder evaluation. Ultrasound is valuable, but it does not directly assess every cavity lesion or every systemic cause.
ಪುನರಾವರ್ತಿತ ಕಬ್ಬಿಣದ ನಷ್ಟವನ್ನು ತಡೆಯುವ ಫಾಲೋ-ಅಪ್ ಯೋಜನೆ
A good follow-up plan checks whether bleeding improved and whether iron stores recovered; treating one without the other commonly leads to relapse. Repeat timing depends on starting hemoglobin, ferritin, symptoms, treatment, and whether heavy flow continues.
For uncomplicated iron deficiency treated orally, clinicians often recheck a full blood count in 4 to 8 weeks and ferritin after a longer interval, commonly 8 to 12 weeks or more. Hemoglobin should rise by roughly 10 to 20 g/L over 2 to 4 weeks when absorption, adherence, and bleeding control are adequate, although no single response rate fits every patient.
Keep a record of bleeding days, flooding episodes, missed work or school, pain score, and treatment dates. This exposes a pattern that raw lab data cannot: a ferritin of 28 µg/L may be improving after treatment, or worsening from 90 µg/L after six months of repeated unaddressed heavy cycles.
Kantesti’s AI ಲ್ಯಾಬ್ ಟೆಸ್ಟ್ ಇಂಟರ್ಪ್ರಿಟೇಶನ್ ಸೇವೆ can compare serial iron markers and blood counts, while our physicians’ ವೈದ್ಯಕೀಯ ಸಲಹಾ ಮಂಡಳಿ emphasizes that persistent abnormal bleeding requires in-person gynecologic assessment. The goal is not merely a less inconvenient period; it is preventing recurrent anemia, unsafe delay, and loss of quality of life.
Questions worth taking to your appointment
Ask what category is most likely—ovulatory, structural, pregnancy-related, medication-related, or bleeding disorder—and what finding would change the plan. Also ask when to repeat hemoglobin and ferritin, what symptoms override the follow-up date, and whether your fertility preferences alter the treatment choice.
ಪದೇ ಪದೇ ಕೇಳಲಾಗುವ ಪ್ರಶ್ನೆಗಳು
අධික ಋತುస్రా specifiche ರಕ್ತಸ್ರಾವಕ್ಕಾಗಿ ನಾನು ಯಾವಾಗ ತುರ್ತು ಕೋಣೆಗೆ ಹೋಗಬೇಕು?
ನಿಮಗೆ ತೀವ್ರ ಋತುಸ್ರಾವ ಉಂಟಾದರೆ, 2 ಗಂಟೆಗಳ ಕಾಲ ಪ್ರತಿ ಗಂಟೆಗೆ ಕನಿಷ್ಠ 1 ಪ್ಯಾಡ್ ಅಥವಾ ಟ್ಯಾಂಪೂನ್ ಸಂಪೂರ್ಣವಾಗಿ ನೆನೆದುಹೋಗುವಂತಿದ್ದರೆ, ಮತ್ತು ತಲೆತಿರುಗುವಿಕೆ, ಮೂರ್ಛೆ, ಎದೆ ನೋವು, ಉಸಿರಾಟದ ತೊಂದರೆ, ಗೊಂದಲ, ತೀವ್ರ ಸೊಂಟದ ನೋವು, ಅಥವಾ ಹೃದಯ ಬಡಿತ ಹೆಚ್ಚಾಗಿದ್ದರೆ, ತುರ್ತು ಚಿಕಿತ್ಸೆ ಪಡೆಯಿರಿ. ಗರ್ಭಧಾರಣೆ ದೃಢಪಟ್ಟಾಗ ಅಥವಾ ಅನುಮಾನವಿದ್ದಾಗ ಅತಿಯಾದ ರಕ್ತಸ್ರಾವವು, ವಿಶೇಷವಾಗಿ ಒಂದು ಬದಿಯ ನೋವು ಅಥವಾ ಭುಜದ ತುದಿಯ ನೋವಿದ್ದರೆ, ಅದೇ ದಿನ ತುರ್ತು ಮೌಲ್ಯಮಾಪನ ಅಗತ್ಯವಿದೆ. ಈ ರೋಗಲಕ್ಷಣಗಳು ಗಮನಾರ್ಹ ರಕ್ತ ನಷ್ಟ, ಗರ್ಭಕೋಶದ ಹೊರಗಿನ ಗರ್ಭಧಾರಣೆ, ಗರ್ಭಪಾತದ ತೊಡಕುಗಳು, ಅಥವಾ ಸಮಯ-ಸಂವೇದನೆಯ ಮತ್ತೊಂದು ಸ್ಥಿತಿಯನ್ನು ಸೂಚಿಸಬಹುದು. ನಿಮಗೆ ಖಚಿತವಿಲ್ಲದಿದ್ದರೆ, ರಾತ್ರಿಯಿಡೀ ಕಾಯುವುದಕ್ಕಿಂತ ತುರ್ತು ವೈದ್ಯಕೀಯ ಸಲಹೆ ಪಡೆಯುವುದು ಸುರಕ್ಷಿತವಾಗಿದೆ.
ಅತಿಯಾದ ಋತುಸ್ರಾವಕ್ಕೆ ಸಾಮಾನ್ಯ ಕಾರಣಗಳು ಯಾವುವು?
ಸಾಮಾನ್ಯ ಭಾರೀ ಋತುಸ್ರಾವದ ಕಾರಣಗಳಲ್ಲಿ ಅನಿಯಮಿತ ಅಂಡೋತ್ಪತ್ತಿ, ಗರ್ಭಕೋಶದ ಗೆಡ್ಡೆಗಳು (fibroids), ಅಡೆನೊಮೈಯೋಸಿಸ್, ಗರ್ಭಕೋಶದ ಪಾಲಿಪ್ಸ್, ತಾಮ್ರದ IUD ಬಳಕೆ, ಥೈராய್ಡ್ ಕಾಯಿಲೆ, ರಕ್ತ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ನಿರೋಧಕ ಔಷಧಗಳು, ಮತ್ತು ವಾನ್ ವಿಲೆಬ್ರಾಂಡ್ ಕಾಯಿಲೆಯಂತಹ ಆನುವಂಶಿಕ ರಕ್ತಸ್ರಾವದ ಅಸ್ವಸ್ಥತೆಗಳು ಸೇರಿವೆ. ಋತುಸ್ರಾವವು ದೀರ್ಘಕಾಲದ, ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯೊಂದಿಗೆ ಮತ್ತು ಸೊಂಟದ ಒತ್ತಡ ಅಥವಾ ಮೂತ್ರ ವಿಸರ್ಜನೆಯ ಹೆಚ್ಚಳದೊಂದಿಗೆ ಸಂಬಂಧ ಹೊಂದಿದ್ದರೆ ಗೆಡ್ಡೆ-ಸಂಬಂಧಿತ ರಕ್ತಸ್ರಾವವು ವಿಶೇಷವಾಗಿ ಸಂಭವನೀಯವಾಗಿರುತ್ತದೆ. ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ಗಾತ್ರ ಅಥವಾ ರಕ್ತಸ್ರಾವದ ಪ್ರಮಾಣದಿಂದ ಮಾತ್ರ ಕಾರಣವನ್ನು ನಿರ್ಧರಿಸಲಾಗುವುದಿಲ್ಲ, ಆದ್ದರಿಂದ ಗರ್ಭಧಾರಣೆಯ ಪರೀಕ್ಷೆ, ಸಂಪೂರ್ಣ ರಕ್ತದ ಎಣಿಕೆ, ಫೆರಿಟಿನ್, ಮತ್ತು ಆಯ್ದ ಅಲ್ಟ್ರಾಸೌಂಡ್ ಸಾಮಾನ್ಯ ಮೊದಲ ಹಂತಗಳಾಗಿವೆ. ಅನೇಕ ಕಾರಣಗಳನ್ನು ಶಸ್ತ್ರಚಿಕಿತ್ಸೆ ಇಲ್ಲದೆ ಚಿಕಿತ್ಸೆ ನೀಡಬಹುದು.
ಹೆವಿ ಪೀರಿಯಡ್ಸ್ ಸಾಮಾನ್ಯ ಹಿಮೋಗ್ಲೋಬಿನ್ನೊಂದಿಗೆ ಕಬ್ಬಿಣದ ಕೊರತೆಯನ್ನು ಉಂಟುಮಾಡಬಹುದೇ?
ಹೌದು, ಗರ್ಭಿಣಿಯಲ್ಲದ ವಯಸ್ಕ ಮಹಿಳೆಯರಿಗೆ 120 g/L ಗಿಂತ ಕಡಿಮೆಯಾಗುವ ಮೊದಲೇ, ಅಂದರೆ ಸಾಮಾನ್ಯ ರಕ್ತಹೀನತೆಯ ಮಿತಿಗಿಂತ ಮೊದಲೇ, ಅತಿಯಾದ ಋತುಸ್ರಾವವು ಕಬ್ಬಿಣದ ಸಂಗ್ರಹವನ್ನು ಕಡಿಮೆ ಮಾಡಬಹುದು. 15 µg/L ಗಿಂತ ಕಡಿಮೆಯಿರುವ ಫೆರಿಟಿನ್ ಮಟ್ಟವು ಕಬ್ಬಿಣದ ಕೊರತೆಯನ್ನು ಬಲವಾಗಿ ಬೆಂಬಲಿಸುತ್ತದೆ, ಆದರೆ 30 µg/L ಗಿಂತ ಕಡಿಮೆಯಿರುವ ಮೌಲ್ಯಗಳು ನಿರಂತರ ಋತುಸ್ರಾವದ ನಷ್ಟವಿದ್ದಾಗಲೂ ರೋಗಲಕ್ಷಣಗಳನ್ನು ವಿವರಿಸಬಹುದು. ಅತಿಯಾದ ರಕ್ತಹೀನತೆ ಬೆಳೆಯುವ ಮೊದಲು ಆಯಾಸ, ಕಾಲುಗಳಲ್ಲಿ ಚಡಪಡಿಕೆ, ತಲೆನೋವು, ಎದೆಬಡಿತ, ಕೂದಲು ಉದುರುವುದು ಮತ್ತು ವ್ಯಾಯಾಮದ ಸಹಿಷ್ಣುತೆ ಕಡಿಮೆಯಾಗಬಹುದು. ಉರಿಯೂತದ ಸಮಯದಲ್ಲಿ ಫೆರಿಟಿನ್ ಸುಳ್ಳು ಭರವಸೆ ನೀಡಬಹುದು, ಆದ್ದರಿಂದ ವೈದ್ಯರು ಇದನ್ನು C-ಪ್ರತಿಕ್ರಿಯಾತ್ಮಕ ಪ್ರೋಟೀನ್ ಮತ್ತು ಟ್ರಾನ್ಸ್ಫೆರಿನ್ ಸ್ಯಾಚುರೇಶನ್ನೊಂದಿಗೆ ಅರ್ಥೈಸಬಹುದು.
ಮುಟ್ಟಿನ ಸಮಯದಲ್ಲಿ ಗಾಲ್ಫ್-ಬಾಲ್-ಗಾತ್ರದ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆ ಅಪಾಯಕಾರಿಯೇ?
ಸುಮಾರು 2.5 ಸೆಂ.ಮೀ.ಗಿಂತ ದೊಡ್ಡ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಗಳು, ಅಂದರೆ ಗೋಲ್ಫ್-ಬಾಲ್ ಗಾತ್ರದಷ್ಟು, ಋತುಸ್ರಾವ ಗರ್ಭಕೋಶದಿಂದ ಹೊರಬರುವ ಮೊದಲು ಹೆಪ್ಪುಗಟ್ಟುವಷ್ಟು ಭಾರವಾಗಿದೆ ಎಂದು ಸೂಚಿಸುತ್ತದೆ, ಆದರೆ ಅವುಗಳು ತಮ್ಮಿಂದಲೇ ಅಪಾಯಕಾರಿ ಕಾರಣವನ್ನು ಸಾಬೀತುಪಡಿಸುವುದಿಲ್ಲ. ಗಂಟೆಗೆ ಉತ್ಪನ್ನ ಬದಲಾವಣೆಗಳು, ದೌರ್ಬಲ್ಯ, ಉಸಿರಾಟದ ತೊಂದರೆ, ತೀವ್ರ ನೋವು, ಅಥವಾ ನಿಮ್ಮ ಸಾಮಾನ್ಯ ಋತುಸ್ರಾವದಿಂದ ಅನಿರೀಕ್ಷಿತ ಬದಲಾವಣೆಗಳೊಂದಿಗೆ ಪುನರಾವರ್ತಿತ ದೊಡ್ಡ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಗಳು ತಕ್ಷಣದ ಮೌಲ್ಯಮಾಪನಕ್ಕೆ ಪ್ರೇರೇಪಿಸಬೇಕು. ಫೈಬ್ರಾಯ್ಡ್ಗಳು, ಅಡೆನೊಮೈಯೋಸಿಸ್, ಅಸಮ ಅಂಡೋತ್ಪತ್ತಿ, ಮತ್ತು ಗರ್ಭಧಾರಣೆಗೆ ಸಂಬಂಧಿಸಿದ ರಕ್ತಸ್ರಾವವು ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಗೆ ಕಾರಣವಾಗಬಹುದು. ರೋಗನಿರ್ಣಯವಾಗಿ ಹೆಪ್ಪುಗಟ್ಟುವಿಕೆಯ ಗಾತ್ರವನ್ನು ಬಳಸುವ ಬದಲು, ಒಬ್ಬ ವೈದ್ಯರು ಸಂಪೂರ್ಣ ಮಾದರಿಯನ್ನು ಮೌಲ್ಯಮಾಪನ ಮಾಡುತ್ತಾರೆ.
ಫೈಬ್ರಾಯ್ಡ್ ಅತಿಯಾದ ರಕ್ತಸ್ರಾವಕ್ಕೆ ಕಾರಣವಾಗಬಹುದೇ?
ಗರ್ಭಕೋಶದ ಕುಹರದೊಳಗೆ ಹೊರಚಾಚಿದಾಗ ಅಥವಾ ಅದನ್ನು ವಿರೂಪಗೊಳಿಸಿದಾಗ ಫೈಬ್ರಾಯ್ಡ್ ತೀವ್ರ ರಕ್ತಸ್ರಾವಕ್ಕೆ ಕಾರಣವಾಗಬಹುದು, ಆದರೆ ಗರ್ಭಧಾರಣೆ-ಸಂಬಂಧಿತ ಕಾರಣಗಳು, ಪಾಲಿಪ್ಸ್, ಔಷಧಿಗಳ ಪರಿಣಾಮಗಳು ಅಥವಾ ಇತರ ಪರಿಸ್ಥಿತಿಗಳಿಗಾಗಿ ಇದ್ದಕ್ಕಿದ್ದಂತೆ ತೀವ್ರ ಬದಲಾವಣೆಯನ್ನು ಇನ್ನೂ ಮೌಲ್ಯಮಾಪನ ಮಾಡಬೇಕಾಗುತ್ತದೆ. 2 ಸೆಂ.ಮೀ. ಗಾತ್ರದ ಸಬ್ಮ್ಯೂಕೋಸಲ್ ಫೈಬ್ರಾಯ್ಡ್, ಹೊರ ಗರ್ಭಕೋಶದ ಮೇಲ್ಮೈಯಲ್ಲಿರುವ 6 ಸೆಂ.ಮೀ. ಫೈಬ್ರಾಯ್ಡ್ಗಿಂತ ಹೆಚ್ಚು ರಕ್ತಸ್ರಾವವನ್ನು ಉಂಟುಮಾಡಬಹುದು ಏಕೆಂದರೆ ಸ್ಥಳವು ನೇರವಾಗಿ ಒಳಪದರದ ಮೇಲೆ ಪರಿಣಾಮ ಬೀರುತ್ತದೆ. ರೋಗಲಕ್ಷಣಗಳು ಮುಂದುವರಿದರೆ ಮತ್ತು ಕುಹರವನ್ನು ಸ್ಪಷ್ಟವಾಗಿ ನೋಡದಿದ್ದರೆ ಹಿಸ್ಟರೊಸ್ಕೋಪಿ ಅಗತ್ಯವಾಗಬಹುದು, ಆದರೂ ಅಲ್ಟ್ರಾಸೌಂಡ್ ಸಾಮಾನ್ಯವಾಗಿ ಮೊದಲ ಚಿತ್ರಣ ಪರೀಕ್ಷೆಯಾಗಿದೆ. ತೀವ್ರ ಉಸಿರಾಟದ ತೊಂದರೆ, ದಿಗ್ಭ್ರಮೆ ಅಥವಾ 2 ಗಂಟೆಗಳ ಕಾಲ ಪ್ರತಿ ಗಂಟೆಗೆ ನೆನೆಸುವಷ್ಟು ಸಕ್ರಿಯ ನಷ್ಟ ಉಂಟಾದಾಗ ತಕ್ಷಣದ ಆರೈಕೆ ಅಗತ್ಯ.
ಅತಿಯಾದ ಋತುಸ್ರಾವಕ್ಕೆ ಯಾವ ರಕ್ತ ಪರೀಕ್ಷೆಗಳು ಉಪಯುಕ್ತವಾಗಿವೆ?
ఋతుస్రాವ ಹೆಚ್ಚಾಗಿದ್ದರೆ, ಗರ್ಭಧಾರಣೆ ಸಾಧ್ಯವಿದ್ದಲ್ಲಿ ಗರ್ಭಧಾರಣೆ ಪರೀಕ್ಷೆಯೊಂದಿಗೆ, ಸಂಪೂರ್ಣ ರಕ್ತದ ಎಣಿಕೆ ಮತ್ತು ಫೆರಿಟಿನ್ ಅತ್ಯಂತ ಉಪಯುಕ್ತವಾದ ಮೊದಲ ರಕ್ತ ಪರೀಕ್ಷೆಗಳಾಗಿವೆ. ಹೆಚ್ಚಿನ ಗರ್ಭಿಣಿಯಲ್ಲದ ವಯಸ್ಕ ಮಹಿಳೆಯರಲ್ಲಿ 120 g/L ಗಿಂತ ಕಡಿಮೆ ಹಿಮೋಗ್ಲೋಬಿನ್ ರಕ್ತಹೀನತೆಯನ್ನು ಸೂಚಿಸುತ್ತದೆ, ಆದರೆ 15 µg/L ಗಿಂತ ಕಡಿಮೆ ಫೆರಿಟಿನ್ ಕಬ್ಬಿಣದ ಸಂಗ್ರಹದ ಕೊರತೆಯನ್ನು ಬಲವಾಗಿ ಸೂಚಿಸುತ್ತದೆ. ಅಸಮರ್ಪಕ ಋತುಚಕ್ರಗಳು ಅಥವಾ ಥೈರಾಯ್ಡ್ ಲಕ್ಷಣಗಳು ಕಂಡುಬಂದಾಗ TSH ಪರೀಕ್ಷೆಯು ಉಪಯುಕ್ತವಾಗಿದೆ, ಮತ್ತು ಋತುಸ್ರಾವದ ಆರಂಭದಲ್ಲಿ ಅತಿಯಾದ ರಕ್ತಸ್ರಾವವಾದಾಗ ಅಥವಾ ಸುಲಭವಾಗಿ ಮೂಗೇಟುಗಳು, ಮೂಗಿನಿಂದ ರಕ್ತಸ್ರಾವ ಅಥವಾ ಕುಟುಂಬದ ಇತಿಹಾಸದೊಂದಿಗೆ ಕಂಡುಬಂದರೆ ವಾನ್ ವಿಲಿಬ್ರಾಂಡ್ ಪರೀಕ್ಷೆಯನ್ನು ಪರಿಗಣಿಸಲಾಗುತ್ತದೆ. ಸಾಮಾನ್ಯ PT/INR ಮತ್ತು aPTT ಎಲ್ಲಾ ಆನುವಂಶಿಕ ರಕ್ತಸ್ರಾವದ ಅಸ್ವಸ್ಥತೆಗಳನ್ನು ಹೊರತುಪಡಿಸುವುದಿಲ್ಲ.
අධික ఋతుస్రావం කොපමණ කාලයක් පැවතුනහොත් අධික ලෙස සලකනු ඇත්ද?
7 ದಿನಗಳಿಗಿಂತ ಹೆಚ್ಚು ಕಾಲ ರಕ್ತಸ್ರಾವವನ್ನು ಸಾಮಾನ್ಯವಾಗಿ ದೀರ್ಘಕಾಲದ ಎಂದು ಪರಿಗಣಿಸಲಾಗುತ್ತದೆ, ಆದರೆ ತುರ್ತು ಪರಿಸ್ಥಿತಿ ಗಣನೆಗಿಂತ ಹರಿವಿನ ಪ್ರಮಾಣ ಮತ್ತು ರೋಗಲಕ್ಷಣಗಳನ್ನು ಅವಲಂಬಿಸಿರುತ್ತದೆ. 10 ದಿನಗಳ ಲಘು ಋತುಚಕ್ರವನ್ನು ನಿಯಮಿತ ಪರಿಶೀಲನೆಗೆ ಸೂಕ್ತವೆಂದು ಪರಿಗಣಿಸಬಹುದು, ಆದರೆ ತಲೆತಿರುಗುವಿಕೆಯೊಂದಿಗೆ ಪ್ರತಿ ಗಂಟೆಗೆ 2 ಗಂಟೆಗಳ ಕಾಲ ರಕ್ತಸ್ರಾವವಾಗುವುದು ತುರ್ತು ಚಿಕಿತ್ಸೆಯನ್ನು ಸೂಚಿಸುತ್ತದೆ. 35 ದಿನಗಳಿಗಿಂತ ಹೆಚ್ಚು ಕಾಲದ ಋತುಚಕ್ರ ಮತ್ತು ನಂತರ ದೀರ್ಘಕಾಲದ ಅತಿಯಾದ ರಕ್ತಸ್ರಾವವು ಅಂಡಾಶಯದ ಅಸಮರ್ಪಕ ಕ್ರಿಯೆಯನ್ನು ಸೂಚಿಸುತ್ತದೆ, ವಿಶೇಷವಾಗಿ ಹದಿಹರೆಯ ಮತ್ತು ಋತುಬಂಧದ ಸಮಯದಲ್ಲಿ. 7 ದಿನಗಳು ಅಥವಾ ಅದಕ್ಕಿಂತ ಹೆಚ್ಚು ಕಾಲ ಉಳಿಯುವ ಪುನರಾವರ್ತಿತ ರಕ್ತಸ್ರಾವವನ್ನು ರಕ್ತಹೀನತೆ ಮತ್ತು ಚಿಕಿತ್ಸೆ ನೀಡಬಹುದಾದ ರಚನಾತ್ಮಕ ಅಥವಾ ಹಾರ್ಮೋನುಗಳ ಕಾರಣಗಳಿಗಾಗಿ ಮೌಲ್ಯಮಾಪನ ಮಾಡಬೇಕು.
ಇಂದು AI-ಸಕ್ರಿಯ ರಕ್ತ ಪರೀಕ್ಷೆ ವಿಶ್ಲೇಷಣೆಯನ್ನು ಪಡೆಯಿರಿ
ತಕ್ಷಣದ, ನಿಖರವಾದ ಲ್ಯಾಬ್ ಪರೀಕ್ಷಾ ವಿಶ್ಲೇಷಣೆಗೆ Kantesti ಅನ್ನು ನಂಬುವ ವಿಶ್ವದಾದ್ಯಂತ 2 ಮಿಲಿಯನ್ಗಿಂತ ಹೆಚ್ಚು ಬಳಕೆದಾರರಿಗೆ ಸೇರಿ. ನಿಮ್ಮ ರಕ್ತ ಪರೀಕ್ಷೆ ಫಲಿತಾಂಶಗಳನ್ನು ಅಪ್ಲೋಡ್ ಮಾಡಿ ಮತ್ತು ಕೆಲವೇ ಸೆಕೆಂಡುಗಳಲ್ಲಿ 15,000+ ಬಯೋಮಾರ್ಕರ್ಗಳ ಸಮಗ್ರ ಅರ್ಥೈಸಿಕೆಯನ್ನು ಪಡೆಯಿರಿ.
📚 ಉಲ್ಲೇಖಿತ ಸಂಶೋಧನಾ ಪ್ರಕಟಣೆಗಳು
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). Serum Proteins Guide: Globulins, Albumin & A/G Ratio Blood Test. Zenodo. https://doi.org/10.5281/zenodo.18316300. ResearchGate: https://www.researchgate.net/search/publication?q=Serum%20Proteins%20Guide%20Globulins%20Albumin%20A%2FG%20Ratio%20Blood%20Test. Academia.edu: https://www.academia.edu/search?q=Serum%20Proteins%20Guide%20Globulins%20Albumin%20A%2FG%20Ratio%20Blood%20Test. Kantesti AI ವೈದ್ಯಕೀಯ ಸಂಶೋಧನೆ.
Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti LTD. (2026). C3 C4 Complement Blood Test & ANA Titer Guide. Zenodo. https://doi.org/10.5281/zenodo.18353989. ResearchGate: https://www.researchgate.net/search/publication?q=C3%20C4%20Complement%20Blood%20Test%20ANA%20Titer%20Guide. Academia.edu: https://www.academia.edu/search?q=C3%20C4%20Complement%20Blood%20Test%20ANA%20Titer%20Guide. Kantesti AI ವೈದ್ಯಕೀಯ ಸಂಶೋಧನೆ.
📖 ಬಾಹ್ಯ ವೈದ್ಯಕೀಯ ಉಲ್ಲೇಖಗಳು
ನ್ಯಾಷನಲ್ ಇನ್ಸ್ಟಿಟ್ಯೂಟ್ ಫಾರ್ ಹೆಲ್ತ್ ಅಂಡ್ ಕೇರ್ ಎಕ್ಸಲೆನ್ಸ್ (2018). Heavy menstrual bleeding: assessment and management. NICE Guideline NG88.
⚕️ ವೈದ್ಯಕೀಯ ಹಕ್ಕುತ್ಯಾಗ
ಈ ಲೇಖನವು ಕೇವಲ ಶಿಕ್ಷಣ ಉದ್ದೇಶಗಳಿಗಾಗಿ이며 ವೈದ್ಯಕೀಯ ಸಲಹೆಯನ್ನು ನೀಡುವುದಿಲ್ಲ. ರೋಗನಿರ್ಣಯ ಮತ್ತು ಚಿಕಿತ್ಸೆ ನಿರ್ಧಾರಗಳಿಗಾಗಿ ಸದಾ ಅರ್ಹ ಆರೋಗ್ಯ ಸೇವಾ ಪೂರೈಕೆದಾರರನ್ನು ಸಂಪರ್ಕಿಸಿ.
E-E-A-T ವಿಶ್ವಾಸ ಸಂಕೇತಗಳು
ಅನುಭವ
ಲ್ಯಾಬ್ ಅರ್ಥೈಸುವ ಕಾರ್ಯಪ್ರವಾಹಗಳ ಮೇಲೆ ವೈದ್ಯರಿಂದ ನೇತೃತ್ವದ ಕ್ಲಿನಿಕಲ್ ವಿಮರ್ಶೆ.
ಪರಿಣಿತಿ
ಕ್ಲಿನಿಕಲ್ ಸಂದರ್ಭದಲ್ಲಿನ ಬಯೋಮಾರ್ಕರ್ಗಳು ಹೇಗೆ ವರ್ತಿಸುತ್ತವೆ ಎಂಬುದರ ಮೇಲೆ ಪ್ರಯೋಗಾಲಯ ವೈದ್ಯಕೀಯದ ಕೇಂದ್ರೀಕರಣ.
ಅಧಿಕಾರಯುತತೆ
ಡಾ. ಥಾಮಸ್ ಕ್ಲೈನ್ ಬರಹ; ಡಾ. ಸಾರಾ ಮಿಚೆಲ್ ಮತ್ತು ಪ್ರೊ. ಡಾ. ಹಾನ್ಸ್ ವೆಬರ್ ಅವರ ವಿಮರ್ಶೆಯೊಂದಿಗೆ.
ವಿಶ್ವಾಸಾರ್ಹತೆ
ಎಚ್ಚರಿಕೆಯನ್ನು ಕಡಿಮೆ ಮಾಡಲು ಸ್ಪಷ್ಟವಾದ ಮುಂದಿನ ಹಂತಗಳೊಂದಿಗೆ ಸಾಕ್ಷ್ಯಾಧಾರಿತ ಅರ್ಥೈಸಿಕೆ.